
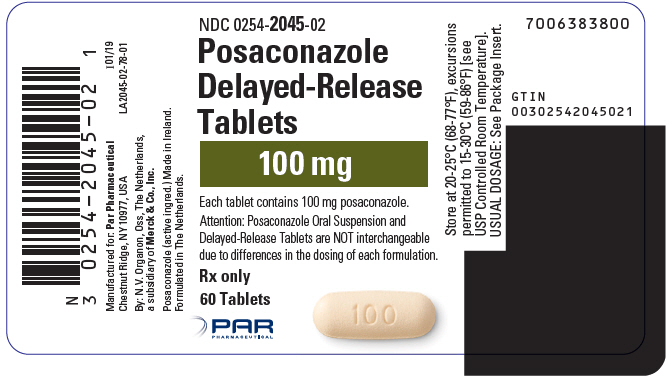
Posaconazole 100 mg Tablet, Coated, 60-count — NDC 0254-2045-02 (Billing 00254-2045-02)
This is a package of 60 tablets of Posaconazole 100 mg Tablet, Coated from ENDO USA, Inc., marketed since Aug 2019 and currently FDA-listed; retail pharmacies pay about $2.03 per tablet (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0254-2045-02 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0254 labeler · 2045 product · 02 package
- Package marketed since
- Aug 30, 2019
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 60 EA per package
- Barcode (UPC)
- 0302542045021
- Medicaid fills, this package
- 124 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Other active recalls for Posaconazole (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 071709
- GCN: 35649
- GPI-14 (Medi-Span): 11407060000620
- HICL (First Databank): 033461
- AHFS class code: 08:14.08.00
- RxCUI (RxNorm): 665019
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Azole Antifungal class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats invasive aspergillosis, a serious mold infection. It also helps prevent serious Aspergillus and Candida infections when your immune system is severely weakened. The oral...
- Delayed-release tablets can be taken with or without food. The oral suspension should be taken with a full meal. The injection is given by a clinician through a central line over a...
- The most common are diarrhea, nausea, vomiting, fever, headache, cough and low potassium. Let your care team know if they are bothersome or severe.
- Call right away for a racing or irregular heartbeat, fainting, signs of liver trouble, rising blood pressure or swelling, or severe vomiting and diarrhea. Those last two can keep t...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Posaconazole — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $2.032 | $121.89 / 60 tablets |
| Medicaid paysCMS SDUD · 12 mo | $3.91 | $234.50 / 60 tablets |
| Medicare drug plans payPart D · Q2 2026 | $10.45 | $627.28 / 60 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Oct 7, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00254-2045-02 You're viewing this Main listing | 60 TABLET, COATED in 1 BOTTLE | 2019-08-30 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Posaconazole 100 mgthis 00254-2045-02 | ENDO | 60 tablets | $2.032 | — | Availability likely | — |
| Posaconazole 100 mg 00406-7711-60 | SpecGx | 60 tablets | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 00904-7149-04 | Major | 1 tablet | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 16714-0535-01 | NorthStar | 60 tablets | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 31722-0677-60 | Camber | 60 tablets | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 43598-0470-60 | Dr.Reddys | 60 tablets | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 50268-0683-12 | AvPAK | 1 tablet | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 59651-0596-60 | Aurobindo | 60 tablets | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 60687-0523-21 | American | 1 tablet | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 62135-0429-60 | Chartwell | 60 tablets | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 70377-0038-11 | Biocon | 60 tablets | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 70748-0258-07 | Lupin | 60 tablets | $2.032 | AB | Availability likely | — |
| posaconazole 100 mg 72205-0168-60 | Novadoz | 60 tablets | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 72319-0023-02 | i3 | 60 tablets | $2.032 | AB | Availability likely | — |
| Noxafil 100 mg 00085-4324-02 | Merck | 60 tablets | — | — | FDA listed | — |
| Posaconazole 100 mg 00527-2133-30 | Lannett | 24 tablets | — | AB | FDA listed | — |
| Posaconazole 100 mg 17856-2133-01 | ATLANTIC | 1 tablet | — | AB | FDA listed | — |
| Posaconazole 100 mg 42291-0919-60 | AvKARE | 60 tablets | — | AB | FDA listed | — |
| Posaconazole 100 mg 51407-0676-60 | Golden | 60 tablets | — | AB | FDA listed | — |
| Posaconazole 100 mg 63629-2236-01 | Bryant | 60 tablets | — | — | Discontinued | — |
| Posaconazole 100 mg 69238-1476-03 | Amneal | 30 tablets | — | AB | FDA listed | — |
| Posaconazole 100 mg 71335-2665-01 | Bryant | 60 tablets | — | AB | FDA listed | — |
| Posaconazole 100 mg 71335-2930-01 | Bryant | 60 tablets | — | AB | FDA listed | — |
| Posaconazole 100 mg 72162-2243-02 | Bryant | 20 tablets | — | AB | FDA listed | — |
| Posaconazole 100 mg 73141-0023-02 | A2A | 60 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Oct 7, 2026
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Code | What it grants | Expires |
|---|---|---|
| NPP | New Patient Population | Jan 27, 2029 |
| ODE-355 | Orphan Drug Exclusivity (7-year) | Jun 17, 2028 |
Is there a generic version of POSACONAZOLE DR 100 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Posaconazole inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII RFW2ET671P
Hydroxypropyl cellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a film-former to coat tablets or control how fast the medicine releases.
-
UNII 6N003M473W
Hypromellose acetate succinate is a modified cellulose polymer that dissolves in the small intestine. It's used as a coating material to protect the medicine from stomach acid and control where and when the drug is released in the digestive tract.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII G2M7P15E5P
Polyethylene glycol 3350 is a synthetic polymer used as a solvent, humectant, and thickening agent in medicines. It helps dissolve other ingredients, retain moisture in the product, and achieve the desired consistency.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from ENDO USA, Inc. labeler code 00254
- Colchicine .6 mg Capsule NDC 0254-0460-01
- Diazoxide 50 mg/mL Suspension NDC 0254-1010-19
- POSACONAZOLE 40 mg/mL Suspension NDC 0254-1016-36
- penicillamine 250 mg Tablet, Film Coated NDC 0254-2000-01
- Chlorzoxazone 750 mg Tablet NDC 0254-2005-01
- Chlorzoxazone 375 mg Tablet NDC 0254-2053-01
- Omega-3-acid ethyl esters 900 mg Capsule NDC 0254-3010-08
- Alvimopan 12 mg Capsule NDC 0254-3012-55
- Nitisinone 2 mg Capsule NDC 0254-3020-02
- Nitisinone 5 mg Capsule NDC 0254-3021-02
- Nitisinone 10 mg Capsule NDC 0254-3022-02
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Posaconazole is an azole antifungal indicated as follows: Posaconazole delayed-release tablets are indicated for the treatment of invasive aspergillosis in adults and pediatric patients 2 years of age and older who weigh greater than 40 kg. ( 1.1 ) Posaconazole is indicated for the prophylaxis of invasive Aspergillus and Candida infections in patients who are at high risk of developing these infections due to being severely immunocompromised, such as hematopoietic stem cell transplant (HSCT) recipients with graft-versus-host disease (GVHD) or those with hematologic malignancies with prolonged neutropenia from chemotherapy as follows: ( 1.2 ) Posaconazole delayed-release tablets : adults and pediatric patients 2 years of age and older who weigh greater than 40 kg Posaconazole oral suspension: adults and pediatric patients 13 years of age and older Posaconazole oral suspension is indicated for the treatment of oropharyngeal candidiasis (OPC), including OPC refractory (rOPC) to itraconazole and/or fluconazole in adults and pediatric patients 13 years of age and older.
( 1.3 )
1.1Treatment of Invasive Aspergillosis Posaconazole delayed-release tablets are indicated for the treatment of invasive aspergillosis in adults and pediatric patients 2 years of age and older who weigh greater than 40 kg.
1.2Prophylaxis of Invasive Aspergillus and Candida Infections Posaconazole is indicated for the prophylaxis of invasive Aspergillus and Candida infections in patients who are at high risk of developing these infections due to being severely immunocompromised, such as hematopoietic stem cell transplant (HSCT) recipients with graft-versus-host disease (GVHD) or those with hematologic malignancies with prolonged neutropenia from chemotherapy [see Clinical Studies (14.1) ] as follows: Posaconazole delayed-release tablets : adults and pediatric patients 2 years of age and older who weigh greater than 40 kg Posaconazole oral suspension: adults and pediatric patients 13 years of age and older
1.3Treatment of Oropharyngeal Candidiasis Including Oropharyngeal Candidiasis Refractory to Itraconazole and/or Fluconazole Posaconazole oral suspension is indicated for the treatment of oropharyngeal candidiasis, including oropharyngeal candidiasis refractory to itraconazole and/or fluconazole in adults and pediatric patients 13 years of age and older.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Posaconazole formulations are supplied in different dose strengths of posaconazole, are approved for different indications, age groups, and weights, have different dosages and duration of therapy; and have different preparation and administration instructions. ( 2.1 ) Posaconazole oral suspension is not substitutable with Posaconazole delayed-release tablets or Noxafil PowderMix for delayed-release oral suspension due to the differences in the dosing of each formulation. Therefore, follow the specific dosage recommendations for each of the formulations.
( 2.1 , 2.2 , 2.3 ) Administer Posaconazole delayed-release tablets with or without food. ( 2.1 ) Administer Posaconazole oral suspension with a full meal. ( 2.1 ) See the full prescribing information for important administration and preparation instructions for Posaconazole (delayed-release tablets and Posaconazole oral suspension ( 2.5 , 2.6 , 2.7 ) For adult and pediatric patients aged 2 years of age and older, see the Full Prescribing Information for dosing recommendations for Posaconazole delayed-release tablets and Posaconazole oral suspension based on the indication, age, and weight associated with the dosage form.
( 1.1 , 1.2 , 1.3 , 2.1 , 2.2 , 2.3 , 2.4 )
2.1Important Administration Instructions Posaconazole delayed-release tablets and Posaconazole oral suspension are approved for different indications, age groups and weights; have different dosages and duration of therapy; and have different preparation and administration instructions. Therefore, select the recommended dosage form based on the indication, age group, and weight and carefully follow the recommended dosage, preparation and administration instructions described for each product [see Dosage and Administration (2.2 to 2.8) ] , and the following important administration instructions described below.
Non-substitutable Posaconazole oral suspension is not substitutable with Posaconazole delayed-release tablets or Noxafil PowderMix for delayed-release oral suspension due to the differences in the dosing of each formulation. Therefore, follow the specific dosage recommendations for each of the formulations [see Dosage and Administration (2.2 , 2.3) ]. Posaconazole delayed-release tablets Swallow tablets whole.
Do not divide, crush, or chew. Administer with or without food [see Dosage and Administration (2.2) and Clinical Pharmacology (12.3) ] . For patients who cannot eat a full meal, Posaconazole delayed-release tablets should be used instead of Posaconazole oral suspension for the prophylaxis indication.
Posaconazole delayed-release tablets generally provide higher plasma drug exposures than Posaconazole oral suspension under both fed and fasted conditions [see Dosage and Administration (2.6) ] . Posaconazole oral suspension Administer with a full meal or with a liquid nutritional supplement or an acidic carbonated beverage (e.g., ginger ale) in patients who cannot eat a full meal [see Dosage and Administration (2.8) ].
2.2Recommended Dosage of Posaconazole in Adult Patients The recommended dosage of Posaconazole delayed-release tablets and Posaconazole oral suspension in adult patients for the treatment of invasive aspergillosis, prophylaxis of invasive Aspergillus and Candida infections in patients who are at high risk of developing these infections due to being severely immunocompromised, or for the treatment of oropharyngeal candidiasis (OPC) is shown in Table 1 [see Dosage and Administration (2.5 , 2.6 , 2.7) and Clinical Pharmacology (12.3) ].
Table 1: Recommended Dosage of Posaconazole Delayed-Release Tablets and Posaconazole Oral Suspension in Adult Patients Dosage Duration of Therapy Treatment of Invasive Aspergillosis Switching between the Noxafil injection and Posaconazole delayed-release tablets is acceptable. A loading dose is not required when switching between dosage forms. Posaconazole Delayed-Release Tablets: Loading dose: 300 mg (three 100 mg delayed-release tabl… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Posaconazole Delayed-Release Tablets 100 mg of posaconazole: Yellow, coated, oblong tablets, debossed with "100" on one side. Posaconazole Oral Suspension 4,200 mg/105 mL (40 mg/mL) of posaconazole: White, cherry-flavored suspension in amber glass bottles with child-resistant closures. Posaconazole delayed-release tablet: 100 mg ( 3 ) Posaconazole oral suspension: 40 mg per mL ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Known hypersensitivity to posaconazole or other azole antifungal agents. ( 4.1 ) Coadministration of posaconazole with the following drugs is contraindicated: posaconazole increases concentrations and toxicities of: Sirolimus ( 4.2 , 7.2 ) CYP3A4 substrates (pimozide, quinidine): can result in QTc interval prolongation and cases of torsades de pointes (TdP) ( 4.3 , 5.2 , 7.2 ) HMG-CoA Reductase Inhibitors Primarily Metabolized through CYP3A4 ( 4.4 , 7.2 ) Ergot alkaloids ( 4.5 , 7.2 ) Venetoclax: In patients with chronic lymphocytic leukemia (CLL) or small lymphocytic lymphoma (SLL) at initiation and during the ramp-up phase ( 4.6 , 5.10 , 7.2 )
4.1Hypersensitivity Posaconazole is contraindicated in persons with known hypersensitivity to posaconazole or other azole antifungal agents.
4.2Use with Sirolimus Posaconazole is contraindicated with sirolimus. Concomitant administration of posaconazole with sirolimus increases the sirolimus blood concentrations by approximately 9-fold and can result in sirolimus toxicity [see Drug Interactions (7.2) and Clinical Pharmacology (12.3) ] .
4.3QT Prolongation with Concomitant Use with CYP3A4 Substrates Posaconazole is contraindicated with CYP3A4 substrates that prolong the QT interval. Concomitant administration of posaconazole with the CYP3A4 substrates, pimozide and quinidine may result in increased plasma concentrations of these drugs, leading to QTc prolongation and cases of torsades de pointes [see Warnings and Precautions (5.2) and Drug Interactions (7.2) ] .
4.4HMG-CoA Reductase Inhibitors Primarily Metabolized Through CYP3A4 Coadministration with the HMG-CoA reductase inhibitors that are primarily metabolized through CYP3A4 (e.g., atorvastatin, lovastatin, and simvastatin) is contraindicated since increased plasma concentration of these drugs can lead to rhabdomyolysis [see Drug Interactions (7.3) and Clinical Pharmacology (12.3) ] .
4.5Use with Ergot Alkaloids Posaconazole may increase the plasma concentrations of ergot alkaloids (ergotamine and dihydroergotamine) which may lead to ergotism [see Drug Interactions (7.2) ] .
4.6Use with Venetoclax Coadministration of posaconazole with venetoclax at initiation and during the ramp-up phase is contraindicated in patients with chronic lymphocytic leukemia (CLL) or small lymphocytic lymphoma (SLL) due to the potential for increased risk of tumor lysis syndrome [see Warnings and Precautions (5.10) and Drug Interactions (7.2) ].
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Calcineurin-Inhibitor Toxicity: Posaconazole increases concentrations of cyclosporine or tacrolimus; reduce dose of cyclosporine and tacrolimus and monitor concentrations frequently. ( 5.1 ) Arrhythmias and QTc Prolongation: Posaconazole has been shown to prolong the QTc interval and cause cases of TdP. Administer with caution to patients with potentially proarrhythmic conditions.
Do not administer with drugs known to prolong QTc interval and metabolized through CYP3A4. ( 5.2 , 7.2 ) Electrolyte Disturbances: Monitor and correct, especially those involving potassium (K + ), magnesium (Mg ++ ), and calcium (Ca ++ ), before and during posaconazole therapy. ( 5.3 ) Pseudoaldosteronism : Manifested by the onset or worsening of hypertension, and abnormal laboratory findings.
Monitor blood pressure and potassium levels, and manage as necessary. ( 5.4 ) Hepatic Toxicity: Elevations in liver tests may occur. Discontinuation should be considered in patients who develop abnormal liver tests or monitor liver tests during treatment.
( 5.5 ) Concomitant Use with Midazolam: Posaconazole can prolong hypnotic/sedative effects. Monitor patients and benzodiazepine receptor antagonists should be available. ( 5.7 , 7.2 ) Vincristine Toxicity: Concomitant administration of azole antifungals, including posaconazole, with vincristine has been associated with neurotoxicity and other serious adverse reactions; reserve azole antifungals, including posaconazole, for patients receiving a vinca alkaloid, including vincristine, who have no alternative antifungal treatment options.
( 5.8 , 7.2 ) Breakthrough Fungal Infections : Monitor patients with severe diarrhea or vomiting when receiving Posaconazole delayed-release tablets and Posaconazole oral suspension. ( 5.9 ) Venetoclax Toxicity: Concomitant administration of posaconazole with venetoclax may increase venetoclax toxicities, including the risk of tumor lysis syndrome, neutropenia, and serious infections; monitor for toxicity and reduce venetoclax dose. ( 4.6 , 5.10 , 7.2 )
5.1Calcineurin-Inhibitor Toxicity Concomitant administration of posaconazole with cyclosporine or tacrolimus increases the whole blood trough concentrations of these calcineurin-inhibitors [see Drug Interactions (7.2) and Clinical Pharmacology (12.3) ] . Nephrotoxicity and leukoencephalopathy (including deaths) have been reported in clinical efficacy studies in patients with elevated cyclosporine or tacrolimus concentrations. Frequent monitoring of tacrolimus or cyclosporine whole blood trough concentrations should be performed during and at discontinuation of posaconazole treatment and the tacrolimus or cyclosporine dose adjusted accordingly.
5.2Arrhythmias and QT Prolongation Some azoles, including posaconazole, have been associated with prolongation of the QT interval on the electrocardiogram. In addition, cases of torsades de pointes have been reported in patients taking posaconazole. Results from a multiple time-matched ECG analysis in healthy volunteers did not show any increase in the mean of the QTc interval.
Multiple, time-matched ECGs collected over a 12-hour period were recorded at baseline and steady-state from 173 healthy male and female volunteers (18-85 years of age) administered Noxafil oral suspension 400 mg twice daily with a high-fat meal. In this pooled analysis, the mean QTc (Fridericia) interval change from baseline was –5 msec following administration of the recommended clinical dose. A decrease in the QTc(F) interval (–3 msec) was also observed in a small number of subjects (n=16) administered placebo.
The placebo-adjusted mean maximum QTc(F) interval change from baseline was <0 msec (–8 msec). No healthy subject administered Noxafil had a QTc(F) interval ≥500 msec or an increase ≥60 msec in their QTc(F) interval from baseline. Posaconazole should be administered with caution to patients with potentially proarrhythmic conditions.
Do not administer with drugs that are known to pr… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious and otherwise important adverse reactions are discussed in detail in another section of the labeling: Arrhythmias and QT Prolongation [see Warnings and Precautions (5.2) ] Electrolyte Disturbances [see Warnings and Precautions (5.3) ] Pseudoaldosteronism [see Warnings and Precautions (5.4) ] Hepatic Toxicity [see Warnings and Precautions (5.5) ] Common adverse reactions in studies with posaconazole are diarrhea, nausea, fever, vomiting, headache, coughing, and hypokalemia. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Merck Sharp & Dohme LLC at 1-877-888-4231 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in clinical trials of Noxafil cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Treatment of Invasive Aspergillosis in Adults and Adolescents (Noxafil Injection and Noxafil Delayed-Release Tablets) The safety of Noxafil injection and Noxafil delayed-release tablets was assessed in a randomized, double-blind, active-controlled clinical study of Noxafil injection and Noxafil delayed-release tablets versus voriconazole for treatment of invasive aspergillosis (Aspergillosis Treatment Study).
A total of 575 adult and pediatric patients 14 years of age and older (288 in the Noxafil group, 287 in voriconazole group (voriconazole for injection or voriconazole tablets)) with proven, probable or possible invasive aspergillosis were included. The median duration of treatment was 67 days for Noxafil injection or Noxafil delayed-release tablet and 64 days for voriconazole (voriconazole for injection). In this study, with 55% to 60% of patients started intravenous treatment with Noxafil (Noxafil injection) or voriconazole (voriconazole for injection).
The median duration of the first instance of intravenous treatment (before switching to oral treatment or discontinuing or completing study treatment) was 9 days for both groups. Table 5 presents adverse reactions reported at an incidence of ≥10% in either one of the treatment groups in the Aspergillosis Treatment Study. Adverse reactions leading to treatment discontinuation were reported for 34% of patients.
The most commonly reported adverse reactions (>2% of patients) leading to treatment discontinuation were septic shock, respiratory failure, and bronchopulmonary aspergillosis in the Noxafil group, and septic shock and acute myeloid leukemia in the voriconazole group. The most frequently reported adverse reactions in the Noxafil-treated group were pyrexia (28%), hypokalemia (28%), and nausea (23%). Table 5: Adverse Reactions in at least 10% of Adults and Adolescents Receiving Noxafil Injection or Noxafil Delayed-Release Tablets for the Treatment of Invasive Aspergillosis Adverse Reactions Noxafil injection or Noxafil delayed-release tablets n=288 (%) Voriconazole for injection or Voriconazole tablets n=287 (%) Percentage of Patients Reporting any Adverse Reaction 97.6
97.6Hypokalemia 28.5
17.1Pyrexia 28.1
25.1Nausea 22.6
17.8Diarrhea 18.1
18.1Vomiting 18.1
13.6Alanine aminotransferase increased 14.6
12.9Febrile neutropenia 14.6
13.2Aspartate aminotransferase increased 13.2
12.5Pneumonia 12.5
9.1Headache 12.2
8.7Constipation 11.1
8.0Edema peripheral 11.1
8.4Epistaxis 11.1
5.9Cough 10.4
8.4Abdominal pain 10.1
8.4Hypomagnesemia 10.1
6.3Clinical Trial Experience with Noxafil Delayed-Release Tablets for Prophylaxis of Invasive Aspergillus and Candida Infections The safety of Noxafil delayed-release tablets has been assessed in 230 patients in clinical trials. Patients were enrolled in a non-comparative pharmacokinetic and safety trial of Noxafil delayed-release tablets when given as antifungal prophylaxis (Noxafil Delayed-Release Tablet Study). Patients were immunocompromised with underlying conditions including he… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 12 and Table 13 include drugs with clinically important drug interactions when administered concomitantly with posaconazole and instructions for preventing or managing them. Table 14 includes important drug interactions specific to the absorption of posaconazole administered as Posaconazole oral suspension. These recommendations are based on either drug interaction studies or predicted interactions due to the expected magnitude of interaction and potential for serious adverse reactions or loss of efficacy [see Clinical Pharmacology (12.3) ] .
The following information was derived from data with Noxafil oral suspension or another posaconazole tablet formulation unless otherwise noted. All clinically important drug interactions with Posaconazole oral suspension, except for those that affect the absorption of posaconazole (via gastric pH and motility), are considered relevant to clinically important drug interactions with Posaconazole delayed-release tablets [see Clinical Pharmacology (12.3) ] . Consult the labeling of concomitantly used drugs to obtain further information about interactions with posaconazole.
Interaction Drug Interaction Rifabutin, phenytoin, efavirenz, cimetidine, esomeprazole The drug interactions with esomeprazole and metoclopramide do not apply to Posaconazole tablets ( 7.3 , 12.3 ) . Avoid coadministration unless the benefit outweighs the risks ( 7.1 , 7.2 ) Other drugs metabolized by CYP3A4 Consider dosage adjustment and monitor for adverse effects and toxicity ( 7.2 ) Digoxin Monitor digoxin plasma concentrations ( 7.2 ) Fosamprenavir, metoclopramide Monitor for breakthrough fungal infections ( 7.1 )
7.1Effects of Other Drugs on Posaconazole Posaconazole is primarily metabolized via UDP-glucuronosyltransferase and is a substrate of p-glycoprotein (P-gp) efflux. Therefore, inhibitors or inducers of these clearance pathways may affect posaconazole plasma concentrations. Concomitant use of posaconazole with drugs that can decrease the plasma posaconazole concentrations should generally be avoided unless the benefit outweighs the risk.
If such drugs are necessary, patients should be monitored closely for breakthrough fungal infections. Table 12: Drug Interactions Affecting Posaconazole When Administered Concomitantly with Other Drugs UDP-Glucuronidase Inducers Mechanism and Clinical Effect(s) Posaconazole is a UDP-glucuronosyltransferase substrate. Concomitant use of posaconazole with UDP-glucuronidase inducers may decrease posaconazole exposure [see Clinical Pharmacology (12.3) ], which may reduce the effectiveness of posaconazole.
Prevention or Management Efavirenz Avoid concomitant use of posaconazole with efavirenz, unless the benefit outweighs the risks. Rifabutin Avoid concomitant use of posaconazole with rifabutin unless the benefit to the patient outweighs the risk. If concomitant use is needed, monitor closely for breakthrough fungal infections.
See Table 17 for rifabutin monitoring considerations when posaconazole affects rifabutin via CYP3A4 inhibition. Phenytoin Avoid concomitant use of posaconazole with phenytoin unless the benefit to the patient outweighs the risk. If concomitant use is needed, monitor for breakthrough fungal infections.
See Table 17 for phenytoin monitoring considerations when posaconazole affects phenytoin via CYP3A4 inhibition. Fosamprenavir Mechanism and Clinical Effect(s) Concomitant use of posaconazole with fosamprenavir may lead to decreased posaconazole plasma concentrations [see Clinical Pharmacology (12.3) ], which may reduce effectiveness of posaconazole. Prevention or Management If concomitant use of posaconazole with fosamprenavir is needed, monitor closely for breakthrough fungal infections.
Table 13: Drug Interactions Affecting Posaconazole Oral Suspension Absorption When Administered Concomitantly with Other Drugs Posaconazole Oral Suspension Cimetidine and Esomeprazole Mechanism and Clinical Effect(s) Concomitant use of Noxafil oral su… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause fetal harm. ( 8.1 ) Pediatrics: Safety and effectiveness in patients younger than 2 years of age have not been established. ( 8.4 ) Severe Renal Impairment : Monitor closely for breakthrough fungal infections. ( 8.6 )
8.1Pregnancy Risk Summary Based on findings from animal data, posaconazole may cause fetal harm when administered to pregnant women. Available data for use of Noxafil in pregnant women are insufficient to establish a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies, skeletal malformations were observed when posaconazole was dosed orally to pregnant rats during organogenesis at doses ≥1.4 times the 400 mg twice daily oral suspension regimen based on steady-state plasma concentrations of Noxafil in healthy volunteers.
In pregnant rabbits dosed orally during organogenesis, doses of ≥3 times the clinical exposure caused an increase in resorptions (see Data ) . Based on animal data, advise pregnant women of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data : Posaconazole resulted in maternal toxicity (reduced food consumption and reduced body weight gain) and skeletal malformations (cranial malformations and missing ribs) when given orally to pregnant rats during organogenesis (Gestational Days 6 through 15) at doses ≥27 mg/kg (≥1.4 times the 400 mg twice daily oral suspension regimen based on steady-state plasma concentrations of drug in healthy volunteers).
The no-effect dose for malformations and maternal toxicity in rats was 9 mg/kg, which is 0.7 times the exposure achieved with the 400 mg twice daily oral suspension regimen. No malformations were seen in rabbits dosed during organogenesis (Gestational Days 7 through 19) at doses up to 80 mg/kg (5 times the exposure achieved with the 400 mg twice daily oral suspension regimen). In the rabbit, the no-effect dose was 20 mg/kg, while high doses of 40 mg/kg and 80 mg/kg (3 or 5 times the clinical exposure) caused an increase in resorptions.
In rabbits dosed at 80 mg/kg, a reduction in body weight gain of females and a reduction in litter size were seen.
8.2Lactation Risk Summary There are no data on the presence of posaconazole in human milk, the effects on the breastfed infant, or the effects on milk production. Posaconazole is excreted in the milk of lactating rats. When a drug is present in animal milk, it is likely that the drug will be present in human milk.
The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for posaconazole and any potential adverse effects on the breastfed child from posaconazole or from the underlying maternal condition.
8.4Pediatric Use The posaconazole dosage forms (delayed-release tablets and oral suspension) are different products; are approved for different pediatric indications, age groups, and weights; have different dosing regimens; and have different preparation and administration instructions. Therefore, select the recommended dosage form based on the pediatric indication, age group, and weight [see Dosage and Administration (2.1) ]. Treatment of Invasive Aspergillosis The safety and effectiveness of Posaconazole delayed-release tablets have been established for the treatment of invasive aspergillosis in pediatric patients 2 years of age and older.
Use of posaconazole for these pediatric indications is supported by evidence from adequate and well-controlled studies of Noxafil in adults and safety and pharmacokinetic (PK) data from pediatric studies [se… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings from animal data, posaconazole may cause fetal harm when administered to pregnant women. Available data for use of Noxafil in pregnant women are insufficient to establish a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies, skeletal malformations were observed when posaconazole was dosed orally to pregnant rats during organogenesis at doses ≥1.4 times the 400 mg twice daily oral suspension regimen based on steady-state plasma concentrations of Noxafil in healthy volunteers.
In pregnant rabbits dosed orally during organogenesis, doses of ≥3 times the clinical exposure caused an increase in resorptions (see Data ) . Based on animal data, advise pregnant women of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data : Posaconazole resulted in maternal toxicity (reduced food consumption and reduced body weight gain) and skeletal malformations (cranial malformations and missing ribs) when given orally to pregnant rats during organogenesis (Gestational Days 6 through 15) at doses ≥27 mg/kg (≥1.4 times the 400 mg twice daily oral suspension regimen based on steady-state plasma concentrations of drug in healthy volunteers).
The no-effect dose for malformations and maternal toxicity in rats was 9 mg/kg, which is 0.7 times the exposure achieved with the 400 mg twice daily oral suspension regimen. No malformations were seen in rabbits dosed during organogenesis (Gestational Days 7 through 19) at doses up to 80 mg/kg (5 times the exposure achieved with the 400 mg twice daily oral suspension regimen). In the rabbit, the no-effect dose was 20 mg/kg, while high doses of 40 mg/kg and 80 mg/kg (3 or 5 times the clinical exposure) caused an increase in resorptions.
In rabbits dosed at 80 mg/kg, a reduction in body weight gain of females and a reduction in litter size were seen.
🧒 Pediatric Use ▾
8.4Pediatric Use The posaconazole dosage forms (delayed-release tablets and oral suspension) are different products; are approved for different pediatric indications, age groups, and weights; have different dosing regimens; and have different preparation and administration instructions. Therefore, select the recommended dosage form based on the pediatric indication, age group, and weight [see Dosage and Administration (2.1) ]. Treatment of Invasive Aspergillosis The safety and effectiveness of Posaconazole delayed-release tablets have been established for the treatment of invasive aspergillosis in pediatric patients 2 years of age and older.
Use of posaconazole for these pediatric indications is supported by evidence from adequate and well-controlled studies of Noxafil in adults and safety and pharmacokinetic (PK) data from pediatric studies [see Adverse Reactions (6.1) and Clinical Pharmacology (12.3) ] . The safety of Noxafil in pediatric patients for these pediatric indications was consistent with the known safety profile of Noxafil in adults [see Adverse Reactions (6.1) ]. The safety and effectiveness of posaconazole have not been established in pediatric patients less than 2 years of age .
Prophylaxis of Invasive Aspergillus and Candida Infections The safety and effectiveness of Posaconazole delayed-release tablets have been established for the prophylaxis of invasive Aspergillus and Candida infections in pediatric patients 2 years of age and older who are at high risk of developing these infections due to being severely immunocompromised. The safety and effectiveness of Posaconazole oral suspension have been established for the prophylaxis of invasive Aspergillus and Candida infections in pediatric patients 13 years of age and older who are at high risk of developing these infections due to being severely immunocompromised.
Use of posaconazole for these pediatric indications is supported by adequate and well-controlled studies of Noxafil in adults and pediatric patients aged 13 years and older and additional PK and safety data in pediatric patients 2 years of age and older [see Clinical Pharmacology (12.3) and Clinical Studies (14) ] . The safety and effectiveness of posaconazole have not been established in pediatric patients younger than 2 years of age. Treatment of Oropharyngeal Candidiasis, including Refractory to Itraconazole and/or Fluconazole The safety and effectiveness of Posaconazole oral suspension have been established for the treatment of oropharyngeal candidiasis (OPC), including OPC refractory (rOPC) to itraconazole and/or fluconazole in pediatric patients 13 years of age and older.
Use of Posaconazole oral suspension for this pediatric indication is supported by adequate and well controlled studies in adults and pediatric patients 13 years of age and older [see Clinical studies (14.4) ]. Posaconazole delayed-release tablets are not approved for the treatment of oropharyngeal candidiasis in pediatric patients. Posaconazole oral suspension is the only dosage form approved for the treatment of OPC and rOPC in pediatric patients [see Dosage and Administration (2.4) ].
The safety and effectiveness of Posaconazole oral suspension for the treatment of OPC and rOPC have not been established in pediatric patients less than 13 years of age.
🧓 Geriatric Use ▾
8.5Geriatric Use No overall differences in the safety of Noxafil delayed-release tablets and Noxafil oral suspension have been observed between geriatric patients and younger adult patients in the clinical trials; therefore, the recommended dosage in geriatric patients is the same as that for younger adult patients. No clinically meaningful differences in posaconazole pharmacokinetics were observed in Noxafil-treated geriatric patients compared to Noxafil-treated younger adult patients during clinical trials [see Clinical Pharmacology (12.3) ] .
Of the 230 patients treated with Noxafil delayed-release tablets, 38 (17%) patients were >65 years of age. Of the 605 patients treated with Noxafil oral suspension in Noxafil Oral Suspension Study 1 and Study 2 (prophylaxis of invasive Aspergillus and Candida infections in those at high risk of developing these infections due to being severely immunocompromised), 63 (10%) patients were ≥65 years of age. In studies of Noxafil for an unapproved indication, 48 patients treated with Noxafil oral suspension (greater than or equal to 800 mg/day (eight times the maximum recommended maintenance dosage for the treatment of OPC)) were ≥65 years of age.
Of the 288 patients treated with Noxafil injection or Noxafil delayed-release tablets in the Aspergillosis Treatment Study, 85 (29%) patients were ≥65 years of age.
🆘 Overdosage ▾
10 OVERDOSAGE There is no experience with overdosage of Posaconazole delayed-release tablets. During the clinical trials, some patients received Noxafil oral suspension up to 1600 mg/day with no adverse reactions noted that were different from the lower doses. In addition, accidental overdose was noted in one patient who took 1200 mg twice daily Noxafil oral suspension for 3 days.
No related adverse reactions were noted by the investigator. Posaconazole is not removed by hemodialysis.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Posaconazole is an azole antifungal agent [see Clinical Pharmacology (12.4) ] .
12.2Pharmacodynamics Exposure Response Relationship: Prophylaxis of invasive Aspergillus and Candida Infections in Adults Who Are at High Risk of Developing These Infections Due to Being Severely Immunocompromised In clinical studies of neutropenic patients who were receiving cytotoxic chemotherapy for acute myelogenous leukemia (AML) or myelodysplastic syndromes (MDS) or hematopoietic stem cell transplant (HSCT) recipients with Graft versus Host Disease (GVHD), a wide range of plasma posaconazole exposures was noted following administration of Noxafil oral suspension.
A pharmacokinetic-pharmacodynamic analysis of patient data revealed an apparent association between average posaconazole concentrations (Cavg) and prophylactic efficacy (Table 15). A lower Cavg may be associated with an increased risk of treatment failure, defined as treatment discontinuation, use of empiric systemic antifungal therapy (SAF), or occurrence of breakthrough invasive fungal infections. Table 15: Noxafil Oral Suspension Exposure Analysis (Cavg) in Prophylaxis Trials Prophylaxis in AML/MDS Neutropenic patients who were receiving cytotoxic chemotherapy for AML or MDS Prophylaxis in GVHD HSCT recipients with GVHD Cavg Range (ng/mL) Treatment Failure Defined as treatment discontinuation, use of empiric systemic antifungal therapy (SAF), or occurrence of breakthrough invasive fungal infections (%) Cavg Range (ng/mL) Treatment Failure (%) Cavg = the average posaconazole concentration when measured at steady state Quartile 1 90-322 54.7 22-557
44.4Quartile 2 322-490 37.0 557-915
20.6Quartile 3 490-734 46.8 915-1563
17.5Quartile 4 734-2200 27.8 1563-3650
17.5Exposure Response Relationship: Treatment of Invasive Aspergillosis in Adult and Adolescent Patients: Across a range of posaconazole plasma minimum concentrations (C min, range: 244 to 5663 ng/mL) following administration of Noxafil injection and Noxafil delayed-release tablets in adult and pediatric patients aged 14 years and older treated for invasive aspergillosis in Aspergillosis Treatment Study, there was no association between posaconazole C min and treatment efficacy [see Clinical Pharmacology (12.3) and Clinical Studies (14.1) ] .
Similarly, across a range of population pharmacokinetic model-predicted steady-state plasma average concentrations (Cavg, range: 589 to 6315 ng/mL), there was no association between posaconazole Cavg and treatment efficacy.
12.3Pharmacokinetics General Pharmacokinetic Characteristics General Pharmacokinetic Characteristics of Posaconazole Delayed-Release Tablets Noxafil delayed-release tablets exhibit dose proportional pharmacokinetics after single and multiple dosing up to 300 mg. The mean pharmacokinetic parameters of posaconazole at steady state following administration of Noxafil delayed-release tablets 300 mg twice daily on Day 1, then 300 mg once daily thereafter in healthy volunteers and in neutropenic patients who are receiving cytotoxic chemotherapy for AML or MDS or HSCT recipients with GVHD are shown in Table 16.
Table 16: Arithmetic Mean (%CV) of Steady State PK Parameters in Healthy Volunteers and Patients Following Administration of Noxafil Delayed-Release Tablets (300 mg) 300 mg twice daily on Day 1, then 300 mg once daily thereafter N AUC 0-24 hr (ng∙hr/mL) Cav Cav = time-averaged concentrations (i.e., AUC 0-24 hr /24 hr) (ng/mL) C max (ng/mL) C min (ng/mL) T max Median (minimum-maximum) (hr) t 1/2 (hr) CL/F (L/hr) CV = coefficient of variation expressed as a percentage (%CV); AUC 0-T = Area under the plasma concentration-time curve from time zero to 24 hr; C max = maximum observed concentration; C min = minimum observed plasma concentration; T max = time of maximum observed concentration; t ½ = terminal phase half-life; CL/F = Apparent total body clearance Healthy Volunteers 12 51618 (25) 2151 (25) 2764 (21) 1785 (29)… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Posaconazole is an azole antifungal agent [see Clinical Pharmacology (12.4) ] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Posaconazole Delayed-Release Tablets Posaconazole delayed-release tablets are yellow, coated, oblong, debossed with "100" on one side containing 100 mg of posaconazole. Bottles with child-resistant closures of 60 delayed-release tablets (NDC 0254-2045-02). Posaconazole Oral Suspension Posaconazole oral suspension is a white, cherry-flavored suspension in 4-ounce (123 mL) amber glass bottles with child-resistant closures containing 105 mL of suspension (40 mg of posaconazole per mL).
Supplied with each oral suspension bottle is a plastic dosing spoon calibrated for measuring 2.5-mL and 5-mL doses (NDC 0254-1016-36).
16.2Storage and Handling Posaconazole Delayed-Release Tablets Store at 20°C to 25°C (68°F to 77°F), excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Posaconazole Oral Suspension Store at 25°C (77°F); excursions permitted to 15 to 30°C (59 to 86°F) [see USP Controlled Room Temperature]. DO NOT FREEZE.
16.1How Supplied Posaconazole Delayed-Release Tablets Posaconazole delayed-release tablets are yellow, coated, oblong, debossed with "100" on one side containing 100 mg of posaconazole. Bottles with child-resistant closures of 60 delayed-release tablets (NDC 0254-2045-02). Posaconazole Oral Suspension Posaconazole oral suspension is a white, cherry-flavored suspension in 4-ounce (123 mL) amber glass bottles with child-resistant closures containing 105 mL of suspension (40 mg of posaconazole per mL).
Supplied with each oral suspension bottle is a plastic dosing spoon calibrated for measuring 2.5-mL and 5-mL doses (NDC 0254-1016-36).
📦 Storage and Handling ▾
16.2Storage and Handling Posaconazole Delayed-Release Tablets Store at 20°C to 25°C (68°F to 77°F), excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Posaconazole Oral Suspension Store at 25°C (77°F); excursions permitted to 15 to 30°C (59 to 86°F) [see USP Controlled Room Temperature]. DO NOT FREEZE.
📋 Description ▾
11 DESCRIPTION Posaconazole delayed-release tablets and Posaconazole oral suspension contain posaconazole; an azole antifungal agent. Posaconazole is designated chemically as 4-[4-[4-[4-[[ (3 R ,5 R )-5- (2,4-difluorophenyl)tetrahydro-5- (1 H -1,2,4-triazol-1-ylmethyl)-3-furanyl]methoxy]phenyl]-1-piperazinyl]phenyl]-2-[(1 S ,2 S )-1-ethyl-2-hydroxypropyl]-2,4-dihydro-3 H -1,2,4-triazol-3-one with an empirical formula of C 37 H 42 F 2 N 8 O 4 and a molecular weight of 700.8. The chemical structure is: Posaconazole is a white powder with a low aqueous solubility.
Posaconazole Delayed-Release Tablets Posaconazole delayed-release tablet, for oral use, is yellow, coated, and oblong and contains 100 mg of posaconazole. Each delayed-release tablet contains the inactive ingredients: croscarmellose sodium, hydroxypropylcellulose, hypromellose acetate succinate, iron oxide yellow, Macrogol/PEG 3350, magnesium stearate, microcrystalline cellulose, polyvinyl alcohol partially hydrolyzed, silicon dioxide, talc, and titanium dioxide. Posaconazole Oral Suspension Posaconazole oral suspension is a white, cherry-flavored immediate-release suspension that contains 40 mg of posaconazole per mL and the following inactive ingredients: artificial cherry flavor, citric acid monohydrate, glycerin, liquid glucose, polysorbate 80, purified water, simethicone, sodium benzoate, sodium citrate dihydrate, titanium dioxide, and xanthan gum.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information ). Important Administration Instructions Posaconazole Delayed-Release Tablets Advise patients that Posaconazole delayed-release tablets must be swallowed whole and not divided, crushed, or chewed. Instruct patients that if they miss a dose, they should take it as soon as they remember.
If they do not remember until it is within 12 hours of the next dose, they should be instructed to skip the missed dose and go back to the regular schedule. Patients should not double their next dose or take more than the prescribed dose. Posaconazole Oral Suspension Advise patients to take each dose of Posaconazole oral suspension during or immediately (i.e., within 20 minutes) following a full meal.
In patients who cannot eat a full meal, each dose of Posaconazole oral suspension should be administered with a liquid nutritional supplement or an acidic carbonated beverage (e.g., ginger ale) in order to enhance absorption. Instruct patients that if they miss a dose, they should take it as soon as they remember. However, if it is almost time for the next dose, they should be instructed to skip the missed dose and go back to the regular schedule.
Patients should not double their next dose or take more than the prescribed dose. Drug Interactions Advise patients to inform their physician immediately if they: develop severe diarrhea or vomiting. are currently taking drugs that are known to prolong the QTc interval and are metabolized through CYP3A4. are currently taking a cyclosporine or tacrolimus, or they notice swelling in an arm or leg or shortness of breath. are taking other drugs or before they begin taking other drugs as certain drugs can decrease or increase the plasma concentrations of posaconazole.
Serious and Potentially Serious Adverse Reactions Advise patients to inform their physician immediately if they: notice a change in heart rate or heart rhythm or have a heart condition or circulatory disease. Posaconazole can be administered with caution to patients with potentially proarrhythmic conditions. are pregnant, plan to become pregnant, or are nursing. have liver disease or develop itching, nausea or vomiting, their eyes or skin turn yellow, they feel more tired than usual or feel like they have the flu. have ever had an allergic reaction to other antifungal medicines such as ketoconazole, fluconazole, itraconazole, or voriconazole.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics General Pharmacokinetic Characteristics General Pharmacokinetic Characteristics of Posaconazole Delayed-Release Tablets Noxafil delayed-release tablets exhibit dose proportional pharmacokinetics after single and multiple dosing up to 300 mg. The mean pharmacokinetic parameters of posaconazole at steady state following administration of Noxafil delayed-release tablets 300 mg twice daily on Day 1, then 300 mg once daily thereafter in healthy volunteers and in neutropenic patients who are receiving cytotoxic chemotherapy for AML or MDS or HSCT recipients with GVHD are shown in Table 16.
Table 16: Arithmetic Mean (%CV) of Steady State PK Parameters in Healthy Volunteers and Patients Following Administration of Noxafil Delayed-Release Tablets (300 mg) 300 mg twice daily on Day 1, then 300 mg once daily thereafter N AUC 0-24 hr (ng∙hr/mL) Cav Cav = time-averaged concentrations (i.e., AUC 0-24 hr /24 hr) (ng/mL) C max (ng/mL) C min (ng/mL) T max Median (minimum-maximum) (hr) t 1/2 (hr) CL/F (L/hr) CV = coefficient of variation expressed as a percentage (%CV); AUC 0-T = Area under the plasma concentration-time curve from time zero to 24 hr; C max = maximum observed concentration; C min = minimum observed plasma concentration; T max = time of maximum observed concentration; t ½ = terminal phase half-life; CL/F = Apparent total body clearance Healthy Volunteers 12 51618 (25) 2151 (25) 2764 (21) 1785 (29) 4 (3-6) 31 (40) 7.5 (26) Patients 50 37900 (42) 1580 (42) 2090 (38) 1310 (50) 4 (1.3-8.3) - 9.39 (45) General Pharmacokinetic Characteristics of Posaconazole Oral Suspension Dose-proportional increases in plasma exposure (AUC) to Noxafil oral suspension were observed following single oral doses from 50 mg to 800 mg and following multiple-dose administration from 50 mg twice daily to 400 mg twice daily in healthy volunteers.
No further increases in exposure were observed when the dose of the oral suspension increased from 400 mg twice daily to 600 mg twice daily in febrile neutropenic patients or those with refractory invasive fungal infections. The mean (%CV) [min-max] Noxafil oral suspension average steady-state plasma concentrations (Cavg) and steady-state pharmacokinetic parameters in patients following administration of 200 mg three times a day and 400 mg twice daily of the oral suspension are provided in Table 17. Table 17: The Mean (%CV) [min-max] Posaconazole Steady-State Pharmacokinetic Parameters in Patients Following Oral Administration of Noxafil Oral Suspension 200 mg Three Times a Day and 400 mg Twice Daily Dose Oral suspension administration Cavg (ng/mL) AUC AUC (0-24 hr) for 200 mg three times a day and AUC (0-12 hr) for 400 mg twice daily (ng∙hr/mL) CL/F (L/hr) V/F (L) t ½ (hr) Cavg = the average posaconazole concentration when measured at steady state 200 mg three times a day HSCT recipients with GVHD (n=252) 1103 (67) [21.5-3650] ND Not done ND ND ND 200 mg three times a day Neutropenic patients who were receiving cytotoxic chemotherapy for acute myelogenous leukemia or myelodysplastic syndromes (n=215) 583 (65) [89.7-2200] 15,900 (62) [4100-56,100] 51.2 (54) [10.7-146] 2425 (39) [828-5702] 37.2 (39) [19.1-148] 400 mg twice daily Febrile neutropenic patients or patients with refractory invasive fungal infections, Cavg n=24 The variability in average plasma posaconazole concentrations in patients was relatively higher than that in healthy subjects.
(n=23) 723 (86) [6.70-2256] 9093 (80) [1564-26,794] 76.1 (78) [14.9-256] 3088 (84) [407-13,140] 31.7 (42) [12.4-67.3] Absorption: Absorption of Posaconazole Delayed-Release Tablets When given orally in healthy volunteers, Noxafil delayed-release tablets are absorbed with a median T max of 4 to 5 hours. Steady-state plasma concentrations are attained by Day 6 at the 300 mg dose (once daily after twice daily loading dose at Day 1). The absolute bioavailability of the oral delayed-release tablet is approximately 54% under fasted conditions.
The C max and AU… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Exposure Response Relationship: Prophylaxis of invasive Aspergillus and Candida Infections in Adults Who Are at High Risk of Developing These Infections Due to Being Severely Immunocompromised In clinical studies of neutropenic patients who were receiving cytotoxic chemotherapy for acute myelogenous leukemia (AML) or myelodysplastic syndromes (MDS) or hematopoietic stem cell transplant (HSCT) recipients with Graft versus Host Disease (GVHD), a wide range of plasma posaconazole exposures was noted following administration of Noxafil oral suspension.
A pharmacokinetic-pharmacodynamic analysis of patient data revealed an apparent association between average posaconazole concentrations (Cavg) and prophylactic efficacy (Table 15). A lower Cavg may be associated with an increased risk of treatment failure, defined as treatment discontinuation, use of empiric systemic antifungal therapy (SAF), or occurrence of breakthrough invasive fungal infections. Table 15: Noxafil Oral Suspension Exposure Analysis (Cavg) in Prophylaxis Trials Prophylaxis in AML/MDS Neutropenic patients who were receiving cytotoxic chemotherapy for AML or MDS Prophylaxis in GVHD HSCT recipients with GVHD Cavg Range (ng/mL) Treatment Failure Defined as treatment discontinuation, use of empiric systemic antifungal therapy (SAF), or occurrence of breakthrough invasive fungal infections (%) Cavg Range (ng/mL) Treatment Failure (%) Cavg = the average posaconazole concentration when measured at steady state Quartile 1 90-322 54.7 22-557
44.4Quartile 2 322-490 37.0 557-915
20.6Quartile 3 490-734 46.8 915-1563
17.5Quartile 4 734-2200 27.8 1563-3650
17.5Exposure Response Relationship: Treatment of Invasive Aspergillosis in Adult and Adolescent Patients: Across a range of posaconazole plasma minimum concentrations (C min, range: 244 to 5663 ng/mL) following administration of Noxafil injection and Noxafil delayed-release tablets in adult and pediatric patients aged 14 years and older treated for invasive aspergillosis in Aspergillosis Treatment Study, there was no association between posaconazole C min and treatment efficacy [see Clinical Pharmacology (12.3) and Clinical Studies (14.1) ] .
Similarly, across a range of population pharmacokinetic model-predicted steady-state plasma average concentrations (Cavg, range: 589 to 6315 ng/mL), there was no association between posaconazole Cavg and treatment efficacy.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Treatment of Invasive Aspergillosis with Noxafil Injection and Noxafil Delayed-Release Tablets Aspergillosis Treatment Study (NCT01782131) was a randomized, double-blind, controlled trial which evaluated the safety and efficacy of Noxafil injection and Noxafil delayed-release tablets versus voriconazole for primary treatment of invasive fungal disease caused by Aspergillus species. Eligible patients had proven, probable, or possible invasive fungal infections per the European Organization for Research and Treatment of Cancer/Mycoses Study Group, EORTC/MSG criteria.
Patients were stratified by risk for mortality or poor outcome where high risk included a history of allogeneic bone marrow transplant, liver transplant, or relapsed leukemia undergoing salvage chemotherapy. The median age of patients was 57 years (range: 14-91 years), with 27.8% of patients aged ≥65 years; 5 patients were pediatric patients 14-16 years of age, of whom 3 were treated with Noxafil and 2 with voriconazole. The majority of patients were male (59.8%) and white (67.1%).
With regard to risk factors for invasive aspergillosis, approximately two-thirds of the patients in the study had a recent history of neutropenia, while approximately 20% with a history of an allogeneic stem cell transplant. Over 80% of subjects in each treatment group had infection limited to the lower respiratory tract (primarily lung), while approximately 11% to 13% also had infection in another organ. Invasive aspergillosis was proven or probable in 58.1% of patients as classified by independent adjudicators blinded to study treatment assignment.
At least one Aspergillus species was identified in 21% of the patients; A. fumigatus and A. flavus were the most common pathogens identified. Patients randomized to receive Noxafil were given a dose of 300 mg once daily (twice daily on Day 1) IV or tablet. Patients randomized to receive voriconazole were given a dose of 6 mg/kg twice daily Day 1 followed by 4 mg/kg twice daily IV, or oral 300 mg twice daily Day 1 followed by 200 mg twice daily.
The recommended initial route of administration was IV; however, patients could begin oral therapy if clinically stable and able to tolerate oral dosing. The transition from IV to oral therapy occurred when the patient was clinically stable. The protocol recommended duration of therapy was 84 days with a maximum allowed duration of 98 days.
Median treatment duration was 67 days for Noxafil patients and 64 days for voriconazole patients. Overall, 55% to 60% of patients began treatment with the IV formulation with a median duration of 9 days for the initial IV dosing. The Intent to Treat (ITT) population included all patients randomized and receiving at least one dose of study treatment.
All-cause mortality through Day 42 in the overall population (ITT) was 15.3% for Noxafil patients compared to 20.6% for voriconazole patients for an adjusted treatment difference of -5.3% with a 95% confidence interval of -11.6 to 1.0%. Consistent results were seen in patients with proven or probable invasive aspergillosis per EORTC criteria (see Table 26 ). Table 26: Noxafil Injection and Noxafil Delayed-Release Tablets Invasive Aspergillosis Treatment Study: All-Cause Mortality Through Day 42 Noxafil Injection and Delayed-Release Tablets Voriconazole Population N n (%) N n (%) Difference Adjusted treatment difference based on Miettinen and Nurminen’s method stratified by randomization factor (risk for mortality/poor outcome), using Cochran-Mantel-Haenszel weighting scheme.
(95% CI) Intent to Treat 288 44 (15.3) 287 59 (20.6) -5.3 (-11.6, 1.0) Proven/Probable Invasive Aspergillosis 163 31 (19.0) 171 32 (18.7) 0.3 (-8.2, 8.8) Global clinical response at Week 6 was assessed by a blinded, independent adjudication committee based upon prespecified clinical, radiologic, and mycologic criteria. In the subgroup of patients with proven or probable invasive aspergillosis per EORTC criteria, the global cl… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis No drug-related neoplasms were recorded in rats or mice treated with posaconazole for 2 years at doses higher than the clinical dose. In a 2 years carcinogenicity study, rats were given posaconazole orally at doses up to 20 mg/kg (females), or 30 mg/kg (males). These doses are equivalent to 3.9- or 3.5-times the exposure achieved with a 400 mg twice daily oral suspension regimen, respectively, based on steady-state AUC in healthy volunteers administered a high-fat meal (400 mg twice daily oral suspension regimen).
In the mouse study, mice were treated at oral doses up to 60 mg/kg/day or 4.8-times the exposure achieved with a 400 mg twice daily oral suspension regimen. Mutagenesis Posaconazole was not genotoxic or clastogenic when evaluated in bacterial mutagenicity (Ames), a chromosome aberration study in human peripheral blood lymphocytes, a Chinese hamster ovary cell mutagenicity study, and a mouse bone marrow micronucleus study. Impairment of Fertility Posaconazole had no effect on fertility of male rats at a dose up to 180 mg/kg (1.7 x the 400 mg twice daily oral suspension regimen based on steady-state plasma concentrations in healthy volunteers) or female rats at a dose up to 45 mg/kg (2.2 x the 400 mg twice daily oral suspension regimen).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis No drug-related neoplasms were recorded in rats or mice treated with posaconazole for 2 years at doses higher than the clinical dose. In a 2 years carcinogenicity study, rats were given posaconazole orally at doses up to 20 mg/kg (females), or 30 mg/kg (males). These doses are equivalent to 3.9- or 3.5-times the exposure achieved with a 400 mg twice daily oral suspension regimen, respectively, based on steady-state AUC in healthy volunteers administered a high-fat meal (400 mg twice daily oral suspension regimen).
In the mouse study, mice were treated at oral doses up to 60 mg/kg/day or 4.8-times the exposure achieved with a 400 mg twice daily oral suspension regimen. Mutagenesis Posaconazole was not genotoxic or clastogenic when evaluated in bacterial mutagenicity (Ames), a chromosome aberration study in human peripheral blood lymphocytes, a Chinese hamster ovary cell mutagenicity study, and a mouse bone marrow micronucleus study. Impairment of Fertility Posaconazole had no effect on fertility of male rats at a dose up to 180 mg/kg (1.7 x the 400 mg twice daily oral suspension regimen based on steady-state plasma concentrations in healthy volunteers) or female rats at a dose up to 45 mg/kg (2.2 x the 400 mg twice daily oral suspension regimen).
📄 Patient Package Insert ▾
This Patient Information has been approved by the U.S. Food and Drug Administration. Revised: 1/2026 Patient Information Posaconazole delayed-release tablets Posaconazole oral suspension What is posaconazole?
Posaconazole (which refers to delayed-release tablets and oral suspension) is a prescription medicine used in adults and children to help prevent or treat fungal infections that can spread throughout your body (invasive fungal infections). These infections are caused by fungi called Aspergillus or Candida . Posaconazole is used in people who have an increased chance of getting these infections due to a weak immune system.
These include people who have had a hematopoietic stem cell transplantation (bone marrow transplant) with graft versus host disease or those with a low white blood cell count due to chemotherapy for blood cancers (hematologic malignancies). Posaconazole delayed-release tablets are used for: prevention of fungal infections in adults and children 2 years of age and older who weigh greater than 88 lbs (40 kg). treatment of fungal infections in adults and children 2 years of age and older who weigh greater than 88 lbs (40 kg).
Posaconazole oral suspension is used for: prevention of fungal infections in adults and children 13 years of age and older. Posaconazole oral suspension is also used to treat a fungal infection called “thrush” caused by Candida in your mouth or throat area. Posaconazole oral suspension can be used as the first treatment for thrush, or as another treatment for thrush after itraconazole or fluconazole treatment has not worked.
Posaconazole oral suspension is for adults and children 13 years of age and older. It is not known if Posaconazole oral suspension is safe and effective in children under 13 years of age for the treatment of thrush as the first treatment for thrush, or as another treatment for thrush after itraconazole or fluconazole treatment has not worked. It is not known if posaconazole is safe and effective in children under 2 years of age.
Do not take posaconazole if you: are allergic to posaconazole, any of the ingredients in posaconazole, or other azole antifungal medicines. See the end of this Patient Information leaflet for a complete list of ingredients in posaconazole. are taking any of the following medicines: sirolimus pimozide quinidine certain statin medicines that lower cholesterol (atorvastatin, lovastatin, simvastatin) ergot alkaloids (ergotamine, dihydroergotamine) have chronic lymphocytic leukemia (CLL) or small lymphocytic lymphoma (SLL) and you have just started taking venetoclax or your venetoclax dose is being slowly increased.
Ask your healthcare provider or pharmacist if you are not sure if you are taking any of these medicines. Do not start taking a new medicine without talking to your healthcare provider or pharmacist. Before you take posaconazole, tell your healthcare provider about all of your medical conditions, including if you: are taking certain medicines that lower your immune system like cyclosporine or tacrolimus. are taking certain drugs for HIV infection, such as ritonavir, atazanavir, efavirenz, or fosamprenavir.
Efavirenz and fosamprenavir can cause a decrease in the posaconazole levels in your body. Efavirenz and fosamprenavir should not be taken with posaconazole. are taking midazolam, a hypnotic and sedative medicine. are taking vincristine, vinblastine and other "vinca alkaloids" (medicines used to treat cancer). are taking venetoclax, a medicine used to treat cancer. have or had liver problems. have or had kidney problems. have or had an abnormal heart rate or rhythm, heart problems, or blood circulation problems. are pregnant or plan to become pregnant.
It is not known if posaconazole will harm your unborn baby. are breastfeeding or plan to breastfeed. It is not known if posaconazole passes into your breast milk. You and your healthcare provider should decide if you will take posaconazole or breastfeed.
You should not do both. Tell yo… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Indications and Usage ( 1.1 , 1.2 ) 1/2026 Dosage and Administration ( 2 ) 1/2026
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 100 mg Tablet Bottle Label NDC 0254-2045-02 Posaconazole Delayed-Release Tablets 100 mg Each tablet contains 100 mg posaconazole. Attention: Posaconazole Oral Suspension and Delayed-Release Tablets are NOT substitutable due to differences in the dosing of each formulation. Rx only 60 Tablets endo ® PRINCIPAL DISPLAY PANEL - 100 mg Tablet Bottle Label
PRINCIPAL DISPLAY PANEL - 105 ML BOTTLE CARTON NDC 0254-1016-36 105 mL Posaconazole Oral Suspension 200 mg/5 mL Each mL contains: 40 mg posaconazole. Attention: Posaconazole Oral Suspension and Delayed-Release Tablets are NOT substitutable due to differences in the dosing of each formulation. SHAKE WELL BEFORE EACH USE.
Take with a meal, or a nutritional supplement, or an acidic carbonated beverage. Carton contains measured dosing spoon. Rx only endo ® PRINCIPAL DISPLAY PANEL - 105 ML BOTTLE CARTON