
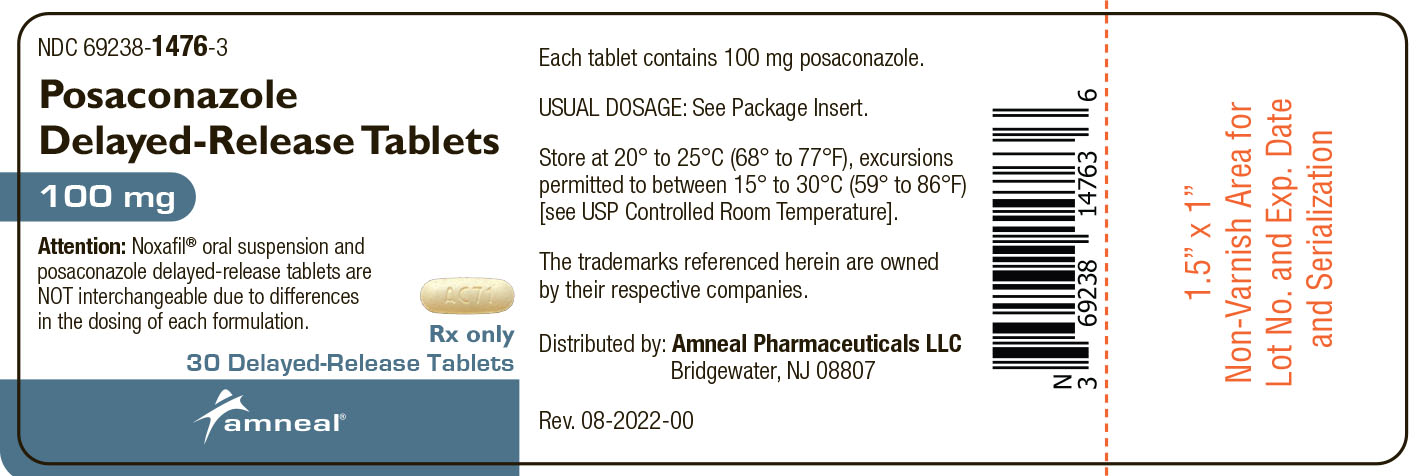
Posaconazole 100 mg Tablet, Delayed Release, 30-count — NDC 69238-1476-3 (Billing 69238-1476-03)
This is a package of 30 tablets of Posaconazole 100 mg Tablet, Delayed Release from Amneal Pharmaceuticals NY LLC, marketed since Dec 2022 and currently FDA-listed.
Other active recalls for Posaconazole (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 071709
- GCN: 35649
- GPI-14 (Medi-Span): 11407060000620
- HICL (First Databank): 033461
- AHFS class code: 08:14.08.00
- RxCUI (RxNorm): 1482908
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Azole Antifungal class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats invasive aspergillosis, a serious mold infection. It also helps prevent serious Aspergillus and Candida infections when your immune system is severely weakened. The oral...
- Delayed-release tablets can be taken with or without food. The oral suspension should be taken with a full meal. The injection is given by a clinician through a central line over a...
- The most common are diarrhea, nausea, vomiting, fever, headache, cough and low potassium. Let your care team know if they are bothersome or severe.
- Call right away for a racing or irregular heartbeat, fainting, signs of liver trouble, rising blood pressure or swelling, or severe vomiting and diarrhea. Those last two can keep t...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Posaconazole — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $10.45 | $313.64 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 2, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 69238-1476-03 You're viewing this | 30 TABLET, DELAYED RELEASE in 1 BOTTLE | — | — | 2022-12-30 | — | Active |
| 69238-1476-06 69238-1476-6 Main listing | 60 TABLET, DELAYED RELEASE in 1 BOTTLE | $2.03 / ea | $121.89 | 2022-12-30 | — | Active |
You're viewing the smallest of 2 pack sizes for this product.
This pack shows little to no recent Medicaid volume — the 60 tablets pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 69238-1476-06?
What NDC number is used to bill for this package of Posaconazole 100 mg Tablet, Delayed Release?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Posaconazole 100 mg 00254-2045-02 | ENDO | 60 tablets | $2.032 | — | Availability likely | — |
| Posaconazole 100 mg 00406-7711-60 | SpecGx | 60 tablets | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 00904-7149-04 | Major | 1 tablet | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 16714-0535-01 | NorthStar | 60 tablets | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 31722-0677-60 | Camber | 60 tablets | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 43598-0470-60 | Dr.Reddys | 60 tablets | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 50268-0683-12 | AvPAK | 1 tablet | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 59651-0596-60 | Aurobindo | 60 tablets | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 60687-0523-21 | American | 1 tablet | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 62135-0429-60 | Chartwell | 60 tablets | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 70377-0038-11 | Biocon | 60 tablets | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 70748-0258-07 | Lupin | 60 tablets | $2.032 | AB | Availability likely | — |
| posaconazole 100 mg 72205-0168-60 | Novadoz | 60 tablets | $2.032 | AB | Availability likely | — |
| Posaconazole 100 mg 72319-0023-02 | i3 | 60 tablets | $2.032 | AB | Availability likely | — |
| Noxafil 100 mg 00085-4324-02 | Merck | 60 tablets | — | — | FDA listed | — |
| Posaconazole 100 mg 00527-2133-30 | Lannett | 24 tablets | — | AB | FDA listed | — |
| Posaconazole 100 mg 17856-2133-01 | ATLANTIC | 1 tablet | — | AB | FDA listed | — |
| Posaconazole 100 mg 42291-0919-60 | AvKARE | 60 tablets | — | AB | FDA listed | — |
| Posaconazole 100 mg 51407-0676-60 | Golden | 60 tablets | — | AB | FDA listed | — |
| Posaconazole 100 mg 63629-2236-01 | Bryant | 60 tablets | — | — | Discontinued | — |
| Posaconazole 100 mgthis 69238-1476-03 | Amneal | 30 tablets | — | AB | FDA listed | — |
| Posaconazole 100 mg 71335-2665-01 | Bryant | 60 tablets | — | AB | FDA listed | — |
| Posaconazole 100 mg 71335-2930-01 | Bryant | 60 tablets | — | AB | FDA listed | — |
| Posaconazole 100 mg 72162-2243-02 | Bryant | 20 tablets | — | AB | FDA listed | — |
| Posaconazole 100 mg 73141-0023-02 | A2A | 60 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Posaconazole delayed-release tablets are an azole antifungal indicated as follows: Posaconazole delayed-release tablets are indicated for the prophylaxis of invasive Aspergillus and Candida infections in patients who are at high risk of developing these infections due to being severely immunocompromised, such as hematopoietic stem cell transplant (HSCT) recipients with graft-versus-host disease (GVHD) or those with hematologic malignancies with prolonged neutropenia from chemotherapy as follows: (1.2) Posaconazole delayed-release tablets: adults and pediatric patients 2 years of age and older who weigh greater than 40 kg
1.2Prophylaxis of Invasive Aspergillus and Candida Infections Posaconazole delayed-release tablets are indicated for the prophylaxis of invasive Aspergillus and Candida infections in patients who are at high risk of developing these infections due to being severely immunocompromised, such as hematopoietic stem cell transplant (HSCT) recipients with graft-versus-host disease (GVHD) or those with hematologic malignancies with prolonged neutropenia from chemotherapy as follows: Posaconazole delayed-release tablets: adults and pediatric patients 2 years of age and older who weigh greater than 40 kg Additional Pediatric Use information is approved for Merck Sharp & Dohme Corp.’s NOXAFIL (posaconazole) delayed-release tablets.
However, due to Merck Sharp & Dohme Corp.’s marketing exclusivity rights, this drug product is not labeled with that pediatric information.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Posaconazole delayed-release tablets formulations are supplied in different dose strengths of posaconazole, are approved for different indications, age groups, and weights, have different dosages and duration of therapy; and have different preparation and administration instructions. (2.1) Noxafil oral suspension is not substitutable with posaconazole delayed-release tablets or Noxafil PowderMix for delayed-release oral suspension due to the differences in the dosing of each formulation. Therefore, follow the specific dosage recommendations for each of the formulations.
(2.1 , 2.2 , 2.3) Administer posaconazole delayed-release tablets with or without food. (2.1) See the full prescribing information for important administration instructions and preparation instructions for posaconazole delayed -release tablets (2.7 , 2.9) For adult and pediatric patients aged 2 years of age and older, see the Full Prescribing Information for dosing recommendations for posaconazole delayed-release tablets, based on the indication, age, and weight associated with the dosage form (1.2 , 2.1 , 2.2 , 2.3)
2.1Important Administration Instructions Noxafil injection, posaconazole delayed-release tablets, Noxafil oral suspension and Noxafil PowderMix for delayed-release oral suspension are supplied in different dose strengths of posaconazole, are approved for different indications, age groups and weights; have different dosages and duration of therapy; and have different preparation and administration instructions. Therefore, select the recommended dosage form based on the indication, age group, and weight and carefully follow the recommended dosage, preparation and administration instructions described for each product [see Dosage and Administration (2.2 to 2.11) ] , and the following important administration instructions described below.
Non-substitutable Noxafil oral suspension is not substitutable with posaconazole delayed-release tablets or Noxafil PowderMix for delayed-release oral suspension due to the differences in the dosing of each formulation. Therefore, follow the specific dosage recommendations for each of the formulations [see Dosage and Administration (2.2 , 2.3) ] . Posaconazole delayed-release tablets Swallow tablets whole.
Do not divide, crush, or chew. Administer with or without food [see Dosage and Administration (2.7) and Clinical Pharmacology (12.3) ] . For patients who cannot eat a full meal, posaconazole delayed-release tablets should be used instead of Noxafil oral suspension for the prophylaxis indication.
Posaconazole delayed-release tablets generally provide higher plasma drug exposures than Noxafil oral suspension under both fed and fasted conditions, and therefore is the preferred oral formulation for the prophylaxis indication.
2.2Recommended Dosage of Posaconazole Delayed-Release Tablets in Adult Patients The recommended dosage of posaconazole delayed-release tablets in adult patients for the prophylaxis of invasive Aspergillus and Candida infections in patients who are at high risk of developing these infections due to being severely immunocompromised is shown in Table 1 [see Dosage and Administration (2.7 , 2.9) and Clinical Pharmacology (12.3) ] . Table 1: Recommended Dosage of Posaconazole Delayed-Release Tablets in Adult Patients Dosage Duration of Therapy Prophylaxis of Invasive Aspergillus and Candida Infections Posaconazole Delayed-Release Tablets: Loading dose: 300 mg (three 100 mg delayed-release tablets) twice a day on the first day.
Maintenance dose: 300 mg (three 100 mg delayed-release tablets) once a day, starting on the second day. Loading dose: 1 day Maintenance dose: Duration of therapy is based on recovery from neutropenia or immunosuppression
2.3Recommended Dosage of Posaconazole Delayed-Release Tablets for the Prophylaxis of Invasive Aspergillus and Candida Infections in Pediatric Patients 2 Years of Age and Older Posaconazole delayed-release tablets The recommended dosa… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Posaconazole Delayed-Release Tablets Posaconazole delayed-release tablets are available as yellow, oblong, film coated, unscored tablets, debossed with "AC71" on one side and plain on other side containing 100 mg of posaconazole. Posaconazole delayed-release tablet: 100 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Known hypersensitivity to posaconazole or other azole antifungal agents. (4.1) Co-administration of posaconazole with the following drugs is contraindicated; posaconazole increases concentrations and toxicities of: Sirolimus (4.2 , 7.2) CYP3A4 substrates (pimozide, quinidine): can result in QTc interval prolongation and cases of torsades de pointes (TdP) (4.3 , 5.2 , 7.2) HMG-CoA Reductase Inhibitors Primarily Metabolized through CYP3A4 (4.4 , 7.2) Ergot alkaloids (4.5 , 7.2) Venetoclax: In patients with chronic lymphocytic leukemia (CLL) or small lymphocytic lymphoma (SLL) at initiation and during the ramp-up phase (4.6 , 5.11 , 7.2)
4.1Hypersensitivity Posaconazole delayed-release tablets are contraindicated in persons with known hypersensitivity to posaconazole or other azole antifungal agents.
4.2Use with Sirolimus Posaconazole is contraindicated with sirolimus. Concomitant administration of posaconazole with sirolimus increases the sirolimus blood concentrations by approximately 9-fold and can result in sirolimus toxicity [see Drug Interactions (7.2) and Clinical Pharmacology (12.3) ] .
4.3QT Prolongation with Concomitant Use with CYP3A4 Substrates Posaconazole is contraindicated with CYP3A4 substrates that prolong the QT interval. Concomitant administration of posaconazole with the CYP3A4 substrates, pimozide and quinidine may result in increased plasma concentrations of these drugs, leading to QTc prolongation and cases of torsades de pointes [see Warnings and Precautions (5.2) and Drug Interactions (7.2) ] .
4.4HMG-CoA Reductase Inhibitors Primarily Metabolized Through CYP3A4 Co-administration with the HMG-CoA reductase inhibitors that are primarily metabolized through CYP3A4 (e.g., atorvastatin, lovastatin, and simvastatin) is contraindicated since increased plasma concentration of these drugs can lead to rhabdomyolysis [see Drug Interactions (7.2) and Clinical Pharmacology (12.3) ] .
4.5Use with Ergot Alkaloids Posaconazole may increase the plasma concentrations of ergot alkaloids (ergotamine and dihydroergotamine) which may lead to ergotism [see Drug Interactions (7.2) ] .
4.6Use with Venetoclax Co-administration of posaconazole with venetoclax at initiation and during the ramp-up phase is contraindicated in patients with chronic lymphocytic leukemia (CLL) or small lymphocytic lymphoma (SLL) due to the potential for increased risk of tumor lysis syndrome [see Warnings and Precautions (5.11) and Drug Interactions (7.2) ] .
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Calcineurin-Inhibitor Toxicity: Posaconazole increases concentrations of cyclosporine or tacrolimus; reduce dose of cyclosporine and tacrolimus and monitor concentrations frequently. (5.1) Arrhythmias and QTc Prolongation: Posaconazole has been shown to prolong the QTc interval and cause cases of TdP. Administer with caution to patients with potentially proarrhythmic conditions.
Do not administer with drugs known to prolong QTc interval and metabolized through CYP3A4. (5.2 , 7.2) Electrolyte Disturbances: Monitor and correct, especially those involving potassium (K + ), magnesium (Mg ++ ), and calcium (Ca ++ ), before and during posaconazole therapy. (5.3) Pseudoaldosteronism: Manifested by the onset or worsening of hypertension, and abnormal laboratory findings.
Monitor blood pressure and potassium levels, and manage as necessary. (5.4) Hepatic Toxicity: Elevations in liver tests may occur. Discontinuation should be considered in patients who develop abnormal liver tests or monitor liver tests during treatment.
(5.5) Concomitant Use with Midazolam: Posaconazole can prolong hypnotic/sedative effects. Monitor patients and benzodiazepine receptor antagonists should be available. (5.7 , 7.2) Vincristine Toxicity: Concomitant administration of azole antifungals, including posaconazole, with vincristine has been associated with neurotoxicity and other serious adverse reactions; reserve azole antifungals, including posaconazole, for patients receiving a vinca alkaloid, including vincristine, who have no alternative antifungal treatment options.
(5.8 , 7.2) Breakthrough Fungal Infections: Monitor patients with severe diarrhea or vomiting when receiving posaconazole delayed-release tablets. (5.10) Venetoclax Toxicity: Concomitant administration of posaconazole with venetoclax may increase venetoclax toxicities, including the risk of tumor lysis syndrome, neutropenia, and serious infections; monitor for toxicity and reduce venetoclax dose. (4.6 , 5.11 , 7.2)
5.1Calcineurin-Inhibitor Toxicity Concomitant administration of posaconazole with cyclosporine or tacrolimus increases the whole blood trough concentrations of these calcineurin-inhibitors [see Drug Interactions (7.2) and Clinical Pharmacology (12.3) ] . Nephrotoxicity and leukoencephalopathy (including deaths) have been reported in clinical efficacy studies in patients with elevated cyclosporine or tacrolimus concentrations. Frequent monitoring of tacrolimus or cyclosporine whole blood trough concentrations should be performed during and at discontinuation of posaconazole treatment and the tacrolimus or cyclosporine dose adjusted accordingly.
5.2Arrhythmias and QT Prolongation Some azoles, including posaconazole, have been associated with prolongation of the QT interval on the electrocardiogram. In addition, cases of torsades de pointes have been reported in patients taking posaconazole. Results from a multiple time-matched ECG analysis in healthy volunteers did not show any increase in the mean of the QTc interval.
Multiple, time-matched ECGs collected over a 12-hour period were recorded at baseline and steady-state from 173 healthy male and female volunteers (18 to 85 years of age) administered Noxafil oral suspension 400 mg twice daily with a high-fat meal. In this pooled analysis, the mean QTc (Fridericia) interval change from baseline was –5 msec following administration of the recommended clinical dose. A decrease in the QTc(F) interval (–3 msec) was also observed in a small number of subjects (n=16) administered placebo.
The placebo-adjusted mean maximum QTc(F) interval change from baseline was <0 msec (–8 msec). No healthy subject administered posaconazole had a QTc(F) interval ≥500 msec or an increase ≥60 msec in their QTc(F) interval from baseline. Posaconazole should be administered with caution to patients with potentially proarrhythmic conditions.
Do not administer with drugs that are known to prolong the QTc interval and are metabolized t… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious and otherwise important adverse reactions are discussed in detail in another section of the labeling: Arrhythmias and QT Prolongation [see Warnings and Precautions (5.2) ] Electrolyte Disturbances [see Warnings and Precautions (5.3) ] Pseudoaldosteronism [see Warnings and Precautions (5.4) ] Hepatic Toxicity [see Warnings and Precautions (5.5) ] Adult Patients: Common adverse reactions in studies with posaconazole in adults are diarrhea, nausea, fever, vomiting, headache, coughing, and hypokalemia.
(6.1) To report SUSPECTED ADVERSE REACTIONS, contact Amneal Pharmaceuticals LLC at 1-877-835-5472 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1CLINICAL TRIALS EXPERIENCE Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in clinical trials of posaconazole cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Clinical Trial Experience with Posaconazole Delayed-Release Tablets for Prophylaxis of Invasive Aspergillus and Candida Infections The safety of posaconazole delayed-release tablets has been assessed in 230 patients in clinical trials.
Patients were enrolled in a non-comparative pharmacokinetic and safety trial of posaconazole delayed-release tablets when given as antifungal prophylaxis (Posaconazole Delayed-Release Tablet Study). Patients were immunocompromised with underlying conditions including hematological malignancy, neutropenia post-chemotherapy, GVHD, and post HSCT. This patient population was 62% male, had a mean age of 51 years (range 19 to 78 years, 17% of patients were ≥65 years of age), and were 93% White and 16% Hispanic.
Posaconazole delayed-release tablets were given for a median duration of 28 days. In this study, 20 adult patients received 200 mg daily dosage (this is not a recommended dosage [see Dosage and Administration (2.2) ] ) and 210 adult patients received 300 mg daily dosage (following twice daily dosing on Day 1 in each cohort). Table 9 presents adverse reactions (incidence of ≥10%) observed in patients treated with the posaconazole delayed-release tablets 300 mg daily dosage in the Posaconazole Delayed-Release Tablet Study.
The most frequently reported adverse reactions (>25%) in patients treated with posaconazole delayed-release tablets 300 mg once daily were diarrhea, pyrexia, and nausea. The most common adverse reaction leading to discontinuation of posaconazole delayed-release tablets 300 mg once daily was nausea (2%). Table 9: Adverse Reactions in at least 10% of Adults Receiving Posaconazole Delayed-Release Tablets (300 mg Daily Dosage) for the Prophylaxis of Invasive Aspergillus and Candida infections Adverse Reactions Posaconazole delayed-release tablet (300 mg) n=210 (%) Percentage of Patients Reporting any Adverse Reaction 99 Diarrhea 29 Pyrexia 28 Nausea 27 Hypokalemia 22 Cough 17 Edema Peripheral 16 Rash 16 Epistaxis 14 Headache 14 Mucosal Inflammation 14 Thrombocytopenia 14 Vomiting 13 Abdominal Pain 11 Hypertension 11 Anemia 10 Asthenia 10 Chills 10 Constipation 10 Hypomagnesemia 10 Additional Adverse Reactions Reported in Less Than 5% of Posaconazole-Treated Patients in Clinical Trials Other clinically significant adverse reactions reported in less than 5% of patients in clinical trials of posaconazole are listed below: Blood and lymphatic system disorders: hemolytic uremic syndrome, thrombotic thrombocytopenic purpura, neutropenia aggravated Endocrine disorders: adrenal insufficiency Nervous system disorders: paresthesia Immune system disorders: allergic reaction [see Contraindications (4.1) ] Cardiac disorders: torsades de pointes [see Warnings and Precautions (5.2) ] Vascular disorders: pulmonary embolism Gastrointestinal disorders: pancreatitis Liver and Biliary System Disorders: hepatic enzymes increased, hepatic function abnormal, hepatitis, hepatomegaly, jaundice Renal & Urinary System Disorders: renal f… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 15 and Table 17 include drugs with clinically important drug interactions when administered concomitantly with posaconazole and Noxafil PowderMix and instructions for preventing or managing them. These recommendations are based on either drug interaction studies or predicted interactions due to the expected magnitude of interaction and potential for serious adverse reactions or loss of efficacy [see Clinical Pharmacology (12.3) ] . The following information was derived from data with Noxafil oral suspension or another posaconazole tablet formulation unless otherwise noted.
All clinically important drug interactions with Noxafil oral suspension, except for those that affect the absorption of posaconazole (via gastric pH and motility), are considered relevant to clinically important drug interactions with Noxafil injection, posaconazole delayed-release tablets, and Noxafil PowderMix for delayed-release oral suspension [ Clinical Pharmacology (12.3) ] . Consult the labeling of concomitantly used drugs to obtain further information about interactions with posaconazole. Interaction Drug Interaction Rifabutin, phenytoin, efavirenz, cimetidine, esomeprazole* Avoid co-administration unless the benefit outweighs the risks (7.1 , 7.2) Other drugs metabolized by CYP3A4 Consider dosage adjustment and monitor for adverse effects and toxicity (7.2) Digoxin Monitor digoxin plasma concentrations (7.2) Fosamprenavir, metoclopramide* Monitor for breakthrough fungal infections (7.1) *The drug interactions with esomeprazole and metoclopramide do not apply to posaconazole tablets (7.3 , 12.3 ).
7.1Effects of Other Drugs on Posaconazole and Noxafil PowderMix Posaconazole is primarily metabolized via UDP-glucuronosyltransferase and is a substrate of p-glycoprotein (P-gp) efflux. Therefore, inhibitors or inducers of these clearance pathways may affect posaconazole plasma concentrations. Concomitant use of posaconazole with drugs that can decrease the plasma posaconazole concentrations should generally be avoided unless the benefit outweighs the risk.
If such drugs are necessary, patients should be monitored closely for breakthrough fungal infections. Table 15: Drug Interactions Affecting Posaconazole and Noxafil PowderMix When Administered Concomitantly with Other Drugs UDP-Glucuronidase Inducers Mechanism and Clinical Effect(s) Posaconazole is a UDP-glucuronosyltransferase substrate. Concomitant use of posaconazole with UDP-glucuronidase inducers may decrease posaconazole exposure [see Clinical Pharmacology (12.3) ] , which may reduce the effectiveness of posaconazole.
Prevention or Management Efavirenz Avoid concomitant use of posaconazole with efavirenz, unless the benefit outweighs the risks. Rifabutin Avoid concomitant use of posaconazole with rifabutin unless the benefit to the patient outweighs the risk. If concomitant use is needed, monitor closely for breakthrough fungal infections.
See Table 17 for rifabutin monitoring considerations when posaconazole affects rifabutin via CYP3A4 inhibition. Phenytoin Avoid concomitant use of posaconazole with phenytoin unless the benefit to the patient outweighs the risk. If concomitant use is needed, monitor for breakthrough fungal infections.
See Table 17 for phenytoin monitoring considerations when posaconazole affects phenytoin via CYP3A4 inhibition. Fosamprenavir Mechanism and Clinical Effect(s) Concomitant use of posaconazole with fosamprenavir may lead to decreased posaconazole plasma concentrations [see Clinical Pharmacology (12.3) ] , which may reduce effectiveness of posaconazole. Prevention or Management If concomitant use of posaconazole with fosamprenavir is needed, monitor closely for breakthrough fungal infections.
7.2Effects of Posaconazole and Noxafil PowderMix on Other Drugs Posaconazole is a strong CYP3A4 inhibitor. Therefore, concomitant use of posaconazole may increase plasma concentrations of drugs that are CYP3A4 substrates [see Clinical Pharmacology (12.… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause fetal harm. (8.1) Pediatrics: Safety and effectiveness in patients younger than 2 years of age have not been established. (8.4) Severe Renal Impairment: Monitor closely for breakthrough fungal infections.
(8.6) Additional Pediatric Use information is approved for Merck Sharp & Dohme Corp.’s NOXAFIL (posaconazole) delayed-release tablets. However, due to Merck Sharp & Dohme Corp.’s marketing exclusivity rights, this drug product is not labeled with that pediatric information.
8.1Pregnancy Risk Summary Based on findings from animal data, posaconazole may cause fetal harm when administered to pregnant women. Available data for use of posaconazole in pregnant women are insufficient to establish a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies, skeletal malformations were observed when posaconazole was dosed orally to pregnant rats during organogenesis at doses ≥1.4 times the 400 mg twice daily oral suspension regimen based on steady-state plasma concentrations of posaconazole in healthy volunteers.
In pregnant rabbits dosed orally during organogenesis, doses of ≥ 3 times the clinical exposure caused an increase in resorptions (see Data ) . Based on animal data, advise pregnant women of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data: Posaconazole resulted in maternal toxicity (reduced food consumption and reduced body weight gain) and skeletal malformations (cranial malformations and missing ribs) when given orally to pregnant rats during organogenesis (Gestational Days 6 through 15) at doses ≥27 mg/kg (≥1.4 times the 400 mg twice daily oral suspension regimen based on steady-state plasma concentrations of drug in healthy volunteers).
The no-effect dose for malformations and maternal toxicity in rats was 9 mg/kg, which is 0.7 times the exposure achieved with the 400 mg twice daily oral suspension regimen. No malformations were seen in rabbits dosed during organogenesis (Gestational Days 7 through 19) at doses up to 80 mg/kg (5 times the exposure achieved with the 400 mg twice daily oral suspension regimen). In the rabbit, the no-effect dose was 20 mg/kg, while high doses of 40 mg/kg and 80 mg/kg (3 or 5 times the clinical exposure) caused an increase in resorptions.
In rabbits dosed at 80 mg/kg, a reduction in body weight gain of females and a reduction in litter size were seen.
8.2Lactation Risk Summary There are no data on the presence of posaconazole in human milk, the effects on the breastfed infant, or the effects on milk production. Posaconazole is excreted in the milk of lactating rats. When a drug is present in animal milk, it is likely that the drug will be present in human milk.
The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for posaconazole and any potential adverse effects on the breastfed child from posaconazole or from the underlying maternal condition.
8.4Pediatric Use The three posaconazole dosage forms (injection, delayed-release tablets, oral suspension) and one Noxafil PowderMix (for delayed-release oral suspension) dosage form are different products; are approved for different pediatric indications, age groups, and weights; have different dosing regimens; and have different preparation and administration instructions. Therefore, select the recommended dosage form based on the pediatric indication, age group, and weight [see Dosage and Administration (2.1) ] .
Prophylaxis of Invasive Aspergillus and Candida Infections T… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings from animal data, posaconazole may cause fetal harm when administered to pregnant women. Available data for use of posaconazole in pregnant women are insufficient to establish a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. In animal reproduction studies, skeletal malformations were observed when posaconazole was dosed orally to pregnant rats during organogenesis at doses ≥1.4 times the 400 mg twice daily oral suspension regimen based on steady-state plasma concentrations of posaconazole in healthy volunteers.
In pregnant rabbits dosed orally during organogenesis, doses of ≥ 3 times the clinical exposure caused an increase in resorptions (see Data ) . Based on animal data, advise pregnant women of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data: Posaconazole resulted in maternal toxicity (reduced food consumption and reduced body weight gain) and skeletal malformations (cranial malformations and missing ribs) when given orally to pregnant rats during organogenesis (Gestational Days 6 through 15) at doses ≥27 mg/kg (≥1.4 times the 400 mg twice daily oral suspension regimen based on steady-state plasma concentrations of drug in healthy volunteers).
The no-effect dose for malformations and maternal toxicity in rats was 9 mg/kg, which is 0.7 times the exposure achieved with the 400 mg twice daily oral suspension regimen. No malformations were seen in rabbits dosed during organogenesis (Gestational Days 7 through 19) at doses up to 80 mg/kg (5 times the exposure achieved with the 400 mg twice daily oral suspension regimen). In the rabbit, the no-effect dose was 20 mg/kg, while high doses of 40 mg/kg and 80 mg/kg (3 or 5 times the clinical exposure) caused an increase in resorptions.
In rabbits dosed at 80 mg/kg, a reduction in body weight gain of females and a reduction in litter size were seen.
🧒 Pediatric Use ▾
8.4Pediatric Use The three posaconazole dosage forms (injection, delayed-release tablets, oral suspension) and one Noxafil PowderMix (for delayed-release oral suspension) dosage form are different products; are approved for different pediatric indications, age groups, and weights; have different dosing regimens; and have different preparation and administration instructions. Therefore, select the recommended dosage form based on the pediatric indication, age group, and weight [see Dosage and Administration (2.1) ] .
Prophylaxis of Invasive Aspergillus and Candida Infections The safety and effectiveness of posaconazole delayed-release tablets have been established for the prophylaxis of invasive Aspergillus and Candida infections in pediatric patients 2 years of age and older who are at high risk of developing these infections due to being severely immunocompromised. Use of posaconazole for these pediatric indications is supported by adequate and well controlled studies of posaconazole in adults and pediatric patients aged 2 years of age and older and additional PK and safety data in pediatric patients 2 years of age and older [see Clinical Pharmacology (12.3) and Clinical studies (14) ] .
The safety and effectiveness of posaconazole have not been established in pediatric patients less than 2 years of age. Additional Pediatric Use information is approved for Merck Sharp & Dohme Corp.’s NOXAFIL (posaconazole) delayed-release tablets. However, due to Merck Sharp & Dohme Corp.’s marketing exclusivity rights, this drug product is not labeled with that pediatric information.
🧓 Geriatric Use ▾
8.5Geriatric Use No overall differences in the safety or effectiveness of posaconazole delayed-release tablets have been observed between geriatric patients and younger adult patients in the clinical trials; therefore, the recommended dosage in geriatric patients is the same as that for younger adult patients. No clinically meaningful differences in posaconazole pharmacokinetics were observed in posaconazole-treated geriatric patients compared to posaconazole-treated younger adult patients during clinical trials [see Clinical Pharmacology (12.3) ] .
Of the 230 patients treated with posaconazole delayed-release tablets, 38 (17%) patients were >65 years of age.
🆘 Overdosage ▾
10 OVERDOSAGE There is no experience with overdosage of posaconazole delayed-release tablets. During the clinical trials, some patients received Noxafil oral suspension up to 1,600 mg/day with no adverse reactions noted that were different from the lower doses. In addition, accidental overdose was noted in one patient who took 1200 mg twice daily Noxafil oral suspension for 3 days.
No related adverse reactions were noted by the investigator. Posaconazole is not removed by hemodialysis.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Posaconazole is an azole antifungal agent [see Clinical Pharmacology (12.4) ] .
12.2Pharmacodynamics Exposure Response Relationship: Prophylaxis of invasive Aspergillus and Candida Infections in Adults Who Are at High Risk of Developing These Infections Due to Being Severely Immunocompromised In clinical studies of neutropenic patients who were receiving cytotoxic chemotherapy for acute myelogenous leukemia (AML) or myelodysplastic syndromes (MDS) or hematopoietic stem cell transplant (HSCT) recipients with Graft versus Host Disease (GVHD), a wide range of plasma posaconazole exposures was noted following administration of Noxafil oral suspension.
A pharmacokinetic-pharmacodynamic analysis of patient data revealed an apparent association between average posaconazole concentrations (Cavg) and prophylactic efficacy (Table 18). A lower Cavg may be associated with an increased risk of treatment failure, defined as treatment discontinuation, use of empiric systemic antifungal therapy (SAF), or occurrence of breakthrough invasive fungal infections. Table 18: Noxafil Oral Suspension Exposure Analysis (Cavg) in Prophylaxis Trials Prophylaxis in AML/MDS* Prophylaxis in GVHD † Cavg Range (ng/mL) Treatment Failure‡ (%) Cavg Range (ng/mL) Treatment Failure ‡ (%) Quartile 1 90 to 322 54.7 22 to 557
44.4Quartile 2 322 to 490 37.0 557 to 915
20.6Quartile 3 490 to 734 46.8 915 to 1563
17.5Quartile 4 734 to 2200 27.8 1563 to 3650
17.5Cavg = the average posaconazole concentration when measured at steady-state * Neutropenic patients who were receiving cytotoxic chemotherapy for AML or MDS † HSCT recipients with GVHD ‡ Defined as treatment discontinuation, use of empiric systemic antifungal therapy (SAF), or occurrence of breakthrough invasive fungal infections
12.3Pharmacokinetics General Pharmacokinetic Characteristics General Pharmacokinetic Characteristics of Posaconazole Delayed-Release Tablets Posaconazole delayed-release tablets exhibit dose proportional pharmacokinetics after single and multiple dosing up to 300 mg. The mean pharmacokinetic parameters of posaconazole at steady-state following administration of posaconazole delayed-release tablets 300 mg twice daily on Day 1, then 300 mg once daily thereafter in healthy volunteers and in neutropenic patients who are receiving cytotoxic chemotherapy for AML or MDS or HSCT recipients with GVHD are shown in Table 21 .
Table 21: Arithmetic Mean (%CV) of Steady-State PK Parameters in Healthy Volunteers and Patients Following Administration of Posaconazole Delayed-Release Tablets (300 mg)* N AUC 0-24 hr (ng·hr/mL) Cav † (ng/mL) C max (ng/mL) C min (ng/mL) ‡ T max (hr) t 1/2 (hr) CL/F (L/hr) Healthy Volunteers 12 51618 (25) 2151 (25) 2764 (21) 1785 (29) 4 (3 to 6) 31 (40) 7.5 (26) Patients 50 37900 (42) 1580 (42) 2090 (38) 1310 (50) 4 (1.38.3) - 9.39 (45) CV = coefficient of variation expressed as a percentage (%CV); AUC 0-T = Area under the plasma concentration-time curve from time zero to 24 hr; C max = maximum observed concentration; C min = minimum observed plasma concentration; T max = time of maximum observed concentration; t ½ = terminal phase half-life; CL/F = Apparent total body clearance * 300 mg twice daily on Day 1, then 300 mg once daily thereafter † Cav = time-averaged concentrations (i.e., AUC 0-24 hr/24 hr ) ‡ Median (minimum-maximum) Absorption: Absorption of Posaconazole Delayed-Release Tablets When given orally in healthy volunteers, posaconazole delayed-release tablets are absorbed with a median T max of 4 to 5 hours.
Steady-state plasma concentrations are attained by Day 6 at the 300 mg dose (once daily after twice daily loading dose at Day 1). The absolute bioavailability of the oral delayed-release tablet is approximately 54% under fasted conditions. The C max and AUC of posaconazole following administration of posaconazole delayed-release tablets are increased 16% and 51%, respectively, when given with a high… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Posaconazole is an azole antifungal agent [see Clinical Pharmacology (12.4) ] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Posaconazole Delayed-Release Tablets Posaconazole delayed-release tablets 100 mg are available as yellow, oblong, film coated, unscored tablets, debossed with "AC71" on one side and plain on other side. They are supplied as follows: Bottles of 30 with child-resistant closure: NDC 69238-1476-3. Bottles of 60 with child-resistant closure: NDC 69238-1476-6.
16.2Storage and Handling Posaconazole Delayed-Release Tablets Store at 20 to 25°C (68 to 77°F), excursions permitted between 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
16.1How Supplied Posaconazole Delayed-Release Tablets Posaconazole delayed-release tablets 100 mg are available as yellow, oblong, film coated, unscored tablets, debossed with "AC71" on one side and plain on other side. They are supplied as follows: Bottles of 30 with child-resistant closure: NDC 69238-1476-3. Bottles of 60 with child-resistant closure: NDC 69238-1476-6.
📦 Storage and Handling ▾
16.2Storage and Handling Posaconazole Delayed-Release Tablets Store at 20 to 25°C (68 to 77°F), excursions permitted between 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Posaconazole delayed-release tablets contain posaconazole, an azole antifungal agent. Posaconazole is designated chemically as 4-[4-[4-[4-[[ (3R,5R)-5-(2,4-difluorophenyl)tetrahydro-5(1 H -1,2,4-triazol-1-ylmethyl)-3-furanyl]methoxy]phenyl]-1-piperazinyl]phenyl]-2-[(1 S ,2 S )-1-ethyl-2hydroxypropyl]-2,4-dihydro-3 H -1,2,4-triazol-3-one with an empirical formula of C 37 H 42 F 2 N 8 O 4 and a molecular weight of 700.8. The chemical structure is: Posaconazole is a white powder with a low aqueous solubility.
Posaconazole Delayed-Release Tablets Posaconazole delayed-release tablet, for oral use, are yellow, oblong, film coated, unscored tablets containing 100 mg of posaconazole. Each delayed-release tablet contains the inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, ferrosoferric oxide black, hydroxypropylcellulose, hypromellose acetate succinate, iron oxide yellow, Macrogol/PEG 3350, magnesium stearate, microcrystalline cellulose, polyvinyl alcohol partially hydrolyzed, talc and titanium dioxide.
Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information and Instructions for Use). Important Administration Instructions Posaconazole Delayed-Release Tablets Advise patients that posaconazole delayed-release tablets must be swallowed whole and not divided, crushed, or chewed. Instruct patients that if they miss a dose, they should take it as soon as they remember.
If they do not remember until it is within 12 hours of the next dose, they should be instructed to skip the missed dose and go back to the regular schedule. Patients should not double their next dose or take more than the prescribed dose. Drug Interactions Advise patients to inform their physician immediately if they: develop severe diarrhea or vomiting. are currently taking drugs that are known to prolong the QTc interval and are metabolized through CYP3A4. are currently taking a cyclosporine or tacrolimus, or they notice swelling in an arm or leg or shortness of breath. are taking other drugs or before they begin taking other drugs as certain drugs can decrease or increase the plasma concentrations of posaconazole.
Serious and Potentially Serious Adverse Reactions Advise patients to inform their physician immediately if they: ·notice a change in heart rate or heart rhythm or have a heart condition or circulatory disease. Posaconazole can be administered with caution to patients with potentially proarrhythmic conditions. are pregnant, plan to become pregnant, or are nursing. have liver disease or develop itching, nausea or vomiting, their eyes or skin turn yellow, they feel more tired than usual or feel like they have the flu. have ever had an allergic reaction to other antifungal medicines such as ketoconazole, fluconazole, itraconazole, or voriconazole.
The trademarks referenced herein are owned by their respective companies. Distributed by: Amneal Pharmaceuticals LLC Bridgewater, NJ 08807 Rev. 03-2026-03
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics General Pharmacokinetic Characteristics General Pharmacokinetic Characteristics of Posaconazole Delayed-Release Tablets Posaconazole delayed-release tablets exhibit dose proportional pharmacokinetics after single and multiple dosing up to 300 mg. The mean pharmacokinetic parameters of posaconazole at steady-state following administration of posaconazole delayed-release tablets 300 mg twice daily on Day 1, then 300 mg once daily thereafter in healthy volunteers and in neutropenic patients who are receiving cytotoxic chemotherapy for AML or MDS or HSCT recipients with GVHD are shown in Table 21 .
Table 21: Arithmetic Mean (%CV) of Steady-State PK Parameters in Healthy Volunteers and Patients Following Administration of Posaconazole Delayed-Release Tablets (300 mg)* N AUC 0-24 hr (ng·hr/mL) Cav † (ng/mL) C max (ng/mL) C min (ng/mL) ‡ T max (hr) t 1/2 (hr) CL/F (L/hr) Healthy Volunteers 12 51618 (25) 2151 (25) 2764 (21) 1785 (29) 4 (3 to 6) 31 (40) 7.5 (26) Patients 50 37900 (42) 1580 (42) 2090 (38) 1310 (50) 4 (1.38.3) - 9.39 (45) CV = coefficient of variation expressed as a percentage (%CV); AUC 0-T = Area under the plasma concentration-time curve from time zero to 24 hr; C max = maximum observed concentration; C min = minimum observed plasma concentration; T max = time of maximum observed concentration; t ½ = terminal phase half-life; CL/F = Apparent total body clearance * 300 mg twice daily on Day 1, then 300 mg once daily thereafter † Cav = time-averaged concentrations (i.e., AUC 0-24 hr/24 hr ) ‡ Median (minimum-maximum) Absorption: Absorption of Posaconazole Delayed-Release Tablets When given orally in healthy volunteers, posaconazole delayed-release tablets are absorbed with a median T max of 4 to 5 hours.
Steady-state plasma concentrations are attained by Day 6 at the 300 mg dose (once daily after twice daily loading dose at Day 1). The absolute bioavailability of the oral delayed-release tablet is approximately 54% under fasted conditions. The C max and AUC of posaconazole following administration of posaconazole delayed-release tablets are increased 16% and 51%, respectively, when given with a high fat meal compared to a fasted state (see Table 23 ).
Table 23: Statistical Comparison of Plasma Pharmacokinetics of Posaconazole Following Single Oral Dose Administration of 300 mg Posaconazole Delayed-Release Tablet to Healthy Subjects under Fasting and Fed Conditions Fasting Conditions Fed Conditions (High Fat Meal)* Fed/Fasting Pharmacokinetic Parameter N Mean (%CV) N Mean (%CV) GMR (90% CI) C max (ng/mL) 14 935 (34) 16 1060 (25) 1.16 (0.96, 1.41) AUC 0-72hr (hr∙ng/mL) 14 26200 (28) 16 38400 (18) 1.51 (1.33, 1.72) T max † (hr) 14 5.00 (3.00, 8.00) 16 6.00 (5.00, 24.00) N/A GMR=Geometric least-squares mean ratio; CI=Confidence interval * 48.5 g fat † Median (Min, Max) reported for T max Distribution: The mean volume of distribution of posaconazole after intravenous solution administration was 261 L and ranged from 226 to 295 L between studies and dose levels.
Posaconazole is highly bound to human plasma proteins (>98%), predominantly to albumin. Metabolism: Posaconazole primarily circulates as the parent compound in plasma. Of the circulating metabolites, the majority are glucuronide conjugates formed via UDP glucuronidation (phase 2 enzymes).
Posaconazole does not have any major circulating oxidative (CYP450 mediated) metabolites. The excreted metabolites in urine and feces account for ~17% of the administered radiolabeled dose. Posaconazole is a substrate for p-glycoprotein (P-gp) efflux.
In vitro studies with human hepatic microsomes and clinical studies indicate that posaconazole is an inhibitor primarily of CYP3A4. Excretion: Following administration of Noxafil oral suspension, posaconazole is predominantly eliminated in the feces (71% of the radiolabeled dose up to 120 hours) with the major component eliminated as parent drug (66% of the radiolabeled dose). Renal clearance is a minor elim… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Exposure Response Relationship: Prophylaxis of invasive Aspergillus and Candida Infections in Adults Who Are at High Risk of Developing These Infections Due to Being Severely Immunocompromised In clinical studies of neutropenic patients who were receiving cytotoxic chemotherapy for acute myelogenous leukemia (AML) or myelodysplastic syndromes (MDS) or hematopoietic stem cell transplant (HSCT) recipients with Graft versus Host Disease (GVHD), a wide range of plasma posaconazole exposures was noted following administration of Noxafil oral suspension.
A pharmacokinetic-pharmacodynamic analysis of patient data revealed an apparent association between average posaconazole concentrations (Cavg) and prophylactic efficacy (Table 18). A lower Cavg may be associated with an increased risk of treatment failure, defined as treatment discontinuation, use of empiric systemic antifungal therapy (SAF), or occurrence of breakthrough invasive fungal infections. Table 18: Noxafil Oral Suspension Exposure Analysis (Cavg) in Prophylaxis Trials Prophylaxis in AML/MDS* Prophylaxis in GVHD † Cavg Range (ng/mL) Treatment Failure‡ (%) Cavg Range (ng/mL) Treatment Failure ‡ (%) Quartile 1 90 to 322 54.7 22 to 557
44.4Quartile 2 322 to 490 37.0 557 to 915
20.6Quartile 3 490 to 734 46.8 915 to 1563
17.5Quartile 4 734 to 2200 27.8 1563 to 3650
17.5Cavg = the average posaconazole concentration when measured at steady-state * Neutropenic patients who were receiving cytotoxic chemotherapy for AML or MDS † HSCT recipients with GVHD ‡ Defined as treatment discontinuation, use of empiric systemic antifungal therapy (SAF), or occurrence of breakthrough invasive fungal infections
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.2Prophylaxis of Aspergillus and Candida Infections with Noxafil Oral Suspension Two randomized, controlled studies were conducted using posaconazole as prophylaxis for the prevention of invasive fungal infections (IFIs) among patients at high risk due to severely compromised immune systems. The first study (Noxafil Oral Suspension Study 1) was a randomized, double-blind trial that compared Noxafil oral suspension (200 mg three times a day) with fluconazole capsules (400 mg once daily) as prophylaxis against invasive fungal infections in allogeneic hematopoietic stem cell transplant (HSCT) recipients with Graft versus Host Disease (GVHD).
Efficacy of prophylaxis was evaluated using a composite endpoint of proven/probable IFIs, death, or treatment with systemic antifungal therapy (patients may have met more than one of these criteria). This assessed all patients while on study therapy plus 7 days and at 16 weeks post-randomization. The mean duration of therapy was comparable between the 2 treatment groups (80 days, Noxafil oral suspension; 77 days, fluconazole).
Table 34 contains the results from Noxafil Oral Suspension Study 1. Table 34: Results from Blinded Clinical Study in Prophylaxis of IFI in All Randomized Patients with Hematopoietic Stem Cell Transplant (HSCT) and Graft-vs.-Host Disease (GVHD): Noxafil Oral Suspension Study 1 Posaconazole n=301 Fluconazole n=299 On therapy plus 7 days Clinical Failure* 50 (17%) 55 (18%) Failure due to: Proven/Probable IFI 7 (2%) 22 (7%) (Aspergillus) 3 (1%) 17 (6%) (Candida) 1 (<1%) 3 (1%) (Other) 3 (1%) 2 (1%) All Deaths 22 (7%) 24 (8%) Proven/probable fungal infection prior to death 2 (<1%) 6 (2%) SAF † 27 (9%) 25 (8%) Through 16 weeks Clinical Failure* ,‡ 99 (33%) 110 (37%) Failure due to: Proven/Probable IFI 16 (5%) 27 (9%) (Aspergillus) 7 (2%) 21 (7%) (Candida) 4 (1%) 4 (1%) (Other) 5 (2%) 2 (1%) All Deaths 58 (19%) 59 (20%) Proven/probable fungal infection prior to death 10 (3%) 16 (5%) SAF † 26 (9%) 30 (10%) Event free lost to follow-up § 24 (8%) 30 (10%) * Patients may have met more than one criterion defining failure. † Use of systemic antifungal therapy (SAF) criterion is based on protocol definitions (empiric/IFI usage >4 consecutive days). ‡ 95% confidence interval (posaconazole-fluconazole) = (-11.5%,+3.7%). § Patients who are lost to follow-up (not observed for 112 days), and who did not meet another clinical failure endpoint.
These patients were considered failures. The second study (Noxafil Oral Suspension Study 2) was a randomized, open-label study that compared Noxafil oral suspension (200 mg 3 times a day) with fluconazole suspension (400 mg once daily) or itraconazole oral solution (200 mg twice a day) as prophylaxis against IFIs in neutropenic patients who were receiving cytotoxic chemotherapy for AML or MDS. As in Noxafil Oral Suspension Study 1, efficacy of prophylaxis was evaluated using a composite endpoint of proven/probable IFIs, death, or treatment with systemic antifungal therapy (Patients might have met more than one of these criteria).
This study assessed patients while on treatment plus 7 days and 100 days post-randomization. The mean duration of therapy was comparable between the 2 treatment groups (29 days, posaconazole; 25 days, fluconazole or itraconazole). Table 35 contains the results from Noxafil Oral Suspension Study 2.
Table 35: Results from Open-Label Clinical Study 2 in Prophylaxis of IFI in All Randomized Patients with Hematologic Malignancy and Prolonged Neutropenia: Noxafil Oral Suspension Study 2 Posaconazole n=304 Fluconazole/Itraconazole n=298 On therapy plus 7 days Clinical Failure* ,† 82 (27%) 126 (42%) Failure due to: Proven/Probable IFI 7 (2%) 25 (8%) (Aspergillus) 2 (1%) 20 (7%) (Candida) 3 (1%) 2 (1%) (Other) 2 (1%) 3 (1%) All Deaths 17 (6%) 25 (8%) Proven/probable fungal infection prior to death 1 (<1%) 2 (1%) SAF ‡ 67 (22%) 98 (33%) Through 100 days post-randomization Clinical Failure † 158 (52%) 191 (64%) F… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis No drug-related neoplasms were recorded in rats or mice treated with posaconazole for 2 years at doses higher than the clinical dose. In a 2 year carcinogenicity study, rats were given posaconazole orally at doses up to 20 mg/kg (females), or 30 mg/kg (males). These doses are equivalent to 3.9- or 3.5 times the exposure achieved with a 400 mg twice daily oral suspension regimen, respectively, based on steady-state AUC in healthy volunteers administered a high-fat meal (400 mg twice daily oral suspension regimen).
In the mouse study, mice were treated at oral doses up to 60 mg/kg/day or 4.8 times the exposure achieved with a 400 mg twice daily oral suspension regimen. Mutagenesis Posaconazole was not genotoxic or clastogenic when evaluated in bacterial mutagenicity (Ames), a chromosome aberration study in human peripheral blood lymphocytes, a Chinese hamster ovary cell mutagenicity study, and a mouse bone marrow micronucleus study. Impairment of Fertility Posaconazole had no effect on fertility of male rats at a dose up to 180 mg/kg (1.7 x the 400 mg twice daily oral suspension regimen based on steady-state plasma concentrations in healthy volunteers) or female rats at a dose up to 45 mg/kg (2.2 x the 400 mg twice daily oral suspension regimen).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis No drug-related neoplasms were recorded in rats or mice treated with posaconazole for 2 years at doses higher than the clinical dose. In a 2 year carcinogenicity study, rats were given posaconazole orally at doses up to 20 mg/kg (females), or 30 mg/kg (males). These doses are equivalent to 3.9- or 3.5 times the exposure achieved with a 400 mg twice daily oral suspension regimen, respectively, based on steady-state AUC in healthy volunteers administered a high-fat meal (400 mg twice daily oral suspension regimen).
In the mouse study, mice were treated at oral doses up to 60 mg/kg/day or 4.8 times the exposure achieved with a 400 mg twice daily oral suspension regimen. Mutagenesis Posaconazole was not genotoxic or clastogenic when evaluated in bacterial mutagenicity (Ames), a chromosome aberration study in human peripheral blood lymphocytes, a Chinese hamster ovary cell mutagenicity study, and a mouse bone marrow micronucleus study. Impairment of Fertility Posaconazole had no effect on fertility of male rats at a dose up to 180 mg/kg (1.7 x the 400 mg twice daily oral suspension regimen based on steady-state plasma concentrations in healthy volunteers) or female rats at a dose up to 45 mg/kg (2.2 x the 400 mg twice daily oral suspension regimen).
📄 Recent Major Changes ▾
RECENT MAJOR CHANGES Indications and Usage (1.2) 1/2026 Dosage and Administration (2) 1/2026
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL 30ct label
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |