
Clindamycin phosphate 300 mg/50mL Injection, Solution — NDC 0338-3410-24 (Billing 00338-3410-24)
This is a package of Clindamycin phosphate 300 mg/50mL Injection, Solution from Baxter Healthcare Company, marketed since Jun 2017 and currently FDA-listed. It is this product's only package size.
Other active recalls for Clindamycin Phosphate (different manufacturers) — 4 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 013052
- GCN: 40820
- GPI-14 (Medi-Span): 16220020312020
- HICL (First Databank): 004704
- AHFS class code: 08:12.28.20
- RxCUI (RxNorm): 309335
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Lincosamide Antibacterial class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats serious bacterial infections, such as anaerobic infections, skin, lung, abdominal, gynecological, and bone and joint infections, depending on the product. It is often use...
- Swallow them with a full glass of water and stay upright for at least 30 minutes afterward. This helps prevent irritation of your throat. Take it as often as your prescriber says a...
- Rash, nausea, vomiting, stomach pain and itching are among the more commonly reported effects. Call your doctor right away if you get severe, watery or bloody diarrhea, even weeks...
- What side effects are normal, and when should I call you?
Patient education
Supplement & herbal interactions
Clindamycin may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $0.0208 | $24.96 / 1200 ml |
| Medicare drug plans payPart D · Q2 2026 | $0.1430 | $171.60 / 1200 ml |
| Medicare Part B allowsASP · J0736 | $1.974 / J0736 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00338-3410-24 You're viewing this Main listing | 24 BAG in 1 CARTON / 50 mL in 1 BAG | 2017-06-28 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Clindamycin in 5 percent Dextrose 6 mg/mL 00143-9267-01 | Hikma | 1 vial | — | AP | FDA listed | — |
| Clindamycin phosphate 300 mg/50mLthis 00338-3410-24 | Baxter | 50 ml | — | AP | FDA listed | — |
| clindamycin phosphate 300 mg/50mL 00338-9545-24 | Baxter | 50 ml | — | — | FDA listed | — |
| Clindamycin in 5 Percent Dextrose 6 mg/mL 00781-3288-09 | Sandoz | 50 ml | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
2.50 g / 50 mL
UNII LX22YL083G
A simple sugar derived from corn or other sources. It acts as a filler to give the medicine bulk and volume, and as a sweetener to improve taste in oral medications.
-
2 mg / 50 mL
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING Clostridioides difficile -associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including Clindamycin Injection USP in 5% Dextrose and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile . Because Clindamycin Injection USP in 5% Dextrose therapy has been associated with severe colitis which may end fatally, it should be reserved for serious infections where less toxic antimicrobial agents are inappropriate, as described in the INDICATIONS AND USAGE section.
It should not be used in patients with nonbacterial infections such as most upper respiratory tract infections. C. difficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy.
CDAD must be considered in all patients who present with diarrhea following antibacterial drug use. Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents. If CDAD is suspected or confirmed, ongoing antibacterial drug use not directed against C. difficile may need to be discontinued.
Appropriate fluid and electrolyte management, protein supplementation, antibacterial drug treatment of C. difficile , and surgical evaluation should be instituted as clinically indicated.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Clindamycin Injection USP in 5% Dextrose products are indicated in the treatment of serious infections caused by susceptible anaerobic bacteria. Clindamycin Injection USP in 5% Dextrose products are also indicated in the treatment of serious infections due to susceptible strains of streptococci, pneumococci, and staphylococci. Its use should be reserved for penicillin-allergic patients or other patients for whom, in the judgment of the physician, a penicillin is inappropriate.
Because of the risk of antibacterial drug-associated pseudomembranous colitis, as described in the BOXED WARNING , before selecting clindamycin the physician should consider the nature of the infection and the suitability of less toxic alternatives (e.g., erythromycin). Bacteriologic studies should be performed to determine the causative organisms and their susceptibility to clindamycin. Indicated surgical procedures should be performed in conjunction with antibacterial drug therapy.
Clindamycin Injection USP in 5% Dextrose is indicated in the treatment of serious infections caused by susceptible strains of the designated organisms in the conditions listed below: Lower respiratory tract infections including pneumonia, empyema, and lung abscess caused by anaerobes, Streptococcus pneumoniae , other streptococci (except E. faecalis ), and Staphylococcus aureus . Skin and skin structure infections caused by Streptococcus pyogenes , Staphylococcus aureus , and anaerobes. Gynecological infections including endometritis, nongonococcal tubo-ovarian abscess, pelvic cellulitis, and postsurgical vaginal cuff infection caused by susceptible anaerobes.
Intra-abdominal infections including peritonitis and intra-abdominal abscess caused by susceptible anaerobic organisms. Septicemia caused by Staphylococcus aureus , streptococci (except Enterococcus faecalis ), and susceptible anaerobes. Bone and joint infections including acute hematogenous osteomyelitis caused by Staphylococcus aureus and as adjunctive therapy in the surgical treatment of chronic bone and joint infections due to susceptible organisms.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of Clindamycin Injection USP in 5% Dextrose and other antibacterial drugs, Clindamycin Injection USP in 5% Dextrose should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION If diarrhea occurs during therapy, this antibacterial drug should be discontinued (see WARNING box). Adults: Parenteral (Intravenous Administration): Serious infections due to aerobic gram-positive cocci and the more susceptible anaerobes (NOT generally including Bacteroides fragilis , Peptococcus species and Clostridium species other than Clostridium perfringens ): 600-1200 mg/day in 2, 3 or 4 equal doses. More severe infections, particularly those due to proven or suspected Bacteroides fragilis, Peptococcus species, or Clostridium species other than Clostridium perfringens : 1200-2700 mg/day in 2, 3 or 4 equal doses.
For more serious infections, these doses may have to be increased. In life-threatening situations due to either aerobes or anaerobes these doses may be increased. Doses of as much as 4800 mg daily have been given intravenously to adults.
See Dilution for Intravenous use and Intravenous Infusion Rates section below. Alternatively, drug may be administered in the form of a single rapid infusion of the first dose followed by continuous intravenous infusion as follows: Table 2: Serum Clindamycin Levels Maintained, Rapid Infusion Rate and Maintenance Infusion Rate To maintain serum clindamycin levels Rapid infusion rate Maintenance infusion rate Above 4 mcg/mL 10 mg/min for 30 min 0.75 mg/min Above 5 mcg/mL 15 mg/min for 30 min 1.00 mg/min Above 6 mcg/mL 20 mg/min for 30 min 1.25 mg/min Pediatric patients 1 month of age to 16 years: Parenteral (Intravenous) Administration: 20 to 40 mg/kg/day in 3 or 4 equal doses.
The higher doses would be used for more severe infections. Clindamycin should be dosed based on total body weight regardless of obesity. As an alternative to dosing on a body weight basis, pediatric patients may be dosed on the basis of square meters body surface: 350 mg/m 2 /day for serious infections and 450 mg/m 2 /day for more severe infections.
Parenteral therapy may be changed to oral clindamycin palmitate hydrochloride powder for oral solution or clindamycin hydrochloride capsules when the condition warrants and at the discretion of the physician. In cases of β-hemolytic streptococcal infections, treatment should be continued for at least 10 days. Pediatric Patients less than 1 month: The recommended dosage is 15 to 20 mg/kg/day in 3 to 4 equal doses.
See Table 3 regarding the dosing regimen for pediatric patients with post-menstrual age (PMA) less than or equal to 32 weeks, or greater than 32 weeks to less than or equal to 40 weeks. Table 3: Dosing Regimens for Pediatric Patients with PMA less than or equal to 32 weeks, or greater than 32 weeks to less than or equal to 40 weeks PMA (weeks) Dose (mg/kg) Dosing Interval (hours) Less than or equal to 32 5 8 Greater than or equal to 32 to less than or equal to 40 7 8 PMA: Post-Menstrual age Dilution for Intravenous use and Intravenous Infusion Rates: The concentration of clindamycin in diluent for infusion should not exceed 18 mg per mL.
Infusion rates should not exceed 30 mg per minute. The usual infusion dilutions and rates are as follows: Dose Diluent Time 300 mg 50 mL 10 min 600 mg 50 mL 20 min 900 mg 50–100 mL 30 min 1200 mg 100 mL 40 min Administration of more than 1200 mg in a single 1-hour infusion is not recommended. Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration, whenever solution and container permit.
⛔ Contraindications ▾
CONTRAINDICATIONS This drug is contraindicated in individuals with a history of hypersensitivity to preparations containing clindamycin or lincomycin.
⚠️ Warnings ▾
WARNINGS See BOXED WARNING . Clostridioides difficile -Associated Diarrhea Clostridioides difficile -associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including Clindamycin Injection USP in 5% Dextrose, and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile .
C. difficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy. CDAD must be considered in all patients who present with diarrhea following antibacterial drug use.
Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents. If CDAD is suspected or confirmed, ongoing antibacterial drug use not directed against C. difficile may need to be discontinued. Appropriate fluid and electrolyte management, protein supplementation, antibacterial drug treatment of C. difficile , and surgical evaluation should be instituted as clinically indicated.
Anaphylactic and Severe Hypersensitivity Reactions Anaphylactic shock and anaphylactic reactions have been reported (see ADVERSE REACTIONS ). Severe hypersensitivity reactions, including acute myocardial ischemia with or without myocardial infarction, and severe skin reactions such as toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS), Stevens-Johnson syndrome (SJS), some with fatal outcome, have been reported (see ADVERSE REACTIONS ). In case of such an anaphylactic or severe hypersensitivity reaction, discontinue treatment permanently and institute appropriate therapy.
A careful inquiry should be made concerning previous sensitivities to drugs and other allergens. Nephrotoxicity Clindamycin is potentially nephrotoxic and cases with acute kidney injury have been reported. Consider monitoring of renal function particularly in patients with pre-existing renal dysfunction or those taking concomitant nephrotoxic drugs.
In case of acute kidney injury, discontinue Clindamycin Injection USP in 5% Dextrose when no other etiology is identified. Usage in Meningitis- Since clindamycin does not diffuse adequately into the cerebrospinal fluid, the drug should not be used in the treatment of meningitis.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The following reactions have been reported with the use of clindamycin. Infections and Infestations: Clostridioides difficile colitis Gastrointestinal: Antibacterial drug-associated colitis (see WARNINGS ), pseudomembranous colitis, abdominal pain, nausea, and vomiting. The onset of pseudomembranous colitis symptoms may occur during or after antibacterial treatment (see WARNINGS ).
An unpleasant or metallic taste has been reported after intravenous administration of the higher doses of clindamycin phosphate. Hypersensitivity Reactions: Maculopapular rash and urticaria have been observed during drug therapy. Generalized mild to moderate morbilliform-like skin rashes are the most frequently reported of all adverse reactions.
Severe skin reactions such as toxic epidermal necrolysis, some with fatal outcome, have been reported (see WARNINGS ). Cases of acute generalized exanthematous pustulosis (AGEP), erythema multiforme, some resembling Stevens-Johnson syndrome, have been associated with clindamycin. Anaphylactic shock, anaphylactic reaction, hypersensitivity, and acute myocardial ischemia with or without myocardial infarction occurring as part of an allergic reaction have also been reported (see WARNINGS ).
Cutaneous vasculitis and symmetrical drug-related intertriginous and flexural exanthema have also been reported. Skin and Mucous Membranes: Pruritus, vaginitis, angioedema and rare instances of exfoliative dermatitis have been reported (see Hypersensitivity Reactions ). Liver: Jaundice and abnormalities in liver function tests have been observed during clindamycin therapy.
Renal: Acute kidney injury (see WARNINGS ). Hematopoietic: Transient neutropenia (leukopenia) and eosinophilia have been reported. Reports of agranulocytosis and thrombocytopenia have been made.
No direct etiologic relationship to concurrent clindamycin therapy could be made in any of the foregoing. Immune System: Drug reaction with eosinophilia and systemic symptoms (DRESS) cases have been reported. Local Reactions: Thrombophlebitis has been reported after intravenous infusion.
Reactions can be minimized by avoiding prolonged use of indwelling intravenous catheters. Musculoskeletal: Polyarthritis cases have been reported. Cardiovascular: Cardiopulmonary arrest and hypotension have been reported following too rapid intravenous administration (see DOSAGE AND ADMINISTRATION ).
To report SUSPECTED ADVERSE REACTIONS, contact Baxter Healthcare at 1-866-888-2472 or the FDA at 1 800 FDA-1088 or www.fda.gov/medwatch .
🔄 Drug Interactions ▾
Drug Interactions Clindamycin has been shown to have neuromuscular blocking properties that may enhance the action of other neuromuscular blocking agents. Therefore, it should be used with caution in patients receiving such agents. Clindamycin is metabolized predominantly by CYP3A4, and to a lesser extent by CYP3A5, to the major metabolite clindamycin sulfoxide and minor metabolite N-desmethylclindamycin.
Therefore, inhibitors of CYP3A4 and CYP3A5 may increase plasma concentrations of clindamycin and inducers of these isoenzymes may reduce plasma concentrations of clindamycin. In the presence of strong CYP3A4 inhibitors, monitor for adverse reactions. In the presence of strong CYP3A4 inducers such as rifampicin, monitor for loss of effectiveness.
In vitro studies indicate that clindamycin does not inhibit CYP1A2, CYP2C9, CYP2C19, CYP2E1 or CYP2D6 and only moderately inhibits CYP3A4.
🧒 Pediatric Use ▾
Pediatric Use When Clindamycin Injection USP in 5% Dextrose is administered to the pediatric population (birth to 16 years) appropriate monitoring of organ system functions is desirable (see CLINICAL PHARMACOLOGY and DOSAGE AND ADMINISTRATION ).
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of clindamycin did not include sufficient numbers of patients age 65 and over to determine whether they respond differently from younger patients. However, other reported clinical experience indicates that antibacterial drug-associated colitis and diarrhea (due to Clostridioides difficile ) seen in association with most antibacterial drugs occur more frequently in the elderly (>60 years) and may be more severe. These patients should be carefully monitored for the development of diarrhea.
Pharmacokinetic studies with clindamycin have shown no clinically important differences between young and elderly subjects with normal hepatic function and normal (age-adjusted) renal function after oral or intravenous administration.
🆘 Overdosage ▾
OVERDOSAGE Significant mortality was observed in mice at an intravenous dose of 855 mg/kg and in rats at an oral or subcutaneous dose of approximately 2618 mg/kg. In the mice, convulsions and depression were observed. Hemodialysis and peritoneal dialysis are not effective in removing clindamycin from the serum.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Distribution Biologically inactive clindamycin phosphate is converted to active clindamycin. By the end of short-term intravenous infusion, peak serum concentrations of active clindamycin are reached. After intramuscular injection of clindamycin phosphate, peak concentrations of active clindamycin are reached within 3 hours in adults and 1 hour in pediatric patients.
Serum concentrations of clindamycin can be maintained above the in vitro minimum inhibitory concentrations for most indicated organisms by administration of clindamycin phosphate every 8 to 12 hours in adults and every 6 to 8 hours in pediatric patients, or by continuous intravenous infusion. An equilibrium state is reached by the third dose. No significant concentrations of clindamycin are attained in the cerebrospinal fluid even in the presence of inflamed meninges.
Metabolism In vitro studies in human liver and intestinal microsomes indicated that clindamycin is predominantly metabolized by Cytochrome P450 3A4 (CYP3A4), with minor contribution from CYP3A5, to form clindamycin sulfoxide and a minor metabolite, N‑desmethylclindamycin. Excretion Biologically inactive clindamycin phosphate disappears from the serum with 6 minutes of the average elimination half-life; however, the average serum elimination half-life of active clindamycin is about 3 hours in adults and 2½ hours in pediatric patients.
Specific Populations Patients with Renal/Hepatic Impairment The elimination half-life of clindamycin is increased slightly in patients with markedly reduced renal or hepatic function. Hemodialysis and peritoneal dialysis are not effective in removing clindamycin from the serum. Dosage schedules do not need to be modified in patients with renal or hepatic disease.
Geriatric Patients Pharmacokinetic studies in elderly volunteers (61-79 years) and younger adults (18-39 years) indicate that age alone does not alter clindamycin pharmacokinetics (clearance, elimination half-life, volume of distribution, and area under the serum concentration-time curve) after intravenous administration of clindamycin phosphate. After oral administration of clindamycin hydrochloride, the average elimination half-life is increased to approximately 4.0 hours (range 3.4-5.1 h) in the elderly, compared to 3.2 hours (range 2.1-4.2 h) in younger adults.
The extent of absorption, however, is not different between age groups and no dosage alteration is necessary for the elderly with normal hepatic function and normal (age-adjusted) renal function 1 . Pharmacokinetics in Pediatric Patients with PMA ≤ 32 weeks, or > 32 to ≤ 40 weeks Systemic clearance (CL) in premature infants increases with increases in body weight (kg) and post-menstrual age (PMA). The dosing regimens for pediatric patients ≤ 32 weeks PMA (5 mg/kg) and > 32 to ≤ 40 weeks PMA (7 mg/kg), both administered intravenously every 8 hours, achieve exposures comparable to therapeutic exposures in adults (weighing 70 kg) administered clindamycin 600 mg every 8 hours (Table 1).
Table 1: Predicted Drug Exposure (Mean ± SD) of Clindamycin in Adults and in Pediatric Patients with PMA ≤ 32 weeks, or > 32 to ≤ 40 weeks Age Adult (70 kg) PMA ≤ 32 weeks PMA > 32 - ≤ 40 weeks Dose (every 8 hours) 600 mg 5 mg/kg 7 mg/kg AUC ss,0-8 hour (mcg h/mL) 50.5 (30.95) 52.5 (17.0) 55.9 (23.55) C max,ss (mcg/mL) 12.0 (3.49) 9.0 (2.02) 10.5 (2.79) C min,ss (mcg/mL) 3.1 (3.34) 4.6 (2.00) 4.4 (2.77) PMA: post-menstrual age; AUC ss,0-8 hour : area under the concentration-time curve during a dosing interval at steady state; C max,ss : maximum drug concentration at steady state; C min,ss : minimum or trough drug concentration at steady state.
Obese Pediatric Patients Aged 2 to Less than 18 Years and Obese Adults Aged 18 to 20 Years An analysis of pharmacokinetic data in obese pediatric patients aged 2 to less than 18 years and obese adults aged 18 to 20 years demonstrated that clindamycin clearance and volume of distribution, normalized by total body… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Each 50 mL of Clindamycin Injection USP in 5% Dextrose contains Clindamycin phosphate, USP equivalent to 300 mg, 600 mg, or 900 mg clindamycin; 2.5 g dextrose hydrous, USP; 2 mg edetate disodium dihydrate, USP; and Water for Injection, USP. pH may have been adjusted with sodium hydroxide and/or hydrochloric acid. The single dose GALAXY containers are available as follows: Code Product Description Container NDC Number Carton NDC Number 2G3452 Supplied as 24 bags per case 300 mg per 50 mL NDC 0338-3410-50 NDC 0338-3410-24 2G3453 Supplied as 24 bags per case 600 mg per 50 mL NDC 0338-3612-50 NDC 0338-3612-24 2G3454 Supplied as 24 bags per case 900 mg per 50 mL NDC 0338-3814-50 NDC 0338-3814-24 Exposure of pharmaceutical products to heat should be minimized.
It is recommended that GALAXY plastic containers be stored at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature]. Avoid temperatures above 30°C.
📋 Description ▾
DESCRIPTION Clindamycin Injection USP in 5% Dextrose in the GALAXY plastic container for intravenous use is composed of clindamycin phosphate equivalent to 300, 600 and 900 mg of clindamycin premixed with 5% dextrose as a sterile solution. Disodium edetate has been added at a concentration of 0.04 mg/mL. The pH has been adjusted with sodium hydroxide and/or hydrochloric acid.
Clindamycin is a semisynthetic antibacterial drug produced by a 7(S)‑chloro-substitution of the 7(R)-hydroxyl group of the parent compound lincomycin. The chemical name of clindamycin phosphate is L- threo -α-D- galacto -Octopyranoside, methyl-7-chloro-6,7,8-trideoxy-6-[[(1-methyl-4-propyl-2-pyrrolidinyl)carbonyl] amino]‑1-thio-, 2-(dihydrogen phosphate), (2 S - trans )-. The molecular formula is C 18 H 34 ClN 2 O 8 PS and the molecular weight is 504.96.
The structural formula is represented below: Clindamycin Injection USP in 5% Dextrose in the GALAXY plastic containers is for Intravenous Use. The plastic container is fabricated from a specially designed multilayer plastic. Solutions in contact with the plastic container can leach out certain of its chemical components in very small amounts within the expiration period.
The suitability of the plastic has been confirmed in tests in animals according to the USP biological tests for plastic containers, as well as by tissue culture toxicity studies. Clindamycin in 5% Dextrose Structural Formula
💬 Information for Patients ▾
Information for Patients Patients should be counseled that antibacterial drugs including Clindamycin Injection USP in 5% Dextrose should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold). When Clindamycin Injection USP in 5% Dextrose is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed.
Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by Clindamycin Injection USP in 5% Dextrose or other antibacterial drugs in the future. Diarrhea is a common problem caused by antibacterial drugs which usually ends when the antibacterial drug is discontinued. Sometimes after starting treatment with antibacterial drugs, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibacterial drug.
If this occurs, patients should contact their physician as soon as possible.
⚠️ Precautions ▾
PRECAUTIONS General Review of experience to date suggests that a subgroup of older patients with associated severe illness may tolerate diarrhea less well. When clindamycin is indicated in these patients, they should be carefully monitored for change in bowel frequency. Clindamycin Injection USP in 5% Dextrose products should be prescribed with caution in individuals with a history of gastrointestinal disease, particularly colitis.
Clindamycin Injection USP in 5% Dextrose should be prescribed with caution in atopic individuals. Certain infections may require incision and drainage or other indicated surgical procedures in addition to antibacterial drug therapy. The use of Clindamycin Injection USP in 5% Dextrose may result in overgrowth of nonsusceptible organisms-particularly yeasts.
Should superinfections occur, appropriate measures should be taken as indicated by the clinical situation. Clindamycin Injection USP in 5% Dextrose should not be injected intravenously undiluted as a bolus, but should be infused over at least 10-60 minutes as directed in the DOSAGE AND ADMINISTRATION section. Clindamycin dosage modification is not necessary in patients with renal disease.
In patients with moderate to severe liver disease, prolongation of clindamycin half-life has been found. However, it was postulated from studies that when given every eight hours, accumulation should rarely occur. Therefore, dosage modification in patients with liver disease may not be necessary.
However, periodic liver enzyme determinations should be made when treating patients with severe liver disease. Prescribing Clindamycin Injection USP in 5% Dextrose in the absence of a proven or strongly suspected bacterial infection or a prophylactic indication is unlikely to provide benefit to the patient and increases the risk of the development of drug-resistant bacteria. Information for Patients Patients should be counseled that antibacterial drugs including Clindamycin Injection USP in 5% Dextrose should only be used to treat bacterial infections.
They do not treat viral infections (e.g., the common cold). When Clindamycin Injection USP in 5% Dextrose is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by Clindamycin Injection USP in 5% Dextrose or other antibacterial drugs in the future.
Diarrhea is a common problem caused by antibacterial drugs which usually ends when the antibacterial drug is discontinued. Sometimes after starting treatment with antibacterial drugs, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibacterial drug. If this occurs, patients should contact their physician as soon as possible.
Laboratory Tests During prolonged therapy periodic liver and kidney function tests and blood counts should be performed. Drug Interactions Clindamycin has been shown to have neuromuscular blocking properties that may enhance the action of other neuromuscular blocking agents. Therefore, it should be used with caution in patients receiving such agents.
Clindamycin is metabolized predominantly by CYP3A4, and to a lesser extent by CYP3A5, to the major metabolite clindamycin sulfoxide and minor metabolite N-desmethylclindamycin. Therefore, inhibitors of CYP3A4 and CYP3A5 may increase plasma concentrations of clindamycin and inducers of these isoenzymes may reduce plasma concentrations of clindamycin. In the presence of strong CYP3A4 inhibitors, monitor for adverse reactions.
In the presence of strong CYP3A4 inducers such as rifampicin, monitor for loss of effectiveness. In vitro studies indicate… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Limited published data based on breast milk sampling reports that clindamycin appears in human breast milk in the range of less than 0.5 to 3.8 mcg/mL at dosages of 150 mg orally to 600 mg intravenously. Clindamycin has the potential to cause adverse effects on the breast-fed infant’s gastrointestinal flora. If oral or intravenous clindamycin is required by a nursing mother, it is not a reason to discontinue breastfeeding, but an alternate drug may be preferred.
Monitor the breast-fed infant for possible adverse effects on the gastrointestinal flora, such as diarrhea, candidiasis (thrush, diaper rash) or rarely, blood in the stool indicating possible antibacterial drug-associated colitis. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for clindamycin and any potential adverse effects on the breast‑fed child from clindamycin or from the underlying maternal condition.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility Long term studies in animals have not been performed with clindamycin to evaluate carcinogenic potential. Genotoxicity tests performed included a rat micronucleus test and an Ames Salmonella reversion test. Both tests were negative.
Fertility studies in rats treated orally with up to 300 mg/kg/day (approximately 1.1 times the highest recommended adult human dose based on mg/m 2 ) revealed no effects on fertility or mating ability.
📚 References ▾
REFERENCES 1. Smith RB, Phillips JP: Evaluation of CLEOCIN HCl and CLEOCIN Phosphate in an Aged Population. Upjohn TR 8147-82-9122-021, December 1982.
📄 Package Label / Principal Display Panel ▾
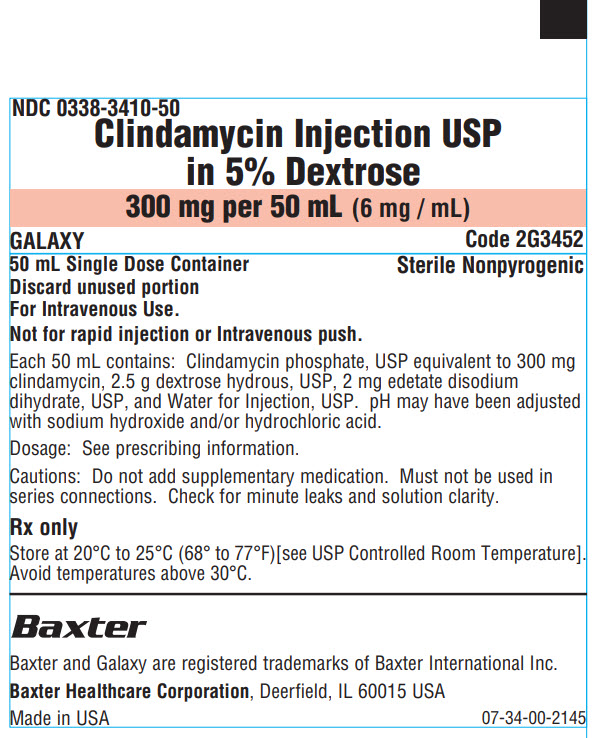
PACKAGE/LABEL PRINCIPAL DISPLAY PANEL Container Label NDC 0338-3410-50 Clindamycin Injection USP In 5% Dextrose 300 mg per 50 mL (6 mg / mL) GALAXY Code 2G3452 50 mL Single Dose Container Discard unused portion For Intravenous Use. Sterile Nonpyrogenic Not for rapid injection or Intravenous push. Each 50 mL contains: Clindamycin phosphate, USP equivalent to 300 mg clindamycin, 2.5 g dextrose hydrous, USP, 2 mg edetate disodium dihydrate, USP, and Water for Injection, USP. pH may have been adjusted with sodium hydroxide and/or hydrochloric acid.
Dosage: See prescribing information. Cautions: Do not add supplementary medication. Must not be used in series connections.
Check for minute leaks and solution clarity. Rx only Store at 20°C to 25°C (68° to 77°F)[see USP Controlled Room Temperature]. Avoid temperatures above 30°C.
Baxter Logo Baxter and Galaxy are registered trademarks of Baxter International Inc. Baxter Healthcare Corporation , Deerfield, IL 60015 USA Made in USA 07-34-00-2145 BAR CODE POSITION ONLY 303383410504 Carton Label GALAXY Container Baxter Logo Baxter and Galaxy are registered trademarks of Baxter International Inc. Baxter Healthcare Corporation , Deerfield, IL 60015 Made in USA 07-04-00-1225 Clindamycin Injection USP in 5% Dextrose 300 mg per 50 mL (6 mg / mL) Contains 12 - 50 mL Single Dose Containers Store at 20° to 25°C (68° to 77°F)[see USP Controlled Room Temperature].
Avoid temperatures above 30°C. Rx only NDC 0338-3410-24 Code 2G3452 *FOR BAR CODE POSITION ONLY (01) 20303383410249 For Intravenous Use. Not for rapid injection or Intravenous push.
Sterile Nonpyrogenic Each 50 mL contains: Clindamycin phosphate, USP equivalent to 300 mg clindamycin, 2.5 g dextrose hydrous, USP, 2 mg edetate disodium dihydrate, USP, and Water for Injection, USP. pH may have been adjusted with sodium hydroxide and/or hydrochloric acid. Dosage: See prescribing information. Cautions: Do not add supplementary medication.
Must not be used in series connections. Check for minute leaks and solution clarity. Container Label NDC 0338-3612-50 Clindamycin Injection USP In 5% Dextrose 600 mg per 50 mL (12 mg / mL) GALAXY Code 2G3453 50 mL Single Dose Container Discard unused portion For Intravenous Use.
Not for rapid injection or Intravenous push. Sterile Nonpyrogenic Each 50 mL contains: Clindamycin phosphate, USP equivalent to 600 mg clindamycin, 2.5 g dextrose hydrous, USP, 2 mg edetate disodium dihydrate, USP, and Water for Injection, USP. pH may have been adjusted with sodium hydroxide and/or hydrochloric acid. Dosage: See prescribing information.
Cautions: Do not add supplementary medication. Must not be used in series connections. Check for minute leaks and solution clarity.
Rx only Store at 20°C to 25°C (68° to 77°F)[see USP Controlled Room Temperature]. Avoid temperatures above 30°C. Baxter Logo Baxter and Galaxy are registered trademarks of Baxter International Inc.
Baxter Healthcare Corporation , Deerfield, IL 60015 USA Made in USA 07-34-00-2146 BAR CODE POSITION ONLY 303383612502 Carton Label GALAXY Container Baxter Logo Baxter and Galaxy are registered trademarks of Baxter International Inc. Baxter Healthcare Corporation , Deerfield, IL 60015 Made in USA 07-04-00-1226 Clindamycin Injection USP in 5% Dextrose 600 mg per 50 mL (12 mg / mL) Contains 12 - 50 mL Single Dose Containers Store at 20° to 25°C (68° to 77°F)[see USP Controlled Room Temperature]. Avoid temperatures above 30°C.
Rx only NDC 0338-3612-24 Code 2G3453 *FOR BAR CODE POSITION ONLY (01) 20303383612247 For Intravenous Use. Not for rapid injection or Intravenous push. Sterile Nonpyrogenic Each 50 mL contains: Clindamycin phosphate, USP equivalent to 600 mg clindamycin, 2.5 g dextrose hydrous, USP, 2 mg edetate disodium dihydrate, USP, and Water for Injection, USP. pH may have been adjusted with sodium hydroxide and/or hydrochloric acid.
Dosage: See prescribing information. Cautions: Do not add supplementary medication. Must not be used in series connections.
C… [Excerpted — this section continues on DailyMed.]
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |