
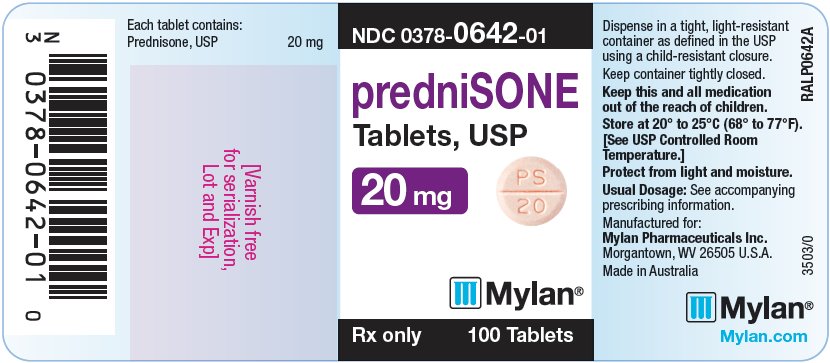
Prednisone 20 mg Tablet, 100-count — NDC 0378-0642-01 (Billing 00378-0642-01)
This is a package of 100 tablets of Prednisone 20 mg Tablet from Mylan Pharmaceuticals Inc., marketed since Feb 2020 and currently FDA-listed; retail pharmacies pay about $0.0643 per tablet (NADAC).
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 006751
- GCN: 27174
- GPI-14 (Medi-Span): 22100045000325
- HICL (First Databank): 002879
- AHFS class code: 68:04.00.00
- RxCUI (RxNorm): 198145
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Corticosteroid class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Prednisone is used alone or with other medications to treat the symptoms of low corticosteroid levels (lack of certain substances that are usually produced by the body and are needed for normal body functioning). Prednisone is also used to treat other conditions in patients with normal corticosteroid levels. These conditions include certain types of arthritis; severe allergic reactions; multiple sclerosis (a disease in which the nerves do not function properly); lupus (a disease in which the body attacks many of its own organs); and certain conditions that affect the lungs, skin, eyes, kidneys...
Read the full MedlinePlus article ↗- It calms inflammation and lowers immune activity. It is used for allergies, arthritis, lupus, skin, gut, lung, eye and blood conditions, and more. Your prescriber chose it for your...
- Take it with food or milk to protect your stomach. A once-daily dose is usually best in the morning. If you have delayed-release tablets, take them with food and swallow them whole...
- No, not after long-term use. Your body may need time to restart its own steroid production. Your doctor will lower the dose gradually.
- Bigger appetite, weight gain, trouble sleeping, mood swings and stomach upset are common. Call your doctor for signs of infection, black stools, severe stomach pain, vision changes...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Prednisone — tap one for details:
Prednisone may be associated with lower levels of 8 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.064 | $6.43 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $4.33 | $432.79 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.2837 | $28.37 / 100 tablets |
| Medicare Part B allowsASP · J7512 | $0.004 / J7512 unit | — |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 00378-0642-01 You're viewing this | 100 TABLET in 1 BOTTLE, PLASTIC | $0.0643 / ea | $6.43 | 2020-02-11 | — | Active |
| 00378-0642-05 0378-0642-05 | 500 TABLET in 1 BOTTLE, PLASTIC | $0.0643 / ea | $32.16 | 2020-02-06 | — | Active |
| 00378-0642-10 0378-0642-10 Main listing | 1000 TABLET in 1 BOTTLE, PLASTIC | $0.0643 / ea | $64.31 | 2020-02-11 | — | Active |
You're viewing the smallest of 3 pack sizes for this product.
This pack has the lowest per-ea cost of the 3 priced pack sizes ($0.0643 NADAC).
This pack accounts for about 12% of this product's recent Medicaid fills; most go to the 1000 tablets pack. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 00378-0642-05?
What NDC number is used to bill for this package of Prednisone 20 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Prednisone 20 mgthis 00378-0642-01 | Mylan | 100 tablets | $0.064 | AB | Availability likely | — |
| Prednisone 20 mg 00591-5443-01 | Actavis | 100 tablets | $0.064 | AB | Availability likely | — |
| Prednisone 20 mg 00603-5339-21 | Par | 100 tablets | $0.064 | AB | Availability likely | — |
| Prednisone 20 mg 59651-0488-01 | Aurobindo | 100 tablets | $0.064 | AB | Availability likely | — |
| prednisone 20 mg 60219-1708-01 | Amneal | 100 tablets | $0.064 | AB | Availability likely | — |
| Prednisone 20 mg 60687-0145-01 | American | 100 tablets | $0.064 | AB | Availability likely | — |
| Prednisone 20 mg 60687-0925-01 | American | 100 tablets | $0.064 | AB | Availability likely | — |
| Prednisone 20 mg 62135-0553-30 | Chartwell | 30 tablets | $0.064 | BX | Availability likely | — |
| PredniSONE Tablets, USP, 20 mg 63561-0122-01 | Granulation | 100 tablets | $0.064 | AB | Availability likely | — |
| Prednisone 20 mg 70954-0060-10 | ANI | 100 tablets | $0.064 | AB | Availability likely | — |
| PredniSONE 20 mg 00054-0018-20 | Hikma | 100 tablets | $0.092 | AB | FDA listed | +43% |
| PredniSONE 20 mg 00054-9818-25 | Hikma | 100 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 00615-8441-39 | NCS | 30 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 10135-0778-01 | Marlex | 100 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 42708-0105-10 | QPharma, | 10 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 42708-0195-10 | QPharma, | 10 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 45865-0884-21 | Medsource | 21 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 50090-2786-00 | A-S | 21 tablets | — | AB | Discontinued | — |
| Prednisone 20 mg 50090-2789-01 | A-S | 10 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 50090-2804-00 | A-S | 20 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 50090-6122-01 | A-S | 10 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 50090-6123-00 | A-S | 20 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 50090-6259-00 | A-S | 21 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 51407-0923-05 | Golden | 500 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 51655-0242-53 | Northwind | 10 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 51655-0541-20 | Northwind | 20 tablets | — | AB | FDA listed | — |
| PredniSONE 20 mg 51655-0701-18 | Northwind | 18 tablets | — | — | FDA listed | — |
| Prednisone 20 mg 55154-2147-00 | Cardinal | 10 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 55154-2581-00 | Cardinal | 10 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 60760-0790-12 | St. | 12 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 60760-0797-12 | St. | 12 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 60760-0840-12 | ST. | 12 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 63187-0807-05 | Proficient | 5 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 64380-0785-01 | Strides | 100 tablets | — | AB | FDA listed | — |
| Prednisone 5 mg 66267-0172-06 | NuCare | 6 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 66267-0860-03 | NuCare | 3 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 67046-1610-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 67296-2081-01 | Redpharm | 10 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 67296-2182-01 | Redpharm | 10 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 68071-3143-01 | NuCare | 100 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 68071-3617-01 | NuCare | 10 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 68071-3637-01 | NuCare | 10 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 68071-3721-00 | NuCare | 10 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 68071-3738-01 | NuCare | 10 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 68071-4685-02 | NuCare | 21 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 68788-8663-01 | Preferred | 10 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 68788-8819-01 | Preferred | 10 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 70518-3401-00 | REMEDYREPACK | 34 tablets | — | AB | Discontinued | — |
| prednisone 20 mg 70518-3540-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 70518-4243-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 70518-4293-00 | REMEDYREPACK | 10 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 71205-0239-05 | Proficient | 5 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 71205-0407-10 | Proficient | 10 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 71205-0741-06 | Proficient | 6 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 71205-0797-10 | Proficient | 10 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 71335-0623-00 | Bryant | 11 tablets | — | AB | Discontinued | — |
| prednisone 20 mg 71335-2079-00 | Bryant | 11 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 71335-2149-01 | Bryant | 6 tablets | — | AB | FDA listed | — |
| PredniSONE Tablets, USP, 20 mg 71335-2737-00 | Bryant | 100 tablets | — | AB | FDA listed | — |
| PredniSONE Tablets, USP, 20 mg 71335-2754-00 | Bryant | 11 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 71335-2895-01 | Bryant | 9 tablets | — | AB | FDA listed | — |
| PredniSONE Tablets, USP, 20 mg 71335-2938-01 | Bryant | 9 tablets | — | AB | FDA listed | — |
| PredniSONE Tablets, USP, 20 mg 71335-3046-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| PredniSONE Tablets, USP, 20 mg 71335-3047-01 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| PredniSONE Tablets, USP, 20 mg 72162-2486-00 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 72189-0430-05 | Direct_Rx | 5 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 72789-0393-02 | PD-Rx | 2 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 72789-0448-21 | PD-Rx | 21 tablets | — | AB | FDA listed | — |
| PredniSONE Tablets, USP, 20 mg 72789-0473-01 | PD-Rx | 100 tablets | — | AB | FDA listed | — |
| PredniSONE Tablets, USP, 20 mg 72789-0500-21 | PD-Rx | 21 tablets | — | AB | FDA listed | — |
| PredniSONE Tablets, USP, 20 mg 72789-0509-06 | PD-Rx | 6 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 76420-0069-10 | Asclemed | 10 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 76420-0413-00 | Asclemed | 1000 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 80425-0105-01 | Advanced | 20 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 80425-0486-01 | Advanced | 21 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 80425-0487-01 | Advanced | 21 tablets | — | AB | FDA listed | — |
| P- Pack Prednisone 20Mg, 7- Day Tapering Dose Pack 20 mg 85000-0012-01 | INTERSTELLAR | 15 tablets | — | AB | Discontinued | — |
| prednisone 20 mg 85766-0002-00 | Sportpharm | 1000 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 87063-0045-01 | ASCLEMED | 100 tablets | — | AB | FDA listed | — |
| PredniSONE 20 mg 68788-4182-01 | Preferred | 10 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 50090-8051-01 | A-S | 10 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 50090-8083-00 | A-S | 8 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 50090-8087-00 | A-S | 21 tablets | — | AB | FDA listed | — |
| Prednisone 20 mg 50090-8084-00 | A-S | 20 tablets | — | AB | FDA listed | — |
| prednisone 20 mg 50090-8052-00 | A-S | 20 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 7T9FYH5QMK
A plant-derived powder that serves as a binder and filler in tablets and capsules. It helps hold ingredients together, adds bulk, and aids in smooth tablet disintegration when swallowed.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Prednisone tablets are indicated in the following conditions: Endocrine Disorders Primary or secondary adrenocortical insufficiency (hydrocortisone or cortisone is the first choice: synthetic analogs may be used in conjunction with mineralocorticoids where applicable; in infancy mineralocorticoid supplementation is of particular importance); congenital adrenal hyperplasia; hypercalcemia associated with cancer; nonsuppurative thyroiditis. Rheumatic Disorders As adjunctive therapy for short-term administration (to tide the patient over an acute episode or exacerbation) in: psoriatic arthritis, rheumatoid arthritis, including juvenile rheumatoid arthritis (selected cases may require low-dose maintenance therapy), ankylosing spondylitis, acute and subacute bursitis, acute nonspecific tenosynovitis, acute gouty arthritis, post-traumatic osteoarthritis, synovitis of osteoarthritis, epicondylitis.
Collagen Diseases During an exacerbation or as maintenance therapy in selected cases of: systemic lupus erythematosus, systemic dermatomyositis (polymyositis), acute rheumatic carditis. Dermatologic Diseases Pemphigus; bullous dermatitis herpetiformis; severe erythema multiforme (Stevens-Johnson syndrome); exfoliative dermatitis; mycosis fungoides; severe psoriasis; severe seborrheic dermatitis. Allergic States Control of severe or incapacitating allergic conditions intractable to adequate trials of conventional treatment: seasonal or perennial allergic rhinitis; bronchial asthma; contact dermatitis; atopic dermatitis; serum sickness; drug hypersensitivity reactions.
Ophthalmic Diseases Severe acute and chronic allergic and inflammatory processes involving the eye and its adnexa such as: allergic corneal marginal ulcers, herpes zoster ophthalmicus, anterior segment inflammation, diffuse posterior uveitis and choroiditis, sympathetic ophthalmia, allergic conjunctivitis, keratitis, chorioretinitis, optic neuritis, iritis and iridocyclitis. Respiratory Diseases Symptomatic sarcoidosis; Loeffler’s syndrome not manageable by other means; berylliosis; fulminating or disseminated pulmonary tuberculosis when used concurrently with appropriate antituberculous chemotherapy; aspiration pneumonitis.
Hematologic Disorders Idiopathic thrombocytopenic purpura in adults; secondary thrombocytopenia in adults; acquired (autoimmune) hemolytic anemia; erythroblastopenia (RBC anemia); congenital (erythroid) hypoplastic anemia. Neoplastic Diseases For palliative management of: leukemias and lymphomas in adults, acute leukemia of childhood. Edematous States To induce a diuresis or remission of proteinuria in the nephrotic syndrome, without uremia, of the idiopathic type or that due to lupus erythematosus.
Gastrointestinal Diseases To tide the patient over a critical period of the disease in: ulcerative colitis, regional enteritis. Miscellaneous Tuberculous meningitis with subarachnoid block or impending block when used concurrently with appropriate antituberculous chemotherapy; trichinosis with neurologic or myocardial involvement.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Gastric irritation may be reduced if taken before, during, or immediately after meals or with food or milk. The maximal activity of the adrenal cortex is between 2 am and 8 am, and it is minimal between 4 pm and midnight. Exogenous corticosteroids suppress adrenocorticoid activity the least when given at the time of maximal activity (am) for single dose administration.
Therefore, it is recommended that prednisone be administered in the morning prior to 9 am and when large doses are given, administration of antacids between meals to help prevent peptic ulcers. Multiple dose therapy should be evenly distributed in evenly spaced intervals throughout the day. Dietary salt restriction may be advisable in patients.
Do not stop taking this medicine without first talking to your doctor. Avoid abrupt withdraw of therapy. The initial dosage of prednisone may vary from 5 mg to 60 mg per day, depending on the specific disease entity being treated.
In situations of less severity lower doses will generally suffice, while in selected patients higher initial doses may be required. The initial dosage should be maintained or adjusted until a satisfactory response is noted. If after a reasonable period of time there is a lack of satisfactory clinical response, prednisone should be discontinued and the patient transferred to other appropriate therapy.
IT SHOULD BE EMPHASIZED THAT DOSAGE REQUIREMENTS ARE VARIABLE AND MUST BE INDIVIDUALIZED ON THE BASIS OF THE DISEASE UNDER TREATMENT AND THE RESPONSE OF THE PATIENT. After a favorable response is noted, the proper maintenance dosage should be determined by decreasing the initial drug dosage in small increments at appropriate time intervals until the lowest dosage which will maintain an adequate clinical response is reached. It should be kept in mind that constant monitoring is needed in regard to drug dosage.
Included in the situations which may make dosage adjustments necessary are changes in clinical status secondary to remissions or exacerbations in the disease process, the patient’s individual drug responsiveness, and the effect of patient exposure to stressful situations not directly related to the disease entity under treatment; in this latter situation, it may be necessary to increase the dosage of prednisone for a period of time consistent with the patient’s condition. If after long-term therapy the drug is to be stopped, it is recommended that it be withdrawn gradually rather than abruptly.
Multiple Sclerosis In the treatment of acute exacerbations of multiple sclerosis daily doses of 200 mg of prednisolone for a week followed by 80 mg every other day for 1 month have been shown to be effective. (Dosage range is the same for prednisone and prednisolone.) Alternate Day Therapy Alternate day therapy is a corticosteroid dosing regimen in which twice the usual daily dose of corticoid is administered every other morning. The purpose of this mode of therapy is to provide the patient requiring long-term pharmacologic dose treatment with the beneficial effects of corticoids while minimizing certain undesirable effects, including pituitary-adrenal suppression, the cushingoid state, corticoid withdrawal symptoms, and growth suppression in children.
The rationale for this treatment schedule is based on two major premises: (a) the anti-inflammatory or therapeutic effect of corticoids persists longer than their physical presence and metabolic effects and (b) administration of the corticosteroid every other morning allows for re-establishment of more nearly normal hypothalamic-pituitary-adrenal (HPA) activity on the off-steroid day. A brief review of the HPA physiology may be helpful in understanding this rationale. Acting primarily through the hypothalamus a fall in free cortisol stimulates the pituitary gland to produce increasing amounts of corticotropin (ACTH) while a rise in free cortisol inhibits ACTH secretion.
Normally the HPA system is characterized by diurnal (circadia… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Prednisone tablets are contraindicated in systemic fungal infections and known hypersensitivity to components.
⚠️ Warnings ▾
WARNINGS General Rare instances of anaphylactoid reactions have occurred in patients receiving corticosteroid therapy (see ADVERSE REACTIONS: Allergic Reactions ). Increased dosage of rapidly acting corticosteroids is indicated in patients on corticosteroid therapy subjected to any unusual stress before, during and after the stressful situation. Immunosuppression and Increased Risk of Infection Corticosteroids, including prednisone tablets, suppress the immune system and increase the risk of infection with any pathogen, including viral, bacterial, fungal, protozoan, or helminthic pathogens.
Corticosteroids can: • Reduce resistance to new infections • Exacerbate existing infections • Increase the risk of disseminated infections • Increase the risk of reactivation or exacerbation of latent infections • Mask some signs of infection Corticosteroid-associated infections can be mild but can be severe and at times fatal. The rate of infectious complications increases with increasing corticosteroid dosages. Monitor for the development of infection and consider prednisone tablets withdrawal or dosage reduction as needed.
Do not administer prednisone tablets by an intraarticular, intrabursal, intratendinous, or intralesional route in the presence of acute local infection. Tuberculosis If prednisone tablets are used to treat a condition in patients with latent tuberculosis or tuberculin reactivity, reactivation of tuberculosis may occur. Closely monitor such patients for reactivation.
During prolonged prednisone tablets therapy, patients with latent tuberculosis or tuberculin reactivity should receive chemoprophylaxis. Varicella Zoster and Measles Viral Infections Varicella and measles can have a serious or even fatal course in non-immune patients taking corticosteroids, including prednisone tablets. In corticosteroid-treated patients who have not had these diseases or are non-immune, particular care should be taken to avoid exposure to varicella and measles: • If a prednisone tablets-treated patient is exposed to varicella, prophylaxis with varicella zoster immune globulin may be indicated.
If varicella develops, treatment with antiviral agents may be considered. • If a prednisone tablets-treated patient is exposed to measles, prophylaxis with immunoglobulin may be indicated. Hepatitis B Virus Reactivation Hepatitis B virus reactivation can occur in patients who are hepatitis B carriers treated with immunosuppressive dosages of corticosteroids, including prednisone tablets. Reactivation can also occur infrequently in corticosteroid-treated patients who appear to have resolved hepatitis B infection.
Screen patients for hepatitis B infection before initiating immunosuppressive (e.g., prolonged) treatment with prednisone tablets. For patients who show evidence of hepatitis B infection, recommend consultation with physicians with expertise in managing hepatitis B regarding monitoring and consideration for hepatitis B antiviral therapy. Fungal Infections Corticosteroids, including prednisone tablets, may exacerbate systemic fungal infections; therefore, avoid prednisone tablets use in the presence of such infections unless prednisone tablets are needed to control drug reactions.
For patients on chronic prednisone tablets therapy who develop systemic fungal infections, prednisone tablets withdrawal or dosage reduction is recommended. Amebiasis Corticosteroids, including prednisone tablets, may activate latent amebiasis. Therefore, it is recommended that latent amebiasis or active amebiasis be ruled out before initiating prednisone tablets in patients who have spent time in the tropics or patients with unexplained diarrhea.
Strongyloides Infestation Corticosteroids, including prednisone tablets, should be used with great care in patients with known or suspected Strongyloides (threadworm) infestation. In such patients, corticosteroid-induced immunosuppression may lead to Strongyloides hyperinfection and dissemination with widespread larval migr… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS (listed alphabetically, under each subsection) The following adverse reactions have been reported with prednisone or other corticosteroids: Allergic Reactions anaphylactoid or hypersensitivity reactions, anaphylaxis, angioedema. Cardiovascular System bradycardia, cardiac arrest, cardiac arrhythmias, cardiac enlargement, circulatory collapse, congestive heart failure, ECG changes caused by potassium deficiency, edema, fat embolism, hypertension or aggravation of hypertension, hypertrophic cardiomyopathy in premature infants, myocardial rupture following recent myocardial infarction (see WARNINGS: Cardio-Renal ), necrotizing angiitis, pulmonary edema, syncope, tachycardia, thromboembolism, thrombophlebitis, vasculitis.
Dermatologic acne, acneiform eruptions, allergic dermatitis, alopecia, angioedema, angioneurotic edema, atrophy and thinning of skin, dry scaly skin, ecchymoses and petechiae (bruising), erythema, facial edema, hirsutism, impaired wound healing, increased sweating, Karposi’s sarcoma (see WARNINGS: General: Kaposi's Sarcoma ), lupus erythematosus-like lesions, perineal irritation, purpura, rash, striae, subcutaneous fat atrophy, suppression of reactions to skin tests, striae, telangiectasis, thin fragile skin, thinning scalp hair, urticaria.
Endocrine Adrenal insufficiency-greatest potential caused by high potency glucocorticoids with long duration of action (associated symptoms include: arthralgias, buffalo hump, dizziness, life-threatening hypotension, nausea, severe tiredness or weakness), amenorrhea, postmenopausal bleeding or other menstrual irregularities, decreased carbohydrate and glucose tolerance, development of cushingoid state, diabetes mellitus (new onset or manifestations of latent), glycosuria, hyperglycemia, hypertrichosis, hyperthyroidism (see WARNINGS: Endocrine ), hypothyroidism, increased requirements for insulin or oral hypoglycemic agents in diabetics, lipids abnormal, moon face, negative nitrogen balance caused by protein catabolism, secondary adrenocortical and pituitary unresponsiveness (particularly in times of stress, as in trauma, surgery or illness) (see WARNINGS: Endocrine ), suppression of growth in pediatric patients.
Fluid and Electrolyte Disturbances congestive heart failure in susceptible patients, fluid retention, hypokalemia, hypokalemic alkalosis, metabolic alkalosis, hypotension or shock-like reaction, potassium loss, sodium retention with resulting edema. Gastrointestinal abdominal distention, abdominal pain, anorexia which may result in weight loss, constipation, diarrhea, elevation in serum liver enzyme levels (usually reversible upon discontinuation), gastric irritation, hepatomegaly, increased appetite and weight gain, nausea, oropharyngeal candidiasis, pancreatitis, peptic ulcer with possible perforation and hemorrhage, perforation of the small and large intestine (particularly in patients with inflammatory bowel disease), ulcerative esophagitis, vomiting.
Hematologic anemia, neutropenia (including febrile neutropenia). Metabolic negative nitrogen balance due to protein catabolism. Musculoskeletal arthralgias, aseptic necrosis of femoral and humeral heads, increase risk of fracture, loss of muscle mass, muscle weakness, myalgias, osteopenia, osteoporosis (see PRECAUTIONS: Musculoskeletal ), pathologic fracture of long bones, steroid myopathy, tendon rupture (particularly of the Achilles tendon), vertebral compression fractures.
Neurological/Psychiatric amnesia, anxiety, benign intracranial hypertension, convulsions, delirium, dementia (characterized by deficits in memory retention, attention, concentration, mental speed and efficiency, and occupational performance), depression, dizziness, EEG abnormalities, emotional instability and irritability, euphoria, hallucinations, headache, impaired cognition, incidence of severe psychiatric symptoms, increased intracranial pressure with papilledema (pseudotumor cerebri) usually following discontinuation of trea… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
Drug Interactions Amphotericin B Injection and Potassium-Depleting Agents When corticosteroids are administered concomitantly with potassium-depleting agents (e.g., amphotericin B, diuretics ), patients should be observed closely for development of hypokalemia. In addition, there have been cases reported in which concomitant use of amphotericin B and hydrocortisone was followed by cardiac enlargement and congestive heart failure.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Corticosteroids have been shown to be teratogenic in many species when given in doses equivalent to the human dose. Animal studies in which corticosteroids have been given to pregnant mice, rats, and rabbits have yielded an increased incidence of cleft palate in the offspring. There are no adequate and well-controlled studies in pregnant women.
Corticosteroids should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Infants born to mothers who have received substantial doses of corticosteroids during pregnancy should be carefully observed for signs of hypoadrenalism.
🧒 Pediatric Use ▾
Pediatric Use The efficacy and safety of corticosteroids in the pediatric population are based on the well-established course of effect of corticosteroids, which is similar in pediatric and adult populations. Published studies provide evidence of efficacy and safety in pediatric patients for the treatment of nephrotic syndrome (patients > 2 years of age), and aggressive lymphomas and leukemias (patients > 1 month of age). Other indications for pediatric use of corticosteroids, e.g., severe asthma and wheezing, are based on adequate and well-controlled trials conducted in adults, on the premises that the course of the diseases and their pathophysiology are considered to be substantially similar in both populations.
The adverse effects of corticosteroids in pediatric patients are similar to those in adults (see ADVERSE REACTIONS ). Like adults, pediatric patients should be carefully observed with frequent measurements of blood pressure, weight, height, intraocular pressure, and clinical evaluation for the presence of infection, psychosocial disturbances, thromboembolism, peptic ulcers, cataracts, and osteoporosis. Pediatric patients who are treated with corticosteroids by any route, including systemically administered corticosteroids, may experience a decrease in their growth velocity.
This negative impact of corticosteroids on growth has been observed at low systemic doses and in the absence of laboratory evidence of hypothalamic-pituitary-adrenal (HPA) axis suppression (i.e., cosyntropin stimulation and basal cortisol plasma levels). Growth velocity may therefore be a more sensitive indicator of systemic corticosteroid exposure in pediatric patients than some commonly used tests of HPA axis function. The linear growth of pediatric patients treated with corticosteroids should be monitored, and the potential growth effects of prolonged treatment should be weighed against clinical benefits obtained and the availability of treatment alternatives.
In order to minimize the potential growth effects of corticosteroids, pediatric patients should be titrated to the lowest effective dose.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
In particular, the increased risk of diabetes mellitus, fluid retention and hypertension in elderly patients treated with corticosteroids should be considered.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Naturally occurring glucocorticoids (hydrocortisone and cortisone), which also have salt-retaining properties, are used as replacement therapy in adrenocortical deficiency states. Their synthetic analogs are primarily used for their potent anti-inflammatory effects in disorders of many organ systems. Glucocorticoids cause profound and varied metabolic effects. In addition, they modify the body’s immune responses to diverse stimuli.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Prednisone Tablets, USP are available containing 5 mg, 10 mg or 20 mg of prednisone, USP. The 5 mg tablets are white, round, scored tablets debossed with M on one side of the tablet and PS above the score and 5 below the score on the other side. They are available as follows: NDC 0378-0640-01 bottles of 100 tablets NDC 0378-0640-10 bottles of 1000 tablets The 10 mg tablets are white, round, scored tablets debossed with M on one side of the tablet and PS above the score and 10 below the score on the other side.
They are available as follows: NDC 0378-0641-01 bottles of 100 tablets NDC 0378-0641-10 bottles of 1000 tablets The 20 mg tablets are peach, round, scored tablets debossed with M on one side of the tablet and PS above the score and 20 below the score on the other side. They are available as follows: NDC 0378-0642-01 bottles of 100 tablets NDC 0378-0642-05 bottles of 500 tablets NDC 0378-0642-10 bottles of 1000 tablets Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Protect from light and moisture.
Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure.
📋 Description ▾
DESCRIPTION Each tablet for oral administration contains: Prednisone, USP.................................................5 mg, 10 mg and 20 mg Inactive Ingredients Prednisone tablets, USP of 5 mg and 10 mg strengths contain anhydrous lactose, colloidal silicon dioxide, magnesium stearate, microcrystalline cellulose, sodium starch glycolate, and talc. Prednisone tablets of 20 mg strength contain anhydrous lactose, D&C Yellow No. 10 Aluminum Lake, FD&C Yellow No.
6 Aluminum Lake, magnesium stearate, microcrystalline cellulose and sodium starch glycolate. Prednisone tablets contain prednisone which is a glucocorticoid. Glucocorticoids are adrenocortical steroids, both naturally occurring and synthetic, which are readily absorbed from the gastrointestinal tract.
The chemical name for prednisone is pregna-1,4-diene-3,11,20-trione monohydrate,17,21-dihydroxy-. The structural formula is represented below: C 21 H 26 O 5 M.W. 358.43 Prednisone, USP is a white to practically white, odorless, crystalline powder.
It is very slightly soluble in water; slightly soluble in alcohol, chloroform, dioxane, and methanol. structural formula
💬 Information for Patients ▾
Information for Patients Patients should be warned not to discontinue the use of corticosteroids abruptly or without medical supervision. As prolonged use may cause adrenal insufficiency and make patients dependent on corticosteroids, they should advise any medical attendants that they are taking corticosteroids and they should seek medical advice at once should they develop an acute illness including fever or other signs of infection. Following prolonged therapy, withdrawal of corticosteroids may result in symptoms of the corticosteroid withdrawal syndrome including, myalgia, arthralgia, and malaise.
Persons who are on corticosteroids should be warned to avoid exposure to chickenpox or measles. Patients should also be advised that if they are exposed, medical advice should be sought without delay.
⚠️ Precautions ▾
PRECAUTIONS General Precautions The lowest possible dose of corticosteroids should be used to control the condition under treatment. When reduction in dosage is possible, the reduction should be gradual. Since complications of treatment with glucocorticoids are dependent on the size of the dose and the duration of treatment, a risk/benefit decision must be made in each individual case as to dose and duration of treatment and as to whether daily or intermittent therapy should be used.
Cardio-Renal As sodium retention with resultant edema and potassium loss may occur in patients receiving corticosteroids, these agents should be used with caution in patients with congestive heart failure, hypertension, or renal insufficiency. Endocrine Drug-induced secondary adrenocortical insufficiency may be minimized by gradual reduction of dosage. This type of relative insufficiency may persist for up to 12 months after discontinuation of therapy following large doses for prolonged periods; therefore, in any situation of stress occurring during that period, hormone therapy should be reinstituted.
Since mineralocorticoid secretion may be impaired, salt and/or a mineralocorticoid should be administered concurrently. There is an enhanced effect of corticosteroids on patients with hypothyroidism. Gastrointestinal Steroids should be used with caution in active or latent peptic ulcers, diverticulitis, fresh intestinal anastomoses, and nonspecific ulcerative colitis, since they may increase the risk of a perforation.
Signs of peritoneal irritation following gastrointestinal perforation in patients receiving corticosteroids may be minimal or absent. There is an enhanced effect due to decreased metabolism of corticosteroids in patients with cirrhosis. Musculoskeletal Corticosteroids decrease bone formation and increase bone resorption both through their effect on calcium regulation (i.e., decreasing absorption and increasing excretion) and inhibition of osteoblast function.
This, together with a decrease in the protein matrix of the bone secondary to an increase in protein catabolism, and reduced sex hormone production, may lead to inhibition of bone growth in pediatric patients and the development of osteoporosis at any age. Growth and development of infants and children on prolonged corticosteroid therapy should be carefully observed. Special consideration should be given to patients at increased risk of osteoporosis (e.g., postmenopausal women) before initiating corticosteroid therapy.
Inclusion of therapy for osteoporosis prevention or treatment should be considered. To minimize the risk of glucocorticoid-induced bone loss, the smallest possible effective dosage and duration should be used. Lifestyle modification to reduce the risk of osteoporosis (e.g., cigarette smoking cessation, limitation of alcohol consumption, participation in weight-bearing exercise for 30-60 minutes daily) should be encouraged.
Calcium and vitamin D supplementation, bisphosphonate (e.g., alendronate, risedronate), and a weight-bearing exercise program that maintains muscle mass are suitable first-line therapies aimed at reducing the risk of adverse bone effects. Current recommendations suggest that all interventions be initiated in any patient in whom glucocorticoid therapy with at least the equivalent of 5 mg of prednisone for at least 3 months is anticipated; in addition, sex hormone replacement therapy (combined estrogen and progestin in women; testosterone in men) should be offered to such patients who are hypogonadal or in whom replacement is otherwise clinically indicated and biphosphonate therapy should be initiated (if not already) if bone mineral density (BMD) of the lumbar spine and/or hip is below normal.
Neuro-Psychiatric Although controlled clinical trials have shown corticosteroids to be effective in speeding the resolution of acute exacerbations of multiple sclerosis, they do not show that they affect the ultimate outcome or natural history of the disease.… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Systemically administered corticosteroids appear in human milk and could suppress growth, interfere with endogenous corticosteroid production, or cause other untoward effects. Because of the potential for serious adverse reactions in nursing infants from corticosteroids, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility No adequate studies have been conducted in animals to determine whether corticosteroids have a potential for carcinogenesis or mutagenesis. Steroids may increase or decrease motility and number of spermatozoa in some patients.
📚 References ▾
REFERENCES 1. Fekety R. Infections associated with corticosteroids and immunosuppressive therapy.
In: Gorbach SL, Bartlett JG, Blacklow NR, eds. Infectious Diseases . Philadelphia: WBSaunders Company 1992:1050-1.
2. Stuck AE, Minder CE, Frey FJ. Risk of infectious complications in patients taking glucocorticoids.
Rev Infect Dis 1989:11(6):954-63. Manufactured for: Mylan Pharmaceuticals Inc. Morgantown, WV 26505 U.S.A.
Manufactured by: ALPHAPHARM PTY LTD 15 Garnet Street Carole Park QLD 4300 Australia Revised: 6/2024 ALP:PREDT:R3 (3506/2)
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL – 5 mg NDC 0378-0640-01 predniSONE Tablets, USP 5 mg Rx only 100 Tablets Each tablet contains: Prednisone, USP 5 mg Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure. Keep container tightly closed. Keep this and all medication out of the reach of children.
Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Protect from light and moisture. Usual Dosage: See accompanying prescribing information. Manufactured for: Mylan Pharmaceuticals Inc.
Morgantown, WV 26505 U.S.A. Made in Australia Mylan.com 3490/0 RALP0640A Prednisone Tablets, USP 5 mg Bottle Label
PRINCIPAL DISPLAY PANEL – 10 mg NDC 0378-0641-01 predniSONE Tablets, USP 10 mg Rx only 100 Tablets Each tablet contains: Prednisone, USP 10 mg Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure. Keep container tightly closed. Keep this and all medication out of the reach of children.
Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Protect from light and moisture. Usual Dosage: See accompanying prescribing information. Manufactured for: Mylan Pharmaceuticals Inc.
Morgantown, WV 26505 U.S.A. Made in Australia Mylan.com 3501/0 RALP0641A Prednisone Tablets, USP 10 mg Bottle Label
PRINCIPAL DISPLAY PANEL – 20 mg NDC 0378-0642-01 predniSONE Tablets, USP 20 mg Rx only 100 Tablets Each tablet contains: Prednisone, USP 20 mg Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure. Keep container tightly closed. Keep this and all medication out of the reach of children.
Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Protect from light and moisture. Usual Dosage: See accompanying prescribing information. Manufactured for: Mylan Pharmaceuticals Inc.
Morgantown, WV 26505 U.S.A. Made in Australia Mylan.com 3503/0 RALP0642A Prednisone Tablets, USP 20 mg Bottle Label