
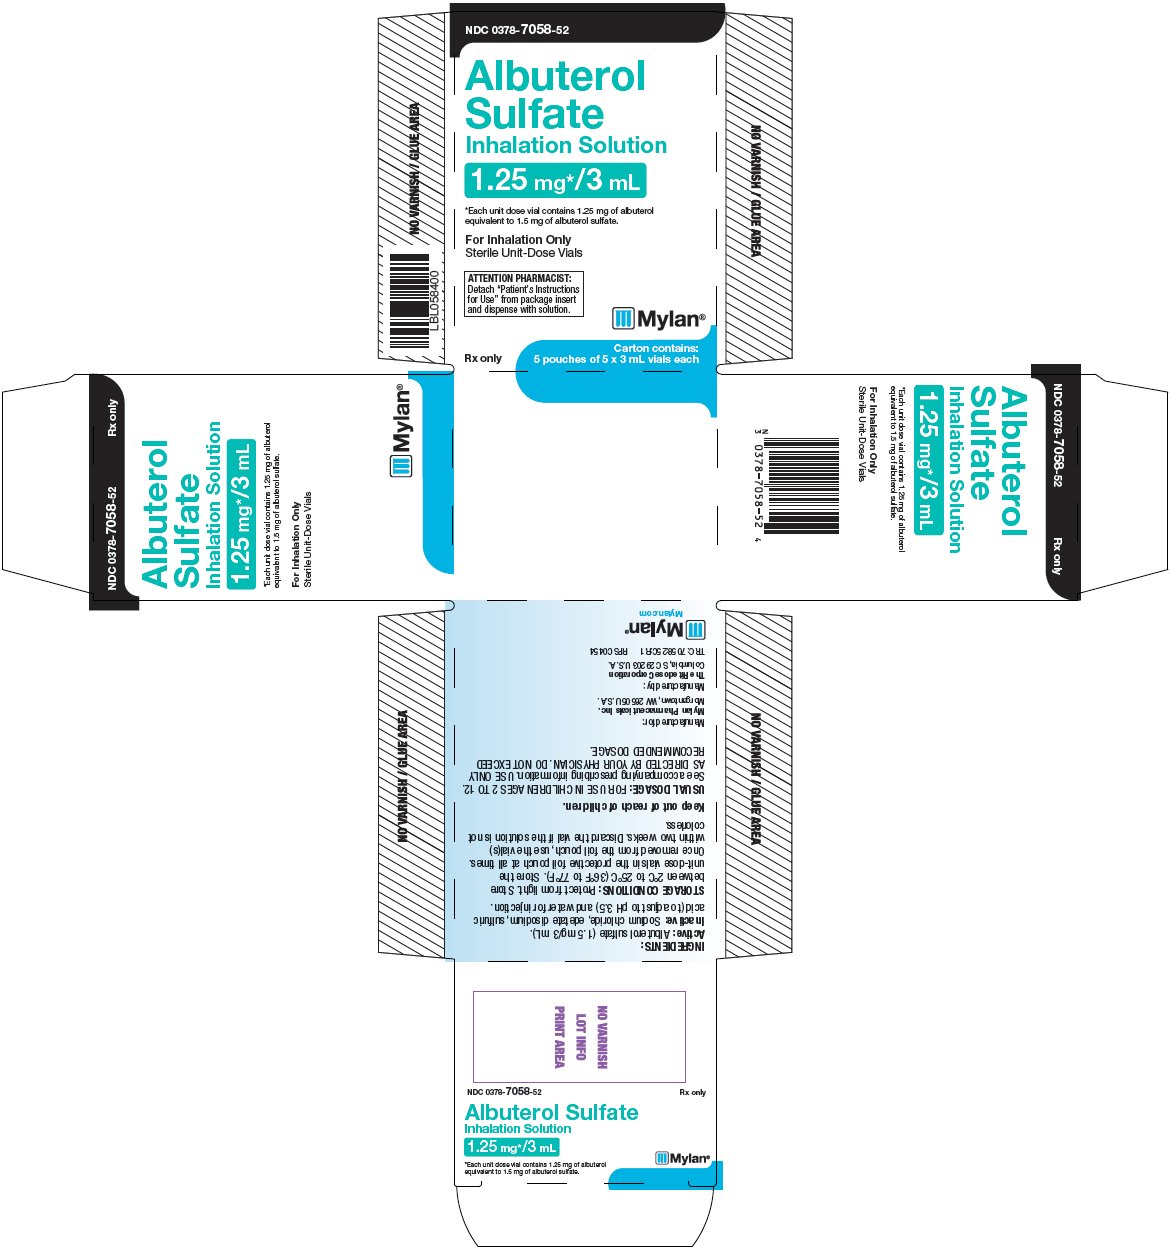
Albuterol 1.25 mg/3mL Solution — NDC 0378-7058-52 (Billing 00378-7058-52)
This is a package of Albuterol 1.25 mg/3mL Solution from Mylan Pharmaceuticals Inc., marketed since Oct 2022 and currently FDA-listed; retail pharmacies pay about $0.1979 per mL (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0378-7058-52 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0378 labeler · 7058 product · 52 package
- Package marketed since
- Oct 7, 2022
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 0378705852 4
- Medicaid fills, this package
- 148,667 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 048699
- GCN: 14634
- GPI-14 (Medi-Span): 44201010102560
- HICL (First Databank): 002073
- AHFS class code: 12:12.08.12
- RxCUI (RxNorm): 351136
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the beta2-Adrenergic Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Albuterol opens up your airways when the muscles around them tighten (bronchospasm), as in asthma. Inhalers and powders are also used before exercise to prevent exercise-induced br...
- It is breathed in through your mouth. The usual pattern for bronchospasm is a couple of puffs every 4 to 6 hours, and before exercise it is used 15 to 30 minutes ahead. Some inhale...
- The most common are throat irritation, cough, upper respiratory irritation, viral respiratory infections and muscle or bone aches. These are usually manageable. Call me or your doc...
- Get help right away if your breathing gets worse after a dose, or if you have hives, swelling of the face or throat, or chest pain or a racing heartbeat. Also call your doctor if y...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Albuterol — tap one for details:
Albuterol may be associated with lower levels of 2 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.198 | $14.84 / 75 ml |
| Medicaid paysCMS SDUD · 12 mo | $0.2372 | $17.79 / 75 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J7613 | $0.063 / J7613 unit | — |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Oct 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00378-7058-52 You're viewing this Main listing | 5 POUCH in 1 CARTON / 5 VIAL in 1 POUCH / 3 mL in 1 VIAL | 2022-10-07 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Albuterol 1.25 mg/3mLthis 00378-7058-52 | Mylan | 5 pouches | $0.198 | AN | Availability likely | — |
| Albuterol Sulfate 1.25 mg/3mL 50742-0393-25 | Ingenus | 5 pouches | $0.198 | AN | Availability likely | — |
| Albuterol Sulfate 1.25 mg/3mL 62135-0827-84 | Chartwell | 30 pouches | $0.220 | AN | Availability likely | +11% |
| Albuterol Sulfate 1.25 mg/3mL 00487-9904-01 | Nephron | 30 pouches | $0.226 | AN | Availability likely | +14% |
| Albuterol Sulfate Inhalation Solution 1.25 mg/3mL 76204-0011-01 | Ritedose | 30 pouches | $0.226 | AN | Availability likely | +14% |
| Albuterol Sulfate 1.25 mg/3mL 59651-0184-25 | Aurobindo | 25 pouches | — | AN | FDA listed | — |
| Albuterol Sulfate 1.25 mg/3mL 64980-0644-02 | Rising | 25 pouches | — | AN | FDA listed | — |
| Albuterol Sulfate 1.25 mg/3mL 81894-0106-25 | Luoxin | 5 pouches | — | AN | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Albuterol inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII O40UQP6WCF
A strong acid used in small amounts to adjust and maintain the pH balance of a medicine, helping ensure stability and proper dissolution of the active ingredients.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Mylan Pharmaceuticals Inc. labeler code 00378
- Paroxetine 30 mg Tablet, Film Coated NDC 0378-7003-10
- Paroxetine 40 mg Tablet, Film Coated NDC 0378-7004-10
- Acitretin 10 mg Capsule NDC 0378-7020-93
- Acitretin 25 mg Capsule NDC 0378-7023-93
- Bepotastine Besilate 15 mg/mL Solution/ Drops NDC 0378-7055-35
- Albuterol .63 mg/3mL Solution NDC 0378-7057-52
- Bromocriptine Mesylate 5 mg Capsule NDC 0378-7096-01
- Metformin Hydrochloride 500 mg Tablet, Film Coated NDC 0378-7185-05
- Metformin Hydrochloride 850 mg Tablet, Film Coated NDC 0378-7186-05
- Metformin Hydrochloride 1000 mg Tablet, Film Coated NDC 0378-7187-05
- Norethindrone Acetate and Ethinyl Estradiol .03 mg; 1.5 mg Tablet NDC 0378-7274-53
- Norethindrone Acetate and Ethinyl Estradiol .02 mg; 1 mg Tablet NDC 0378-7280-53
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Albuterol Inhalation Solution is indicated for the relief of bronchospasm in patients 2 to 12 years of age with asthma (reversible obstructive airway disease).
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The usual starting dosage for patients 2 to 12 years of age is 1.25 mg or 0.63 mg of Albuterol Inhalation Solution administered 3 or 4 times daily, as needed, by nebulization. More frequent administration is not recommended. To administer 1.25 mg or 0.63 mg of albuterol, use the entire contents of one unit-dose vial (3 mL of 1.25 mg or 0.63 mg inhalation solution) by nebulization.
Adjust nebulizer flow rate to deliver Albuterol Inhalation Solution over 5 to 15 minutes. The use of Albuterol Inhalation Solution can be continued as medically indicated to control recurring bouts of bronchospasm. During this time most patients gain optimum benefit from regular use of the inhalation solution.
Patients 6 to 12 years of age with more severe asthma (baseline FEV 1 less than 60% predicted), weight > 40 kg, or patients 11 to 12 years of age may achieve a better initial response with the 1.25 mg dose. Albuterol Inhalation Solution has not been studied in the setting of acute attacks of bronchospasm. A 2.5 mg dose of albuterol provided by a higher concentration product (2.5 mg albuterol per 3 mL) may be more appropriate for treating acute exacerbations, particularly in children 6 years old and above.
If a previously effective dosage regimen fails to provide the usual relief, medical advice should be sought immediately, as this is often a sign of seriously worsening asthma which would require reassessment of therapy. The drug compatibility (physical and chemical), clinical efficacy and safety of Albuterol Inhalation Solution, when mixed with other drugs in a nebulizer have not been established. The safety and efficacy of Albuterol Inhalation Solution have been established in clinical trials when administered using the Pari LC Plus™ nebulizer and Pari PRONEB™ compressor.
The safety and efficacy of Albuterol Inhalation Solution when administered with other nebulizer systems have not been established. Albuterol Inhalation Solution should be administered via jet nebulizer connected to an air compressor with adequate air flow, equipped with a mouthpiece or suitable face mask.
⛔ Contraindications ▾
CONTRAINDICATIONS Albuterol Inhalation Solution is contraindicated in patients with a history of hypersensitivity to any of its components.
⚠️ Warnings ▾
WARNINGS Paradoxical Bronchospasm As with other inhaled beta-adrenergic agonists, Albuterol Inhalation Solution can produce paradoxical bronchospasm, which may be life threatening. If paradoxical bronchospasm occurs, Albuterol Inhalation Solution should be discontinued immediately and alternative therapy instituted. It should be noted that paradoxical bronchospasm, when associated with inhaled formulations, frequently occurs with the first use of a new canister or vial.
Use of Anti-Inflammatory Agents The use of beta-adrenergic bronchodilators alone may not be adequate to control asthma in many patients. Early consideration should be given to adding anti-inflammatory agents (e.g., corticosteroids). Deterioration of Asthma Asthma may deteriorate acutely over a period of hours or chronically over several days or longer.
If the patient needs more doses of Albuterol Inhalation Solution than usual, this may be a marker of destabilization of asthma and requires re-evaluation of the patient and the treatment regimen, giving special consideration of the possible need for anti-inflammatory treatment (e.g., corticosteroids). Fatalities have been reported in association with excessive use of inhaled sympathomimetic drugs and with the home use of nebulizers. It is, therefore, essential that the physician instruct the patient in the need for further evaluation, if his/her asthma becomes worse.
Cardiovascular Effects Albuterol Inhalation Solution, like other beta-adrenergic agonists, can produce a clinically significant cardiovascular effect in some patients as measured by pulse rate, blood pressure, and/or symptoms. Although such effects are uncommon for Albuterol Inhalation Solution at recommended doses, if they occur, the drug may need to be discontinued. In addition, beta-agonists have been reported to produce ECG changes, such as flattening of the T-wave, prolongation of the QTc interval, and ST segment depression.
The clinical significance of these findings is unknown. Therefore, Albuterol Inhalation Solution like all other sympathomimetic amines, should be used with caution in patients with cardiovascular disorders, especially coronary insufficiency, cardiac arrhythmias, and hypertension. Immediate Hypersensitivity Reactions Immediate hypersensitivity reactions may occur after administration of albuterol as demonstrated by rare cases of urticaria, angioedema, rash, bronchospasm, and oropharyngeal edema.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Clinical Trial Experience Adverse events reported in >1% of patients receiving Albuterol Inhalation Solution and more frequently than in patients receiving placebo in a four-week double-blind study are listed in the following table. Table 1: Adverse Events with an Incidence of >1% of Patients Receiving Albuterol Inhalation Solution and Greater than Placebo (expressed as % of treatment group) 1.25 mg Albuterol Inhalation Solution (N=115) 0.63 mg Albuterol Inhalation Solution (N=117) Placebo (N=117) Asthma Exacerbation 13 11.1
8.5Otitis Media 4.3 0.9 0 Allergic Reaction 0.9 3.4
1.7Gastroenteritis 0.9 3.4
0.9Cold Symptoms 0 3.4
1.7Flu Syndrome 2.6 2.6
1.7Lymphadenopathy 2.6 0.9
1.7Skin/Appendage Infection 1.7 0 0 Urticaria 1.7 0.9 0 Migraine 0.9 1.7 0 Chest Pain 0.9 1.7 0 Bronchitis 0.9 1.7
0.9Nausea 1.7 0.9
0.9There was one case of ST segment depression in the 1.25 mg Albuterol Inhalation Solution treatment group. No clinically relevant laboratory abnormalities related to Albuterol Inhalation Solution administration were seen in this study. Postmarketing Experience Metabolic acidosis has been reported after the use of albuterol inhalation solution.
Because this reaction is reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate its frequency or establish a causal relationship to drug exposure.
🔄 Drug Interactions ▾
Drug Interactions Other short-acting sympathomimetic aerosol bronchodilators or epinephrine should not be used concomitantly with albuterol inhalation solution. Albuterol Inhalation Solution should be administered with extreme caution to patients being treated with monoamine oxidase inhibitors or tricyclic antidepressants or within 2 weeks of discontinuation of such agents, since the action of albuterol on the vascular system may be potentiated. Beta-receptor blocking agents not only block the pulmonary effect of beta-agonists, such as Albuterol Inhalation Solution, but may produce severe bronchospasm in asthmatic patients.
Therefore, patients with asthma should not normally be treated with beta-blockers. However, under certain circumstances (e.g., prophylaxis after myocardial infarction), there may be no acceptable alternatives to the use of beta-adrenergic blocking agents in patients with asthma. In this setting, cardioselective beta-blockers should be considered, although they should be administered with caution.
The ECG changes and/or hypokalemia that may result from the administration of non-potassium sparing diuretics (such as loop or thiazide diuretics) can be acutely worsened by beta-agonists, especially when the dose of the beta-agonist is exceeded. Although the clinical significance of these effects is unknown, caution is advised in the co-administration of beta-agonists with non-potassium sparing diuretics. Mean decreases of 16% to 22% in serum digoxin levels were demonstrated after single dose intravenous and oral administration of albuterol, respectively, to normal volunteers who had received digoxin for 10 days.
The clinical significance of these findings for patients with obstructive airway disease who are receiving albuterol and digoxin on a chronic basis is unclear. Nevertheless, it would be prudent to carefully evaluate the serum digoxin levels in patients who are currently receiving digoxin and albuterol.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Albuterol has been shown to be teratogenic in mice. A study in CD-1 mice given albuterol subcutaneously showed cleft palate formation in 5 of 111 (4.5%) fetuses at 0.25 mg/kg (less than the maximum recommended daily inhalation dose of Albuterol Inhalation Solution on a mg/m 2 basis) and cleft palate formation in 10 of 108 (9.3%) fetuses at 2.5 mg/kg (approximately equal to the maximum recommended daily inhalation dose of Albuterol Inhalation Solution on a mg/m 2 basis). The drug did not induce cleft palate formation when administered subcutaneously at a dose of 0.025 mg/kg (less than the maximum recommended daily inhalation dose of Albuterol Inhalation Solution on a mg/m 2 basis).
Cleft palate formation also occurred in 23 of 72 (30.5%) fetuses from females treated subcutaneously with 2.5 mg/kg isoproterenol (positive control). A reproduction study in Stride rabbits revealed cranioschisis in 7 of 19 (37%) fetuses when albuterol sulfate was administered orally at 50 mg/kg (approximately 60 times the maximum recommended daily inhalation dose of Albuterol Inhalation Solution on a mg/m 2 basis). A study in which pregnant rats were dosed with radiolabeled albuterol sulfate demonstrated that drug-related material was transferred from the maternal circulation to the fetus.
There are no adequate and well-controlled studies of the use of albuterol sulfate in pregnant women. Albuterol should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. During worldwide marketing experience, various congenital anomalies, including cleft palate and limb defects, have been reported in the offspring of patients being treated with albuterol.
Some of the mothers were taking multiple medications during their pregnancies. Because no consistent pattern of defects can be discerned, a relationship between albuterol use and congenital anomalies has not been established.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness of Albuterol Inhalation Solution 1.25 mg and 0.63 mg have been established in pediatric patients between the ages of 2 and 12 years. The use of Albuterol Inhalation Solution in these age groups is supported by evidence from adequate and well-controlled studies of Albuterol Inhalation Solution in children age 6 to 12 years and published reports of albuterol sulfate trials in pediatric patients 3 years of age and older. The safety and effectiveness of Albuterol Inhalation Solution in children below 2 years of age have not been established.
🆘 Overdosage ▾
OVERDOSAGE The expected symptoms with overdosage are those of excessive beta-adrenergic stimulation and/or occurrence or exaggeration of symptoms such as seizures, angina, hypertension or hypotension, tachycardia with rates up to 200 beats per minute, arrhythmias, nervousness, headache, tremor, dry mouth, palpitation, nausea, dizziness, fatigue, malaise, insomnia, and exaggeration of the pharmacological effects listed in ADVERSE REACTIONS . Hypokalemia may also occur. As with all sympathomimetic aerosol medications, cardiac arrest and even death may be associated with abuse of Albuterol Inhalation Solution.
Treatment consists of discontinuation of Albuterol Inhalation Solution together with appropriate symptomatic therapy. The judicious use of a cardioselective beta-receptor blocker may be considered, bearing in mind that such medication can produce bronchospasm. There is insufficient evidence to determine if dialysis is beneficial for overdosage of Albuterol Inhalation Solution.
The oral median lethal dose of albuterol sulfate in mice is greater than 2000 mg/kg (approximately 580 times the maximum recommended daily inhalation dose of Albuterol Inhalation Solution on a mg/m 2 basis). The subcutaneous median lethal dose of albuterol sulfate in mature rats and small young rats is approximately 450 mg/kg and 2000 mg/kg, respectively (approximately 260 and 1200 times the maximum recommended daily inhalation dose of Albuterol Inhalation Solution on a mg/m 2 basis). The inhalation median lethal dose has not been determined in animals.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY The prime action of beta-adrenergic drugs is to stimulate adenyl cyclase, the enzyme which catalyzes the formation of cyclic-3’,5’-adenosine monophosphate (cyclic AMP) from adenosine triphosphate (ATP). The cyclic AMP thus formed mediates the cellular responses. In vitro studies and in vivo pharmacologic studies have demonstrated that albuterol has a preferential effect on beta 2 -adrenergic receptors compared with isoproterenol.
While it is recognized that beta 2 -adrenergic receptors are the predominant receptors in bronchial smooth muscle, recent data indicate that 10% to 50% of the beta-receptors in the human heart may be beta 2 -receptors. The precise function of these receptors, however, is not yet established. Controlled clinical studies and other clinical experience have shown that inhaled albuterol, like other beta-adrenergic agonist drugs, can produce a significant cardiovascular effect in some patients, as measured by pulse rate, blood pressure, symptoms, and/or electrocardiographic changes.
Albuterol is longer acting than isoproterenol in most patients by any route of administration because it is not a substrate for the cellular uptake processes for catecholamines nor for catechol-O-methyl transferase. Pharmacokinetics Studies in asthmatic patients have shown that less than 20% of a single albuterol dose was absorbed following either intermittent positive-pressure breathing (IPPB) or nebulizer administration; the remaining amount was recovered from the nebulizer and apparatus, and expired air. Most of the absorbed dose was recovered in urine collected during the 24 hours after drug administration.
Following oral administration of 4 mg albuterol, the elimination half-life was five to six hours. Following a 3 mg dose of nebulized albuterol in adults, the mean maximum albuterol plasma level at 0.5 hours was 2.1 ng/mL (range, 1.4 to 3.2 ng/mL). The pharmacokinetics of albuterol following administration of 0.63 mg or 1.25 mg albuterol inhalation solution by nebulization have not been determined in children 2 to 12 years old.
Animal Pharmacology/Toxicology Intravenous studies in rats with albuterol sulfate have demonstrated that albuterol crosses the blood-brain barrier and reaches brain concentrations amounting to approximately 5% of plasma concentrations. In structures outside the blood-brain barrier (pineal and pituitary glands), albuterol concentrations were found to be 100 times those found in whole brain. Studies in laboratory animals (minipigs, rodents, and dogs) have demonstrated the occurrence of cardiac arrhythmias and sudden death (with histologic evidence of myocardial necrosis) when beta-agonists and methylxanthines are administered concurrently.
The clinical significance of these findings is unknown. Clinical Trials The safety and efficacy of Albuterol Inhalation Solution was evaluated in a 4-week, multi-center, randomized, double-blind, placebo-controlled, parallel group study in 349 children 6 to 12 years of age with mild-to-moderate asthma (mean baseline FEV 1 60% to 70% of predicted). Approximately half of the patients were also receiving inhaled corticosteroids.
Patients were randomized to receive Albuterol Inhalation Solution 0.63 mg, Albuterol Inhalation Solution 1.25 mg, or placebo three times a day administered via a Pari LC Plus™ nebulizer and a Pari PRONEB™ compressor. Racemic albuterol, delivered by a chlorofluorocarbon (CFC) metered dose inhaler (MDI) or nebulized, was used on an as-needed basis as the rescue medication. Efficacy, as measured by the mean percent change from baseline in the area under the 6-hour curve for FEV 1 , was demonstrated for both active treatment regimens (n=112 [1.25 mg group] and n=110 [0.63 mg group]) compared with placebo (n=110) on day 1 and day 28.
Figures 1 and 2 illustrate the mean percentage change from pre-dose FEV 1 on day 1 and day 28, respectively. The mean baseline FEV 1 for all patients was
1.49L. Figure 1 % Change from Pre-Dose FEV… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Albuterol Inhalation Solution, USP is supplied as a 3 mL, clear, colorless, sterile, preservative-free, aqueous solution in two different strengths, 0.63 mg/3 mL and 1.25 mg/3 mL, of albuterol (equivalent to 0.75 mg of albuterol sulfate or 1.5 mg of albuterol sulfate per 3 mL) in unit-dose low-density polyethylene (LDPE) vials. Each unit-dose LDPE vial is protected in a foil pouch, and each foil pouch contains 5 unit-dose LDPE vials. Each strength of Albuterol Inhalation Solution, USP is available in a shelf carton containing multiple foil pouches.
Albuterol Inhalation Solution, USP, 0.63 mg/3 mL (potency expressed as albuterol) contains 0.75 mg albuterol sulfate per 3 mL in unit-dose vials and is available in the following packaging configuration. NDC 0378-7057-52 5 foil pouches, each containing 5 vials, total 25 vials per carton Albuterol Inhalation Solution, USP, 1.25 mg/3 mL (potency expressed as albuterol) contains 1.5 mg albuterol sulfate per 3 mL in unit-dose vials and is available in the following packaging configuration. NDC 0378-7058-52 5 foil pouches, each containing 5 vials, total 25 vials per carton Rx only STORAGE Store between 2°C to 25°C (36°F to 77°F).
Protect from light and excessive heat. Store unit-dose vials in protective foil pouch until time of use. Discard the vial if the solution is not colorless.
Keep out of the reach of children. The brands listed are trademarks of their respective owners. Distributed by: Mylan Pharmaceuticals Inc., a Viatris Company Morgantown, WV 26505 U.S.A.
Manufactured by: The Ritedose Corporation Columbia, SC 29203 U.S.A. TRC:ASISLD:R3 RPIN0222 March 2026
📋 Description ▾
DESCRIPTION Albuterol inhalation solution, USP is a sterile, clear, colorless solution of the sulfate salt of racemic albuterol, albuterol sulfate. Albuterol sulfate is a relatively selective beta 2 - adrenergic bronchodilator (see CLINICAL PHARMACOLOGY ). The chemical name for albuterol sulfate is α 1 [(tert-butylamino) methyl]-4-hydroxy-m-xylene-α, α’-diol sulfate (2:1) (salt), and its established chemical structure is as follows: The molecular weight of albuterol sulfate is 576.7 and the empirical formula is (C 13 H 21 NO 3 ) 2 • H 2 SO 4 .
Albuterol sulfate is a white crystalline powder, soluble in water and slightly soluble in ethanol. The World Health Organization recommended name for albuterol is salbutamol. Albuterol Inhalation Solution, USP is supplied in two strengths in unit dose vials.
Each unit dose vial contains either 0.63 mg of albuterol equivalent to 0.75 mg of albuterol sulfate or 1.25 mg of albuterol equivalent to 1.5 mg of albuterol sulfate with sodium chloride, edetate disodium (EDTA), and sulfuric acid in a 3-mL isotonic, sterile, aqueous solution. Sodium chloride is added to adjust isotonicity of the solution, EDTA is added as a stabilizer for the active pharmaceutical ingredient, and sulfuric acid is added to adjust pH of the solution to 3.5 (see HOW SUPPLIED ). Albuterol Inhalation Solution, USP does not require dilution prior to administration by nebulization.
For Albuterol Inhalation Solution, USP, like all other nebulized treatments, the amount delivered to the lungs will depend on patient factors, the jet nebulizer utilized, and compressor performance. Using the Pari LC Plus™ nebulizer (with face mask or mouthpiece) connected to a Pari PRONEB™ compressor, under in vitro conditions, the mean delivered dose from the mouth piece (% nominal dose) was approximately 43% of albuterol (1.25 mg strength) and 39% of albuterol (0.63 mg strength) at a mean flow rate of
3.6L/min. The mean nebulization time was 15 minutes or less. Albuterol Inhalation Solution, USP should be administered from a jet nebulizer at an adequate flow rate, via a mouthpiece or face mask (see DOSAGE AND ADMINISTRATION ). Albuterol Sulfate Structural Formula
💬 Information for Patients ▾
Information for Patients The action of Albuterol Inhalation Solution may last up to six hours, and therefore it should not be used more frequently than recommended. Do not increase the dose or frequency of medication without consulting your physician. If you find that treatment with Albuterol Inhalation Solution becomes less effective for symptomatic relief, your symptoms become worse, and/or you need to use the product more frequently than usual, you should seek medical attention immediately.
All asthma medication should only be used under the supervision and direction of a physician. Common effects with medications such as Albuterol Inhalation Solution include palpitations, chest pain, rapid heart rate, tremor, or nervousness. If you are pregnant or nursing, contact your physician about the use of Albuterol Inhalation Solution.
Effective and safe use of Albuterol Inhalation Solution includes an understanding of the way it should be administered. If the solution in the vial changes color or becomes cloudy, you should not use it. The drug compatibility (physical and chemical), clinical efficacy, and safety of Albuterol Inhalation Solution, when mixed with other drugs in a nebulizer, has not been established.
See illustrated Patient’s Instructions for Use .
⚠️ Precautions ▾
PRECAUTIONS General Large doses of intravenous albuterol have been reported to aggravate pre-existing diabetes mellitus and ketoacidosis. As with other beta-agonists, inhaled and intravenous albuterol may produce a significant hypokalemia in some patients, possibly through intracellular shunting, which has the potential to produce adverse cardiovascular effects. The decrease is usually transient, not requiring potassium supplementation.
Information for Patients The action of Albuterol Inhalation Solution may last up to six hours, and therefore it should not be used more frequently than recommended. Do not increase the dose or frequency of medication without consulting your physician. If you find that treatment with Albuterol Inhalation Solution becomes less effective for symptomatic relief, your symptoms become worse, and/or you need to use the product more frequently than usual, you should seek medical attention immediately.
All asthma medication should only be used under the supervision and direction of a physician. Common effects with medications such as Albuterol Inhalation Solution include palpitations, chest pain, rapid heart rate, tremor, or nervousness. If you are pregnant or nursing, contact your physician about the use of Albuterol Inhalation Solution.
Effective and safe use of Albuterol Inhalation Solution includes an understanding of the way it should be administered. If the solution in the vial changes color or becomes cloudy, you should not use it. The drug compatibility (physical and chemical), clinical efficacy, and safety of Albuterol Inhalation Solution, when mixed with other drugs in a nebulizer, has not been established.
See illustrated Patient’s Instructions for Use . Drug Interactions Other short-acting sympathomimetic aerosol bronchodilators or epinephrine should not be used concomitantly with albuterol inhalation solution. Albuterol Inhalation Solution should be administered with extreme caution to patients being treated with monoamine oxidase inhibitors or tricyclic antidepressants or within 2 weeks of discontinuation of such agents, since the action of albuterol on the vascular system may be potentiated.
Beta-receptor blocking agents not only block the pulmonary effect of beta-agonists, such as Albuterol Inhalation Solution, but may produce severe bronchospasm in asthmatic patients. Therefore, patients with asthma should not normally be treated with beta-blockers. However, under certain circumstances (e.g., prophylaxis after myocardial infarction), there may be no acceptable alternatives to the use of beta-adrenergic blocking agents in patients with asthma.
In this setting, cardioselective beta-blockers should be considered, although they should be administered with caution. The ECG changes and/or hypokalemia that may result from the administration of non-potassium sparing diuretics (such as loop or thiazide diuretics) can be acutely worsened by beta-agonists, especially when the dose of the beta-agonist is exceeded. Although the clinical significance of these effects is unknown, caution is advised in the co-administration of beta-agonists with non-potassium sparing diuretics.
Mean decreases of 16% to 22% in serum digoxin levels were demonstrated after single dose intravenous and oral administration of albuterol, respectively, to normal volunteers who had received digoxin for 10 days. The clinical significance of these findings for patients with obstructive airway disease who are receiving albuterol and digoxin on a chronic basis is unclear. Nevertheless, it would be prudent to carefully evaluate the serum digoxin levels in patients who are currently receiving digoxin and albuterol.
Carcinogenesis, Mutagenesis, and Impairment of Fertility In a 2-year study in Sprague-Dawley rats, albuterol sulfate caused a significant dose-related increase in the incidence of benign leiomyomas of the mesovarium and above dietary doses of 2 mg/kg (approximately equivalent to the maximum recommended daily inhalation dos… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers It is not known whether this drug is excreted in human milk. Because of the potential for tumorigenicity shown for albuterol in some animal studies, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
🧬 Pharmacokinetics ▾
Pharmacokinetics Studies in asthmatic patients have shown that less than 20% of a single albuterol dose was absorbed following either intermittent positive-pressure breathing (IPPB) or nebulizer administration; the remaining amount was recovered from the nebulizer and apparatus, and expired air. Most of the absorbed dose was recovered in urine collected during the 24 hours after drug administration. Following oral administration of 4 mg albuterol, the elimination half-life was five to six hours.
Following a 3 mg dose of nebulized albuterol in adults, the mean maximum albuterol plasma level at 0.5 hours was 2.1 ng/mL (range, 1.4 to 3.2 ng/mL). The pharmacokinetics of albuterol following administration of 0.63 mg or 1.25 mg albuterol inhalation solution by nebulization have not been determined in children 2 to 12 years old.
📄 Patient Package Insert ▾
Patient Information Albuterol Inhalation Solution, USP (al bue' ter ol) 0.63 mg/3 mL and 1.25 mg/3 mL Read the patient information that comes with Albuterol Inhalation Solution before using it and each time you get a refill for your child. There may be new information. This leaflet does not take the place of talking to your child’s doctor about your child’s medical condition or treatment.
What is Albuterol Inhalation Solution? Albuterol Inhalation Solution is a medicine that is used for the relief of bronchospasms caused by asthma in children ages 2 to 12 years. Bronchospasm is the tightening and swelling of the muscles around the airways.
Albuterol Inhalation Solution can help relax these airway muscles for up to 6 hours so that your child may breathe more easily. Who should not use Albuterol Inhalation Solution? Do not give your child Albuterol Inhalation Solution if he or she is allergic to any of its ingredients.
The active ingredient is albuterol sulfate. See the end of this leaflet for a complete list of ingredients. What should I tell my child’s doctor before giving Albuterol Inhalation Solution?
Tell your child’s doctor about all of your child’s medical conditions including if your child has: • Heart problems • High blood pressure • Seizures • A thyroid problem called hyperthyroidism • Diabetes Tell your child’s doctor about all the medicines your child takes, including prescription and non-prescription medicines, vitamins and herbal supplements. Albuterol Inhalation Solution and some other medicines can affect each other and may cause serious side effects. Especially tell your child’s doctor if your child is taking or using: • Any short-acting bronchodilator medicines (sometimes called rescue inhalers) • Epinephrine • Medicines called monoamine oxidase inhibitors (MAOIs) or tricyclic anti-depressants or has stopped taking them in the past 2 weeks.
These medicines are usually used for mental problems. • Medicines called beta-blockers (used for heart problems and high blood pressure) • Certain diuretic medicines (water pills) • Digoxin Know the medicines your child takes. Keep a list of them and show it to your child’s doctor and pharmacist each time your child gets a new medicine. How should Albuterol Inhalation Solution be given?
Read the Patient’s Instructions for Use that comes with Albuterol Inhalation Solution. Ask your pharmacist for these instructions if they are not with your medicine. Keep the instructions with Albuterol Inhalation Solution because you may want to read them again. • Give Albuterol Inhalation Solution exactly as prescribed for your child.
Do not change your child’s dose or how often it is used without talking to your child’s doctor first. • Albuterol Inhalation Solution is breathed into the lungs. Albuterol Inhalation Solution is used with a special breathing machine called a nebulizer. Do not mix other medicines with Albuterol Inhalation Solution in the nebulizer.
Do not use Albuterol Inhalation Solution that is not clear and colorless. • Call your child’s doctor or get emergency help right away if your child’s breathing is not helped or gets worse during treatment with Albuterol Inhalation Solution. • Call your child’s doctor right away if your child needs to use Albuterol Inhalation Solution more often than prescribed. • Albuterol Inhalation Solution has not been studied for treating acute attacks of bronchospasm (rescue use). Your child may need a different medicine for rescue use. • If you give your child too much Albuterol Inhalation Solution call your child’s doctor right away.
What are the side effects with Albuterol Inhalation Solution? Albuterol Inhalation Solution may cause the following serious side effects: • Worsening of the tightening and swelling of the muscles around your child’s airways (bronchospasm). This side effect can be life threatening.
Call your child’s doctor or get emergency help right away if your child’s breathing is not helped or gets worse during treatment with A… [Excerpted — this section continues on DailyMed.]
📖 Instructions for Use ▾
Instructions for Use 1. Remove one vial from the foil pouch. Place remaining vials back into foil pouch for storage.
2. Twist the cap completely off the vial and squeeze the contents into the nebulizer reservoir (Figure 1). 3.
Connect the nebulizer to the mouthpiece or face mask (Figure 2). 4. Connect the nebulizer to the compressor.
5. Sit in a comfortable, upright position; place the mouthpiece in your mouth (Figure 3) or put on the face mask (Figure 4); and turn on the compressor. 6.
Breathe as calmly, deeply and evenly as possible through your mouth until no more mist is formed in the nebulizer chamber (about 5-15 minutes). At this point, the treatment is finished. 7.
Clean the nebulizer (see manufacturer’s instructions). Distributed by: Mylan Pharmaceuticals Inc., a Viatris Company Morgantown, WV 26505 U.S.A. Manufactured by: The Ritedose Corporation Columbia, SC 29203 U.S.A.
TRC:PIL:ASISLD:R3 RPIN0222 March 2026 Instructions for Use Figure 1 Instructions for Use Figure 2 Instructions for Use Figures 3 and 4
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL – 0.63 mg/3 mL NDC 0378-7057-52 Albuterol Inhalation Solution, USP 0.63 mg/3 mL For Inhalation Only Sterile Unit-Dose Vials ATTENTION PHARMACIST: Detach “Patient’s Instructions for Use” from package insert and dispense with solution. Rx only Carton contains: 5 pouches of 5 x 3 mL vials each INGREDIENTS: Active: Albuterol sulfate (0.75 mg/3 mL). Inactive: Sodium chloride, edetate disodium, sulfuric acid (to adjust to pH 3.5) and water for injection.
STORAGE CONDITIONS: Protect from light. Store between 2°C to 25°C (36°F to 77°F). Store in the pouch until time of use.
Discard the vial if the solution is not colorless. Keep out of reach of children. USUAL DOSAGE: FOR USE IN CHILDREN AGES 2 TO 12.
See accompanying prescribing information. USE ONLY AS DIRECTED BY YOUR PHYSICIAN. DO NOT EXCEED RECOMMENDED DOSAGE.
Distributed by: Mylan Pharmaceuticals Inc., a Viatris Company Morgantown, WV 26505 U.S.A. Manufactured by: The Ritedose Corporation Columbia, SC 29203 U.S.A. TRC:7057:25C:R2 RPSC0564 Albuterol Sulfate Inhalation Solution 0.63 mg/3 mL Carton Label
PRINCIPAL DISPLAY PANEL – 1.25 mg/3 mL NDC 0378-7058-52 Albuterol Inhalation Solution, USP 1.25 mg/3 mL For Inhalation Only Sterile Unit-Dose Vials ATTENTION PHARMACIST: Detach “Patient’s Instructions for Use” from package insert and dispense with solution. Rx only Carton contains: 5 pouches of 5 x 3 mL vials each INGREDIENTS: Active: Albuterol sulfate (1.5 mg/3 mL). Inactive: Sodium chloride, edetate disodium, sulfuric acid (to adjust to pH 3.5) and water for injection.
STORAGE CONDITIONS: Protect from light. Store between 2°C to 25°C (36°F to 77°F). Store in the pouch until time of use.
Discard the vial if the solution is not colorless. Keep out of reach of children. USUAL DOSAGE: FOR USE IN CHILDREN AGES 2 TO 12.
See accompanying prescribing information. USE ONLY AS DIRECTED BY YOUR PHYSICIAN. DO NOT EXCEED RECOMMENDED DOSAGE.
Distributed by: Mylan Pharmaceuticals Inc., a Viatris Company Morgantown, WV 26505 U.S.A. Manufactured by: The Ritedose Corporation Columbia, SC 29203 U.S.A. TRC:7058:25C:R2 RPSC0565 Albuterol Sulfate Inhalation Solution 1.25 mg/3 mL Carton Label