
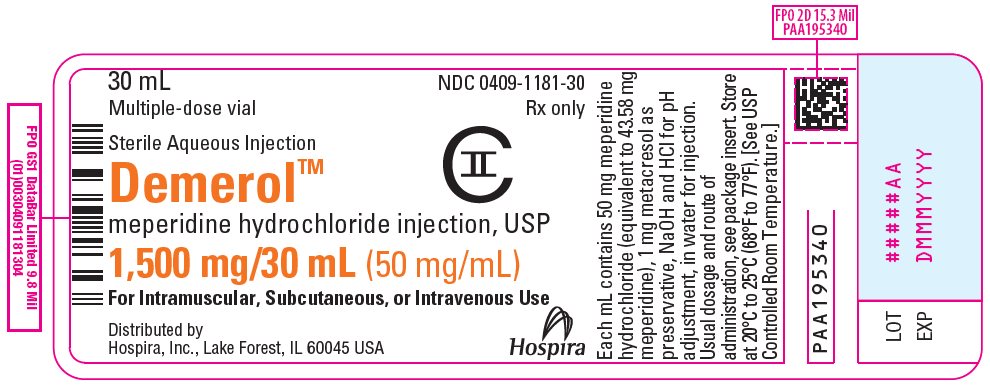
DEMEROL MEPERIDINE HYDROCHLORIDE 50 mg/mL Injection, Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Opioid Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Meperidine injection is used to relieve severe pain. Meperidine injection is also used before and during surgery or other medical procedures. Meperidine injection is in a class of medications called opiate (narcotic) analgesics. It works by changing the way the body senses pain.
Read the full MedlinePlus article ↗- Meperidine injection is a strong opioid pain reliever used in a few specific situations: managing severe pain when other treatments haven't worked, preparing patients before surger...
- What is meperidine injection actually used for?
- The most common things people notice are dizziness, nausea, vomiting, drowsiness, and sweating. These are unpleasant but expected. What you need to call about immediately — or have...
- What side effects should I expect, and which ones should I call about right away?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII GGO4Y809LO
Metacresol is a preservative derived from coal tar or petroleum. It prevents bacterial and fungal growth in liquid medicines, helping keep the product safe and stable during storage.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $23.13 | $693.80 / 30 ml |
| Medicare Part B allowsASP · J2175 | $6.339 / J2175 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Demerol 50 mg/mLthis 00409-1181-30 | Hospira, | 1 vial | — | AP | FDA listed | — |
| Demerol 50 mg/mL 00409-1178-30 | Hospira, | 10 cartridges | — | AP | FDA listed | — |
| Meperidine Hydrochloride 50 mg/mL 00641-6053-25 | Hikma | 25 vials | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2025 (Q1-Q4)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00409-1181-30 You're viewing this | 1 VIAL, MULTI-DOSE in 1 CARTON (0409-1181-30) / 30 mL in 1 VIAL, MULTI-DOSE | 2006-02-24 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SERIOUS AND LIFE-THREATENING RISKS FROM USE OF DEMEROL Addiction, Abuse, and Misuse Because the use of DEMEROL Injection exposes patients and other users to the risks of opioid addiction, abuse, and misuse, which can lead to overdose and death, assess each patient’s risk prior to prescribing and reassess all patients regularly for the development of these behaviors and conditions [see Warnings and Precautions (5.1) ] . Life-Threatening Respiratory Depression Serious, life-threatening, or fatal respiratory depression may occur with use of DEMEROL Injection, especially during initiation or following a dosage increase.
To reduce the risk of respiratory depression, proper dosing and titration of DEMEROL Injection are essential [see Warnings and Precautions (5.2) ] . Risks from Concomitant Use with Benzodiazepines or Other CNS Depressants Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing of DEMEROL Injection and benzodiazepines or other CNS depressants for use in patients for whom alternative treatment options are inadequate [see Warnings and Precautions (5.3) , Drug Interactions (7) ] .
Neonatal Opioid Withdrawal Syndrome (NOWS) Advise pregnant women using opioids for an extended period of time of the risk of Neonatal Opioid Withdrawal Syndrome, which may be life-threatening if not recognized and treated. Ensure that management by neonatology experts will be available at delivery [see Warnings and Precautions (5.4) ] . Cytochrome P450 3A4 Interaction The concomitant use of DEMEROL Injection with all cytochrome P450 3A4 inhibitors may result in an increase in meperidine plasma concentrations, which could increase or prolong adverse reactions and may cause potentially fatal respiratory depression.
In addition, discontinuation of a concomitantly used cytochrome P450 3A4 inducer may result in an increase in meperidine plasma concentration. Monitor patients receiving DEMEROL Injection and any CYP3A4 inhibitor or inducer [see Warnings and Precautions (5.5) , Drug Interactions (7) ] . Concomitant Use of DEMEROL Injection with Monoamine Oxidase (MAO) Inhibitors Concomitant use of DEMEROL Injection with monoamine oxidase (MAO) inhibitors can result in coma, severe respiratory depression, cyanosis, and hypotension.
Use of DEMEROL Injection with MAO inhibitors within last 14 days is contraindicated [see Contraindications (4) , Warnings and Precautions (5.6) , Drug Interactions (7) ] . WARNING: SERIOUS AND LIFE-THREATENING RISKS FROM USE OF DEMEROL INJECTION See full prescribing information for complete boxed warning. • DEMEROL Injection exposes users to risks of addiction, abuse, and misuse, which can lead to overdose and death. Assess patient’s risk before prescribing and reassess regularly for these behaviors and conditions.
( 5.1 ) • Serious, life-threatening, or fatal respiratory depression may occur with use of DEMEROL Injection, especially during initiation or following a dosage increase. To reduce the risk of respiratory depression, proper dosing and titration of DEMEROL Injection are essential. ( 5.2 ) • Concomitant use of opioids with benzodiazepines or other central nervous system (CNS) depressants, including alcohol, may result in profound sedation, respiratory depression, coma, and death. Reserve concomitant prescribing for use in patients for whom alternative treatment options are inadequate.
( 5.3 , 7 ) • Advise pregnant women using opioids for an extended period of time of the risk of Neonatal Opioid Withdrawal Syndrome, which may be life-threatening if not recognized and treated. Ensure that management by neonatology experts will be available at delivery. ( 5.4 ) • Concomitant use with CYP3A4 inhibitors (or discontinuation of CYP3A4 inducers) can result in a fatal overdose of meperidine.
( 5.5 , 7 ) • Concomitant use of DEMEROL Injection wi…
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE DEMEROL Injection is indicated for preoperative medication, support of anesthesia, and obstetrical analgesia. DEMEROL Injection is indicated for the management of pain severe enough to require an opioid analgesic and for which alternative treatments are inadequate. DEMEROL Injection is indicated for preoperative medication, support of anesthesia, for obstetrical analgesia, and for the management of pain severe enough to require an opioid analgesic and for which alternative treatments are inadequate.
( 1 ) Limitations of Use Because of the risks of addiction, abuse, misuse, overdose, and death, which can occur at any dosage or duration and persist over the course of therapy, reserve opioid analgesics, including DEMEROL Injection, for use in patients for whom alternative treatment options are ineffective, not tolerated, or would be otherwise inadequate to provide sufficient management of pain. Use of DEMEROL Injection for an extended period of time may increase the risk of toxicity (e.g., seizures) from the accumulation of the meperidine metabolite, normeperidine.
( 1 , 5.1 ) Limitations of Use: Because of the risks of addiction, abuse, misuse , overdose, and death , which can occur at any dosage or duration and persist over the course of therapy, [see Warnings and Precautions (5.1) ] , reserve opioid analgesics, including DEMEROL Injection, for use in patients for whom alternative treatment options are ineffective, not tolerated, or would be otherwise inadequate to provide sufficient management of pain. Use of DEMEROL Injection for an extended period of time may increase the risk of toxicity (e.g., seizures) from the accumulation of the meperidine metabolite, normeperidine.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • DEMEROL Injection should be prescribed only by healthcare professionals who are knowledgeable about the use of opioids and how to mitigate the associated risks. ( 2.1 ) • Use the lowest effective dosage for the shortest duration of time consistent with individual patient treatment goals. Reserve titration to higher doses of DEMEROL Injection for patients in whom lower doses are insufficiently effective and in whom the expected benefits of using a higher dose opioid clearly outweigh the substantial risks.
( 2.1 , 5 ) • Many acute pain conditions (e.g., the pain that occurs with a number of surgical procedures or acute musculoskeletal injuries) require no more than a few days of an opioid analgesic. Clinical guidelines on opioid prescribing for some acute pain conditions are available. ( 2.1 ) • Initiate the dosing regimen for each patient individually, taking into account the patient’s underlying cause and severity of pain, prior analgesic treatment and response, and risk factors for addiction, abuse, and misuse.
( 2.1 , 5.2 ) • Respiratory depression can occur at any time during opioid therapy, especially when initiating and following dosage increases with DEMEROL Injection. Consider this risk when selecting an initial dose and when making dose adjustments. ( 2.2 , 5.3 ) • Periodically reassess patients receiving DEMEROL Injection to evaluate the continued need for opioid analgesics to maintain pain control, for the signs or symptoms of adverse reactions, and for the development of addiction, abuse, or misuse.
( 2.2 ) • For Relief of Pain: Titrate the dose based upon the individual patient’s response to their initial dose of DEMEROL Injection. ( 2.2 , 5 ) Adults: 50 mg to 150 mg intramuscularly or subcutaneously every 3 to 4 hours. ( 2.2 ) Children: 0.5 mg/lb to 0.8 mg/lb intramuscularly or subcutaneously up to the adult dose every 3 to 4 hours.
( 2.2 ) • Preoperative Medication: Adults: 50 mg to 100 mg intramuscularly or subcutaneously, 30 to 90 minutes before beginning anesthesia. ( 2.3 ) Children: 0.5 mg/lb to 1 mg/lb intramuscularly or subcutaneously up to the adult dose, 30 to 90 minutes before beginning anesthesia. ( 2.3 ) • Obstetrical Analgesia: 50 mg to 100 mg intramuscularly or subcutaneously; may be repeated at 1 to 3 hour intervals.
( 2.4 ) • Do not rapidly reduce or abruptly discontinue DEMEROL Injection in a physically‑dependent patient. ( 2.2 , 5.15 )
2.1Important Dosage and Administration Instructions • DEMEROL Injection should be prescribed only by healthcare professionals who are knowledgeable about the use of opioids and how to mitigate the associated risks. • Use the lowest effective dosage for the shortest duration of time consistent with individual patient treatment goals [see Warnings and Precautions (5) ]. Because the risk of overdose increases as opioid doses increase, reserve titration to higher doses of DEMEROL Injection for patients in whom lower doses are insufficiently effective and in whom the expected benefits of using a higher dose opioid clearly outweigh the substantial risks. • Many acute pain conditions (e.g., the pain that occurs with a number of surgical procedures or acute musculoskeletal injuries) require no more than a few days of an opioid analgesic.
Clinical guidelines on opioid prescribing for some acute pain conditions are available. • There is variability in the opioid analgesic dose and duration needed to adequately manage pain due both to the cause of pain and to individual patient factors. Initiate the dosing regimen for each patient individually, taking into account the patient's underlying cause and severity of pain, prior analgesic treatment and response, and risk factors for addiction, abuse, and misuse [see Warnings and Precautions (5.1) ] . • Respiratory depression can occur at any time during opioid therapy, especially when initiating and following dosage increases with DEMEROL Injection. Consider t…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS DEMEROL Injection is a clear, colorless, sterile aqueous solution, available in the following dosage forms and strengths: • Single-dose Carpuject™ cartridge with Luer Lock for the Carpuject Syringe System, ONLY to be used with Carpuject™ Holder, and available in the following strengths: 25 mg/mL, 50 mg/mL, 75 mg/mL, and 100 mg/mL. • Multiple-dose vials containing 0.1% metacresol as a preservative, available in the following strength: 1,500 mg/30 mL (50 mg/mL). • Single-dose NexJect TM Prefilled Syringe with Luer Lock, available in the following strengths: 25 mg/mL and 50 mg/mL. • Injectable, Carpuject™ Single-dose cartridge with Luer Lock for the Carpuject Syringe System, to be used ONLY with Carpuject™ Holder: 25 mg/mL, 50 mg/mL, 75 mg/mL, and 100 mg/mL.
( 3 ) • Injectable, Multiple-dose vials: 1,500 mg/30 mL (50 mg/mL). ( 3 ) • Injectable, NexJect™ Single-dose Prefilled Syringe with Luer Lock: 25 mg/mL and 50 mg/mL. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS DEMEROL Injection is contraindicated in patients with: • Significant respiratory depression [see Warnings and Precautions (5.2) ] • Acute or severe bronchial asthma in an unmonitored setting or in the absence of resuscitative equipment [see Warnings and Precautions (5.9) ] • Concurrent use of monoamine oxidase inhibitors (MAOIs) or use of MAOIs within the last 14 days [see Warnings and Precautions (5.6) , Drug Interactions (7) ] • Known or suspected gastrointestinal obstruction, including paralytic ileus [see Warnings and Precautions (5.13) ] • Hypersensitivity to meperidine (e.g., anaphylaxis) [see Adverse Reactions (6) ] • Significant respiratory depression.
( 4 ) • Acute or severe bronchial asthma in an unmonitored setting or in absence of resuscitative equipment. ( 4 ) • Concurrent use of monoamine oxidase inhibitors (MAOIs) or use of MAOIs within the last 14 days. ( 7 ) • Known or suspected gastrointestinal obstruction, including paralytic ileus.
( 4 ) • Hypersensitivity to meperidine or to any other ingredients of the product. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Opioid-Induced Hyperalgesia and Allodynia : Opioid-Induced Hyperalgesia (OIH) occurs when an opioid analgesic paradoxically causes an increase in pain, or an increase in sensitivity to pain. If OIH is suspected, carefully consider appropriately decreasing the dose of the current opioid analgesic or opioid rotation. ( 5.7 ) • Serotonin Syndrome with Concomitant Use of Serotonergic Drugs : Potentially life-threatening condition could result from concomitant serotonergic drug administration.
Discontinue DEMEROL Injection if serotonin syndrome is suspected. ( 5.8 ) • Life-Threatening Respiratory Depression in Patients with Chronic Pulmonary Disease or in Elderly, Cachectic, or Debilitated Patients : Monitor closely, particularly during initiation and titration. ( 5.9 ) • Adrenal Insufficiency : If diagnosed, treat with physiologic replacement of corticosteroids, and wean patient off of the opioid.
( 5.10 ) • Severe Hypotension : Monitor during dosage initiation and titration. Avoid use of DEMEROL Injection in patients with circulatory shock. ( 5.11 ) • Risks of Use in Patients with Increased Intracranial Pressure, Brain Tumors, Head Injury, or Impaired Consciousness : Monitor for sedation and respiratory depression.
Avoid use of DEMEROL Injection in patients with impaired consciousness or coma. ( 5.12 )
5.1Addiction, Abuse, and Misuse DEMEROL Injection contains meperidine, a Schedule II controlled substance. As an opioid, DEMEROL Injection exposes users to the risks of addiction, abuse, and misuse [see Drug Abuse and Dependence (9) ]. Although the risk of addiction in any individual is unknown, it can occur in patients appropriately prescribed DEMEROL Injection.
Addiction can occur at recommended dosages and if the drug is misused or abused. The risk of opioid-related overdose or overdose-related death is increased with higher opioid doses, and this risk persists over the course of therapy. In postmarketing studies, addiction, abuse, misuse, and fatal and non-fatal opioid overdose were observed in patients with long-term opioid use [see Adverse Reactions (6) ] .
Assess each patient's risk for opioid addiction, abuse, or misuse prior to prescribing DEMEROL Injection, and monitor all patients receiving DEMEROL Injection for the development of these behaviors and conditions. Risks are increased in patients with a personal or family history of substance abuse (including drug or alcohol abuse or addiction) or mental illness (e.g., major depression). The potential for these risks should not, however, prevent the proper management of pain in any given patient.
Patients at increased risk may be prescribed opioids such as DEMEROL Injection but use in such patients necessitates intensive counseling about the risks and proper use of DEMEROL Injection along with intensive monitoring for signs of addiction, abuse, and misuse. Opioids are sought for nonmedical use and are subject to diversion from legitimate prescribed use. Strategies to reduce these risks include prescribing the drug in the smallest appropriate quantity.
Contact local state professional licensing board or state-controlled substances authority for information on how to prevent and detect abuse or diversion of this product.
5.2Life-Threatening Respiratory Depression Serious, life-threatening, or fatal respiratory depression has been reported with the use of opioids, even when used as recommended. Respiratory depression, if not immediately recognized and treated, may lead to respiratory arrest and death. Management of respiratory depression may include close observation, supportive measures, and use of opioid overdose reversal agents (e.g., naloxone, nalmefene), depending on the patient's clinical status [see Overdosage (10) ] .
Carbon dioxide (CO 2 ) retention from opioid-induced respiratory depression can exacerbate the sedating effects of opioids. While serious, life-threatening, or fatal respiratory depression can occur at any time during…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described, or described in greater detail, in other sections: • Addiction, Abuse, and Misuse [see Warnings and Precautions (5.1) ] • Life-Threatening Respiratory Depression [see Warnings and Precautions (5.2) ] • Interactions with Benzodiazepines or Other CNS Depressants [see Warnings and Precautions (5.3) ] • Neonatal Opioid Withdrawal Syndrome [see Warnings and Precautions (5.4) ] • Opioid-Induced Hyperalgesia and Allodynia [see Warnings and Precautions (5.7) ] • Serotonin Syndrome with Concomitant Use of Serotonergic Drugs [see Warnings and Precautions (5.8) ] • Adrenal Insufficiency [see Warnings and Precautions (5.10) ] • Severe Hypotension [see Warnings and Precautions (5.11) ] • Gastrointestinal Adverse Reactions [see Warnings and Precautions (5.13) ] • Seizures [see Warnings and Precautions (5.14) ] • Withdrawal [see Warnings and Precautions (5.15) ] The following adverse reactions associated with the use of meperidine were identified in clinical studies or postmarketing reports.
Because some of these reactions were reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. The major hazards of meperidine, as with other opioid analgesics, are respiratory depression and, to a lesser degree, circulatory depression; respiratory arrest, shock, and cardiac arrest have occurred. The most frequently observed adverse reactions include lightheadedness, dizziness, sedation, nausea, vomiting, and sweating.
These effects seem to be more prominent in ambulatory patients and in those who are not experiencing severe pain. In such individuals, lower doses are advisable. Some adverse reactions in ambulatory patients may be alleviated if the patient lies down.
Other adverse reactions include: Nervous System : Mood changes (e.g., euphoria, dysphoria), weakness, headache, agitation, tremor, involuntary muscle movements (e.g., muscle twitches, myoclonus), severe convulsions, seizures, transient hallucinations and disorientation, confusion, delirium, visual disturbances. Inadvertent injection about a nerve trunk may result in sensory-motor paralysis which is usually, though not always, transitory. Gastrointestinal : Dry mouth, constipation, biliary tract spasm.
Cardiovascular : Flushing of the face, tachycardia, bradycardia, palpitation, hypotension [see Warnings and Precautions (5.18) ] , syncope, phlebitis following intravenous injection. Genitourinary : Urinary retention. Allergic : Pruritus, urticaria, other skin rashes, wheal and flare over the vein with intravenous injection.
Hypersensitivity reactions, anaphylaxis. Histamine release leading to hypotension and/or tachycardia, flushing, sweating, and pruritus. Other : Pain at injection site; local tissue irritation and induration following subcutaneous injection, particularly when repeated; antidiuretic effect.
Serotonin syndrome : Cases of serotonin syndrome, a potentially life-threatening condition, have been reported during concomitant use of opioids with serotonergic drugs. Adrenal insufficiency : Cases of adrenal insufficiency have been reported with opioid use, more often following greater than one month of use. Androgen deficiency : Cases of androgen deficiency have occurred with use of opioids for an extended period of time [see Clinical Pharmacology (12.2) ] .
Hyperalgesia and Allodynia : Cases of hyperalgesia and allodynia have been reported with opioid therapy of any duration [see Warnings and Precautions (5.7) ]. Hypoglycemia : Cases of hypoglycemia have been reported in patients taking opioids. Most reports were in patients with at least one predisposing risk factor (e.g., diabetes). Opioid-induced esophageal dysfunction (OIED) : Cases of OIED have been reported in patients taking opioids and may occur more frequently in patients taking higher doses of opioids, and/or in patients taking op…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 1 includes clinically significant drug interactions with DEMEROL Injection. Table 1: Clinically Significant Drug Interactions with DEMEROL Injection Monoamine Oxidase Inhibitors (MAOIs) Clinical Impact: Meperidine is contraindicated in patients who are receiving monoamine oxidase (MAO) inhibitors or those who have recently received such agents. Therapeutic doses of meperidine have occasionally precipitated unpredictable, severe, and occasionally fatal reactions in patients who have received such agents within 14 days.
The mechanism of these reactions is unclear but may be related to a preexisting hyperphenylalaninemia. Some have been characterized by coma, severe respiratory depression, cyanosis, and hypotension, and have resembled the syndrome of acute opioid overdose. Serotonin syndrome with agitation, hyperthermia, diarrhea, tachycardia, sweating, tremors, and impaired consciousness may also occur.
In other reactions the predominant manifestations have been hyperexcitability, convulsions, tachycardia, hyperpyrexia, and hypertension [see Warnings and Precautions (5.6) ] . Intervention: Do not use DEMEROL Injection in patients taking MAOIs or within 14 days of stopping such treatment. Intravenous hydrocortisone or prednisolone have been used to treat severe reactions, with the addition of intravenous chlorpromazine in those cases exhibiting hypertension and hyperpyrexia.
The usefulness and safety of opioid overdose reversal agents in the treatment of these reactions are unknown. Examples: Phenelzine, tranylcypromine, linezolid Inhibitors of CYP3A4 and CYP2B6 Clinical Impact: The concomitant use of DEMEROL Injection and CYP3A4 or CYP2B6 inhibitors can increase the plasma concentration of meperidine, resulting in increased or prolonged opioid effects. These effects could be more pronounced with concomitant use of DEMEROL Injection and CYP2B6 and CYP3A4 inhibitors, particularly when an inhibitor is added after a stable dose of DEMEROL Injection is achieved [see Warnings and Precautions (5.5) ] .
After stopping a CYP3A4 inhibitor, as the effects of the inhibitor decline, the meperidine plasma concentration will decrease [see Clinical Pharmacology (12.3) ] , potentially resulting in decreased opioid efficacy or a withdrawal syndrome in patients who had developed physical dependence to meperidine. Intervention: If concomitant use is necessary, consider dosage reduction of DEMEROL Injection until stable drug effects are achieved. Monitor patients for respiratory depression and sedation at frequent intervals.
If a CYP3A4 or CYP2B6 inhibitor is discontinued, consider increasing the DEMEROL Injection dosage until stable drug effects are achieved. Monitor for signs of opioid withdrawal. Examples: Macrolide antibiotics (e.g., erythromycin), azole-antifungal agents (e.g., ketoconizole), protease inhibitors (e.g., ritonavir) CYP3A4 and CYP2B6 Inducers Clinical Impact: The concomitant use of DEMEROL Injection and CYP3A4 inducers or CYP2B6 inducers can decrease the plasma concentration of meperidine [see Clinical Pharmacology (12.3) ] , resulting in decreased efficacy or onset of a withdrawal syndrome in patients who have developed physical dependence to meperidine [see Warnings and Precautions (5.5) ] .
After stopping a CYP3A4 or CYP2B6 inducer, as the effects of the inducer decline, the meperidine plasma concentration will increase [see Clinical Pharmacology (12.3) ] , which could increase or prolong both the therapeutic effects and adverse reactions and may cause serious respiratory depression. Intervention: If concomitant use is necessary, consider increasing the DEMEROL Injection dosage until stable drug effects are achieved. Monitor for signs of opioid withdrawal.
If a CYP3A4 or CYP2B6 inducer is discontinued, consider DEMEROL Injection dosage reduction and monitor for signs of respiratory depression. Examples: Rifampin, carbamazepine, phenytoin Benzodiazepines and Other Central Nervous System (CNS) Depressan…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Pregnancy: May cause fetal harm. ( 8.1 ) • Geriatric Patients: Use caution during dose selection, starting at the low end of the dosing range while carefully monitoring for side effects. ( 8.5 )
8.1Pregnancy Risk Summary Use of opioid analgesics for an extended period of time during pregnancy may cause neonatal opioid withdrawal syndrome [see Warnings and Precautions (5.4) ] . Available data with DEMEROL Injection are insufficient to inform a drug-associated risk for major birth defects and miscarriage or adverse maternal outcomes. There are adverse outcomes reported with fetal exposure to opioid analgesics [see Clinical Considerations ] .
Formal animal reproduction studies have not been conducted with meperidine. Neural tube defects (exencephaly and cranioschisis) have been reported in hamsters administered a single bolus dose of meperidine during a critical period of organogenesis at 0.85 and 1.5 times the total human daily dose of 1200 mg [see Data ] . The background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions Use of opioid analgesics for an extended period of time during pregnancy for medical or nonmedical purposes can result in physical dependence in the neonate and neonatal opioid withdrawal syndrome shortly after birth.
Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea, and failure to gain weight. The onset, duration, and severity of neonatal opioid withdrawal syndrome vary based on the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn. Observe newborns for symptoms of neonatal opioid withdrawal syndrome and manage accordingly [see Warnings and Precautions (5.4) ] .
Labor or Delivery Opioids cross the placenta and may produce respiratory depression and psycho-physiologic effects in neonates. An opioid overdose reversal agents, such as naloxone or nalmefene, must be available for reversal of opioid-induced respiratory depression in the neonate. DEMEROL Injection is not recommended for use in pregnant women during or immediately prior to labor, when other analgesic techniques are more appropriate.
Opioid analgesics, including DEMEROL Injection, can prolong labor through actions which temporarily reduce the strength, duration, and frequency of uterine contractions. However, this effect is not consistent and may be offset by an increased rate of cervical dilation, which tends to shorten labor. Monitor neonates exposed to opioid analgesics during labor for signs of excess sedation and respiratory depression.
Data Animal Data Formal reproductive and developmental toxicology studies for meperidine have not been completed. In a published study, neural tube defects (exencephaly and cranioschisis) were noted following subcutaneous administration of meperidine hydrochloride (127 and 218 mg/kg, respectively) on Gestation Day 8 to pregnant hamsters (0.85 and 1.5 times the total daily dose of 1200 mg/day based on body surface area). The findings cannot be clearly attributed to maternal toxicity.
8.2Lactation Risk Summary Meperidine appears in the milk of nursing mothers receiving the drug. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for DEMEROL Injection and any potential adverse effects on the breastfed infant from DEMEROL Injection or from the underlying maternal condition. Clinical Considerations Monitor infants exposed to DEMEROL Injection through breast milk for excess sedation and respi…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Use of opioid analgesics for an extended period of time during pregnancy may cause neonatal opioid withdrawal syndrome [see Warnings and Precautions (5.4) ] . Available data with DEMEROL Injection are insufficient to inform a drug-associated risk for major birth defects and miscarriage or adverse maternal outcomes. There are adverse outcomes reported with fetal exposure to opioid analgesics [see Clinical Considerations ] .
Formal animal reproduction studies have not been conducted with meperidine. Neural tube defects (exencephaly and cranioschisis) have been reported in hamsters administered a single bolus dose of meperidine during a critical period of organogenesis at 0.85 and 1.5 times the total human daily dose of 1200 mg [see Data ] . The background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Fetal/Neonatal Adverse Reactions Use of opioid analgesics for an extended period of time during pregnancy for medical or nonmedical purposes can result in physical dependence in the neonate and neonatal opioid withdrawal syndrome shortly after birth.
Neonatal opioid withdrawal syndrome presents as irritability, hyperactivity and abnormal sleep pattern, high pitched cry, tremor, vomiting, diarrhea, and failure to gain weight. The onset, duration, and severity of neonatal opioid withdrawal syndrome vary based on the specific opioid used, duration of use, timing and amount of last maternal use, and rate of elimination of the drug by the newborn. Observe newborns for symptoms of neonatal opioid withdrawal syndrome and manage accordingly [see Warnings and Precautions (5.4) ] .
Labor or Delivery Opioids cross the placenta and may produce respiratory depression and psycho-physiologic effects in neonates. An opioid overdose reversal agents, such as naloxone or nalmefene, must be available for reversal of opioid-induced respiratory depression in the neonate. DEMEROL Injection is not recommended for use in pregnant women during or immediately prior to labor, when other analgesic techniques are more appropriate.
Opioid analgesics, including DEMEROL Injection, can prolong labor through actions which temporarily reduce the strength, duration, and frequency of uterine contractions. However, this effect is not consistent and may be offset by an increased rate of cervical dilation, which tends to shorten labor. Monitor neonates exposed to opioid analgesics during labor for signs of excess sedation and respiratory depression.
Data Animal Data Formal reproductive and developmental toxicology studies for meperidine have not been completed. In a published study, neural tube defects (exencephaly and cranioschisis) were noted following subcutaneous administration of meperidine hydrochloride (127 and 218 mg/kg, respectively) on Gestation Day 8 to pregnant hamsters (0.85 and 1.5 times the total daily dose of 1200 mg/day based on body surface area). The findings cannot be clearly attributed to maternal toxicity.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and efficacy of DEMEROL Injection in patients less than 18 years of age have not been established. The safety and effectiveness of meperidine in pediatric patients has not been established. Literature reports indicate that meperidine has a slower elimination rate in neonates and young infants compared to older children and adults.
Neonates and young infants may also be more susceptible to the effects, especially the respiratory depressant effects. If meperidine use is contemplated in neonates or young infants, any potential benefits of the drug need to be weighed against the relative risk of the patient.
🧓 Geriatric Use ▾
8.5Geriatric Use Elderly patients (aged 65 years or older) may have increased sensitivity to meperidine. In general, use caution when selecting a dosage for an elderly patient, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function and of concomitant disease or other drug therapy. Respiratory depression is the chief risk for elderly patients treated with opioids, and has occurred after large initial doses were administered to patients who were not opioid-tolerant or when opioids were co-administered with other agents that depress respiration.
Titrate the dosage of DEMEROL Injection slowly in geriatric patients and monitor closely for signs of central nervous system and respiratory depression [see Warnings and Precautions (5.2) ] . Meperidine is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
🆘 Overdosage ▾
10 OVERDOSAGE Clinical Presentation Acute overdose with meperidine can be manifested by respiratory depression, somnolence progressing to stupor or coma, skeletal muscle flaccidity, cold and clammy skin, constricted pupils, and, in some cases, pulmonary edema, bradycardia, hypotension, hypoglycemia, partial or complete airway obstruction, atypical snoring, and death. Marked mydriasis rather than miosis may be seen with hypoxia in overdose situations [see Clinical Pharmacology (12.2) ] . Toxic leukoencephalopathy has been reported after opioid overdose and can present hours, days, or weeks after apparent recovery from the initial intoxication.
In severe overdose, particularly by the intravenous route, apnea, circulatory collapse, cardiac arrest, and death may occur. Accumulation of normeperidine as in chronic use or possibly following introduction of a concomitant CYP3A4 inducer presents as excitatory syndrome including hallucinations, tremors, muscle twitches, dilated pupils, hyperactive reflexes, and convulsions. Treatment of Overdose In case of overdose, priorities are the reestablishment of a patent and protected airway and institution of assisted or controlled ventilation, if needed.
Employ other supportive measures (including oxygen and vasopressors) in the management of circulatory shock and pulmonary edema as indicated. Cardiac arrest or arrhythmias will require advanced life-support measures. For clinically significant respiratory or circulatory depression secondary to meperidine overdose, administer an opioid overdose reversal agent such as naloxone or nalmefene.
Because the duration of opioid reversal is expected to be less than the duration of action of meperidine in DEMEROL Injection, carefully monitor the patient until spontaneous respiration is reliably re-established. If the response to an opioid overdose reversal agent is suboptimal or only brief in nature, administer additional reversal agent as directed by the product's prescribing information. In an individual physically dependent on opioids, administration of the recommended usual dosage of the opioid overdose reversal agent will precipitate an acute withdrawal syndrome.
The severity of the withdrawal symptoms experienced will depend on the degree of physical dependence and the dose of the reversal agent administered. If a decision is made to treat serious respiratory depression in the physically-dependent patient, administration of the reversal agent should be begun with care and by titration with smaller than usual doses of the reversal agent.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Meperidine hydrochloride is an opioid agonist with multiple actions qualitatively similar to those of morphine; the most prominent of these involve the central nervous system and organs composed of smooth muscle. The principal actions of therapeutic value are analgesia and sedation.
12.2Pharmacodynamics Effects on the Central Nervous System Meperidine produces respiratory depression by direct action on brain stem respiratory centers. The respiratory depression involves a reduction in the responsiveness of the brain stem respiratory centers to both increases in carbon dioxide tension and electrical stimulation. Meperidine causes miosis, even in total darkness.
Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origins may produce similar findings). Marked mydriasis rather than miosis may be seen due to hypoxia in overdose situations. Effects on the Gastrointestinal Tract and Other Smooth Muscle Meperidine causes a reduction in motility associated with an increase in smooth muscle tone in the antrum of the stomach duodenum.
Digestion of food in the small intestine is delayed and propulsive contractions are decreased. Propulsive peristaltic waves in the colon are decreased, while tone may be increased to the point of spasm, resulting in constipation. Other opioid-induced effects may include a reduction in biliary and pancreatic secretions, spasm of sphincter of Oddi, transient elevations in serum amylase, and opioid-induced esophageal dysfunction (OIED).
Effects of the Cardiovascular System Meperidine produces peripheral vasodilation which may result in orthostatic hypotension or syncope. Manifestations of histamine release and/or peripheral vasodilation may include pruritus, flushing, red eyes, and sweating and/or orthostatic hypotension. Effects on the Endocrine System Opioids inhibit the secretion of adrenocorticotropic hormone (ACTH), cortisol, and luteinizing hormones (LH) in humans [see Adverse Reactions (6) ] .
They also stimulate prolactin, growth hormone (GH) secretion, and pancreatic secretion of insulin and glucagon. Use of opioids for an extended period of time may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility. The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date [see Adverse Reactions (6) ] .
Effects on the Immune System Opioids have been shown to have a variety of effects on components of the immune system in in vitro and animal models. The clinical significance of these findings is unknown. Overall, the effects of opioids appear to be modestly immunosuppressive.
Concentration–Efficacy Relationships The minimum effective analgesic concentration will vary widely among patients, especially among patients who have been previously treated with opioid agonists. The minimum effective analgesic concentration of meperidine for any individual patient may increase over time due to an increase in pain, the development of a new pain syndrome and/or the development of analgesic tolerance [see Dosage and Administration (2.1 , 2.2) ] . Meperidine, in 60 mg to 80 mg parenteral doses, is approximately equivalent in analgesic effect to 10 mg of morphine.
The onset of action is slightly more rapid than with morphine, and the duration of action is slightly shorter. Meperidine is significantly less effective by the oral than by the parenteral route, but the exact ratio of oral to parenteral effectiveness is unknown. Concentration–Adverse Reaction Relationships There is a relationship between increasing meperidine plasma concentration and increasing frequency of dose-related opioi…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Meperidine hydrochloride is an opioid agonist with multiple actions qualitatively similar to those of morphine; the most prominent of these involve the central nervous system and organs composed of smooth muscle. The principal actions of therapeutic value are analgesia and sedation.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING For Parenteral Use DEMEROL (meperidine hydrochloride injection) is clear and colorless. DEMEROL (meperidine hydrochloride injection) is supplied as a sterile solution in a multiple-dose vial, single-dose Carpuject™ cartridges for use ONLY with the Carpuject™ Holders and NexJect™ prefilled syringes for subcutaneous, intramuscular, and intravenous administration, and available as follows: Unit of Sale Concentration (per total volume) NDC 0409-1181-30 Carton of 1 30 mL fill in 30 mL Multiple-dose Vial 1,500 mg/30 mL (50 mg/mL) NDC 0409-1176-30 Carton of 10 1 mL fill in 2.5 mL Carpuject™ Single-dose cartridge with Luer Lock 25 mg/mL NDC 0409-1178-30 Carton of 10 1 mL fill in 2.5 mL Carpuject™ Single-dose cartridge with Luer Lock 50 mg/mL NDC 0409-1179-30 Carton of 10 1 mL fill in 2.5 mL Carpuject™ Single-dose cartridge with Luer Lock 75 mg/mL NDC 0409-1180-69 Carton of 10 1 mL fill in 2.5 mL Carpuject™ Single-dose cartridge with Luer Lock 100 mg/mL NDC 0409-1362-01 Clamshell of 10 1 mL fill in 1.5 mL NexJect™ Single-dose Prefilled Syringe with Luer Lock 25 mg/mL NDC 0409-1418-01 Clamshell of 10 1 mL fill in 1.5 mL NexJect™ Single-dose Prefilled Syringe with Luer Lock 50 mg/mL Carpuject™ Single-dose cartridges are packaged in a Slim-Pak tamper detection package.
Note that a needle is not included with Carpuject™ Single-dose cartridges and NexJect™ Single-dose Prefilled Syringes. Carpuject TM and NexJect TM Single-dose products: Discard unused portion. Multiple-dose vials: Discard unused portion after 28 days.
Store at 20°C to 25°C (68°F to 77°F), excursions permitted between 15°C to 30°C (59°F to 86°F). [See USP Controlled Room Temperature.]
📦 Storage and Handling ▾
Store at 20°C to 25°C (68°F to 77°F), excursions permitted between 15°C to 30°C (59°F to 86°F). [See USP Controlled Room Temperature.]
📋 Description ▾
11 DESCRIPTION DEMEROL (meperidine hydrochloride injection) is an opioid agonist available as a sterile aqueous solution, for intramuscular, intravenous, or subcutaneous administration. It contains meperidine hydrochloride as the active pharmaceutical ingredient. Meperidine hydrochloride chemical name is 4‑Piperidinecarboxylic acid, 1‑methyl-4-phenyl-,ethyl ester, hydrochloride.
The molecular weight is 283.79 g/mol. Its molecular formula is C 15 H 21 NO 2 ·HCl, and it has the following chemical structure. Meperidine hydrochloride is a white crystalline substance with a melting point of 186° C to 189° C, and it is readily soluble in water.
DEMEROL (meperidine hydrochloride injection) is available as: Single-dose Carpuject TM cartridge with Luer Lock for the Carpuject Syringe System: 25 mg/mL, 50 mg/mL, 75 mg/mL, and 100 mg/mL. Each mL of Single-dose cartridge contains 25 mg, 50 mg, 75 mg or 100 mg of meperidine hydrochloride USP (equivalent to 21.79 mg, 43.58 mg, 65.36 mg or 87.15 mg of meperidine), respectively, and sodium hydroxide NF, and hydrochloric acid NF as pH adjusters, in water for injection. Only the 25 mg strength contains 3.8 mg of sodium chloride USP as isotonicity agent.
Multiple-dose vials: 1,500 mg/30 mL (50 mg/mL) strength. Each mL of vial contains 50 mg of meperidine hydrochloride USP (equivalent to 43.58 mg of meperidine), 1 mg of meta-cresol USP, as a preservative, and sodium hydroxide NF, and hydrochloric acid NF as pH adjusters, in water for injection. Single-dose NexJect™ Prefilled Syringe with Luer Lock: 25 mg/mL and 50 mg/mL strengths.
Each mL contains 25 mg or 50 mg of meperidine hydrochloride USP (equivalent to 21.79 mg or 43.58 mg of meperidine), respectively, and sodium hydroxide NF, and hydrochloric acid NF as pH adjusters, in water for injection. Only the 25 mg strength contains 3.8 mg of sodium chloride USP as isotonicity agent. The pH of DEMEROL (meperidine hydrochloride injection) solutions is between 3.5 and 6.0.
DEMEROL (meperidine hydrochloride injection) 5 percent solution has a specific gravity of 1.0086 at 20°C, and the 10 percent solution has a specific gravity of 1.0165 at 20°C. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Addiction, Abuse, and Misuse Inform patients that the use of DEMEROL Injection, even when taken as recommended, can result in addiction, abuse, and misuse, which can lead to overdose and death [see Warnings and Precautions (5.1) ] . Instruct patients not to share DEMEROL Injection with others and to take steps to protect DEMEROL Injection from theft or misuse. Life-Threatening Respiratory Depression Inform patients of the risk of life-threatening respiratory depression, including information that the risk is greatest when DEMEROL Injection or when the dosage is increased, and that it can occur even at recommended dosages [see Warnings and Precautions (5.2) ] .
Hyperalgesia and Allodynia Advise patients to inform their healthcare provider if they experience symptoms of hyperalgesia, including worsening pain, increased sensitivity to pain, or new pain [see Warnings and Precautions (5.7) , Adverse Reactions (6) ] . Serotonin Syndrome Inform patients that opioids could cause a rare but potentially life-threatening condition called serotonin syndrome resulting from concomitant administration of serotonergic drugs. Warn patients of the symptoms of serotonin syndrome and to seek medical attention right away if symptoms develop after discharge from the hospital.
Instruct patients to inform their healthcare provider if they are taking, or plan to take serotonergic medications [see Warnings and Precautions (5.8) , Drug Interactions (7) ] . Constipation Advise patients of the potential for severe constipation, including management instructions and when to seek medical attention [see Adverse Reactions (6) , Clinical Pharmacology (12.1) ] .