
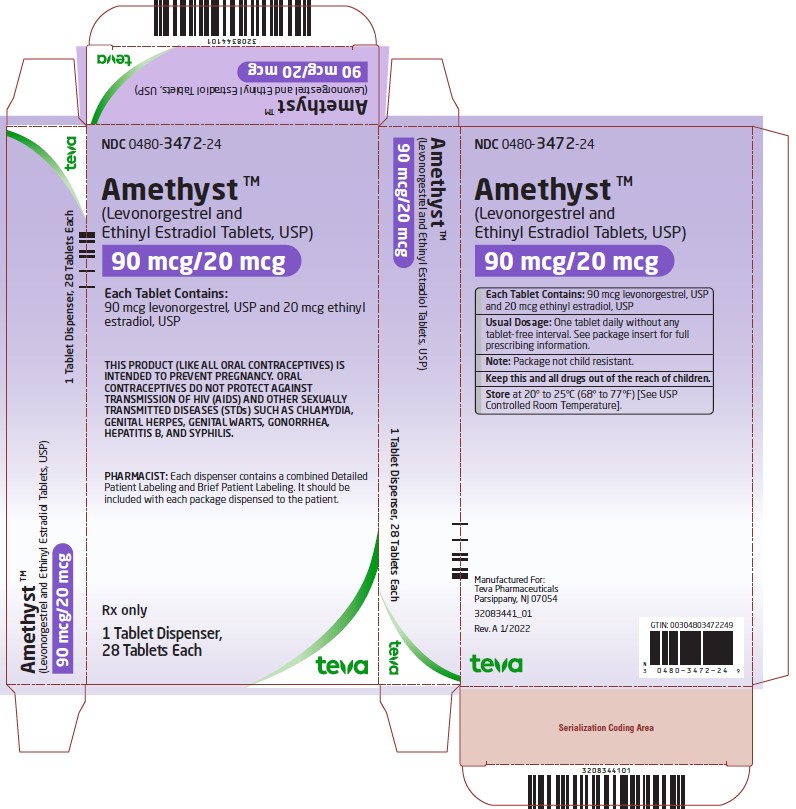
Amethyst Levonorgestrel and Ethinyl Estradiol 90 ug; 20 ug Tablet, 28-count — NDC 0480-3472-24 (Billing 00480-3472-24)
This is a package of 28 tablets of Amethyst Levonorgestrel and Ethinyl Estradiol 90 ug; 20 ug Tablet from Teva Pharmaceuticals, Inc., marketed since Mar 2023 and currently FDA-listed; retail pharmacies pay about $1.14 per tablet (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0480-3472-24 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0480 labeler · 3472 product · 24 package
- Package marketed since
- Mar 1, 2023
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 28 EA per package
- Barcode (UPC-A, from the NDC)
- 3 0480347224 9
- Medicaid fills, this package
- 2,202 prescriptions in the last four reported quarters
- FDA record last changed
- Aug 27, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 062777
- GCN: 98551
- GPI-14 (Medi-Span): 25994002350320
- HICL (First Databank): 001460
- AHFS class code: 68:12.00.00
- RxCUI (RxNorm): 722152
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Estrogen class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Oral contraceptives (birth-control pills) containing ethinyl estradiol (an estrogen) and levonorgestrel (a progestin) are used to prevent pregnancy. Estrogen and progestin are two female sex hormones. Combinations of estrogen and progestin work by preventing ovulation (the release of eggs from the ovaries). Oral contraceptives are an effective method of birth control, but they do not prevent the spread of human immunodeficiency virus (HIV, the virus that causes acquired immunodeficiency syndrome [AIDS]) and other sexually transmitted diseases.
Read the full MedlinePlus article ↗- It prevents pregnancy. It is a combined hormonal birth control with an estrogen and a progestin. It comes as daily tablets or as the weekly Twirla patch.
- With tablets, you take one at the same time every day, no more than 24 hours apart. With the Twirla patch, you wear one patch for a week, three weeks in a row, then take a patch-fr...
- Headache, nausea, acne, breast tenderness, mood changes, and irregular bleeding are the common ones. Bleeding changes often settle with time. Call your doctor if they persist.
- Get help for chest pain, sudden shortness of breath, leg swelling or pain, vision loss, or severe new headaches. These can signal a blood clot or stroke. Also report yellowing of y...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $1.136 | $31.80 / 28 tablets |
| Medicaid paysCMS SDUD · 12 mo | $1.16 | $32.46 / 28 tablets |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00480-3472-24 You're viewing this Main listing | 1 POUCH in 1 CARTON / 1 BLISTER PACK in 1 POUCH / 28 TABLET in 1 BLISTER PACK | 2023-03-01 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Amethyst 90 ug/1; 20 ugthis 00480-3472-24 | Teva | 28 tablets | $1.136 | AB | Availability likely | — |
| Dolishale 90 ug/1; 20 ug 50742-0659-28 | Ingenus | 28 tablets | $1.136 | AB | Availability likely | — |
| Levonorgestrel and Ethinyl Estradiol 90 ug/1; 20 ug 68462-0637-29 | Glenmark | 84 tablets | $1.136 | AB | Availability likely | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Ethinyl Estradiol / Levonorgestrel inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Teva Pharmaceuticals, Inc. labeler code 00480
- Amphetamine 9.4 mg Tablet, Orally Disintegrating NDC 0480-3317-65
- Amphetamine 12.5 mg Tablet, Orally Disintegrating NDC 0480-3318-65
- Amphetamine 15.7 mg Tablet, Orally Disintegrating NDC 0480-3319-65
- Amphetamine 18.8 mg Tablet, Orally Disintegrating NDC 0480-3320-65
- Dalbavancin 500 mg/25mL Injection, Powder, For Solution NDC 0480-3325-01
- Tolvaptan Kit NDC 0480-3414-66
- Nora BE Norethindrone .35 mg Tablet NDC 0480-3475-16
- Naloxone Hydrochloride 4 mg/.1mL Spray, Metered NDC 0480-3478-68
- Lubiprostone 8 ug Capsule, Gelatin Coated NDC 0480-3479-06
- Cryselle Norgestrel and Ethinyl Estradiol Kit NDC 0480-3493-16
- Gabapentin 100 mg Capsule NDC 0480-3494-05
- Gabapentin 300 mg Capsule NDC 0480-3495-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Amethyst™ (levonorgestrel and ethinyl estradiol tablets) is indicated for the prevention of pregnancy in women who elect to use oral contraceptives as a method of contraception. Oral contraceptives are highly effective for pregnancy prevention. Table 2 lists the typical unintended pregnancy rates for users of combination oral contraceptives and other methods of contraception.
The efficacy of these contraceptive methods, except sterilization, the IUD, and implants, depend upon the reliability with which they are used. Correct and consistent use of methods can result in lower failure rates. Table 2: Percentage of Women Experiencing an Unintended Pregnancy During The First Year of Typical Use and The First Year of Perfect Use of Contraception and The Percentage Continuing Use at The End of the First Year.
United States. % of Women Experiencing an Unintended Pregnancy within the First Year of Use % of Women Continuing Use at One Year 3 Method (1) Typical Use 1 (2) Perfect Use 2 (3) (4) Chance 4 85 85 Spermicides 5 26 6 40 Periodic abstinence 25 63 Calendar 9 Ovulation method 3 Sympto-thermal 6 2 Post-ovulation 1 Cap 7 Parous women 40 26 42 Nulliparous women 20 9 56 Sponge Parous women 40 20 42 Nulliparous women 20 9 56 Diaphragm 7 20 6 56 Withdrawal 19 4 Condom 8 Female (Reality ® ) 21 5 56 Male 14 3 61 Pill 5 71 Progestin only
0.5 Combined
0.1IUD Progesterone T 2.0 1.5 81 Copper T380A 0.8 0.6 78 LNg 20 0.1 0.1 81 Depo-Provera ® 0.3 0.3 70 Levonorgestrel Implants (Norplant ® ) 0.05 0.05 88 Female sterilization 0.5 0.5 100 Male sterilization 0.15 0.10 100 Emergency Contraceptive Pills: The FDA has concluded that certain combined oral contraceptives containing ethinyl estradiol and norgestrel or levonorgestrel are safe and effective for use as postcoital emergency contraception. Treatment initiated within 72 hours after unprotected intercourse reduces the risk of pregnancy by at least 75%.
9 Lactation Amenorrhea Method: LAM is a highly effective, temporary method of contraception. 10 Source: Trussell J. Contraceptive efficacy.
In: Hatcher RA, Trussell J, Stewart F, Cates W, Stewart GK, Kowel D, Guest F. Contraceptive Technology: Seventeenth Revised Edition. New York NY: Irvington Publishers; 1998.
Among typical couples who initiate use of a method (not necessarily for the first time), the percentage who experience an accidental pregnancy during the first year if they do not stop use for any other reason. Among couples who initiate use of a method (not necessarily for the first time) and who use it perfectly (both consistently and correctly), the percentage who experience an accidental pregnancy during the first year if they do not stop use for any other reason. Among couples attempting to avoid pregnancy, the percentage who continue to use a method for one year.
The percents becoming pregnant in columns (2) and (3) are based on data from populations where contraception is not used and from women who cease using contraception in order to become pregnant. Among such populations, about 89% become pregnant within one year. This estimate was lowered slightly (to 85%) to represent the percent who would become pregnant within one year among women now relying on reversible methods of contraception if they abandoned contraception altogether.
Foams, creams, gels, vaginal suppositories, and vaginal film. Cervical mucus (ovulation) method supplemented by calendar in the pre-ovulatory and basal body temperature in the post-ovulatory phases. With spermicidal cream or jelly.
Without spermicides. The treatment schedule is one dose within 72 hours after unprotected intercourse, and a second dose 12 hours after the first dose. The FDA has declared the following dosage regimens of oral contraceptives to be safe and effective for emergency contraception: for tablets containing 50 mcg of ethinyl estradiol and 500 mcg of norgestrel 1 dose is 2 tablets; for tablets containing 20 mcg of ethinyl estradiol and 100 mcg of levonorgestrel… [Excerpted — this section continues on DailyMed.]
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION To achieve maximum contraceptive effectiveness, Amethyst™ (levonorgestrel and ethinyl estradiol tablets) must be taken exactly as directed and at intervals not exceeding 24 hours. The possibility of ovulation and conception prior to initiation of medication should be considered. Women who do not wish to become pregnant after discontinuation should be advised to immediately use another method of birth control.
The dosage of Amethyst™ is one white tablet daily without any tablet-free interval. It is recommended that Amethyst™ tablets be taken at the same time each day. Initiation of Therapy Instructions for beginning Amethyst™ are provided in Table 4 below.
Table 4 Current contraceptive therapy Amethyst™ start day Nonhormonal back-up method of birth control needed when correctly starting Amethyst™ ? None Day 1 of patient’s menstrual cycle (during the first 24 hours of her period) No 21-day COC regimen OR 28-day COC regimen Day 1 of patient’s withdrawal bleed, at the latest 7 days after her last active tablet No Progestin-only pill Day after taking a progestin-only pill Yes, for the first 7 days of Amethyst™ tablet-taking Implant Day of implant removal Yes, for the first 7 days of Amethyst™ tablet-taking Injection Day the next injection is due Yes, for the first 7 days of Amethyst™ tablet-taking If spotting or unscheduled bleeding occurs, the patient is instructed to continue on the same regimen.
This type of bleeding is usually transient and without significance; however, if the bleeding is persistent or prolonged, the patient is advised to consult her health care professional. The possibility of ovulation increases with each successive day that scheduled white tablets are missed. If the patient has not adhered to the prescribed schedule (missed one or more tablets or started taking them on a day later than she should have), the probability of pregnancy should be considered.
Hormonal contraception must be discontinued if pregnancy is confirmed. The risk of pregnancy increases with each tablet missed. For additional patient instructions regarding missed tablets, see the WHAT TO DO IF YOU MISS PILLS section in the DETAILED PATIENT LABELING below.
Amethyst™ may be initiated no earlier than day 28 postpartum in the nonlactating mother or after a second-trimester abortion due to the increased risk for thromboembolism (see CONTRAINDICATIONS , WARNINGS , and PRECAUTIONS concerning thromboembolic disease). The patient should be advised to use a nonhormonal back-up method for the first 7 days of tablet-taking. However, if intercourse has already occurred, pregnancy should be excluded before the start of combined oral contraceptive use or the patient must wait for her first menstrual period.
In the case of first-trimester abortion, if the patient starts Amethyst™ immediately, additional contraceptive measures are not needed.
⛔ Contraindications ▾
CONTRAINDICATIONS Amethyst™ (levonorgestrel and ethinyl estradiol tablets) is contraindicated in females who are known to have or develop the following conditions: Thrombophlebitis or thromboembolic disorders History of deep-vein thrombophlebitis or thromboembolic disorders Cerebrovascular or coronary artery disease (current or past history) Valvular heart disease with thrombogenic complications Thrombogenic rhythm disorders Hereditary or acquired thrombophilias Major surgery with prolonged immobilization Diabetes with vascular involvement Headaches with focal neurological symptoms such as aura Uncontrolled hypertension Current diagnosis of, or history of, breast cancer, which may be hormone-sensitive Carcinoma of the endometrium or other known or suspected estrogen-dependent neoplasia Undiagnosed abnormal genital bleeding Cholestatic jaundice of pregnancy or jaundice with prior pill use Hepatic adenomas or carcinomas, or active liver disease Known or suspected pregnancy Hypersensitivity to any of the components of Amethyst™ Are receiving Hepatitis C drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir, due to the potential for ALT elevations (see WARNINGS, Risk of Liver Enzyme Elevations with Concomitant Hepatitis C Treatment ).
⚠️ Warnings ▾
WARNINGS Cigarette smoking increases the risk of serious cardiovascular side effects from oral contraceptive use. This risk increases with age and with the extent of smoking (in epidemiologic studies, 15 or more cigarettes per day was associated with a significantly increased risk) and is quite marked in women over 35 years of age. Women who use oral contraceptives should be strongly advised not to smoke.
The use of oral contraceptives is associated with increased risks of several serious conditions including venous and arterial thrombotic and thromboembolic events (such as myocardial infarction, thromboembolism, stroke, and transient ischemic attack), hepatic neoplasia, gallbladder disease, and hypertension, although the risk of serious morbidity or mortality is very small in healthy women without underlying risk factors. The risk of morbidity and mortality increases significantly in the presence of other underlying risk factors such as certain inherited or acquired thrombophilias, hypertension, hyperlipidemias, obesity, diabetes, and surgery or trauma with increased risk of thrombosis (see CONTRAINDICATIONS ).
Practitioners prescribing oral contraceptives should be familiar with the following information relating to these risks. The information contained in this package insert is principally based on studies carried out in patients who used oral contraceptives with higher doses of estrogens and progestogens than those in common use today. The effect of long-term use of the oral contraceptives with lower doses of both estrogens and progestogens remains to be determined.
Throughout this labeling, epidemiological studies reported are of two types: retrospective or case control studies and prospective or cohort studies. Case control studies provide a measure of the relative risk of disease, namely, a ratio of the incidence of a disease among oral contraceptive users to that among nonusers. The relative risk does not provide information on the actual clinical occurrence of a disease.
Cohort studies provide a measure of attributable risk, which is the difference in the incidence of disease between oral contraceptive users and nonusers. The attributable risk does provide information about the actual occurrence of a disease in the population. For further information, the reader is referred to a text on epidemiological methods.
1. Thromboembolic Disorders and Other Vascular Problems Amethyst™ is a non-cyclic oral contraceptive that provides a low daily dose of estrogen and progestin; however, Amethyst™ provides women with more hormonal exposure on a yearly basis (13 additional weeks of hormone intake per year) than conventional cyclic oral contraceptives containing the same strength of synthetic estrogens and similar strength of progestins. a. Myocardial Infarction An increased risk of myocardial infarction has been attributed to oral contraceptive use.
This risk is primarily in smokers or women with other underlying risk factors for coronary-artery disease such as hypertension, hypercholesterolemia, morbid obesity, and diabetes. The relative risk of heart attack for current oral contraceptive users has been estimated to be two to six. The risk is very low under the age of 30.
Smoking in combination with oral contraceptive use has been shown to contribute substantially to the incidence of myocardial infarction in women in their mid-thirties or older with smoking accounting for the majority of excess cases. Mortality rates associated with circulatory disease have been shown to increase substantially in smokers over the age of 35 and nonsmokers over the age of 40 (Figure 3) among women who use oral contraceptives. Figure 3: Circulatory Disease Mortality Rates per 100,000 Woman Years by Age, Smoking Status and Oral Contraceptive Use Adapted from P.M.
Layde and V. Beral, Lancet, 1 :541-546, 1981. Oral contraceptives may compound the effects of well-known risk factors, such as hypertension, diabetes, hyperlipidemias, age, and obesity.
In… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Postmarketing Experience: Five studies that compared breast cancer risk between ever-users (current or past use) of COCs and never-users of COCs reported no association between ever use of COCs and breast cancer risk, with effect estimates ranging from 0.90 to 1.12 (Figure 6). Three studies compared breast cancer risk between current or recent COC users (<6 months since last use) and never users of COCs (Figure 6). One of these studies reported no association between breast cancer risk and COC use.
The other two studies found an increased relative risk of 1.19 to 1.33 with current or recent use. Both of these studies found an increased risk of breast cancer with current use of longer duration, with relative risks ranging from 1.03 with less than one year of COC use to approximately 1.4 with more than 8 to 10 years of COC use. Figure 6: Risk of Breast Cancer with Combined Oral Contraceptive Use RR = relative risk; OR = odds ratio; HR = hazard ratio. “ever COC” are females with current or past COC use; “never COC use” are females that never used COCs.
An increased risk of the following serious adverse reactions (see WARNINGS section for additional information) has been associated with the use of oral contraceptives: • Thromboembolic and thrombotic disorders and other vascular problems (including thrombophlebitis and venous thrombosis with or without pulmonary embolism, mesenteric thrombosis, arterial thromboembolism, myocardial infarction, cerebral hemorrhage, cerebral thrombosis, transient ischemic attack) • Carcinoma of the reproductive organs and breasts • Hepatic neoplasia/liver disease (including hepatic adenomas or benign liver tumors) • Ocular lesions (including retinal vascular thrombosis) • Gallbladder disease • Carbohydrate and lipid effects • Elevated blood pressure • Headache including migraine The following adverse reactions have been reported in patients receiving oral contraceptives and are believed to be drug related (alphabetically listed): • Acne • Amenorrhea • Anaphylactic/anaphylactoid reactions, including urticaria, angioedema, and severe reactions with respiratory and circulatory symptoms • Breast changes: tenderness, pain, enlargement, secretion • Budd-Chiari syndrome • Cervical erosion and secretion, change in • Cholestatic jaundice • Chorea, exacerbation of • Colitis • Contact lenses, intolerance to • Corneal curvature (steepening), change in • Dizziness • Edema/fluid retention • Erythema multiforme • Erythema nodosum • Focal nodular hyperplasia • Gastrointestinal symptoms (such as abdominal pain, cramps, and bloating) • Hirsutism • Infertility after discontinuation of treatment, temporary • Lactation, diminution in, when given immediately postpartum • Libido, change in • Melasma/chloasma which may persist • Menstrual flow, change in • Mood changes, including depression • Nausea • Nervousness • Pancreatitis • Porphyria, exacerbation of • Rash (allergic) • Scalp hair, loss of • Serum folate levels, decrease in • Spotting • Systemic lupus erythematosus, exacerbation of • Unscheduled bleeding • Vaginitis, including candidiasis • Varicose veins, aggravation of • Vomiting • Weight or appetite (increase or decrease), change in The following adverse reactions have been reported in users of oral contraceptives: • Cataracts • Cystitis-like syndrome • Dysmenorrhea • Hemolytic uremic syndrome • Hemorrhagic eruption • Optic neuritis, which may lead to partial or complete loss of vision • Premenstrual syndrome • Renal function, impaired To report SUSPECTED ADVERSE EVENTS, contact Teva at 1-888-838-2872 or FDA at 1-800-FDA-1088 or http://www.fda.gov/medwatch for voluntary reporting of adverse reactions.
Figure 6
🔄 Drug Interactions ▾
Drug-Drug Interactions See PRECAUTIONS section – Drug Interactions .
9. Drug Interactions Changes in Contraceptive Effectiveness Associated with Coadministration of Other Products: Contraceptive effectiveness may be reduced when hormonal contraceptives are coadministered with antibiotics, anticonvulsants, and other drugs that increase the metabolism of contraceptive steroids. This could result in unintended pregnancy or unscheduled bleeding.
Examples include rifampin, rifabutin, barbiturates, primidone, phenylbutazone, phenytoin, dexamethasone, carbamazepine, felbamate, oxcarbazepine, topiramate, griseofulvin, and modafinil. In such cases a nonhormonal back-up method of birth control should be considered. Several cases of contraceptive failure and unscheduled bleeding have been reported in the literature with concomitant administration of antibiotics such as ampicillin and other penicillins, and tetracyclines.
However, clinical pharmacology studies investigating drug interactions between combined oral contraceptives and these antibiotics have reported inconsistent results. Enterohepatic recirculation of estrogens may also be decreased by substances that reduce gut transit time. Several of the anti-HIV protease inhibitors have been studied with coadministration of oral combination hormonal contraceptives; significant changes (increase and decrease) in the plasma levels of the estrogen and progestin have been noted in some cases.
The safety and efficacy of oral contraceptive products may be affected with coadministration of anti-HIV protease inhibitors. Health care professionals should refer to the label of the individual anti-HIV protease inhibitors for further drug-drug interaction information. Concomitant Use with HCV Combination Therapy – Liver Enzyme Elevation Do not coadminister levonorgestrel and ethinyl estradiol tablets with HCV drug combinations containing ombitasvir/paritaprevir/ritonavir, with or without dasabuvir, due to potential for ALT elevations (see WARNINGS, Risk of Liver Enzyme Elevations with Concomitant Hepatitis C Treatment ).
Herbal products containing St. John's Wort (Hypericum perforatum) may induce hepatic enzymes (cytochrome P 450) and p-glycoprotein transporter and may reduce the effectiveness of contraceptive steroids. This may also result in unscheduled bleeding.
Increase in Plasma Levels Associated with Coadministered Drugs: Coadministration of atorvastatin and certain oral contraceptives containing ethinyl estradiol increases AUC values for ethinyl estradiol by approximately 20%. Ascorbic acid and acetaminophen increase the bioavailability of ethinyl estradiol since these drugs act as competitive inhibitors for sulfation of ethinyl estradiol in the gastrointestinal wall, a known pathway of elimination for ethinyl estradiol. CYP 3A4 inhibitors such as indinavir, itraconazole, ketoconazole, fluconazole, and troleandomycin may increase plasma hormone levels.
Troleandomycin may also increase the risk of intrahepatic cholestasis during coadministration with combination oral contraceptives. Changes in Plasma Levels of Coadministered Drugs: Combination hormonal contraceptives containing some synthetic estrogens (e.g., ethinyl estradiol) may inhibit the metabolism of other compounds. Increased plasma concentrations of cyclosporine, prednisolone and other corticosteroids, and theophylline have been reported with concomitant administration of oral contraceptives.
Decreased plasma concentrations of acetaminophen and lamotrigine, and increased clearance of temazepam, salicylic acid, morphine, and clofibric acid, due to induction of conjugation (particularly glucuronidation), have been noted when these drugs were administered with oral contraceptives. The prescribing information of concomitant medications should be consulted to identify potential interactions.
👥 Use in Specific Populations ▾
Special Populations Race No formal studies on the effect of race on the pharmacokinetic parameters of Amethyst™ were conducted.
🤰 Pregnancy ▾
12. Pregnancy Pregnancy Category X. See CONTRAINDICATIONS and WARNINGS sections.
🧒 Pediatric Use ▾
14. Pediatric Use Safety and efficacy of Amethyst™ tablets have been established in women of reproductive age. Safety and efficacy are expected to be the same for postpubertal adolescents under the age of 16 and for users 16 years and older. Use of this product before menarche is not indicated.
🧓 Geriatric Use ▾
15. Geriatric Use This product has not been studied in women over 65 years of age and is not indicated in this population.
🆘 Overdosage ▾
OVERDOSAGE Symptoms of oral contraceptive overdosage in adults and children may include nausea, vomiting, breast tenderness, dizziness, abdominal pain, drowsiness/fatigue; withdrawal bleeding may occur in females. There is no specific antidote and further treatment of overdose, if necessary, is directed to the symptoms.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mode of Action Combination oral contraceptives act by suppression of gonadotropins. Although the primary mechanism of this action is inhibition of ovulation, other alterations include changes in the cervical mucus (which increase the difficulty of sperm entry into the uterus) and the endometrium (which reduce the likelihood of implantation). Pharmacokinetics Absorption No specific investigation of the absolute bioavailability of Amethyst™ in humans has been conducted.
However, literature indicates that levonorgestrel is rapidly and completely absorbed after oral administration (bioavailability about 100%) and is not subject to first-pass metabolism. Ethinyl estradiol is rapidly and almost completely absorbed from the gastrointestinal tract but, due to first-pass metabolism in gut mucosa and liver, the bioavailability of ethinyl estradiol is between 38% and 48%. A summary of the single dose and multiple dose levonorgestrel and ethinyl estradiol pharmacokinetic parameters for 18 women under fasting conditions is provided in Table 1.
The plasma concentrations of levonorgestrel and ethinyl estradiol reached steady-state by approximately day 14. Levonorgestrel and ethinyl estradiol concentrations did not increase from days 14 to 28, but did increase from days 1 to 28. Table 1: Mean (SD) Pharmacokinetic Parameters of Amethyst™ Over a 28-Day Dosing Period Levonorgestrel Day C max (ng/mL) T max (h) t 1/2 (h) AUC 0-24 (ng•h/mL) 1 2.4 (0.9) 1.2 (0.4) - 16 (8) 14 5.4 (2.1) 1.7 (1.4) - 68 (36) 28 5.7 (2.1) 1.3 (0.8) 36 (19) 74 (41) Ethinyl Estradiol Day (pg/mL) (h) (h) (pg•h/mL) 1 47.7 (20.1) 1.3 (0.5) - 378 (140) 14 72.7 (37.2) 1.4 (0.5) - 695 (361) 28 74.4 (29.7) 1.4 (0.5) 21 (7) 717 (351) The mean plasma concentrations of levonorgestrel and ethinyl estradiol following single (day 1) and multiple (days 14 and 28) oral administrations of levonorgestrel 90 mcg in combination with ethinyl estradiol 20 mcg to 18 healthy women is provided in Figure 1.
Figure 1: Mean Plasma ± SD † Concentrations of Levonorgestrel and Ethinyl Estradiol Following Single (Day 1) and Multiple (Days 14 and 28) Oral Administrations of Levonorgestrel 90 mcg in Combination with Ethinyl Estradiol 20 mcg to Healthy Women † SD = standard deviation The effect of food on the rate and the extent of levonorgestrel and ethinyl estradiol absorption following oral administration of Amethyst™ has not been evaluated. Figure 1 Distribution Levonorgestrel in serum is primarily bound to sex hormone-binding globulin (SHBG).
Ethinyl estradiol is about 97% bound to serum albumin. Ethinyl estradiol does not bind to SHBG, but induces SHBG synthesis. Metabolism Levonorgestrel: The most important metabolic pathways are reduction of the ∆4-3-oxo group and hydroxylation at positions 2α, 1β, and 16β, followed by conjugation.
Most of the circulating metabolites are sulfates of 3α, 5β-tetrahydro-levonorgestrel, while excretion occurs predominantly in the form of glucuronides. Some of the parent levonorgestrel also circulates as 17β-sulfate. Metabolic clearance rates may differ among individuals by several-fold, and this may account in part for the wide variation observed in levonorgestrel concentrations among users.
Ethinyl estradiol: Cytochrome P450 enzymes (CYP3A4) in the liver are responsible for the 2-hydroxylation that is the major oxidative reaction. The 2-hydroxy metabolite is further transformed by methylation, sulfation, and glucuronidation prior to urinary and fecal excretion. Levels of CYP3A4 vary widely among individuals and can explain the variation in rates of ethinyl estradiol 2-hydroxylation.
Excretion The terminal elimination half-life for levonorgestrel in Amethyst™ is about 36 hours. Levonorgestrel and its metabolites are excreted in the urine (40% to 68%) and in feces (16% to 48%). The terminal elimination half-life of ethinyl estradiol in Amethyst™ is about 21 hours.
Ethinyl estradiol is excreted in the urine and feces as glucuronide and sulfate conju… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Amethyst™ (levonorgestrel and ethinyl estradiol tablets, USP), 90 mcg levonorgestrel, USP and 20 mcg ethinyl estradiol, USP, is available in a 28 tablet dispenser, arranged in 4 rows of 7 active tablets as follows: 28 white, round, flat-faced, beveled edge tablets, debossed with “ Y45 ” on one side and “ TV ” on the other side (NDC 0480-3472-24). Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature]. References available upon request.
Brands listed are the trademarks of their respective owners. Manufactured For: Teva Pharmaceuticals Parsippany, NJ 07054 Rev. A 1/2022
📋 Description ▾
DESCRIPTION Twenty-eight (28) white tablets each containing 90 mcg of levonorgestrel, USP (17α)-(–)13-ethyl-17-hydroxy-18, 19-dinorpregn-4-en-20-yn-3-one, a totally synthetic progestogen, and 20 mcg of ethinyl estradiol, USP (17α)-19-norpregna-1,3,5(10)-trien-20-yne-3,17-diol. The inactive ingredients present are croscarmellose sodium, lactose monohydrate, magnesium stearate, microcrystalline cellulose, and povidone. Levonorgestrel, USP C 21 H 28 O 2 M.W.
312.45 Ethinyl Estradiol, USP C 20 H 24 O 2 M.W. 296.40 Levonorgestrel Ethinyl Estradiol
💬 Information for Patients ▾
16. Information for the Patient See DETAILED PATIENT LABELING printed below.
INFORMATION FOR THE PATIENT Brief Summary Patient Package Insert Amethyst™ ( Levonorgestrel and Ethinyl Estradiol Tablets , USP) 90 mcg / 20 mcg Rx o nly This product (like all oral contraceptives) is intended to prevent pregnancy. Oral contraceptives do not protect against transmission of HIV (AIDS) and other sexually transmitted diseases (STDs) such as chlamydia, genital herpes, genital warts, gonorrhea, hepatitis B, and syphilis. Oral contraceptives, also known as “birth-control pills” or “the pill,” are taken to prevent pregnancy, and when taken correctly, have a failure rate of approximately 1 to 2% per year (1 to 2 pregnancies per 100 women per year of use) when used without missing any pills.
The average failure rate of large numbers of pill users is approximately 5% per year (5 pregnancies per 100 women per year of use) when women who miss pills are included. However, forgetting to take pills considerably increases the chances of pregnancy. Amethyst™ is a birth-control pill that is taken every day.
When you take Amethyst™, the lining of your uterus does not undergo the changes needed for menstruation, and therefore you do not have regular menstrual periods. You are likely to have unscheduled or unplanned bleeding or spotting when you start to use Amethyst™. The number of days each month with unscheduled bleeding and spotting usually decreases over time for the majority of women.
When using Amethyst™, the convenience of having no regular menstrual periods should be weighed against the inconvenience of unscheduled or unplanned breakthrough bleeding and spotting. For the majority of women, oral contraceptives can be taken safely. However, there are some women who are at high risk of developing certain serious diseases that can be life-threatening or may cause temporary or permanent disability or death.
The risks associated with taking oral contraceptives increase significantly if you: smoke have high blood pressure, diabetes, high cholesterol, or a tendency to form blood clots, or are obese have or have had clotting disorders, heart attack, stroke, angina pectoris, cancer of the breast or sex organs, jaundice, malignant or benign liver tumors, or major surgery with prolonged immobilization have headaches with neurological symptoms You should not take the pill if you suspect you are pregnant or have unexplained vaginal bleeding.
Although cardiovascular disease risks may be increased with oral contraceptive use in healthy, nonsmoking women over 40 (even with the newer low-dose formulations), there are also greater potential health risks associated with pregnancy in older women. Cigarette smoking increases the risk of serious adverse effects on the heart and blood vessels from oral contraceptive use. This risk increases with age and with the amount of smoking (15 or more cigarettes per day has been associated with a significantly increased risk) and is quite marked in women over 35 years of age.
Women who use oral contraceptives should not smoke. Most side effects of the pill are not serious. The most common such effects are nausea, vomiting, unscheduled bleeding, weight gain, breast tenderness, and difficulty wearing contact lenses.
These side effects, especially nausea and vomiting, may subside within the first three months of use. The serious side effects of the pill occur very infrequently, especially if you are in good health and do not smoke. However, you should know that the following medical conditions have been associated with or made worse by the pill: Blood clots in the legs (thrombophlebitis), lungs (pulmonary embolism), stoppage or rupture of a blood vessel in the brain (stroke), blockage of blood vessels in the heart (heart attack and angina pectoris) or other organs of the body.
As mentioned above, smoking increases the risk of heart attacks and strokes and subsequent serious medical consequences. Women with migraine also may be at i… [Excerpted — this section continues on DailyMed.]
⚠️ Precautions ▾
PRECAUTIONS 1. General Patients should be counseled that oral contraceptives do not protect against transmission of HIV (AIDS) and other sexually transmitted diseases (STDs) such as chlamydia, genital herpes, genital warts, gonorrhea, hepatitis B, and syphilis. Scheduled withdrawal bleeding does not occur with the use of Amethyst™, therefore, the absence of withdrawal bleeding cannot be used as a sign of an unexpected pregnancy and as such, unexpected pregnancy may be difficult to recognize.
Although pregnancy is unlikely if Amethyst™ is taken as directed, if for any reason, pregnancy is suspected in a woman using Amethyst™, a pregnancy test should be performed. 2. Physical Examination and Follow-Up A periodic personal and family medical history and complete physical examination are appropriate for all women, including women using oral contraceptives.
The physical examination, however, may be deferred until after initiation of oral contraceptives if requested by the woman and judged appropriate by the clinician. The physical examination should include special reference to blood pressure, breasts, abdomen, and pelvic organs, including cervical cytology, and relevant laboratory tests. In case of undiagnosed, persistent, or recurrent abnormal vaginal bleeding, appropriate diagnostic measures should be conducted to rule out malignancy.
Women with a strong family history of breast cancer or who have breast nodules should be monitored with particular care. 3. Lipid Disorders Women who are being treated for hyperlipidemias should be followed closely if they elect to use oral contraceptives.
Some progestogens may elevate LDL levels and may render the control of hyperlipidemias more difficult. (See WARNINGS , 1a., 1d., and 8.) A small proportion of women will have adverse lipid changes while taking oral contraceptives. Nonhormonal contraception should be considered in women with uncontrolled dyslipidemias.
Persistent hypertriglyceridemia may occur in a small population of combination oral contraceptive users. Elevations of plasma triglycerides may lead to pancreatitis and other complications. 4.
Liver Function If jaundice develops in any woman receiving such drugs, the medication should be discontinued. Steroid hormones may be poorly metabolized in patients with impaired liver function. 5.
Fluid Retention Oral contraceptives may cause some degree of fluid retention. They should be prescribed with caution, and only with careful monitoring, in patients with conditions which might be aggravated by fluid retention. 6.
Emotional Disorders Patients becoming significantly depressed while taking oral contraceptives should stop the medication and use an alternate method of contraception in an attempt to determine whether the symptom is drug related. Women with a history of depression should be carefully observed and the drug discontinued if depression recurs to a serious degree. 7.
Contact Lenses Contact lens wearers who develop visual changes or changes in lens tolerance should be assessed by an ophthalmologist. 8. Gastrointestinal Diarrhea and/or vomiting may reduce hormone absorption resulting in decreased serum concentrations.
9. Drug Interactions Changes in Contraceptive Effectiveness Associated with Coadministration of Other Products: Contraceptive effectiveness may be reduced when hormonal contraceptives are coadministered with antibiotics, anticonvulsants, and other drugs that increase the metabolism of contraceptive steroids. This could result in unintended pregnancy or unscheduled bleeding.
Examples include rifampin, rifabutin, barbiturates, primidone, phenylbutazone, phenytoin, dexamethasone, carbamazepine, felbamate, oxcarbazepine, topiramate, griseofulvin, and modafinil. In such cases a nonhormonal back-up method of birth control should be considered. Several cases of contraceptive failure and unscheduled bleeding have been reported in the literature with concomitant administration of antibiotics such as ampicillin and other penici… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
13. Nursing Mothers Small amounts of oral contraceptive steroids and/or metabolites have been identified in the milk of nursing mothers, and a few adverse effects on the child have been reported, including jaundice and breast enlargement. In addition, combination oral contraceptives given in the postpartum period may interfere with lactation by decreasing the quantity and quality of breast milk.
If possible, the nursing mother should be advised not to use combination oral contraceptives, but to use other forms of contraception until she has completely weaned her child.
🧬 Pharmacokinetics ▾
Pharmacokinetics Absorption No specific investigation of the absolute bioavailability of Amethyst™ in humans has been conducted. However, literature indicates that levonorgestrel is rapidly and completely absorbed after oral administration (bioavailability about 100%) and is not subject to first-pass metabolism. Ethinyl estradiol is rapidly and almost completely absorbed from the gastrointestinal tract but, due to first-pass metabolism in gut mucosa and liver, the bioavailability of ethinyl estradiol is between 38% and 48%.
A summary of the single dose and multiple dose levonorgestrel and ethinyl estradiol pharmacokinetic parameters for 18 women under fasting conditions is provided in Table 1. The plasma concentrations of levonorgestrel and ethinyl estradiol reached steady-state by approximately day 14. Levonorgestrel and ethinyl estradiol concentrations did not increase from days 14 to 28, but did increase from days 1 to 28.
Table 1: Mean (SD) Pharmacokinetic Parameters of Amethyst™ Over a 28-Day Dosing Period Levonorgestrel Day C max (ng/mL) T max (h) t 1/2 (h) AUC 0-24 (ng•h/mL) 1 2.4 (0.9) 1.2 (0.4) - 16 (8) 14 5.4 (2.1) 1.7 (1.4) - 68 (36) 28 5.7 (2.1) 1.3 (0.8) 36 (19) 74 (41) Ethinyl Estradiol Day (pg/mL) (h) (h) (pg•h/mL) 1 47.7 (20.1) 1.3 (0.5) - 378 (140) 14 72.7 (37.2) 1.4 (0.5) - 695 (361) 28 74.4 (29.7) 1.4 (0.5) 21 (7) 717 (351) The mean plasma concentrations of levonorgestrel and ethinyl estradiol following single (day 1) and multiple (days 14 and 28) oral administrations of levonorgestrel 90 mcg in combination with ethinyl estradiol 20 mcg to 18 healthy women is provided in Figure 1.
Figure 1: Mean Plasma ± SD † Concentrations of Levonorgestrel and Ethinyl Estradiol Following Single (Day 1) and Multiple (Days 14 and 28) Oral Administrations of Levonorgestrel 90 mcg in Combination with Ethinyl Estradiol 20 mcg to Healthy Women † SD = standard deviation The effect of food on the rate and the extent of levonorgestrel and ethinyl estradiol absorption following oral administration of Amethyst™ has not been evaluated. Figure 1
🔬 Clinical Studies ▾
Clinical Studies The efficacy and safety of Amethyst™ were studied in 2 one-year clinical trials of subjects age 18 to 49. There were no exclusions for body mass index (BMI), weight, or bleeding history. The primary efficacy and safety study (313-NA) was a one-year open-label clinical trial that treated 2,134 subjects in North America.
Of these subjects 1,213 (56.8%) discontinued prematurely, including 102 (4.8%) discontinued by the Sponsor for early study closure. The mean weight of subjects in this study was 70.38 kg. The efficacy of Amethyst™ was assessed by the number of pregnancies that occurred after the onset of treatment and within 14 days of the last dose.
Among subjects 35 years or less, there were 23 pregnancies (4 of these occurred during the interval 1 to 14 days after the last day of pill use) during 12,572 28-day pill packs of use. The resulting total Pearl Index was 2.38 (95% CI: 1.51, 3.57) and the one-year life table pregnancy rate was 2.39 (95% CI: 1.57, 3.62). Pill pack cycles during which subjects used back-up contraception or were not sexually active were not included in these calculations.
Among women 35 years or less who took the pills completely as directed, there were 15 pregnancies (method failures) resulting in a Pearl Index of 1.55 (95% CI: 0.87, 2.56) and the one-year life table pregnancy rate was 1.59 (95% CI: 0.95 to 2.67). In a second supportive study conducted in Europe (315-EU), 641 subjects were randomized to Amethyst™ (n=323) or the cyclic comparator of 100 mcg levonorgestrel and 20 mcg ethinyl estradiol (n=318). The mean weight of subjects in this study was 63.86 kg.
The efficacy analysis among women 35 years or less included 2,756 Amethyst™ pill packs and 2,886 cyclic comparator pill packs. There was one pregnancy in the Amethyst™ group that occurred within 14 days following the last dose. There were three pregnancies in the cyclic comparator group.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
11. Carcinogenesis See WARNINGS section.
📄 Patient Package Insert ▾
DETAILED PATIENT LABELING This product (like all oral contraceptives) is intended to prevent pregnancy. Oral contraceptives do not protect against transmission of HIV (AIDS) and other sexually transmitted diseases (STDs) such as chlamydia, genital herpes, genital warts, gonorrhea, hepatitis B, and syphilis. INTRODUCTION Any woman who considers using oral contraceptives (the “birth-control pill” or “the pill”) should understand the benefits and risks of using this form of birth control.
This leaflet will give you much of the information you will need to make this decision and will also help you determine if you are at risk of developing any of the serious side effects of the pill. It will tell you how to use the pill properly so that it will be as effective as possible. However, this leaflet is not a replacement for a careful discussion between you and your health care professional.
You should discuss the information provided in this leaflet with him or her, both when you first start taking the pill and during your revisits. You should also follow your health care professional’s advice with regard to regular checkups while you are on the pill. Amethyst™ is a birth-control pill that is taken every day.
When you take Amethyst™, the lining of your uterus does not undergo the changes needed for menstruation, and therefore you do not have regular menstrual periods. You are likely to have unscheduled or unplanned bleeding or spotting when you start to use Amethyst™. The number of days each month with unscheduled bleeding and spotting usually decreases over time for the majority of women.
When using Amethyst™, the convenience of having no regular menstrual periods should be weighed against the inconvenience of unscheduled or unplanned breakthrough bleeding and spotting. EFFECTIVENESS OF ORAL CONTRACEPTIVES Oral contraceptives or “birth-control pills” or “the pill” are used to prevent pregnancy and are more effective than other nonsurgical methods of birth control. When they are taken correctly, without missing any pills the chance of becoming pregnant is approximately 1 to 2% per year (1 to 2 pregnancies per 100 women per year of use).
Average failure rates are approximately 5% per year (5 pregnancies per 100 women per year of use) when women who miss pills are included. The chance of becoming pregnant increases with each missed pill. In comparison, average failure rates for other methods of birth control during the first year of use are as follows: IUD: 0.1 to 2% Female condom alone: 21% Depo-Provera ® (injectable progestogen): 0.3% Cervical cap Norplant ® System (levonorgestrel implants): 0.05% Never given birth: 20% Diaphragm with spermicides: 20% Given birth: 40% Spermicides alone: 26% Periodic abstinence: 25% Male condom alone: 14% No methods: 85% WHO SHOULD NOT TAKE ORAL CONTRACEPTIVES Although cardiovascular disease risks may be increased with oral contraceptive use in healthy, nonsmoking women over 40 (even with the newer low-dose formulations), there are also greater potential health risks associated with pregnancy in older women.
Cigarette smoking increases the risk of serious adverse effects on the heart and blood vessels from oral contraceptive use. This risk increases with age and with the amount of smoking (15 or more cigarettes per day has been associated with a significantly increased risk) and is quite marked in women over 35 years of age. Women who use oral contraceptives should not smoke.
Some women should not use the pill. For example, you should not take the pill if you have any of the following conditions: History of heart attack or stroke. Blood clots in the legs (thrombophlebitis), lungs (pulmonary embolism), or eyes.
History of blood clots in the deep veins of your legs. Hereditary or acquired blood clotting disorders. Chest pain (angina pectoris).
Known or suspected breast cancer or cancer of the lining of the uterus, cervix or vagina, or certain hormonally-sensitive cancers. Unexplained vaginal bleeding (unt… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL NDC 0480-3472-24 Amethyst™ (Levonorgestrel and Ethinyl Estradiol Tablets, USP) 90 mcg/20 mcg Each Tablet Contains: 90 mcg levonorgestrel, USP and 20 mcg ethinyl estradiol, USP THIS PRODUCT (LIKE ALL ORAL CONTRACEPTIVES) IS INTENDED TO PREVENT PREGNANCY. ORAL CONTRACEPTIVES DO NOT PROTECT AGAINST TRANSMISSION OF HIV (AIDS) AND OTHER SEXUALLY TRANSMITTED DISEASES (STDs) SUCH AS CHLAMYDIA, GENITAL HERPES, GENITAL WARTS, GONORRHEA, HEPATITIS B, AND SYPHILIS. PHARMACIST: Each dispenser contains a combined Detailed Patient Labeling and Brief Patient Labeling.
It should be included with each package dispensed to the patient. Rx only 1 Tablet Dispenser, 28 Tablets Each Carton