
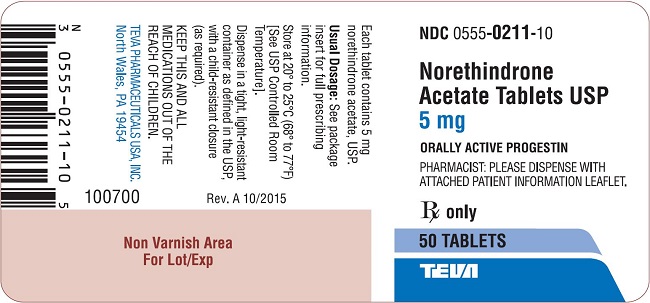
Norethindrone Acetate 5 mg Tablet, 50-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Progestin class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- It depends on the product. Most norethindrone tablets — including brands like Camila, Errin, Emzahh, and Affodel — are progestin-only birth control pills taken daily to prevent pre...
- Regular combination birth control pills contain two hormones — estrogen and progestin. Norethindrone is a progestin-only pill, sometimes called the 'mini-pill.' Because it has no e...
- How is this different from regular birth control pills?
- The most common thing people notice is irregular bleeding — spotting between periods, or changes in your cycle. Headache, breast tenderness, nausea, and dizziness are also reported...
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.295 | $14.74 / 50 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.4746 | $23.73 / 50 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.4972 | $24.86 / 50 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Norethindrone Acetate 5 mgthis 00555-0211-10 | Teva | 50 tablets | $0.295 | AB | Availability likely | — |
| Norethindrone acetate 5 mg 50742-0267-50 | Ingenus | 50 tablets | $0.295 | AB | Availability likely | — |
| Norethindrone Acetate 5 mg 60687-0921-21 | American | 30 tablets | $0.295 | AB | Availability likely | — |
| Gallifrey 5 mg 70700-0326-50 | Xiromed | 50 tablets | $0.295 | AB | Availability likely | — |
| Norethindrone Acetate 5 mg 42291-0650-90 | AvKARE | 90 tablets | — | AB | FDA listed | — |
| Norethindrone Acetate 5 mg 51407-0599-50 | Golden | 50 tablets | — | AB | FDA listed | — |
| Norethindrone Acetate 5 mg 65162-0475-03 | Amneal | 30 tablets | — | AB | FDA listed | — |
| Norethindrone Acetate 5 mg 68462-0304-05 | Glenmark | 500 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00555-0211-10 You're viewing this | 50 TABLET in 1 BOTTLE (0555-0211-10) | 2001-06-29 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Norethindrone Acetate Tablets, USP are indicated for the treatment of secondary amenorrhea, endometriosis, and abnormal uterine bleeding due to hormonal imbalance in the absence of organic pathology, such as submucous fibroids or uterine cancer. Norethindrone Acetate Tablets, USP are not intended, recommended or approved to be used with concomitant estrogen therapy in postmenopausal women for endometrial protection.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Therapy with norethindrone acetate tablets must be adapted to the specific indications and therapeutic response of the individual patient. Secondary amenorrhea, abnormal uterine bleeding due to hormonal imbalance in the absence of organic pathology 2.5 to 10 mg norethindrone acetate tablets may be given daily for 5 to 10 days to produce secretory transformation of an endometrium that has been adequately primed with either endogenous or exogenous estrogen. Progestin withdrawal bleeding usually occurs within three to seven days after discontinuing norethindrone acetate tablets therapy.
Patients with a past history of recurrent episodes of abnormal uterine bleeding may benefit from planned menstrual cycling with norethindrone acetate tablets. Endometriosis Initial daily dosage of 5 mg norethindrone acetate tablets for two weeks. Dosage should be increased by 2.5 mg per day every two weeks until 15 mg per day of norethindrone acetate tablets is reached.
Therapy may be held at this level for six to nine months or until annoying breakthrough bleeding demands temporary termination.
⛔ Contraindications ▾
CONTRAINDICATIONS Known or suspected pregnancy. There is no indication for norethindrone acetate in pregnancy. (See PRECAUTIONS .) Undiagnosed vaginal bleeding Known, suspected or history of cancer of the breast Active deep vein thrombosis, pulmonary embolism or history of these conditions Active or recent (e.g., within the past year) arterial thromboembolic disease (e.g., stroke, myocardial infarction) Impaired liver function or liver disease As a diagnostic test for pregnancy Hypersensitivity to any of the drug components
⚠️ Warnings ▾
WARNINGS Cardiovascular Disorders Patients with risk factors for arterial vascular disease (e.g., hypertension, diabetes mellitus, tobacco use, hypercholesterolemia, and obesity) and/or venous thromboembolism (e.g., personal history or family history of VTE, obesity, and systemic lupus erythematosus) should be managed appropriately. Visual Abnormalities Discontinue medication pending examination if there is a sudden partial or complete loss of vision or if there is sudden onset of proptosis, diplopia, or migraine. If examination reveals papilledema or retinal vascular lesions, medication should be discontinued.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS See WARNINGS and PRECAUTIONS . The following adverse reactions have been observed in women taking progestins: Breakthrough bleeding Spotting Change in menstrual flow Amenorrhea Edema Changes in weight (decreases, increases) Changes in the cervical squamo-columnar junction and cervical secretions Cholestatic jaundice Rash (allergic) with and without pruritus Melasma or chloasma Clinical depression Acne Breast enlargement/tenderness Headache/migraine Urticaria Abnormalities of liver tests (i.e., AST, ALT, Bilirubin) Decreased HDL cholesterol and increased LDL/HDL ratio Mood swings Nausea Insomnia Anaphylactic/anaphylactoid reactions Thrombotic and thromboembolic events (e.g., deep vein thrombosis, pulmonary embolism, retinal vascular thrombosis, cerebral thrombosis and embolism) Optic neuritis (which may lead to partial or complete loss of vision) To report SUSPECTED ADVERSE REACTIONS, contact Teva at 1-888-838-2872 or FDA at 1-800-FDA-1088 or http://www.fda.gov/medwatch.
🔄 Drug / Laboratory Test Interactions ▾
Drug/Laboratory Tests Interactions The following laboratory test results may be altered by the use of estrogen/progestin combination drugs: Accelerated prothrombin time, partial thromboplastin time, and platelet aggregation time; increased platelet count; increased factors II, VII antigen, VIII antigen, VIII coagulant activity, IX, X, XII, VII-X complex, II-VII-X complex, and beta-thromboglobulin; decreased levels of antifactor X a and antithrombin III, decreased antithrombin III activity; increased levels of fibrinogen and fibrinogen activity; increased plasminogen antigen and activity.
Increased thyroid-binding globulin (TBG) levels leading to increased circulating total thyroid hormone levels as measured by protein-bound iodine (PBI), T 4 levels (by column or by radioimmunoassay) or T 3 levels by radioimmunoassay. T 3 resin uptake is decreased, reflecting the elevated TBG. Free T 4 and free T 3 concentrations are unaltered.
Patients on thyroid replacement therapy may require higher doses of thyroid hormone. Other binding proteins may be elevated in serum (i.e., corticosteroid binding globulin (CBG), sex hormone binding globulin (SHBG)) leading to increased circulating corticosteroid and sex steroids, respectively. Free or biologically active hormone concentrations are unchanged.
Other plasma proteins may be increased (angiotensinogen/renin substrate, alpha-1-antitrypsin, ceruloplasmin). Increased plasma HDL and HDL 2 cholesterol subfraction concentrations, reduced LDL cholesterol concentration, increased triglycerides levels. Impaired glucose metabolism.
Reduced response to metyrapone test.
🤰 Pregnancy ▾
Pregnancy Norethindrone acetate is contraindicated during pregnancy as it may cause fetal harm when administered to pregnant women. Several reports suggest an association between intrauterine exposure to progestational drugs in the first trimester of pregnancy and congenital abnormalities in male and female fetuses. Some progestational drugs induce mild virilization of the external genitalia of female fetuses.
🧒 Pediatric Use ▾
Pediatric Use Norethindrone acetate tablets are not indicated in children.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Norethindrone acetate induces secretory changes in an estrogen-primed endometrium. On a weight basis, it is twice as potent as norethindrone. Pharmacokinetics Absorption Norethindrone acetate is completely and rapidly deacetylated to norethindrone (NET) after oral administration, and the disposition of norethindrone acetate is indistinguishable from that of orally administered norethindrone.
Norethindrone acetate is rapidly absorbed from norethindrone acetate tablets, with maximum plasma concentration of norethindrone generally occurring at about 2 hours post-dose. The pharmacokinetic parameters of norethindrone following single oral administration of norethindrone acetate in 29 healthy female volunteers are summarized in Table 1. Table 1 Pharmacokinetic Parameters after a Single Dose of Norethindrone Acetate in Healthy Women Norethindrone Acetate (n = 29) Arithmetic Mean ± SD Norethindrone (NET) AUC (0-inf)(ng/ml*h) 166.90 ±
56.28C max (ng/ml) 26.19 ± 6.19 t max (h) 1.83 ± 0.58 t 1/2 (h) 8.51 ±
2.19AUC = area under the curve, C max = maximum plasma concentration, t max = time at maximum plasma concentration, t 1/2 = half-life, SD = standard deviation Figure 1. Mean Plasma Concentration Profile after a Single Dose of 5 mg Administered to 29 Healthy Female Volunteers under Fasting Conditions Figure 1 Effect of Food The effect of food administration on the pharmacokinetics of norethindrone acetate has not been studied. Distribution Norethindrone is 36% bound to sex hormone-binding globulin (SHBG) and 61% bound to albumin.
Volume of distribution of norethindrone is about 4 L/kg. Metabolism Norethindrone undergoes extensive biotransformation, primarily via reduction, followed by sulfate and glucuronide conjugation. The majority of metabolites in the circulation are sulfates, with glucuronides accounting for most of the urinary metabolites.
Excretion Plasma clearance value for norethindrone is approximately
0.4L/hr/kg. Norethindrone is excreted in both urine and feces, primarily as metabolites. The mean terminal elimination half-life of norethindrone following a single dose administration of norethindrone acetate is approximately 9 hours.
Special Populations Geriatrics The effect of age on the pharmacokinetics of norethindrone after norethindrone acetate administration has not been evaluated. Race The effect of race on the disposition of norethindrone after norethindrone acetate administration has not been evaluated. Renal Insufficiency The effect of renal disease on the disposition of norethindrone after norethindrone acetate administration has not been evaluated.
In premenopausal women with chronic renal failure undergoing peritoneal dialysis who received multiple doses of an oral contraceptive containing ethinyl estradiol and norethindrone, plasma norethindrone concentration was unchanged compared to concentrations in premenopausal women with normal renal function. Hepatic Insufficiency The effect of hepatic disease on the disposition of norethindrone after norethindrone acetate administration has not been evaluated. However, norethindrone acetate is contraindicated in markedly impaired liver function or liver disease.
Drug Interactions No pharmacokinetic drug interaction studies investigating any drug-drug interactions with norethindrone acetate have been conducted.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Norethindrone Acetate Tablets, USP are available as: 5 mg: White, oval, flat-faced, beveled-edge, scored tablet. Debossed with stylized b on one side and 211/5 on the scored side. Available in bottles of 50 tablets (NDC 0555-0211-10).
Dispense in a tight, light-resistant container as defined in the USP, with a child-resistant closure (as required). Store at 20º to 25ºC (68º to 77ºF) [See USP Controlled Room Temperature]. Keep this and all medications out of the reach of children.
Manufactured For: Teva Pharmaceuticals Parsippany, NJ 07054 Rev. B 11/2022
📋 Description ▾
DESCRIPTION Norethindrone Acetate Tablets, USP (17-hydroxy-19-nor-17α-pregn-4-en-20-yn-3-one acetate), a synthetic, orally active progestin, is the acetic acid ester of norethindrone. It is a white, or creamy white, crystalline powder. The structural formula is as follows: C 22 H 28 O 3 M.W.
340.46 Each Norethindrone Acetate Tablet, USP for oral administration, contains norethindrone acetate, USP 5 mg. In addition, each tablet contains the following inactive ingredients: anhydrous lactose, magnesium stearate, and microcrystalline cellulose. Norethindrone Acetate structural formula
💬 Information for Patients ▾
Information for the Patient Healthcare providers are advised to discuss the PATIENT INFORMATION leaflet with patients for whom they prescribe norethindrone acetate tablets.