
Estazolam 2 mg Tablet, 80,004-count — NDC 0591-0745-77 (Billing 00591-0745-77)
This is a package of 80,004 tablets of Estazolam 2 mg Tablet from Actavis Pharma, Inc., marketed since Oct 1997 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 0591-0745-77 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0591 labeler · 0745 product · 77 package
- Package marketed since
- Jul 31, 2024
- Listing certified through
- Dec 31, 2026
- Barcode (UPC)
- 0305910745011, 0305910744014
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 015604
- GCN: 19182
- GPI-14 (Medi-Span): 60201005000320
- HICL (First Databank): 006036
- AHFS class code: 28:24.08.00
- RxCUI (RxNorm): 197653
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Benzodiazepine class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It's used for short-term treatment of insomnia, meaning trouble falling asleep, waking often, or waking too early. Because insomnia often comes and goes, it isn't meant for long-te...
- Take it by mouth at bedtime, exactly as your prescriber directs. Don't take more than prescribed. If you've been on it a while, don't stop suddenly. Your prescriber will help you t...
- Sleepiness is the most common one. You may also feel dizzy, uncoordinated, weak, or slowed down, and some people feel groggy the next day. Avoid driving or anything needing full al...
- Alcohol adds to the sedation, so it's best avoided. Opioid pain medicines are especially risky because the combination can slow breathing dangerously, even causing coma or death. A...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Estazolam — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 5, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 00591-0745-01 0591-0745-01 Main listing | 100 TABLET in 1 BOTTLE, PLASTIC | $0.8394 / ea | $83.94 | 1997-10-01 | — | Active |
| 00591-0745-00 0591-0745-00 | 66700 TABLET in 1 BAG | — | — | — | — | Active |
| 00591-0745-77 You're viewing this | 80004 TABLET in 1 CONTAINER | — | — | — | — | Active |
You're viewing the largest of 3 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 00591-0745-01?
What NDC number is used to bill for this package of Estazolam 2 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Estazolam 2 mg 70954-0481-10 | Novitium | 100 tablets | $0.839 | AB | Availability likely | — |
| Estazolam 2 mg 75907-0029-01 | Dr. | 100 tablets | $0.839 | AB | Availability likely | — |
| Estazolam 2 mgthis 00591-0745-77 | Actavis | 80004 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Actavis Pharma, Inc. labeler code 00591
- Glipizide 5 mg Tablet NDC 0591-0460-00
- Glipizide 10 mg Tablet NDC 0591-0461-00
- Propafenone HCl Propafenone hydrochloride 150 mg Tablet, Film Coated NDC 0591-0582-00
- Labetalol hydrochloride 100 mg Tablet, Film Coated NDC 0591-0605-00
- Labetalol hydrochloride 200 mg Tablet, Film Coated NDC 0591-0606-00
- Estazolam 1 mg Tablet NDC 0591-0744-00
- Dicyclomine Hydrochloride 10 mg Capsule NDC 0591-0794-00
- Dicyclomine Hydrochloride 20 mg Tablet NDC 0591-0795-00
- Lisinopril and Hydrochlorothiazide 10 mg; 12.5 mg Tablet NDC 0591-0860-00
- Lisinopril and Hydrochlorothiazide 20 mg; 12.5 mg Tablet NDC 0591-0861-00
- Lisinopril and hydrochlorothiazide 20 mg; 25 mg Tablet NDC 0591-0862-00
- Lisinopril 30 mg Tablet NDC 0591-0885-00
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: RISKS FROM CONCOMITANT USE WITH OPIOIDS; ABUSE, MISUSE, AND ADDICTION; and DEPENDENCE AND WITHDRAWAL REACTIONS Concomitant use of benzodiazepines and opioids may result in profound sedation, respiratory depression, coma, and death (see WARNINGS ). Reserve concomitant prescribing of these drugs in patients for whom alternative treatment options are inadequate. Limit dosages and durations to the minimum required.
Follow patients for signs and symptoms of respiratory depression and sedation (see WARNINGS and PRECAUTIONS ). The use of benzodiazepines, including estazolam, exposes users to risks of abuse, misuse, and addiction, which can lead to overdose or death. Abuse and misuse of benzodiazepines commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes.
Before prescribing estazolam and throughout treatment, assess each patient’s risk for abuse, misuse, and addiction (see WARNINGS). The continued use of benzodiazepines, including estazolam, may lead to clinically significant physical dependence. The risks of dependence and withdrawal increase with longer treatment duration and higher daily dose.
Abrupt discontinuation or rapid dosage reduction of estazolam after continued use may precipitate acute withdrawal reactions, which can be life-threatening. To reduce the risk of withdrawal reactions, use a gradual taper to discontinue estazolam or reduce the dosage (see DOSAGE AND ADMINISTRATION and WARNINGS ).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Estazolam tablets, USP are indicated for the short-term management of insomnia characterized by difficulty in falling asleep, frequent nocturnal awakenings, and/or early morning awakenings. Both outpatient studies and a sleep laboratory study have shown that estazolam administered at bedtime improved sleep induction and sleep maintenance (see CLINICAL PHARMACOLOGY ). Because insomnia is often transient and intermittent, the prolonged administration of estazolam is generally neither necessary nor recommended.
Since insomnia may be a symptom of several other disorders, the possibility that the complaint may be related to a condition for which there is a more specific treatment should be considered. There is evidence to support the ability of estazolam to enhance the duration and quality of sleep for intervals up to 12 weeks (see CLINICAL PHARMACOLOGY ).
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The recommended initial dose for adults is 1 mg at bedtime; however, some patients may need a 2 mg dose. In healthy elderly patients, 1 mg is also the appropriate starting dose, but increases should be initiated with particular care. In small or debilitated older patients, a starting dose of 0.5 mg, while only marginally effective in the overall elderly population, should be considered.
Discontinuation or Dosage Reduction of Estazolam To reduce the risk of withdrawal reactions, use a gradual taper to discontinue estazolam or reduce the dosage. If a patient develops withdrawal reactions, consider pausing the taper or increasing the dosage to the previous tapered dosage level. Subsequently decrease the dosage more slowly (see WARNINGS , Dependence and Withdrawal Reactions and DRUG ABUSE AND DEPENDENCE, Dependence ).
⛔ Contraindications ▾
CONTRAINDICATIONS Estazolam is contraindicated with ketoconazole and itraconazole, since these medications significantly impair oxidative metabolism mediated by CYP3A (see WARNINGS and PRECAUTIONS, Drug Interactions ).
⚠️ Warnings ▾
WARNINGS Risks from Concomitant Use with Opioids Concomitant use of benzodiazepines, including estazolam, and opioids may result in profound sedation, respiratory depression, coma, and death. Because of these risks, reserve concomitant prescribing of these drugs in patients for whom alternative treatment options are inadequate. Observational studies have demonstrated that concomitant use of opioid analgesics and benzodiazepines increases the risk of drug-related mortality compared to use of opioids alone.
If a decision is made to prescribe estazolam concomitantly with opioids, prescribe the lowest effective dosages and minimum durations of concomitant use, and follow patients closely for signs and symptoms of respiratory depression and sedation. In patients already receiving an opioid analgesic, prescribe a lower initial dose of estazolam than indicated in the absence of an opioid and titrate based on clinical response. If an opioid is initiated in a patient already taking estazolam, prescribe a lower initial dose of the opioid and titrate based upon clinical response.
Advise both patients and caregivers about the risks of respiratory depression and sedation when estazolam is used with opioids. Advise patients not to drive or operate heavy machinery until the effects of concomitant use with the opioid have been determined (see PRECAUTIONS , Drug Interactions ). Abuse, Misuse, and Addiction The use of benzodiazepines, including estazolam, exposes users to the risks of abuse, misuse, and addiction, which can lead to overdose or death.
Abuse and misuse of benzodiazepines often (but not always) involve the use of doses greater than the maximum recommended dosage and commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes, including respiratory depression, overdose, or death (see DRUG ABUSE AND DEPENDENCE , Abuse ) . Before prescribing estazolam and throughout treatment, assess each patient’s risk for abuse, misuse, and addiction (e.g., using a standardized screening tool).
Use of estazolam, particularly in patients at elevated risk, necessitates counseling about the risks and proper use of estazolam along with monitoring for signs and symptoms of abuse, misuse, and addiction. Prescribe the lowest effective dosage; avoid or minimize concomitant use of CNS depressants and other substances associated with abuse, misuse, and addiction (e.g., opioid analgesics, stimulants); and advise patients on the proper disposal of unused drug. If a substance use disorder is suspected, evaluate the patient and institute (or refer them for) early treatment, as appropriate.
Dependence and Withdrawal Reactions To reduce the risk of withdrawal reactions, use a gradual taper to discontinue estazolam or reduce the dosage (a patient-specific plan should be used to taper the dose) (see DOSAGE AND ADMINISTRATION , Discontinuation or Dosage Reduction of Estazolam ). Patients at an increased risk of withdrawal adverse reactions after benzodiazepine discontinuation or rapid dosage reduction include those who take higher dosages, and those who have had longer durations of use. Acute Withdrawal Reactions The continued use of benzodiazepines, including estazolam, may lead to clinically significant physical dependence.
Abrupt discontinuation or rapid dosage reduction of estazolam after continued use, or administration of flumazenil (a benzodiazepine antagonist) may precipitate acute withdrawal reactions, which can be life-threatening (e.g., seizures) (see DRUG ABUSE AND DEPENDENCE , Dependence ) . Protracted Withdrawal Syndrome In some cases, benzodiazepine users have developed a protracted withdrawal syndrome with withdrawal symptoms lasting weeks to more than 12 months (see DRUG ABUSE AND DEPENDENCE , Dependence ). Because sleep disturbances may be the presenting manifestation of a physical and/or psychiatric disorder, symptomatic treatment of insomnia… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Commonly Observed The most commonly observed adverse events associated with the use of estazolam, not seen at an equivalent incidence among placebo-treated patients were somnolence, hypokinesia, dizziness, and abnormal coordination. A ssociated with Discontinuation of Treatment Approximately 3% of 1277 patients who received estazolam in U.S. premarketing clinical trials discontinued treatment because of an adverse clinical event. The only event commonly associated with discontinuation, accounting for 1.3% of the total, was somnolence.
Incidence in Controlled Clinical Trials The table below enumerates adverse events that occurred at an incidence of 1% or greater among patients with insomnia who received estazolam in 7-night, placebo-controlled trials. Events reported by investigators were classified into standard dictionary (COSTART) terms to establish event frequencies. Event frequencies reported were not corrected for the occurrence of these events at baseline.
The frequencies were obtained from data pooled across six studies: estazolam, N = 685; placebo, N = 433. The prescriber should be aware that these figures cannot be used to predict the incidence of side effects in the course of usual medical practice in which patient characteristics and other factors differ from those that prevailed in these six clinical trials. Similarly, the cited frequencies cannot be compared with figures obtained from other clinical investigators involving related drug products and uses, since each group of drug trials was conducted under a different set of conditions.
However, the cited figures provide the physician with a basis of estimating the relative contribution of drug and nondrug factors to the incidence of side effects in the population studied. INCIDENCE OF ADVERSE EXPERIENCES IN PLACEBO-CONTROLLED CLINICAL TRIALS (Percentage of Patients Reporting) Estazolam Placebo Body System/Adverse Event* (N=685) (N=433) Body as a Whole Headache 16 27 Asthenia 11 8 Malaise 5 5 Lower extremity pain 3 2 Back pain 2 2 Body pain 2 2 Abdominal pain 1 2 Chest pain 1 1 Digestive System Nausea 4 5 Dyspepsia 2 2 Musculoskeletal System Stiffness 1 -- Nervous System Somnolence 42 27 Hypokinesia 8 4 Nervousness 8 11 Dizziness 7 3 Coordination abnormal 4 1 Hangover 3 2 Confusion 2 -- Depression 2 3 Dream abnormal 2 2 Thinking abnormal 2 1 Respiratory System Cold symptoms 3 5 Pharyngitis 1 2 Skin and Appendages Pruritus 1 -- * Events reported by at least 1% of estazolam patients.
Other Adverse Events During clinical trials, some of which were not placebo-controlled, estazolam was administered to approximately 1300 patients. Untoward events associated with this exposure were recorded by clinical investigators using terminology of their own choosing. To provide a meaningful estimate of the proportion of individuals experiencing adverse events, similar types of untoward events must be grouped into a smaller number of standardized event categories.
In the tabulations that follow, a standard COSTART dictionary terminology has been used to classify reported adverse events. The frequencies presented, therefore, represent the proportion of the 1277 individuals exposed to estazolam who experienced an event of the type cited on at least one occasion while receiving estazolam. All reported events are included except those already listed in the previous table, those COSTART terms too general to be informative, and those events where a drug cause was remote.
Events are further classified within body system categories and enumerated in order of decreasing frequency using the following definitions: frequent adverse events are defined as those occurring on one or more occasions in at least 1/100 patients; infrequent adverse events are those occurring in 1/100 to 1/1000 patients; rare events are those occurring in less than 1/1000 patients. It is important to emphasize that, although the events reported did occur during treatment with estazolam, they were not ne… [Excerpted — this section continues on DailyMed.]
🆘 Overdosage ▾
OVERDOSAGE Overdosage of benzodiazepines is characterized by central nervous system depression ranging from drowsiness to coma. In mild to moderate cases, symptoms can include drowsiness, confusion, dysarthria, lethargy, hypnotic state, diminished reflexes, ataxia, and hypotonia. Rarely, paradoxical or disinhibitory reactions (including agitation, irritability, impulsivity, violent behavior, confusion, restlessness, excitement, and talkativeness) may occur.
In severe overdosage cases, patients may develop respiratory depression and coma. Overdosage of benzodiazepines in combination with other CNS depressants (including alcohol and opioids) may be fatal (see WARNINGS: Dependence and Withdrawal Reactions ). Markedly abnormal (lowered or elevated) blood pressure, heart rate, or respiratory rate raise the concern that additional drugs and/or alcohol are involved in the overdosage.
In managing benzodiazepine overdosage, employ general supportive measures, including intravenous fluids and airway management. Flumazenil, a specific benzodiazepine receptor antagonist, is indicated for the complete or partial reversal of the sedative effects of benzodiazepines in the management of benzodiazepine overdosage, can lead to withdrawal and adverse reactions, including seizures, particularly in the context of mixed overdosage with drugs that increase seizure risk (e.g., tricyclic and tetracyclic antidepressants) and in patients with long-term benzodiazepine use and physical dependency.
The risk of withdrawal seizures with flumazenil use may be increased in patients with epilepsy. Flumazenil is contraindicated in patients who have received a benzodiazepine for control of a potentially life-threatening condition (e.g., status epilepticus). If the decision is made to use flumazenil, it should be used as an adjunct to, not as a substitute for, supportive management of benzodiazepine overdosage.
See the flumazenil injection Prescribing Information. Consider contacting a poison center (1-800-222-1222), poisoncontrol.org, or a medical toxicologist for additional overdosage management recommendations.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Pharmacokinetics Absorption Estazolam tablets have been found to be equivalent in absorption to an orally administered solution of estazolam. In healthy subjects who received up to three times the recommended dose of estazolam, peak estazolam plasma concentrations occurred within two hours after dosing (range 0.5 to 6 hours) and were proportional to the administered dose, suggesting linear pharmacokinetics over the dosage range tested. Distribution Independent of concentration, estazolam in plasma is 93% protein bound.
Metabolism Estazolam is extensively metabolized. Only two metabolites (1-oxo-estazolam and 4-hydroxy-estazolam) were detected in human plasma up to 18 hours. The pharmacologic activity of estazolam is primarily from the parent drug.
The elimination of the parent drug takes place via hepatic metabolism of estazolam to hydroxylated and other metabolites that are eliminated largely in the urine both free and conjugated. In humans, greater than 70% of a single dose of estazolam was recovered in the urine as metabolites. Less than 5% of a 2 mg dose of estazolam was excreted unchanged in the urine, with only 4% of the dose appearing in the feces.
The principal urinary excretion product is an unidentified metabolite, presumed to be a metabolic product of 4-hydroxy-estazolam, accounting for at least 27% of the administered dose. 4-hydroxy-estazolam is the major metabolite in plasma, with concentrations approaching 12% of those of the parent eight hours after administration. Urinary 4-hydroxy-estazolam and 1-oxo-estazolam account for 11.9% and 4.4% of the dose respectively.
In vitro studies with human liver microsomes indicate that the biotransformation of estazolam to the major circulating metabolite 4-hydroxy-estazolam is mediated by cytochrome P450 3A (CYP3A). While 4-hydroxy-estazolam and the lesser metabolite, 1-oxo-estazolam, have some pharmacologic activity, their low potencies and low concentrations preclude any significant contribution to the hypnotic effect of estazolam. Elimination The range of estimates for the mean elimination half-life of estazolam varied from 10 to 24 hours.
Radiolabel mass balance studies indicate that the main route of excretion is via the kidneys. After 5 days, 87% of the administered radioactivity was excreted in human urine. Less than 4% of the dose was excreted unchanged.
Eleven metabolites were found in urine. Four metabolites were identified as 1-oxo-estazolam, 4’-hydroxy-estazolam, 4-hydroxy-estazolam, and benzophenone, as free metabolites and glucuronides. The predominant metabolite in urine (17% of the administered dose) has not been identified, but is likely to be a metabolite of 4-hydroxy-estazolam.
Special Populations In a small study (N=8) using various doses in older subjects (59 to 68 years), peak estazolam concentrations were found to be similar to those observed in younger subjects with a mean elimination half-life of 18.4 hours (range 13.5 to 34.6 hours). The influence of hepatic or renal impairment on the pharmacokinetics of estazolam has not been studied. Pediatrics The pharmacokinetics of estazolam have not been studied in pediatric patients.
Race The influence of race on the pharmacokinetics of estazolam has not been studied. Gender The gender-effect on the pharmacokinetics of estazolam has not been investigated. Cigarette Smoking The clearance of benzodiazepines is accelerated in smokers compared to nonsmokers, and there is evidence that this occurs with estazolam.
This decrease in half-life, presumably due to enzyme induction by smoking, is consistent with other drugs with similar hepatic clearance characteristics. In all subjects and at all doses, the mean elimination half-life appeared to be independent of the dose. Drug-Drug Interaction The metabolism of estazolam to the major circulating metabolite 4-hydroxy-estazolam is catalyzed by CYP3A.
While no in vivo drug-drug interaction studies were conducted between estazolam and inhibitors/indu… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Estazolam tablets USP, 1 mg are white, scored, diamond-shaped tablets, debossed with 744 above the score and 1 below the score on one side, and WATSON on the other side, supplied in bottles of 100 (NDC 0591-0744-01). Estazolam tablets USP, 2 mg are dark pink, scored, diamond-shaped tablets, debossed with 745 above the score and 2 below the score on one side, and WATSON on the other side, supplied in bottles of 100 (NDC 0591-0745-01). Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature].
Dispense in a tight, light-resistant container as defined in the USP, with a child-resistant closure (as required). Manufactured In India By: Watson Pharma Private Limited Verna, Salcette Goa 403 722 INDIA Manufactured For: Teva Pharmaceuticals Parsippany, NJ 07054 Rev. G 6/2024
📋 Description ▾
DESCRIPTION Estazolam, USP, a triazolobenzodiazepine derivative, is an oral hypnotic agent. Estazolam occurs as a fine, white, odorless powder that is soluble in alcohol and practically insoluble in water. The chemical name for estazolam is 8-chloro-6-phenyl-4 H - s -triazolo[4,3-α][1,4]benzodiazepine.
The structural formula is represented as follows: C 16 H 11 ClN 4 M. W. 294.75 Each tablet, for oral administration, contains either 1 mg or 2 mg of estazolam, USP.
In addition, each tablet contains the following inactive ingredients: docusate sodium, lactose monohydrate, magnesium stearate, microcrystalline cellulose, sodium benzoate, sodium starch glycolate and stearic acid. The 2 mg tablets also contain FD&C Red #40 Aluminum Lake. Estazolam Structural Formula
💬 Medication Guide ▾
MEDICATION GUIDE Estazolam (es taz'oh lam) Tablets, USP C-IV What is the most important information I should know about estazolam? Estazolam is a benzodiazepine medicine. Taking benzodiazepines with opioid medicines, alcohol, or other central nervous system depressants (CNS) (including street drugs) can cause severe drowsiness, breathing problems (respiratory depression), coma and death.
Get emergency help right away if any of the following happens: shallow or slowed breathing breathing stops (which may lead to the heart stopping) excessive sleepiness (sedation) Do not drive or operate heavy machinery until you know how taking estazolam with opioids affects you. Risk of abuse, misuse, and addiction. There is a risk of abuse, misuse, and addiction with benzodiazepines, including estazolam, which can lead to overdose and serious side effects including coma and death.
Serious side effects including coma and death have happened in people who have abused or misused benzodiazepines, including estazolam . These serious side effects may also include delirium, paranoia, suicidal thoughts or actions, seizures, and difficulty breathing. Call your healthcare provider or go to the nearest hospital emergency room right away if you get any of these serious side effects.
You can develop an addiction even if you take estazolam exactly as prescribed by your healthcare provider. Take estazolam exactly as your healthcare provider prescribed. Do not share your estazolam with other people.
Keep estazolam in a safe place and away from children. Physical dependence and withdrawal reactions. Estazolam can cause physical dependence and withdrawal reactions, especially if you continue to take estazolam for several days to several weeks.
Do not suddenly stop taking estazolam. Stopping estazolam suddenly can cause serious and life-threatening side effects, including unusual movements, responses, or expressions, seizures, sudden and severe mental or nervous system changes, depression, seeing or hearing things that others do not see or hear, an extreme increase in activity or talking, losing touch with reality, and suicidal thoughts or actions. Call your healthcare provider or go to the nearest hospital emergency room right away if you get any of these symptoms.
Some people who suddenly stop benzodiazepines have symptoms that can last for several weeks to more than 12 months, including, anxiety, trouble remembering, learning, or concentrating, depression, problems sleeping, feeling like insects are crawling under your skin, weakness, shaking, muscle twitching, burning or prickling feeling in your hands, arms, legs or feet, and ringing in your ears. Physical dependence is not the same as drug addiction. Your healthcare provider can tell you more about the differences between physical dependence and drug addiction.
Do not take more estazolam than prescribed or take estazolam for longer than prescribed. After taking estazolam, you may get up out of bed while not being fully awake and do an activity that you do not know you are doing. The next morning, you may not remember that you did anything during the night.
You have a higher chance for doing these activities if you drink alcohol or take other medicines that make you sleepy with estazolam. Reported activities include: driving a car (“sleep-driving”) making and eating food talking on the phone having sex sleep-walking Call your healthcare provider right away if you find out that you have done any of the above activities after taking estazolam. Do not take estazolam unless you are able to stay in bed a full night (7 to 8 hours) before you must be active again.
What is estazolam? Estazolam is a prescription medicine used short-term to treat certain types of insomnia including difficulty falling asleep, waking up often during the night, or waking up early in the morning. Estazolam is a federal controlled substance (C-IV) because it contains estazolam that can be abused or lead to dependence.
Keep estazolam in a… [Excerpted — this section continues on DailyMed.]
⚠️ Precautions ▾
PRECAUTIONS General Impaired motor and/or cognitive performance attributable to the accumulation of benzodiazepines and their active metabolites following several days of repeated use at their recommended doses is a concern in certain vulnerable patients (e.g., those especially sensitive to the effects of benzodiazepines or those with a reduced capacity to metabolize and eliminate them) (see DOSAGE AND ADMINISTRATION ). Elderly or debilitated patients and those with impaired renal or hepatic function should be cautioned about these risks and advised to monitor themselves for signs of excessive sedation or impaired conditions.
Estazolam appears to cause dose-related respiratory depression that is ordinarily not clinically relevant at recommended doses in patients with normal respiratory function. However, patients with compromised respiratory function may be at risk and should be monitored appropriately. As a class, benzodiazepines have the capacity to depress respiratory drive; there are insufficient data available, however, to characterize their relative potency in depressing respiratory drive at clinically recommended doses.
As with other benzodiazepines, estazolam should be administered with caution to patients exhibiting signs or symptoms of depression. Suicidal tendencies may be present in such patients and protective measures may be required. Intentional overdosage is more common in this group of patients; therefore, the least amount of drug that is feasible should be prescribed for the patient at any one time.
Information for Patients Advise the patient to read the FDA-approved patient labeling (Medication Guide). Risks from Concomitant Use with Opioids Advise both patients and caregivers about the risks of potentially fatal respiratory depression and sedation when estazolam is used with opioids and not to use such drugs concomitantly unless supervised by a health care provider. Advise patients not to drive or operate heavy machinery until the effects of concomitant use with the opioid have been determined (see WARNINGS : Risks from Concomitant Use with Opioids and PRECAUTIONS , Drug Interactions ).
Abuse, Misuse, and Addiction Inform patients that the use of estazolam, even at recommended dosages, exposes users to risks of abuse, misuse, and addiction, which can lead to overdose and death, especially when used in combination with other medications (e.g., opioid analgesics), alcohol, and/or illicit substances. Inform patients about the signs and symptoms of benzodiazepine abuse, misuse, and addiction; to seek medical help if they develop these signs and/or symptoms; and on the proper disposal of unused drug (see WARNINGS , Abuse, Misuse, and Addiction and DRUG ABUSE AND DEPENDENCE ).
Withdrawal Reactions Inform patients that the continued use of estazolam may lead to clinically significant physical dependence and that abrupt discontinuation or rapid dosage reduction of estazolam may precipitate acute withdrawal reactions, which can be life-threatening. Inform patients that in some cases, patients taking benzodiazepines have developed a protracted withdrawal syndrome with withdrawal symptoms lasting weeks to more than 12 months. Instruct patients that discontinuation or dosage reduction of estazolam may require a slow taper (see WARNINGS , Dependence and Withdrawal Reactions and DRUG ABUSE AND DEPENDENCE ). “Sleep-Driving” and Other Complex Behaviors There have been reports of people getting out of bed after taking a sedative-hypnotic and driving their cars while not fully awake, often with no memory of the event.
If a patient experiences such an episode, it should be reported to his or her doctor immediately, since “sleep-driving” can be dangerous. This behavior is more likely to occur when sedative-hypnotics are taken with alcohol or other central nervous system depressants (see WARNINGS ). Other complex behaviors (e.g., preparing and eating food, making phone calls, or having sex) have been reported in patients who ar… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
CLINICAL STUDIES Controlled Trials Supporting Efficacy In three 7 night, double-blind, parallel-group trials comparing estazolam 1 mg and/or 2 mg with placebo in adult outpatients with chronic insomnia, estazolam 2 mg was consistently superior to placebo in subjective measures of sleep induction (latency) and sleep maintenance (duration, number of awakenings, depth and quality of sleep); estazolam 1 mg was similarly superior to placebo on all measures of sleep maintenance, however, it significantly improved sleep induction in only one of two studies.
In a similarly designed trial comparing estazolam 0.5 mg and 1 mg with placebo in geriatric outpatients with chronic insomnia, only the 1 mg estazolam dose was consistently superior to placebo in sleep induction (latency) and in only one measure of sleep maintenance (i.e., duration of sleep). In a single-night, double-blind, parallel-group trial comparing estazolam 2 mg and placebo in patients admitted for elective surgery and requiring sleep medications, estazolam was superior to placebo in subjective measures of sleep induction and maintenance.
In a 12 week, double-blind, parallel-group trial including a comparison of estazolam 2 mg and placebo in adult outpatients with chronic insomnia, estazolam was superior to placebo in subjective measures of sleep induction (latency) and maintenance (duration, number of awakenings, total wake time during sleep) at week 2, but produced consistent improvement over 12 weeks only for sleep duration and total wake time during sleep. Following withdrawal at week 12, rebound insomnia was seen at the first withdrawal week, but there was no difference between drug and placebo by the second withdrawal week in all parameters except latency, for which normalization did not occur until the fourth withdrawal week.
Adult outpatients with chronic insomnia were evaluated in a sleep laboratory trial comparing four doses of estazolam (0.25, 0.5, 1 and 2 mg) and placebo, each administered for 2 nights in a crossover design. The higher estazolam doses were superior to placebo in most EEG measures of sleep induction and maintenance, especially at the 2 mg dose, but only for sleep duration in subjective measures of sleep.
🔒 Drug Abuse and Dependence ▾
DRUG ABUSE AND DEPENDENCE Controlled Substance Estazolam is a controlled substance in Schedule IV. Abuse Estazolam is a benzodiazepine and a CNS depressant with a potential for abuse and addiction. Abuse is the intentional, non-therapeutic use of a drug, even once, for its desirable psychological or physiological effects.
Misuse is the intentional use, for therapeutic purposes, of a drug by an individual in a way other than prescribed by a health care provider or for whom it was not prescribed. Drug addiction is a cluster of behavioral, cognitive, and physiological phenomena that may include a strong desire to take the drug, difficulties in controlling drug use (e.g., continuing drug use despite harmful consequences, giving a higher priority to drug use than other activities and obligations), and possible tolerance or physical dependence.
Even taking benzodiazepines as prescribed may put patients at risk for abuse and misuse of their medication. Abuse and misuse may lead to addiction. Abuse and misuse of benzodiazepines often (but not always) involve the use of doses greater than the maximum recommended dosage and commonly involve concomitant use of other medications, alcohol, and/or illicit substances, which is associated with an increased frequency of serious adverse outcomes, including respiratory depression, overdose, or death.
Benzodiazepines are often sought by individuals who abuse drugs and other substances, and by individuals with addictive disorders (see WARNINGS , Abuse, Misuse, and Addiction ). The following adverse reactions have occurred with benzodiazepine abuse and/or misuse: abdominal pain, amnesia, anorexia, anxiety, aggression, ataxia, blurred vision, confusion, depression, disinhibition, disorientation, dizziness, euphoria, impaired concentration and memory, indigestion, irritability, muscle pain, slurred speech, tremors, and vertigo.
The following severe adverse reactions have occurred with benzodiazepine abuse and/or misuse: delirium, paranoia, suicidal ideation and behavior, seizures, coma, breathing difficulty, and death. Death is more often associated with polysubstance use (especially benzodiazepines with other CNS depressants such as opioids and alcohol). Dependence Physical Dependence Estazolam may produce physical dependence from continued therapy.
Physical dependence is a state that develops as a result of physiological adaptation in response to repeated drug use, manifested by withdrawal signs and symptoms after abrupt discontinuation or a significant dose reduction of a drug. Abrupt discontinuation or rapid dosage reduction of benzodiazepines or administration of flumazenil, a benzodiazepine antagonist, may precipitate acute withdrawal reactions, including seizures, which can be life-threatening. Patients at an increased risk of withdrawal adverse reactions after benzodiazepine discontinuation or rapid dosage reduction include those who take higher dosages (i.e., higher and/or more frequent doses) and those who have had longer durations of use (see WARNINGS , Dependence and Withdrawal Reactions ).
To reduce the risk of withdrawal reactions, use a gradual taper to discontinue estazolam or reduce the dosage (see DOSAGE AND ADMINISTRATION , Discontinuation or Dosage Reduction of estazolam and WARNINGS, Dependence and Withdrawal Reactions ). Acute Withdrawal Signs and Symptoms Acute withdrawal signs and symptoms associated with benzodiazepines have included abnormal involuntary movements, anxiety, blurred vision, depersonalization, depression, derealization, dizziness, fatigue, gastrointestinal adverse reactions (e.g., nausea, vomiting, diarrhea, weight loss, decreased appetite), headache, hyperacusis, hypertension, irritability, insomnia, memory impairment, muscle pain and stiffness, panic attacks, photophobia, restlessness, tachycardia, and tremor.
More severe acute withdrawal signs and symptoms, including life-threatening reactions, have included catatonia, convulsions, delirium tremens, depressi… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL NDC 0591- 0744 -01 CIV Estazolam Tablets, USP 1mg PHARMACIST: Dispense the accompanying Medication Guide to each patient. Rx only 100 Tablets 1
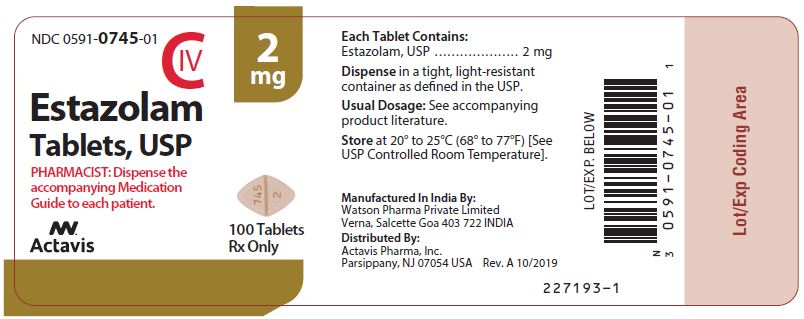
PRINCIPAL DISPLAY PANEL NDC 0591- 0745 -01 CIV Estazolam Tablets, USP 2 mg PHARMACIST: Dispense the accompanying Medication Guide to each patient. Rx only 100 Tablets 1
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |