
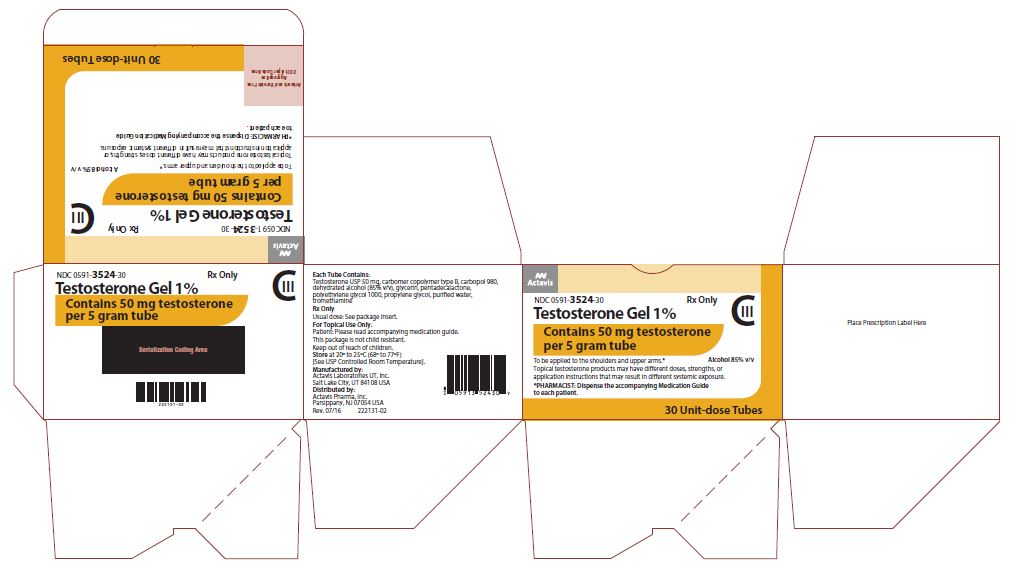
Testosterone 50 mg/5g Gel — NDC 0591-3524-30 (Billing 00591-3524-30)
This is a package of Testosterone 50 mg/5g Gel from Actavis Pharma, Inc., marketed since Oct 2017 and currently FDA-listed; retail pharmacies pay about $0.7365 per g (NADAC). It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0591-3524-30 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0591 labeler · 3524 product · 30 package
- Package marketed since
- Oct 12, 2017
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 0591352430 9
- Medicaid fills, this package
- 2,299 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Other active recalls for Testosterone (different manufacturers) — 4 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 061294
- GCN: 97089
- GPI-14 (Medi-Span): 23100030004030
- HICL (First Databank): 001403
- AHFS class code: 68:08.00.00
- RxCUI (RxNorm): 1597129
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Androgen class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It's for adult men whose bodies make too little testosterone, called hypogonadism. Your doctor should confirm this with morning blood tests on at least two different days before st...
- Testosterone gel can pass to others through skin contact. Children and women should avoid touching unwashed or unclothed application sites, and you should follow the instructions f...
- How do I keep my family safe if I use a gel?
- Common ones include a higher PSA, mood changes, acne, higher blood pressure and skin irritation. Your doctor will check blood tests such as PSA and blood counts and monitor your bl...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Testosterone — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.737 | $110.48 / 150 g |
| Medicaid paysCMS SDUD · 12 mo | $0.7608 | $114.12 / 150 g |
| Medicare drug plans payPart D · Q2 2026 | $2.07 | $311.03 / 150 g |
Where does this data come from?
- CMS NADAC weekly file · file of Oct 7, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00591-3524-30 You're viewing this Main listing | 30 TUBE in 1 CARTON / 5 g in 1 TUBE | 2017-10-12 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Testosterone 10 mg/g 00591-3217-30 | Actavis | 30 packets | $0.406 | AB1 | Availability likely | save 45% |
| Testosterone Gel, 1% 10 mg/g 21922-0019-02 | Encube | 30 packets | $0.406 | AB1 | Availability likely | save 45% |
| Testosterone 50 mg/5g 64380-0152-02 | Strides | 30 doses | $0.406 | AB1 | Availability likely | save 45% |
| Testosterone 50 mg/5g 66993-0955-30 | Prasco | 30 packets | $0.406 | AB1 | Availability likely | save 45% |
| Testosterone 50 mg/5gthis 00591-3524-30 | Actavis | 30 tubes | $0.737 | AB2 | Availability likely | — |
| Testosterone 50 mg/5g 00832-1120-05 | Upsher-Smith | 30 tubes | $0.737 | AB2 | Availability likely | — |
| Vogelxo 50 mg/5g 00245-0871-05 | Upsher-Smith | 30 tubes | $3.778 | AB2 | FDA listed | +413% |
| Testim 50 mg/5g 66887-0001-05 | Endo | 30 tubes | $3.785 | AB2 | Availability likely | +414% |
| AndroGel 10 mg/g 17139-0550-30 | ASCEND | 30 packets | — | AB1 | Discontinued | — |
| Testosterone Gel, 1% 10 mg/g 72162-1274-03 | Bryant | 30 packets | — | AB1 | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Oct 7, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Testosterone inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII 809Y72KV36
A synthetic polymer made from acrylic acid and crosslinked with allyl pentaerythritol. It's used as a thickening agent and gelling ingredient in creams, gels, and lotions to create the proper texture and help the medicine spread and stay on the skin.
-
UNII 4Q93RCW27E
A synthetic polymer made from acrylic acid that's crosslinked for stability. It acts as a thickener and gelling agent in creams and gels, helping the medicine spread evenly and maintain its texture.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII OK17S3S98K
A waxy, fatty substance derived from plant or animal sources. It acts as a lubricant and glidant to help the medicine flow smoothly during manufacturing and tablet compression.
-
UNII U076Q6Q621
Polyethylene glycol 1000 is a synthetic compound made from ethylene oxide. It serves as a solvent, lubricant, and humectant in medicines, helping dissolve active ingredients and improve how the product flows and feels.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 023C2WHX2V
Tromethamine is a chemical buffer that helps maintain the proper acidity level in liquid medicines. It neutralizes acids and stabilizes the solution so the medication remains effective and safe throughout its shelf life.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Actavis Pharma, Inc. labeler code 00591
- Orphenadrine Citrate 30 mg/mL Injection NDC 0591-3222-47
- Bupropion Hydrochloride XL 150 mg Tablet, Film Coated, Extended Release NDC 0591-3331-05
- Butalbital, Acetaminophen, and Caffeine 50 mg; 325 mg; 40 mg Tablet NDC 0591-3369-01
- Clonidine transdermal system .1 mg/d Patch NDC 0591-3508-04
- Clonidine transdermal system .2 mg/d Patch NDC 0591-3509-04
- Clonidine transdermal system .3 mg/d Patch NDC 0591-3510-04
- Lidocaine 50 mg/g Patch NDC 0591-3525-30
- Bupropion Hydrochloride SR 100 mg Tablet, Film Coated, Extended Release NDC 0591-3540-05
- Bupropion Hydrochloride SR 150 mg Tablet, Film Coated, Extended Release NDC 0591-3541-05
- Bupropion Hydrochloride SR 200 mg Tablet, Film Coated, Extended Release NDC 0591-3542-60
- Bupropion Hydrochloride SR 150 mg Tablet, Film Coated, Extended Release NDC 0591-3543-60
- Trospium Chloride 60 mg Capsule, Extended Release NDC 0591-3636-05
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SECONDARY EXPOSURE TO TESTOSTERONE Virilization has been reported in children who were secondarily exposed to testosterone gel [see Warnings and Precautions ( 5.1 ) and Adverse Reactions ( 6.2 )] . Children should avoid contact with unwashed or unclothed application sites in men using testosterone gel [see Dosage and Administration ( 2.2 ) and Warnings and Precautions ( 5.1 )] . Healthcare providers should advise patients to strictly adhere to recommended instructions for use [see Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.1 ), and Patient Counseling Information ( 17 )] .
WARNING: SECONDARY EXPOSURE TO TESTOSTERONE See full prescribing information for complete boxed warning. Virilization has been reported in children who were secondarily exposed to testosterone gel ( 5.1 , 6.2 ) Children should avoid contact with unwashed or unclothed application sites in men using testosterone gel ( 2.2 , 5.1 ) Healthcare providers should advise patients to strictly adhere to recommended instructions for use ( 2.2 , 5.1 , 17 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Testosterone gel 1% is indicated for testosterone replacement therapy in adult males for conditions associated with a deficiency or absence of endogenous testosterone: Primary hypogonadism (congenital or acquired): testicular failure due to cryptorchidism, bilateral torsion, orchitis, vanishing testis syndrome, orchiectomy, Klinefelter's syndrome, chemotherapy, or toxic damage from alcohol or heavy metals. These men usually have low serum testosterone concentrations and gonadotropins (follicle-stimulating hormone [FSH], luteinizing hormone [LH]) above the normal range.
Hypogonadotropic hypogonadism (congenital or acquired): gonadotropin or luteinizing hormone-releasing hormone (LHRH) deficiency or pituitary-hypothalamic injury from tumors, trauma, or radiation. These men have low testosterone serum concentrations but have gonadotropins in the normal or low range. Limitations of Use: Safety and efficacy of testosterone gel 1% in men with “age-related hypogonadism” (also referred to as “late-onset hypogonadism”) have not been established.
Safety and efficacy of testosterone gel 1% in males less than 18 years old have not been established [see Use in Specific Populations ( 8.4 )] . Topical testosterone products may have different doses, strengths, or application instructions that may result in different systemic exposure [see Dosage and Administration ( 2 ) and Clinical Pharmacology ( 12.3 )] . Testosterone gel 1% is an androgen indicated for testosterone replacement therapy in males for conditions associated with a deficiency or absence of endogenous testosterone: Primary Hypogonadism (Congenital or Acquired) ( 1 ) Hypogonadotropic Hypogonadism ( 1 ) Limitations of Use : Safety and efficacy of testosterone gel 1% in men with “age-related hypogonadism” have not been established.
( 1 ) Safety and efficacy of testosterone gel 1% in males less than 18 years old have not been established. ( 8.4 ) Topical testosterone products may have different doses, strengths, or application instructions that may result in different systemic exposure. ( 1 , 12.3 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Prior to initiating testosterone gel 1%, confirm the diagnosis of hypogonadism by ensuring that serum testosterone concentrations have been measured in the morning on at least two separate days and that these serum testosterone concentrations are below the normal range. Prior to initiating testosterone gel 1%, confirm the diagnosis of hypogonadism by ensuring that serum testosterone has been measured in the morning on at least two separate days and that these concentrations are below the normal range.
( 2 ) Recommended starting dose for adult males: 50 mg of testosterone (one tube) applied topically once daily. ( 2.1 ) Apply to clean, dry, intact skin of the shoulders and/or upper arms. Do NOT apply testosterone gel 1% to the genitals or abdomen.
( 2.1 , 2.2 ) If morning pre-dose serum testosterone concentration is below normal range, increase dose to 100 mg. ( 2.1 ) Pre-dose serum testosterone concentration should be assessed periodically. ( 2.1 ) Patients should wash hands with soap and water immediately after applying testosterone gel 1% and cover application site(s) with clothing after gel has dried.
Wash the application site thoroughly with soap and water prior to any situation where skin-to-skin contact of the application site with another person is anticipated. ( 2.2 ) Testosterone gel 1% is not substitutable with other topical testosterone products. ( 2.1 )
2.1Dosing and Dose Adjustment The recommended starting dose of testosterone gel 1% is 50 mg of testosterone (one tube) applied once daily (preferably in the morning) to clean, dry intact skin of the shoulders and/or upper arms. Dose Adjustment To ensure proper dosing, serum testosterone concentrations should be measured. Morning, pre-dose serum testosterone concentrations should be measured approximately 14 days after initiation of therapy to ensure proper serum testosterone concentrations are achieved.
If the serum testosterone concentration is below the normal range (300 ng/dL to 1,000 ng/dL), the daily testosterone gel 1% dose may be increased from 50 mg testosterone (one tube) to 100 mg testosterone (two tubes) once daily. The maximum recommended dose of testosterone gel 1% is 100 mg once daily. The application site and dose of testosterone gel 1% are not substitutable with other topical testosterone products.
2.2Administration Instructions Upon opening the tube the entire contents should be squeezed into the palm of the hand and immediately applied to the shoulders and/or upper arms (area of application should be limited to the area that will be covered by the patient’s short sleeve T-shirt ( see figure below ). Do not apply testosterone gel 1% to the genitals or to the abdomen. Application sites should be allowed to dry for a few minutes prior to dressing.
Hands should be washed thoroughly with soap and water after testosterone gel 1% has been applied. Avoid fire, flame or smoking during the application of testosterone gel 1% until the testosterone gel 1% has dried [see Warnings and Precautions ( 5.1 , 5.16) ] . In order to prevent transfer to another person, wear clothing to cover the application sites.
If direct skin-to-skin contact with another person is anticipated, the application sites must be washed thoroughly with soap and water [see Warnings and Precautions ( 5.1 ) and Clinical Pharmacology ( 12.3 )] . The patient should avoid swimming or showering or washing the administration site for a minimum of 2 hours after application [see Clinical Pharmacology ( 12.3) ] . Strict adherence to the following precautions is advised in order to minimize the potential for secondary exposure to testosterone from testosterone-treated skin: Children and women should avoid contact with unwashed or unclothed application site(s) of men using testosterone gel 1%.
Testosterone gel 1% should only be applied to the upper arms and shoulders. The area of application should be limited to the area that will be covered by a short sleeve T-shirt. Patie… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Testosterone gel 1% is a clear to translucent hydroalcoholic gel, for topical use and is available in a unit-dose tube. Each tube contains 50 mg testosterone in 5 g of gel. Topical gel: 50 mg of testosterone in a unit-dose tube ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Testosterone gel 1% is contraindicated in men with carcinoma of the breast or known or suspected carcinoma of the prostate [see Warnings and Precautions ( 5.4 )] . Testosterone gel 1% is contraindicated in women who are pregnant. Testosterone can cause virilization of the female fetus when administered to a pregnant woman [see Use in Specific Populations ( 8.1, 8.2 )] .
Men with known carcinoma of the breast or known or suspected carcinoma of the prostate. ( 4 , 5.4 ) Women who are pregnant. Testosterone may cause fetal harm.
( 4 , 5.7 , 8.1 , 8.2 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Potential for Secondary Exposure to Testosterone: Avoid unintentional exposure of women or children to testosterone gel 1%. Secondary exposure to testosterone can produce signs of virilization. Testosterone gel 1% should be discontinued until the cause of virilization is identified.
( 5.1 ) Venous thromboembolism (VTE): VTE, including deep vein thrombosis (DVT) and pulmonary embolism (PE), have been reported in patients using testosterone products. Evaluate patients with signs or symptoms consistent with DVT or PE. ( 5.3 ) Worsening of Benign Prostatic Hyperplasia (BPH) and Potential Risk of Prostate Cancer: Monitor patients with benign prostatic hyperplasia (BPH) for worsening of signs and symptoms of BPH.
( 5.4 ) Blood Pressure Increases: Testosterone can increase blood pressure, which can increase cardiovascular risk over time. Measure blood pressure periodically. Not recommended for use in men with uncontrolled hypertension ( 5.5 ) Abuse of Testosterone: Testosterone has been subject to abuse, typically at doses higher than recommended for the approved indication and in combination with other anabolic androgenic steroids ( 5.6 ).
Potential for Adverse Effects on Spermatogenesis Exogenous administration of androgens may lead to azoospermia. ( 5.8 ) Edema: Edema, with or without congestive heart failure, may be a complication in patients with preexisting cardiac, renal, or hepatic disease. ( 5.10 , 6.2 ) Sleep apnea: Sleep apnea may occur in those with risk factors.
( 5.12 ) Monitor prostate specific antigen (PSA), hematocrit, and lipid concentrations periodically. ( 5.2 , 5.4 , 5.13 ) Testosterone gel 1% is flammable until dry. ( 5.16 )
5.1Potential for Secondary Exposure to Testosterone Cases of secondary exposure resulting in virilization of children have been reported in postmarketing surveillance. Signs and symptoms have included enlargement of the penis or clitoris, development of pubic hair, increased erections and libido, aggressive behavior, and advanced bone age. In most cases, these signs and symptoms regressed with removal of the exposure to testosterone gel.
In a few cases, however, enlarged genitalia did not fully return to age-appropriate normal size, and bone age remained modestly greater than chronological age. The risk of transfer was increased in some of these cases by not adhering to precautions for the appropriate use of the topical testosterone product. Children and women should avoid contact with unwashed or unclothed application sites in men using testosterone gel 1% [see Dosage and Administration ( 2.2 ), Use in Specific Populations ( 8.1 ), and Clinical Pharmacology ( 12.3 )] .
Inappropriate changes in genital size or development of pubic hair or libido in children, or changes in body hair distribution, significant increase in acne, or other signs of virilization in adult women should be brought to the attention of a physician and the possibility of secondary exposure to testosterone gel should also be brought to the attention of a physician. Testosterone gel should be promptly discontinued until the cause of virilization has been identified.
5.2Polycythemia Increases in hematocrit, reflective of increases in red blood cell mass, may require lowering or discontinuation of testosterone. Check hematocrit prior to initiating treatment. It would also be appropriate to re-evaluate the hematocrit 3 to 6 months after starting treatment, and then annually.
If hematocrit becomes elevated, stop therapy until hematocrit decreases to an acceptable concentration. An increase in red blood cell mass may increase the risk of thromboembolic events.
5.3Venous Thromboembolism (VTE) There have been postmarketing reports of venous thromboembolic events, including deep vein thrombosis (DVT) and pulmonary embolism (PE), in patients using testosterone products, such as testosterone gel 1%. In the Testosterone Replacement therapy for Assessment of long-term Vascular Events and efficacy ResponSE… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (incidence ≥ 2% of the testosterone gel 1% patients and greater than placebo) are application site reaction and increased hematocrit. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Teva at 1-888-838-2872 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Studies Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In a controlled clinical study, 304 patients were treated with testosterone gel 1% 50 mg or 100 mg or placebo gel for up to 90 days. Two hundred five (205) patients received testosterone gel 1% 50 mg or 100 mg daily and 99 patients received placebo.
Subjects could be counted in both testosterone gel 1% treatment groups if they received both 50 mg and 100 mg at different points in the study and experienced an adverse reaction at both dose levels. Adverse reactions reported by ≥ 1% of the testosterone gel 1% patients and greater than placebo are listed in Table 1. Table 1: Incidence of Adverse Reactions (Reported by ≥1% of the Testosterone Gel 1% Patients and Greater than Placebo) in the Controlled Clinical Trial Through 90 Days Event Testosterone Gel 1% Testosterone Gel 1% Placebo 50 mg 100 mg (n=103) (n=149) (n=99) Application Site Reactions 2% 4% 3% Blood Pressure Increased 1% 1% 0% Gynecomastia 1% 0% 0% Headache 1% 1% 0% Hematocrit / hemoglobin Increased 1% 2% 0% Hot Flushes 1% 0% 0% Insomnia 1% 0% 0% Mood Swings 1% 0% 0% Smell Disorder 1% 0% 0% Spontaneous Penile Erection 1% 0% 0% Taste Disorder 1% 1% 0% The following adverse reactions occurred in fewer than 1% of patients but were greater in testosterone gel 1% groups compared to the placebo group: activated partial thromboplastin time prolonged, blood creatinine increased, prothrombin time prolonged, appetite increased, sensitive nipples, and acne.
In this clinical trial of testosterone gel 1%, 6 patients had adverse reactions that led to their discontinuation. These events included: depression with suicidal ideation, urinary tract infection, mood swings and hypertension. No testosterone gel 1% patients discontinued due to skin reaction.
In one foreign Phase 3 trial, one subject discontinued due to a skin-related adverse reaction. In the pivotal US and European Phase 3 trials combined, at the 50-mg dosage strength, the percentage of subjects reporting clinically notable increases in hematocrit or hemoglobin were similar to placebo. However, in the 100-mg dose group, 2.3% and 2.8% of patients had a clinically notable increase in hemoglobin (≥ 19 g/dL) or hematocrit (≥ 58%), respectively, compared to 1.0% and 1.5% of patients in the placebo group, respectively.
In the combined US and European open-label extension studies, approximately 140 patients received testosterone gel 1% for at least 6 months. The results from these studies are consistent with those reported for the US controlled clinical trial. Blood Pressure Increases In a 4-month clinical study, 24-hour ambulatory blood pressure monitoring (ABPM) was conducted on 225 patients.
ABPM was conducted at baseline and at Week 16 of testosterone gel 1% therapy. A total of 113 patients had acceptable ABPM recordings at both baseline and Week 16 and were at least 85% compliant with study drug. In that group, the mean change in 24-hour systolic blood pressure (BP) and diastolic BP from baseline to end-of-treatment at Week 16 (n=113) was 2.7 mm Hg (95% CI 0.7, 4.8) and 1.1 mm Hg (95% CI -0.1, 2.3), respectively.
In patients with a history of hypertension who were receiving antihypertensive therapy, the mean ABPM systolic and diastolic BP increased by 1.9 mm Hg [95% CI -1.4, 5.2] and 0.3 mm Hg [95% CI -1.6, 2.2], respectively [n=55]). In patients with no history of hypertension, the mean systolic and diastolic blood pressure incre… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Androgens may decrease blood glucose and therefore may decrease insulin requirements in diabetic patients. ( 7.1 ) Changes in anticoagulant activity may be seen with androgens. More frequent monitoring of international normalized ratio (INR) and prothrombin time is recommended in patients taking warfarin.
( 7.2 ) Use of testosterone with corticosteroids may result in increased fluid retention. Use with caution, particularly in patients with cardiac, renal, or hepatic disease. ( 7.3 )
7.1Insulin Changes in insulin sensitivity or glycemic control may occur in patients treated with androgens. In diabetic patients, the metabolic effects of androgens may decrease blood glucose and, therefore, may necessitate a decrease in the dose of anti-diabetic medication.
7.2Oral Anticoagulants Changes in anticoagulant activity may be seen with androgens, therefore more frequent monitoring of international normalized ratio (INR) and prothrombin time are recommended in patients taking warfarin, especially at the initiation and termination of androgen therapy.
7.3Corticosteroids The concurrent use of testosterone with corticosteroids may result in increased fluid retention and requires careful monitoring particularly in patients with cardiac, renal or hepatic disease.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Geriatric Patients: There are insufficient long-term safety data to assess the potential risks of cardiovascular disease and prostate cancer. ( 8.5 )
8.1Pregnancy Risk Summary Testosterone gel 1% is contraindicated in pregnant women. Testosterone is teratogenic and may cause fetal harm based on data from animal studies and its mechanism of action [see Contraindications ( 4 ) and Clinical Pharmacology ( 12.1 )] . Exposure of a female fetus to androgens may result in varying degrees of virilization.
In animal development studies, exposure to testosterone in utero resulted in hormonal and behavioral changes in offspring and structural impairments of reproductive tissues in female and male offspring. These studies did not meet current standards for nonclinical development toxicity studies. Data Animal Data In developmental studies conducted in rats, rabbits, pigs, sheep, and rhesus monkeys, pregnant animals received intramuscular injection of testosterone during the period of organogenesis.
Testosterone treatment at doses that were comparable to those used for testosterone replacement therapy resulted in structural impairments in both female and male offspring. Structural impairments observed in females included increased anogenital distance, phallus development, empty scrotum, no external vagina, intrauterine growth retardation, reduced ovarian reserve, and increased ovarian follicular recruitment. Structural impairments seen in male offspring included increased testicular weight, larger seminal tubular lumen diameter, and higher frequency of occluded tubule lumen.
Increased pituitary weight was seen in both sexes. Testosterone exposure in utero also resulted in hormonal and behavioral changes in offspring. Hypertension was observed in pregnant female rats and their offspring exposed to doses approximately twice those used for testosterone replacement therapy.
8.2Lactation Risk Summary Testosterone is not indicated for use in females.
8.3Females and Males of Reproductive Potential Infertility During treatment with large doses of exogenous androgens, including testosterone, spermatogenesis may be suppressed through feedback inhibition of the hypothalamic-pituitary-testicular axis [see Warnings and Precautions ( 5.8 )] , possible leading to adverse effects on semen parameters including sperm count. Reduced fertility is observed in some men taking testosterone replacement therapy. Testicular atrophy, subfertility, and infertility have also been reported in men who abuse anabolic androgenic steroids [see Drug Abuse and Dependence ( 9.2 )] .
With either type of use, the impact on fertility may be irreversible.
8.4Pediatric Use The safety and effectiveness of testosterone gel 1% in pediatric patients less than 18 years old have not been established. Improper use may result in acceleration of bone age and premature closure of epiphyses.
8.5Geriatric Use There is insufficient long-term safety data in geriatric patients to assess the potentially increased risks of cardiovascular disease and prostate cancer [see Warnings and Precautions ( 5.4 )] .
8.6Renal Impairment No studies were conducted in patients with renal impairment.
8.7Hepatic Impairment No studies were conducted in patients with hepatic impairment.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Testosterone gel 1% is contraindicated in pregnant women. Testosterone is teratogenic and may cause fetal harm based on data from animal studies and its mechanism of action [see Contraindications ( 4 ) and Clinical Pharmacology ( 12.1 )] . Exposure of a female fetus to androgens may result in varying degrees of virilization.
In animal development studies, exposure to testosterone in utero resulted in hormonal and behavioral changes in offspring and structural impairments of reproductive tissues in female and male offspring. These studies did not meet current standards for nonclinical development toxicity studies. Data Animal Data In developmental studies conducted in rats, rabbits, pigs, sheep, and rhesus monkeys, pregnant animals received intramuscular injection of testosterone during the period of organogenesis.
Testosterone treatment at doses that were comparable to those used for testosterone replacement therapy resulted in structural impairments in both female and male offspring. Structural impairments observed in females included increased anogenital distance, phallus development, empty scrotum, no external vagina, intrauterine growth retardation, reduced ovarian reserve, and increased ovarian follicular recruitment. Structural impairments seen in male offspring included increased testicular weight, larger seminal tubular lumen diameter, and higher frequency of occluded tubule lumen.
Increased pituitary weight was seen in both sexes. Testosterone exposure in utero also resulted in hormonal and behavioral changes in offspring. Hypertension was observed in pregnant female rats and their offspring exposed to doses approximately twice those used for testosterone replacement therapy.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of testosterone gel 1% in pediatric patients less than 18 years old have not been established. Improper use may result in acceleration of bone age and premature closure of epiphyses.
🧓 Geriatric Use ▾
8.5Geriatric Use There is insufficient long-term safety data in geriatric patients to assess the potentially increased risks of cardiovascular disease and prostate cancer [see Warnings and Precautions ( 5.4 )] .
🆘 Overdosage ▾
10 OVERDOSAGE There were no reports of overdose in the testosterone gel 1% clinical trials. There is a single report in the literature of acute overdosage after injection of testosterone enanthate. This subject had serum testosterone concentrations of up to 11,400 ng/dL, which were implicated in a cerebrovascular accident.
Treatment of overdosage would consist of discontinuation of testosterone gel 1%, washing the application site with soap and water, and appropriate symptomatic and supportive care.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Endogenous androgens, including testosterone and dihydrotestosterone (DHT), are responsible for the normal growth and development of the male sex organs and for maintenance of secondary sex characteristics. These effects include the growth and maturation of prostate, seminal vesicles, penis and scrotum; the development of male hair distribution, such as facial, pubic, chest and axillary hair; laryngeal enlargement; vocal cord thickening; and alterations in body musculature and fat distribution.
Testosterone and DHT are necessary for the normal development of secondary sex characteristics. Male hypogonadism, a clinical syndrome resulting from insufficient secretion of testosterone, has 2 main etiologies. Primary hypogonadism is caused by defects of the gonads, such as Klinefelter's syndrome or Leydig cell aplasia, while secondary hypogonadism (hypogonadotropic hypogonadism) is the failure of the hypothalamus (or pituitary) to produce sufficient gonadotropins (FSH, LH).
12.2Pharmacodynamics No specific pharmacodynamic studies were conducted using testosterone gel 1%.
12.3Pharmacokinetics Absorption Testosterone gel 1% delivers physiologic amounts of testosterone, producing circulating testosterone concentrations that approximate normal concentrations (e.g., 300 to 1,000 ng/dL) seen in healthy men. The skin serves as a reservoir for the sustained release of testosterone into the systemic circulation. Approximately 10% of the testosterone applied on the skin surface is absorbed into the systemic circulation during a 24-hour period.
Single Dose In single-dose studies, when either testosterone gel 1% 50 mg or 100 mg was administered, absorption of testosterone into the blood continued for the entire 24-hour dosing period. Also, mean peak and average serum concentrations within the normal range were achieved within 24 hours. Multiple Dose With single daily applications of testosterone gel 1% 50 mg and 100 mg, follow-up measurements at 30 and 90 days after starting treatment have confirmed that serum testosterone and DHT concentrations are generally maintained within the normal range.
Figure 1 summarizes the 24-hour pharmacokinetic profile of testosterone for patients maintained on testosterone gel 1% 50 mg or testosterone gel 1% 100 mg for 30 days. Figure 1: Mean Steady-State Serum Testosterone (± SD) (ng/dL) Concentrations on Day 30 in Patients Applying Testosterone gel 1% Once Daily The average daily testosterone concentration produced by testosterone gel 1% 100 mg at Day 30 was 612 (± 286) ng/dL and by testosterone gel 1% 50 mg at Day 30 was 365 (± 187) ng/dL. Distribution Circulating testosterone is primarily bound in the serum to sex hormone-binding globulin (SHBG) and albumin.
Approximately 40% of testosterone in plasma is bound to SHBG, 2% remains unbound (free) and the rest is loosely bound to albumin and other proteins. Metabolism Testosterone is metabolized to various 17-keto steroids through 2 different pathways. The major active metabolites of testosterone are estradiol and DHT.
The average daily DHT concentration produced by testosterone gel 1% 100 mg at Day 30 was 555 (± 293) pg/mL and by testosterone gel 1% 50 mg at Day 30 was 346 (± 212) pg/mL. Figure 2 summarizes the 24-hour pharmacokinetic profile of DHT for patients maintained on testosterone gel 1% 50 mg or testosterone gel 1% 100 mg for 30 days. Figure 2: Mean Steady-State Serum Dihydrotestosterone (± SD) (pg/mL) Concentrations on Day 30 in Patients Applying Testosterone Gel 1% Once Daily Excretion There is considerable variation in the half-life of testosterone concentration as reported in the literature, ranging from 10 to 100 minutes.
About 90% of a dose of testosterone given intramuscularly is excreted in the urine as glucuronic acid and sulfuric acid conjugates of testosterone and its metabolites. About 6% of a dose is excreted in the feces, mostly in the unconjugated form. Inactivation of testosterone occu… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Endogenous androgens, including testosterone and dihydrotestosterone (DHT), are responsible for the normal growth and development of the male sex organs and for maintenance of secondary sex characteristics. These effects include the growth and maturation of prostate, seminal vesicles, penis and scrotum; the development of male hair distribution, such as facial, pubic, chest and axillary hair; laryngeal enlargement; vocal cord thickening; and alterations in body musculature and fat distribution.
Testosterone and DHT are necessary for the normal development of secondary sex characteristics. Male hypogonadism, a clinical syndrome resulting from insufficient secretion of testosterone, has 2 main etiologies. Primary hypogonadism is caused by defects of the gonads, such as Klinefelter's syndrome or Leydig cell aplasia, while secondary hypogonadism (hypogonadotropic hypogonadism) is the failure of the hypothalamus (or pituitary) to produce sufficient gonadotropins (FSH, LH).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Testosterone gel 1% is supplied in unit-dose tubes in cartons of 30. Each tube contains 50 mg testosterone in 5 g of gel, and is supplied as follows: NDC Number Package Size 0591-3524-30 30 tubes: 50 mg testosterone in 5 g of gel per tube Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature]. Discard used testosterone gel 1% tubes in household trash in a manner that prevents accidental exposure of women, children, or pets [see Boxed Warning and Warnings and Precautions ( 5.1 )] .
Contents are flammable [see Warnings and Precautions ( 5.16 )] .
📋 Description ▾
11 DESCRIPTION Testosterone gel 1% is a clear to translucent hydroalcoholic topical gel containing testosterone USP, an androgen. Testosterone gel 1% provides continuous transdermal delivery of testosterone for 24 hours, following a single application to intact, clean, dry skin of the shoulders and/or upper arms. One 5-g tube of Testosterone gel 1% contains 50 mg of testosterone, USP to be applied daily to the skin’s surface.
Approximately 10% of the applied testosterone dose is absorbed across skin of average permeability during a 24-hour period. The active pharmacological ingredient in testosterone gel 1% is testosterone, USP. Testosterone, USP is a white to practically white crystalline powder chemically described as 17-β hydroxyandrost-4-en-3-one.
The structural formula is shown in the following figure: Testosterone gel 1% may have an alcoholic/musk odor. Inactive ingredients in testosterone gel 1% are carbomer copolymer type B, carbopol 980, dehydrated alcohol (85% v/v), glycerin, pentadecalactone, polyethylene glycol 1000, propylene glycol, purified water, and tromethamine. 1
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Medication Guide ). Advise patients of the following :
17.1Men with Known or Suspected Carcinoma of the Breast or Prostate Men with known or suspected prostate or breast cancer should not use testosterone gel 1% [see Contraindications ( 4 ) and Warnings and Precautions ( 5.4 )] .
17.2Potential for Secondary Exposure to Testosterone and Steps to Prevent Secondary Exposure Secondary exposure to testosterone in children and women can occur with the use of testosterone gel in men. Cases of secondary exposure to testosterone have been reported in children. Physicians should advise patients of the reported signs and symptoms of secondary exposure which may include the following: In children; unexpected sexual development including inappropriate enlargement of the penis or clitoris, premature development of pubic hair, increased erections, and aggressive behavior In women; changes in hair distribution, increase in acne, or other signs of testosterone effects The possibility of secondary exposure to testosterone gel should be brought to the attention of a healthcare provider Testosterone gel 1% should be promptly discontinued until the cause of virilization is identified Strict adherence to the following precautions is advised to minimize the potential for secondary exposure to testosterone from testosterone gel in men [see Medication Guide ] : Children and women should avoid contact with unwashed or unclothed application site(s) of men using testosterone gel Patients using testosterone gel 1% should apply the product as directed and strictly adhere to the following: - Wash hands with soap and water immediately after application. - Cover the application site(s) with clothing after the gel has dried. - Wash the application site(s) thoroughly with soap and water prior to any situation where skin-to-skin contact of the application site with another person is anticipated. - In the event that unwashed or unclothed skin to which testosterone gel 1% has been applied comes in contact with the skin of another person, the general area of contact on the other person should be washed with soap and water as soon as possible [see Dosage and Administration ( 2.2 ), Warnings and Precautions ( 5.1 ), and Clinical Pharmacology ( 12.3 )] .
17.3Potential Adverse Reactions with Androgens Patients should be informed that treatment with androgens may lead to adverse reactions which include: Changes in urinary habits, such as increased urination at night, trouble starting the urine stream, passing urine many times during the day, having an urge to go the bathroom right away, having a urine accident, or being unable to pass urine or weak urine flow Breathing disturbances, including those associated with sleep or excessive daytime sleepiness Too frequent or persistent erections of the penis Nausea, vomiting, changes in skin color, or ankle swelling Venous thromboembolism, the signs and symptoms of which may include lower limb pain, edema, or erythema; dyspnea; or chest pain.
Increased blood pressure that can increase cardiovascular risk over time.
17.4Patients Should Be Advised of the Following Instructions for Use Read the Medication Guide before starting testosterone gel 1% therapy and reread it each time the prescription is renewed. Testosterone gel 1% should be applied and used appropriately to maximize the benefits and to minimize the risk of secondary exposure in children and women. Keep testosterone gel 1% out of the reach of children.
The package is not child resistant. Testosterone gel 1% is an alcohol-based product and is flammable; therefore avoid fire, flame or smoking until the gel has dried. It is important to adhere to all recommended monitoring.
Report any changes in their state of health, such as changes in urinary habits, breathing, sleep, and mood. Testosterone gel 1% is prescribed to meet the patient’s specific needs; therefore, the patient… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
MEDICATION GUIDE Testosterone (tes tos ' ter one) Gel 1% , CIII for topical use What is the most important information I should know about testosterone gel 1%? Testosterone gel 1% can transfer from your body to others including, children and women. Children and women should avoid contact with the unwashed or not covered (unclothed) areas where testosterone gel 1% has been applied to your skin.
Early signs and symptoms of puberty have occurred in young children who have come in direct contact with testosterone by touching areas where men have used testosterone gel 1%. Children Signs and symptoms of early puberty in a child when they come in direct contact with testosterone gel 1% may include: Abnormal sexual changes: enlarged penis or clitoris. early growth of hair near the vagina or around the penis (pubic hair). erections or acting out sexual urges (sex drive). Behavior problems: acting aggressively, behaving in an angry or violent way.
Women Signs and symptoms in women when they come in direct contact with testosterone gel 1% may include: changes in body hair. an abnormal increase in pimples (acne). Stop using testosterone gel 1% and call your healthcare provider right away if you see any signs and symptoms in a child or a woman that may have happened through accidental touching of the area where you have placed testosterone gel 1%. To lower the risk of transfer of testosterone gel 1% from your body to others, follow these important instructions: Apply testosterone gel 1% only to the areas of your shoulders and upper arms that will be covered by a short sleeve t-shirt.
Wash your hands right away with soap and water after applying testosterone gel 1%. After the gel has dried, cover the application area with clothing. Keep the area covered until you have washed the application area well or have showered.
If you expect to have skin-to-skin contact with another person, first wash the application area well with soap and water. If a child or woman touches the area where you have applied testosterone gel 1%, that area on the child or woman should be washed well with soap and water right away. What is testosterone gel 1%?
Testosterone gel 1% is a prescription medicine that contains testosterone. Testosterone gel 1% is used to treat adult males who have low or no testosterone due to certain medical conditions. Your healthcare provider will test your blood before you start and while you are using testosterone gel 1%.
It is not known if testosterone gel 1% is safe or effective to treat men who have low testosterone due to aging. It is not known if testosterone gel 1% is safe or effective in children younger than 18 years old. Improper use of testosterone in children may affect bone growth.
Testosterone gel 1% is a controlled substance (CIII) because it contains testosterone that can be a target for people who abuse prescription medicines. Keep your testosterone gel 1% in a safe place to protect it. Never give your testosterone gel 1% to anyone else, even if they have the same symptoms you have.
Selling or giving away this medicine may harm others and it is against the law. Testosterone gel 1% is not meant for use in women. Do not use testosterone gel 1% if you: have breast cancer. have or might have prostate cancer. are pregnant.
Testosterone gel 1% may harm your unborn baby. Women who are pregnant should avoid contact with the area of skin where testosterone gel 1% has been applied. Before using testosterone gel 1%, tell your healthcare provider about all of your medical conditions including if you: have breast cancer. have or might have prostate cancer. have urinary problems due to an enlarged prostate. have high blood pressure or are being treated for high blood pressure have heart problems. have liver or kidney problems. have problems breathing while you sleep (sleep apnea).
Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements. Using… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
8.3Females and Males of Reproductive Potential Infertility During treatment with large doses of exogenous androgens, including testosterone, spermatogenesis may be suppressed through feedback inhibition of the hypothalamic-pituitary-testicular axis [see Warnings and Precautions ( 5.8 )] , possible leading to adverse effects on semen parameters including sperm count. Reduced fertility is observed in some men taking testosterone replacement therapy. Testicular atrophy, subfertility, and infertility have also been reported in men who abuse anabolic androgenic steroids [see Drug Abuse and Dependence ( 9.2 )] .
With either type of use, the impact on fertility may be irreversible.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Testosterone gel 1% delivers physiologic amounts of testosterone, producing circulating testosterone concentrations that approximate normal concentrations (e.g., 300 to 1,000 ng/dL) seen in healthy men. The skin serves as a reservoir for the sustained release of testosterone into the systemic circulation. Approximately 10% of the testosterone applied on the skin surface is absorbed into the systemic circulation during a 24-hour period.
Single Dose In single-dose studies, when either testosterone gel 1% 50 mg or 100 mg was administered, absorption of testosterone into the blood continued for the entire 24-hour dosing period. Also, mean peak and average serum concentrations within the normal range were achieved within 24 hours. Multiple Dose With single daily applications of testosterone gel 1% 50 mg and 100 mg, follow-up measurements at 30 and 90 days after starting treatment have confirmed that serum testosterone and DHT concentrations are generally maintained within the normal range.
Figure 1 summarizes the 24-hour pharmacokinetic profile of testosterone for patients maintained on testosterone gel 1% 50 mg or testosterone gel 1% 100 mg for 30 days. Figure 1: Mean Steady-State Serum Testosterone (± SD) (ng/dL) Concentrations on Day 30 in Patients Applying Testosterone gel 1% Once Daily The average daily testosterone concentration produced by testosterone gel 1% 100 mg at Day 30 was 612 (± 286) ng/dL and by testosterone gel 1% 50 mg at Day 30 was 365 (± 187) ng/dL. Distribution Circulating testosterone is primarily bound in the serum to sex hormone-binding globulin (SHBG) and albumin.
Approximately 40% of testosterone in plasma is bound to SHBG, 2% remains unbound (free) and the rest is loosely bound to albumin and other proteins. Metabolism Testosterone is metabolized to various 17-keto steroids through 2 different pathways. The major active metabolites of testosterone are estradiol and DHT.
The average daily DHT concentration produced by testosterone gel 1% 100 mg at Day 30 was 555 (± 293) pg/mL and by testosterone gel 1% 50 mg at Day 30 was 346 (± 212) pg/mL. Figure 2 summarizes the 24-hour pharmacokinetic profile of DHT for patients maintained on testosterone gel 1% 50 mg or testosterone gel 1% 100 mg for 30 days. Figure 2: Mean Steady-State Serum Dihydrotestosterone (± SD) (pg/mL) Concentrations on Day 30 in Patients Applying Testosterone Gel 1% Once Daily Excretion There is considerable variation in the half-life of testosterone concentration as reported in the literature, ranging from 10 to 100 minutes.
About 90% of a dose of testosterone given intramuscularly is excreted in the urine as glucuronic acid and sulfuric acid conjugates of testosterone and its metabolites. About 6% of a dose is excreted in the feces, mostly in the unconjugated form. Inactivation of testosterone occurs primarily in the liver.
Potential for Testosterone Transfer from Male Patients to Female Partners The potential for dermal testosterone transfer following testosterone gel 1% use was evaluated in two clinical trials with males dosed with testosterone gel 1% and their untreated female partners. In the first trial, 30 couples were evenly randomized to 5 groups. In the first 4 groups, 100 mg of testosterone gel 1% was applied to the male abdomen and the couples were then asked to rub abdomen-to-abdomen for 15 minutes at 1 hour, 4 hours, 8 hours, or 12 hours after dose application, respectively.
In these couples, serum testosterone concentrations in female partners increased from baseline by at least 6 times and potential for transfer was seen at all time points. When 6 males used a shirt to cover the abdomen at 15 minutes post-application and partners again rubbed abdomens for 15 minutes at the 1-hour time point, serum testosterone concentrations in female partners increased from baseline by approximately 3 times. In the second trial, 24 couples were evenly randomized to 4 groups.
Testosterone gel 1% 100 mg was appl… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics No specific pharmacodynamic studies were conducted using testosterone gel 1%.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Clinical Trials in Adult Hypogonadal Males Testosterone gel 1% was evaluated in a randomized multicenter, multi-dose, active and placebo controlled 90-day study in 406 adult males with morning testosterone concentrations ≤ 300 ng/dL. The study was double-blind for the doses of testosterone gel 1% and placebo, but open-label for the non-scrotal testosterone transdermal system. During the first 60 days, patients were evenly randomized to testosterone gel 1% 50 mg, testosterone gel 1% 100 mg, placebo gel, or testosterone transdermal system.
At Day 60, patients receiving testosterone gel 1% were maintained at the same dose, or were titrated up or down within their treatment group, based on 24-hour averaged serum testosterone concentration obtained on Day 30. Of 192 hypogonadal men who were appropriately titrated with testosterone gel 1% and who had sufficient data for analysis, 74% achieved an average serum testosterone concentration within the normal range (300 to 1,000 ng/dL) on treatment Day 90. Table 2 summarizes the mean testosterone concentrations on Day 30 for patients receiving testosterone gel 1% 50 mg or 100 mg.
Table 2: Mean (± SD) Steady-State Serum Testosterone Concentrations on Day 30 Testosterone Gel 1% Testosterone Gel 1% 50 mg 100 mg Placebo ( n=94) ( n=95) ( n=93) C avg 365 ± 187 612 ± 286 216 ± 79 (ng/dL) C max 538 ± 371 897 ± 565 271 ± 110 (ng/dL) C min 223 ± 126 394 ± 189 164 ± 64 (ng/dL)
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.1Controlled Substance Testosterone gel 1% contains testosterone, a Schedule III controlled substance in the Controlled Substances Act.
9.2Abuse Drug abuse is intentional non-therapeutic use of a drug, even once, for its rewarding psychological and physiological effects. Abuse and misuse of testosterone are seen in male and female adults and adolescents. Testosterone, often in combination with other anabolic androgenic steroids (AAS), and not obtained by prescription through a pharmacy, may be abused by athletes and bodybuilders.
There have been reports of misuse of men taking higher doses of legally obtained testosterone than prescribed and continuing testosterone despite adverse events or against medical advice. Abuse-Related Adverse Reactions Serious adverse reactions have been reported in individuals who abuse anabolic androgenic steroids, and include cardiac arrest, myocardial infarction, hypertrophic cardiomyopathy, congestive heart failure, cerebrovascular accident, hepatotoxicity, and serious psychiatric manifestations, including major depression, mania, paranoia, psychosis, delusions, hallucinations, hostility, and aggression.
The following adverse reactions have also been reported in men: transient ischemic attacks, convulsions, hypomania, irritability, dyslipidemias, testicular atrophy, subfertility, and infertility. The following additional adverse reactions have been reported in women: hirsutism, virilization, deepening of voice, clitoral enlargement, breast atrophy, male-pattern baldness, and menstrual irregularities. The following adverse reactions have been reported in male and female adolescents: premature closure of bony epiphyses with termination of growth, and precocious puberty.
Because these reactions are reported voluntarily from a population of uncertain size and may include abuse of other agents, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
9.3Dependence Behaviors Associated with Addiction Continued abuse of testosterone and other anabolic steroids, leading to addiction is characterized by the following behaviors: Taking greater dosages than prescribed Continued drug use despite medical and social problems due to drug use Spending significant time to obtain the drug when supplies of the drug are interrupted Giving a higher priority to drug use than other obligations Having difficulty in discontinuing the drug despite desires and attempts to do so Experiencing withdrawal symptoms upon abrupt discontinuation of use Physical dependence is characterized by withdrawal symptoms after abrupt drug discontinuation or a significant dose reduction of a drug.
Individuals taking supratherapeutic doses of testosterone may experience withdrawal symptoms lasting for weeks or months which include depressed mood, major depression, fatigue, craving, restlessness, irritability, anorexia, insomnia, decreased libido and hypogonadotropic hypogonadism. Drug dependence in individuals using approved doses of testosterone for approved indications has not been documented.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Testosterone has been tested by subcutaneous injection and implantation in mice and rats. In mice, the implant induced cervical-uterine tumors, which metastasized in some cases. There is suggestive evidence that injection of testosterone into some strains of female mice increases their susceptibility to hepatoma.
Testosterone is also known to increase the number of tumors and decrease the degree of differentiation of chemically induced carcinomas of the liver in rats. Mutagenesis Testosterone was negative in the in vitro Ames and in the in vivo mouse micronucleus assays. Impairment of Fertility The administration of exogenous testosterone has been reported to suppress spermatogenesis in the rat, dog, and non-human primates, which was reversible on cessation of the treatment.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Testosterone has been tested by subcutaneous injection and implantation in mice and rats. In mice, the implant induced cervical-uterine tumors, which metastasized in some cases. There is suggestive evidence that injection of testosterone into some strains of female mice increases their susceptibility to hepatoma.
Testosterone is also known to increase the number of tumors and decrease the degree of differentiation of chemically induced carcinomas of the liver in rats. Mutagenesis Testosterone was negative in the in vitro Ames and in the in vivo mouse micronucleus assays. Impairment of Fertility The administration of exogenous testosterone has been reported to suppress spermatogenesis in the rat, dog, and non-human primates, which was reversible on cessation of the treatment.
📖 Instructions for Use ▾
INSTRUCTIONS FOR USE Testosterone (tes tos' ter one) Gel 1%, CIII for topical use Read this Instructions for Use for testosterone gel 1% before you start using it and each time you get a refill. There may be new information. This leaflet does not take the place of talking to your healthcare provider about your medical condition or treatment.
Important Information about Testosterone gel 1%: Children and women should avoid contact with the unwashed or not covered (unclothed) areas where testosterone gel 1% has been applied to your skin. If a child or woman touches the area where you have applied testosterone gel 1%, that area on the child or woman should be washed well with soap and water right away. If you expect to have skin-to-skin contact with another person, first wash the application area well with soap and water.
Testosterone gel 1% is flammable until dry. Let the testosterone gel 1% dry before smoking or going near an open flame. Before applying testosterone gel 1%, make sure that your shoulders and upper arms are clean, dry, and there is no broken skin.
The application sites for testosterone gel 1% are the shoulders and upper arms that will be covered by a short sleeve t-shirt (see Figure A). Do not apply testosterone gel 1% to any other parts of your body such as your stomach area (abdomen), penis, or scrotum. Applying Testosterone gel 1%: Remove the cap from the tube and use the top of the cap to pierce the metal seal on the top of the tube by pushing or screwing the cap in.
Testosterone gel 1% may have an alcoholic or musk odor. Squeeze all of the testosterone gel 1% out of the tube by pushing or screwing the cap in. Apply all of the testosterone gel 1% to the application site.
Rub the gel onto your skin for several seconds. Let the application site dry for a few minutes before putting on a t-shirt. Testosterone gel 1% is flammable until dry.
Let the testosterone gel 1% dry before smoking or going near an open flame. Wash your hands with soap and water right away after applying testosterone gel 1% . Avoid showering, swimming, or bathing for at least 2 hours after you apply testosterone gel 1%.
How should I store testosterone gel 1%? Store testosterone gel 1% at room temperature between 68° to 77°F (20° to 25°C). Safely throw away used testosterone gel 1% in the household trash.
Be careful to prevent accidental exposure of women, children or pets. Keep testosterone gel 1% away from fire. Keep testosterone gel 1% and all medicines out of the reach of children.
This Instructions for Use has been approved by the U.S. Food and Drug Administration. Manufactured For: Teva Pharmaceuticals Parsippany, NJ 07054 Rev.
D 9/2025 1
📄 Recent Major Changes ▾
Warnings and Precautions, Venous Thromboembolism (5.3) 07/2025 Warnings and Precautions, Blood Pressure Increases (5.5) 07/2025 Warnings and Precautions, Cardiovascular Risk (5.5) Removed 07/2025
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL NDC 0591-3524-30 Testosterone Gel 1% CIII Contains 50 mg testosterone per 5 gram tube To be applied to the shoulders and upper arms.* Alcohol 85% v/v Topical testosterone products may have different doses, strengths, or application instructions that may result in different systemic exposure. *PHARMACIST: Dispense the accompanying Medication Guide to each patient. Rx only 30 Unit-dose Tubes 1