
Tradjenta linagliptin 5 mg Tablet, Film Coated, 30-count — NDC 0597-0140-30 (Billing 00597-0140-30)
This is a package of 30 tablets of Tradjenta linagliptin 5 mg Tablet, Film Coated from Boehringer Ingelheim Pharmaceuticals, Inc., marketed since May 2011 and currently FDA-listed; retail pharmacies pay about $16.80 per tablet (NADAC). It is the main listing for this product, which comes in 4 package sizes.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 067353
- GCN: 29890
- GPI-14 (Medi-Span): 27550050000320
- HICL (First Databank): 037576
- AHFS class code: 68:20.05.00
- RxCUI (RxNorm): 1100702
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Dipeptidyl Peptidase 4 Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Linagliptin is used along with diet and exercise and sometimes with other medications to lower blood sugar levels in patients with type 2 diabetes (condition in which blood sugar is too high because the body does not produce or use insulin normally). Linagliptin is in a class of medications called dipeptidyl peptidase-4 (DPP-4) inhibitors. It works by increasing the amounts of certain natural substances that lower blood sugar when it is high. Linagliptin is not used to treat type 1 diabetes (condition in which the body does not produce insulin and, therefore, cannot control the amount of sugar...
Read the full MedlinePlus article ↗- It helps lower blood sugar in adults with type 2 diabetes, alongside diet and exercise. It is not meant for type 1 diabetes, where it would not work.
- Take one tablet by mouth once a day. You can take it with or without food. Follow your prescriber's directions and the label on your prescription.
- Common ones are a stuffy or runny nose, sore throat, diarrhea and cough. Other effects depend on what you take with it, such as urinary tract infections with a sulfonylurea or cons...
- Call for severe stomach pain that won't go away, which could be pancreatitis. Also call for swelling of the face or throat, hives, blisters, severe joint pain, or heart failure sig...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Linagliptin — tap one for details:
Linagliptin may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $16.798 | $503.95 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $17.14 | $514.27 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $16.81 | $504.35 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 00597-0140-30 You're viewing this Main listing | 30 TABLET, FILM COATED in 1 BOTTLE | $16.80 / ea | $503.95 | 2011-05-09 | — | Active |
| 00597-0140-61 0597-0140-61 | 100 BLISTER PACK in 1 CARTON / 1 TABLET, FILM COATED in 1 BLISTER PACK | $16.80 / ea | $1,679.82 | 2011-05-09 | — | Active |
| 00597-0140-70 0597-0140-70 | 7 BLISTER PACK in 1 CARTON / 1 TABLET, FILM COATED in 1 BLISTER PACK | — | — | 2011-05-09 | — | Discontinued by firm |
| 00597-0140-90 0597-0140-90 | 90 TABLET, FILM COATED in 1 BOTTLE | $16.80 / ea | $1,511.84 | 2011-05-09 | — | Active |
This pack has the lowest per-ea cost of the 3 priced pack sizes ($16.80 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 84% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 00597-0140-90?
What NDC number is used to bill for this package of Tradjenta linagliptin 5 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Tradjenta 5 mgthis 00597-0140-30 | Boehringer | 30 tablets | $16.798 | AB | Availability likely | — |
| Tradjenta 5 mg 50090-4383-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Tradjenta 5 mg 55154-0410-08 | Cardinal | 2640 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8853156 ↗ | Method of use | U-1642 | Mar 5, 2031 |
| US 8673927 ↗ delist req. | Method of use | U-1503 | May 4, 2027 |
| US 8846695 ↗ delist req. | Method of use | U-1503 | Jun 4, 2030 |
| US 9486526 ↗ | Method of use | U-1915 | Aug 5, 2029 |
| US 12364700 ↗ | Method of use | U-4224 | Jun 8, 2037 |
| US 11911388 ↗ | Method of use | U-3854 | Apr 10, 2030 |
| US 10034877 ↗ | Method of use | U-2347 | Aug 5, 2029 |
| US 12178819 ↗ | Drug product | — | May 4, 2027 |
| US 11033552 ↗ | Drug product | — | May 4, 2027 |
| US 8883805 ↗ | Drug product | — | Nov 26, 2025 |
| US 8846695*PED ↗ | Drug product | — | Dec 4, 2030 |
| US 8883805*PED ↗ | Drug product | — | May 26, 2026 |
| US 8673927*PED ↗ | Drug product | — | Nov 4, 2027 |
| US 8853156*PED ↗ | Drug product | — | Sep 5, 2031 |
| US 10034877*PED ↗ | Drug product | — | Feb 5, 2030 |
| US 9486526*PED ↗ | Drug product | — | Feb 5, 2030 |
| US 11033552*PED ↗ | Drug product | — | Nov 4, 2027 |
| US 12364700*PED ↗ | Drug product | — | Dec 8, 2037 |
| Code | What it grants | Expires |
|---|---|---|
| M-295 | New indication / labeling change (3-year) | Jun 20, 2026 |
| PED | Pediatric Exclusivity (+6 months) | Dec 20, 2026 |
Is there a generic version of TRADJENTA 5 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE TRADJENTA is indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus . TRADJENTA is a dipeptidyl peptidase-4 (DPP-4) inhibitor indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus ( 1 ) Limitations of Use Not recommended in patients with type 1 diabetes mellitus as it would not be effective ( 1 ) Has not been studied in patients with a history of pancreatitis ( 1 ) Limitations of Use TRADJENTA is not recommended in patients with type 1 diabetes mellitus as it would not be effective.
TRADJENTA has not been studied in patients with a history of pancreatitis. It is unknown whether patients with a history of pancreatitis are at an increased risk for the development of pancreatitis while using TRADJENTA [see Warnings and Precautions (5.1) ].
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended dosage of TRADJENTA is 5 mg orally once daily ( 2.1 ) TRADJENTA can be taken with or without food ( 2.1 )
2.1Recommended Dosage and Administration The recommended dosage of TRADJENTA is 5 mg taken orally once daily, with or without food.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 5 mg, light red, round, biconvex, bevel-edged, film-coated tablets with "D5" debossed on one side and the Boehringer Ingelheim symbol debossed on the other side. Tablets: 5 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS TRADJENTA is contraindicated in patients with hypersensitivity to linagliptin or any of the excipients in TRADJENTA, reactions such as anaphylaxis, angioedema, exfoliative skin conditions, urticaria, or bronchial hyperreactivity have occurred [see Warnings and Precautions (5.3) and Adverse Reactions (6) ]. Hypersensitivity to linagliptin or any of the excipients in TRADJENTA ( 4 , 5.3 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Pancreatitis: There have been reports of acute pancreatitis, including fatal pancreatitis. If pancreatitis is suspected, promptly discontinue TRADJENTA. ( 5.1 ) Hypoglycemia: Consider lowering the dosage of insulin secretagogue or insulin to reduce the risk of hypoglycemia when initiating TRADJENTA ( 5.2 ) Hypersensitivity reactions: Serious hypersensitivity reactions (e.g., anaphylaxis, angioedema, and exfoliative skin conditions) have occurred with TRADJENTA.
If hypersensitivity reactions occur, discontinue TRADJENTA, treat promptly, and monitor until signs and symptoms resolve. ( 5.3 ) Arthralgia: Severe and disabling arthralgia has been reported in patients taking TRADJENTA. Consider as a possible cause for severe joint pain and discontinue drug if appropriate.
( 5.4 ) Bullous pemphigoid: There have been reports of bullous pemphigoid requiring hospitalization. Tell patients to report development of blisters or erosions. If bullous pemphigoid is suspected, discontinue TRADJENTA.
( 5.5 ) Heart failure: Heart failure has been observed with two other members of the DPP-4 inhibitor class. Consider risks and benefits of TRADJENTA in patients who have known risk factors for heart failure. Monitor for signs and symptoms.
( 5.6 )
5.1Pancreatitis Acute pancreatitis, including fatal pancreatitis, has been reported in patients treated with TRADJENTA. In the CARMELINA trial [see Clinical Studies (14.2) ] , acute pancreatitis was reported in 9 (0.3%) patients treated with TRADJENTA and in 5 (0.1%) patients treated with placebo. Two patients treated with TRADJENTA in the CARMELINA trial had acute pancreatitis with a fatal outcome.
There have been postmarketing reports of acute pancreatitis, including fatal pancreatitis, in patients treated with TRADJENTA. Take careful notice of potential signs and symptoms of pancreatitis. If pancreatitis is suspected, promptly discontinue TRADJENTA and initiate appropriate management.
It is unknown whether patients with a history of pancreatitis are at increased risk for the development of pancreatitis while using TRADJENTA.
5.2Hypoglycemia with Concomitant Use with Insulin and Insulin Secretagogues Insulin secretagogues and insulin are known to cause hypoglycemia. The risk of hypoglycemia is increased when TRADJENTA is used in combination with an insulin secretagogue (e.g., sulfonylurea) or insulin [see Adverse Reactions (6.1) ] . The use of TRADJENTA in combination with insulin in subjects with severe renal impairment was associated with a higher rate of hypoglycemia [see Adverse Reactions (6.1) ] .
Therefore, a lower dosage of the insulin secretagogue or insulin may be required to reduce the risk of hypoglycemia when used in combination with TRADJENTA.
5.3Hypersensitivity Reactions There have been postmarketing reports of serious hypersensitivity reactions in patients treated with TRADJENTA. These reactions include anaphylaxis, angioedema, and exfoliative skin conditions. Onset of these reactions occurred predominantly within the first 3 months after initiation of treatment with TRADJENTA, with some reports occurring after the first dose.
If a serious hypersensitivity reaction is suspected, discontinue TRADJENTA, assess for other potential causes for the event, and institute alternative treatment for diabetes mellitus. Angioedema has also been reported with other dipeptidyl peptidase-4 (DPP-4) inhibitors. Use caution in a patient with a history of angioedema to another DPP-4 inhibitor because it is unknown whether such patients will be predisposed to angioedema with TRADJENTA.
5.4Severe and Disabling Arthralgia There have been postmarketing reports of severe and disabling arthralgia in patients taking TRADJENTA [see Adverse Reactions (6) ] . The time to onset of symptoms following initiation of drug therapy varied from one day to years. Patients experienced relief of symptoms upon discontinuation of the medication. A subset of patients experienced a recurrence of sympto… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described below or elsewhere in the prescribing information: Pancreatitis [see Warnings and Precautions (5.1) ] Hypoglycemia with Concomitant Use with Insulin and Insulin Secretagogues [see Warnings and Precautions (5.2) ] Hypersensitivity Reactions [see Warnings and Precautions (5.3) ] Severe and Disabling Arthralgia [see Warnings and Precautions (5.4) ] Bullous Pemphigoid [see Warnings and Precautions (5.5) ] Heart Failure [see Warnings and Precautions (5.6) ] Most common adverse reaction (incidence ≥5% and more often than placebo) was nasopharyngitis ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Boehringer Ingelheim Pharmaceuticals, Inc. at 1-800-542-6257, or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety evaluation of TRADJENTA 5 mg once daily in patients with type 2 diabetes mellitus is based on 14 placebo-controlled trials, 1 active-controlled trial, and one trial in patients with severe renal impairment. In the 14 placebo-controlled studies, a total of 3,625 patients were randomized and treated with TRADJENTA 5 mg daily and 2,176 with placebo.
The mean exposure in patients treated with TRADJENTA across studies was 29.6 weeks. The maximum follow-up was 78 weeks. TRADJENTA 5 mg once daily was studied as monotherapy in three placebo-controlled trials of 18 and 24 weeks' duration and in five additional placebo-controlled studies lasting ≤18 weeks.
The use of TRADJENTA in combination with other antihyperglycemic agents was studied in six placebo-controlled trials: two with metformin (12 and 24 weeks' treatment duration); one with a sulfonylurea (18 weeks' treatment duration); one with metformin and sulfonylurea (24 weeks' treatment duration); one with pioglitazone (24 weeks' treatment duration); and one with insulin (primary endpoint at 24 weeks). In a pooled dataset of 14 placebo-controlled clinical trials, adverse reactions that occurred in ≥2% of patients receiving TRADJENTA (n = 3,625) and more commonly than in patients given placebo (n = 2,176), are shown in Table 1.
Table 1 Adverse Reactions Reported in ≥2% of Patients Treated with TRADJENTA and Greater than Placebo in Placebo-Controlled Clinical Studies of TRADJENTA Monotherapy or Combination Therapy Adverse Reactions TRADJENTA 5 mg (%) n = 3,625 Placebo (%) n = 2,176 Nasopharyngitis 7.0
6.1Diarrhea 3.3
3.0Cough 2.1
1.4Rates for other adverse reactions for TRADJENTA 5 mg vs placebo when TRADJENTA was used in combination with specific antidiabetic agents were: urinary tract infection (3.1% vs 0%) and hypertriglyceridemia (2.4% vs 0%) when TRADJENTA was used as add-on to sulfonylurea; hyperlipidemia (2.7% vs 0.8%) and weight increased (2.3% vs 0.8%) when TRADJENTA was used as add-on to pioglitazone; and constipation (2.1% vs 1%) when TRADJENTA was used as add-on to basal insulin therapy. Other adverse reactions reported in clinical studies with treatment of TRADJENTA were hypersensitivity (e.g., urticaria, angioedema, localized skin exfoliation, or bronchial hyperreactivity) and myalgia.
Following 104 weeks' treatment in a controlled trial comparing TRADJENTA with glimepiride in which all patients were also receiving metformin, adverse reactions reported in ≥5% of patients treated with TRADJENTA (n = 776) and more frequently than in patients treated with a sulfonylurea (n = 775) were back pain (9.1% vs 8.4%), arthralgia (8.1% vs 6.1%), upper respiratory tract infection (8.0% vs 7.6%), headache (6.4% vs 5.2%), cough (6.1% vs 4.9%), and pain in extremity (5.3% vs 3.9%). In the clinical trial program, pancreatitis was reported in 15.2 cases per 10,000 patient year exposure while being treated with… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Strong P-glycoprotein/CYP3A4 inducer: The efficacy of TRADJENTA may be reduced when administered in combination (e.g., with rifampin). Use of alternative treatments is strongly recommended. ( 7.1 )
7.1Inducers of P-glycoprotein or CYP3A4 Enzymes Rifampin decreased linagliptin exposure, suggesting that the efficacy of TRADJENTA may be reduced when administered in combination with a strong P-gp or CYP3A4 inducer. Therefore, use of alternative treatments is strongly recommended when linagliptin is to be administered with a strong P-gp or CYP3A4 inducer [see Clinical Pharmacology (12.3) ] .
7.2Insulin Secretagogues or Insulin Insulin and insulin secretagogues are known to cause hypoglycemia. The risk of hypoglycemia is increased when linagliptin is used in combination with an insulin secretagogue (e.g., sulfonylurea) or insulin. Coadministration of TRADJENTA with an insulin secretagogue (e.g., sulfonylurea) or insulin may require lower dosages of the insulin secretagogue or insulin to reduce the risk of hypoglycemia [see Warnings and Precautions (5.2) ] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary The limited data with TRADJENTA use in pregnant women are not sufficient to inform of drug-associated risk for major birth defects and miscarriage. There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy [see Clinical Considerations ]. In animal reproduction studies, no adverse developmental effects were observed when linagliptin was administered to pregnant rats during the period of organogenesis at doses similar to the maximum recommended clinical dose, based on exposure [see Data ] .
The estimated background risk of major birth defects is 6% to 10% in women with pre-gestational diabetes with a HbA1c >7 and has been reported to be as high as 20% to 25% in women with HbA1c >10. The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, preeclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity. Data Animal Data No adverse developmental outcome was observed when linagliptin was administered to pregnant Wistar Han rats and Himalayan rabbits during the period of organogenesis at doses up to 240 mg/kg/day and 150 mg/kg/day, respectively.
These doses represent approximately 943-times (rats) and 1,943-times (rabbits) the 5 mg maximum clinical dose, based on exposure. No adverse functional, behavioral, or reproductive outcome was observed in offspring following administration of linagliptin to Wistar Han rats from gestation day 6 to lactation day 21 at a dose 49-times the maximum recommended human dose, based on exposure. Linagliptin crosses the placenta into the fetus following oral dosing in pregnant rats and rabbits.
8.2Lactation Risk Summary There is no information regarding the presence of linagliptin in human milk, the effects on the breastfed infant, or the effects on milk production. However, linagliptin is present in rat milk. Therefore, the developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for TRADJENTA and any potential adverse effects on the breastfed child from TRADJENTA or from the underlying maternal condition.
8.4Pediatric Use The safety and effectiveness of TRADJENTA have not been established in pediatric patients. Effectiveness of TRADJENTA was not demonstrated in a 26-week randomized, double-blind, placebo-controlled trial (NCT03429543) in 157 pediatric patients aged 10 to 17 years with inadequately controlled type 2 diabetes mellitus.
8.5Geriatric Use In linagliptin studies, 1,085 linagliptin-treated patients were 65 years of age and older and 131 patients were 75 years of age and older. In these linagliptin studies, no overall differences in safety or effectiveness of linagliptin were observed between geriatric patients and younger adult patients.
8.6Renal Impairment No dosage adjustment is recommended for patients with renal impairment [see Clinical Pharmacology (12.3) ]. In the TRADJENTA treatment arm of the CARMELINA trial [see Clinical Studies (14) ] , 2,200 (63%) patients had renal impairment (eGFR <60 mL/min/1.73 m 2 ). Approximately 20% of the population had eGFR ≥45 to <60 mL/min/1.73 m 2 , 28% of the population had eGFR ≥30 to <45 mL/min/1.73 m 2 and 15% had eGFR <30 mL/min/1.73 m 2 .
The overall incidence of adverse reactions were generally similar between the TRADJENTA and placebo treatment arms.
8.7Hepatic Impairment No dose adjustment is recommended for patients with hepatic impairment [see Clinical Pharmacology (12.3) ] .
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary The limited data with TRADJENTA use in pregnant women are not sufficient to inform of drug-associated risk for major birth defects and miscarriage. There are risks to the mother and fetus associated with poorly controlled diabetes in pregnancy [see Clinical Considerations ]. In animal reproduction studies, no adverse developmental effects were observed when linagliptin was administered to pregnant rats during the period of organogenesis at doses similar to the maximum recommended clinical dose, based on exposure [see Data ] .
The estimated background risk of major birth defects is 6% to 10% in women with pre-gestational diabetes with a HbA1c >7 and has been reported to be as high as 20% to 25% in women with HbA1c >10. The estimated background risk of miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Poorly controlled diabetes in pregnancy increases the maternal risk for diabetic ketoacidosis, preeclampsia, spontaneous abortions, preterm delivery, and delivery complications. Poorly controlled diabetes increases the fetal risk for major birth defects, stillbirth, and macrosomia related morbidity. Data Animal Data No adverse developmental outcome was observed when linagliptin was administered to pregnant Wistar Han rats and Himalayan rabbits during the period of organogenesis at doses up to 240 mg/kg/day and 150 mg/kg/day, respectively.
These doses represent approximately 943-times (rats) and 1,943-times (rabbits) the 5 mg maximum clinical dose, based on exposure. No adverse functional, behavioral, or reproductive outcome was observed in offspring following administration of linagliptin to Wistar Han rats from gestation day 6 to lactation day 21 at a dose 49-times the maximum recommended human dose, based on exposure. Linagliptin crosses the placenta into the fetus following oral dosing in pregnant rats and rabbits.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of TRADJENTA have not been established in pediatric patients. Effectiveness of TRADJENTA was not demonstrated in a 26-week randomized, double-blind, placebo-controlled trial (NCT03429543) in 157 pediatric patients aged 10 to 17 years with inadequately controlled type 2 diabetes mellitus.
🧓 Geriatric Use ▾
8.5Geriatric Use In linagliptin studies, 1,085 linagliptin-treated patients were 65 years of age and older and 131 patients were 75 years of age and older. In these linagliptin studies, no overall differences in safety or effectiveness of linagliptin were observed between geriatric patients and younger adult patients.
🆘 Overdosage ▾
10 OVERDOSAGE In the event of an overdose with TRADJENTA, consider contacting the Poison Help Line (1-800-222-1222) or a medical toxicologist for additional overdosage management recommendations. Removal of linagliptin by hemodialysis or peritoneal dialysis is unlikely.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Linagliptin is an inhibitor of DPP-4, an enzyme that degrades the incretin hormones glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP). Thus, linagliptin increases the concentrations of active incretin hormones, stimulating the release of insulin in a glucose-dependent manner and decreasing the levels of glucagon in the circulation. Both incretin hormones are involved in the physiological regulation of glucose homeostasis.
Incretin hormones are secreted at a low basal level throughout the day and levels rise immediately after meal intake. GLP-1 and GIP increase insulin biosynthesis and secretion from pancreatic beta cells in the presence of normal and elevated blood glucose levels. Furthermore, GLP-1 also reduces glucagon secretion from pancreatic alpha-cells, resulting in a reduction in hepatic glucose output.
12.2Pharmacodynamics Linagliptin binds to DPP-4 in a reversible manner and thus increases the concentrations of incretin hormones. Linagliptin glucose-dependently increases insulin secretion and lowers glucagon secretion, thus resulting in better regulation of glucose homeostasis. Linagliptin binds selectively to DPP-4 and selectively inhibits DPP-4, but not DPP-8 or DPP-9 activity in vitro at concentrations approximating therapeutic exposures.
Cardiac Electrophysiology In a randomized, placebo-controlled, active-comparator, 4-way crossover study, 36 healthy subjects were administered a single oral dose of linagliptin 5 mg, linagliptin 100 mg (20 times the recommended dose), moxifloxacin, and placebo. No increase in QTc was observed with either the recommended dose of 5 mg or the 100 mg dose. At the 100 mg dose, peak linagliptin plasma concentrations were approximately 38-fold higher than the peak concentrations following a 5 mg dose.
12.3Pharmacokinetics The pharmacokinetics of linagliptin has been characterized in healthy subjects and patients with type 2 diabetes mellitus. After oral administration of a single 5 mg dose to healthy subjects, peak plasma concentrations of linagliptin occurred at approximately 1.5 hours post dose (T max ); the mean plasma area under the curve (AUC) was 139 nmol*h/L and maximum concentration (C max ) was 8.9 nmol/L. Plasma concentrations of linagliptin decline in at least a biphasic manner with a long terminal half-life (>100 hours), related to the saturable binding of linagliptin to DPP-4.
The prolonged elimination phase does not contribute to the accumulation of the drug. The effective half-life for accumulation of linagliptin, as determined from oral administration of multiple doses of linagliptin 5 mg, is approximately 12 hours. After once-daily dosing, steady-state plasma concentrations of linagliptin 5 mg are reached by the third dose, and C max and AUC increased by a factor of 1.3 at steady-state compared with the first dose.
The intra-subject and inter-subject coefficients of variation for linagliptin AUC were small (12.6% and 28.5%, respectively). Plasma AUC of linagliptin increased in a less than dose-proportional manner in the dose range of 1 to 10 mg. The pharmacokinetics of linagliptin is similar in healthy subjects and in patients with type 2 diabetes mellitus.
Absorption The absolute bioavailability of linagliptin is approximately 30%. A high-fat meal reduced C max by 15% and increased AUC by 4%; this effect is not clinically relevant. TRADJENTA may be administered with or without food.
Distribution The mean apparent volume of distribution at steady-state following a single intravenous dose of linagliptin 5 mg to healthy subjects is approximately 1,110 L, indicating that linagliptin extensively distributes to the tissues. Plasma protein binding of linagliptin is concentration-dependent, decreasing from about 99% at 1 nmol/L to 75%-89% at ≥30 nmol/L, reflecting saturation of binding to DPP-4 with increasing concentration of linagliptin. At high concentrations, where DPP-4 is fully satura… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Linagliptin is an inhibitor of DPP-4, an enzyme that degrades the incretin hormones glucagon-like peptide-1 (GLP-1) and glucose-dependent insulinotropic polypeptide (GIP). Thus, linagliptin increases the concentrations of active incretin hormones, stimulating the release of insulin in a glucose-dependent manner and decreasing the levels of glucagon in the circulation. Both incretin hormones are involved in the physiological regulation of glucose homeostasis.
Incretin hormones are secreted at a low basal level throughout the day and levels rise immediately after meal intake. GLP-1 and GIP increase insulin biosynthesis and secretion from pancreatic beta cells in the presence of normal and elevated blood glucose levels. Furthermore, GLP-1 also reduces glucagon secretion from pancreatic alpha-cells, resulting in a reduction in hepatic glucose output.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING TRADJENTA tablets are available as light red, round, biconvex, bevel-edged, film-coated tablets containing 5 mg of linagliptin. TRADJENTA tablets are debossed with "D5" on one side and the Boehringer Ingelheim symbol on the other side. They are supplied as follows: Bottles of 30 (NDC 0597-0140-30) Bottles of 90 (NDC 0597-0140-90) Cartons containing 10 blister cards of 10 tablets each (10 × 10) (NDC 0597-0140-61), institutional pack.
If repackaging is required, dispense in a tight container as defined in USP. Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📦 Storage and Handling ▾
Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION TRADJENTA tablets for oral use contain linagliptin, an inhibitor of the DPP-4 enzyme. The chemical name of linagliptin is 1H-Purine-2,6-dione, 8-[(3R)-3-amino-1-piperidinyl]-7-(2-butyn-1-yl)-3,7-dihydro-3-methyl-1-[(4-methyl-2-quinazolinyl)methyl]- The molecular formula is C 25 H 28 N 8 O 2 and the molecular weight is 472.54 g/mol. The structural formula is: Linagliptin is a white to yellowish, not or only slightly hygroscopic solid substance.
It is very slightly soluble in water (0.9 mg/mL). Linagliptin is soluble in methanol (ca. 60 mg/mL), sparingly soluble in ethanol (ca.
10 mg/mL), very slightly soluble in isopropanol (<1 mg/mL), and very slightly soluble in acetone (ca. 1 mg/mL). Each film-coated tablet of TRADJENTA contains 5 mg of linagliptin free base and the following inactive ingredients: copovidone, corn starch, magnesium stearate, mannitol, and pregelatinized starch.
In addition, the film coating contains the following inactive ingredients: hypromellose, polyethylene glycol, red ferric oxide, talc, and titanium dioxide. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Pancreatitis Inform patients that acute pancreatitis has been reported during use of TRADJENTA. Inform patients that persistent severe abdominal pain, sometimes radiating to the back, which may or may not be accompanied by vomiting, is the hallmark symptom of acute pancreatitis.
Instruct patients to discontinue TRADJENTA promptly and contact their healthcare provider if persistent severe abdominal pain occurs [see Warnings and Precautions (5.1) ] . Hypoglycemia with Concomitant Use with Insulin and Insulin Secretagogues Inform patients that the incidence of hypoglycemia is increased when TRADJENTA is used in combination with an insulin secretagogue (e.g., sulfonylurea) or insulin [see Warnings and Precautions (5.2) ] . Hypersensitivity Reactions Inform patients that serious allergic reactions, such as anaphylaxis, angioedema, and exfoliative skin conditions, have been reported during postmarketing use of TRADJENTA.
If symptoms of allergic reactions (such as rash, skin flaking or peeling, urticaria, swelling of the skin, or swelling of the face, lips, tongue, and throat that may cause difficulty in breathing or swallowing) occur, patients must stop taking TRADJENTA and seek medical advice promptly [see Warnings and Precautions (5.3) ] . Severe and Disabling Arthralgia Inform patients that severe and disabling joint pain may occur with this class of drugs. The time to onset of symptoms can range from one day to years.
Instruct patients to seek medical advice if severe joint pain occurs [see Warnings and Precautions (5.4) ]. Bullous Pemphigoid Inform patients that bullous pemphigoid has been reported during use of TRADJENTA. Instruct patients to seek medical advice if blisters or erosions occur [see Warnings and Precautions (5.5) ].
Heart Failure Inform patients of the signs and symptoms of heart failure. Before initiating TRADJENTA, patients should be asked about a history of heart failure or other risk factors for heart failure including moderate to severe renal impairment. Instruct patients to contact their healthcare provider as soon as possible if they experience symptoms of heart failure, including increasing shortness of breath, rapid increase in weight or swelling of the feet [see Warnings and Precautions (5.6) ].
Missed Dose Instruct patients to take TRADJENTA only as prescribed. If a dose is missed, it should be taken as soon as the patient remembers. Advise patients not to double their next dose.
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: June 2023 MEDICATION GUIDE TRADJENTA ® (TRAD gen ta) (linagliptin tablets) for oral use What is the most important information I should know about TRADJENTA?
TRADJENTA can cause serious side effects, including: Inflammation of the pancreas (pancreatitis) which may be severe and lead to death. Certain medical problems make you more likely to get pancreatitis. Before you start taking TRADJENTA, tell your healthcare provider if you have ever had: inflammation of your pancreas (pancreatitis) a history of alcoholism stones in your gallbladder (gallstones) high blood triglyceride levels Stop taking TRADJENTA and call your healthcare provider right away if you have pain in your stomach area (abdomen) that is severe and will not go away.
The pain may be felt going from your abdomen to your back. The pain may happen with or without vomiting. These may be symptoms of pancreatitis.
What is TRADJENTA? TRADJENTA is a prescription medicine used along with diet and exercise to lower blood sugar in adults with type 2 diabetes mellitus. TRADJENTA is not for people with type 1 diabetes mellitus.
If you have had pancreatitis in the past, it is not known if you have a higher chance of getting pancreatitis while you take TRADJENTA. It is not known if TRADJENTA is safe and effective in children. Who should not take TRADJENTA?
Do not take TRADJENTA if you: are allergic to linagliptin or any of the ingredients in TRADJENTA. See the end of this Medication Guide for a complete list of ingredients in TRADJENTA. Symptoms of a serious allergic reaction to TRADJENTA may include: skin rash, itching, flaking or peeling raised red patches on your skin (hives) swelling of your face, lips, tongue and throat that may cause difficulty in breathing or swallowing difficulty with swallowing or breathing If you have any of these symptoms, stop taking TRADJENTA and call your healthcare provider right away or go to the nearest hospital emergency room.
What should I tell my healthcare provider before taking TRADJENTA? Before taking TRADJENTA, tell your healthcare provider about all of your medical conditions, including if you: have or have had inflammation of your pancreas (pancreatitis). are pregnant or plan to become pregnant. It is not known if TRADJENTA will harm your unborn baby.
If you are pregnant, talk with your healthcare provider about the best way to control your blood sugar while you are pregnant. are breastfeeding or plan to breastfeed. It is not known if TRADJENTA passes into your breast milk. Talk with your healthcare provider about the best way to feed your baby if you take TRADJENTA.
Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements. TRADJENTA may affect the way other medicines work, and other medicines may affect how TRADJENTA works. Know the medicines you take.
Keep a list of them to show your healthcare provider and pharmacist when you get a new medicine. How should I take TRADJENTA? Take TRADJENTA exactly as your healthcare provider tells you to take it.
Take 1 tablet 1 time each day with or without food. If you miss a dose, take it as soon as you remember. If you do not remember until it is time for your next dose, skip the missed dose and go back to your regular schedule.
Do not take two doses of TRADJENTA at the same time. Your healthcare provider may tell you to take TRADJENTA along with other diabetes medicines. Low blood sugar can happen more often when TRADJENTA is taken with certain other diabetes medicines.
See " What are the possible side effects of TRADJENTA? " If you take too much TRADJENTA, call your healthcare provider or local poison control center or go to the nearest hospital emergency room right away. What are the possible side effects of TRADJENTA? TRADJENTA may cause serious side effects, including: See " What is the most important informat… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetics of linagliptin has been characterized in healthy subjects and patients with type 2 diabetes mellitus. After oral administration of a single 5 mg dose to healthy subjects, peak plasma concentrations of linagliptin occurred at approximately 1.5 hours post dose (T max ); the mean plasma area under the curve (AUC) was 139 nmol*h/L and maximum concentration (C max ) was 8.9 nmol/L. Plasma concentrations of linagliptin decline in at least a biphasic manner with a long terminal half-life (>100 hours), related to the saturable binding of linagliptin to DPP-4.
The prolonged elimination phase does not contribute to the accumulation of the drug. The effective half-life for accumulation of linagliptin, as determined from oral administration of multiple doses of linagliptin 5 mg, is approximately 12 hours. After once-daily dosing, steady-state plasma concentrations of linagliptin 5 mg are reached by the third dose, and C max and AUC increased by a factor of 1.3 at steady-state compared with the first dose.
The intra-subject and inter-subject coefficients of variation for linagliptin AUC were small (12.6% and 28.5%, respectively). Plasma AUC of linagliptin increased in a less than dose-proportional manner in the dose range of 1 to 10 mg. The pharmacokinetics of linagliptin is similar in healthy subjects and in patients with type 2 diabetes mellitus.
Absorption The absolute bioavailability of linagliptin is approximately 30%. A high-fat meal reduced C max by 15% and increased AUC by 4%; this effect is not clinically relevant. TRADJENTA may be administered with or without food.
Distribution The mean apparent volume of distribution at steady-state following a single intravenous dose of linagliptin 5 mg to healthy subjects is approximately 1,110 L, indicating that linagliptin extensively distributes to the tissues. Plasma protein binding of linagliptin is concentration-dependent, decreasing from about 99% at 1 nmol/L to 75%-89% at ≥30 nmol/L, reflecting saturation of binding to DPP-4 with increasing concentration of linagliptin. At high concentrations, where DPP-4 is fully saturated, 70% to 80% of linagliptin remains bound to plasma proteins and 20% to 30% is unbound in plasma.
Plasma binding is not altered in patients with renal or hepatic impairment. Elimination Linagliptin has a terminal half-life of about 200 hours at steady-state, though the accumulation half-life is about 11 hours. Renal clearance at steady-state was approximately 70 mL/min.
Metabolism Following oral administration, the majority (about 90%) of linagliptin is excreted unchanged, indicating that metabolism represents a minor elimination pathway. A small fraction of absorbed linagliptin is metabolized to a pharmacologically inactive metabolite, which shows a steady-state exposure of 13.3% relative to linagliptin. Excretion Following administration of an oral [ 14 C]-linagliptin dose to healthy subjects, approximately 85% of the administered radioactivity was eliminated via the enterohepatic system (80%) or urine (5%) within 4 days of dosing.
Specific Populations Patients with Renal Impairment An open-label pharmacokinetic study evaluated the pharmacokinetics of linagliptin 5 mg in male and female patients with varying degrees of chronic renal impairment. The study included 6 healthy subjects with normal renal function (creatinine clearance [CrCl] ≥80 mL/min), 6 patients with mild renal impairment (CrCl 50 to <80 mL/min), 6 patients with moderate renal impairment (CrCl 30 to <50 mL/min), 10 patients with type 2 diabetes mellitus and severe renal impairment (CrCl <30 mL/min), and 11 patients with type 2 diabetes mellitus and normal renal function.
Creatinine clearance was measured by 24-hour urinary creatinine clearance measurements or estimated from serum creatinine based on the Cockcroft-Gault formula. Under steady-state conditions, linagliptin exposure in patients with mild renal impairment was comparable to healthy subjects. In pa… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Linagliptin binds to DPP-4 in a reversible manner and thus increases the concentrations of incretin hormones. Linagliptin glucose-dependently increases insulin secretion and lowers glucagon secretion, thus resulting in better regulation of glucose homeostasis. Linagliptin binds selectively to DPP-4 and selectively inhibits DPP-4, but not DPP-8 or DPP-9 activity in vitro at concentrations approximating therapeutic exposures.
Cardiac Electrophysiology In a randomized, placebo-controlled, active-comparator, 4-way crossover study, 36 healthy subjects were administered a single oral dose of linagliptin 5 mg, linagliptin 100 mg (20 times the recommended dose), moxifloxacin, and placebo. No increase in QTc was observed with either the recommended dose of 5 mg or the 100 mg dose. At the 100 mg dose, peak linagliptin plasma concentrations were approximately 38-fold higher than the peak concentrations following a 5 mg dose.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Glycemic Control Trials in Adults with Type 2 Diabetes Mellitus TRADJENTA has been studied as monotherapy and in combination with metformin, sulfonylurea, pioglitazone, and insulin. TRADJENTA has also been studied in patients with type 2 diabetes mellitus and severe chronic renal impairment. In patients with type 2 diabetes mellitus, treatment with TRADJENTA produced clinically significant improvements in hemoglobin A1c (A1C), fasting plasma glucose (FPG), and 2-hour post-prandial glucose (PPG) compared with placebo.
Monotherapy A total of 730 patients with type 2 diabetes mellitus participated in 2 double-blind, placebo-controlled studies, one of 18 weeks' and another of 24 weeks' duration, to evaluate the efficacy and safety of TRADJENTA monotherapy. In both monotherapy studies, patients currently on an antihyperglycemic agent discontinued the agent and underwent a diet, exercise, and drug washout period of about 6 weeks that included an open-label placebo run-in during the last 2 weeks. Patients with inadequate glycemic control (A1C 7% to 10%) after the washout period were randomized; patients not currently on antihyperglycemic agents (off therapy for at least 8 weeks) with inadequate glycemic control (A1C 7% to 10%) were randomized after completing the 2-week, open-label, placebo run-in period.
In the 18-week trial, only patients ineligible for metformin were recruited. In the 18-week trial, 76 patients were randomized to placebo and 151 to TRADJENTA 5 mg; in the 24-week trial, 167 patients were randomized to placebo and 336 to TRADJENTA 5 mg. Patients who failed to meet specific glycemic goals during the 18-week trial received rescue therapy with pioglitazone and/or insulin; metformin rescue therapy was used in the 24-week trial.
Treatment with TRADJENTA 5 mg daily provided statistically significant improvements in A1C, FPG, and 2-hour PPG compared with placebo (Table 5). In the 18-week trial, 12% of patients receiving TRADJENTA 5 mg and 18% who received placebo required rescue therapy. In the 24-week trial, 10.2% of patients receiving TRADJENTA 5 mg and 20.9% of patients receiving placebo required rescue therapy.
The improvement in A1C compared with placebo was not affected by gender, age, race, prior antihyperglycemic therapy, baseline BMI, or a standard index of insulin resistance (HOMA-IR). As is typical for trials of agents to treat type 2 diabetes mellitus, the mean reduction in A1C with TRADJENTA appears to be related to the degree of A1C elevation at baseline. In these 18- and 24-week studies, the changes from baseline in A1C were -0.4% and -0.4%, respectively, for those given TRADJENTA, and 0.1% and 0.3%, respectively, for those given placebo.
Change from baseline in body weight did not differ significantly between the groups. Table 5 Glycemic Parameters in Placebo-Controlled Monotherapy Trials of TRADJENTA* 18-Week Trial 24-Week Trial TRADJENTA 5 mg Placebo TRADJENTA 5 mg Placebo *Full analysis population using last observation on trial **18-week trial: Placebo, n=68; TRADJENTA, n=136 24-week trial: Placebo, n=147; TRADJENTA, n=306 ***18-week trial. HbA1c: ANCOVA model included treatment, reason for metformin intolerance and number of prior oral anti-diabetic medicine(s) (OADs) as class-effects, as well as baseline HbA1c as continuous covariates.
FPG: ANCOVA model included treatment, reason for metformin intolerance and number of prior OADs as class-effects, as well as baseline HbA1c and baseline FPG as continuous covariates. 24-week trial. HbA1c: ANCOVA model included treatment and number of prior OADs as class-effects, as well as baseline HbA1c as continuous covariates.
FPG: ANCOVA model included treatment and number of prior OADs as class-effects, as well as baseline HbA1c and baseline FPG as continuous covariates. PPG: ANCOVA model included treatment and number of prior OADs as class-effects, as well as baseline HbA1c and baseline postprandial glucose after two hours as covariate. A1… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Linagliptin did not increase the incidence of tumors in male and female rats in a 2-year study at doses of 6, 18, and 60 mg/kg. The highest dose of 60 mg/kg is approximately 418 times the clinical dose of 5 mg/day based on AUC exposure. Linagliptin did not increase the incidence of tumors in mice in a 2-year study at doses up to 80 mg/kg (males) and 25 mg/kg (females), or approximately 35- and 270-times the clinical dose based on AUC exposure.
Higher doses of linagliptin in female mice (80 mg/kg) increased the incidence of lymphoma at approximately 215-times the clinical dose based on AUC exposure. Linagliptin was not mutagenic or clastogenic with or without metabolic activation in the Ames bacterial mutagenicity assay, a chromosomal aberration test in human lymphocytes, and an in vivo micronucleus assay. In fertility studies in rats, linagliptin had no adverse effects on early embryonic development, mating, fertility, or bearing live young up to the highest dose of 240 mg/kg (approximately 943-times the clinical dose based on AUC exposure).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Linagliptin did not increase the incidence of tumors in male and female rats in a 2-year study at doses of 6, 18, and 60 mg/kg. The highest dose of 60 mg/kg is approximately 418 times the clinical dose of 5 mg/day based on AUC exposure. Linagliptin did not increase the incidence of tumors in mice in a 2-year study at doses up to 80 mg/kg (males) and 25 mg/kg (females), or approximately 35- and 270-times the clinical dose based on AUC exposure.
Higher doses of linagliptin in female mice (80 mg/kg) increased the incidence of lymphoma at approximately 215-times the clinical dose based on AUC exposure. Linagliptin was not mutagenic or clastogenic with or without metabolic activation in the Ames bacterial mutagenicity assay, a chromosomal aberration test in human lymphocytes, and an in vivo micronucleus assay. In fertility studies in rats, linagliptin had no adverse effects on early embryonic development, mating, fertility, or bearing live young up to the highest dose of 240 mg/kg (approximately 943-times the clinical dose based on AUC exposure).
📄 Package Label / Principal Display Panel ▾
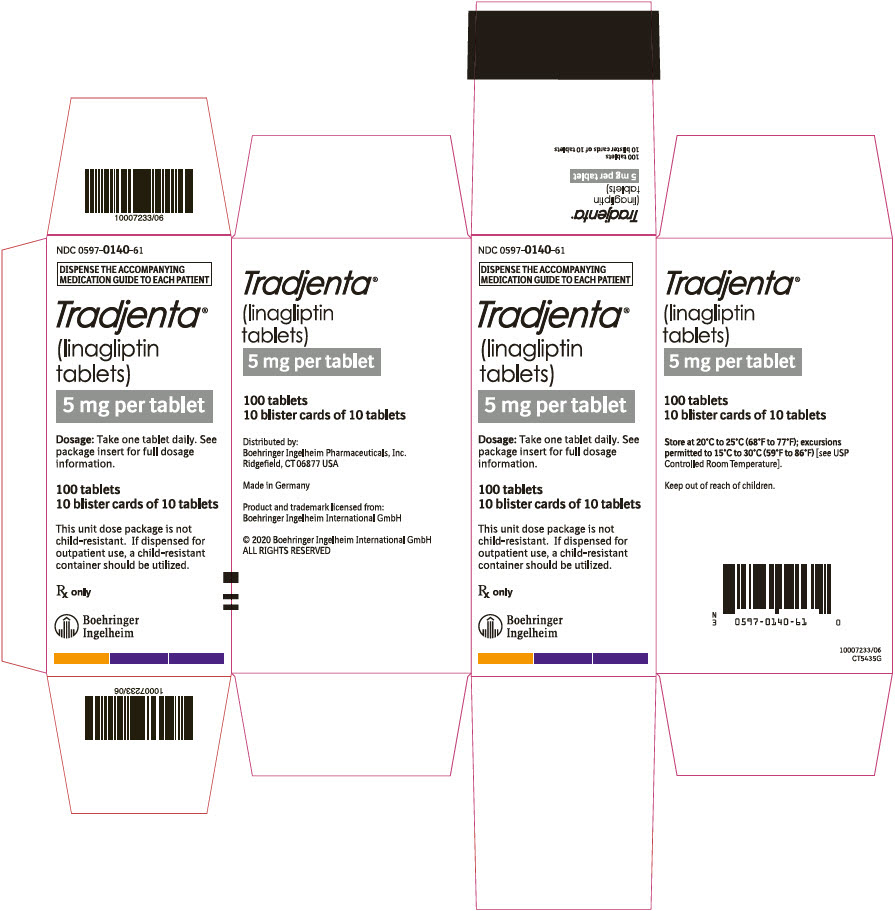
PRINCIPAL DISPLAY PANEL - 5 mg Tablet Blister Card Carton NDC 0597-0140-61 DISPENSE THE ACCOMPANYING MEDICATION GUIDE TO EACH PATIENT Tradjenta ® (linagliptin tablets) 5 mg per tablet Recommended Dosage: Take one tablet daily. See Prescribing Information. 100 tablets 10 blister cards of 10 tablets This unit dose package is not child-resistant.
If dispensed for outpatient use, a child-resistant container should be utilized. Rx only Boehringer Ingelheim PRINCIPAL DISPLAY PANEL - 5 mg Tablet Blister Card Carton