
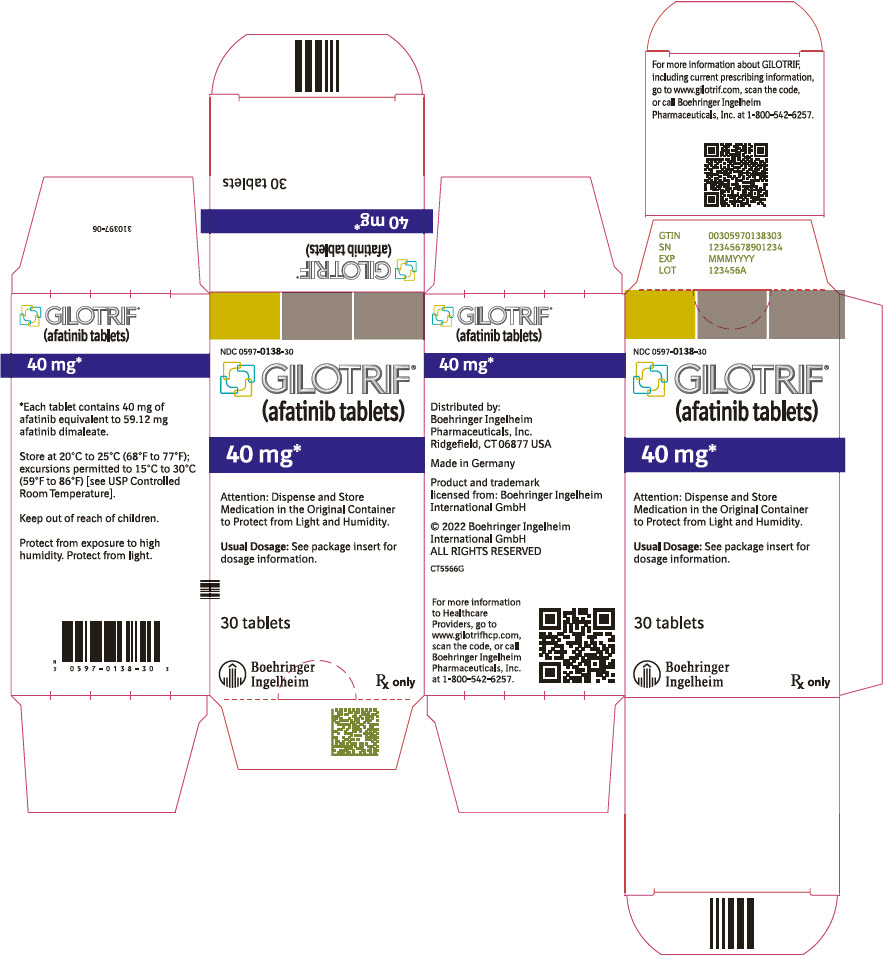
Gilotrif afatinib 40 mg Tablet, Film Coated, 30-count — NDC 0597-0138-30 (Billing 00597-0138-30)
This is a package of 30 tablets of Gilotrif afatinib 40 mg Tablet, Film Coated from Boehringer Ingelheim Pharmaceuticals, Inc., marketed since Jul 2013 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 0597-0138-30 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0597 labeler · 0138 product · 30 package
- Package marketed since
- Aug 8, 2013
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 30 EA per package
- Barcode (UPC-A, from the NDC)
- 3 0597013830 3
- Medicaid fills, this package
- 12 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 071231
- GCN: 34958
- GPI-14 (Medi-Span): 21360006100340
- HICL (First Databank): 040478
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 1430446
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Kinase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats metastatic non-small cell lung cancer. It's used first-line when the tumor has certain non-resistant EGFR mutations found by an FDA-approved test. It's also used for squa...
- Take one tablet by mouth once a day, at least 1 hour before or 2 hours after eating. Food reduces how much you absorb. If you miss a dose, don't take it if your next dose is less t...
- Diarrhea and skin rash are very common. Mouth sores, nail infections, dry skin, itching, poor appetite, nausea and vomiting can also happen. Your care team will usually give you an...
- Call right away for severe or ongoing diarrhea, severe skin blistering or peeling, new or worse cough or shortness of breath, eye pain or redness, or severe stomach pain. Also repo...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Afatinib Dimaleate — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $393.32 | $11,799.69 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $396.97 | $11,909.17 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00597-0138-30 You're viewing this Main listing | 1 BOTTLE in 1 CARTON / 30 TABLET, FILM COATED in 1 BOTTLE | 2013-08-08 | — | Active |
| 00597-0138-95 0597-0138-95 | 1 BOTTLE in 1 CARTON / 30 TABLET, FILM COATED in 1 BOTTLE Sample | 2013-08-08 | Apr 30, 2027 | Active |
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 00597-0138-95?
What NDC number is used to bill for this package of Gilotrif afatinib 40 mg Tablet, Film Coated?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Gilotrif 40 mgthis 00597-0138-30 | Boehringer | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9539258 ↗ | Method of use | U-1950 | Nov 9, 2026 |
| US 9539258 ↗ | Method of use | U-1950 | Nov 9, 2026 |
| US 9539258 ↗ | Method of use | U-1950 | Nov 9, 2026 |
| US 8545884 ↗ | Drug product | — | Dec 19, 2029 |
| US 8426586 ↗ | Drug substance | — | Oct 10, 2029 |
| US 8545884 ↗ | Drug product | — | Dec 19, 2029 |
| US 8426586 ↗ | Drug substance | — | Oct 10, 2029 |
| US RE43431 ↗ | Drug substance | — | Jan 13, 2026 |
| US 8545884 ↗ | Drug product | — | Dec 19, 2029 |
| US 10004743 ↗ | Drug product | — | Jul 5, 2030 |
| US RE43431 ↗ | Drug substance | — | Jan 13, 2026 |
| US 10004743 ↗ | Drug product | — | Jul 5, 2030 |
| US 8426586 ↗ | Drug substance | — | Oct 10, 2029 |
| US RE43431 ↗ | Drug substance | — | Jan 13, 2026 |
| US 10004743 ↗ | Drug product | — | Jul 5, 2030 |
| US 8545884*PED ↗ | Drug product | — | Jun 19, 2030 |
| US 8545884*PED ↗ | Drug product | — | Jun 19, 2030 |
| US 8545884*PED ↗ | Drug product | — | Jun 19, 2030 |
| US 8426586*PED ↗ | Drug product | — | Apr 10, 2030 |
| US RE43431*PED ↗ | Drug product | — | Jul 13, 2026 |
| US RE43431*PED ↗ | Drug product | — | Jul 13, 2026 |
| US 8426586*PED ↗ | Drug product | — | Apr 10, 2030 |
| US RE43431*PED ↗ | Drug product | — | Jul 13, 2026 |
| US 8426586*PED ↗ | Drug product | — | Apr 10, 2030 |
| US 10004743*PED ↗ | Drug product | — | Jan 5, 2031 |
| US 10004743*PED ↗ | Drug product | — | Jan 5, 2031 |
| US 10004743*PED ↗ | Drug product | — | Jan 5, 2031 |
| US 9539258*PED ↗ | Drug product | — | May 9, 2027 |
| US 9539258*PED ↗ | Drug product | — | May 9, 2027 |
| US 9539258*PED ↗ | Drug product | — | May 9, 2027 |
Is there a generic version of GILOTRIF 40 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Afatinib inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Boehringer Ingelheim Pharmaceuticals, Inc. labeler code 00597
- Micardis HCT telmisartan and hydrochlorothiazide 80 mg; 12.5 mg Tablet NDC 0597-0044-37
- Spiriva HandiHaler TIOTROPIUM BROMIDE 18 ug Capsule NDC 0597-0075-41
- Atrovent HFA ipratropium bromide 17 ug Aerosol, Metered NDC 0597-0087-17
- Spiriva Respimat tiotropium bromide inhalation spray 3.124 ug Spray, Metered NDC 0597-0100-28
- Pradaxa dabigatran etexilate mesylate 110 mg Capsule NDC 0597-0108-54
- Gilotrif afatinib 30 mg Tablet, Film Coated NDC 0597-0137-30
- Tradjenta linagliptin 5 mg Tablet, Film Coated NDC 0597-0140-30
- Gilotrif afatinib 20 mg Tablet, Film Coated NDC 0597-0141-30
- Ofev nintedanib 100 mg Capsule NDC 0597-0143-60
- Ofev nintedanib 150 mg Capsule NDC 0597-0145-60
- Jentadueto linagliptin and metformin hydrochloride 2.5 mg; 500 mg Tablet, Film Coated NDC 0597-0146-18
- Jentadueto linagliptin and metformin hydrochloride 2.5 mg; 850 mg Tablet, Film Coated NDC 0597-0147-18
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE GILOTRIF is a kinase inhibitor indicated for: First-line treatment of patients with metastatic non-small cell lung cancer (NSCLC) whose tumors have non-resistant epidermal growth factor receptor (EGFR) mutations as detected by an FDA-approved test ( 1.1 ) Limitations of Use : Safety and efficacy of GILOTRIF were not established in patients whose tumors have resistant EGFR mutations ( 1.1 ) Treatment of patients with metastatic, squamous NSCLC progressing after platinum-based chemotherapy ( 1.2 )
1.1EGFR Mutation-Positive, Metastatic Non-Small Cell Lung Cancer GILOTRIF is indicated for the first-line treatment of patients with metastatic non-small cell lung cancer (NSCLC) whose tumors have non-resistant epidermal growth factor receptor (EGFR) mutations as detected by an FDA-approved test [see Dosage and Administration (2.1) , Clinical Pharmacology (12.1) , Clinical Studies (14.1) ]. Limitations of Use : The safety and efficacy of GILOTRIF have not been established in patients whose tumors have resistant EGFR mutations [see Clinical Studies (14.1) ].
1.2Previously Treated, Metastatic Squamous NSCLC GILOTRIF is indicated for the treatment of patients with metastatic squamous NSCLC progressing after platinum-based chemotherapy .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended dosage : 40 mg orally once daily ( 2.2 ) Renal impairment : 30 mg orally once daily in patients with severe renal impairment ( 2.4 , 8.6 , 12.3 ) Instruct patients to take GILOTRIF at least 1 hour before or 2 hours after a meal ( 2.2 )
2.1Patient Selection for Non-Resistant EGFR Mutation-Positive Metastatic NSCLC Select patients for first-line treatment of metastatic NSCLC with GILOTRIF based on the presence of non-resistant EGFR mutations in tumor specimens [see Clinical Pharmacology (12.1) , Clinical Studies (14.1) ]. Information on FDA-approved tests for the detection of EGFR mutations in NSCLC is available at: http://www.fda.gov/CompanionDiagnostics .
2.2Recommended Dosage The recommended dosage of GILOTRIF is 40 mg orally once daily until disease progression or no longer tolerated by the patient. Take GILOTRIF at least 1 hour before or 2 hours after a meal. Do not take a missed dose within 12 hours of the next dose.
2.3Dosage Modifications for Adverse Reactions Withhold GILOTRIF for: Grade* 3 or higher adverse reactions Diarrhea of Grade 2 persisting for 2 or more consecutive days while taking anti-diarrheal medication [see Warnings and Precautions (5.1) ] Cutaneous reactions of Grade 2 that are prolonged (lasting more than 7 days) or intolerable [see Warnings and Precautions (5.2) ] * National Cancer Institute Common Terminology Criteria for Adverse Events (NCI CTCAE), v
3.0Resume treatment when the adverse reaction fully resolves, returns to baseline, or improves to Grade 1. Reinstitute GILOTRIF at a reduced dose, i.e., 10 mg per day less than the dose at which the adverse reaction occurred. Permanently discontinue GILOTRIF for: Life-threatening bullous, blistering, or exfoliating skin lesions [see Warnings and Precautions (5.2) ] Confirmed interstitial lung disease (ILD) [see Warnings and Precautions (5.3) ] Severe drug-induced hepatic impairment [see Warnings and Precautions (5.4) ] Gastrointestinal perforation [see Warnings and Precautions (5.5) ] Persistent ulcerative keratitis [see Warnings and Precautions (5.6) ] Symptomatic left ventricular dysfunction [see Adverse Reactions (6.1) ] Severe or intolerable adverse reaction occurring at a dose of 20 mg per day
2.4Dosage Modification for Pre-Existing Severe Renal Impairment The recommended dosage of GILOTRIF in patients with pre-existing severe renal impairment (estimated glomerular filtration rate [eGFR*] 15 to 29 mL/min /1.73 m 2 ) is 30 mg orally once daily [see Use in Specific Populations (8.6) , Clinical Pharmacology (12.3) ] . * Use the Modification of Diet in Renal Disease [MDRD] formula to estimate eGFR.
2.5Dosage Modifications for Drug Interactions P-glycoprotein Inhibitors Reduce GILOTRIF daily dose by 10 mg if not tolerated for patients who require therapy with a P-glycoprotein (P-gp) inhibitor. Resume the previous dose after discontinuation of the P-gp inhibitor as tolerated [see Drug Interactions (7) , Clinical Pharmacology (12.3) ] . P-glycoprotein Inducers Increase GILOTRIF daily dose by 10 mg as tolerated for patients who require chronic therapy with a P-gp inducer.
Resume the previous dose 2 to 3 days after discontinuation of the P-gp inducer [see Drug Interactions (7) , Clinical Pharmacology (12.3) ].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS GILOTRIF is available as: 40 mg tablets: light blue, film-coated, round, biconvex, bevel-edged tablets debossed with "T40" on one side and the Boehringer Ingelheim company symbol on the other side. 30 mg tablets: dark blue, film-coated, round, biconvex, bevel-edged tablets debossed with "T30" on one side and the Boehringer Ingelheim company symbol on the other side. 20 mg tablets: white to slightly yellowish, film-coated, round, biconvex, bevel-edged tablets debossed with "T20" on one side and the Boehringer Ingelheim company symbol on the other side.
Tablets: 40 mg, 30 mg, and 20 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Diarrhea : Diarrhea may result in dehydration and renal failure. Withhold GILOTRIF for severe and prolonged diarrhea not responsive to anti-diarrheal agents. ( 2.3 , 5.1 ) Bullous and exfoliative skin disorders : Severe bullous, blistering, and exfoliating lesions occurred in 0.2% of patients.
Discontinue for life-threatening cutaneous reactions. Withhold GILOTRIF for severe and prolonged cutaneous reactions. ( 2.3 , 5.2 ) Interstitial lung disease (ILD) : Occurs in 1.6% of patients.
Withhold GILOTRIF for acute onset or worsening of pulmonary symptoms. Discontinue GILOTRIF if ILD is diagnosed. ( 2.3 , 5.3 ) Hepatic toxicity : Fatal hepatic impairment occurs in 0.2% of patients.
Monitor with periodic liver testing. Withhold or discontinue GILOTRIF for severe or worsening liver tests. ( 2.3 , 5.4 ) Gastrointestinal perforation : Occurs in 0.2% of patients.
Permanently discontinue GILOTRIF in patients who develop gastrointestinal perforation. ( 2.3 , 5.5 ) Keratitis : Occurs in 0.7% of patients. Withhold GILOTRIF for keratitis evaluation.
Withhold or discontinue GILOTRIF for confirmed ulcerative keratitis. ( 2.3 , 5.6 ) Embryo-fetal toxicity : Can cause fetal harm when administered to a pregnant woman. Advise pregnant women and females of reproductive potential of the potential risk to the fetus and to use effective contraception.
( 5.7 )
5.1Diarrhea Diarrhea has resulted in dehydration with or without renal impairment across the clinical experience; some cases were fatal. Grade 3-4 diarrhea occurred in 697 (16%) of the 4257 patients who received GILOTRIF across 44 clinical trials. In LUX-Lung 3, diarrhea occurred in 96% of patients treated with GILOTRIF (n=229), of which 15% were Grade 3 in severity and occurred within the first 6 weeks .
Renal impairment as a consequence of diarrhea occurred in 6% of patients treated with GILOTRIF, of which 1.3% were Grade 3. In LUX-Lung 8, diarrhea occurred in 75% of patients treated with GILOTRIF (n=392), of which 10% were Grade 3 in severity and 0.8% were Grade 4 in severity . Renal impairment as a consequence of diarrhea occurred in 7% of patients treated with GILOTRIF, of which 2% were Grade 3 [see Adverse Reactions (6.1) ].
For patients who develop prolonged Grade 2 diarrhea lasting more than 48 hours or greater than or equal to Grade 3 diarrhea, withhold GILOTRIF until diarrhea resolves to Grade 1 or less and resume GILOTRIF with appropriate dose reduction [see Dosage and Administration (2.3) ]. Provide patients with an anti-diarrheal agent (e.g., loperamide) for self-administration at the onset of diarrhea and instruct patients to continue anti-diarrheal therapy until loose bowel movements cease for 12 hours.
5.2Bullous and Exfoliative Skin Disorders Grade 3 cutaneous reactions characterized by bullous, blistering, and exfoliating skin lesions, occurred in 0.2% of the 4257 patients who received GILOTRIF across clinical trials . In LUX-Lung 3, the overall incidence of cutaneous reactions consisting of rash, erythema, and acneiform rash was 90%, and the incidence of Grade 3 cutaneous reactions was 16%. In addition, the incidence of Grade 1-3 palmar-plantar erythrodysesthesia syndrome was 7%.
In LUX-Lung 8, the overall incidence of cutaneous reactions consisting of rash, erythema, and acneiform rash was 70%, and the incidence of Grade 3 cutaneous reactions was 7%. In addition, the incidence of Grade 1-3 palmar-plantar erythrodysesthesia syndrome was 1.5% [see Adverse Reactions (6.1) ] . Discontinue GILOTRIF in patients who develop life-threatening bullous, blistering, or exfoliating skin lesions .
For patients who develop prolonged Grade 2 cutaneous adverse reactions lasting more than 7 days, intolerable Grade 2 cutaneous reactions, or Grade 3 cutaneous reactions, withhold GILOTRIF until the adverse reaction resolves to Grade 1 or less and resume GILOTRIF with appropriate dose reduction [see Dosage and Administration (2.3) ] . Postmarketing cases consistent wit… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Diarrhea [see Warnings and Precautions (5.1) ] Bullous and Exfoliative Skin Disorders [see Warnings and Precautions (5.2) ] Interstitial Lung Disease [see Warnings and Precautions (5.3) ] Hepatic Toxicity [see Warnings and Precautions (5.4) ] Gastrointestinal Perforation [see Warnings and Precautions (5.5) ] Keratitis [see Warnings and Precautions (5.6) ] Most common adverse reactions (≥20%) were diarrhea, rash/acneiform dermatitis, stomatitis, paronychia, dry skin, decreased appetite, nausea, vomiting, pruritus ( 6.1 ).
To report SUSPECTED ADVERSE REACTIONS, contact Boehringer Ingelheim Pharmaceuticals, Inc. at (800) 542-6257 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The data in the Warnings and Precautions section reflect exposure to GILOTRIF for clinically significant adverse reactions in 4257 patients enrolled in LUX-Lung 3 (n=229) and LUX-Lung 8 (n=392), and 3636 patients with cancer enrolled in 42 studies of GILOTRIF administered alone or in combination with other anti-neoplastic drugs at GILOTRIF doses ranging from 10-70 mg daily or at doses 10-160 mg in other regimens.
The mean exposure was 5.5 months. The population included patients with various cancers, the most common of which were NSCLC, breast, colorectal, brain, and head and neck. The data described below reflect exposure to GILOTRIF as a single agent in LUX-Lung 3, a randomized, active-controlled trial conducted in patients with EGFR mutation-positive, metastatic NSCLC, and in LUX-Lung 8, a randomized, active-controlled trial in patients with metastatic squamous NSCLC progressing after platinum-based chemotherapy.
EGFR Mutation-Positive Metastatic NSCLC The safety of GILOTRIF was evaluated in 229 EGFR-tyrosine kinase inhibitor-naïve patients with EGFR mutation-positive, metastatic non-squamous NSCLC enrolled in a randomized (2:1), multicenter, open-label trial (LUX-Lung 3). Patients received either GILOTRIF 40 mg daily until documented disease progression or intolerance to the therapy or pemetrexed 500 mg/m² followed after 30 minutes by cisplatin 75 mg/m² every three weeks for a maximum of six treatment courses. The median exposure was 11 months for patients treated with GILOTRIF and 3.4 months for patients treated with pemetrexed/cisplatin.
The overall trial population had a median age of 61 years; 61% of patients in the GILOTRIF arm and 60% of patients in the pemetrexed/cisplatin arm were younger than 65 years. A total of 64% of patients on GILOTRIF and 67% of pemetrexed/cisplatin patients were female. More than two-thirds of patients were from Asia (GILOTRIF 70%; pemetrexed/cisplatin 72%).
Serious adverse reactions were reported in 29% of patients treated with GILOTRIF. The most frequent serious adverse reactions reported in patients treated with GILOTRIF were diarrhea (6.6%); vomiting (4.8%); and dyspnea, fatigue, and hypokalemia (1.7% each). Fatal adverse reactions in GILOTRIF-treated patients in LUX-Lung 3 included pulmonary toxicity/ILD-like adverse reactions (1.3%), sepsis (0.43%), and pneumonia (0.43%).
Dose reductions due to adverse reactions were required in 57% of GILOTRIF-treated patients. The most frequent adverse reactions that led to dose reduction in the patients treated with GILOTRIF were diarrhea (20%), rash/acne (19%), paronychia (14%), and stomatitis (10%). Discontinuation of therapy in GILOTRIF-treated patients for adverse reactions was 14.0%.
The most frequent adverse reactions that led to discontinuation in GILOTRIF-treated patients were diarrhea (1.3%), ILD (0.9%), and paronychia (0.9%). Clinical trials of GILOTRIF excluded… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS P-glycoprotein (P-gp) Inhibitors : Co-administration of P-gp inhibitors can increase afatinib exposure. Reduce GILOTRIF by 10 mg per day if not tolerated. ( 2.5 , 7 ) P-gp Inducers : Co-administration of chronic P-gp inducers orally can decrease afatinib exposure.
Increase GILOTRIF by 10 mg per day as tolerated. ( 2.5 , 7 ) Effect of P-glycoprotein (P-gp) Inhibitors and Inducers Concomitant taking of P-gp inhibitors (including but not limited to ritonavir, cyclosporine A, ketoconazole, itraconazole, erythromycin, verapamil, quinidine, tacrolimus, nelfinavir, saquinavir, and amiodarone) with GILOTRIF can increase exposure to afatinib [see Clinical Pharmacology (12.3) ]. Reduce GILOTRIF daily dose as recommended [see Dosage and Administration (2.5) ].
Concomitant taking of P-gp inducers (including but not limited to rifampicin, carbamazepine, phenytoin, phenobarbital, and St. John's wort) with GILOTRIF can decrease exposure to afatinib [see Clinical Pharmacology (12.3) ]. Increase GILOTRIF daily dose as recommended [see Dosage and Administration (2.5) ].
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation : Advise women not to breastfeed ( 8.2 )
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action [see Clinical Pharmacology (12.1) ] , GILOTRIF can cause fetal harm when administered to a pregnant woman. There are no available data on the use of GILOTRIF in pregnant women. Administration of afatinib to pregnant rabbits during organogenesis at exposures approximately 0.2 times the exposure in humans at the recommended dose of 40 mg daily resulted in embryotoxicity and, in rabbits showing maternal toxicity, increased abortions at late gestational stages (see Data ) .
Advise a pregnant woman of the potential risk to a fetus . The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data In an embryo-fetal development study in rabbits, administration of afatinib to pregnant animals at doses of 5 mg/kg (approximately 0.2 times the exposure by AUC at the recommended human dose of 40 mg daily) or greater during the period of organogenesis caused increased post-implantation loss, and in animals showing maternal toxicity, abortion at late gestational stages. In the same study, at the high dose level of 10 mg/kg (approximately 0.7 times the exposure by AUC at the recommended human dose of 40 mg daily), there were reduced fetal weights, and increases in the incidence of runts, as well as visceral and dermal variations.
In an embryo-fetal development study in rats, there were skeletal alterations consisting of incomplete or delayed ossifications and reduced fetal weight at a dose of 16 mg/kg (approximately twice the exposure based on AUC at the recommended human dose of 40 mg daily).
8.2Lactation Risk Summary There are no data on the presence of afatinib in human milk or its effects on the breastfed infant or on milk production. Afatinib was present in the milk of lactating rats (see Data ) . Because of the potential for serious adverse reactions in breastfed infants from GILOTRIF, advise women not to breastfeed during treatment with GILOTRIF and for 2 weeks after the final dose.
Data Afatinib was present in the milk of lactating rats at concentrations 80 and 150 times higher than those found in plasma at 1 and 6 hours after administration.
8.3Females and Males of Reproductive Potential Contraception Females GILOTRIF can cause fetal harm when administered to a pregnant woman. Advise females of reproductive potential to use effective contraception during treatment with GILOTRIF and for at least 2 weeks after the last dose of GILOTRIF [see Use in Specific Populations (8.1) , Clinical Pharmacology (12.3) ]. Infertility Based on results from an animal fertility study, GILOTRIF may reduce fertility in females and males of reproductive potential.
It is not known if the effects on fertility are reversible [see Nonclinical Toxicology (13.1) ].
8.4Pediatric Use Safety and effectiveness of GILOTRIF in pediatric patients have not been established. The safety and efficacy of afatinib were assessed, but not established, in a single-arm, open-label, multicenter trial [NCT02372006] which included 37 pediatric patients 2 to <17 years of age with recurrent/refractory solid tumors with known ErbB pathway deregulation who received 80% of the adult dose per body surface area. No new safety signals were observed in pediatric patients in this trial.
In these 37 patients, the pharmacokinetic parameters were within range of values in adults.
8.5Geriatric Use LUX-Lung 3 did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In LUX-Lung 8, 53% of the 398 patients randomized to receive afatinib were 65 years of age or older and 11% were 75 years or older. In an exploratory subgr… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action [see Clinical Pharmacology (12.1) ] , GILOTRIF can cause fetal harm when administered to a pregnant woman. There are no available data on the use of GILOTRIF in pregnant women. Administration of afatinib to pregnant rabbits during organogenesis at exposures approximately 0.2 times the exposure in humans at the recommended dose of 40 mg daily resulted in embryotoxicity and, in rabbits showing maternal toxicity, increased abortions at late gestational stages (see Data ) .
Advise a pregnant woman of the potential risk to a fetus . The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data In an embryo-fetal development study in rabbits, administration of afatinib to pregnant animals at doses of 5 mg/kg (approximately 0.2 times the exposure by AUC at the recommended human dose of 40 mg daily) or greater during the period of organogenesis caused increased post-implantation loss, and in animals showing maternal toxicity, abortion at late gestational stages. In the same study, at the high dose level of 10 mg/kg (approximately 0.7 times the exposure by AUC at the recommended human dose of 40 mg daily), there were reduced fetal weights, and increases in the incidence of runts, as well as visceral and dermal variations.
In an embryo-fetal development study in rats, there were skeletal alterations consisting of incomplete or delayed ossifications and reduced fetal weight at a dose of 16 mg/kg (approximately twice the exposure based on AUC at the recommended human dose of 40 mg daily).
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of GILOTRIF in pediatric patients have not been established. The safety and efficacy of afatinib were assessed, but not established, in a single-arm, open-label, multicenter trial [NCT02372006] which included 37 pediatric patients 2 to <17 years of age with recurrent/refractory solid tumors with known ErbB pathway deregulation who received 80% of the adult dose per body surface area. No new safety signals were observed in pediatric patients in this trial.
In these 37 patients, the pharmacokinetic parameters were within range of values in adults.
🧓 Geriatric Use ▾
8.5Geriatric Use LUX-Lung 3 did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In LUX-Lung 8, 53% of the 398 patients randomized to receive afatinib were 65 years of age or older and 11% were 75 years or older. In an exploratory subgroup analysis of LUX-Lung 8, the hazard ratio for overall survival (OS) in patients less than 65 years old was 0.68 (95% CI: 0.55, 0.85) and in patients 65 years or older was 0.95 (95% CI: 0.76, 1.19).
No overall differences in safety were observed between patients 65 years and older and younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE Overdose was reported in 2 healthy adolescents each of whom ingested 360 mg of GILOTRIF (as part of a mixed-drug ingestion) resulting in nausea, vomiting, asthenia, dizziness, headache, abdominal pain, and elevated amylase [<1.5 times upper limit of normal (ULN)]. Both subjects recovered.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Afatinib covalently binds to the kinase domains of EGFR (ErbB1), HER2 (ErbB2), and HER4 (ErbB4) and irreversibly inhibits tyrosine kinase autophosphorylation, resulting in downregulation of ErbB signaling. Certain mutations in EGFR, including non-resistant mutations in its kinase domain, can result in increased autophosphorylation of the receptor, leading to receptor activation, sometimes in the absence of ligand binding, and can support cell proliferation in NSCLC. Non-resistant mutations are defined as those occurring in exons constituting the kinase domain of EGFR that lead to increased receptor activation and where efficacy is predicted by 1) clinically meaningful tumor shrinkage with the recommended dose of afatinib and/or 2) inhibition of cellular proliferation or EGFR tyrosine kinase phosphorylation at concentrations of afatinib sustainable at the recommended dosage according to validated methods.
The most commonly found of these mutations are exon 21 L858R substitutions and exon 19 deletions. Afatinib demonstrated inhibition of autophosphorylation and/or in vitro proliferation of cell lines expressing wild-type EGFR and in those expressing selected EGFR exon 19 deletion mutations, exon 21 L858R mutations, or other less common non-resistant mutations, at afatinib concentrations achieved in patients. In addition, afatinib inhibited in vitro proliferation of cell lines overexpressing HER2.
Treatment with afatinib resulted in inhibition of tumor growth in nude mice implanted with tumors either overexpressing wild type EGFR or HER2 or in an EGFR L858R/T790M double mutant model.
12.2Pharmacodynamics Cardiac Electrophysiology The effect of multiple doses of GILOTRIF (50 mg once daily) on the QTc interval was evaluated in an open-label, single-arm study in patients with relapsed or refractory solid tumors. No large changes in the mean QTc interval (i.e., >20 ms) were detected in the study.
12.3Pharmacokinetics Absorption Following oral administration of GILOTRIF tablets, time to peak afatinib plasma concentrations (T max ) is 2 to 5 hours. Maximum concentration (C max ) and area under the concentration-time curve from time zero to infinity (AUC 0-INF ) values increased slightly more than dose proportional in the range of 20 to 50 mg. The geometric mean relative bioavailability of 20 mg GILOTRIF tablets was 92% as compared to an oral solution.
Steady-state plasma concentrations are achieved within 8 days of repeat dosing of GILOTRIF resulting in an accumulation of 2.8-fold for AUC and 2.1-fold for C max . Effect of Food A high-fat meal decreased C max by 50% and AUC 0-INF by 39% relative to the fasted condition [see Dosage and Administration (2.2) ] . Distribution In vitro binding of afatinib to human plasma proteins is approximately 95%.
Elimination The elimination half-life of afatinib is 37 hours after repeat dosing in cancer patients. Metabolism Covalent adducts to proteins are the major circulating metabolites of afatinib and enzymatic metabolism of afatinib is minimal. The metabolites formed by CYP450-dependent reactions were approximately 9% of the total metabolic turnover in sandwich-cultured human hepatocytes.
Approximately 2% of the afatinib dose was metabolized by FMO3; the CYP3A4-dependent N-demethylation was not detected. Excretion In humans, excretion of afatinib is primarily via the feces (85%) with 4% recovered in the urine following a single oral dose of [ 14 C]-labeled afatinib solution. The parent compound accounted for 88% of the recovered dose.
Specific Populations Based on the population pharmacokinetic analysis, weight, gender, age, and race do not have a clinically important effect on exposure of afatinib. Patients with Renal Impairment A pharmacokinetic study was conducted in 14 subjects with normal (eGFR ≥90 mL/min/1.73 m 2 ) renal function, 8 subjects with moderate (eGFR 30 to 59 mL/min/1.73 m 2 ) and 8 subjects with severe (eGFR 15 to 29 mL/min/1.73… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Afatinib covalently binds to the kinase domains of EGFR (ErbB1), HER2 (ErbB2), and HER4 (ErbB4) and irreversibly inhibits tyrosine kinase autophosphorylation, resulting in downregulation of ErbB signaling. Certain mutations in EGFR, including non-resistant mutations in its kinase domain, can result in increased autophosphorylation of the receptor, leading to receptor activation, sometimes in the absence of ligand binding, and can support cell proliferation in NSCLC. Non-resistant mutations are defined as those occurring in exons constituting the kinase domain of EGFR that lead to increased receptor activation and where efficacy is predicted by 1) clinically meaningful tumor shrinkage with the recommended dose of afatinib and/or 2) inhibition of cellular proliferation or EGFR tyrosine kinase phosphorylation at concentrations of afatinib sustainable at the recommended dosage according to validated methods.
The most commonly found of these mutations are exon 21 L858R substitutions and exon 19 deletions. Afatinib demonstrated inhibition of autophosphorylation and/or in vitro proliferation of cell lines expressing wild-type EGFR and in those expressing selected EGFR exon 19 deletion mutations, exon 21 L858R mutations, or other less common non-resistant mutations, at afatinib concentrations achieved in patients. In addition, afatinib inhibited in vitro proliferation of cell lines overexpressing HER2.
Treatment with afatinib resulted in inhibition of tumor growth in nude mice implanted with tumors either overexpressing wild type EGFR or HER2 or in an EGFR L858R/T790M double mutant model.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING GILOTRIF tablets are available as follows: 40 mg: light blue, film-coated, round, biconvex, bevel-edged tablets debossed with "T40" on one side and the Boehringer Ingelheim company symbol on the other side. Unit of use bottles of 30 NDC: 0597-0138-30 30 mg: dark blue, film-coated, round, biconvex, bevel-edged tablets debossed with "T30" on one side and the Boehringer Ingelheim company symbol on the other side. Unit of use bottles of 30 NDC: 0597-0137-30 20 mg: white to slightly yellowish, film-coated, round, biconvex, bevel-edged tablets debossed with "T20" on one side and the Boehringer Ingelheim company symbol on the other side.
Unit of use bottles of 30 NDC: 0597-0141-30 Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Dispense medication in the original container to protect from exposure to high humidity and light.
📦 Storage and Handling ▾
Storage Store at 20°C to 25°C (68°F to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Dispense medication in the original container to protect from exposure to high humidity and light.
📋 Description ▾
11 DESCRIPTION GILOTRIF tablets contain afatinib, a tyrosine kinase inhibitor which is a 4-anilinoquinazoline. Afatinib is presented as the dimaleate salt, with the chemical name 2-butenamide, N -[4-[(3-chloro-4-fluorophenyl)amino]-7-[[(3 S )-tetrahydro-3-furanyl]oxy]-6-quinazolinyl]-4-(dimethylamino)-,(2 E )-, (2 Z )-2-butenedioate (1:2). Its structural formula is: Afatinib dimaleate is a white to brownish yellow powder, water soluble and hygroscopic, with an empirical formula of C 32 H 33 ClFN 5 O 11 , and a molecular weight of 718.1 g/mol.
GILOTRIF tablets for oral administration are available in 40 mg, 30 mg, or 20 mg of afatinib (equivalent to 59.12 mg, 44.34 mg, or 29.56 mg afatinib dimaleate, respectively). The inactive ingredients of GILOTRIF are the following: Tablet Core: lactose monohydrate, microcrystalline cellulose, crospovidone, colloidal silicon dioxide, magnesium stearate and Coating: hypromellose, polyethylene glycol, titanium dioxide, talc, polysorbate 80, FD&C Blue No. 2 (40 mg and 30 mg tablets only).
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Diarrhea Advise patients that diarrhea occurs in nearly all patients who receive GILOTRIF. Inform patients that diarrhea may result in dehydration and renal impairment if not treated.
Advise patients to notify their physician if diarrhea develops and to seek medical attention promptly for severe or persistent diarrhea [see Warnings and Precautions (5.1) and Adverse Reactions (6.1) ]. Bullous and Exfoliative Skin Disorders Advise patients to minimize sun exposure with protective clothing and use of sunscreen while taking GILOTRIF [see Warnings and Precautions (5.2) ]. Interstitial Lung Disease Advise patients to immediately report any new or worsening lung symptoms, or any combination of the following symptoms: trouble breathing or shortness of breath, cough, fever [see Warnings and Precautions (5.3) ].
Hepatic Toxicity Advise patients that they will need to undergo liver function monitoring periodically. Advise patients to immediately report any symptoms of a liver problem [e.g., skin or the whites of eyes turn yellow, urine turns dark or brown (tea colored), pain on the right side of stomach, bleeds or bruises more easily than normal, lethargy] [see Warnings and Precautions (5.4) ]. Gastrointestinal Perforation Advise patients that GILOTRIF can increase the risk of gastrointestinal perforation and to seek immediate medical attention for severe abdominal pain [see Warnings and Precautions (5.5) ] .
Keratitis Advise patients to immediately report eye problems (e.g., eye pain, swelling, redness, blurred vision, or other vision changes) [see Warnings and Precautions (5.6) ]. Left Ventricular Dysfunction Advise patients to contact a healthcare professional immediately for any of the following: new onset or worsening shortness of breath or exercise intolerance, cough, fatigue, swelling of the ankles/legs, palpitations, or sudden weight gain [see Dosage and Administration (2.3) and Adverse Reactions (6.1) ]. Instructions for Taking GILOTRIF Advise patients to take GILOTRIF on an empty stomach at least 1 hour before or 2 hours after eating [see Dosage and Administration (2.2) ].
Advise patients not to take a missed dose within 12 hours of the next dose. Embryo-Fetal Toxicity Advise pregnant women and females of reproductive potential that GILOTRIF can result in fetal harm. Advise female patients to contact their healthcare provider with a known or suspected pregnancy .
Advise females of reproductive potential to use effective contraception during treatment with GILOTRIF and for at least 2 weeks after the last dose of GILOTRIF [see Use in Specific Populations (8.1 , 8.3) ]. Lactation Advise women not to breastfeed during treatment with GILOTRIF and for 2 weeks after the last dose of GILOTRIF [see Use in Specific Populations (8.2) ]. Infertility Advise females and males of reproductive potential of the potential for reduced fertility from GILOTRIF [see Use in Specific Populations (8.3) ] .
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Following oral administration of GILOTRIF tablets, time to peak afatinib plasma concentrations (T max ) is 2 to 5 hours. Maximum concentration (C max ) and area under the concentration-time curve from time zero to infinity (AUC 0-INF ) values increased slightly more than dose proportional in the range of 20 to 50 mg. The geometric mean relative bioavailability of 20 mg GILOTRIF tablets was 92% as compared to an oral solution.
Steady-state plasma concentrations are achieved within 8 days of repeat dosing of GILOTRIF resulting in an accumulation of 2.8-fold for AUC and 2.1-fold for C max . Effect of Food A high-fat meal decreased C max by 50% and AUC 0-INF by 39% relative to the fasted condition [see Dosage and Administration (2.2) ] . Distribution In vitro binding of afatinib to human plasma proteins is approximately 95%.
Elimination The elimination half-life of afatinib is 37 hours after repeat dosing in cancer patients. Metabolism Covalent adducts to proteins are the major circulating metabolites of afatinib and enzymatic metabolism of afatinib is minimal. The metabolites formed by CYP450-dependent reactions were approximately 9% of the total metabolic turnover in sandwich-cultured human hepatocytes.
Approximately 2% of the afatinib dose was metabolized by FMO3; the CYP3A4-dependent N-demethylation was not detected. Excretion In humans, excretion of afatinib is primarily via the feces (85%) with 4% recovered in the urine following a single oral dose of [ 14 C]-labeled afatinib solution. The parent compound accounted for 88% of the recovered dose.
Specific Populations Based on the population pharmacokinetic analysis, weight, gender, age, and race do not have a clinically important effect on exposure of afatinib. Patients with Renal Impairment A pharmacokinetic study was conducted in 14 subjects with normal (eGFR ≥90 mL/min/1.73 m 2 ) renal function, 8 subjects with moderate (eGFR 30 to 59 mL/min/1.73 m 2 ) and 8 subjects with severe (eGFR 15 to 29 mL/min/1.73 m 2 ) renal impairment. All subjects received a single 40 mg oral dose of GILOTRIF.
The geometric mean AUC INF for afatinib was 50% higher in subjects with severe renal impairment and was 22% higher in subjects with moderate renal impairment as compared to subjects with normal renal function. Geometric mean C max was 22% higher in subjects with severe renal impairment and was comparable in subjects with moderate renal impairment to subjects with normal renal function [see Dosage and Administration (2.4) , Use in Specific Populations (8.6) ] . GILOTRIF has not been studied in patients with eGFR <15 mL/min/1.73 m 2 or on dialysis.
Patients with Hepatic Impairment Mild (Child Pugh A) or moderate (Child Pugh B) hepatic impairment had no influence on the afatinib exposure following a single dose of GILOTRIF. Subjects with severe (Child Pugh C) hepatic impairment have not been studied [see Use in Specific Populations (8.7) ] . Drug Interactions Studies Clincial Studies Effect of P-gp Inhibitors and Inducers on Afatinib: The effect of ritonavir dosing time relative to a single oral dose of GILOTRIF was evaluated in healthy subjects taking 40 mg of GILOTRIF alone as compared to those after ritonavir (200 mg twice daily for 3 days) co-administration at 6 hours after GILOTRIF administration.
The relative bioavailability for AUC 0-INF and C max of afatinib was 119% and 104% when co-administered with ritonavir, and 111% and 105% when ritonavir was administered 6 hours after taking GILOTRIF. In another study, when ritonavir (200 mg twice daily for 3 days) was administered 1 hour before a 20 mg single dose of GILOTRIF, exposure to afatinib increased by 48% for AUC 0-INF and 39% for C max [see Drug Interactions (7) ]. Pre-treatment with a potent inducer of P-gp, rifampicin (600 mg once daily for 7 days) decreased the plasma exposure to afatinib by 34% (AUC 0-INF ) and 22% (C max ) [see Drug Interactions (7) ] .
In Vitro Studies Effect of Afatinib on P-gp… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Cardiac Electrophysiology The effect of multiple doses of GILOTRIF (50 mg once daily) on the QTc interval was evaluated in an open-label, single-arm study in patients with relapsed or refractory solid tumors. No large changes in the mean QTc interval (i.e., >20 ms) were detected in the study.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1EGFR Mutation-Positive, Metastatic NSCLC The efficacy of GILOTRIF for the first-line treatment of patients with EGFR mutation-positive, metastatic [Stage IV and Stage IIIb with pleural and/or pericardial effusion as classified by the American Joint Commission on Cancer (AJCC, 6th edition)] NSCLC was established in a randomized, multicenter, open-label trial (LUX-Lung 3 [NCT00949650]). Patients were randomized (2:1) to receive GILOTRIF 40 mg orally once daily (n=230) or intravenous pemetrexed (500 mg/m 2 ) plus cisplatin (75 mg/m 2 ) once every 21 days for up to 6 cycles (n=115).
Randomization was stratified according to EGFR mutation category (exon 19 deletion vs exon 21 L858R vs other) and race (Asian vs non-Asian). The major efficacy outcome was progression-free survival (PFS) as assessed by an independent review committee (IRC). Other efficacy outcomes included overall response rate (ORR) and OS.
EGFR mutation status was prospectively determined for screening and enrollment of patients by a clinical trial assay (CTA). Tumor samples from 264 patients (178 randomized to GILOTRIF and 86 patients randomized to chemotherapy) were tested retrospectively by the companion diagnostic therascreen ® EGFR RGQ PCR Kit, which is FDA-approved for selection of patients for GILOTRIF treatment. Among the patients randomized, 65% were female, median age was 61 years, baseline ECOG performance status (PS) was 0 (39%) or 1 (61%), 26% were White and 72% were Asian.
The majority of the patients had a tumor sample with an EGFR mutation categorized by the CTA as either exon 19 deletion (49%) or exon 21 L858R substitution (40%), while the remaining 11% had other mutations. A statistically significant improvement in PFS as determined by the IRC was demonstrated for patients randomized to GILOTRIF compared with those randomized to chemotherapy. See Table 5 and Figure 1 .
There was no statistically significant difference for OS between the treatment arms at the final pre-planned analysis. Table 5 Efficacy Results in LUX-Lung 3 GILOTRIF (N=230) Pemetrexed/Cisplatin (N=115) *Stratified by EGFR mutation status and race. HR=hazard ratio; CR=complete response; PR=partial response Progression-Free Survival by IRC Number of Deaths or Progressions, N (%) 152 (66.1%) 69 (60.0%) Median Progression-Free Survival (months) 11.1 6.9 95% CI (9.6, 13.6) (5.4, 8.2) HR (95% CI) 0.58 (0.43, 0.78) Stratified Log-Rank Test p-value* <0.001 Overall Survival Number of Deaths, N (%) 140 (60.9%) 73 (63.5%) Median Overall Survival (months) 28.2 28.2 95% CI (24.6, 33.6) (20.7, 33.2) HR (95% CI) 0.88 (0.66, 1.17) Stratified Log-Rank Test p-value*
0.39Overall Response Rate (CR + PR) by IRC N (%) 116 (50.4%) 22 (19.1%) Response Duration Median (months) 12.5
6.7Figure 1 Kaplan-Meier Curve for PFS by Independent Review by Treatment Group in LUX-Lung 3 Pre-specified exploratory subgroup analyses were conducted according to the stratification factor of EGFR mutation category. See Figure 2 and text below Figure 2. Figure 2 Forest Plots of PFS and OS by EGFR Mutation Subgroups in LUX-Lung 3 Overall Response Rate in Other EGFR Mutations The efficacy of GILOTRIF in patients with NSCLC harboring non-resistant EGFR mutations (S768I, L861Q, and G719X) other than exon 19 deletions or exon 21 L858R substitutions was evaluated in a pooled analysis of such patients enrolled in one of three clinical trials (LUX-Lung 2 [NCT00525148], LUX-Lung 3 [NCT00949650], and LUX-Lung 6 [NCT01121393]).
LUX-Lung 2 was a single arm, multicenter study of afatinib 40 or 50 mg orally once daily until disease progression or intolerable side effects. EGFR status was determined by bi-directional Sanger sequencing of tumor tissue. LUX-Lung 3 was a randomized, multicenter study comparing treatment with afatinib 40 mg orally once daily to intravenous cisplatin 75 mg/m 2 plus pemetrexed 500 mg/m 2 every 21 days for up to 6 cycles.
EGFR status was determined by the therascreen ® EGFR RGQ PCR Kit. L… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies have not been conducted with afatinib. A marginal response to afatinib was observed in a single tester strain of a bacterial (Ames) mutagenicity assay. No mutagenic or genotoxic potential was identified in an in vitro chromosomal aberration test at non-cytotoxic concentrations as well as in the in vivo bone marrow micronucleus assay, the in vivo Comet assay, and an in vivo 4-week oral mutation study in the Muta ™ Mouse.
In a dedicated fertility study, male and female rats received afatinib daily by oral administration at doses of 4, 6, or 8 mg/kg. In males at doses of 6 mg/kg (approximately equal to the exposure by AUC in patients at the recommended human dose of 40 mg daily) or greater, there was an increase in the incidence of low or no sperm count, though overall fertility was not affected; decreases in sperm count were supported by findings of increased apoptosis in the testes and atrophy in the seminal vesicles and the prostate in general toxicology studies.
In females at the high dose of 8 mg/kg (approximately 0.63 times the exposure by AUC in patients at the recommended human dose of 40 mg daily), there was a mild decrease in the number of corpora lutea along with a mild increase in post-implantation loss due to early resorptions. In a 4-week general toxicology study, female rats had decreases in ovarian weights at all dose levels; organ weight had not fully recovered by the end of a 2-week recovery period.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies have not been conducted with afatinib. A marginal response to afatinib was observed in a single tester strain of a bacterial (Ames) mutagenicity assay. No mutagenic or genotoxic potential was identified in an in vitro chromosomal aberration test at non-cytotoxic concentrations as well as in the in vivo bone marrow micronucleus assay, the in vivo Comet assay, and an in vivo 4-week oral mutation study in the Muta ™ Mouse.
In a dedicated fertility study, male and female rats received afatinib daily by oral administration at doses of 4, 6, or 8 mg/kg. In males at doses of 6 mg/kg (approximately equal to the exposure by AUC in patients at the recommended human dose of 40 mg daily) or greater, there was an increase in the incidence of low or no sperm count, though overall fertility was not affected; decreases in sperm count were supported by findings of increased apoptosis in the testes and atrophy in the seminal vesicles and the prostate in general toxicology studies.
In females at the high dose of 8 mg/kg (approximately 0.63 times the exposure by AUC in patients at the recommended human dose of 40 mg daily), there was a mild decrease in the number of corpora lutea along with a mild increase in post-implantation loss due to early resorptions. In a 4-week general toxicology study, female rats had decreases in ovarian weights at all dose levels; organ weight had not fully recovered by the end of a 2-week recovery period.
📄 Patient Package Insert ▾
Patient Information GILOTRIF ® (JEE-loh-trif) (afatinib tablets) This Patient Information has been approved by the U.S. Food and Drug Administration. Revised: April 2022 What is GILOTRIF?
GILOTRIF is a prescription medicine that is used to treat people with non-small cell lung cancer (NSCLC) that: has certain (non-resistant) abnormal epidermal growth factor receptor (EGFR) gene(s). Your healthcare provider will perform a test to make sure that GILOTRIF is right for you. has spread to other parts of the body (metastatic), and has not been previously treated for metastatic lung cancer It is not known if GILOTRIF is safe and effective in treating people with lung cancer that has resistant abnormal EGFR genes. or is used to treat people with squamous cell lung cancer that: has spread to other parts of the body, and has been previously treated with chemotherapy that contains platinum.
It is not known if GILOTRIF is safe and effective in children. Before you take GILOTRIF, tell your healthcare provider about all of your medical conditions, including if you: have kidney or liver problems have lung or breathing problems other than lung cancer have a history of an ulcer, a tear (perforation) in your stomach or intestine, or diverticular disease (inflammation) in parts of your large intestine. See " What are the possible side effects of GILOTRIF? " have a history of severe dry eye or any other eye problems.
Tell your healthcare provider if you wear contact lenses. have heart problems are pregnant or plan to become pregnant. GILOTRIF can harm your unborn baby. Females who are able to become pregnant should use effective birth control during treatment with GILOTRIF and for at least 2 weeks after your last dose of GILOTRIF.
Talk to your healthcare provider about birth control methods that may be right for you. Tell your healthcare provider right away if you become pregnant or think you are pregnant during treatment with GILOTRIF. are breastfeeding or plan to breastfeed. It is not known if GILOTRIF passes into your breast milk.
Do not breastfeed during treatment with GILOTRIF and for 2 weeks after your last dose of GILOTRIF. Talk to your healthcare provider about the best way to feed your baby if you take GILOTRIF. Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements.
GILOTRIF may affect the way other medicines work, and other medicines may affect the way GILOTRIF works. Taking certain medicines with GILOTRIF may increase your risk of developing a tear (perforation) in your stomach or intestine. See " What are the possible side effects of GILOTRIF? " Know the medicines you take.
Keep a list of them to show your healthcare provider or pharmacist when you get a new medicine. How should I take GILOTRIF? Take GILOTRIF exactly as your healthcare provider tells you to take it.
Your healthcare provider will tell you how many GILOTRIF tablets to take and when to take them. Do not change your dose or stop GILOTRIF unless your healthcare provider tells you to. Take GILOTRIF on an empty stomach at least 1 hour before a meal or 2 hours after a meal.
If you miss a dose of GILOTRIF, take it as soon as you remember. If it is within 12 hours of your next dose, skip the dose and just take your next dose at your regular time. Do not take 2 doses of GILOTRIF at the same time.
If you take too much GILOTRIF, call your healthcare provider or go to the nearest hospital emergency room right away. What should I avoid while taking GILOTRIF? Limit your time in the sun.
GILOTRIF can make your skin sensitive to sunlight. You could get or have worsening rash or acne. You could get a severe sunburn.
Use sunscreen and wear a hat and clothes that cover your skin if you have to be in sunlight during treatment with GILOTRIF. What are the possible side effects of GILOTRIF? GILOTRIF may cause serious side effects, including: diarrhea.
Diarrhea is common with GILOTRIF and may some… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 20 mg Tablet Bottle Carton NDC 0597-0141-30 GILOTRIF ® (afatinib tablets) 20 mg* Attention: Dispense and Store Medication in the Original Container to Protect from Light and Humidity. Recommended Dosage: See Prescribing Information. 30 tablets Boehringer Ingelheim Rx only PRINCIPAL DISPLAY PANEL - 20 mg Tablet Bottle Carton
PRINCIPAL DISPLAY PANEL - 30 mg Tablet Bottle Carton NDC 0597-0137-30 GILOTRIF ® (afatinib tablets) 30 mg* Attention: Dispense and Store Medication in the Original Container to Protect from Light and Humidity. Recommended Dosage: See Prescribing Information. 30 tablets Boehringer Ingelheim Rx only PRINCIPAL DISPLAY PANEL - 30 mg Tablet Bottle Carton
PRINCIPAL DISPLAY PANEL - 40 mg Tablet Bottle Carton NDC 0597-0138-30 GILOTRIF ® (afatinib tablets) 40 mg* Attention: Dispense and Store Medication in the Original Container to Protect from Light and Humidity. Recommended Dosage: See Prescribing Information. 30 tablets Boehringer Ingelheim Rx only PRINCIPAL DISPLAY PANEL - 40 mg Tablet Bottle Carton
Medicaid utilization & spend
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |