
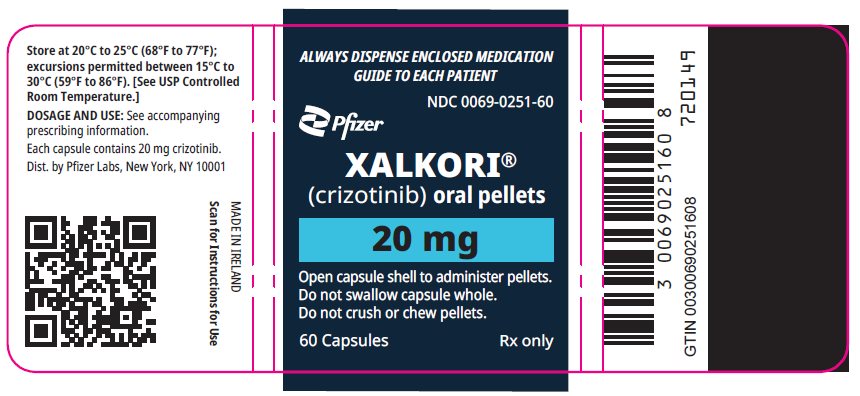
Xalkori CRIZOTINIB 20 mg Capsule, Coated Pellets, 60-count — NDC 0069-0251-60 (Billing 00069-0251-60)
This is a package of 60 capsules of Xalkori CRIZOTINIB 20 mg Capsule, Coated Pellets from Pfizer Laboratories Div Pfizer Inc, marketed since Nov 2023 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 0069-0251-60 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0069 labeler · 0251 product · 60 package
- Package marketed since
- Nov 20, 2023
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 60 EA per package
- Barcode (UPC)
- 0300698140201, 0300690507606, 0300690251608, 0300691500606 +1 more
- FDA record last changed
- Oct 1, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 085522
- GCN: 55027
- GPI-14 (Medi-Span): 21530517006820
- HICL (First Databank): 037916
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 1148498
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Kinase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Crizotinib is used to treat certain types of non-small cell lung cancer (NSCLC) that has spread to nearby tissues or to other parts of the body. It is also used to treat a certain type of anaplastic large cell lymphoma (ALCL) that has returned or is unresponsive to other treatment(s) in certain adults and children 1 year of age and older. Crizotinib is also used to treat a certain type of inflammatory myofibroblastic tumor (IMT; type of cancer that occurs in mucosal tissues usually in the abdominal area, involving the lungs, bladder, stomach, uterus, liver, or intestines) that cannot be treate...
Read the full MedlinePlus article ↗- It treats certain cancers driven by ALK or ROS1 gene changes. These are metastatic non-small cell lung cancer in adults, ALK-positive ALCL in children and young adults, and ALK-pos...
- Swallow Xalkori capsules whole, twice a day, with or without food. Don't chew, crush or split them. If you miss a dose, take it unless the next one is due within 6 hours. If you vo...
- Vision changes, nausea, vomiting, diarrhea, constipation, swelling and tiredness are common. Many people also notice less appetite, dizziness or tingling. Tell your care team if th...
- Call for yellow skin or eyes, dark urine, new cough or trouble breathing, fainting, a very slow heartbeat, or any new vision change or vision loss. These can signal liver, lung, he...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Crizotinib — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $40.18 | $2,410.74 / 60 capsules |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 6, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00069-0251-60 You're viewing this Main listing | 60 CAPSULE, COATED PELLETS in 1 BOTTLE | 2023-11-20 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Xalkori 20 mgthis 00069-0251-60 | Pfizer | 60 capsules | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 7825137 ↗ | Method of use | U-3057 | May 12, 2027 |
| US 7825137 ↗ | Method of use | U-3403 | May 12, 2027 |
| US 7825137 ↗ | Method of use | U-3058 | May 12, 2027 |
| US 7825137 ↗ | Method of use | U-3057 | May 12, 2027 |
| US 7825137 ↗ | Method of use | U-3058 | May 12, 2027 |
| US 7825137 ↗ | Method of use | U-3403 | May 12, 2027 |
| US 7825137 ↗ | Method of use | U-3403 | May 12, 2027 |
| US 7825137 ↗ | Method of use | U-3057 | May 12, 2027 |
| US 7825137 ↗ | Method of use | U-3058 | May 12, 2027 |
| US 7858643 ↗ | Drug substance | — | Oct 8, 2029 |
| US 7858643 ↗ | Drug substance | — | Oct 8, 2029 |
| US 7858643 ↗ | Drug substance | — | Oct 8, 2029 |
| US 8217057 ↗ | Drug substance | — | Nov 6, 2029 |
| US 8217057 ↗ | Drug substance | — | Nov 6, 2029 |
| US 8217057 ↗ | Drug substance | — | Nov 6, 2029 |
Is there a generic version of XALKORI 20 MG PELLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Crizotinib inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 230OU9XXE4
A waxy substance made from glycerin and stearic acid that acts as an emulsifier to blend oily and watery ingredients together. It also helps thicken and stabilize the medicine's texture.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII C9H2L21V7U
A fat derived from coconut or palm oil containing shorter fatty acid chains. It serves as a solvent and carrier to help dissolve or suspend active ingredients, improving absorption and stability in liquid formulations.
-
UNII TUF2IVW3M2
Poloxamer 407 is a synthetic polymer made from ethylene oxide and propylene oxide. In medicines, it acts as a thickener, emulsifier, and solubilizer to help mix ingredients and create the right texture.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 2KR89I4H1Y
Stearyl alcohol is a waxy, fatty substance derived from natural oils or made synthetically. It acts as an emulsifier and thickener in medicines, helping mix ingredients together and give the product the right texture.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Pfizer Laboratories Div Pfizer Inc labeler code 00069
- Cibinqo abrocitinib 50 mg Tablet, Film Coated NDC 0069-0235-30
- Ruxience rituximab-pvvr 100 mg/10mL Injection, Solution NDC 0069-0238-01
- Toviaz fesoterodine fumarate 4 mg Tablet, Film Coated, Extended Release NDC 0069-0242-30
- Toviaz fesoterodine fumarate 8 mg Tablet, Film Coated, Extended Release NDC 0069-0244-30
- Propofol 10 mg/mL Injection, Emulsion NDC 0069-0248-10
- Ruxience rituximab-pvvr 500 mg/50mL Injection, Solution NDC 0069-0249-01
- Talzenna talazoparib .1 mg Capsule, Liquid Filled NDC 0069-0252-30
- Fragmin Dalteparin Sodium 2500 [iU]/mL Injection NDC 0069-0253-10
- Doxorubicin Hydrochloride 2 mg/mL Injection, Solution NDC 0069-0255-10
- Velsipity etrasimod 2 mg Tablet, Film Coated NDC 0069-0274-30
- Doxorubicin Hydrochloride 2 mg/mL Injection, Solution NDC 0069-0277-02
- Ibrance palbociclib 75 mg Tablet, Film Coated NDC 0069-0284-03
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE XALKORI is a kinase inhibitor indicated for the treatment of • adult patients with metastatic non-small cell lung cancer (NSCLC) whose tumors are anaplastic lymphoma kinase (ALK) or ROS1-positive as detected by an FDA-approved test. ( 1.1 , 2.1 ) • pediatric patients 1 year of age and older and young adults with relapsed or refractory, systemic anaplastic large cell lymphoma (ALCL) that is ALK-positive. ( 1.2 , 2.3 ) o Limitations of Use: The safety and efficacy of XALKORI have not been established in older adults with relapsed or refractory, systemic ALK-positive ALCL. • adult and pediatric patients 1 year of age and older with unresectable, recurrent, or refractory inflammatory myofibroblastic tumor (IMT) that is ALK-positive.
( 1.3 , 2.3 )
1.1ALK- or ROS1-Positive Metastatic Non-Small Cell Lung Cancer XALKORI is indicated for the treatment of adult patients with metastatic non-small cell lung cancer (NSCLC) whose tumors are anaplastic lymphoma kinase (ALK) or ROS1-positive as detected by an FDA-approved test [see Dosage and Administration (2.1) ] .
1.2Relapsed or Refractory, Systemic ALK-Positive Anaplastic Large Cell Lymphoma XALKORI is indicated for the treatment of pediatric patients 1 year of age and older and young adults with relapsed or refractory, systemic anaplastic large cell lymphoma (ALCL) that is ALK-positive . Limitations of Use : The safety and efficacy of XALKORI have not been established in older adults with relapsed or refractory, systemic ALK-positive ALCL.
1.3Unresectable, Recurrent, or Refractory ALK-Positive Inflammatory Myofibroblastic Tumor XALKORI is indicated for the treatment of adult and pediatric patients 1 year of age and older with unresectable, recurrent, or refractory inflammatory myofibroblastic tumor (IMT) that is ALK-positive.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Metastatic NSCLC: The recommended dosage is 250 mg orally twice daily. ( 2.3 ) • Systemic ALCL: The recommended dosage is 280 mg/m 2 orally twice daily based on body surface area. ( 2.3 ) • Unresectable IMT: o Adult: The recommended dosage is 250 mg orally twice daily.
( 2.3 ) o Pediatric: The recommended dosage is 280 mg/m 2 orally twice daily based on body surface area. ( 2.3 ) • See full prescribing information for dosage adjustments by indication for patients with moderate or severe hepatic impairment or severe renal impairment. ( 2.7 , 2.8 )
2.1Patient Selection Select patients for the treatment of metastatic NSCLC with XALKORI based on the presence of ALK or ROS1 positivity in tumor specimens [see Clinical Studies (14.1 , 14.2 , 14.3) ] . Information on FDA-approved tests for the detection of ALK and ROS1 rearrangements in NSCLC is available at http://www.fda.gov/companiondiagnostics .
2.2Recommended Testing During Treatment with XALKORI • Monitor liver function tests, including alanine aminotransferase (ALT), aspartate aminotransferase (AST), and total bilirubin, every 2 weeks during the first 2 months of treatment, then once a month, and as clinically indicated, with more frequent repeat testing for increased liver transaminases, alkaline phosphatase, or total bilirubin in patients who develop increased transaminases [see Warnings and Precautions (5.1) ] . • Monitor complete blood counts including differential weekly for the first month of therapy and then at least monthly, with more frequent monitoring if Grade 3 or 4 abnormalities, fever, or infection occur [see Adverse Reactions (6.1) ] . • For pediatric and young adult patients with ALCL or pediatric patients with IMT, obtain baseline and follow-up ophthalmologic examinations including retinal examination within 1 month of starting XALKORI and every 3 months thereafter [see Warnings and Precautions (5.5) ] .
2.3Recommended Dosage The recommended dosage of XALKORI is provided in Table 1. Table 1. Recommended Dosage of XALKORI Indication Recommended Dosage of XALKORI ALK- or ROS1-Positive Metastatic NSCLC Adults : 250 mg orally twice daily Relapsed or Refractory, Systemic ALK-Positive ALCL Pediatric Patients and Young Adults : 280 mg/m 2 orally twice daily See Table 2 for Recommended Dosage based on body surface area for pediatric patients and young adults with ALCL for the capsules and oral pellets.
Unresectable, Recurrent, or Refractory ALK-Positive IMT Adults : 250 mg orally twice daily Pediatric Patients : 280 mg/m 2 orally twice daily See Table 3 for Recommended Dosage based on body surface area for pediatric patients with IMT for the capsules and oral pellets. Recommended Dosage for Adult Patients with ALK- or ROS1-Positive Metastatic NSCLC • The recommended dosage for adult patients with ALK- or ROS1-positive metastatic NSCLC is XALKORI capsules 250 mg orally, twice daily, with or without food until disease progression or unacceptable toxicity occurs. • For adults who cannot swallow capsules, the recommended dosage of XALKORI pellets is 250 mg (2 x 50 mg + 1 x 150 mg) orally, twice daily, with or without food until disease progression or unacceptable toxicity occurs.
Recommended Dosage for Pediatric and Young Adult Patients with ALK-Positive ALCL • The recommended dosage for pediatric patients 1 year of age and older and young adults with relapsed or refractory, systemic ALK-positive ALCL is based on body surface area (BSA) and is provided in Table 2. • Administer XALKORI capsules or pellets orally, twice daily, with or without food until disease progression or unacceptable toxicity occurs. Table 2 provides the dosage based on body surface area (BSA) for XALKORI capsules or pellets.
Table 2. Recommended XALKORI Dosage for Pediatric Patients 1 Year of Age and Older and Young Adults With ALK-Positive ALCL Using Either XALKORI Capsules or Pellets Body Surface Area (BSA) Recommended XALKORI Dosage to Achieve 280 mg/m 2 Twice Daily… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Capsules: • 200 mg: hard gelatin capsule, size 1, white opaque body and pink opaque cap, with "Pfizer" on the cap and "CRZ 200" on the body. • 250 mg: hard gelatin capsule, size 0, pink opaque cap and body, with "Pfizer" on the cap and "CRZ 250" on the body. Oral Pellets: • 20 mg: hard gelatin capsule, size 4, white opaque body and light blue opaque cap, printed with black ink “Pfizer” on the cap and “CRZ 20” on the body. • 50 mg: hard gelatin capsule, size 3, light gray opaque body and gray opaque cap, printed with black ink “Pfizer” on the cap and “CRZ 50” on the body. • 150 mg: hard gelatin capsule, size 0, light blue opaque body and cap, printed with black ink “Pfizer” on the cap and “CRZ 150” on the body.
Capsules: 200 mg, 250 mg ( 3 ) Oral pellets: 20 mg, 50 mg, 150 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Hepatotoxicity: Fatal hepatotoxicity has occurred. Monitor with periodic liver testing. Temporarily suspend, dose reduce, or permanently discontinue XALKORI.
( 2.2 , 2.6 , 5.1 ) • Interstitial Lung Disease (ILD)/Pneumonitis: Permanently discontinue in patients with ILD/pneumonitis. ( 2.6 , 5.2 ) • QT Interval Prolongation: Monitor electrocardiograms and electrolytes in patients who have a history of or predisposition for QTc prolongation, or who are taking medications that prolong QT. Temporarily suspend, dose reduce, or permanently discontinue XALKORI.
( 2.6 , 5.3 ) • Bradycardia: XALKORI can cause bradycardia. Monitor heart rate and blood pressure regularly. Temporarily suspend, dose reduce, or permanently discontinue XALKORI.
( 2.6 , 5.4 ) • Severe Visual Loss: XALKORI can cause visual changes including severe visual loss. Monitor and evaluate for ocular toxicity throughout treatment. Discontinue XALKORI in patients with severe visual loss.
( 2.2 , 2.6 , 5.5 ) • Gastrointestinal Toxicity in Pediatric and Young Adult Patients with ALCL or Pediatric Patients with IMT: XALKORI can cause severe nausea, vomiting, diarrhea, and stomatitis. Provide standard antiemetic and antidiarrheal agents. Temporarily suspend, dose reduce, or permanently discontinue XALKORI.
( 2.6 , 5.6 ) • Embryo-Fetal Toxicity: Can cause fetal harm. Advise females of reproductive potential of the potential risk to a fetus and use of effective contraception. ( 5.7 , 8.1 , 8.3 )
5.1Hepatotoxicity Drug-induced hepatotoxicity with fatal outcome occurred in 0.1% of the 1719 patients treated with XALKORI for NSCLC across clinical trials [see Adverse Reactions (6.1) ] . Concurrent elevations in ALT or AST ≥3 times the ULN and total bilirubin ≥2 times the ULN, with normal alkaline phosphatase, occurred in <1% of patients treated with XALKORI. Increased ALT or AST >5 times the ULN occurred in 11% and 6% of patients, respectively.
One percent (1.0%) of patients required permanent discontinuation due to elevated transaminases. Increased transaminases generally occurred within the first 2 months of treatment. In Study ADVL0912, of 121 patients ages 1 to ≤21 years treated with XALKORI for relapsed or refractory tumors including ALCL and IMT, 71% and 79% had increases of AST and ALT, respectively, with increased ALT or AST >5 times the ULN in 6% each.
Of the 26 patients with ALCL treated with XALKORI, 65% and 81% had increases of AST and ALT, respectively, with increases >5 times the ULN in 4% each. Of the 14 pediatric patients with IMT treated with XALKORI, 71% had increases of AST and 71% had increases of ALT. In Study A8081013, of the 7 adult patients with IMT treated with XALKORI, 57% and 43% had increases of AST and ALT, respectively.
Monitor liver function tests, including ALT, AST, and total bilirubin, every 2 weeks during the first 2 months of treatment, then once a month, and as clinically indicated, with more frequent repeat testing for increased liver transaminases, alkaline phosphatase, or total bilirubin in patients who develop increased transaminases. Withhold, reduce dose, or permanently discontinue XALKORI for hepatotoxicity as recommended [see Dosage and Administration (2.6) ] .
5.2Interstitial Lung Disease/Pneumonitis Severe, life-threatening, or fatal interstitial lung disease (ILD)/pneumonitis can occur in patients treated with XALKORI. Across clinical trials in patients with NSCLC (n=1719), 2.9% of XALKORI-treated patients had ILD of any grade, 1% had Grade 3 or 4 ILD, and 0.5% had fatal ILD [see Adverse Reactions (6.1) ] . Interstitial lung disease generally occurred within 3 months after the initiation of XALKORI.
In Study ADVL0912, among 121 patients ages 1 to ≤21 years with relapsed or refractory tumors, including ALCL and IMT, ILD occurred in 0.8% of patients. Monitor patients for pulmonary symptoms indicative of ILD/pneumonitis. Exclude other potential causes of ILD/pneumonitis, and permanently discontinue XALKORI… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: • Hepatotoxicity [see Warnings and Precautions (5.1) ] • Interstitial Lung Disease/Pneumonitis [see Warnings and Precautions (5.2) ] • QT Interval Prolongation [see Warnings and Precautions (5.3) ] • Bradycardia [see Warnings and Precautions (5.4) ] • Severe Visual Loss [see Warnings and Precautions (5.5) ] • Gastrointestinal Toxicity in Pediatric and Young Adult Patients with ALCL or Pediatric Patients with IMT [see Warnings and Precautions (5.6) ] The most common adverse reactions (≥25%) in adult patients with NSCLC are vision disorders, nausea, diarrhea, vomiting, edema, constipation, elevated transaminases, fatigue, decreased appetite, upper respiratory infection, dizziness, and neuropathy.
( 6.1 ) The most common adverse reactions (≥35%) in patients with ALCL are diarrhea, vomiting, nausea, vision disorder, headache, musculoskeletal pain, stomatitis, fatigue, decreased appetite, pyrexia, abdominal pain, cough, and pruritus. Grade 3–4 laboratory abnormalities (≥15%) are neutropenia, lymphopenia, and thrombocytopenia. ( 6.1 ) The most common adverse reactions (≥35%) in adult patients with IMT are vision disorders, nausea, and edema.
( 6.1 ) The most common adverse reactions (≥35%) in pediatric patients with IMT are vomiting, nausea, diarrhea, abdominal pain, rash, vision disorder, upper respiratory tract infection, cough, pyrexia, musculoskeletal pain, fatigue, edema, constipation, and headache. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Pfizer Inc. at 1-800-438-1985 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. The data in the Warnings and Precautions reflect exposure to XALKORI in 1719 patients with NSCLC who received XALKORI 250 mg twice daily enrolled on Studies 1 (including an additional 109 patients who crossed over from the control arm), 2, 3, a single-arm trial (n=1063) of ALK-positive NSCLC, and an additional ALK-positive NSCLC expansion cohort of a dose finding study (n=154).
The data also reflect exposure to XALKORI in 121 patients ages 1 to ≤21 years with relapsed or refractory tumors, including 26 patients with systemic ALCL and 14 pediatric patients with IMT, in a single-arm trial (Study ADVL0912). The data are also described for 7 adult patients with IMT treated with XALKORI in a single-arm trial (Study A8081013). ALK- or ROS1-Positive Metastatic NSCLC The data described below is based primarily on 343 patients with ALK-positive metastatic NSCLC who received XALKORI 250 mg orally twice daily from 2 open-label, randomized, active-controlled trials (Studies 1 and 2).
The safety of XALKORI was also evaluated in 50 patients with ROS1-positive metastatic NSCLC from a single-arm study (Study 3). The most common adverse reactions (≥25%) of XALKORI in patients with NSCLC are vision disorders, nausea, diarrhea, vomiting, edema, constipation, elevated transaminases, fatigue, decreased appetite, upper respiratory infection, dizziness, and neuropathy. Previously Untreated ALK-Positive Metastatic NSCLC - Study 1 (PROFILE 1014) The data in Table 9 are derived from 340 patients with ALK-positive metastatic NSCLC who had not received previous systemic treatment for advanced disease who received treatment in a randomized, multicenter, open-label, active-controlled trial (Study 1).
Patients in the XALKORI arm (n=171) received XALKORI 250 mg orally twice daily until documented disease progression, intolerance to therapy, or the investigator determined that the patient was no longer experiencing clinical benefit. A total of 169 patients in the chemotherapy arm received pemetrexed 500 mg/m 2 with cisp… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Strong CYP3A Inhibitors: Avoid concomitant use. ( 2.9 , 7.1 ) • Strong CYP3A Inducers: Avoid concomitant use. ( 7.1 ) • CYP3A Substrates: Avoid concomitant use with CYP3A substrates, where minimal concentration changes may lead to serious adverse reactions. ( 7.2 )
7.1Effect of Other Drugs on XALKORI Strong or Moderate CYP3A Inhibitors Concomitant use of crizotinib with strong CYP3A inhibitors increases crizotinib plasma concentrations [see Clinical Pharmacology (12.3) ] , which may increase the risk of adverse reactions of XALKORI. Avoid concomitant use of strong CYP3A inhibitors. If concomitant use of strong CYP3A inhibitors is unavoidable, reduce the XALKORI dosage [see Dosage and Administration (2.9) ] .
Avoid grapefruit or grapefruit juice which may also increase plasma concentrations of crizotinib. Use caution with concomitant use of moderate CYP3A inhibitors. Strong CYP3A Inducers Concomitant use of crizotinib with strong CYP3A inducers decreases crizotinib plasma concentrations [see Clinical Pharmacology (12.3) ] , which may decrease the efficacy of XALKORI.
Avoid concomitant use of strong CYP3A inducers.
7.2Effect of XALKORI on Other Drugs CYP3A Substrates Concomitant use of crizotinib increases plasma concentrations of CYP3A substrates [see Clinical Pharmacology (12.3) ] , which may increase the risk of adverse reactions of these substrates. Avoid concomitant use of XALKORI with CYP3A substrates where minimal concentration changes may lead to serious adverse reactions. If concomitant use of XALKORI is unavoidable, decrease the CYP3A substrate dosage in accordance with approved product labeling.
7.3Drugs That Prolong the QT Interval XALKORI can prolong the QT/QTc interval. Avoid concomitant use of XALKORI with drugs that prolong the QT interval [see Warnings and Precautions (5.3) , Clinical Pharmacology (12.2) ] .
7.4Drugs That Cause Bradycardia XALKORI can cause bradycardia. Avoid concomitant use of XALKORI with drugs that cause bradycardia (e.g., beta-blockers, non-dihydropyridine calcium channel blockers, clonidine, and digoxin) [see Warnings and Precautions (5.4) ] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action, XALKORI can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . There are no available data on the use of XALKORI in pregnant women. In animal reproduction studies, oral administration of crizotinib to pregnant rats during organogenesis at exposures similar to those expected with the maximum recommended human dose resulted in embryotoxicity and fetotoxicity (see Data ) .
Advise pregnant women of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Crizotinib was administered to pregnant rats and rabbits during organogenesis to study the effects on embryo-fetal development.
Postimplantation loss was increased at doses ≥50 mg/kg/day (approximately 0.6 times the recommended human dose based on AUC) in rats. No teratogenic effects were observed in rats at doses up to the maternally toxic dose of 200 mg/kg/day (approximately 2.7 times the recommended human dose based on AUC) or in rabbits at doses of up to 60 mg/kg/day (approximately 1.6 times the recommended human dose based on AUC), though fetal body weights were reduced at these doses.
8.2Lactation Risk Summary There is no information regarding the presence of crizotinib or its metabolites in human milk, or the effects on the breastfed child or on milk production. Because of the potential for adverse reactions in breastfed children, advise women not to breastfeed during treatment with XALKORI and for 45 days after the last dose.
8.3Females and Males of Reproductive Potential Pregnancy Testing Verify the pregnancy status of females of reproductive potential prior to initiating XALKORI [see Use in Specific Population (8.1) ]. Contraception XALKORI can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ] . Females Advise females of reproductive potential to use effective contraception during treatment with XALKORI and for 45 days after the last dose.
Males Because of the potential for genotoxicity, advise male patients with female partners of reproductive potential to use condoms during treatment with XALKORI and for 90 days after the last dose [see Nonclinical Toxicology (13.1) ]. Infertility Based on reproductive organ findings in animals, XALKORI may cause reduced fertility in females and males of reproductive potential. It is not known whether these effects on fertility are reversible [see Nonclinical Toxicology (13.1) ].
8.4Pediatric Use The safety and effectiveness of XALKORI have been established in pediatric patients 1 year of age and older with relapsed or refractory, systemic ALK-positive ALCL or with unresectable, recurrent, or refractory ALK-positive IMT [see Adverse Reactions (6.1) , Clinical Studies (14.2 , 14.3) ] . The safety and effectiveness have not been established in pediatric patients younger than 1 year of age with ALCL or with IMT, or in any pediatric patients with NSCLC. In a study that evaluated XALKORI in combination with chemotherapy in pediatric patients with newly diagnosed ALCL (Study ANHL12P1; NCT01979536), 13 of 66 (20%) patients had a Grade 2 or higher thromboembolic event, including pulmonary embolism in 6%.
The safety and effectiveness of XALKORI in combination with chemotherapy have not been established in patients with newly diagnosed ALCL. Juvenile Animal Toxicity Data Decreased bone formation in growing long bones was observed in immature rats at 150 mg/kg/day following once daily dosing for 28 days (approximately 5.4 times the recommended human dose based on AUC). Other toxicities of potential concern to pediatric patients have not been evaluated in juvenile animals.
8.5Geriatric Use Of the total number of patients wi… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action, XALKORI can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . There are no available data on the use of XALKORI in pregnant women. In animal reproduction studies, oral administration of crizotinib to pregnant rats during organogenesis at exposures similar to those expected with the maximum recommended human dose resulted in embryotoxicity and fetotoxicity (see Data ) .
Advise pregnant women of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Crizotinib was administered to pregnant rats and rabbits during organogenesis to study the effects on embryo-fetal development.
Postimplantation loss was increased at doses ≥50 mg/kg/day (approximately 0.6 times the recommended human dose based on AUC) in rats. No teratogenic effects were observed in rats at doses up to the maternally toxic dose of 200 mg/kg/day (approximately 2.7 times the recommended human dose based on AUC) or in rabbits at doses of up to 60 mg/kg/day (approximately 1.6 times the recommended human dose based on AUC), though fetal body weights were reduced at these doses.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of XALKORI have been established in pediatric patients 1 year of age and older with relapsed or refractory, systemic ALK-positive ALCL or with unresectable, recurrent, or refractory ALK-positive IMT [see Adverse Reactions (6.1) , Clinical Studies (14.2 , 14.3) ] . The safety and effectiveness have not been established in pediatric patients younger than 1 year of age with ALCL or with IMT, or in any pediatric patients with NSCLC. In a study that evaluated XALKORI in combination with chemotherapy in pediatric patients with newly diagnosed ALCL (Study ANHL12P1; NCT01979536), 13 of 66 (20%) patients had a Grade 2 or higher thromboembolic event, including pulmonary embolism in 6%.
The safety and effectiveness of XALKORI in combination with chemotherapy have not been established in patients with newly diagnosed ALCL. Juvenile Animal Toxicity Data Decreased bone formation in growing long bones was observed in immature rats at 150 mg/kg/day following once daily dosing for 28 days (approximately 5.4 times the recommended human dose based on AUC). Other toxicities of potential concern to pediatric patients have not been evaluated in juvenile animals.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of patients with ALK-positive metastatic NSCLC in clinical studies of XALKORI (n=1669), 16% were 65 years or older and 3.8% were 75 years or older. No overall differences in safety or effectiveness were observed between these patients and younger patients. Clinical studies of XALKORI in patients with ROS1-positive metastatic NSCLC did not include sufficient numbers of patients age 65 years and older to determine whether they respond differently from younger patients.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Crizotinib is an inhibitor of receptor tyrosine kinases including ALK, Hepatocyte Growth Factor Receptor (HGFR, c-Met), ROS1 (c-ros), and Recepteur d'Origine Nantais (RON). Translocations can affect the ALK gene resulting in the expression of oncogenic fusion proteins. The formation of ALK fusion proteins results in activation and dysregulation of the gene's expression and signaling which can contribute to increased cell proliferation and survival in tumors expressing these proteins.
Crizotinib demonstrated concentration-dependent inhibition of ALK, ROS1, and c-Met phosphorylation in cell-based assays using tumor cell lines and demonstrated antitumor activity in mice bearing tumor xenografts that expressed echinoderm microtubule-associated protein-like 4 (EML4)- or nucleophosmin (NPM)-ALK fusion proteins or c-Met. In vitro, crizotinib induced apoptosis and inhibited proliferation and ALK-mediated signaling in ALCL-derived cell lines (containing NPM-ALK) at clinically achievable exposures. In vivo data obtained in an ALCL-derived mouse model showed complete regression of the tumor at a dose of 100 mg/kg once daily.
12.2Pharmacodynamics Cardiac Electrophysiology In an ECG substudy conducted in 52 patients with ALK-positive NSCLC, the maximum mean QTcF (corrected QT by the Fridericia method) change from baseline was 12.3 ms (2-sided 90% upper CI: 19.5 ms) following administration of XALKORI 250 mg orally twice daily. An exposure-QT analysis suggested a crizotinib plasma concentration-dependent increase in QTcF [see Warnings and Precautions (5.3) ] .
12.3Pharmacokinetics Following XALKORI 250 mg capsules twice daily, steady-state was reached within 15 days with a median accumulation ratio of 4.8. Steady-state minimum concentration (C min.ss ) and AUC increased in a greater than dose-proportional manner over the dose range of 200 mg to 300 mg twice daily (0.8 to 1.2 times the approved recommended dosage). Absorption A single crizotinib capsule dose was absorbed with median time to achieve peak concentration (T max ) of 4 to 6 hours, and the mean absolute bioavailability of 43% (range: 32% to 66%).
The oral pellets had a comparable crizotinib bioavailability compared with the capsules. Effect of Food A high-fat meal, reduced AUC 0-INF and maximum plasma concentration (C max ) of crizotinib each by 14% for the capsule formulation; reduced AUC 0-INF and C max of crizotinib by 15% and 23%, respectively, for the pellet formulation as compared to those under fasted conditions. Distribution The geometric mean volume of distribution (V ss ) of crizotinib was 1772 L following a single intravenous dose.
Protein binding of crizotinib is 91% and is independent of drug concentration in vitro. Crizotinib is a substrate for P-glycoprotein (P-gp) in vitro. The blood-to-plasma concentration ratio is approximately 1.
Elimination The mean apparent plasma terminal half-life of crizotinib was 42 hours following single doses of crizotinib in patients. The mean apparent clearance (CL/F) of crizotinib was lower at steady-state (60 L/h) after 250 mg twice daily than after a single 250 mg oral dose (100 L/h). Metabolism Crizotinib is predominantly metabolized by CYP3A.
Excretion Following administration of a single oral 250 mg dose of radiolabeled crizotinib dose to healthy subjects, 63% (53% as unchanged) of the administered dose was recovered in feces and 22% (2.3% as unchanged) in urine. Specific Populations No clinically significant difference in crizotinib pharmacokinetics were observed based on age, sex, or ethnicity (Asian, non-Asian). For patients <18 years of age, body weight has a significant effect on the pharmacokinetics of crizotinib, with lower crizotinib exposures observed in patients with higher body weight.
Pediatric Patients In pediatric patients, crizotinib steady-state exposure increased proportionally with dose over the dose range of 165 mg/m 2 to 280 mg/m 2 orally twice daily. At a do… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Crizotinib is an inhibitor of receptor tyrosine kinases including ALK, Hepatocyte Growth Factor Receptor (HGFR, c-Met), ROS1 (c-ros), and Recepteur d'Origine Nantais (RON). Translocations can affect the ALK gene resulting in the expression of oncogenic fusion proteins. The formation of ALK fusion proteins results in activation and dysregulation of the gene's expression and signaling which can contribute to increased cell proliferation and survival in tumors expressing these proteins.
Crizotinib demonstrated concentration-dependent inhibition of ALK, ROS1, and c-Met phosphorylation in cell-based assays using tumor cell lines and demonstrated antitumor activity in mice bearing tumor xenografts that expressed echinoderm microtubule-associated protein-like 4 (EML4)- or nucleophosmin (NPM)-ALK fusion proteins or c-Met. In vitro, crizotinib induced apoptosis and inhibited proliferation and ALK-mediated signaling in ALCL-derived cell lines (containing NPM-ALK) at clinically achievable exposures. In vivo data obtained in an ALCL-derived mouse model showed complete regression of the tumor at a dose of 100 mg/kg once daily.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Capsules: • 200 mg capsules Hard gelatin capsule with pink opaque cap and white opaque body, printed with black ink "Pfizer" on the cap, "CRZ 200" on the body; available in: Bottles of 60 capsules: NDC 0069-8141-20 • 250 mg capsules Hard gelatin capsule with pink opaque cap and body, printed with black ink "Pfizer" on the cap, "CRZ 250" on the body; available in: Bottles of 60 capsules: NDC 0069-8140-20 Store at room temperature 20° to 25°C (68° to 77°F); excursions permitted between 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
Oral Pellets: • 20 mg oral pellets Hard gelatin capsule, size 4, light blue opaque cap and white opaque body, printed with black ink “Pfizer” on the cap, “CRZ 20” on the body; available in: Bottles of 60 capsules: NDC 0069-0251-60 • 50 mg oral pellets Hard gelatin capsule, size 3, gray opaque cap and light gray opaque body, printed with black ink “Pfizer” on the cap, “CRZ 50” on the body; available in: Bottles of 60 capsules: NDC 0069-0507-60 • 150 mg oral pellets Hard gelatin capsule, size 0, light blue opaque cap and body, printed with black ink “Pfizer” on the cap, “CRZ 150” on the body; available in: Bottles of 60 capsules: NDC 0069-1500-60 Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Crizotinib is a kinase inhibitor. The molecular formula for crizotinib is C 21 H 22 Cl 2 FN 5 O and the molecular weight is 450.34 daltons. Crizotinib is described chemically as ( R )-3-[1-(2,6-Dichloro-3-fluorophenyl)ethoxy]-5-[1-(piperidin-4-yl)-1 H -pyrazol-4-yl]pyridin-2-amine.
The chemical structure of crizotinib is shown below: Crizotinib is a white to pale-yellow powder with a pKa of 9.4 (piperidinium cation) and 5.6 (pyridinium cation). The solubility of crizotinib in aqueous media decreases over the range pH 1.6 to pH 8.2 from greater than 10 mg/mL to less than 0.1 mg/mL. The log of the distribution coefficient (octanol/water) at pH 7.4 is 1.65.
Capsules: XALKORI (crizotinib) capsules for oral administration are supplied as printed hard-shell capsules containing 250 mg or 200 mg of crizotinib together with colloidal silicon dioxide, microcrystalline cellulose, anhydrous dibasic calcium phosphate, sodium starch glycolate, magnesium stearate, and hard gelatin capsule shells as inactive ingredients. The pink opaque capsule shell components contain gelatin, titanium dioxide, and red iron oxide. The white opaque capsule shell components contain gelatin and titanium dioxide.
The printing ink contains shellac, propylene glycol, strong ammonia solution, potassium hydroxide, and black iron oxide. Oral Pellets: XALKORI (crizotinib) oral pellets for oral administration are supplied as 20 mg, 50 mg, 150 mg of crizotinib contained in hard gelatin capsules. The inactive ingredients in the uncoated pellets are poloxamer and stearyl alcohol.
The film-coating consists of hypromellose, glyceryl monostearate, medium chain triglycerides, polyethylene glycol/macrogol, sucrose, and talc. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient or caregiver to read the FDA-approved patient labeling (Medication Guide; Instructions for Use). Hepatotoxicity Inform patients to immediately report symptoms of hepatotoxicity [see Warnings and Precautions (5.1) ] . Interstitial Lung Disease (Pneumonitis) Advise patients to immediately report any new or worsening pulmonary symptoms [see Warnings and Precautions (5.2) ].
Bradycardia Advise patients to report any symptoms of bradycardia and to inform their healthcare provider about the use of any heart or blood pressure medications [see Warnings and Precautions (5.4) ]. Severe Visual Loss Inform patients of the potential risk of severe visual loss and to immediately contact their healthcare provider if they develop severe visual loss. Inform patients that visual changes such as perceived flashes of light, blurry vision, light sensitivity, and floaters are commonly reported adverse reactions and may occur while driving or operating machinery.
The onset of visual disorders most commonly occurs during the first week of treatment [see Warnings and Precautions (5.5) , Adverse Reactions (6) ] . Gastrointestinal Toxicity in Pediatric and Young Adult Patients with ALCL or Pediatric Patients with IMT Inform patients with ALCL or pediatric patients with IMT of the risk of severe nausea, vomiting, diarrhea, and stomatitis. Advise patients to immediately inform their healthcare provider of problems with swallowing, vomiting, or diarrhea [see Warnings and Precautions (5.6) ].
Drug Interactions Inform patients to avoid grapefruit or grapefruit juice while taking XALKORI. Advise patients to inform their healthcare providers of all concomitant medications, including prescription medicines, over-the-counter drugs, vitamins, and herbal products [see Drug Interactions (7) ] . Photosensitivity Inform patients of the signs and symptoms of photosensitivity.
Advise patients to avoid prolonged sun exposure and to use sunscreen or protective clothing during treatment with XALKORI [see Adverse Reactions (6.1) ] . Dosage and Administration Advise patients to take XALKORI with or without food. If a patient misses a dose, advise the patient to take it as soon as remembered unless it is less than 6 hours until the next dose, in which case, advise the patient not to take the missed dose.
If a patient vomits after taking a dose of XALKORI, advise the patient not to take an extra dose, but to take the next dose at the regular time [see Dosage and Administration (2.4) ] . Capsules: Advise patients to swallow XALKORI capsules whole [see Dosage and Administration (2.4) ] . Oral Pellets: Inform patient or caregiver to open the encapsulated XALKORI oral pellets and administer the oral pellets directly in the patient’s mouth or with a consumer-supplied oral dosing aid, for example a spoon or medicine cup.
Advise patient or caregiver that the oral pellets are not to be chewed and to give a sufficient amount of water after pellets are administered to ensure all oral pellets are swallowed [see Dosage and Administration (2.4) ] . Embryo-Fetal Toxicity Advise females of reproductive potential of the potential risk to a fetus and to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.7) , Use in Specific Populations (8.1) ] . Females and Males of Reproductive Potential Advise females of reproductive potential to use effective contraception during treatment with XALKORI and for 45 days after the last dose [see Use in Specific Populations (8.3) ] .
Advise male patients with female partners of reproductive potential to use condoms during treatment with XALKORI and for 90 days after the last dose [see Use in Specific Populations (8.3) , Nonclinical Toxicology (13.1) ] . Lactation Advise females not to breastfeed during treatment with XALKORI and for 45 days after the last dose [see Use in Specific Populations (8.2) ] . Infertility Advise females and males of reproductive poten… [Excerpted — this section continues on DailyMed.]
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: Sep 2023 MEDICATION GUIDE XALKORI ® (zal-KOR-ee) (crizotinib) capsules XALKORI ® (zal-KOR-ee) (crizotinib) oral pellets What is the most important information I should know about XALKORI?
XALKORI may cause serious side effects, including: • Liver problems. XALKORI may cause life-threatening liver injury that may lead to death. Your healthcare provider should do blood tests to check your liver every 2 weeks during the first 2 months of treatment with XALKORI, then 1 time a month and as recommended by your healthcare provider during treatment.
Tell your healthcare provider right away if you develop any of the following new or worsening symptoms: o yellowing of your skin or the white part of your eyes o severe tiredness o dark or brown (tea color) urine o nausea or vomiting o decreased appetite o pain on the right side of your stomach o bleed or bruise more easily than normal o itching • Lung problems (pneumonitis). XALKORI may cause life-threatening lung problems that may lead to death. Symptoms may be similar to those symptoms from lung cancer.
Tell your healthcare provider right away if you have any new or worsening symptoms, including: o trouble breathing or shortness of breath o cough with or without mucous o fever • Heart problems. XALKORI may cause very slow, very fast, or abnormal heartbeats. Your healthcare provider may check your pulse rate and blood pressure regularly during treatment with XALKORI.
Tell your healthcare provider right away if you feel dizzy or faint or have abnormal heartbeats. Tell your healthcare provider if you take any heart or blood pressure medicines. • Severe vision problems. Vision problems are common with XALKORI.
These problems usually happen within 1 week of starting treatment with XALKORI. Vision problems with XALKORI can be severe and may cause partial or complete loss of vision in one or both eyes. Your healthcare provider may hold or permanently stop your treatment with XALKORI and refer you to an eye specialist if any vision problems develop during treatment with XALKORI.
Tell your healthcare provider right away if you have any new vision problems, loss of vision or any change in vision, including: o double vision o seeing flashes of light o blurry vision o light hurting your eyes o new or increased floaters In addition, for children or young adults taking XALKORI to treat anaplastic large cell lymphoma (ALCL) or children taking XALKORI to treat inflammatory myofibroblastic tumor (IMT): Your healthcare provider may refer you to an eye specialist before starting XALKORI, and within 1 month of starting XALKORI to check for vision problems.
You should have an eye examination every 3 months during treatment with XALKORI and more often if there are any new vision problems. • Severe stomach, intestine, and mouth (gastrointestinal) problems in children or young adults with ALCL or children with IMT. XALKORI may cause severe diarrhea, nausea, vomiting, or mouth sores. Tell your healthcare provider right away if problems with swallowing, vomiting, or diarrhea develop during treatment with XALKORI. o Your healthcare provider may give medicines as needed to prevent or treat diarrhea, nausea, and vomiting. o Your healthcare provider may recommend drinking more fluids or may prescribe electrolyte supplements or other kinds of nutritional support if severe symptoms develop.
See " What are possible side effects of XALKORI? " for more information about side effects. What is XALKORI? XALKORI is a prescription medicine that is used to treat: • adults with non-small cell lung cancer (NSCLC) that has spread to other parts of the body and is caused by a defect in either a gene called ALK (anaplastic lymphoma kinase) or a gene called ROS1. • children 1 year of age and older and young adults with ALCL when your ALCL with a defect in a gene called ALK has returned or you have tried a treatment and it did not work or is no… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Following XALKORI 250 mg capsules twice daily, steady-state was reached within 15 days with a median accumulation ratio of 4.8. Steady-state minimum concentration (C min.ss ) and AUC increased in a greater than dose-proportional manner over the dose range of 200 mg to 300 mg twice daily (0.8 to 1.2 times the approved recommended dosage). Absorption A single crizotinib capsule dose was absorbed with median time to achieve peak concentration (T max ) of 4 to 6 hours, and the mean absolute bioavailability of 43% (range: 32% to 66%).
The oral pellets had a comparable crizotinib bioavailability compared with the capsules. Effect of Food A high-fat meal, reduced AUC 0-INF and maximum plasma concentration (C max ) of crizotinib each by 14% for the capsule formulation; reduced AUC 0-INF and C max of crizotinib by 15% and 23%, respectively, for the pellet formulation as compared to those under fasted conditions. Distribution The geometric mean volume of distribution (V ss ) of crizotinib was 1772 L following a single intravenous dose.
Protein binding of crizotinib is 91% and is independent of drug concentration in vitro. Crizotinib is a substrate for P-glycoprotein (P-gp) in vitro. The blood-to-plasma concentration ratio is approximately 1.
Elimination The mean apparent plasma terminal half-life of crizotinib was 42 hours following single doses of crizotinib in patients. The mean apparent clearance (CL/F) of crizotinib was lower at steady-state (60 L/h) after 250 mg twice daily than after a single 250 mg oral dose (100 L/h). Metabolism Crizotinib is predominantly metabolized by CYP3A.
Excretion Following administration of a single oral 250 mg dose of radiolabeled crizotinib dose to healthy subjects, 63% (53% as unchanged) of the administered dose was recovered in feces and 22% (2.3% as unchanged) in urine. Specific Populations No clinically significant difference in crizotinib pharmacokinetics were observed based on age, sex, or ethnicity (Asian, non-Asian). For patients <18 years of age, body weight has a significant effect on the pharmacokinetics of crizotinib, with lower crizotinib exposures observed in patients with higher body weight.
Pediatric Patients In pediatric patients, crizotinib steady-state exposure increased proportionally with dose over the dose range of 165 mg/m 2 to 280 mg/m 2 orally twice daily. At a dosing regimen of 280 mg/m 2 (approximately 2 times the recommended adult dose), geometric mean (CV%) steady-state maximum plasma concentrations (C max ) of crizotinib was 621 (73%) ng/mL and AUC 0–tau was 6530 (34%) ng∙hr/mL. Patients with Hepatic Impairment Steady-state mean crizotinib AUC and C max decreased by 9% in patients with mild hepatic impairment (AST >ULN and total bilirubin ≤1 times ULN or any AST and total bilirubin >1 times ULN but ≤1.5 times ULN) compared to patients with normal hepatic function following XALKORI 250 mg orally twice daily.
Steady-state mean crizotinib AUC increased by 14% and C max increased by 9% in patients with moderate hepatic impairment (any AST and total bilirubin >1.5 times ULN and ≤3 times ULN) following XALKORI 200 mg orally twice daily compared with patients with normal hepatic function following XALKORI 250 mg orally twice daily. Mean crizotinib AUC decreased by 35% and C max decreased by 27% in patients with severe hepatic impairment (any AST and total bilirubin >3 times ULN) following XALKORI 250 mg orally once daily compared with patients with normal hepatic function following XALKORI 250 mg orally twice daily [see Dosage and Administration (2.7) , Use in Specific Populations (8.6) ] .
Patients with Renal Impairment Mild or moderate renal impairment (CL cr of 60–89 ml/min or 30–59 ml/min, respectively, calculated using the modified Cockcroft-Gault equation) has no clinically significant effect on the exposure of crizotinib. Following a single 250 mg dose, the mean AUC 0–INF of crizotinib increased by 79% and the mean C max increased by 34% in patients w… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Cardiac Electrophysiology In an ECG substudy conducted in 52 patients with ALK-positive NSCLC, the maximum mean QTcF (corrected QT by the Fridericia method) change from baseline was 12.3 ms (2-sided 90% upper CI: 19.5 ms) following administration of XALKORI 250 mg orally twice daily. An exposure-QT analysis suggested a crizotinib plasma concentration-dependent increase in QTcF [see Warnings and Precautions (5.3) ] .
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1ALK- or ROS1-Positive Metastatic Non-Small Cell Lung Cancer Previously Untreated ALK-Positive Metastatic NSCLC - Study 1 (PROFILE 1014; NCT01154140) The efficacy of XALKORI for the treatment of patients with ALK-positive metastatic NSCLC, who had not received previous systemic treatment for advanced disease, was demonstrated in a randomized, multicenter, open-label, active-controlled study (Study 1). Patients were required to have ALK-positive NSCLC as identified by the FDA-approved assay, Vysis ALK Break-Apart fluorescence in situ hybridization (FISH) Probe Kit, prior to randomization.
The major efficacy outcome measure was progression-free survival (PFS) according to Response Evaluation Criteria in Solid Tumors (RECIST) version 1.1 as assessed by independent radiology review (IRR) committee. Additional efficacy outcome measures included objective response rate (ORR) as assessed by IRR, DOR, and overall survival (OS). Patient-reported lung cancer symptoms were assessed at baseline and periodically during treatment.
Patients were randomized to receive XALKORI (n=172) or chemotherapy (n=171). Randomization was stratified by Eastern Cooperative Oncology Group (ECOG) performance status (0–1, 2), race (Asian, non-Asian), and brain metastases (present, absent). Patients in the XALKORI arm received XALKORI 250 mg orally twice daily until documented disease progression, intolerance to therapy, or the investigator determined that the patient was no longer experiencing clinical benefit.
Chemotherapy consisted of pemetrexed 500 mg/m 2 with cisplatin 75 mg/m 2 or carboplatin AUC of 5 or 6 mg×min/mL by intravenous infusion every 3 weeks for up to 6 cycles. Patients in the chemotherapy arm were not permitted to receive maintenance chemotherapy. At the time of documented disease progression, as per independent radiology review, patients randomized to chemotherapy were offered XALKORI.
The demographic characteristics of the overall study population were 62% female, median age of 53 years, baseline ECOG performance status 0 or 1 (95%), 51% White and 46% Asian, 4% current smokers, 32% past smokers, and 64% never smokers. The disease characteristics of the overall study population were metastatic disease in 98% of patients, 92% of patients' tumors were classified as adenocarcinoma histology, 27% of patients had brain metastases, and 7% received systemic chemotherapy as adjuvant or neoadjuvant therapy.
At the time of the final analysis of overall survival, 84% of patients randomized to the chemotherapy arm subsequently received XALKORI. Study 1 demonstrated a statistically significant improvement in PFS in patients treated with XALKORI. There was no statistically significant difference in OS between patients treated with XALKORI and patients treated with chemotherapy.
Table 16 and Figure 1 summarize the efficacy results. Exploratory patient-reported symptom measures of baseline and post-treatment dyspnea, cough, and chest pain suggested a delay in time to development of or worsening of dyspnea, but not cough or chest pain, in patients treated with XALKORI as compared to chemotherapy. The patient-reported delay in onset or worsening of dyspnea may be an overestimation because patients were not blinded to treatment assignment.
Table 16. Previously Untreated ALK-Positive Metastatic NSCLC - Efficacy Results in Study 1 XALKORI (N=172) Chemotherapy (N=171) HR=hazard ratio; CI=confidence interval; IRR=independent radiology review; NR=not reached; CR=complete response; PR=partial response. Progression-Free Survival (Based on IRR) Number of Events (%) 100 (58%) 137 (80%) Progressive Disease 89 (52%) 132 (77%) Death 11 (6%) 5 (3%) Median, Months (95% CI) 10.9 (8.3, 13.9) 7.0 (6.8, 8.2) HR (95% CI) Based on the Cox proportional hazards stratified analysis.
0.45(0.35, 0.60) p-value Based on the stratified log-rank test. <0.001 Overall Survival Number of Events (%) 71 (41%) 81 (47%) Median, Months (95% CI) NR (45.8, NR) 47.5 (32.2,… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies with crizotinib have not been conducted. Crizotinib was genotoxic in an in vitro micronucleus assay in Chinese Hamster Ovary cultures, in an in vitro human lymphocyte chromosome aberration assay, and in in vivo rat bone marrow micronucleus assays. Crizotinib was not mutagenic in vitro in the bacterial reverse mutation (Ames) assay.
No specific studies with crizotinib have been conducted in animals to evaluate the effect on fertility; however, crizotinib is considered to have the potential to impair reproductive function and fertility in humans based on findings in repeat-dose toxicity studies in the rat. Findings observed in the male reproductive tract included testicular pachytene spermatocyte degeneration in rats given greater than or equal to 50 mg/kg/day for 28 days (greater than 1.7 times the recommended human dose based on AUC). Findings observed in the female reproductive tract included single-cell necrosis of ovarian follicles of a rat given 500 mg/kg/day (approximately 10 times the recommended human dose based on body surface area) for 3 days.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies with crizotinib have not been conducted. Crizotinib was genotoxic in an in vitro micronucleus assay in Chinese Hamster Ovary cultures, in an in vitro human lymphocyte chromosome aberration assay, and in in vivo rat bone marrow micronucleus assays. Crizotinib was not mutagenic in vitro in the bacterial reverse mutation (Ames) assay.
No specific studies with crizotinib have been conducted in animals to evaluate the effect on fertility; however, crizotinib is considered to have the potential to impair reproductive function and fertility in humans based on findings in repeat-dose toxicity studies in the rat. Findings observed in the male reproductive tract included testicular pachytene spermatocyte degeneration in rats given greater than or equal to 50 mg/kg/day for 28 days (greater than 1.7 times the recommended human dose based on AUC). Findings observed in the female reproductive tract included single-cell necrosis of ovarian follicles of a rat given 500 mg/kg/day (approximately 10 times the recommended human dose based on body surface area) for 3 days.
📖 Instructions for Use ▾
Instructions for Use INSTRUCTIONS FOR USE XALKORI ® [zal-KOR-ee] (crizotinib) oral pellets This Instructions for Use contains information on how to give or take XALKORI oral pellets. Read this Instructions for Use each time you get a refill. There may be new information.
This information does not take the place of talking to your healthcare provider or pharmacist about your or your child’s medical condition or treatment. Important information you need to know before giving or taking XALKORI oral pellets: • XALKORI oral pellets come in a capsule “shell” that must be opened before giving or taking a dose. Do not swallow the shell containing the oral pellets.
Do not chew or crush the oral pellets. • XALKORI oral pellets come in 3 dosage strengths: 20 mg, 50 mg, and 150 mg. Your healthcare provider may combine different strengths for your prescribed dose. No more than 4 XALKORI oral pellet shells are to be used for a single dose. • Your healthcare provider will decide the right dose of XALKORI oral pellets for you or your child.
Follow your healthcare provider’s instructions for the dose of XALKORI oral pellets to give your child or for you to take. • Empty XALKORI oral pellets from the shells as described in Steps 1 to 4 below. • Check the expiration date on the bottle containing XALKORI oral pellets. Do not use XALKORI oral pellets after the expiration date on the bottle has passed. • Ask your healthcare provider or pharmacist if you are not sure how to prepare and give or take the prescribed dose of XALKORI oral pellets. Supplies needed to give or take XALKORI oral pellets: • XALKORI oral pellet(s), as prescribed by your healthcare provider. • Spoon or medicine cup (optional).
See Step 4 “Giving or taking XALKORI oral pellets” . Preparing XALKORI oral pellets (Steps 1 to 3): Step 1 Remove the number of XALKORI oral pellet shell(s) needed for the prescribed dose from each bottle(s). Step 2 • Hold the shell with the writing “Pfizer” at the top (see Figure A) . • Tap the shell to make sure the oral pellets fall to the bottom.
Gently squeeze the bottom of the shell to loosen the top of the shell from the bottom. Figure A Step 3 Carefully hold and twist the top and bottom parts of the shell in opposite directions and pull apart to open the shell (see Figure B) . Figure B Giving or taking XALKORI oral pellets (Step 4): There are 2 options for giving or taking the oral pellets.
Step 4 Option 1 (Pour directly into the mouth) • Pour all oral pellets from 1 shell directly into your or your child’s mouth (see Figure C) . • Gently tap the shell body with a finger as needed to make sure all pellets come out. • Right after giving or taking XALKORI oral pellets, give or drink enough water to make sure all oral pellets are swallowed . • If more than 1 shell is required for the prescribed dose, repeat Steps 1 to 4 for giving or taking the oral pellets from each shell. Figure C Option 2 (Pour from a spoon or medicine cup) • Empty the oral pellets from the shell(s) that make up the prescribed dose into a dry spoon or medicine cup (see Figure D) . • Pour the oral pellets from the dry spoon or medicine cup into your or your child’s mouth . • Right after giving or taking XALKORI oral pellets, give or drink enough water to make sure all oral pellets are swallowed . • If the entire prescribed dose cannot be taken at one time, give or take the oral pellets in smaller portions followed by giving or drinking water until the entire prescribed dose is given or taken.
Figure D After Step 4 is completed, other drinks or foods can be given or taken, except grapefruit juice, grapefruit, or supplements containing grapefruit extract. Storing XALKORI oral pellets: • Store XALKORI oral pellets at room temperature between 68°F to 77°F (20°C to 25°C). • Keep XALKORI oral pellets and all medicines out of the reach of children. Disposing of empty XALKORI oral pellet shells: • Dispose of (throw away) the empty XALKORI oral pellet shell(s) in the household trash. • Ask… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Dosage and Administration ( 2 ) 9/2023
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 250 mg Capsule Bottle Label ALWAYS DISPENSE ENCLOSED MEDICATION GUIDE TO EACH PATIENT Pfizer NDC 0069-8140-20 XALKORI ® (crizotinib) capsules 250 mg Swallow capsule whole 60 Capsules Rx only PRINCIPAL DISPLAY PANEL - 250 mg Capsule Bottle Label
PRINCIPAL DISPLAY PANEL - 200 mg Capsule Bottle Label ALWAYS DISPENSE ENCLOSED MEDICATION GUIDE TO EACH PATIENT Pfizer NDC 0069-8141-20 XALKORI ® (crizotinib) capsules 200 mg Swallow capsule whole 60 Capsules Rx only PRINCIPAL DISPLAY PANEL - 200 mg Capsule Bottle Label
PRINCIPAL DISPLAY PANEL - 20 mg Oral Pellets Label ALWAYS DISPENSE ENCLOSED MEDICATION GUIDE TO EACH PATIENT NDC 0069-0251-60 Pfizer XALKORI ® (crizotinib) oral pellets 20 mg Open capsule shell to administer pellets. Do not swallow capsule whole. Do not crush or chew pellets. 60 Capsules Rx only PRINCIPAL DISPLAY PANEL - 20 mg Oral Pellets Label
PRINCIPAL DISPLAY PANEL - 50 mg Oral Pellets Label ALWAYS DISPENSE ENCLOSED MEDICATION GUIDE TO EACH PATIENT NDC 0069-0507-60 Pfizer XALKORI ® (crizotinib) oral pellets 50 mg Open capsule shell to administer pellets. Do not swallow capsule whole. Do not crush or chew pellets. 60 Capsules Rx only PRINCIPAL DISPLAY PANEL - 50 mg Oral Pellets Label
PRINCIPAL DISPLAY PANEL - 150 mg Oral Pellets Label ALWAYS DISPENSE ENCLOSED MEDICATION GUIDE TO EACH PATIENT NDC 0069-1500-60 Pfizer XALKORI ® (crizotinib) oral pellets 150 mg Open capsule shell to administer pellets. Do not swallow capsule whole. Do not crush or chew pellets. 60 Capsules Rx only PRINCIPAL DISPLAY PANEL - 150 mg Oral Pellets Label
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |