
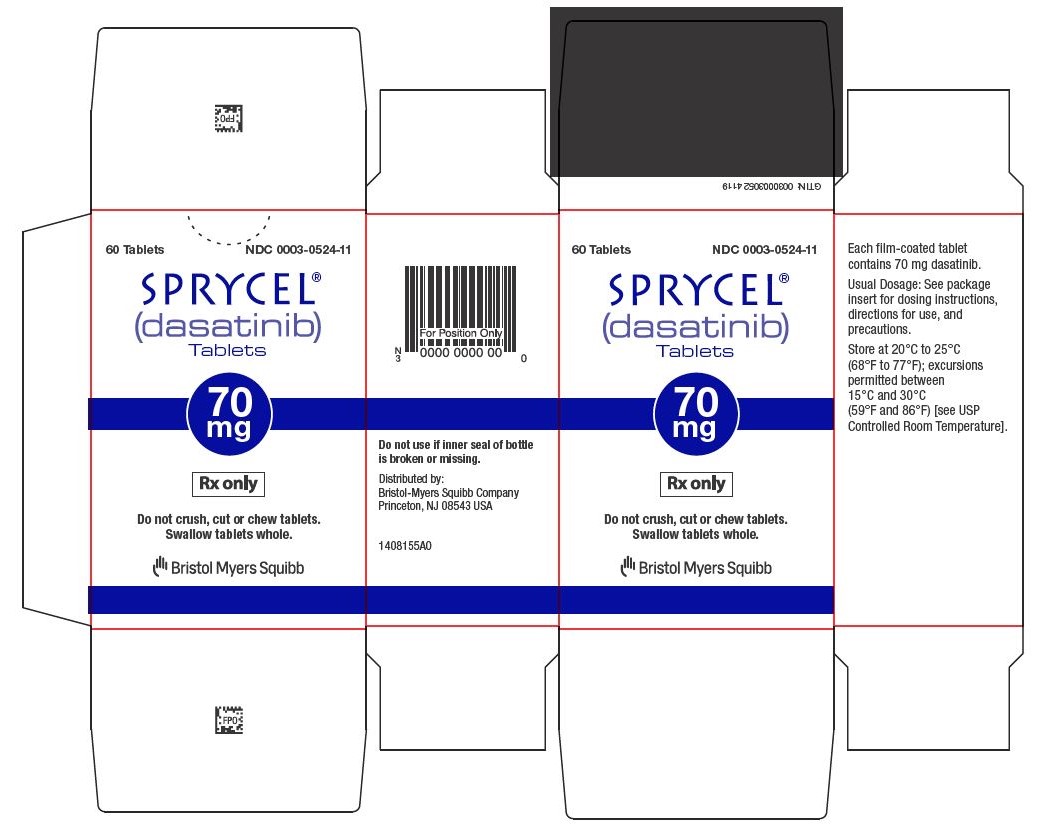
SPRYCEL dasatinib 70 mg Tablet, 60-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Kinase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Dasatinib is used to treat a certain type of chronic myeloid leukemia (CML; a type of cancer of the white blood cells) as a first treatment and in adults who can no longer benefit from other leukemia medications including imatinib (Gleevec®) or in those who cannot take these medications because of side effects. Dasatinib is also used to treat a certain type of chronic CML in children 1 year of age or older. Dasatinib is also used to treat a certain type of acute lymphoblastic leukemia (ALL; a type of cancer of the white blood cells) in adults who can no longer benefit from other leukemia medi...
Read the full MedlinePlus article ↗- Your leukemia is driven by an abnormal protein called BCR-ABL, which is produced because of a chromosomal change called the Philadelphia chromosome. Think of BCR-ABL as a switch st...
- What exactly is dasatinib treating in my body?
- You can take dasatinib with or without a meal — that flexibility is built in. Just pick a consistent time of day, morning or evening, and stick with it. The one thing to avoid is g...
- Does it matter whether I take this with food or on an empty stomach?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Dasatinib — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII RFW2ET671P
Hydroxypropyl cellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a film-former to coat tablets or control how fast the medicine releases.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $337.00 | $20,219.80 / 60 tablets |
| Medicare drug plans payPart D · Q2 2026 | $325.59 | $19,535.35 / 60 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Sprycel 70 mgthis 00003-0524-11 | E.R. | 60 tablets | — | AB | FDA listed | — |
| Dasatinib 70 mg 00480-5103-06 | Teva | 60 tablets | — | AB | FDA listed | — |
| Dasatinib 70 mg 43598-0601-60 | Dr.Reddys | 60 tablets | — | AB | FDA listed | — |
| Dasatinib 70 mg 46708-0686-60 | Alembic | 60 tablets | — | AB | FDA listed | — |
| Dasatinib 70 mg 59651-0544-15 | Aurobindo | 15 tablets | — | AB | FDA listed | — |
| Dasatinib 70 mg 60505-3630-06 | Apotex | 60 tablets | — | AB | FDA listed | — |
| Dasatinib 70 mg 62332-0686-60 | Alembic | 60 tablets | — | AB | FDA listed | — |
| Dasatinib 70 mg 66993-0235-60 | Prasco | 60 tablets | — | AB | FDA listed | — |
| Dasatinib 70 mg 68001-0662-06 | BluePoint | 60 tablets | — | AB | FDA listed | — |
| Dasatinib 70 mg 70377-0085-11 | Biocon | 60 tablets | — | AB | FDA listed | — |
| Phyrago 70 mg 70709-0153-70 | Cycle | 60 tablets | — | — | FDA listed | — |
| dasatinib 70 mg 70710-1743-06 | Zydus | 60 tablets | — | AB | FDA listed | — |
| Dasatinib 70 mg 70748-0210-07 | Lupin | 60 tablets | — | AB | FDA listed | — |
| dasatinib 70 mg 70771-1903-06 | Zydus | 60 tablets | — | AB | FDA listed | — |
| Dasatinib 70 mg 72603-0924-01 | NorthStar | 60 tablets | — | AB | FDA listed | — |
| Dasatinib 70 mg 73190-0048-60 | AvKARE | 60 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 7491725 ↗ | Drug substance | — | Mar 28, 2026 |
| US 7491725 ↗ | Drug substance | — | Mar 28, 2026 |
| US 7491725 ↗ | Drug substance | — | Mar 28, 2026 |
| US 7491725 ↗ | Drug substance | — | Mar 28, 2026 |
| US 7491725 ↗ | Drug substance | — | Mar 28, 2026 |
| US 7491725 ↗ | Drug substance | — | Mar 28, 2026 |
| US 7491725*PED ↗ | Drug product | — | Sep 28, 2026 |
| US 7491725*PED ↗ | Drug product | — | Sep 28, 2026 |
| US 7491725*PED ↗ | Drug product | — | Sep 28, 2026 |
| US 7491725*PED ↗ | Drug product | — | Sep 28, 2026 |
| US 7491725*PED ↗ | Drug product | — | Sep 28, 2026 |
| US 7491725*PED ↗ | Drug product | — | Sep 28, 2026 |
| Code | What it grants | Expires |
|---|---|---|
| ODE-225 | Orphan Drug Exclusivity (7-year) | Dec 21, 2025 |
| ODE-225 | Orphan Drug Exclusivity (7-year) | Dec 21, 2025 |
| ODE-225 | Orphan Drug Exclusivity (7-year) | Dec 21, 2025 |
| ODE-225 | Orphan Drug Exclusivity (7-year) | Dec 21, 2025 |
| ODE-225 | Orphan Drug Exclusivity (7-year) | Dec 21, 2025 |
| ODE-225 | Orphan Drug Exclusivity (7-year) | Dec 21, 2025 |
| PED | Pediatric Exclusivity (+6 months) | Jun 21, 2026 |
| PED | Pediatric Exclusivity (+6 months) | Jun 21, 2026 |
| PED | Pediatric Exclusivity (+6 months) | Jun 21, 2026 |
| PED | Pediatric Exclusivity (+6 months) | Jun 21, 2026 |
| PED | Pediatric Exclusivity (+6 months) | Jun 21, 2026 |
| PED | Pediatric Exclusivity (+6 months) | Jun 21, 2026 |
Is there a generic version of SPRYCEL 70 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00003-0524-11 You're viewing this | 1 BOTTLE in 1 CARTON (0003-0524-11) / 60 TABLET in 1 BOTTLE | 2006-06-27 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE SPRYCEL (dasatinib) is indicated for the treatment of adult patients with • newly diagnosed Philadelphia chromosome-positive (Ph+) chronic myeloid leukemia (CML) in chronic phase. • chronic, accelerated, or myeloid or lymphoid blast phase Ph+ CML with resistance or intolerance to prior therapy including imatinib. • Philadelphia chromosome-positive acute lymphoblastic leukemia (Ph+ ALL) with resistance or intolerance to prior therapy. SPRYCEL (dasatinib) is indicated for the treatment of pediatric patients 1 year of age and older with • Ph+ CML in chronic phase. • newly diagnosed Ph+ ALL in combination with chemotherapy.
SPRYCEL is a kinase inhibitor indicated for the treatment of • newly diagnosed adults with Philadelphia chromosome-positive (Ph+) chronic myeloid leukemia (CML) in chronic phase. (1 , 14) • adults with chronic, accelerated, or myeloid or lymphoid blast phase Ph+ CML with resistance or intolerance to prior therapy including imatinib. (1 , 14) • adults with Philadelphia chromosome-positive acute lymphoblastic leukemia (Ph+ ALL) with resistance or intolerance to prior therapy.
(1 , 14) • pediatric patients 1 year of age and older with Ph+ CML in chronic phase. (1 , 14) • pediatric patients 1 year of age and older with newly diagnosed Ph+ ALL in combination with chemotherapy. (1 , 14)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Chronic phase CML in adults: 100 mg once daily. (2) • Accelerated phase CML, myeloid or lymphoid blast phase CML, or Ph+ ALL in adults: 140 mg once daily. (2) • Chronic phase CML and ALL in pediatrics: starting dose based on body weight. (2) • Administer orally, with or without a meal. Do not crush, cut, or chew tablets. (2)
2.1Dosage of SPRYCEL in Adult Patients The recommended starting dosage of SPRYCEL for chronic phase CML in adults is 100 mg administered orally once daily. The recommended starting dosage of SPRYCEL for accelerated phase CML, myeloid or lymphoid blast phase CML, or Ph+ ALL in adults is 140 mg administered orally once daily. Tablets should not be crushed, cut, or chewed; they should be swallowed whole.
SPRYCEL can be taken with or without a meal, either in the morning or in the evening.
2.2Dosage of SPRYCEL in Pediatric Patients with CML or Ph+ ALL The recommended starting dosage for pediatrics is based on body weight as shown in Table 1. The recommended dose should be administered orally once daily with or without food. Recalculate the dose every 3 months based on changes in body weight, or more often if necessary.
Do not crush, cut or chew tablets. Swallow tablets whole. There are additional administration considerations for pediatric patients who have difficulty swallowing tablets whole [see Use in Specific Populations (8.4) and Clinical Pharmacology (12.3) ] .
Table 1: Dosage of SPRYCEL for Pediatric Patients a Body Weight (kg) b Daily Dose (mg) a For pediatric patients with Ph+ ALL, begin SPRYCEL therapy on or before day 15 of induction chemotherapy, when diagnosis is confirmed and continue for 2 years. b Tablet dosing is not recommended for patients weighing less than 10 kg. 10 to less than 20 40 mg 20 to less than 30 60 mg 30 to less than 45 70 mg at least 45 100 mg Refer to Section 2.4 for recommendations on dose escalation in adults with CML and Ph+ ALL, and pediatric patients with CML.
2.3Dose Modification Strong CYP3A4 Inducers Avoid the use of concomitant strong CYP3A4 inducers and St. John’s wort. If patients must be coadministered a strong CYP3A4 inducer, consider a SPRYCEL dose increase.
If the dose of SPRYCEL is increased, monitor the patient carefully for toxicity [see Drug Interactions (7.1) ] . Strong CYP3A4 Inhibitors Avoid the use of concomitant strong CYP3A4 inhibitors and grapefruit juice. Recommend selecting an alternate concomitant medication with no or minimal enzyme inhibition potential, if possible.
If SPRYCEL must be administered with a strong CYP3A4 inhibitor, consider a dose decrease to: • 40 mg daily for patients taking SPRYCEL 140 mg daily. • 20 mg daily for patients taking SPRYCEL 100 mg daily. • 20 mg daily for patients taking SPRYCEL 70 mg daily. For patients taking SPRYCEL 60 mg or 40 mg daily, consider interrupting SPRYCEL until the inhibitor is discontinued. Allow a washout period of approximately 1 week after the inhibitor is stopped before reinitiating SPRYCEL.
These reduced doses of SPRYCEL are predicted to adjust the area under the curve (AUC) to the range observed without CYP3A4 inhibitors; however, clinical data are not available with these dose adjustments in patients receiving strong CYP3A4 inhibitors. If SPRYCEL is not tolerated after dose reduction, either discontinue the strong CYP3A4 inhibitor or interrupt SPRYCEL until the inhibitor is discontinued. Allow a washout period of approximately 1 week after the inhibitor is stopped before the SPRYCEL dose is increased [see Drug Interactions (7.1) ] .
2.4Dose Escalation in Adults with CML and Ph+ ALL, and Pediatric Patients with CML For adult patients with CML and Ph+ ALL, consider dose escalation to 140 mg once daily (chronic phase CML) or 180 mg once daily (advanced phase CML and Ph+ ALL) in patients who do not achieve a hematologic or cytogenetic response at the recommended starting dosage. For pediatric patients with CML, consider dose escalation to 120 mg once daily (see Tab…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS SPRYCEL (dasatinib) Tablets are available as 20-mg, 50-mg, 70-mg, 80-mg, 100-mg, and 140-mg white to off-white, biconvex, film-coated tablets. Tablets: 20 mg, 50 mg, 70 mg, 80 mg, 100 mg, and 140 mg. (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Myelosuppression and Bleeding Events: Severe thrombocytopenia, neutropenia, and anemia may occur. Use caution if used concomitantly with medications that inhibit platelet function or anticoagulants. Monitor complete blood counts regularly.
Transfuse and interrupt SPRYCEL when indicated. (2.5 , 5.1 , 5.2) • Fluid Retention: Fluid retention, sometimes severe, including pleural effusions. Manage with supportive care measures and/or dose modification.
(2.5 , 5.3) • Cardiovascular Toxicity: Monitor patients for signs or symptoms and treat appropriately. (5.4) • Pulmonary Arterial Hypertension (PAH): SPRYCEL may increase the risk of developing PAH which may be reversible on discontinuation. Consider baseline risk and evaluate patients for signs and symptoms of PAH during treatment.
Stop SPRYCEL if PAH is confirmed. (5.5) • QT Prolongation: Use SPRYCEL with caution in patients who have or may develop prolongation of the QT interval. (5.6) • Severe Dermatologic Reactions: Individual cases of severe mucocutaneous dermatologic reactions have been reported.
(5.7) • Tumor Lysis Syndrome: Tumor lysis syndrome has been reported. Maintain adequate hydration and correct uric acid levels prior to initiating therapy with SPRYCEL. (5.8) • Embryo-Fetal Toxicity: Can cause fetal harm.
Advise patients of reproductive potential of potential risk to fetus and to use effective contraception. (5.9 , 8.1 , 8.3) • Effects on Growth and Development in Pediatric Patients: epiphyses delayed fusion, osteopenia, growth retardation, and gynecomastia have been reported. Monitor bone growth and development in pediatric patients.
(5.10) • Hepatotoxicity: Assess liver function before initiation of treatment and monthly thereafter or as clinically indicated. Monitor liver function when combined with chemotherapy known to be associated with liver dysfunction. (5.11)
5.1Myelosuppression Treatment with SPRYCEL is associated with severe (NCI CTCAE Grade 3 or 4) thrombocytopenia, neutropenia, and anemia, which occur earlier and more frequently in patients with advanced phase CML or Ph+ ALL than in patients with chronic phase CML [see Adverse Reactions (6.1) ] . In patients with chronic phase CML, perform complete blood counts (CBCs) every 2 weeks for 12 weeks, then every 3 months thereafter, or as clinically indicated. In patients with advanced phase CML or Ph+ ALL, perform CBCs weekly for the first 2 months and then monthly thereafter, or as clinically indicated.
In pediatric patients with Ph+ ALL treated with SPRYCEL in combination with chemotherapy, perform CBCs prior to the start of each block of chemotherapy and as clinically indicated. During the consolidation blocks of chemotherapy, perform CBCs every 2 days until recovery. Myelosuppression is generally reversible and usually managed by withholding SPRYCEL temporarily and/or dose reduction [see Dosage and Administration (2.5) ] .
5.2Bleeding-Related Events SPRYCEL can cause serious and fatal bleeding. In all CML or Ph+ ALL clinical studies, Grade ≥3 central nervous system (CNS) hemorrhages, including fatalities, occurred in <1% of patients receiving SPRYCEL. The incidence of Grade 3/4 hemorrhage occurred in 5.8% of adult patients and generally required treatment interruptions and transfusions.
The incidence of Grade 5 hemorrhage occurred in 0.4% of adult patients. The most frequent site of hemorrhage was gastrointestinal [see Adverse Reactions (6.1) ] . Most bleeding events in clinical studies were associated with severe thrombocytopenia.
In addition to causing thrombocytopenia in human subjects, dasatinib caused platelet dysfunction in vitro . Concomitant medications that inhibit platelet function or anticoagulants may increase the risk of hemorrhage.
5.3Fluid Retention SPRYCEL may cause fluid retention [see Adverse Reactions (6.1) ] . After 5 years of follow-up in the adult randomized newly diagnosed chronic phase CML study (n=258), Grade 3 or 4 fluid retention was reported in 5%…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are discussed in greater detail in other sections of the labeling: • Myelosuppression [see Dosage and Administration (2.5) and Warnings and Precautions (5.1) ] . • Bleeding-related events [see Warnings and Precautions (5.2) ] . • Fluid retention [see Warnings and Precautions (5.3) ] . • Cardiovascular toxicity [see Warnings and Precautions (5.4) ] . • Pulmonary arterial hypertension [see Warnings and Precautions (5.5) ] . • QT prolongation [see Warnings and Precautions (5.6) ] . • Severe dermatologic reactions [see Warnings and Precautions (5.7) ] . • Tumor lysis syndrome [see Warnings and Precautions (5.8) ] . • Effects on growth and development in pediatric patients [see Warnings and Precautions (5.10) ] . • Hepatotoxicity [see Warnings and Precautions (5.11) ] .
Most common adverse reactions (≥15%) in patients receiving SPRYCEL as single-agent therapy included myelosuppression, fluid retention events, diarrhea, headache, skin rash, hemorrhage, dyspnea, fatigue, nausea, and musculoskeletal pain. (6) Most common adverse reactions (≥30%) in pediatric patients receiving SPRYCEL in combination with chemotherapy included mucositis, febrile neutropenia, pyrexia, diarrhea, nausea, vomiting, musculoskeletal pain, abdominal pain, cough, headache, rash, fatigue, constipation, arrhythmia, hypertension, edema, infections (bacterial, viral and fungal), hypotension, decreased appetite, hypersensitivity, dyspnea, epistaxis, peripheral neuropathy, and altered state of consciousness.
(6) To report SUSPECTED ADVERSE REACTIONS, contact Bristol-Myers Squibb at 1-800-721-5072 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The data described below reflect exposure to SPRYCEL administered as single-agent therapy at all doses tested in clinical studies (n=2809), including 324 adult patients with newly diagnosed chronic phase CML, 2388 adult patients with imatinib-resistant or -intolerant chronic or advanced phase CML or Ph+ ALL, and 97 pediatric patients with chronic phase CML.
The median duration of therapy in a total of 2712 adult patients was 19.2 months (range 0 to 93.2 months). In a randomized trial in patients with newly diagnosed chronic phase CML, the median duration of therapy was approximately 60 months. The median duration of therapy in 1618 adult patients with chronic phase CML was 29 months (range 0 to 92.9 months).
The median duration of therapy in 1094 adult patients with advanced phase CML or Ph+ ALL was 6.2 months (range 0 to 93.2 months). In two non-randomized trials in 97 pediatric patients with chronic phase CML (51 patients newly diagnosed and 46 patients resistant or intolerant to previous treatment with imatinib), the median duration of therapy was 51.1 months (range 1.9 to 99.6 months). In the overall population of 2712 adult patients, 88% of patients experienced adverse reactions at some time and 19% experienced adverse reactions leading to treatment discontinuation.
In the randomized trial in adult patients with newly diagnosed chronic phase CML, drug was discontinued for adverse reactions in 16% of patients with a minimum of 60 months of follow-up. After a minimum of 60 months of follow-up, the cumulative discontinuation rate was 39%. Among the 1618 patients with chronic phase CML, drug-related adverse reactions leading to discontinuation were reported in 329 (20.3%) patients; among the 1094 patients with advanced phase CML or Ph+ ALL, drug-related adverse reactions leading to discontinuation were reported in 191 (17.5%) patients.
Among the 97 pediatric subjects, drug-related adverse reactions leading to discontinuation were reported in 1 patient (1%). Ad…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Strong CYP3A4 Inhibitors: Dose reduction may be necessary. (2.3 , 7.1) • Strong CYP3A4 Inducers: Dose increase may be necessary. (2.3 , 7.1) • Antacids: Avoid simultaneous administration. (7.1) • H 2 Antagonists and Proton Pump Inhibitors: Avoid coadministration. (7.1)
7.1Effect of Other Drugs on Dasatinib Strong CYP3A4 Inhibitors The coadministration with strong CYP3A inhibitors may increase dasatinib concentrations [see Clinical Pharmacology (12.3) ] . Increased dasatinib concentrations may increase the risk of toxicity. Avoid concomitant use of strong CYP3A4 inhibitors.
If concomitant administration of a strong CYP3A4 inhibitor cannot be avoided, consider a SPRYCEL dose reduction [see Dosage and Administration (2.5) ] . Strong CYP3A4 Inducers The coadministration of SPRYCEL with strong CYP3A inducers may decrease dasatinib concentrations [see Clinical Pharmacology (12.3) ] . Decreased dasatinib concentrations may reduce efficacy.
Consider alternative drugs with less enzyme induction potential. If concomitant administration of a strong CYP3A4 inducer cannot be avoided, consider a SPRYCEL dose increase. Gastric Acid Reducing Agents The coadministration of SPRYCEL with a gastric acid reducing agent may decrease the concentrations of dasatinib.
Decreased dasatinib concentrations may reduce efficacy. Do not administer H 2 antagonists or proton pump inhibitors with SPRYCEL. Consider the use of antacids in place of H 2 antagonists or proton pump inhibitors.
Administer the antacid at least 2 hours prior to or 2 hours after the dose of SPRYCEL. Avoid simultaneous administration of SPRYCEL with antacids.
7.2Effect of Dasatinib on Other Drugs Methotrexate SPRYCEL may delay the clearance of methotrexate and result in sustained methotrexate concentrations when methotrexate is used at high doses (> 500 mg/m 2 ). Refer to the prescribing information for methotrexate injection for recommendations on management of methotrexate concentrations.
7.1Effect of Other Drugs on Dasatinib Strong CYP3A4 Inhibitors The coadministration with strong CYP3A inhibitors may increase dasatinib concentrations [see Clinical Pharmacology (12.3) ] . Increased dasatinib concentrations may increase the risk of toxicity. Avoid concomitant use of strong CYP3A4 inhibitors.
If concomitant administration of a strong CYP3A4 inhibitor cannot be avoided, consider a SPRYCEL dose reduction [see Dosage and Administration (2.5) ] . Strong CYP3A4 Inducers The coadministration of SPRYCEL with strong CYP3A inducers may decrease dasatinib concentrations [see Clinical Pharmacology (12.3) ] . Decreased dasatinib concentrations may reduce efficacy.
Consider alternative drugs with less enzyme induction potential. If concomitant administration of a strong CYP3A4 inducer cannot be avoided, consider a SPRYCEL dose increase. Gastric Acid Reducing Agents The coadministration of SPRYCEL with a gastric acid reducing agent may decrease the concentrations of dasatinib.
Decreased dasatinib concentrations may reduce efficacy. Do not administer H 2 antagonists or proton pump inhibitors with SPRYCEL. Consider the use of antacids in place of H 2 antagonists or proton pump inhibitors.
Administer the antacid at least 2 hours prior to or 2 hours after the dose of SPRYCEL. Avoid simultaneous administration of SPRYCEL with antacids.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Lactation: Advise women not to breastfeed. (8.2)
8.1Pregnancy Risk Summary Based on limited human data, SPRYCEL can cause fetal harm when administered to a pregnant woman. Adverse pharmacologic effects including hydrops fetalis, fetal leukopenia, and fetal thrombocytopenia have been reported with maternal exposure to SPRYCEL. Animal reproduction studies in rats have demonstrated extensive mortality during organogenesis, the fetal period, and in neonates.
Skeletal malformations were observed in a limited number of surviving rat and rabbit conceptuses. These findings occurred at dasatinib plasma concentrations below those in humans receiving therapeutic doses of dasatinib [see Data] . Advise a pregnant woman of the potential risk to a fetus.
The estimated background risk in the U.S. general population of major birth defects is 2% to 4% and of miscarriage is 15% to 20% of clinically recognized pregnancies. Clinical Considerations Fetal/Neonatal Adverse Reactions Transplacental transfer of dasatinib has been reported. Dasatinib has been measured in fetal plasma and amniotic fluid at concentrations comparable to those in maternal plasma.
Hydrops fetalis, fetal leukopenia, and fetal thrombocytopenia have been reported with maternal exposure to dasatinib. These adverse pharmacologic effects on the fetus are similar to adverse reactions observed in adult patients and may result in fetal harm or neonatal death [see Warnings and Precautions (5.1 , 5.3) ] . Data Human Data Based on human experience, dasatinib is suspected to cause congenital malformations, including neural tube defects, and harmful pharmacological effects on the fetus when administered during pregnancy.
Animal Data In nonclinical studies at plasma concentrations below those observed in humans receiving therapeutic doses of dasatinib, embryo-fetal toxicities were observed in rats and rabbits. Fetal death was observed in rats. In both rats and rabbits, the lowest doses of dasatinib tested (rat: 2.5 mg/kg/day [15 mg/m 2 /day] and rabbit: 0.5 mg/kg/day [6 mg/m 2 /day]) resulted in embryo-fetal toxicities.
These doses produced maternal AUCs of 105 ng•h/mL and 44 ng•h/mL (0.1-fold the human AUC) in rats and rabbits, respectively. Embryo-fetal toxicities included skeletal malformations at multiple sites (scapula, humerus, femur, radius, ribs, and clavicle), reduced ossification (sternum; thoracic, lumbar, and sacral vertebrae; forepaw phalanges; pelvis; and hyoid body), edema, and microhepatia. In a pre- and postnatal development study in rats, administration of dasatinib from gestation day (GD) 16 through lactation day (LD) 20, GD 21 through LD 20, or LD 4 through LD 20 resulted in extensive pup mortality at maternal exposures that were below the exposures in patients treated with dasatinib at the recommended labeling dose.
8.2Lactation Risk Summary No data are available regarding the presence of dasatinib in human milk, the effects of the drug on the breastfed child, or the effects of the drug on milk production. However, dasatinib is present in the milk of lactating rats. Because of the potential for serious adverse reactions in nursing children from SPRYCEL, breastfeeding is not recommended during treatment with SPRYCEL and for 2 weeks after the last dose.
8.3Females and Males of Reproductive Potential SPRYCEL can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ] . Contraception Advise females of reproductive potential and males with female partners of reproductive potential to use effective contraception during treatment with SPRYCEL and for 30 days after the last dose. Infertility Based on animal data, dasatinib may result in damage to female and male reproductive tissues [see Nonclinical Toxicology (13.1) ] .
8.4Pediatric Use Ph+ CML in Chronic Phase The safety and effectiveness of SPRYCEL monotherapy have been demonstrated in pediatric patients with newly diagnosed chronic phase CML [see C…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on limited human data, SPRYCEL can cause fetal harm when administered to a pregnant woman. Adverse pharmacologic effects including hydrops fetalis, fetal leukopenia, and fetal thrombocytopenia have been reported with maternal exposure to SPRYCEL. Animal reproduction studies in rats have demonstrated extensive mortality during organogenesis, the fetal period, and in neonates.
Skeletal malformations were observed in a limited number of surviving rat and rabbit conceptuses. These findings occurred at dasatinib plasma concentrations below those in humans receiving therapeutic doses of dasatinib [see Data] . Advise a pregnant woman of the potential risk to a fetus.
The estimated background risk in the U.S. general population of major birth defects is 2% to 4% and of miscarriage is 15% to 20% of clinically recognized pregnancies. Clinical Considerations Fetal/Neonatal Adverse Reactions Transplacental transfer of dasatinib has been reported. Dasatinib has been measured in fetal plasma and amniotic fluid at concentrations comparable to those in maternal plasma.
Hydrops fetalis, fetal leukopenia, and fetal thrombocytopenia have been reported with maternal exposure to dasatinib. These adverse pharmacologic effects on the fetus are similar to adverse reactions observed in adult patients and may result in fetal harm or neonatal death [see Warnings and Precautions (5.1 , 5.3) ] . Data Human Data Based on human experience, dasatinib is suspected to cause congenital malformations, including neural tube defects, and harmful pharmacological effects on the fetus when administered during pregnancy.
Animal Data In nonclinical studies at plasma concentrations below those observed in humans receiving therapeutic doses of dasatinib, embryo-fetal toxicities were observed in rats and rabbits. Fetal death was observed in rats. In both rats and rabbits, the lowest doses of dasatinib tested (rat: 2.5 mg/kg/day [15 mg/m 2 /day] and rabbit: 0.5 mg/kg/day [6 mg/m 2 /day]) resulted in embryo-fetal toxicities.
These doses produced maternal AUCs of 105 ng•h/mL and 44 ng•h/mL (0.1-fold the human AUC) in rats and rabbits, respectively. Embryo-fetal toxicities included skeletal malformations at multiple sites (scapula, humerus, femur, radius, ribs, and clavicle), reduced ossification (sternum; thoracic, lumbar, and sacral vertebrae; forepaw phalanges; pelvis; and hyoid body), edema, and microhepatia. In a pre- and postnatal development study in rats, administration of dasatinib from gestation day (GD) 16 through lactation day (LD) 20, GD 21 through LD 20, or LD 4 through LD 20 resulted in extensive pup mortality at maternal exposures that were below the exposures in patients treated with dasatinib at the recommended labeling dose.
🧒 Pediatric Use ▾
8.4Pediatric Use Ph+ CML in Chronic Phase The safety and effectiveness of SPRYCEL monotherapy have been demonstrated in pediatric patients with newly diagnosed chronic phase CML [see Clinical Studies (14.3) ] . There are no data in children under 1 year of age. Adverse reactions associated with bone growth and development were reported in 5 (5.2%) of patients [see Warnings and Precautions (5.10) ] .
Ph+ ALL The safety and effectiveness of SPRYCEL in combination with chemotherapy have been demonstrated in pediatric patients one year and over with newly diagnosed Ph+ ALL. Use of SPRYCEL in pediatric patients is supported by evidence from one pediatric study. There are no data in children under 1 year of age.
One case of grade 1 osteopenia was reported. The safety profile of SPRYCEL in pediatric subjects was comparable to that reported in studies in adult subjects [see Adverse Reactions (6.1) and Clinical Studies (14.3 , 14.4) ] . Monitor bone growth and development in pediatric patients [see Warnings and Precautions (5.10) ] .
Pediatric Patients with Difficulty Swallowing Tablets Five patients with Ph+ ALL 2 to 10 years of age received at least one dose of SPRYCEL tablet dispersed in juice on Study CA180372. The exposure for dispersed tablets was 36% lower as compared to intact tablets in pediatric patients [see Clinical Pharmacology (12.3) ] . Due to the limited available clinical data, it is unclear whether dispersing SPRYCEL tablets significantly alters the safety and/or efficacy of SPRYCEL.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 2712 patients in clinical studies of SPRYCEL, 617 (23%) were 65 years of age and older, and 123 (5%) were 75 years of age and older. No differences in confirmed Complete Cytogenetic Response (cCCyR) and MMR were observed between older and younger patients. While the safety profile of SPRYCEL in the geriatric population was similar to that in the younger population, patients aged 65 years and older are more likely to experience the commonly reported adverse reactions of fatigue, pleural effusion, diarrhea, dyspnea, cough, lower gastrointestinal hemorrhage, and appetite disturbance, and more likely to experience the less frequently reported adverse reactions of abdominal distention, dizziness, pericardial effusion, congestive heart failure, hypertension, pulmonary edema, and weight decrease, and should be monitored closely.
🆘 Overdosage ▾
10 OVERDOSAGE Experience with overdose of SPRYCEL in clinical studies is limited to isolated cases. The highest overdosage of 280 mg per day for 1 week was reported in two patients and both developed severe myelosuppression and bleeding. Since SPRYCEL is associated with severe myelosuppression [see Warnings and Precautions (5.1) and Adverse Reactions (6.1) ] , monitor patients who ingest more than the recommended dosage closely for myelosuppression and give appropriate supportive treatment.
Acute overdose in animals was associated with cardiotoxicity. Evidence of cardiotoxicity included ventricular necrosis and valvular/ventricular/atrial hemorrhage at single doses ≥100 mg/kg (600 mg/m 2 ) in rodents. There was a tendency for increased systolic and diastolic blood pressure in monkeys at single doses ≥10 mg/kg (120 mg/m 2 ).
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Dasatinib, at nanomolar concentrations, inhibits the following kinases: BCR-ABL, SRC family (SRC, LCK, YES, FYN), c-KIT, EPHA2, and PDGFRβ. Based on modeling studies, dasatinib is predicted to bind to multiple conformations of the ABL kinase. In vitro , dasatinib was active in leukemic cell lines representing variants of imatinib mesylate-sensitive and resistant disease.
Dasatinib inhibited the growth of chronic myeloid leukemia (CML) and acute lymphoblastic leukemia (ALL) cell lines overexpressing BCR-ABL. Under the conditions of the assays, dasatinib could overcome imatinib resistance resulting from BCR-ABL kinase domain mutations, activation of alternate signaling pathways involving the SRC family kinases (LYN, HCK), and multi-drug resistance gene overexpression.
12.2Pharmacodynamics Cardiac Electrophysiology Of 2440 patients treated with SPRYCEL at all doses tested in clinical trials, 16 patients (<1%) had QTc prolongation reported as an adverse reaction. Twenty-two patients (1%) experienced a QTcF > 500 ms. In 865 patients with leukemia treated with SPRYCEL 70 mg BID in five Phase 2 studies, the maximum mean changes in QTcF (90% upper bound CI) from baseline ranged from 7 ms to 13.4 ms.
An analysis of the data from five Phase 2 studies in patients (70 mg BID) and a Phase 1 study in healthy subjects (100 mg single dose) suggests that there is a maximum increase of 3 to 6 milliseconds in Fridericia corrected QTc interval from baseline for subjects receiving therapeutic doses of dasatinib, with associated upper 95% confidence intervals <10 msec.
12.3Pharmacokinetics The pharmacokinetics of dasatinib exhibits dose proportional increases in AUC and linear elimination characteristics over the dose range of 15 mg/day (0.15 times the lowest approved recommended dose) to 240 mg/day (1.7 times the highest approved recommended dose). At 100 mg QD, the maximum concentration at steady state (C max ) is 82.2 ng/mL (CV% 69%), area under the plasma drug concentration time curve (AUC) is 397 ng/mL*hr (CV% 55%). The clearance of dasatinib is found to be time-invariant.
When administered to adult healthy subjects as dispersed tablets in juice, the adjusted geometric mean ratio was 0.97 (90% CI: 0.85, 1.10) for C max and 0.84 (90% CI: 0.78, 0.91) for AUC as compared to intact tablets. Absorption The maximum plasma concentrations (C max ) of dasatinib are observed between 0.5 hours and 6 hours (T max ) following oral administration. Food Effect A high-fat meal increased the mean AUC of dasatinib following a single dose of 100 mg by 14%.
The total calorie content of the high-fat meal was 985 kcal. The calories derived from fat, carbohydrates, and protein were 52%, 34%, and 14% for the high-fat meal. Distribution The apparent volume of distribution is 2505 L (CV% 93%).
Binding of dasatinib to human plasma proteins in vitro was approximately 96% and of its active metabolite was 93%, with no concentration dependence over the range of 100 ng/mL to 500 ng/mL. Dasatinib is a P-gp substrate in vitro . Elimination The mean terminal half-life of dasatinib is 3 hours to 5 hours.
The mean apparent oral clearance is 363.8 L/hr (CV% 81.3%). Metabolism Dasatinib is metabolized in humans, primarily by CYP3A4. CYP3A4 is the primary enzyme responsible for the formation of the active metabolite.
Flavin-containing monooxygenase 3 (FMO-3) and uridine diphosphate-glucuronosyltransferase (UGT) enzymes are also involved in the formation of dasatinib metabolites. The exposure of the active metabolite, which is equipotent to dasatinib, represents approximately 5% of the AUC of dasatinib. The active metabolite of dasatinib is unlikely to play a major role in the observed pharmacology of the drug.
Dasatinib also has several other inactive oxidative metabolites. Excretion Elimination is primarily via the feces. Following a single radiolabeled dose of oral dasatinib, 4% of the administered radioactivity was recovered in…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Dasatinib, at nanomolar concentrations, inhibits the following kinases: BCR-ABL, SRC family (SRC, LCK, YES, FYN), c-KIT, EPHA2, and PDGFRβ. Based on modeling studies, dasatinib is predicted to bind to multiple conformations of the ABL kinase. In vitro , dasatinib was active in leukemic cell lines representing variants of imatinib mesylate-sensitive and resistant disease.
Dasatinib inhibited the growth of chronic myeloid leukemia (CML) and acute lymphoblastic leukemia (ALL) cell lines overexpressing BCR-ABL. Under the conditions of the assays, dasatinib could overcome imatinib resistance resulting from BCR-ABL kinase domain mutations, activation of alternate signaling pathways involving the SRC family kinases (LYN, HCK), and multi-drug resistance gene overexpression.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied SPRYCEL ® (dasatinib) tablets are available as described in Table 21. Table 21: SPRYCEL Trade Presentations NDC Number Strength Description Tablets per Bottle 0003-0527-11 20 mg white to off-white, biconvex, round, film-coated tablet with “BMS” debossed on one side and “527” on the other side 60 0003-0528-11 50 mg white to off-white, biconvex, oval, film-coated tablet with “BMS” debossed on one side and “528” on the other side 60 0003-0524-11 70 mg white to off-white, biconvex, round, film-coated tablet with “BMS” debossed on one side and “524” on the other side 60 0003-0855-22 80 mg white to off-white, biconvex, triangle, film-coated tablet with “BMS” and “80” (BMS over 80) debossed on one side and “855” on the other side 30 0003-0852-22 100 mg white to off-white, biconvex, oval, film-coated tablet with “BMS 100” debossed on one side and “852” on the other side 30 0003-0857-22 140 mg white to off-white, biconvex, round, film-coated tablet with “BMS” and “140” (BMS over 140) debossed on one side and “857” on the other side 30 Storage SPRYCEL tablets should be stored at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C and 30°C (59°F and 86°F) [see USP Controlled Room Temperature].
Handling and Disposal SPRYCEL is an antineoplastic product. Follow special handling and disposal procedures. 1 Personnel who are pregnant should avoid exposure to crushed or broken tablets.
SPRYCEL tablets consist of a core tablet, surrounded by a film coating to prevent exposure of healthcare professionals to the active substance. The use of latex or nitrile gloves for appropriate disposal when handling tablets that are inadvertently crushed or broken is recommended, to minimize the risk of dermal exposure.
📋 Description ▾
11 DESCRIPTION SPRYCEL (dasatinib) is a kinase inhibitor. The chemical name for dasatinib is N-(2-chloro-6-methylphenyl)-2-[[6-[4-(2-hydroxyethyl)-1-piperazinyl]-2-methyl-4-pyrimidinyl]amino]-5-thiazolecarboxamide, monohydrate. The molecular formula is C 22 H 26 ClN 7 O 2 S • H 2 O, which corresponds to a formula weight of 506.02 (monohydrate).
The anhydrous free base has a molecular weight of 488.01. Dasatinib has the following chemical structure: Dasatinib is a white to off-white powder. The drug substance is insoluble in water and slightly soluble in ethanol and methanol.
SPRYCEL tablets are white to off-white, biconvex, film-coated tablets containing dasatinib, with the following inactive ingredients: lactose monohydrate, microcrystalline cellulose, croscarmellose sodium, hydroxypropyl cellulose, and magnesium stearate. The tablet coating consists of hypromellose, titanium dioxide, and polyethylene glycol. dasatinib-struct.jpg
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Myelosuppression Inform patients of the possibility of developing low blood cell counts. Advise patients to immediately report fever particularly in association with any suggestion of infection [see Warnings and Precautions (5.1) ] .
Bleeding Inform patients of the possibility of serious bleeding and to report immediately any signs or symptoms suggestive of hemorrhage (unusual bleeding or easy bruising) [see Warnings and Precautions (5.2) ] . Fluid Retention Patients should be informed of the possibility of developing fluid retention (swelling, weight gain, dry cough, chest pain on respiration, or shortness of breath) and advised to seek medical attention promptly if those symptoms arise [see Warnings and Precautions (5.3) ] . Cardiovascular Toxicity Inform patients of the possibility of developing cardiovascular toxicity, including cardiac ischemic events, cardiac-related fluid retention, conduction abnormalities, and TIAs.
Advise patients to seek immediate medical attention if symptoms suggestive of cardiovascular toxicity occur, such as chest pain, shortness of breath, palpitations, transient vision problems, or slurred speech [see Warnings and Precautions (5.4) ] . Pulmonary Arterial Hypertension Inform patients of the possibility of developing pulmonary arterial hypertension (dyspnea, fatigue, hypoxia, and fluid retention) and advise them to seek medical attention promptly if those symptoms arise [see Warnings and Precautions (5.5) ] .
Tumor Lysis Syndrome Inform patients to immediately report and seek medical attention for any symptoms such as nausea, vomiting, weakness, edema, shortness of breath, muscle cramps, and seizures, which may indicate tumor lysis syndrome [see Warnings and Precautions (5.8) ] . Growth and Development in Pediatric Patients Inform pediatric patients and their caregivers of the possibility of developing bone growth abnormalities, bone pain, or gynecomastia and advise them to seek medical attention promptly if those symptoms arise [see Warnings and Precautions (5.10) ] .
Embryo-Fetal Toxicity • Advise pregnant women of the potential risk to a fetus [see Warnings and Precautions (5.9) and Use in Specific Populations (8.1) ] . • Advise females of reproductive potential and males with female partners of reproductive potential to use effective contraception during treatment with SPRYCEL and for 30 days after the last dose. Advise females to contact their healthcare provider if they become pregnant, or if pregnancy is suspected, while taking SPRYCEL [see Warnings and Precautions (5.9) and Use in Specific Populations (8.1 , 8.3) ] .
Lactation • Advise women that breastfeeding is not recommended during treatment with SPRYCEL and for 2 weeks after the final dose [see Use in Specific Populations (8.2) ] . Gastrointestinal Complaints Inform patients that they may experience nausea, vomiting, or diarrhea with SPRYCEL. Advise patients to seek medical attention if these symptoms are bothersome or persistent.
Advise patients using antacids to avoid taking SPRYCEL and antacids less than 2 hours apart [see Drug Interactions (7.1) ] . Pain Inform patients that they may experience headache or musculoskeletal pain with SPRYCEL. Advise patients to seek medical attention if these symptoms are bothersome or persistent.
Fatigue Inform patients that they may experience fatigue with SPRYCEL. Advise patients to seek medical attention if this symptom is bothersome or persistent. Rash Inform patients that they may experience skin rash with SPRYCEL.
Advise patients to seek medical attention if this symptom is bothersome or persistent. Lactose Inform patients that SPRYCEL contains 135 mg of lactose monohydrate in a 100-mg daily dose and 189 mg of lactose monohydrate in a 140-mg daily dose. Hepatotoxicity Advise patients that SPRYCEL can cause hepatotoxicity and that patients with previous history of liver disea…