
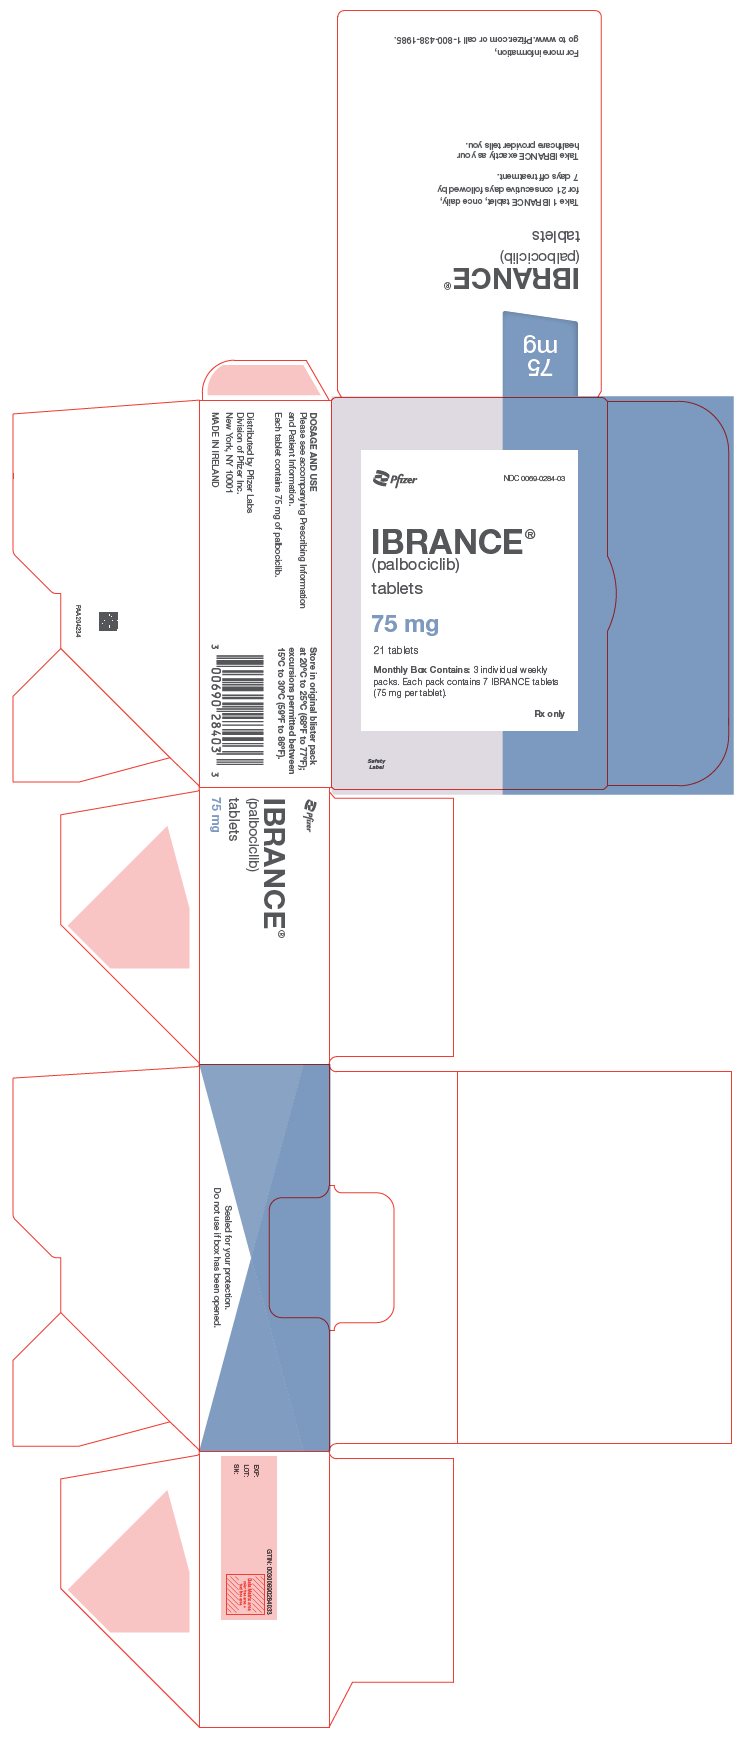
Ibrance palbociclib 75 mg Tablet, Film Coated
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Kinase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Palbociclib is not traditional chemotherapy. It's a targeted therapy that works specifically on proteins called CDK4 and CDK6, which breast cancer cells need in order to divide and...
- What exactly is palbociclib (Ibrance) treating — is it a chemotherapy?
- Palbociclib very commonly lowers your white blood cell count — especially the neutrophils that fight bacterial infections. Low neutrophils can leave you vulnerable to serious infec...
- Why do I need blood tests so often while taking this medicine?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Palbociclib — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII AB6MNQ6J6L
Succinic acid is an organic acid derived from natural sources or chemical synthesis. In medications, it functions as a buffer to help maintain the proper pH level and may also serve as a preservative or flavor enhancer in formulations.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $782.67 | $16,436.10 / 21 tablets |
| Medicare drug plans payPart D · Q2 2026 | $785.69 | $16,499.51 / 21 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ibrance 75 mgthis 00069-0284-03 | Pfizer | 7 tablets | — | — | FDA listed | — |
| Ibrance 75 mg 63539-0284-03 | U.S. | 7 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 10723730 ↗ | Drug substance | — | Feb 8, 2034 |
| US RE47739 ↗ | Drug substance | — | Mar 5, 2027 |
| US RE47739 ↗ | Drug substance | — | Mar 5, 2027 |
| US 10723730 ↗ | Drug substance | — | Feb 8, 2034 |
| US 11065250 ↗ | Drug product | — | Aug 19, 2036 |
| US RE47739 ↗ | Drug substance | — | Mar 5, 2027 |
| US 11065250 ↗ | Drug product | — | Aug 19, 2036 |
| US 11065250 ↗ | Drug product | — | Aug 19, 2036 |
| US 10723730 ↗ | Drug substance | — | Feb 8, 2034 |
| US RE47739*PED ↗ | Drug product | — | Sep 5, 2027 |
| US RE47739*PED ↗ | Drug product | — | Sep 5, 2027 |
| US RE47739*PED ↗ | Drug product | — | Sep 5, 2027 |
| US 10723730*PED ↗ | Drug product | — | Aug 8, 2034 |
| US 10723730*PED ↗ | Drug product | — | Aug 8, 2034 |
| US 10723730*PED ↗ | Drug product | — | Aug 8, 2034 |
| US 11065250*PED ↗ | Drug product | — | Feb 19, 2037 |
| US 11065250*PED ↗ | Drug product | — | Feb 19, 2037 |
| US 11065250*PED ↗ | Drug product | — | Feb 19, 2037 |
| Code | What it grants | Expires |
|---|---|---|
| I-995 | New indication (3-year) | Jun 24, 2029 |
| M-14 | New indication / labeling change (3-year) | Sep 16, 2028 |
| I-995 | New indication (3-year) | Jun 24, 2029 |
| M-14 | New indication / labeling change (3-year) | Sep 16, 2028 |
| I-995 | New indication (3-year) | Jun 24, 2029 |
| M-14 | New indication / labeling change (3-year) | Sep 16, 2028 |
| PED | Pediatric Exclusivity (+6 months) | Mar 16, 2029 |
| PED | Pediatric Exclusivity (+6 months) | Mar 16, 2029 |
| PED | Pediatric Exclusivity (+6 months) | Mar 16, 2029 |
Is there a generic version of IBRANCE 75 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00069-0284-03 You're viewing this | 3 DOSE PACK in 1 CARTON (0069-0284-03) / 7 TABLET, FILM COATED in 1 DOSE PACK (0069-0284-07) | 2020-03-30 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE IBRANCE is a kinase inhibitor indicated: • for the treatment of adult patients with hormone receptor (HR)-positive, human epidermal growth factor receptor 2 (HER2)-negative advanced or metastatic breast cancer in combination with: o an aromatase inhibitor as initial endocrine-based therapy ( 1.1 ); or o fulvestrant in patients with disease progression following endocrine therapy. ( 1.1 ) • in combination with inavolisib and fulvestrant for the treatment of adult patients with endocrine-resistant, PIK3CA -mutated, HR-positive, HER2-negative, locally advanced or metastatic breast cancer, as detected by an FDA‑authorized test, following recurrence on or after completing adjuvant endocrine therapy.
( 1.1 ) • in combination with trastuzumab, with or without pertuzumab, and endocrine therapy for the maintenance treatment of adult patients with HR-positive, HER2‑positive locally advanced or metastatic breast cancer following induction treatment. ( 1.2 )
1.1HER2-Negative Metastatic Breast Cancer IBRANCE is indicated for the treatment of adult patients with hormone receptor (HR)-positive, human epidermal growth factor receptor 2 (HER2)-negative advanced or metastatic breast cancer in combination with: • an aromatase inhibitor as initial endocrine-based therapy; or • fulvestrant in patients with disease progression following endocrine therapy. IBRANCE is indicated in combination with inavolisib and fulvestrant for the treatment of adult patients with endocrine-resistant, PIK3CA -mutated, HR-positive, HER2-negative, locally advanced or metastatic breast cancer, as detected by an FDA- authorized test, following recurrence on or after completing adjuvant endocrine therapy.
1.2HER2-Positive Metastatic Breast Cancer IBRANCE is indicated in combination with trastuzumab, with or without pertuzumab, and endocrine therapy for the maintenance treatment of adult patients with HR-positive, HER2-positive locally advanced or metastatic breast cancer following induction treatment.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Recommended starting dose: 125 mg once daily taken with or without food for 21 days followed by 7 days off treatment. ( 2.1 ) • Dosing interruption and/or dose reductions are recommended based on individual safety and tolerability. ( 2.2 )
2.1Recommended Dosage The recommended dosage of IBRANCE is a 125 mg tablet taken orally once daily for 21 consecutive days followed by 7 days off treatment to comprise a complete cycle of 28 days. IBRANCE tablet may be taken with or without food [see Clinical Pharmacology (12.3) ] . Advise patients to take their dose of IBRANCE at approximately the same time each day.
If the patient vomits or misses a dose, an additional dose should not be taken. The next prescribed dose should be taken at the usual time. IBRANCE tablets should be swallowed whole (do not chew, crush, or split them prior to swallowing).
Tablets should not be ingested if they are broken, cracked, or otherwise not intact. Pre/perimenopausal women treated with the combination IBRANCE plus an aromatase inhibitor or fulvestrant, IBRANCE plus inavolisib and fulvestrant therapy, or IBRANCE plus trastuzumab, with or without pertuzumab, plus endocrine therapy should also be treated with luteinizing hormone-releasing hormone (LHRH) agonists according to current clinical practice standards. For men treated with combination IBRANCE plus aromatase inhibitor, IBRANCE plus inavolisib and fulvestrant therapy, or IBRANCE plus trastuzumab, with or without pertuzumab, plus endocrine therapy, consider treatment with an LHRH agonist according to current clinical practice standards.
Refer to the Prescribing Information for recommended dosage for endocrine therapy, inavolisib, trastuzumab and pertuzumab administered in combination with IBRANCE.
2.2Dose Modification The recommended dose modifications for adverse reactions are listed in Tables 1, 2, and 3. Table 1. Recommended Dose Modification for Adverse Reactions Dose Level Dose Recommended starting dose 125 mg/day First dose reduction 100 mg/day Second dose reduction 75 mg/day If further dose reduction below 75 mg/day is required, discontinue.
Table 2. Dose Modification and Management – Hematologic Toxicities Table applies to all hematologic adverse reactions except lymphopenia (unless associated with clinical events, e.g., opportunistic infections). Grading according to CTCAE 4.0.
CTCAE=Common Terminology Criteria for Adverse Events; LLN=lower limit of normal. Monitor complete blood counts prior to the start of IBRANCE therapy and at the beginning of each cycle, as well as on Day 15 of the first 2 cycles, and as clinically indicated. For patients who experience a maximum of Grade 1 or 2 neutropenia in the first 6 cycles, monitor complete blood counts for subsequent cycles every 3 months, prior to the beginning of a cycle and as clinically indicated.
CTCAE Grade Dose Modifications Grade 1 or 2 No dose adjustment is required. Grade 3 Day 1 of cycle : Withhold IBRANCE, repeat complete blood count monitoring within 1 week. When recovered to Grade ≤2, start the next cycle at the same dose .
Day 15 of first 2 cycles : If Grade 3 on Day 15, continue IBRANCE at current dose to complete cycle and repeat complete blood count on Day 22. If Grade 4 on Day 22, see Grade 4 dose modification guidelines below. Consider dose reduction in cases of prolonged (>1 week) recovery from Grade 3 neutropenia or recurrent Grade 3 neutropenia on Day 1 of subsequent cycles.
Grade 3 neutropenia Absolute neutrophil count (ANC): Grade 1: ANC < LLN – 1500/mm 3 ; Grade 2: ANC 1000 – <1500/mm 3 ; Grade 3: ANC 500 – <1000/mm 3 ; Grade 4: ANC <500/mm 3 . with fever ≥38.5 °C and/or infection At any time : Withhold IBRANCE until recovery to Grade ≤2. Resume at the next lower dose . Grade 4 At any time : Withhold IBRANCE until recovery to Grade ≤2.
Resume at the next lower dose . Table 3. Dose Modification and Management – Non-Hematologic Toxicities Grading according to CTCAE 4.0.
CTCAE=Common Terminolo…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 125 mg tablets: Oval, light purple, film-coated tablets debossed with "Pfizer" on one side and "PBC 125" on the other side. 100 mg tablets: Oval, green, film-coated tablets debossed with "Pfizer" on one side and "PBC 100" on the other side. 75 mg tablets: Round, light purple, film-coated tablets debossed with "Pfizer" on one side and "PBC 75" on the other side. Tablets: 125 mg, 100 mg, and 75 mg. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Neutropenia: Monitor complete blood count prior to start of IBRANCE therapy and at the beginning of each cycle, as well as on Day 15 of the first 2 cycles, and as clinically indicated. ( 2.2 , 5.1 ) • Interstitial Lung Disease (ILD)/Pneumonitis: Severe and fatal cases of ILD/pneumonitis have been reported. Monitor for pulmonary symptoms of ILD/pneumonitis.
Interrupt IBRANCE immediately in patients with suspected ILD/pneumonitis. Permanently discontinue IBRANCE if severe ILD/pneumonitis occurs. ( 5.2 ) • Embryo-Fetal Toxicity: IBRANCE can cause fetal harm.
Advise patients of potential risk to a fetus and to use effective contraception. ( 5.3 , 8.1 , 8.3 )
5.1Neutropenia Neutropenia was the most frequently reported adverse reaction in PALOMA-2 with an incidence of 80% and PALOMA-3 with an incidence of 83%. A Grade ≥3 decrease in neutrophil counts was reported in 66% of patients receiving IBRANCE plus letrozole in PALOMA-2 and 66% of patients receiving IBRANCE plus fulvestrant in PALOMA-3. In PALOMA-2 and PALOMA-3, the median time to first episode of any grade neutropenia was 15 days and the median duration of Grade ≥3 neutropenia was 7 days [see Adverse Reactions (6.1) ] .
Neutropenia was the most frequently reported adverse reaction in PATINA with an incidence of 78%. Grade ≥3 neutropenia was reported in 61% of patients receiving IBRANCE in combination with trastuzumab, with or without pertuzumab, and endocrine therapy. Based on laboratory findings, 93% had a decrease in neutrophil counts including 47% with Grade 3 and 3.1% with Grade 4.
The median time to first episode of any grade neutropenia was 22 days and the median duration of Grade ≥3 neutropenia events was 9 days [see Adverse Reactions (6.1) ] . Monitor complete blood counts prior to starting IBRANCE therapy and at the beginning of each cycle, as well as on Day 15 of the first 2 cycles, and as clinically indicated. Dose interruption, dose reduction, or delay in starting treatment cycles is recommended for patients who develop Grade 3 or 4 neutropenia [see Dosage and Administration (2.2) ] .
Febrile neutropenia has been reported in 1.8% of patients exposed to IBRANCE across PALOMA-2 and PALOMA-3. One death due to neutropenic sepsis was observed in PALOMA-3. Febrile neutropenia has been reported in 0.8% of patients exposed to IBRANCE in the PATINA study.
Physicians should inform patients to promptly report any episodes of fever [see Patient Counseling Information (17) ] .
5.2Interstitial Lung Disease (ILD)/Pneumonitis Severe, life-threatening, or fatal interstitial lung disease (ILD) and/or pneumonitis can occur in patients treated with cyclin-dependent kinase 4/6 (CDK4/6) inhibitors, including IBRANCE when taken in combination with endocrine therapy. Across clinical trials (PALOMA-1, PALOMA-2, PALOMA-3), 1% of IBRANCE-treated patients had ILD/pneumonitis of any grade, 0.1% had Grade 3 or 4 and no fatal cases were reported. In PATINA, 1% of IBRANCE-treated patients had ILD/pneumonitis of any grade.
No Grade 3, 4, or fatal cases were reported. Additional cases of ILD/pneumonitis have been observed in the postmarketing setting, with fatalities reported [see Adverse Reactions (6.2) ] . Monitor patients for pulmonary symptoms indicative of ILD/pneumonitis (e.g. hypoxia, cough, dyspnea).
In patients who have new or worsening respiratory symptoms and are suspected to have developed pneumonitis, interrupt IBRANCE immediately and evaluate the patient. Permanently discontinue IBRANCE in patients with severe ILD or pneumonitis [see Dosage and Administration (2.2) ] .
5.3Embryo-Fetal Toxicity Based on findings from animal studies and its mechanism of action, IBRANCE can cause fetal harm when administered to a pregnant woman. In animal reproduction studies, administration of palbociclib to pregnant rats and rabbits during organogenesis resulted in embryo-fetal toxicity at maternal exposures that were ≥4 times the human clinical exposure based on area u…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: • Neutropenia [see Warnings and Precautions (5.1) ] • ILD/Pneumonitis [see Warnings and Precautions (5.2) ] Most common adverse reactions (incidence ≥20%) in combination with either letrozole or fulvestrant, including laboratory abnormalities, were white blood cell count decreased, neutrophils decreased, blood creatinine increased, hemoglobin decreased, platelets decreased, infections, aspartate aminotransferase increased, alanine aminotransferase increased, fatigue, nausea, stomatitis, diarrhea, and alopecia.
( 6.1 ) The most common adverse reactions (incidence ≥20%) in combination with inavolisib and fulvestrant, including laboratory abnormalities, were neutrophils decreased, hemoglobin decreased, fasting glucose increased, platelets decreased, lymphocytes decreased, stomatitis, diarrhea, calcium decreased, fatigue, potassium decreased, creatinine increased, alanine aminotransferase (ALT) increased, nausea, sodium decreased, magnesium decreased, rash, decreased appetite, COVID-19 infection, and headache. ( 6.1 ) The most common adverse reactions (incidence ≥20%) in combination with trastuzumab, with or without pertuzumab, and endocrine therapy, including laboratory abnormalities, were white blood cell decreased, neutrophil count decreased, creatinine increased, hemoglobin decreased, diarrhea, infections, platelet count decreased, stomatitis, aspartate aminotransferase increased, decreased calcium, alanine aminotransferase increased, decreased potassium, fatigue, alkaline phosphatase increased, nausea, asthenia, headache, rash, pruritus, and muscle spasms.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Pfizer Inc at 1-800-438-1985 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Studies Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. PALOMA-2: IBRANCE plus Letrozole Patients with estrogen receptor (ER)-positive, HER2-negative advanced or metastatic breast cancer for initial endocrine-based therapy The safety of IBRANCE plus letrozole was evaluated in a randomized, double-blind trial (PALOMA-2) in 666 patients with ER-positive, HER2-negative advanced breast cancer [see Clinical Studies (14.1) ] .
The median duration of treatment for IBRANCE plus letrozole was 19.8 months while the median duration of treatment for placebo plus letrozole arm was 13.8 months. Dose reductions due to an adverse reaction of any grade occurred in 36% of patients receiving IBRANCE plus letrozole. No dose reduction was allowed for letrozole in PALOMA-2.
Permanent discontinuation associated with an adverse reaction occurred in 43 of 444 (10%) patients receiving IBRANCE plus letrozole and in 13 of 222 (6%) patients receiving placebo plus letrozole. Adverse reactions leading to permanent discontinuation for patients receiving IBRANCE plus letrozole included neutropenia (1.1%) and alanine aminotransferase increase (0.7%). The most common adverse reactions (≥10%) of any grade reported in patients in the IBRANCE plus letrozole arm by descending frequency were neutropenia, infections, leukopenia, fatigue, nausea, alopecia, stomatitis, diarrhea, anemia, rash, asthenia, thrombocytopenia, vomiting, decreased appetite, dry skin, pyrexia, and dysgeusia.
The most frequently reported Grade ≥3 adverse reactions (≥5%) in patients receiving IBRANCE plus letrozole by descending frequency were neutropenia, leukopenia, infections, and anemia. Adverse reactions (≥10%) reported in patients who received IBRANCE plus letrozole or placebo plus letrozole in PALOMA-2 are listed in Table 4. Table 4.
Adverse Reactions (≥10%) in PALOMA-2 Grading according to CTCAE 4.0. CTCAE=Common Terminology Criteria for Adverse Events;…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Palbociclib is primarily metabolized by CYP3A and sulfotransferase (SULT) enzyme SULT2A1. In vivo, palbociclib is a time-dependent inhibitor of CYP3A. • CYP3A Inhibitors: Avoid concurrent use of IBRANCE with strong CYP3A inhibitors. If the strong inhibitor cannot be avoided, reduce the IBRANCE dose.
( 2.2 , 7.1 ) • CYP3A Inducers: Avoid concurrent use of IBRANCE with strong CYP3A inducers. ( 7.2 ) • CYP3A Substrates: The dose of sensitive CYP3A4 substrates with narrow therapeutic indices may need to be reduced when given concurrently with IBRANCE. ( 7.3 )
7.1Agents That May Increase Palbociclib Plasma Concentrations Effect of CYP3A Inhibitors Coadministration of a strong CYP3A inhibitor (itraconazole) increased the plasma exposure of palbociclib in healthy subjects by 87%. Avoid concomitant use of strong CYP3A inhibitors (e.g., clarithromycin, indinavir, itraconazole, ketoconazole, lopinavir/ritonavir, nefazodone, nelfinavir, posaconazole, ritonavir, saquinavir, telaprevir, telithromycin, and voriconazole). Avoid grapefruit or grapefruit juice during IBRANCE treatment.
If coadministration of IBRANCE with a strong CYP3A inhibitor cannot be avoided, reduce the dose of IBRANCE [see Dosage and Administration (2.2) and Clinical Pharmacology (12.3) ] .
7.2Agents That May Decrease Palbociclib Plasma Concentrations Effect of CYP3A Inducers Coadministration of a strong CYP3A inducer (rifampin) decreased the plasma exposure of palbociclib in healthy subjects by 85%. Avoid concomitant use of strong CYP3A inducers (e.g., phenytoin, rifampin, carbamazepine, enzalutamide, and St John's Wort) [see Clinical Pharmacology (12.3) ] .
7.3Drugs That May Have Their Plasma Concentrations Altered by Palbociclib Coadministration of midazolam with multiple doses of IBRANCE increased the midazolam plasma exposure by 61%, in healthy subjects, compared to administration of midazolam alone. The dose of the sensitive CYP3A substrate with a narrow therapeutic index (e.g., alfentanil, cyclosporine, dihydroergotamine, ergotamine, everolimus, fentanyl, pimozide, quinidine, sirolimus, and tacrolimus) may need to be reduced, as IBRANCE may increase its exposure [see Clinical Pharmacology (12.3) ] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Lactation: Advise not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action, IBRANCE can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . There are no available data in pregnant women to inform the drug-associated risk. In animal reproduction studies, administration of palbociclib to pregnant rats and rabbits during organogenesis resulted in embryo-fetal toxicity at maternal exposures that were ≥4 times the human clinical exposure based on AUC (see Data ) .
Advise pregnant women of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2%–4% and 15%–20%, respectively.
Data Animal Data In a fertility and early embryonic development study in female rats, palbociclib was administered orally for 15 days before mating through to Day 7 of pregnancy, which did not cause embryo toxicity at doses up to 300 mg/kg/day with maternal systemic exposures approximately 4 times the human exposure (AUC) at the recommended dose. In embryo-fetal development studies in rats and rabbits, pregnant animals received oral doses of palbociclib up to 300 mg/kg/day and 20 mg/kg/day, respectively, during the period of organogenesis.
The maternally toxic dose of 300 mg/kg/day was fetotoxic in rats, resulting in reduced fetal body weights. At doses ≥100 mg/kg/day in rats, there was an increased incidence of a skeletal variation (increased incidence of a rib present at the seventh cervical vertebra). At the maternally toxic dose of 20 mg/kg/day in rabbits, there was an increased incidence of skeletal variations, including small phalanges in the forelimb.
At 300 mg/kg/day in rats and 20 mg/kg/day in rabbits, the maternal systemic exposures were approximately 4 and 9 times the human exposure (AUC) at the recommended dose, respectively. CDK4/6 double knockout mice have been reported to die in late stages of fetal development (gestation Day 14.5 until birth) due to severe anemia. However, knockout mouse data may not be predictive of effects in humans due to differences in degree of target inhibition.
8.2Lactation Risk Summary There is no information regarding the presence of palbociclib in human milk, its effects on milk production, or the breastfed infant. Because of the potential for serious adverse reactions in breastfed infants from IBRANCE, advise a lactating woman not to breastfeed during treatment with IBRANCE and for 3 weeks after the last dose.
8.3Females and Males of Reproductive Potential Pregnancy Testing Based on animal studies, IBRANCE can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ]. Females of reproductive potential should have a pregnancy test prior to starting treatment with IBRANCE. Contraception Females IBRANCE can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ] .
Advise females of reproductive potential to use effective contraception during treatment with IBRANCE and for at least 3 weeks after the last dose. Males Because of the potential for genotoxicity, advise male patients with female partners of reproductive potential to use effective contraception during treatment with IBRANCE and for 3 months after the last dose [see Nonclinical Toxicology (13.1) ] . Infertility Males Based on animal studies, IBRANCE may impair fertility in males of reproductive potential [see Nonclinical Toxicology (13.1) ] .
8.4Pediatric Use The safety and effectiveness of IBRANCE in pediatric patients have not been established. The safety and effectiveness of IBRANCE were assessed but not established in three trials: one open-label trial [A5481092, (NCT03709680)] that included 98 pediatric patients 2 to <17…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on findings from animal studies and its mechanism of action, IBRANCE can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . There are no available data in pregnant women to inform the drug-associated risk. In animal reproduction studies, administration of palbociclib to pregnant rats and rabbits during organogenesis resulted in embryo-fetal toxicity at maternal exposures that were ≥4 times the human clinical exposure based on AUC (see Data ) .
Advise pregnant women of the potential risk to a fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2%–4% and 15%–20%, respectively.
Data Animal Data In a fertility and early embryonic development study in female rats, palbociclib was administered orally for 15 days before mating through to Day 7 of pregnancy, which did not cause embryo toxicity at doses up to 300 mg/kg/day with maternal systemic exposures approximately 4 times the human exposure (AUC) at the recommended dose. In embryo-fetal development studies in rats and rabbits, pregnant animals received oral doses of palbociclib up to 300 mg/kg/day and 20 mg/kg/day, respectively, during the period of organogenesis.
The maternally toxic dose of 300 mg/kg/day was fetotoxic in rats, resulting in reduced fetal body weights. At doses ≥100 mg/kg/day in rats, there was an increased incidence of a skeletal variation (increased incidence of a rib present at the seventh cervical vertebra). At the maternally toxic dose of 20 mg/kg/day in rabbits, there was an increased incidence of skeletal variations, including small phalanges in the forelimb.
At 300 mg/kg/day in rats and 20 mg/kg/day in rabbits, the maternal systemic exposures were approximately 4 and 9 times the human exposure (AUC) at the recommended dose, respectively. CDK4/6 double knockout mice have been reported to die in late stages of fetal development (gestation Day 14.5 until birth) due to severe anemia. However, knockout mouse data may not be predictive of effects in humans due to differences in degree of target inhibition.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of IBRANCE in pediatric patients have not been established. The safety and effectiveness of IBRANCE were assessed but not established in three trials: one open-label trial [A5481092, (NCT03709680)] that included 98 pediatric patients 2 to <17 years of age who received IBRANCE in combination with chemotherapy for recurrent or refractory solid tumors and two open-label trials that included 42 pediatric patients 4 to <17 years of age who received IBRANCE as a single agent for recurrent or refractory solid tumors [APEC1621I, (NCT03526250)] or primary central nervous system (CNS) tumors [PBTC-042, (NCT02255461)].
No new safety signals were observed in these trials. Palbociclib exposures in pediatric patients who received IBRANCE as a single agent or in combination were within range of those observed in adults given a similar dose based on body surface area. Juvenile Animal Toxicity Data Altered glucose metabolism (glycosuria, hyperglycemia, decreased insulin) associated with changes in the pancreas (islet cell vacuolation), eye (cataracts, lens degeneration), kidney (tubule vacuolation, chronic progressive nephropathy) and adipose tissue (atrophy) were identified in a 27 week repeat-dose toxicology study in rats that were immature at the beginning of the studies and were most prevalent in males at oral palbociclib doses ≥30 mg/kg/day (approximately 11 times the adult human exposure [AUC] at the recommended dose).
Some of these findings (glycosuria/hyperglycemia, pancreatic islet cell vacuolation, and kidney tubule vacuolation) were present with lower incidence and severity in a 15 week repeat-dose toxicology study in immature rats. Altered glucose metabolism or associated changes in the pancreas, eye, kidney and adipose tissue were not identified in a 27-week repeat-dose toxicology study in rats that were mature at the beginning of the study and in dogs in repeat-dose toxicology studies up to 39 weeks duration. Toxicities in teeth independent of altered glucose metabolism were observed in rats.
Administration of 100 mg/kg palbociclib for 27 weeks (approximately 15 times the adult human exposure [AUC] at the recommended dose) resulted in abnormalities in growing incisor teeth (discolored, ameloblast degeneration/necrosis, mononuclear cell infiltrate). Other toxicities of potential concern to pediatric patients have not been evaluated in juvenile animals.
🧓 Geriatric Use ▾
8.5Geriatric Use Of 444 patients who received IBRANCE in PALOMA-2, 181 patients (41%) were ≥65 years of age and 48 patients (11%) were ≥75 years of age. Of 347 patients who received IBRANCE in PALOMA-3, 86 patients (25%) were ≥65 years of age and 27 patients (8%) were ≥75 years of age. Of the 260 patients who received IBRANCE in PATINA, 41 patients (16%) were ≥65 years of age and 13 patients (5%) were ≥75 years of age.
No clinically significant differences in safety or effectiveness of IBRANCE were observed between patients 65 years of age and older and younger adult patients. Of the 162 patients who received IBRANCE in combination with inavolisib and fulvestrant in INAVO120, 15% were ≥ 65 years of age and 3% were ≥ 75 years of age. Dosage modifications or interruptions due to adverse reactions occurred at a higher incidence in patients ≥ 65 years of age compared with younger patients (79% versus 68%, respectively).
Clinical studies of IBRANCE in combination with inavolisib and fulvestrant did not include sufficient numbers of patients ≥ 65 years of age to determine whether they respond differently from younger patients.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Palbociclib is an inhibitor of cyclin-dependent kinases (CDK) 4 and 6. Cyclin D1 and CDK4/6 are downstream of signaling pathways which lead to cellular proliferation. In vitro, palbociclib reduced cellular proliferation of estrogen receptor (ER)-positive breast cancer cell lines by blocking progression of the cell from G1 into S phase of the cell cycle.
Treatment of breast cancer cell lines with the combination of palbociclib and antiestrogens leads to decreased retinoblastoma (Rb) protein phosphorylation resulting in reduced E2F expression and signaling, and increased growth arrest compared to treatment with each drug alone. In vitro treatment of ER-positive breast cancer cell lines with the combination of palbociclib and antiestrogens led to increased cell senescence compared to each drug alone, which was sustained for up to 6 days following palbociclib removal and was greater if antiestrogen treatment was continued.
In vivo studies using a patient-derived ER-positive breast cancer xenograft model demonstrated that the combination of palbociclib and letrozole increased the inhibition of Rb phosphorylation, downstream signaling, and tumor growth compared to each drug alone. Human bone marrow mononuclear cells treated with palbociclib in the presence or absence of an anti-estrogen in vitro did not become senescent and resumed proliferation following palbociclib withdrawal.
12.2Pharmacodynamics Cardiac Electrophysiology The effect of palbociclib on the QT interval corrected for heart rate (QTc) was evaluated using time-matched electrocardiograms (ECGs) evaluating the change from baseline and corresponding pharmacokinetic data in 77 patients with breast cancer. Palbociclib had no large effect on QTc (i.e., >20 ms) at 125 mg once daily for 21 consecutive days followed by 7 days off treatment to comprise a complete cycle of 28 days.
12.3Pharmacokinetics The pharmacokinetics (PK) of palbociclib were characterized in patients with solid tumors including advanced breast cancer and in healthy subjects. Absorption The maximum observed concentration (C max ) of palbociclib is generally observed between 4 to 12 hours (time to reach maximum concentration, T max ) following oral administration of IBRANCE tablets. The mean absolute bioavailability of IBRANCE after an oral 125 mg dose is 46%.
In the dosing range of 25 mg to 225 mg, the AUC and C max increased proportionally with dose in general. Steady state was achieved within 8 days following repeated once daily dosing. With repeated once daily administration, palbociclib accumulated with a median accumulation ratio of 2.4 (range 1.5 to 4.2).
Food Effect : The area under the concentration-time curve from zero to infinity (AUC INF ) and C max of palbociclib increased by 22% and 26%, respectively, when IBRANCE tablets were given with a high-fat, high-calorie meal (approximately 800 to 1000 calories with 150, 250, and 500 to 600 calories from protein, carbohydrate, and fat, respectively), and by 9% and 10%, respectively, when IBRANCE tablets were given with a moderate-fat, standard-calorie meal (approximately 500 to 700 calories with 75 to 105, 250 to 350 and 175 to 245 calories from protein, carbohydrate, and fat, respectively), compared to IBRANCE tablets given under overnight fasted conditions.
Distribution Binding of palbociclib to human plasma proteins in vitro was approximately 85%, with no concentration dependence over the concentration range of 500 ng/mL to 5000 ng/mL. The mean fraction unbound (f u ) of palbociclib in human plasma in vivo increased incrementally with worsening hepatic function. There was no obvious trend in the mean palbociclib f u in human plasma in vivo with worsening renal function.
The geometric mean apparent volume of distribution (V z /F) was 2583 L with a coefficient of variation (CV) of 26%. Metabolism In vitro and in vivo studies indicated that palbociclib undergoes hepatic metabolism in humans. Following o…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Palbociclib is an inhibitor of cyclin-dependent kinases (CDK) 4 and 6. Cyclin D1 and CDK4/6 are downstream of signaling pathways which lead to cellular proliferation. In vitro, palbociclib reduced cellular proliferation of estrogen receptor (ER)-positive breast cancer cell lines by blocking progression of the cell from G1 into S phase of the cell cycle.
Treatment of breast cancer cell lines with the combination of palbociclib and antiestrogens leads to decreased retinoblastoma (Rb) protein phosphorylation resulting in reduced E2F expression and signaling, and increased growth arrest compared to treatment with each drug alone. In vitro treatment of ER-positive breast cancer cell lines with the combination of palbociclib and antiestrogens led to increased cell senescence compared to each drug alone, which was sustained for up to 6 days following palbociclib removal and was greater if antiestrogen treatment was continued.
In vivo studies using a patient-derived ER-positive breast cancer xenograft model demonstrated that the combination of palbociclib and letrozole increased the inhibition of Rb phosphorylation, downstream signaling, and tumor growth compared to each drug alone. Human bone marrow mononuclear cells treated with palbociclib in the presence or absence of an anti-estrogen in vitro did not become senescent and resumed proliferation following palbociclib withdrawal.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING IBRANCE is supplied in the following strengths and package configurations: IBRANCE Tablets Package Configuration Tablet Strength (mg) NDC Tablet Description Monthly box containing 3 weekly blister packs of 7 tablets each (21 tablets total) 125 NDC 0069-0688-03 Oval, light purple, film-coated tablets debossed with "Pfizer" on one side and "PBC 125" on the other side. Monthly box containing 3 weekly blister packs of 7 tablets each (21 tablets total) 100 NDC 0069-0486-03 Oval, green, film-coated tablets debossed with "Pfizer" on one side and "PBC 100" on the other side.
Monthly box containing 3 weekly blister packs of 7 tablets each (21 tablets total) 75 NDC 0069-0284-03 Round, light purple, film-coated tablets debossed with "Pfizer" on one side and "PBC 75" on the other side. Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature] . Store in the original blister pack.
📦 Storage and Handling ▾
Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature] . Store in the original blister pack.
📋 Description ▾
11 DESCRIPTION IBRANCE tablets for oral administration contain 125 mg, 100 mg, or 75 mg of palbociclib, a kinase inhibitor. The molecular formula for palbociclib is C 24 H 29 N 7 O 2 . The molecular weight is 447.54 daltons.
The chemical name is 6-acetyl-8-cyclopentyl-5-methyl-2-{[5-(piperazin-1-yl)pyridin-2-yl]amino}pyrido[2,3- d ]pyrimidin-7(8 H )-one, and its structural formula is: Palbociclib is a yellow to orange powder. At or below pH 4, palbociclib behaves as a high-solubility compound. Above pH 4, the solubility of the drug substance reduces significantly.
Inactive Ingredients: Microcrystalline cellulose, colloidal silicon dioxide, crospovidone, magnesium stearate, succinic acid, HPMC 2910/hypromellose, titanium dioxide, triacetin, and FD&C Blue #2/Indigo Carmine Aluminum Lake. In addition, the 75 mg and 125 mg tablets contain red iron oxide and the 100 mg tablets contain yellow iron oxide. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Myelosuppression/Infection • Advise patients to immediately report any signs or symptoms of myelosuppression or infection, such as fever, chills, dizziness, shortness of breath, weakness, or any increased tendency to bleed and/or to bruise [see Warnings and Precautions (5.1) ] . Interstitial Lung Disease/Pneumonitis • Advise patients to immediately report new or worsening respiratory symptoms [see Warnings and Precautions (5.2) ] .
Drug Interactions • Grapefruit may interact with IBRANCE. Patients should not consume grapefruit products while on treatment with IBRANCE. • Inform patients to avoid strong CYP3A inhibitors and strong CYP3A inducers. • Advise patients to inform their healthcare providers of all concomitant medications, including prescription medicines, over-the-counter drugs, vitamins, and herbal products [see Drug Interactions (7) ] . Dosing and Administration • Inform patients that IBRANCE tablets may be taken with or without food. • If the patient vomits or misses a dose, an additional dose should not be taken.
The next prescribed dose should be taken at the usual time. IBRANCE tablets should be swallowed whole (do not chew, crush, or split them prior to swallowing). No tablet should be ingested if it is broken, cracked, or otherwise not intact. • Pre/perimenopausal women treated with IBRANCE should also be treated with LHRH agonists [see Dosage and Administration (2.1) ] . • When IBRANCE is used in combination, refer to the other products’ Full Prescribing Information for dosing and administration information [see Dosage and Administration (2.1 , 2.2 )] .
Pregnancy, Lactation, and Infertility • Embryo-Fetal Toxicity o Advise females of reproductive potential of the potential risk to a fetus and to use effective contraception during treatment with IBRANCE therapy and for at least 3 weeks after the last dose. Advise females to inform their healthcare provider of a known or suspected pregnancy [see Warnings and Precautions (5.3) and Use in Specific Populations (8.1 and 8.3) ] . o Advise male patients with female partners of reproductive potential to use effective contraception during treatment with IBRANCE and for at least 3 months after the last dose [see Use in Specific Populations (8.3) ]. • Lactation: Advise women not to breastfeed during treatment with IBRANCE and for 3 weeks after the last dose [see Use in Specific Populations (8.2) ]. • Infertility: Inform males of reproductive potential that IBRANCE may cause infertility and to consider sperm preservation before taking IBRANCE [see Use in Specific Populations (8.3) ] .