
Nivestym filgrastim-aafi 300 ug/.5mL Injection, Solution, 1 syringe — NDC 0069-0291-01 (Billing 00069-0291-01)
This is a package of 1 syringe of Nivestym filgrastim-aafi 300 ug/.5mL Injection, Solution from Pfizer Laboratories Div Pfizer Inc, marketed since Sep 2018 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 0069-0291-01 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 0069 labeler · 0291 product · 01 package
- Package marketed since
- Sep 24, 2018
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 0069029101 7
- Medicaid fills, this package
- 2,050 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 078721
- GCN: 45103
- GPI-14 (Medi-Span): 8240152010E520
- HICL (First Databank): 045154
- AHFS class code: 20:16.00.00
- RxCUI (RxNorm): 2057200
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Leukocyte Growth Factor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Filgrastim injection is used to increase white blood cells and decrease the risk of infection in patients receiving chemotherapy for certain types of cancer to increase white blood cells in people who are undergoing bone marrow transplants and in people who have severe chronic neutropenia (condition in which there are a low number of neutrophils in the blood). to prepare the blood for leukapheresis (a treatment in which certain blood cells are removed from the body). to increase the chance of survival in people who have been exposed to harmful amounts of radiation, which can cause sever...
Read the full MedlinePlus article ↗- It raises your neutrophils, the white blood cells that fight infection. It is used for people on chemotherapy, those with AML, bone marrow transplant patients, stem cell collection...
- It is injected under the skin or given into a vein, depending on your condition. Some people or caregivers are trained to give injections at home. If you miss a dose, call your hea...
- Common ones include bone pain, fever, rash, cough, headache and nosebleeds. Tell your care team about any that bother you.
- Call for left upper belly or shoulder pain, trouble breathing, signs of allergic reaction, blood in your urine, swelling, or unexplained fever with belly or back pain. These can be...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $355.35 | $177.67 / 0.5 ml |
| Medicare drug plans payPart D · Q2 2026 | $416.80 | $208.40 / 0.5 ml |
| Medicare Part B allowsASP · Q5110 | $0.322 / Q5110 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 00069-0291-01 You're viewing this Main listing | 1 SYRINGE in 1 CARTON / .5 mL in 1 SYRINGE | 2018-09-24 | — | Active |
| 00069-0291-10 0069-0291-10 | 10 CARTON in 1 CARTON / 1 SYRINGE in 1 CARTON / .5 mL in 1 SYRINGE | 2018-09-24 | — | Active |
In Medicaid, this is the most-dispensed pack of this product — about 72% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Nivestym filgrastim-aafi 300 ug/.5mL Injection, Solution?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Nivestym 300 ug/.5mLthis 00069-0291-01 | Pfizer | 1 syringe | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Purple Book · refreshed Oct 5, 2026
- CMS NADAC weekly file
Availability & biosimilar status
4 biosimilars are FDA-licensed for this reference biologic — see the list below. (Biologics have no small-molecule generics.)
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Code | What it grants | Expires |
|---|---|---|
| RefProduct | Reference-product exclusivity (12-year, BPCIA) — no biosimilar can be licensed before this date | Jul 20, 2030 |
Is there a biosimilar for NIVESTYM 300 MCG/0.5 ML SYRING?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
- FDA Purple Book · refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Filgrastim Injection inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
0.02 mg / 0.5 mL
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII 4550K0SC9B
Sodium acetate is a salt derived from acetic acid. It acts as a buffer to help maintain the medicine's pH stability and may serve as a preservative or solubilizer in liquid formulations.
-
25 mg / 0.5 mL
UNII 506T60A25R
Sorbitol is a natural sugar alcohol derived from glucose. It serves as a sweetener, humectant, and bulking agent in medications to improve taste and help maintain moisture in the product.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Pfizer Laboratories Div Pfizer Inc labeler code 00069
- Talzenna talazoparib .1 mg Capsule, Liquid Filled NDC 0069-0252-30
- Fragmin Dalteparin Sodium 2500 [iU]/mL Injection NDC 0069-0253-10
- Doxorubicin Hydrochloride 2 mg/mL Injection, Solution NDC 0069-0255-10
- Velsipity etrasimod 2 mg Tablet, Film Coated NDC 0069-0274-30
- Doxorubicin Hydrochloride 2 mg/mL Injection, Solution NDC 0069-0277-02
- Ibrance palbociclib 75 mg Tablet, Film Coated NDC 0069-0284-03
- Nivestym filgrastim-aafi 480 ug/.8mL Injection, Solution NDC 0069-0292-01
- Nivestym filgrastim-aafi 300 ug/mL Injection, Solution NDC 0069-0293-10
- Nivestym filgrastim-aafi 480 ug/1.6mL Injection, Solution NDC 0069-0294-10
- Talzenna talazoparib .25 mg Capsule NDC 0069-0296-30
- TicoVac Tick-Borne Encephalitis Vaccine 1.2 ug/.25mL Injection NDC 0069-0297-02
- Daurismo glasdegib 25 mg Tablet, Film Coated NDC 0069-0298-60
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE NIVESTYM is a leukocyte growth factor indicated to • Decrease the incidence of infection‚ as manifested by febrile neutropenia‚ in patients with nonmyeloid malignancies receiving myelosuppressive anti-cancer drugs associated with a significant incidence of severe neutropenia with fever. ( 1.1 ) • Reduce the time to neutrophil recovery and the duration of fever, following induction or consolidation chemotherapy treatment of patients with acute myeloid leukemia (AML). ( 1.2 ) • Reduce the duration of neutropenia and neutropenia-related clinical sequelae‚ e.g.‚ febrile neutropenia, in patients with nonmyeloid malignancies undergoing myeloablative chemotherapy followed by bone marrow transplantation (BMT).
( 1.3 ) • Mobilize autologous hematopoietic progenitor cells into the peripheral blood for collection by leukapheresis. ( 1.4 ) • Reduce the incidence and duration of sequelae of severe neutropenia (e.g.‚ fever‚ infections‚ oropharyngeal ulcers) in symptomatic patients with congenital neutropenia‚ cyclic neutropenia‚ or idiopathic neutropenia. ( 1.5 )
1.1Patients with Cancer Receiving Myelosuppressive Chemotherapy NIVESTYM is indicated to decrease the incidence of infection‚ as manifested by febrile neutropenia‚ in patients with nonmyeloid malignancies receiving myelosuppressive anti-cancer drugs associated with a significant incidence of severe neutropenia with fever [see Clinical Studies (14.1) ] .
1.2Patients with Acute Myeloid Leukemia Receiving Induction or Consolidation Chemotherapy NIVESTYM is indicated for reducing the time to neutrophil recovery and the duration of fever, following induction or consolidation chemotherapy treatment of patients with acute myeloid leukemia (AML) [see Clinical Studies (14.2) ] .
1.3Patients with Cancer Undergoing Bone Marrow Transplantation NIVESTYM is indicated to reduce the duration of neutropenia and neutropenia-related clinical sequelae‚ e.g.‚ febrile neutropenia, in patients with nonmyeloid malignancies undergoing myeloablative chemotherapy followed by bone marrow transplantation [see Clinical Studies (14.3) ].
1.4Patients Undergoing Autologous Peripheral Blood Progenitor Cell Collection and Therapy NIVESTYM is indicated for the mobilization of autologous hematopoietic progenitor cells into the peripheral blood for collection by leukapheresis [see Clinical Studies (14.4) ] .
1.5Patients with Severe Chronic Neutropenia NIVESTYM is indicated for chronic administration to reduce the incidence and duration of sequelae of neutropenia (e.g.‚ fever‚ infections‚ oropharyngeal ulcers) in symptomatic patients with congenital neutropenia‚ cyclic neutropenia‚ or idiopathic neutropenia [see Clinical Studies (14.5) ] .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Patients with cancer receiving myelosuppressive chemotherapy or induction and/or consolidation chemotherapy for AML. o Recommended starting dose is 5 mcg/kg/day subcutaneous injection, short intravenous infusion (15 to 30 minutes), or continuous intravenous infusion. See Full Prescribing Information for recommended dosage adjustments and timing of administration. ( 2.1 ) • Patients with cancer undergoing bone marrow transplantation. o 10 mcg/kg/day given as an intravenous infusion no longer than 24 hours.
See Full Prescribing Information for recommended dosage adjustments and timing of administration. ( 2.2 ) • Patients undergoing autologous peripheral blood progenitor cell collection and therapy. o 10 mcg/kg/day subcutaneous injection. ( 2.3 ) o Administer for at least 4 days before first leukapheresis procedure and continue until last leukapheresis.
( 2.3 ) • Patients with congenital neutropenia. o Recommended starting dose is 6 mcg/kg subcutaneous injection twice daily. ( 2.4 ) • Patients with cyclic or idiopathic neutropenia. o Recommended starting dose is 5 mcg/kg subcutaneous injection daily. ( 2.4 ) • Direct administration of less than 0.3 mL (180 mcg) using NIVESTYM prefilled syringe is not recommended due to potential for dosing errors.
( 2.5 )
2.1Dosage in Patients with Cancer Receiving Myelosuppressive Chemotherapy or Induction and/or Consolidation Chemotherapy for AML The recommended starting dosage of NIVESTYM is 5 mcg/kg/day‚ administered as a single daily injection by subcutaneous injection‚ by short intravenous infusion (15 to 30 minutes)‚ or by continuous intravenous infusion. Obtain a complete blood count (CBC) and platelet count before instituting NIVESTYM therapy and monitor twice weekly during therapy. Consider dose escalation in increments of 5 mcg/kg for each chemotherapy cycle‚ according to the duration and severity of the absolute neutrophil count (ANC) nadir.
Recommend stopping NIVESTYM if the ANC increases beyond 10‚000/mm 3 [see Warnings and Precautions (5.10) ] . Administer NIVESTYM at least 24 hours after cytotoxic chemotherapy. Do not administer NIVESTYM within the 24-hour period prior to chemotherapy [see Warnings and Precautions (5.13) ] .
A transient increase in neutrophil count is typically seen 1 to 2 days after initiation of NIVESTYM therapy. Therefore, to ensure a sustained therapeutic response‚ administer NIVESTYM daily for up to 2 weeks or until the ANC has reached 10‚000/mm 3 following the expected chemotherapy-induced neutrophil nadir. The duration of NIVESTYM therapy needed to attenuate chemotherapy-induced neutropenia may be dependent on the myelosuppressive potential of the chemotherapy regimen employed.
2.2Dosage in Patients with Cancer Undergoing Bone Marrow Transplantation The recommended dosage of NIVESTYM following bone marrow transplantation (BMT) is 10 mcg/kg/day given as an intravenous infusion no longer than 24 hours. Administer the first dose of NIVESTYM at least 24 hours after cytotoxic chemotherapy and at least 24 hours after bone marrow infusion. Monitor CBCs and platelet counts frequently following marrow transplantation.
During the period of neutrophil recovery‚ titrate the daily dosage of NIVESTYM against the neutrophil response (see Table 1 ). Table 1. Recommended Dosage Adjustments During Neutrophil Recovery in Patients with Cancer Following BMT Absolute Neutrophil Count NIVESTYM Dosage Adjustment When ANC greater than 1,000/mm 3 for 3 consecutive days Reduce to 5 mcg/kg/day If ANC decreases to less than 1,000/mm 3 at any time during the 5 mcg/kg/day administration‚ increase NIVESTYM to 10 mcg/kg/day‚ and then follow the above steps.
Then, if ANC remains greater than 1,000/mm 3 for 3 more consecutive days Discontinue NIVESTYM Then, if ANC decreases to less than 1,000/mm 3 Resume at 5 mcg/kg/day
2.3Dosage in Patients Undergoing Autologous Peripheral Blood Progenitor Cell Collection and Therapy The recommended dosage of NIVESTYM for t… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Vial • Injection: 300 mcg/mL in a single-dose vial ( 3 ) • Injection: 480 mcg/1.6 mL (300 mcg/mL) in a single-dose vial ( 3 ) Prefilled Syringe • Injection: 300 mcg/0.5 mL in a single-dose prefilled syringe ( 3 ) • Injection: 480 mcg/0.8 mL in a single-dose prefilled syringe ( 3 ) NIVESTYM is a clear, colorless solution available as: Vial: • Injection: 300 mcg/mL in a single-dose vial • Injection: 480 mcg/1.6 mL (300 mcg/mL) in a single-dose vial Prefilled Syringe: • Injection: 300 mcg/0.5 mL in a single-dose prefilled syringe • Injection: 480 mcg/0.8 mL in a single-dose prefilled syringe
⛔ Contraindications ▾
4 CONTRAINDICATIONS NIVESTYM is contraindicated in patients with a history of serious allergic reactions to human granulocyte colony-stimulating factors such as filgrastim products or pegfilgrastim products [see Warnings and Precautions (5.3) ] . Patients with a history of serious allergic reactions to human granulocyte colony-stimulating factors such as filgrastim products or pegfilgrastim products. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Fatal splenic rupture: Evaluate patients who report left upper abdominal or shoulder pain for an enlarged spleen or splenic rupture. ( 5.1 ) • Acute respiratory distress syndrome (ARDS): Evaluate patients who develop fever and lung infiltrates or respiratory distress for ARDS. • Discontinue NIVESTYM in patients with ARDS. ( 5.2 ) • Serious allergic reactions, including anaphylaxis: Permanently discontinue NIVESTYM in patients with serious allergic reactions.
( 5.3 ) • Fatal sickle cell crises: Discontinue NIVESTYM if sickle cell crisis occurs. ( 5.4 ) • Glomerulonephritis: Evaluate and consider dose-reduction or interruption of NIVESTYM if causality is likely. ( 5.5 ) • Myelodysplastic Syndrome (MDS) and Acute Myeloid Leukemia (AML): Monitor patients with breast and lung cancer using NIVESTYM in conjunction with chemotherapy and/or radiotherapy for signs and symptoms of MDS/AML.
( 5.8 ) • Thrombocytopenia: Monitor platelet counts. ( 5.9 ) • Aortitis: Aortitis has been reported in patients receiving NIVESTYM. Discontinue NIVESTYM if aortitis is suspected.
( 5.15 )
5.1Splenic Rupture Splenic rupture, including fatal cases, has been reported following the administration of filgrastim products. Evaluate patients who report left upper abdominal or shoulder pain for an enlarged spleen or splenic rupture.
5.2Acute Respiratory Distress Syndrome Acute respiratory distress syndrome (ARDS) has been reported in patients receiving filgrastim products. Evaluate patients who develop fever and lung infiltrates or respiratory distress for ARDS. Discontinue NIVESTYM in patients with ARDS.
5.3Serious Allergic Reactions Serious allergic reactions, including anaphylaxis, have been reported in patients receiving filgrastim products. The majority of reported events occurred upon initial exposure. Provide symptomatic treatment for allergic reactions.
Allergic reactions, including anaphylaxis, in patients receiving filgrastim products can recur within days after the discontinuation of initial anti-allergic treatment. Permanently discontinue NIVESTYM in patients with serious allergic reactions. NIVESTYM is contraindicated in patients with a history of serious allergic reactions to human granulocyte colony-stimulating factors such as filgrastim products or pegfilgrastim products.
5.4Sickle Cell Disorders Severe and sometimes fatal sickle cell crises can occur in patients with sickle cell disorders receiving filgrastim products. Discontinue NIVESTYM if sickle cell crisis occurs.
5.5Glomerulonephritis Glomerulonephritis has occurred in patients receiving filgrastim products. The diagnoses were based upon azotemia, hematuria (microscopic and macroscopic), proteinuria, and renal biopsy. Generally, events of glomerulonephritis resolved after dose reduction or discontinuation of filgrastim products. If glomerulonephritis is suspected, evaluate for cause. If causality is likely, consider dose-reduction or interruption of NIVESTYM.
5.6Alveolar Hemorrhage and Hemoptysis Alveolar hemorrhage manifesting as pulmonary infiltrates and hemoptysis requiring hospitalization have been reported in healthy donors treated with filgrastim products undergoing peripheral blood progenitor cell (PBPC) collection mobilization. Hemoptysis resolved with discontinuation of filgrastim products. The use of NIVESTYM for PBPC mobilization in healthy donors is not an approved indication.
5.7Capillary Leak Syndrome Capillary leak syndrome (CLS) has been reported after G-CSF administration, including filgrastim products, and is characterized by hypotension, hypoalbuminemia, edema and hemoconcentration. Episodes vary in frequency, severity and may be life-threatening if treatment is delayed. Patients who develop symptoms of capillary leak syndrome should be closely monitored and receive standard symptomatic treatment, which may include a need for intensive care.
5.8Myelodysplastic Syndrome (MDS) and Acute Myeloid Leukemia (AML) Patients with Severe Chron… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed in greater detail in other sections of the labeling: • Splenic Rupture [see Warnings and Precautions (5.1) ] • Acute Respiratory Distress Syndrome [see Warnings and Precautions (5.2) ] • Serious Allergic Reactions [see Warnings and Precautions (5.3) ] • Sickle Cell Disorders [see Warnings and Precautions (5.4) ] • Glomerulonephritis [see Warnings and Precautions (5.5) ] • Alveolar Hemorrhage and Hemoptysis [see Warnings and Precautions (5.6) ] • Capillary Leak Syndrome [see Warnings and Precautions (5.7) ] • Myelodysplastic Syndrome [see Warnings and Precautions (5.8) ] • Acute Myeloid Leukemia [see Warnings and Precautions (5.8) ] • Thrombocytopenia [see Warnings and Precautions (5.9) ] • Leukocytosis [see Warnings and Precautions (5.10) ] • Cutaneous Vasculitis [see Warnings and Precautions (5.11) ] • Aortitis [see Warnings and Precautions (5.15) ] Most common adverse reactions in patients: • With nonmyeloid malignancies receiving myelosuppressive anti-cancer drugs (≥ 5% difference in incidence compared to placebo) are pyrexia, pain, rash, cough, and dyspnea.
( 6.1 ) • With AML (≥ 2% difference in incidence) are pain, epistaxis and rash. ( 6.1 ) • With nonmyeloid malignancies undergoing myeloablative chemotherapy followed by BMT (≥ 5% difference in incidence) is rash. ( 6.1 ) • Undergoing peripheral blood progenitor cell mobilization and collection (≥ 5% incidence) are bone pain, pyrexia and headache.
( 6.1 ) • With severe chronic neutropenia (SCN) (≥ 5% difference in incidence) are pain, anemia, epistaxis, diarrhea, hypoesthesia and alopecia. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Pfizer Inc at 1-800-438-1985 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Adverse Reactions in Patients with Cancer Receiving Myelosuppressive Chemotherapy The following adverse reaction data in Table 2 are from three randomized, placebo-controlled studies in patients with: • small cell lung cancer receiving standard dose chemotherapy with cyclophosphamide‚ doxorubicin‚ and etoposide (Study 1) • small cell lung cancer receiving ifosfamide, doxorubicin‚ and etoposide (Study 2), and • non-Hodgkin's lymphoma (NHL) receiving doxorubicin, cyclophosphamide, vindesine, bleomycin, methylprednisolone, and methotrexate ("ACVBP") or mitoxantrone, ifosfamide, mitoguazone, teniposide, methotrexate, folinic acid, methylprednisolone, and methotrexate ("VIM3") (Study 3).
A total of 451 patients were randomized to receive subcutaneous filgrastim 230 mcg/m 2 (Study 1), 240 mcg/m 2 (Study 2) or 4 or 5 mcg/kg/day (Study 3) (n = 294) or placebo (n = 157). The patients in these studies were median age 61 (range 29 to 78) years and 64% were male. The ethnicity was 95% Caucasian, 4% African American, and 1% Asian.
Table 2. Adverse Reactions in Patients with Cancer Receiving Myelosuppressive Chemotherapy (With ≥ 5% Higher Incidence in Filgrastim Compared to Placebo) System Organ Class Preferred Term Filgrastim (N = 294) Placebo (N = 157) Blood and lymphatic system disorders Thrombocytopenia 38% 29% Gastrointestinal disorders Nausea 43% 32% General disorders and administration site conditions Pyrexia 48% 29% Chest pain 13% 6% Pain 12% 6% Fatigue 20% 10% Musculoskeletal and connective tissue disorders Back pain 15% 8% Arthralgia 9% 2% Bone pain 11% 6% Pain in extremity Percent difference (Filgrastim – Placebo) was 4%.
7% 3% Nervous system disorders Dizziness 14% 3% Respiratory, thoracic and mediastinal disorders Cough 14% 8% Dyspnea 13% 8% Skin and subcutaneous tissue disorders Rash 14% 5% Investigations Blood lactate dehydrogenase increased 6% 1% Blood alkaline phosphatase incre… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Available data from published studies, including several observational studies of pregnancy outcomes in women exposed to filgrastim products and those who were unexposed, have not established an association with filgrastim products use during pregnancy and major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data ) . Reports in the scientific literature have described transplacental passage of filgrastim in pregnant women when administered ≤ 30 hours prior to preterm delivery (≤ 30 weeks gestation).
In animal reproduction studies, effects of filgrastim on prenatal development have been studied in rats and rabbits. No malformations were observed in either species. No maternal or fetal effects were observed in pregnant rats at doses up to 58 times the human doses.
Filgrastim has been shown to have adverse effects in pregnant rabbits at doses 2 to 10 times higher than the human doses (see Data ) . The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively. Data Human data Several observational studies based on the Severe Chronic Neutropenia International Registry (SCNIR) described pregnancy outcomes in women with severe chronic neutropenia (SCN) who were exposed to filgrastim products during pregnancy and women with SCN who were unexposed. No major differences were seen between treated and untreated women with respect to pregnancy outcome (including miscarriage and preterm labor), newborn complications (including birth weight) and infections.
Methodological limitations of these studies, include small sample size, and lack of generalizability due to the underlying maternal condition. Animal data Effects of filgrastim on prenatal development have been studied in rats and rabbits. No malformations were observed in either species.
Filgrastim has been shown to have adverse effects in pregnant rabbits at doses 2 to 10 times higher than the human doses. In pregnant rabbits showing signs of maternal toxicity, reduced embryo-fetal survival (at 20 and 80 mcg/kg/day) and increased abortions (at 80 mcg/kg/day) were observed. In pregnant rats, no maternal or fetal effects were observed at doses up to 575 mcg/kg/day, which is approximately 58 times higher than the human dose of 10 mcg/kg/day.
Offspring of rats administered filgrastim during the peri-natal and lactation periods exhibited a delay in external differentiation and growth retardation (≥ 20 mcg/kg/day) and slightly reduced survival rate (100 mcg/kg/day).
8.2Lactation Risk Summary There is published literature documenting transfer of filgrastim into human milk. There are a few case reports describing the use of filgrastim in breastfeeding mothers with no adverse effects noted in the infants. There are no data on the effects of filgrastim products on milk production.
Other filgrastim products are secreted poorly into breast milk, and filgrastim products are not absorbed orally by neonates. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for NIVESTYM and any potential adverse effects on the breastfed child from NIVESTYM or from the underlying maternal condition.
8.4Pediatric Use NIVESTYM prefilled syringe with BD UltraSafe Plus™ Passive Needle Guard may not accurately measure volumes less than 0.3 mL due to the needle spring mechanism design. Therefore, the direct administration of a volume less than 0.3 mL using NIVESTYM prefilled syringe is not recommended due to the potential for dosing errors. For direct administration of doses less than 0.3 mL (180 mcg) use NIVESTYM single-dose vial.
In patients with cancer receiving myelosuppre… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from published studies, including several observational studies of pregnancy outcomes in women exposed to filgrastim products and those who were unexposed, have not established an association with filgrastim products use during pregnancy and major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data ) . Reports in the scientific literature have described transplacental passage of filgrastim in pregnant women when administered ≤ 30 hours prior to preterm delivery (≤ 30 weeks gestation).
In animal reproduction studies, effects of filgrastim on prenatal development have been studied in rats and rabbits. No malformations were observed in either species. No maternal or fetal effects were observed in pregnant rats at doses up to 58 times the human doses.
Filgrastim has been shown to have adverse effects in pregnant rabbits at doses 2 to 10 times higher than the human doses (see Data ) . The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and 15–20%, respectively. Data Human data Several observational studies based on the Severe Chronic Neutropenia International Registry (SCNIR) described pregnancy outcomes in women with severe chronic neutropenia (SCN) who were exposed to filgrastim products during pregnancy and women with SCN who were unexposed. No major differences were seen between treated and untreated women with respect to pregnancy outcome (including miscarriage and preterm labor), newborn complications (including birth weight) and infections.
Methodological limitations of these studies, include small sample size, and lack of generalizability due to the underlying maternal condition. Animal data Effects of filgrastim on prenatal development have been studied in rats and rabbits. No malformations were observed in either species.
Filgrastim has been shown to have adverse effects in pregnant rabbits at doses 2 to 10 times higher than the human doses. In pregnant rabbits showing signs of maternal toxicity, reduced embryo-fetal survival (at 20 and 80 mcg/kg/day) and increased abortions (at 80 mcg/kg/day) were observed. In pregnant rats, no maternal or fetal effects were observed at doses up to 575 mcg/kg/day, which is approximately 58 times higher than the human dose of 10 mcg/kg/day.
Offspring of rats administered filgrastim during the peri-natal and lactation periods exhibited a delay in external differentiation and growth retardation (≥ 20 mcg/kg/day) and slightly reduced survival rate (100 mcg/kg/day).
🧒 Pediatric Use ▾
8.4Pediatric Use NIVESTYM prefilled syringe with BD UltraSafe Plus™ Passive Needle Guard may not accurately measure volumes less than 0.3 mL due to the needle spring mechanism design. Therefore, the direct administration of a volume less than 0.3 mL using NIVESTYM prefilled syringe is not recommended due to the potential for dosing errors. For direct administration of doses less than 0.3 mL (180 mcg) use NIVESTYM single-dose vial.
In patients with cancer receiving myelosuppressive chemotherapy‚ 15 pediatric patients median age 2.6 (range 1.2 to 9.4) years with neuroblastoma were treated with myelosuppressive chemotherapy (cyclophosphamide‚ cisplatin‚ doxorubicin‚ and etoposide) followed by subcutaneous filgrastim at doses of 5, 10, or 15 mcg/kg/day for 10 days (n = 5/dose) (Study 8). The pharmacokinetics of filgrastim in pediatric patients after chemotherapy were similar to those in adults receiving the same weight-normalized doses, suggesting no age-related differences in the pharmacokinetics of filgrastim.
In this population‚ filgrastim was well-tolerated. There was one report of palpable splenomegaly and one report of hepatosplenomegaly associated with filgrastim therapy; however‚ the only consistently reported adverse event was musculoskeletal pain‚ which is no different from the experience in the adult population. The safety and effectiveness of NIVESTYM have been established in pediatric patients with SCN [see Clinical Studies (14.5) ] .
Use of NIVESTYM for this indication is supported by NIVESTYM’s approval as a biosimilar to filgrastim and evidence from a phase 3 study (Study 7) to assess the safety and efficacy of filgrastim in the treatment of SCN where 123 patients with a median age of 12 years (range 7 months to 76 years) were studied. Of the 123 patients, 12 were infants (7 months to 2 years of age), 49 were children (2 to 12 years of age), and 9 were adolescents (12 to 16 years of age). Additional information is available from a SCN postmarketing surveillance study, which includes long-term follow-up of patients in the clinical studies and information from additional patients who entered directly into the postmarketing surveillance study.
Of the 731 patients in the surveillance study, 429 were pediatric patients < 18 years of age (range 0.9 to 17) [see Indications and Usage (1.5) , Dosage and Administration (2.5) , and Clinical Studies (14.5) ] . Long-term follow-up data from the postmarketing surveillance study suggest that height and weight are not adversely affected in patients who received up to 5 years of filgrastim treatment. Limited data from patients who were followed in the phase 3 study for 1.5 years did not suggest alterations in sexual maturation or endocrine function.
Pediatric patients with congenital types of neutropenia (Kostmann's syndrome, congenital agranulocytosis, or Schwachman-Diamond syndrome) have developed cytogenetic abnormalities and have undergone transformation to MDS and AML while receiving chronic filgrastim treatment. The relationship of these events to filgrastim product administration is unknown [see Warnings and Precautions (5.8) and Adverse Reactions (6) ] .
🧓 Geriatric Use ▾
8.5Geriatric Use Among 855 subjects enrolled in 3 randomized, placebo-controlled trials of filgrastim-treated patients receiving myelosuppressive chemotherapy, there were 232 subjects age 65 or older, and 22 subjects age 75 or older. No overall differences in safety or effectiveness were observed between these subjects and younger subjects. Clinical studies of filgrastim in other approved indications (i.e., BMT recipients, PBPC mobilization, and SCN) did not include sufficient numbers of subjects aged 65 and older to determine whether elderly subjects respond differently from younger subjects.
🆘 Overdosage ▾
10 OVERDOSAGE The maximum tolerated dose of filgrastim products has not been determined. In filgrastim clinical trials of patients with cancer receiving myelosuppressive chemotherapy‚ WBC counts > 100‚000/mm 3 have been reported in less than 5% of patients‚ but were not associated with any reported adverse clinical effects. Patients in the BMT studies received up to 138 mcg/kg/day without toxic effects‚ although there was a flattening of the dose response curve above daily doses of greater than 10 mcg/kg/day.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Colony-stimulating factors are glycoproteins which act on hematopoietic cells by binding to specific cell surface receptors and stimulating proliferation‚ differentiation commitment‚ and some end-cell functional activation. Endogenous G-CSF is a lineage-specific colony-stimulating factor that is produced by monocytes‚ fibroblasts, and endothelial cells. G-CSF regulates the production of neutrophils within the bone marrow and affects neutrophil progenitor proliferation‚ differentiation, and selected end-cell functions (including enhanced phagocytic ability‚ priming of the cellular metabolism associated with respiratory burst‚ antibody-dependent killing, and the increased expression of some cell surface antigens).
G-CSF is not species-specific and has been shown to have minimal direct in vivo or in vitro effects on the production or activity of hematopoietic cell types other than the neutrophil lineage.
12.2Pharmacodynamics In phase 1 studies involving 96 patients with various non-myeloid malignancies‚ filgrastim administration resulted in a dose-dependent increase in circulating neutrophil counts over the dose range of 1 to 70 mcg/kg/day. This increase in neutrophil counts was observed whether filgrastim was administered intravenous (1 to 70 mcg/kg twice daily)‚ subcutaneous (1 to 3 mcg/kg once daily)‚ or by continuous subcutaneous infusion (3 to 11 mcg/kg/day). With discontinuation of filgrastim therapy‚ neutrophil counts returned to baseline in most cases within 4 days.
Isolated neutrophils displayed normal phagocytic (measured by zymosan-stimulated chemoluminescence) and chemotactic (measured by migration under agarose using N-formyl-methionyl-leucyl-phenylalanine [fMLP] as the chemotaxin) activity in vitro. The absolute monocyte count was reported to increase in a dose-dependent manner in most patients receiving filgrastim; however‚ the percentage of monocytes in the differential count remained within the normal range. Absolute counts of both eosinophils and basophils did not change and were within the normal range following administration of filgrastim.
Increases in lymphocyte counts following filgrastim administration have been reported in some normal subjects and patients with cancer. White blood cell (WBC) differentials obtained during clinical trials have demonstrated a shift towards earlier granulocyte progenitor cells (left shift)‚ including the appearance of promyelocytes and myeloblasts‚ usually during neutrophil recovery following the chemotherapy-induced nadir. In addition‚ Dohle bodies‚ increased granulocyte granulation‚ and hypersegmented neutrophils have been observed.
Such changes were transient and were not associated with clinical sequelae, nor were they necessarily associated with infection.
12.3Pharmacokinetics Filgrastim products exhibit nonlinear pharmacokinetics. Clearance is dependent on filgrastim product concentration and neutrophil count: G-CSF receptor-mediated clearance is saturated by high concentration of filgrastim products and is diminished by neutropenia. In addition, filgrastim products are cleared by the kidney.
Subcutaneous administration of 3.45 mcg/kg and 11.5 mcg/kg of filgrastim resulted in maximum serum concentrations of 4 and 49 ng/mL‚ respectively‚ within 2 to 8 hours. After intravenous administration, the volume of distribution averaged 150 mL/kg and the elimination half-life was approximately 3.5 hours in both normal subjects and cancer subjects. Clearance rates of filgrastim were approximately 0.5 to 0.7 mL/minute/kg.
Single parenteral doses or daily intravenous doses‚ over a 14-day period‚ resulted in comparable half-lives. The half-lives were similar for intravenous administration (231 minutes‚ following doses of 34.5 mcg/kg) and for subcutaneous administration (210 minutes‚ following filgrastim dosages of 3.45 mcg/kg). Continuous 24-hour intravenous infusions of 20 mcg/kg over an 11 to 20-day period produced steady-state ser… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Colony-stimulating factors are glycoproteins which act on hematopoietic cells by binding to specific cell surface receptors and stimulating proliferation‚ differentiation commitment‚ and some end-cell functional activation. Endogenous G-CSF is a lineage-specific colony-stimulating factor that is produced by monocytes‚ fibroblasts, and endothelial cells. G-CSF regulates the production of neutrophils within the bone marrow and affects neutrophil progenitor proliferation‚ differentiation, and selected end-cell functions (including enhanced phagocytic ability‚ priming of the cellular metabolism associated with respiratory burst‚ antibody-dependent killing, and the increased expression of some cell surface antigens).
G-CSF is not species-specific and has been shown to have minimal direct in vivo or in vitro effects on the production or activity of hematopoietic cell types other than the neutrophil lineage.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING NIVESTYM injection is a clear, colorless, preservative-free solution supplied as: Vials Single-dose vials containing 300 mcg/mL of filgrastim-aafi solution. Dispensing packs of 10 vials (NDC 0069-0293-10). Single-dose vials containing 480 mcg/1.6 mL (300 mcg/mL) of filgrastim-aafi solution.
Dispensing packs of 10 vials (NDC 0069-0294-10). Prefilled Syringes Single-dose prefilled syringe with BD UltraSafe Plus™ Passive Needle Guard, containing 300 mcg/0.5 mL of filgrastim-aafi solution. • Pack of 1 prefilled syringe (NDC 0069-0291-01). • Pack of 10 prefilled syringes (NDC 0069-0291-10). Single-dose, prefilled syringe with BD UltraSafe Plus™ Passive Needle Guard, containing 480 mcg/0.8 mL of filgrastim-aafi solution. • Pack of 1 prefilled syringe (NDC 0069-0292-01). • Pack of 10 prefilled syringes (NDC 0069-0292-10).
The NIVESTYM syringe plunger stopper and needle cover are not made with natural rubber latex [see Dosage and Administration (2.5) ] . Storage Store NIVESTYM in the refrigerator at 2°C to 8°C (36°F to 46°F) in the original carton to protect from light. Do not leave NIVESTYM in direct sunlight.
Avoid freezing; if frozen, thaw in the refrigerator before administration. Discard NIVESTYM if frozen more than once. Avoid shaking.
Transport via a pneumatic tube has not been studied.
📦 Storage and Handling ▾
Storage Store NIVESTYM in the refrigerator at 2°C to 8°C (36°F to 46°F) in the original carton to protect from light. Do not leave NIVESTYM in direct sunlight. Avoid freezing; if frozen, thaw in the refrigerator before administration. Discard NIVESTYM if frozen more than once. Avoid shaking. Transport via a pneumatic tube has not been studied.
📋 Description ▾
11 DESCRIPTION Filgrastim-aafi is a 175 amino acid human granulocyte colony-stimulating factor (G-CSF) manufactured by recombinant DNA technology. NIVESTYM is produced by Escherichia coli ( E coli) bacteria into which has been inserted the human granulocyte colony-stimulating factor gene. NIVESTYM has a molecular weight of 18‚799 daltons.
The protein has an amino acid sequence that is identical to the natural sequence predicted from human DNA sequence analysis‚ except for the addition of an N-terminal methionine necessary for expression in E coli . Because NIVESTYM is produced in E coli ‚ the product is non-glycosylated and thus differs from G-CSF isolated from a human cell. NIVESTYM is a sterile‚ clear‚ colorless‚ preservative-free liquid containing filgrastim-aafi injection for subcutaneous or intravenous use.
The product is available in single-dose vials for subcutaneous or intravenous use and prefilled syringes for subcutaneous use. The single-dose vials contain either 300 mcg/mL or 480 mcg/1.6 mL of filgrastim-aafi. The single-dose prefilled syringes contain either 300 mcg/0.5 mL or 480 mcg/0.8 mL of filgrastim-aafi.
The final pH range of the NIVESTYM drug product solution is 3.8 to 4.3. See Table 4 below for product composition of each single-dose vial or prefilled syringe. Table 4.
Product Composition 300 mcg/mL Vial 480 mcg/1.6 mL Vial 300 mcg/0.5 mL Syringe 480 mcg/0.8 mL Syringe Filgrastim-aafi 300 mcg 480 mcg 300 mcg 480 mcg Acetate 0.59 mg 0.94 mg 0.295 mg 0.472 mg Polysorbate 80 0.04 mg 0.064 mg 0.02 mg 0.032 mg Sodium 0.035 mg 0.056 mg 0.0175 mg 0.028 mg Sorbitol 50 mg 80 mg 25 mg 40 mg Water for Injection USP q.s. ad quantity sufficient to make 1 mL 1.6 mL 0.5 mL 0.8 mL
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use). Review the steps for direct patient administration with patients and caregivers. Training by the healthcare provider should aim to ensure that patients and caregivers can successfully perform all of the steps in the Instructions for Use of NIVESTYM vial and prefilled syringe, including showing the patient or caregiver how to measure the required dose, particularly if a patient is on a dose other than the entire prefilled syringe.
If a patient or caregiver is not able to demonstrate that they can measure the dose and administer the product successfully, you should consider whether the patient is an appropriate candidate for self-administration of NIVESTYM or whether the patient would benefit from a different NIVESTYM presentation. Advise patients of the following risks and potential risks with NIVESTYM: • Rupture or enlargement of the spleen may occur. Symptoms include left upper quadrant abdominal pain or left shoulder pain.
Advise patients to report pain in these areas to their physician immediately [see Warnings and Precautions (5.1) ] . • Dyspnea, with or without fever, progressing to Acute Respiratory Distress Syndrome, may occur. Advise patients to report dyspnea to their physician immediately [see Warnings and Precautions (5.2) ] . • Serious allergic reactions may occur, which may be signaled by rash‚ facial edema‚ wheezing‚ dyspnea‚ hypotension‚ or tachycardia. Advise patients to seek immediate medical attention if signs or symptoms of hypersensitivity reaction occur [see Warnings and Precautions (5.3) ] . • In patients with sickle cell disease, sickle cell crisis and death have occurred.
Discuss potential risks and benefits for patients with sickle cell disease prior to the administration of human granulocyte colony-stimulating factors [see Warnings and Precautions (5.4) ] . • Glomerulonephritis may occur. Symptoms include swelling of the face or ankles, dark colored urine or blood in the urine, or a decrease in urine production. Advise patients to report signs or symptoms of glomerulonephritis to their physician immediately [see Warnings and Precautions (5.5) ] . • There may be an increased risk of Myelodysplastic Syndrome and/or Acute Myeloid Leukemia in patients with congenital neutropenia who receive filgrastim products and in patients with breast and lung cancer who receive filgrastim products in conjunction with chemotherapy and/or radiation therapy.
Symptoms of MDS and AML may include tiredness, fever, and easy bruising or bleeding. Advise patients to report to their physician signs and symptoms of MDS/AML [see Warnings and Precautions (5.8) ] . • Cutaneous vasculitis may occur, which may be signaled by purpura or erythema. Advise patients to report signs or symptoms of vasculitis to their physician immediately [see Warnings and Precautions (5.11) ] . • Aortitis may occur.
Symptoms may include fever, abdominal pain, malaise, back pain, and increased inflammatory markers. Advise patients to report signs and symptoms of aortitis to their physician immediately [see Warnings and Precautions (5.15) ] . Instruct patients who self-administer NIVESTYM using the prefilled syringe or single-dose vial of the: • Importance of following the applicable Instructions for Use. • Dangers of reusing needles, syringes, or unused portions of single-dose vials. • Importance of following local requirements for proper disposal of used syringes, needles, and unused vials. • Importance of informing the healthcare provider if difficulty occurs when measuring or administering partial contents of the NIVESTYM prefilled syringe.
If difficulty occurs, use of the NIVESTYM vial may be considered. • Difference in product concentration of the NIVESTYM prefilled syringe in comparison to the NIVESTYM vial. When switching patients from the NIVESTYM prefilled syringe to the NIVESTYM vial, or vice versa, ensure… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Filgrastim products exhibit nonlinear pharmacokinetics. Clearance is dependent on filgrastim product concentration and neutrophil count: G-CSF receptor-mediated clearance is saturated by high concentration of filgrastim products and is diminished by neutropenia. In addition, filgrastim products are cleared by the kidney.
Subcutaneous administration of 3.45 mcg/kg and 11.5 mcg/kg of filgrastim resulted in maximum serum concentrations of 4 and 49 ng/mL‚ respectively‚ within 2 to 8 hours. After intravenous administration, the volume of distribution averaged 150 mL/kg and the elimination half-life was approximately 3.5 hours in both normal subjects and cancer subjects. Clearance rates of filgrastim were approximately 0.5 to 0.7 mL/minute/kg.
Single parenteral doses or daily intravenous doses‚ over a 14-day period‚ resulted in comparable half-lives. The half-lives were similar for intravenous administration (231 minutes‚ following doses of 34.5 mcg/kg) and for subcutaneous administration (210 minutes‚ following filgrastim dosages of 3.45 mcg/kg). Continuous 24-hour intravenous infusions of 20 mcg/kg over an 11 to 20-day period produced steady-state serum concentrations of filgrastim with no evidence of drug accumulation over the time period investigated.
The absolute bioavailability of filgrastim after subcutaneous administration is 60% to 70%. Specific Populations Pediatric Patients The pharmacokinetics of filgrastim in pediatric patients after chemotherapy are similar to those in adult patients receiving the same weight-normalized doses, suggesting no age-related differences in the pharmacokinetics of filgrastim products [see Use in Specific Populations (8.4) ] . Renal Impairment In a study with healthy volunteers, subjects with moderate renal impairment, and subjects with end-stage renal disease (n = 4 per group), higher serum concentrations were observed in subjects with end-stage renal disease.
However, dose adjustment in patients with renal impairment is not necessary. Hepatic Impairment Pharmacokinetics and pharmacodynamics of filgrastim are similar between subjects with hepatic impairment and healthy subjects (n = 12/group). The study included 10 subjects with mild hepatic impairment (Child-Pugh Class A) and 2 subjects with moderate hepatic impairment (Child-Pugh Class B).
Therefore, NIVESTYM dose adjustment for patients with hepatic impairment is not necessary.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics In phase 1 studies involving 96 patients with various non-myeloid malignancies‚ filgrastim administration resulted in a dose-dependent increase in circulating neutrophil counts over the dose range of 1 to 70 mcg/kg/day. This increase in neutrophil counts was observed whether filgrastim was administered intravenous (1 to 70 mcg/kg twice daily)‚ subcutaneous (1 to 3 mcg/kg once daily)‚ or by continuous subcutaneous infusion (3 to 11 mcg/kg/day). With discontinuation of filgrastim therapy‚ neutrophil counts returned to baseline in most cases within 4 days.
Isolated neutrophils displayed normal phagocytic (measured by zymosan-stimulated chemoluminescence) and chemotactic (measured by migration under agarose using N-formyl-methionyl-leucyl-phenylalanine [fMLP] as the chemotaxin) activity in vitro. The absolute monocyte count was reported to increase in a dose-dependent manner in most patients receiving filgrastim; however‚ the percentage of monocytes in the differential count remained within the normal range. Absolute counts of both eosinophils and basophils did not change and were within the normal range following administration of filgrastim.
Increases in lymphocyte counts following filgrastim administration have been reported in some normal subjects and patients with cancer. White blood cell (WBC) differentials obtained during clinical trials have demonstrated a shift towards earlier granulocyte progenitor cells (left shift)‚ including the appearance of promyelocytes and myeloblasts‚ usually during neutrophil recovery following the chemotherapy-induced nadir. In addition‚ Dohle bodies‚ increased granulocyte granulation‚ and hypersegmented neutrophils have been observed.
Such changes were transient and were not associated with clinical sequelae, nor were they necessarily associated with infection.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Patients with Cancer Receiving Myelosuppressive Chemotherapy The safety and efficacy of filgrastim to decrease the incidence of infection‚ as manifested by febrile neutropenia‚ in patients with nonmyeloid malignancies receiving myelosuppressive anti-cancer drugs were established in a randomized‚ double-blind‚ placebo-controlled trial conducted in patients with small cell lung cancer (Study 1). In Study 1, patients received up to 6 cycles of intravenous chemotherapy including intravenous cyclophosphamide and doxorubicin on day 1; and etoposide on days 1, 2, and 3 of 21 day cycles.
Patients were randomized to receive filgrastim (n = 99) at a dose of 230 mcg/m 2 (4 to 8 mcg/kg/day) or placebo (n = 111). Study drug was administered subcutaneously daily beginning on day 4, for a maximum of 14 days. A total of 210 patients were evaluable for efficacy and 207 were evaluable for safety.
The demographic and disease characteristics were balanced between arms with a median age of 62 (range 31 to 80) years; 64% males; 89% Caucasian; 72% extensive disease and 28% limited disease. The main efficacy endpoint was the incidence of febrile neutropenia. Febrile neutropenia was defined as an ANC < 1,000/mm 3 and temperature > 38.2°C.
Treatment with filgrastim resulted in a clinically and statistically significant reduction in the incidence of infection‚ as manifested by febrile neutropenia, 40% for filgrastim-treated patients and 76% for placebo-treated patients (p < 0.001). There were also statistically significant reductions in the incidence and overall duration of infection manifested by febrile neutropenia; the incidence, severity and duration of severe neutropenia (ANC < 500/mm 3 ); the incidence and overall duration of hospital admissions; and the number of reported days of antibiotic use.
14.2Patients with Acute Myeloid Leukemia Receiving Induction or Consolidation Chemotherapy The safety and efficacy of filgrastim to reduce the time to neutrophil recovery and the duration of fever, following induction or consolidation chemotherapy treatment of patients with acute myeloid leukemia (AML) was established in a randomized, double-blind‚ placebo-controlled‚ multi-center trial in patients with newly diagnosed, de novo AML (Study 4). In Study 4 the initial induction therapy consisted of intravenous daunorubicin days 1, 2, and 3; cytosine arabinoside days 1 to 7; and etoposide days 1 to 5.
Patients were randomized to receive subcutaneous filgrastim (n = 259) at a dose of 5 mcg/kg/day or placebo (n = 262) from 24 hours after the last dose of chemotherapy until neutrophil recovery (ANC ≥ 1,000/mm 3 for 3 consecutive days or ≥ 10,000/mm 3 for 1 day) or for a maximum of 35 days. The demographic and disease characteristics were balanced between arms with a median age of 54 (range 16 to 89) years; 54% males; initial white blood cell count (65% < 25,000/mm 3 and 27% > 100,000/mm 3 ); 29% unfavorable cytogenetics.
The main efficacy endpoint was median duration of severe neutropenia defined as neutrophil count < 500/mm 3 . Treatment with filgrastim resulted in a clinically and statistically significant reduction in median number of days of severe neutropenia, filgrastim-treated patients 14 days, placebo-treated patients 19 days (p = 0.0001: difference of 5 days (95% CI: -6.0, -4.0)). There was a reduction in the median duration of intravenous antibiotic use, filgrastim-treated patients: 15 days versus placebo-treated patients: 18.5 days; a reduction in the median duration of hospitalization, filgrastim-treated patients: 20 days versus placebo-treated patients: 25 days.
There were no statistically significant differences between the filgrastim and the placebo groups in complete remission rate (69% - filgrastim, 68% - placebo), median time to progression of all randomized patients (165 days - filgrastim, 186 days - placebo), or median overall survival (380 days - filgrastim, 425 days - placebo).
14.3Patients with Cancer Undergoing… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility The carcinogenic potential of filgrastim products has not been studied. Filgrastim failed to induce bacterial gene mutations in either the presence or absence of a drug metabolizing enzyme system. Filgrastim had no observed effect on the fertility of male or female rats at doses up to 500 mcg/kg.
13.2Animal Toxicology and Pharmacology Filgrastim was administered to monkeys‚ dogs‚ hamsters‚ rats‚ and mice as part of a nonclinical toxicology program, which included studies up to 1 year duration. In the repeated-dose studies‚ changes observed were attributable to the expected pharmacological actions of filgrastim (i.e.‚ dose-dependent increases in white blood cell counts‚ increased circulating segmented neutrophils‚ and increased myeloid: erythroid ratio in bone marrow). Histopathologic examination of the liver and spleen revealed evidence of ongoing extramedullary granulopoiesis, and dose-related increases in spleen weight were seen in all species.
These changes all reversed after discontinuation of treatment.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility The carcinogenic potential of filgrastim products has not been studied. Filgrastim failed to induce bacterial gene mutations in either the presence or absence of a drug metabolizing enzyme system. Filgrastim had no observed effect on the fertility of male or female rats at doses up to 500 mcg/kg.
📄 Patient Package Insert ▾
Patient Information NIVESTYM ( Neye-ves-tim ) (filgrastim-aafi) injection What is NIVESTYM? NIVESTYM is a man-made form of granulocyte colony-stimulating factor (G-CSF). G-CSF is a substance produced by the body.
It stimulates the growth of neutrophils, a type of white blood cell important in the body's fight against infection. Do not take NIVESTYM if you have had a serious allergic reaction to human G-CSFs such as filgrastim products or pegfilgrastim products. Before you take NIVESTYM, tell your healthcare provider about all of your medical conditions, including if you: • have a sickle cell disorder. • have kidney problems. • are receiving radiation therapy. • are pregnant or plan to become pregnant.
It is not known if NIVESTYM will harm your unborn baby. • are breastfeeding or plan to breastfeed. It is not known if NIVESTYM passes into your breast milk. Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements.
How will I receive NIVESTYM? • NIVESTYM injections can be given by a healthcare provider by intravenous (IV) infusion or under your skin (subcutaneous injection). Your healthcare provider may decide subcutaneous injections can be given at home by you or your caregiver. If NIVESTYM is given at home, see the detailed " Instructions for Use " that comes with your NIVESTYM for information on how to prepare and inject a dose of NIVESTYM. • You and your caregiver should be shown how to prepare and inject NIVESTYM before you use it, by your healthcare provider. • You should not try to inject a dose of NIVESTYM less than 0.3 mL (180 mcg) from a NIVESTYM prefilled syringe.
A dose less than 0.3 mL cannot be accurately measured using the NIVESTYM prefilled syringe. • Your healthcare provider will tell you how much NIVESTYM to inject and when to inject it. Do not change your dose or stop NIVESTYM unless your healthcare provider tells you to. • If you are receiving NIVESTYM because you are also receiving chemotherapy, your dose of NIVESTYM should be injected at least 24 hours before or 24 hours after your dose of chemotherapy. Your healthcare provider will do blood tests to monitor your white blood cell count, and if necessary, adjust your NIVESTYM dose. • If you miss a dose of NIVESTYM, talk to your healthcare provider about when you should give your next dose.
What are the possible side effects of NIVESTYM? NIVESTYM may cause serious side effects, including: • Spleen rupture. Your spleen may become enlarged and can rupture.
A ruptured spleen can cause death. Call your healthcare provider right away if you have pain in the left upper stomach (abdomen) area or your left shoulder. • A serious lung problem called acute respiratory distress syndrome (ARDS). Call your healthcare provider or get emergency medical help right away if you have shortness of breath with or without a fever, trouble breathing, or a fast rate of breathing. • Serious allergic reactions.
NIVESTYM can cause serious allergic reactions. These reactions can cause a rash over your whole body, shortness of breath, wheezing, dizziness, swelling around your mouth or eyes, fast heart rate, and sweating. If you have any of these symptoms, stop using NIVESTYM and call your healthcare provider or get emergency medical help right away. • Sickle cell crises.
You may have a serious sickle cell crisis, which could lead to death, if you have a sickle cell disorder and receive NIVESTYM. Call your healthcare provider right away if you have symptoms of sickle cell crisis such as pain or difficulty breathing. • Kidney injury (glomerulonephritis). NIVESTYM can cause kidney injury.
Call your healthcare provider right away if you develop any of the following symptoms: o swelling of your face or ankles o blood in your urine or dark colored urine o you urinate less than usual • Capillary leak syndrome. NIVESTYM can cause fluid to leak from blood vessels into your body's tissues. This condition i… [Excerpted — this section continues on DailyMed.]
📖 Instructions for Use ▾
Instructions for Use NIVESTYM (Neye-ves-tim) (filgrastim-aafi) injection Single-Dose Prefilled Syringe Important Read the Patient Information for important information you need to know about NIVESTYM before using this Instructions for Use. Before you use a NIVESTYM prefilled syringe, read this important information. Storing your prefilled syringe • Store the NIVESTYM prefilled syringe in the refrigerator between 36˚F to 46˚F (2˚C to 8˚C). • Do not freeze. • Keep the NIVESTYM prefilled syringe in the original carton to protect from light or physical damage. • Take the prefilled syringe out of the refrigerator 30 minutes before use and allow it to reach room temperature before preparing an injection. • The NIVESTYM prefilled syringe may be allowed to reach room temperature for up to 24 hours.
Throw away (dispose of) any NIVESTYM prefilled syringe that has been left at room temperature for longer than 24 hours. • After you inject your dose, throw away (dispose of) any unused NIVESTYM left in the prefilled syringe. Do not save unused NIVESTYM in the prefilled syringe for later use. • Keep NIVESTYM and all medicines out of the reach of children. Using your prefilled syringe • It is important that you do not try to give the injection unless you or your caregiver has received training from your healthcare provider. • You should not inject a dose of NIVESTYM less than 0.3 mL (180 mcg) from a NIVESTYM prefilled syringe.
A dose less than 0.3 mL cannot be accurately measured using the NIVESTYM prefilled syringe. • Make sure the name NIVESTYM appears on the carton and prefilled syringe label. • Do not use a NIVESTYM prefilled syringe after the expiration date on the label. • Do not shake the NIVESTYM prefilled syringe. • The prefilled syringe has a needle guard that needs to be activated to cover the needle after the injection is given. The needle guard will help prevent needle stick injuries to anyone who handles the prefilled syringe. • Do not remove the needle cover from the prefilled syringe until you are ready to inject. • Do not use the NIVESTYM prefilled syringe if the needle cover is missing. • Do not use the prefilled syringe if the carton is open or damaged . • Do not use a prefilled syringe if it has been dropped on a hard surface.
The prefilled syringe may be broken even if you cannot see the break. Use a new prefilled syringe. Call your healthcare provider if you have any questions.
About the NIVESTYM prefilled syringe • NIVESTYM prefilled syringes come in two strengths. Depending on your prescription, you will receive NIVESTYM prefilled syringes that contain 300 mcg/0.5 mL or 480 mcg/0.8 mL of medicine. Your healthcare provider will determine the dose in milliliters (mL) that you will need to give based on your body weight. • When you receive your NIVESTYM prefilled syringes, always check to see that the: o name NIVESTYM appears on the carton and prefilled syringe label. o expiration date on the prefilled syringe label has not passed.
You should not use a prefilled syringe after the date on the label. o strength of NIVESTYM (number of micrograms on the carton containing the prefilled syringe) is the same as what your healthcare provider prescribed. NIVESTYM prefilled syringe parts (see Figure A ). NIVESTYM 300 mcg/0.5 mL prefilled syringe is shown as an example.
Figure A What you need for your injection Included in the carton: • 1 new NIVESTYM prefilled syringe (see Figure A above) Not included in the carton (see Figure B ) • 1 adhesive bandage • 1 alcohol wipe • 1 cotton ball or gauze • sharps disposal container Figure B Preparing the NIVESTYM prefilled syringe Step 1: Find a clean, well-lit flat work surface. Step 2: Take the carton containing the NIVESTYM prefilled syringe out of the refrigerator and leave it unopened on your work surface for at least 30 minutes so that it reaches room temperature.
Put the original carton with any unused prefilled syringes back in the refrigerator. • Do not shake the prefilled syringe. •… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 1 mL Vial Label NDC 0069-0293-01 Rx Only Nivestym™ (filgrastim-aafi) Injection 300 mcg/mL 1 mL Single-Dose Vial Pfizer PRINCIPAL DISPLAY PANEL - 1 mL Vial Label
PRINCIPAL DISPLAY PANEL - 1 mL Vial Carton 10 x 300 mcg/mL Single-Dose Vials (containing 1 mL) Discard unused portion NDC 0069-0293-10 Rx Only Nivestym™ (filgrastim-aafi) Injection 300 mcg/mL A recombinant Granulocyte Colony Stimulating Factor (rG-CSF) derived from E. coli For Intravenous or Subcutaneous Use Only Sterile Solution - No Preservative Pfizer Oncology PRINCIPAL DISPLAY PANEL - 1 mL Vial Carton
PRINCIPAL DISPLAY PANEL - 1.6 mL Vial Label NDC 0069-0294-01 Rx Only Nivestym™ (filgrastim-aafi) Injection 480 mcg/1.6 mL (300 mcg/mL) 1.6 mL Single-Dose Vial Pfizer PRINCIPAL DISPLAY PANEL - 1.6 mL Vial Label
PRINCIPAL DISPLAY PANEL - 1.6 mL Vial Carton 10 x 480 mcg/1.6 mL Single-Dose Vials (containing 1.6 mL) Discard unused portion NDC 0069-0294-10 Rx Only Nivestym™ (filgrastim-aafi) Injection 480 mcg/1.6 mL (300 mcg/mL) A recombinant Granulocyte Colony Stimulating Factor (rG-CSF) derived from E. coli For Intravenous or Subcutaneous Use Only Sterile Solution - No Preservative Pfizer Oncology PRINCIPAL DISPLAY PANEL - 1.6 mL Vial Carton
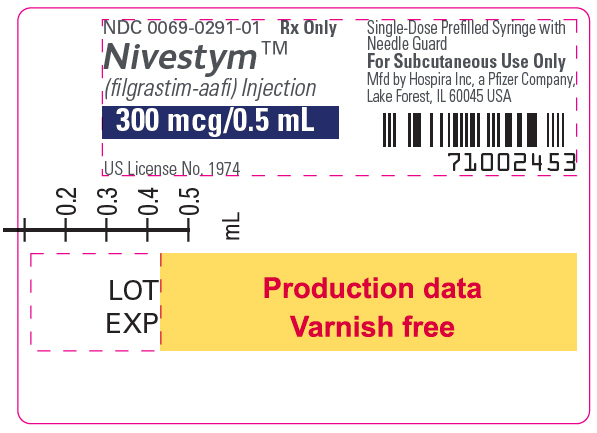
PRINCIPAL DISPLAY PANEL - 0.5 mL Syringe Label NDC 0069-0291-01 Rx Only Nivestym™ (filgrastim-aafi) Injection 300 mcg/0.5 mL Single-Dose Prefilled Syringe with Needle Guard For Subcutaneous Use Only Mfd by Hospira Inc, a Pfizer Company, Lake Forest, IL 60045 USA US License No. 1974 PRINCIPAL DISPLAY PANEL - 0.5 mL Syringe Label
PRINCIPAL DISPLAY PANEL - 0.5 mL Syringe Carton 1 x 300 mcg/0.5 mL Single-Dose Prefilled Syringe with Needle Guard Discard unused portion. Refrigerate at 2° to 8°C (36° to 46°F). Do Not Freeze or Shake.
Protect from light. Subcutaneous Use Only Nivestym™ (filgrastim-aafi) Injection 300 mcg/0.5 mL A recombinant Granulocyte Colony Stimulating Factor (rG-CSF) derived from E. coli Pfizer Oncology NDC 0069-0291-01 Rx Only The syringe plunger stopper and needle cover are not made with natural rubber latex. Sterile Solution - No Preservative PRINCIPAL DISPLAY PANEL - 0.5 mL Syringe Carton
PRINCIPAL DISPLAY PANEL - 0.5 mL Syringe Carton - NDC 0069-0291-10 NDC 0069-0291-10 Rx Only Nivestym™ (filgrastim-aafi) Injection 300 mcg/0.5 mL 10 x 300 mcg/0.5 mL Single-Dose Prefilled Syringe with Needle Guard Discard unused portion. A recombinant Granulocyte Colony Stimulating Factor (rG-CSF) derived from E. coli Subcutaneous Use Only Sterile Solution - No Preservative Pfizer Oncology PRINCIPAL DISPLAY PANEL - 0.5 mL Syringe Carton - NDC 0069-0291-10
PRINCIPAL DISPLAY PANEL - 0.5 mL Syringe Carton - NDC 0069-0291-01 NDC 0069-0291-01 Rx Only Nivestym™ (filgrastim-aafi) Injection 300 mcg/0.5 mL A recombinant Granulocyte Colony Stimulating Factor (rG-CSF) derived from E. coli 1 x 300 mcg/0.5 mL Single-Dose Prefilled Syringe with Needle Guard Discard unused portion. Subcutaneous Use Only Sterile Solution - No Preservative Pfizer Oncology PRINCIPAL DISPLAY PANEL - 0.5 mL Syringe Carton - NDC 0069-0291-01
PRINCIPAL DISPLAY PANEL - 0.8 mL Syringe Label NDC 0069-0292-01 Rx Only Nivestym™ (filgrastim-aafi) Injection 480 mcg/0.8 mL Single-Dose Prefilled Syringe with Needle Guard For Subcutaneous Use Only Mfd by Hospira Inc, a Pfizer Company, Lake Forest, IL 60045 USA US License No. 1974 PRINCIPAL DISPLAY PANEL - 0.8 mL Syringe Label
PRINCIPAL DISPLAY PANEL - 0.8 mL Syringe Carton 1 x 480 mcg/0.8 mL Single-Dose Prefilled Syringe with Needle Guard Discard unused portion. Refrigerate at 2° to 8°C (36° to 46°F). Do Not Freeze or Shake.
Protect from light. Subcutaneous Use Only NDC 0069-0292-01 Rx Only Nivestym™ (filgrastim-aafi) Injection 480 mcg/0.8 mL A recombinant Granulocyte Colony Stimulating Factor (rG-CSF) derived from E. coli Pfizer Oncology The syringe plunger stopper and needle cover are not made with natural rubber latex. Sterile Solution - No Preservative PRINCIPAL DISPLAY PANEL - 0.8 mL Syringe C… [Excerpted — this section continues on DailyMed.]
Medicaid utilization & spend
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |