
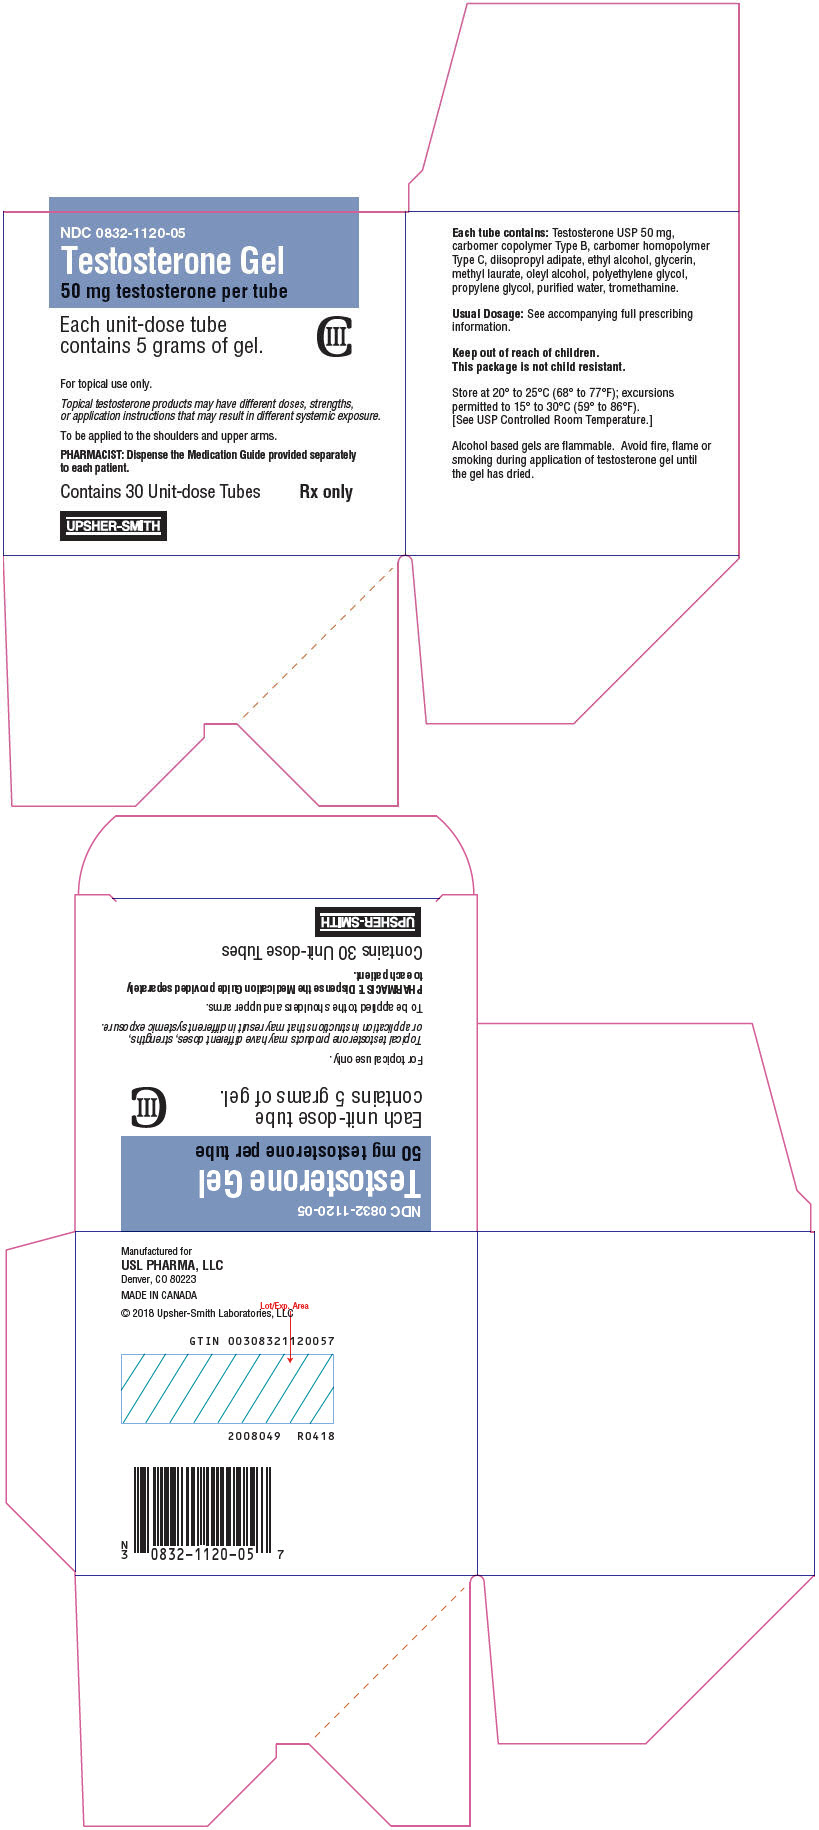
Testosterone 50 mg/5g Gel
Other active recalls for Testosterone (different manufacturers) — 4 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Androgen class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Testosterone topical is used to treat low or no testosterone levels in men. Testosterone is in a class of medications called androgenic hormones. Testosterone is a male sex hormone responsible for development and functioning of male sexual organs and typical male characteristics. Testosterone topical works by replacing the testosterone that is normally produced by the body.
Read the full MedlinePlus article ↗- Testosterone replacement is specifically for men whose bodies aren't making enough testosterone because of a medical condition — like a problem with the testes themselves (primary...
- What exactly is testosterone replacement therapy for — do I really need it?
- Yes, this is a serious concern. Children who accidentally touch the gel on your skin or clothing can absorb testosterone and develop early puberty signs — things like pubic hair gr...
- I use the gel — do I really need to worry about my kids or partner being exposed to it?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Testosterone — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII 809Y72KV36
A synthetic polymer made from acrylic acid and crosslinked with allyl pentaerythritol. It's used as a thickening agent and gelling ingredient in creams, gels, and lotions to create the proper texture and help the medicine spread and stay on the skin.
-
UNII 4Q93RCW27E
A synthetic polymer made from acrylic acid that's crosslinked for stability. It acts as a thickener and gelling agent in creams and gels, helping the medicine spread evenly and maintain its texture.
-
UNII P7E6YFV72X
Diisopropyl adipate is a clear, oily liquid derived from adipic acid. It acts as a plasticizer and solvent in medicines, helping soften coatings and improve how the drug dissolves or spreads in the body.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII 8IPS6BI6KW
Methyl laurate is a fatty acid ester derived from lauric acid. It's used in medicines as a solvent and penetration enhancer to help active ingredients dissolve and absorb effectively.
-
UNII 172F2WN8DV
A fatty alcohol derived from animal or plant oils. It acts as an emollient and helps stabilize emulsions, allowing oil and water to mix evenly in the medication.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 023C2WHX2V
Tromethamine is a chemical buffer that helps maintain the proper acidity level in liquid medicines. It neutralizes acids and stabilizes the solution so the medication remains effective and safe throughout its shelf life.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.405 | $60.80 / 150 g |
| Medicaid paysCMS SDUD · 12 mo | $0.8219 | $123.29 / 150 g |
| Medicare drug plans payPart D · Q2 2026 | $2.07 | $311.03 / 150 g |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Testosterone 10 mg/g 00591-3217-30 | Actavis | 30 packets | $0.405 | AB1 | Availability likely | — |
| Testosterone 50 mg/5gthis 00832-1120-35 | Upsher-Smith | 30 packets | $0.405 | BX | Availability likely | — |
| Testosterone Gel, 1% 10 mg/g 21922-0019-02 | Encube | 30 packets | $0.405 | AB1 | Availability likely | — |
| Testosterone 50 mg/5g 64380-0152-02 | Strides | 30 doses | $0.405 | AB1 | Availability likely | — |
| Testosterone 50 mg/5g 66993-0955-30 | Prasco | 30 packets | $0.405 | AB1 | Availability likely | — |
| Testosterone 50 mg/5g 00591-3524-30 | Actavis | 30 tubes | $0.746 | AB2 | Availability likely | +84% |
| Vogelxo 50 mg/5g 00245-0871-05 | Upsher-Smith | 30 tubes | $3.778 | BX | FDA listed | +832% |
| Testim 50 mg/5g 66887-0001-05 | Endo | 30 tubes | $3.784 | AB2 | Availability likely | +834% |
| AndroGel 10 mg/g 17139-0550-30 | ASCEND | 30 packets | — | AB1 | Discontinued | — |
| Testosterone Gel, 1% 10 mg/g 72162-1274-03 | Bryant | 30 packets | — | AB1 | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8785426 ↗ | Method of use | U-1531 | Feb 11, 2034 |
| US 9662340 ↗ | Method of use | U-1531 | Feb 11, 2034 |
| US 9295675 ↗ | Method of use | U-1531 | Feb 11, 2034 |
| US 8785426 ↗ | Method of use | U-1531 | Feb 11, 2034 |
| US 9662340 ↗ | Method of use | U-1531 | Feb 11, 2034 |
| US 9295675 ↗ | Method of use | U-1531 | Feb 11, 2034 |
Is there a generic version of TESTOSTERONE 50 MG/5 GRAM PKT?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 00832-1120-05 | 30 TUBE in 1 CARTON (0832-1120-05) / 5 g in 1 TUBE (0832-1120-65) | $0.7461 / g | $111.92 | 2014-06-16 | Active |
| 00832-1120-35 You're viewing this | 30 PACKET in 1 CARTON (0832-1120-35) / 5 g in 1 PACKET (0832-1120-89) | $0.4053 / g | $60.79 | 2014-06-16 | Active |
This pack has the lowest per-g cost of the 2 priced pack sizes ($0.4053 NADAC).
This pack accounts for about 41% of this product's recent Medicaid fills; most go to a different pack size. See all packs ↓
Pack size FAQ
What quantity is in NDC 00832-1120-35?
What NDC number is used to bill for this package of Testosterone 50 mg/5g Gel?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SECONDARY EXPOSURE TO TESTOSTERONE Virilization has been reported in children who were secondarily exposed to testosterone gel [see Warnings and Precautions (5.2) and Adverse Reactions (6.2) ] . Children should avoid contact with unwashed or unclothed application sites in men using testosterone gel [see Dosage and Administration (2.2) and Warnings and Precautions (5.2) ] . Healthcare providers should advise patients to strictly adhere to recommended instructions for use [see Dosage and Administration (2.2) , Warnings and Precautions (5.2) and Patient Counseling Information (17) ] .
WARNING: SECONDARY EXPOSURE TO TESTOSTERONE See full prescribing information for complete boxed warning Virilization has been reported in children who were secondarily exposed to testosterone gel. ( 5.2 , 6.2 ) Children should avoid contact with unwashed or unclothed application sites in men using testosterone gel. ( 2.2 , 5.2 ) Healthcare providers should advise patients to strictly adhere to recommended instructions for use.
( 2.2 , 5.2 , 17 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Testosterone gel is indicated for replacement therapy in adult males for conditions associated with a deficiency or absence of endogenous testosterone: Primary hypogonadism (congenital or acquired): testicular failure due to cryptorchidism, bilateral torsion, orchitis, vanishing testis syndrome, orchiectomy, Klinefelter's syndrome, chemotherapy, or toxic damage from alcohol or heavy metals. These men usually have low serum testosterone levels and gonadotropins (follicle-stimulating hormone [FSH], luteinizing hormone [LH]) above the normal range.
Hypogonadotropic hypogonadism (congenital or acquired): gonadotropin or luteinizing hormone-releasing hormone (LHRH) deficiency or pituitary-hypothalamic injury from tumors, trauma, or radiation. These men have low testosterone serum levels but have gonadotropins in the normal or low range. Limitations of Use: Safety and efficacy of testosterone gel in men with "age-related hypogonadism" (also referred to as "late-onset hypogonadism") have not been established.
Safety and efficacy of testosterone gel in males less than 18 years old have not been established [see Use in Specific Populations (8.4) ] . Topical testosterone products may have different doses, strengths, or application instructions that may result in different systemic exposure [see Dosage and Administration (2) and Clinical Pharmacology (12.3) ] . Testosterone gel is an androgen indicated for testosterone replacement therapy in males for conditions associated with a deficiency or absence of endogenous testosterone: Primary hypogonadism (congenital or acquired).
( 1 ) Hypogonadotropic hypogonadism (congenital or acquired). ( 1 ) Limitations of Use: Safety and efficacy of testosterone gel in men with age-related hypogonadism have not been established ( 1 ) Safety and efficacy of testosterone gel in males less than 18 years old have not been established ( 8.4 ) Topical testosterone products may have different doses, strengths, or application instructions that may result in different systemic exposure ( 1 , 12.3 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Prior to initiating testosterone gel, confirm the diagnosis of hypogonadism by ensuring that serum testosterone concentrations have been measured in the morning on at least two separate days and that these serum testosterone concentrations are below the normal range. Prior to initiating testosterone gel, confirm the diagnosis of hypogonadism by ensuring that serum testosterone has been measured in the morning on at least two separate days and that these concentrations are below the normal range ( 2 ).
Recommended starting dose for adult males: 50 mg of testosterone (one tube or one packet or 4 pump actuations) applied topically once daily at approximately the same time each day. ( 2.1 ) Apply to clean, dry, intact skin of the shoulders and/or upper arms. Do not apply testosterone gel to the genitals or abdomen.
( 2.1 , 2.2 ) If morning pre-dose serum testosterone concentration is below the normal range, increase dose to 100 mg. ( 2.1 ) Pre-dose serum testosterone concentration should be assessed periodically. ( 2.1 ) Patients should wash hands with soap and water immediately after applying testosterone gel and cover application site(s) with clothing after gel has dried.
Wash the application sites thoroughly with soap and water prior to any situation where skin-to-skin contact of the application site with another person is anticipated. ( 2.2 )
2.1Dosing and Dose Adjustment The recommended starting dose of testosterone gel is 50 mg of testosterone (one tube, one packet, or 4 pump actuations) applied topically once daily at approximately the same time each day to clean, dry intact skin of the shoulders and/or upper arms. Dose Adjustment To ensure proper dosing, serum testosterone concentrations should be measured. Morning, pre-dose serum testosterone concentrations should be measured approximately 14 days after initiation of therapy to ensure proper serum testosterone concentrations are achieved.
If the serum testosterone concentration is below the normal range (300 ng/dL to 1,000 ng/dL), the daily testosterone gel dose may be increased from 50 mg testosterone (one tube, one packet, or 4 pump actuations) to 100 mg of testosterone (two tubes, two packets, or 8 pump actuations) once daily. The maximum recommended dose of testosterone gel is 100 mg once daily.
2.2Administration Instructions Unit-Dose Tube or Packet Upon opening the tube or packet the entire contents should be squeezed into the palm of the hand and immediately applied to the shoulders and/or upper arms (area of application should be limited to the area that will be covered by the patient's short sleeve t-shirt [ see figure below ]). Table 1 has specific dosing guidelines for when the unit-dose tubes or packets are used. Table 1: Specific Dosing Guideline for Using the Unit-Dose Tubes or Packets Prescribed Daily Dose Number of Unit-Dose Tubes or Packets Application Method 50 mg testosterone One unit-dose tube or packet (once daily) Apply one unit-dose tube or packet to one upper arm and shoulder.
100 mg testosterone Two unit-dose tubes or packets (once daily) Apply one unit-dose tube or packet to one upper arm and shoulder and then apply one unit-dose tube or packet to the opposite upper arm and shoulder. Multi-Dose Metered Pump Patients should be instructed to prime the pump before using it for the first time by fully depressing the pump mechanism (actuation) 3 times and discard this portion of the product to assure precise dose delivery. After the priming procedure, patients should completely depress the pump one time (actuation) for every 12.5 mg of testosterone required to achieve the daily prescribed dosage.
Table 2 has specific dosing guidelines for when the metered pump is used. Table 2: Specific Dosing Guidelines for Using the Multi-Dose Pump Prescribed Daily Dose Number of Pump Actuations Application Method 50 mg testosterone 4 (once daily) Apply 4 pump actuations to one upper arm and shoulder 100 mg testosterone 8 (once daily) A…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Testosterone gel is a clear to translucent hydroalcoholic topical gel for topical use available in unit-dose tubes, unit-dose packets, and multiple-dose metered pumps. Each tube or packet provides 50 mg testosterone in 5 g of gel. One pump actuation delivers 12.5 mg testosterone in 1.25 g of gel (4 actuations = 50 mg testosterone).
Topical Gel available as: 50 mg of testosterone in a unit-dose tube. ( 3 ) 50 mg of testosterone in a unit-dose packet. ( 3 ) 12.5 mg of testosterone per one pump actuation in a metered-dose pump.
( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Testosterone gel is contraindicated in men with carcinoma of the breast or known or suspected carcinoma of the prostate [see Warnings and Precautions (5.1) ] . Testosterone gel is contraindicated in women who are pregnant. Testosterone gel can cause virilization of the female fetus when administered to a pregnant woman.
Pregnant women need to be aware of the potential for skin transfer of testosterone from men treated with testosterone gel. If a pregnant woman is exposed to testosterone gel, she should be apprised of the potential hazard to the fetus [see Warnings and Precautions (5.2) and Use in Specific Populations (8.1) ]. Men with known carcinoma of the breast or known or suspected carcinoma of the prostate.
( 4 , 5.1 ) Women who are pregnant. Testosterone may cause fetal harm. ( 4 , 8.1 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Monitor patients with benign prostatic hyperplasia (BPH) for worsening of signs and symptoms of BPH. ( 5.1 ) Avoid unintentional exposure of women or children to testosterone gel. Secondary exposure to testosterone can produce signs of virilization.
Testosterone gel should be discontinued until the cause of virilization is identified. ( 5.2 ) Venous thromboembolism (VTE), including deep vein thrombosis (DVT) and pulmonary embolism (PE), have been reported in patients using testosterone products. Evaluate patients with signs or symptoms consistent with DVT or PE.
( 5.4 ) Some postmarketing studies have shown an increased risk of myocardial infarction and stroke associated with use of testosterone replacement therapy. ( 5.5 ) Exogenous administration of androgens may lead to azoospermia. ( 5.8 ) Edema, with or without congestive heart failure, may be a complication in patients with preexisting cardiac, renal, or hepatic disease.
( 5.10 ) Sleep apnea may occur in those with risk factors. ( 5.12 ) Monitor prostate specific antigen (PSA), hematocrit, and lipid concentrations periodically. ( 5.1 , 5.3 , 5.13 ) Testosterone gel is flammable until dry.
( 5.16 )
5.1Worsening of Benign Prostatic Hyperplasia (BPH) and Potential Risk of Prostate Cancer Men with BPH treated with androgens are at an increased risk for worsening of signs and symptoms of BPH. Monitor patients with BPH for worsening signs and symptoms. Patients treated with androgens may be at increased risk for prostate cancer. Evaluate patients for prostate cancer prior to initiating and during treatment with androgens [see Contraindications (4) ].
5.2Potential for Secondary Exposure to Testosterone Cases of secondary exposure resulting in virilization of children have been reported in postmarketing surveillance. Signs and symptoms have included enlargement of the penis or clitoris, development of pubic hair, increased erections and libido, aggressive behavior, and advanced bone age. In most cases, these signs and symptoms regressed with removal of the exposure to testosterone gel.
In a few cases, however, enlarged genitalia did not fully return to age-appropriate normal size, and bone age remained modestly greater than chronological age. The risk of transfer was increased in some of these cases by not adhering to precautions for the appropriate use of the topical testosterone product. Children and women should avoid contact with unwashed or unclothed application sites in men using testosterone gel [see Dosage and Administration (2.2) , Use in Specific Populations (8.1) and Clinical Pharmacology (12.3) ] .
Inappropriate changes in genital size or development of pubic hair or libido in children, or changes in body hair distribution, significant increase in acne, or other signs of virilization in adult women should be brought to the attention of a physician and the possibility of secondary exposure to testosterone gel should also be brought to the attention of a physician. Testosterone gel should be promptly discontinued until the cause of virilization has been identified.
5.3Polycythemia Increases in hematocrit, reflective of increases in red blood cell mass, may require lowering or discontinuation of testosterone. Check hematocrit prior to initiating treatment. It would also be appropriate to re-evaluate the hematocrit 3 to 6 months after starting treatment, and then annually.
If hematocrit becomes elevated, stop therapy until hematocrit decreases to an acceptable concentration. An increase in red blood cell mass may increase the risk of thromboembolic events.
5.4Venous Thromboembolism There have been postmarketing reports of venous thromboembolic events, including deep vein thrombosis (DVT) and pulmonary embolism (PE), in patients using testosterone products, such as testosterone gel. Evaluate patients who report signs and symptoms of pain, edema, warmth and erythema in the lower extremity for DVT and those who present with acute shortness of…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (incidence ≥ 2% of the testosterone gel patients and greater than placebo) are application site reactions and increased hematocrit. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact UPSHER-SMITH LABORATORIES, LLC at 1-855-899-9180 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In a controlled clinical study, 304 patients were treated with testosterone gel 50 mg or 100 mg or placebo gel for up to 90 days. Two hundred-five (205) patients received testosterone gel 50 mg or 100 mg daily and 99 patients received placebo.
Subjects could be counted in both testosterone gel treatment groups if they received both 50 mg and 100 mg at different points in the study and experienced an adverse reaction at both dose levels. Adverse reactions reported by ≥1% of the testosterone gel patients and greater than placebo are listed in Table 3. Table 3: Incidence of Adverse Reactions (Reported by ≥1% of the Testosterone Gel Patients and Greater than Placebo) in the Controlled Clinical Trial Through 90 Days Event Testosterone Gel 50 mg (n=103) Testosterone Gel 100 mg (n=149) Placebo (n=99) Application Site Reactions 2% 4% 3% Blood Pressure Increased 1% 1% 0% Gynecomastia 1% 0% 0% Headache 1% 1% 0% Hematocrit/Hemoglobin Increased 1% 2% 0% Hot Flushes 1% 0% 0% Insomnia 1% 0% 0% Mood Swings 1% 0% 0% Smell Disorder 1% 0% 0% Spontaneous Penile Erection 1% 0% 0% Taste Disorder 1% 1% 0% The following adverse reactions occurred in fewer than 1% of patients but were greater in testosterone gel groups compared to the placebo group: activated partial thromboplastin time prolonged, blood creatinine increased, prothrombin time prolonged, appetite increased, sensitive nipples, and acne.
In this clinical trial of testosterone gel, six patients had adverse events that led to their discontinuation. These events included: depression with suicidal ideation, urinary tract infection, mood swings and hypertension. No testosterone gel patients discontinued due to skin reaction.
In one foreign Phase 3 trial, one subject discontinued due to a skin-related adverse event. In the pivotal U.S. and European Phase 3 trials combined, at the 50 mg dosage strength, the percentage of subjects reporting clinically notable increases in hematocrit or hemoglobin were similar to placebo. However, in the 100 mg dose group, 2.3% and 2.8% of patients had a clinically notable increase in hemoglobin (≥ 19 g/dL) or hematocrit (≥ 58%), respectively, compared to 1.0% and 1.5% of patients in the placebo group, respectively.
In the combined U.S. and European open label extension studies, approximately 140 patients received testosterone gel for at least 6 months. The results from these studies are consistent with those reported for the U.S. controlled clinical trial.
6.2Postmarketing Experience The following adverse reactions have been identified during post-approval use of testosterone gel products. Because the reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Secondary Exposure to Testosterone in Children Cases of secondary exposure to testosterone resulting in virilization of children have been reported in postmarketing surveillance of testosterone gel products.
Signs and symptoms of these reported cases have included enlargement of the clitoris (with surgical intervention) or of the penis, development of pubic hair, increased erections and libido, aggressive behavior, and advanced bone age. In most cases with a reported outcome, these signs and symptoms were reported to have regressed with removal of the testoster…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Androgens may decrease blood glucose and therefore may decrease insulin requirements in diabetic patients. ( 7.1 ) Changes in anticoagulant activity may be seen with androgens. More frequent monitoring of International Normalized Ratio (INR) and prothrombin time is recommended in patients taking warfarin.
( 7.2 ) Use of testosterone with corticosteroids may result in increased fluid retention. Use with caution, particularly in patients with cardiac, renal or hepatic disease. ( 7.3 )
7.1Insulin Changes in insulin sensitivity or glycemic control may occur in patients treated with androgens. In diabetic patients, the metabolic effects of androgens may decrease blood glucose and, therefore, may necessitate a decrease in the dose of anti-diabetic medication.
7.2Oral Anticoagulants Changes in anticoagulant activity may be seen with androgens, therefore more frequent monitoring of international normalized ratio (INR) and prothrombin time are recommended in patients taking warfarin, especially at the initiation and termination of androgen therapy.
7.3Corticosteroids The concurrent use of testosterone with corticosteroids may result in increased fluid retention and requires careful monitoring particularly in patients with cardiac, renal or hepatic disease.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Geriatric Patients: There are insufficient long-term safety data to assess the potential risks of cardiovascular disease and prostate cancer. ( 8.5 )
8.1Pregnancy Risk Summary Testosterone gel is contraindicated in pregnant women. Testosterone is teratogenic and may cause fetal harm when administered to a pregnant woman based on data from animal studies and its mechanism of action [see Contraindications (4) and Clinical Pharmacology (12.1) ] . Exposure of a female fetus to androgens may result in varying degrees of virilization.
In animal developmental studies, exposure to testosterone in utero resulted in hormonal and behavioral changes in offspring and structural impairments of reproductive tissues in female and male offspring. These studies did not meet current standards for nonclinical development toxicity studies. Data Animal Data In developmental studies conducted in rats, rabbits, pigs, sheep and rhesus monkeys, pregnant animals received intramuscular injection of testosterone during the period of organogenesis.
Testosterone treatment at doses that were comparable to those used for testosterone replacement therapy resulted in structural impairments in both female and male offspring. Structural impairments observed in females included increased ano-genital distance, phallus development, empty scrotum, no external vagina, intrauterine growth retardation, reduced ovarian reserve, and increased ovarian follicular recruitment. Structural impairments seen in male offspring included increased or decreased testicular weight, larger seminal tubular lumen diameter, and higher frequency of occluded tubule lumen.
Increased pituitary weight was seen in both sexes. Testosterone exposure in utero also resulted in hormonal and behavioral changes in offspring. Hypertension was observed in pregnant female rats and their offspring exposed to doses approximately twice those used for testosterone replacement therapy.
8.2Lactation Risk Summary Testosterone gel is not indicated for use in women.
8.3Females and Males of Reproductive Potential Infertility During treatment with large doses of exogenous androgens, including testosterone gel, spermatogenesis may be suppressed through feedback inhibition of the hypothalamic-pituitary-testicular axis [see Warnings and Precautions (5.8) ] . Reduced fertility is observed in some men taking testosterone replacement therapy. Testicular atrophy, subfertility, and infertility have also been reported in men who abuse anabolic androgenic steroids [see Drug Abuse and Dependence (9.2) ] .
With either type of use, the impact on fertility may be irreversible.
8.4Pediatric Use The safety and efficacy of testosterone gel in pediatric patients less than 18 years old have not been established. Improper use may result in acceleration of bone age and premature closure of epiphyses.
8.5Geriatric Use There is insufficient long-term safety data in geriatric patients to assess the potentially increased risks of cardiovascular disease and prostate cancer [see Warnings and Precautions (5.1) ] .
8.6Renal Impairment No studies were conducted in patients with renal impairment.
8.7Hepatic Impairment No studies were conducted in patients with hepatic impairment.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Testosterone gel is contraindicated in pregnant women. Testosterone is teratogenic and may cause fetal harm when administered to a pregnant woman based on data from animal studies and its mechanism of action [see Contraindications (4) and Clinical Pharmacology (12.1) ] . Exposure of a female fetus to androgens may result in varying degrees of virilization.
In animal developmental studies, exposure to testosterone in utero resulted in hormonal and behavioral changes in offspring and structural impairments of reproductive tissues in female and male offspring. These studies did not meet current standards for nonclinical development toxicity studies. Data Animal Data In developmental studies conducted in rats, rabbits, pigs, sheep and rhesus monkeys, pregnant animals received intramuscular injection of testosterone during the period of organogenesis.
Testosterone treatment at doses that were comparable to those used for testosterone replacement therapy resulted in structural impairments in both female and male offspring. Structural impairments observed in females included increased ano-genital distance, phallus development, empty scrotum, no external vagina, intrauterine growth retardation, reduced ovarian reserve, and increased ovarian follicular recruitment. Structural impairments seen in male offspring included increased or decreased testicular weight, larger seminal tubular lumen diameter, and higher frequency of occluded tubule lumen.
Increased pituitary weight was seen in both sexes. Testosterone exposure in utero also resulted in hormonal and behavioral changes in offspring. Hypertension was observed in pregnant female rats and their offspring exposed to doses approximately twice those used for testosterone replacement therapy.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and efficacy of testosterone gel in pediatric patients less than 18 years old have not been established. Improper use may result in acceleration of bone age and premature closure of epiphyses.
🧓 Geriatric Use ▾
8.5Geriatric Use There is insufficient long-term safety data in geriatric patients to assess the potentially increased risks of cardiovascular disease and prostate cancer [see Warnings and Precautions (5.1) ] .
🆘 Overdosage ▾
10 OVERDOSAGE There were no reports of overdose in the testosterone gel clinical trials. There is a single report in the literature of acute overdosage after injection of testosterone enanthate. This subject had serum testosterone concentrations of up to 11,400 ng/dL, which were implicated in a cerebrovascular accident.
Treatment of overdosage would consist of discontinuation of testosterone gel, washing the application site with soap and water, and appropriate symptomatic and supportive care.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Endogenous androgens, including testosterone and dihydrotestosterone (DHT) are responsible for the normal growth and development of the male sex organs and for maintenance of secondary sex characteristics. These effects include the growth and maturation of the prostate, seminal vesicles, penis, and scrotum; the development of male hair distribution, such as facial, pubic, chest, and axillary hair; laryngeal enlargement, vocal cord thickening, and alterations in body musculature and fat distribution.
Male hypogonadism, a clinical syndrome resulting from insufficient secretion of testosterone, has two main etiologies. Primary hypogonadism is caused by defects of the gonads, such as Klinefelter's syndrome or Leydig cell aplasia, whereas secondary hypogonadism is the failure of the hypothalamus (or pituitary) to produce sufficient gonadotropins (FSH, LH).
12.2Pharmacodynamics No specific pharmacodynamic studies were conducted using testosterone gel.
12.3Pharmacokinetics In a single-dose, replicate crossover clinical study evaluating 58 hypogonadal males, the serum testosterone exposures (AUC 0-24 and AUC 0-t ) and maximum testosterone concentration (C max ) following a topical administration of 100 mg testosterone administration as a 2 × 5 g testosterone gel tubes (applied to the shoulders/upper arms) were bioequivalent to those following a topical administration of an approved testosterone gel product. Absorption Testosterone gel delivers physiologic amounts of testosterone, producing circulating testosterone concentrations that approximate normal levels (e.g., 300 – 1000 ng/dL) seen in healthy men.
The skin serves as a reservoir for the sustained release of testosterone into the systemic circulation. Approximately 10% of the testosterone applied on the skin surface is absorbed into the systemic circulation during a 24-hour period. Single Dose In a single dose, replicate crossover study, when testosterone gel 100 mg was applied, absorption of testosterone into the blood continued for the entire 24 hour dosing period.
The average (± SD) AUC 0-24 and AUC 0-t and C max were 6625 (±3671) ng∙hr/dL, 10425 (±5521) ng∙hr/dL, and 573 (±284) ng/dL, respectively. Multiple Dose With single daily applications of testosterone gel 50 mg and 100 mg, follow-up measurements at 30 and 90 days after starting treatment have confirmed that serum testosterone and DHT concentrations are generally maintained within the normal range. Figure 1 summarizes the 24-hour pharmacokinetic profile of testosterone for patients maintained on testosterone gel 50 mg or testosterone gel 100 mg for 30 days.
Figure 1 Mean Steady-State Serum Testosterone (±SD) (ng/dL) Concentrations on Day 30 in Patients Applying Testosterone Once Daily The average daily testosterone concentration produced by testosterone gel 100 mg at Day 30 was 612 (± 286) ng/dL and by testosterone gel 50 mg at Day 30 was 365 (± 187) ng/dL. Figure 1 Distribution Circulating testosterone is primarily bound in the serum to sex hormone-binding globulin (SHBG) and albumin. Approximately 40% of testosterone in plasma is bound to SHBG, 2% remains unbound (free) and the rest is loosely bound to albumin and other proteins.
Metabolism Testosterone is metabolized to various 17-keto steroids through two different pathways. The major active metabolites of testosterone are estradiol and DHT. The average daily DHT concentration produced by testosterone gel 100 mg at Day 30 was 555 (± 293) pg/mL and by testosterone gel 50 mg at Day 30 was 346 (± 212) pg/mL.
Figure 2 summarizes the 24-hour pharmacokinetic profile of DHT for patients maintained on testosterone gel 50 mg or testosterone gel 100 mg for 30 days. Figure 2 Mean Steady-State Serum Dihydrotestosterone (±SD) (pg/mL) Concentrations on Day 30 in Patients Applying Testosterone Once Daily Figure 2 Excretion There is considerable variation in the half-life of testosterone concentration as reported in the literature…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Endogenous androgens, including testosterone and dihydrotestosterone (DHT) are responsible for the normal growth and development of the male sex organs and for maintenance of secondary sex characteristics. These effects include the growth and maturation of the prostate, seminal vesicles, penis, and scrotum; the development of male hair distribution, such as facial, pubic, chest, and axillary hair; laryngeal enlargement, vocal cord thickening, and alterations in body musculature and fat distribution.
Male hypogonadism, a clinical syndrome resulting from insufficient secretion of testosterone, has two main etiologies. Primary hypogonadism is caused by defects of the gonads, such as Klinefelter's syndrome or Leydig cell aplasia, whereas secondary hypogonadism is the failure of the hypothalamus (or pituitary) to produce sufficient gonadotropins (FSH, LH).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Testosterone gel is supplied in unit-dose tubes in cartons of 30 and unit-dose packets in cartons of 30. Each tube or packet contains 50 mg testosterone in 5 g of gel. Testosterone gel is also supplied in a metered-dose pump that delivers 12.5 mg of testosterone per complete pump actuation.
Each 88 g metered-dose pump is capable of dispensing 75 g of gel or 60-metered pump actuations. Each pump actuation delivers 1.25 g of gel. The metered-dose pump is supplied in cartons of 2.
Testosterone gel is available as follows: NDC Number Strength Package Size 0832-1120-05 50 mg of testosterone 30 tubes (5 g of gel per tube) 0832-1120-65 50 mg of testosterone 1 tube (5 g of gel per tube) 0832-1120-35 50 mg of testosterone 30 packets (5 g of gel per packet) 0832-1120-89 50 mg of testosterone 1 packet (5 g of gel per packet) 0832-1121-42 12.5 mg of testosterone per pump actuation 2 × 75 g pumps (each pump dispenses 60 metered 1.25 g of gel)
16.2Storage Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F). [See USP Controlled Room Temperature.]
16.3Handling and Disposal Used testosterone gel tubes, packets or pumps should be discarded in household trash in a manner that prevents accidental exposure of women, children, or pets [see Boxed Warning and Warnings and Precautions (5.2) ] . Contents are flammable [see Warnings and Precautions (5.16) ] .
📦 Storage and Handling ▾
16.2Storage Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F). [See USP Controlled Room Temperature.]
📋 Description ▾
11 DESCRIPTION Testosterone gel, for topical use is a clear to translucent hydroalcoholic topical gel containing testosterone, an androgen. Testosterone gel provides continuous transdermal delivery of testosterone for 24 hours, following a single application to intact, clean, dry skin of the shoulders and/or upper arms. Testosterone gel is available in unit-dose tubes, unit-dose packets, and a metered-dose pump.
One 5-g or two 5-g tubes/packets of testosterone gel contains 50 mg or 100 mg of testosterone, respectively. One pump actuation dispenses 1.25 g of gel, which contains 12.5 mg of testosterone. Four pump actuations or eight pump actuations contain 50 mg or 100 mg of testosterone, respectively.
Each metered-dose pump container is capable of dispensing 60 pump actuations. The active pharmacological ingredient in testosterone gel is testosterone. Testosterone USP is a white to practically white crystalline powder chemically described as 17-β hydroxyandrost-4-en-3-one.
The structural formula is shown in the following figure: Inactive ingredients in testosterone gel are carbomer copolymer Type B, carbomer homopolymer Type C, diisopropyl adipate, ethyl alcohol, glycerin, methyl laurate, oleyl alcohol, polyethylene glycol, propylene glycol, purified water, and tromethamine. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Men with Known or Suspected Carcinoma of the Breast or Prostate Men with known or suspected prostate or breast cancer should not use testosterone gel [see Contraindications (4) and Warnings and Precautions (5.1) ] . Potential for Secondary Exposure to Testosterone and Steps to Prevent Secondary Exposure Secondary exposure to testosterone in children and women can occur with the use of testosterone gel products in men.
Cases of secondary exposure to testosterone have been reported in children. Physicians should advise patients of the reported signs and symptoms of secondary exposure which may include the following: In children; unexpected sexual development including inappropriate enlargement of the penis or clitoris, premature development of pubic hair, increased erections, and aggressive behavior In women; changes in hair distribution, increase in acne, or other signs of testosterone effects The possibility of secondary exposure to testosterone gel should be brought to the attention of a healthcare provider Testosterone gel should be promptly discontinued until the cause of virilization is identified Strict adherence to the following precautions is advised to minimize the potential for secondary exposure to testosterone from testosterone gel in men [see Medication Guide ] Children and women should avoid contact with unwashed or unclothed application site(s) of men using testosterone gel Patients using testosterone gel should apply the product as directed and strictly adhere to the following: Wash hands with soap and water immediately after application Cover the application site(s) with clothing after the gel has dried Wash the application site(s) thoroughly with soap and water prior to any situation where skin-to-skin contact of the application site with another person is anticipated In the event that unwashed or unclothed skin to which testosterone gel has been applied comes in contact with the skin of another person, the general area of contact on the other person should be washed with soap and water as soon as possible [see Dosage and Administration (2.2) , Warnings and Precautions (5.2) and Clinical Pharmacology (12.3) ] .
Potential Adverse Reactions with Androgens Patients should be informed that treatment with androgens may lead to adverse reactions which include: Changes in urinary habits, such as increased urination at night, trouble starting the urine stream, passing urine many times during the day, having an urge to go the bathroom right away, having a urine accident, or being unable to pass urine or weak urine flow Breathing disturbances, including those associated with sleep or excessive daytime sleepiness. Too frequent or persistent erections of the penis Nausea, vomiting, changes in skin color, or ankle swelling Patients Should Be Advised of the Following Instructions for Use Read the Medication Guide before starting testosterone gel therapy and reread it each time the prescription is renewed.
Testosterone gel should be applied and used appropriately to maximize the benefits and to minimize the risk of secondary exposure in children and women. Keep testosterone gel out of the reach of children. The package is not child resistant.
Testosterone gel is an alcohol-based product and is flammable; therefore avoid fire, flame or smoking until the gel has dried. It is important to adhere to all recommended monitoring. Report any changes in their state of health, such as changes in urinary habits, breathing, sleep, and mood.
Testosterone gel is prescribed to meet the patient's specific needs; therefore, the patient should never share testosterone gel with anyone. Testosterone gel should be applied topically once daily at approximately the same time each day to clean dry skin of the shoulders and/or upper arms. Testosterone gel should not be applied to the scrotum, penis, or abdomen.
Wait 2 hours before washi…
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised 5/2020 MEDICATION GUIDE Testosterone (tes-TOS-te-rōn) Gel, CIII for topical use What is the most important information I should know about testosterone gel?
Testosterone gel can transfer from your body to others including, children and women. Children and women should avoid contact with the unwashed or not covered (unclothed areas) where testosterone gel has been applied to your skin. Early signs and symptoms of puberty have occurred in young children who have come in direct contact with testosterone by touching areas where men have used testosterone gel.
Children Signs and symptoms of early puberty in a child when they come in direct contact with Testosterone gel may include: Abnormal sexual changes: enlarged penis or clitoris. early growth of hair near the vagina or around the penis (pubic hair). erections or acting out sexual urges (sex drive). Behavior problems: acting aggressively, behaving in an angry or violent way. Women Signs and symptoms in women when they come in direct contact with testosterone gel may include: changes in body hair. an abnormal increase in pimples (acne).
Stop using testosterone gel and call your healthcare provider right away if you see any signs and symptoms in a child or a woman that may have happened through accidental touching of the area where you have applied testosterone gel. To lower the risk of transfer of testosterone gel from your body to others, follow these important instructions: Apply testosterone gel only to the areas of your shoulders and upper arms that will be covered by a short sleeve t-shirt. Wash your hands right away with soap and water after applying testosterone gel.
After the gel has dried, cover the application area with clothing . Keep the area covered until you have washed the application area well or have showered. If you expect to have skin-to-skin contact with another person, first wash the application area well with soap and water.
If a child or woman touches the area where you have applied testosterone gel, that area on the child or woman should be washed well with soap and water right away. What is testosterone gel? Testosterone gel is a prescription medicine that contains testosterone.
Testosterone gel is used to treat adult males who have low or no testosterone due to certain medical conditions. Your healthcare provider will test your blood before you start and while you are using Testosterone gel. It is not known if testosterone gel is safe or effective to treat men who have low testosterone due to aging.
It is not known if testosterone gel is safe or effective in children younger than 18 years old. Improper use of testosterone gel may affect bone growth in children. Testosterone gel is a controlled substance (CIII) because it contains testosterone that can be a target for people who abuse prescription medicines.
Keep your testosterone gel in a safe place to protect it. Never give your testosterone gel to anyone else, even if they have the same symptoms you have. Selling or giving away this medicine may harm others and it is against the law.
Testosterone gel is not meant for use in women. Do not use testosterone gel if you: have breast cancer. have or might have prostate cancer. are a woman who is pregnant. Testosterone gel may harm your unborn baby.
Women who are pregnant or who may become pregnant should avoid contact with the area of skin where testosterone gel has been applied. Before using testosterone gel, tell your healthcare provider about all of your medical conditions including if you: have breast cancer. have or might have prostate cancer. have urinary problems due to an enlarged prostate. have heart problems. have liver or kidney problems. have problems breathing while you sleep (sleep apnea). Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements.
Using testostero…