
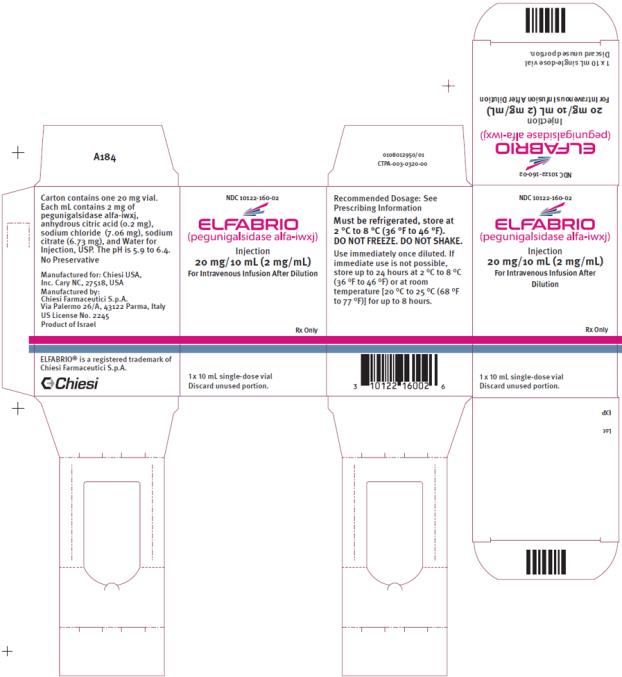
ELFABRIO pegunigalsidase alfa 20 mg/10mL Injection, Solution, Concentrate
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Hydrolytic Lysosomal Neutral Glycosphingolipid-specific Enzyme class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Pegunigalsidase alfa-iwxj injection is used to treat Fabry disease (an inherited condition in which a type of fatty substance builds up in the body, resulting in nerve and organ damage). Pegunigalsidase alfa-iwxj injection is in a class of medications called enzymes. It works by replacing an enzyme that is normally produced by the body that helps prevents the build of the fatty substance in the body.
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
2.0 mg / 10 mL
UNII XF417D3PSL
Anhydrous citric acid is a sour, crystalline powder derived from citric acid with water removed. In medicines, it acts as a buffer to control pH, adds tartness to improve taste, and helps tablets disintegrate.
-
70.6 mg / 10 mL
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
76.7 mg / 10 mL
UNII B22547B95K
A salt derived from citric acid that helps maintain the proper acid-base balance in the medicine. It's used as a buffer to keep the product stable and at the right pH level.
-
9916.7 mg / 10 mL
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J2508 | $225.665 / J2508 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Elfabrio 20 mg/10mLthis 10122-0160-05 | Chiesi | 5 vials | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Code | What it grants | Expires |
|---|---|---|
| RefProduct | Reference-product exclusivity (12-year, BPCIA) — no biosimilar can be licensed before this date | May 9, 2035 |
Is there a biosimilar for ELFABRIO 20 MG/10 ML VIAL?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 10122-0160-02 | 1 VIAL, SINGLE-DOSE in 1 CARTON (10122-160-02) / 10 mL in 1 VIAL, SINGLE-DOSE (10122-160-01) | 2023-05-23 | Active |
| 10122-0160-05 You're viewing this | 5 VIAL, SINGLE-DOSE in 1 CARTON (10122-160-05) / 10 mL in 1 VIAL, SINGLE-DOSE (10122-160-01) | 2023-05-23 | Active |
| 10122-0160-10 | 10 VIAL, SINGLE-DOSE in 1 CARTON (10122-160-10) / 10 mL in 1 VIAL, SINGLE-DOSE (10122-160-01) | 2023-05-23 | Active |
Pack size FAQ
What quantity is in NDC 10122-0160-05?
What NDC number is used to bill for this package of ELFABRIO pegunigalsidase alfa 20 mg/10mL Injection, Solution, Concentrate?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: HYPERSENSITIVITY REACTIONS INCLUDING ANAPHYLAXIS Patients treated with ELFABRIO have experienced hypersensitivity reactions, including anaphylaxis. Appropriate medical support measures, including cardiopulmonary resuscitation equipment, should be readily available during ELFABRIO administration. If a severe hypersensitivity reaction (e.g., anaphylaxis) occurs, discontinue ELFABRIO immediately and initiate appropriate medical treatment.
In patients with severe hypersensitivity reaction, a desensitization procedure to ELFABRIO may be considered [see Warnings and Precautions ( 5.1 )] . WARNING: HYPERSENSITIVITY REACTIONS INCLUDING ANAPHYLAXIS See full prescribing information for complete boxed warning. Appropriate medical support measures, including cardiopulmonary resuscitation equipment, should be readily available.
If a severe hypersensitivity reaction occurs, discontinue ELFABRIO immediately and initiate appropriate medical treatment. ( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ELFABRIO is indicated for the treatment of adults with confirmed Fabry disease. ELFABRIO is a hydrolytic lysosomal neutral glycosphingolipid-specific enzyme indicated for the treatment of adults with confirmed Fabry disease. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION For pretreatment recommendations, see Full Prescribing Information. ( 2.1 ) Recommended dosage is 1 mg/kg every 2 weeks administered as an intravenous infusion. ( 2.2 ) For dosage and administration modifications due to hypersensitivity reactions or infusion-associated reactions (IARs), see Full Prescribing Information.
( 2.3 ) For instructions on preparation (including dilution), storage, and administration (including rates for the initial 4-6 infusions for ERT-experienced and ERT-naïve patients), see Full Prescribing Information. ( 2.4 , 2.5 , 2.6 ) 2. 1 Recommendations Prior to ELFABRIO Treatment Pretreatment In enzyme replacement therapy (ERT)-experienced patients, if pretreatment with antihistamines, antipyretics, and/or corticosteroids was used prior to ERT administration, consider similar pretreatment with these medications before the first several ELFABRIO infusions.
After 4 to 6 ELFABRIO infusions, a stepwise decrease in the pretreatment medication dose(s) and/or discontinuation of the pretreatment medication(s) may be considered if treatment with ELFABRIO was tolerated. In ERT-naïve patients, prior to ELFABRIO administration, pre-treating with antihistamines, antipyretics, and/or corticosteroids may be considered [see Warnings and Precautions ( 5.1 , 5.2 )] . Medical Support Appropriate medical support measures including cardiopulmonary resuscitation equipment should be readily available during ELFABRIO administration.
2. 2 Recommended Dosage and Administration The recommended dosage of ELFABRIO, based on actual body weight, is 1 mg/kg administered by intravenous infusion every 2 weeks. The initial recommended ELFABRIO infusion rates for ERT-experienced or ERT-naïve patients are based on actual body weight [ see Tables 1 and 2 ] .
If one or more doses are missed, restart ELFABRIO treatment as soon as possible, maintaining the 2 week interval between infusions thereafter. Do not double a dose to compensate for a missed dose. 2.
3 Administration Modifications Due to Hypersensitivity Reactions and/or Infusion-Associated Reactions In the event of a severe hypersensitivity reaction (e.g., anaphylaxis) or severe infusion-associated reaction (IAR), immediately discontinue ELFABRIO administration and initiate appropriate medical treatment. For additional recommendations in the event of a severe hypersensitivity reaction or IAR, see Warnings and Precautions ( 5.1 , 5.2 ) . In the event of a mild to moderate hypersensitivity reaction or a mild to moderate IAR, consider temporarily holding the infusion for 15 to 30 minutes or slowing the infusion rate by 25% to 50% [ see Dosage and Administration ( 2.6 )] , and initiating appropriate medical treatment [see Warnings and Precautions ( 5.1 , 5.2 )] .
If symptoms persist despite holding or slowing the infusion, stop the infusion and monitor the patient. Consider re-initiating the infusion within 7 to 14 days at 25% to 50% of the rate at which the reaction occurred with appropriate pretreatment. If symptoms subside after holding the infusion, resume infusion at a 25% to 50% reduced rate as tolerated.
Alternatively, if symptoms subside after slowing the infusion, complete infusion at the reduced rate as tolerated. Starting with the next infusion, increase the infusion rate by increments of 25% every third infusion as tolerated until the infusion rate at which the reaction occurred is reached. Closely monitor the patient.
2. 4 Preparation Instructions Use aseptic technique during preparation. Dilute ELFABRIO in the following manner: Determine the number of ELFABRIO vials to be diluted based on actual body weight in kg and the recommended dose [see Dosage and Administration ( 2.2 ) and Dosage Forms and Strengths ( 3 ) ] .
Round the number of vials up to the next whole number. Remove the appropriate number of ELFABRIO vials from the refrigerator and allow the vials to sit for 15-30 minutes at room temperature 20°C to 25°C (68°F to 77°F) before use. Do not use…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: 20 mg/10 mL or 5 mg/2.5 mL (2 mg/mL) of pegunigalsidase alfa-iwxj in a clear and colorless solution in a single-dose vial. Injection: 20 mg/10 mL or 5 mg/2.5 mL (2 mg/mL) solution in a single-dose vial. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Infusion-Associated Reactions: If severe IARs occur, discontinue ELFABRIO and initiate appropriate medical treatment. ( 5.2 ) Membranoproliferative Glomerulonephritis: Monitor serum creatinine and urinary protein to creatinine ratio. Discontinue ELFABRIO if glomerulonephritis is suspected, until a diagnostic evaluation can be conducted. ( 5.3 )
5.1Hypersensitivity Reactions Including Anaphylaxis Hypersensitivity reactions including anaphylaxis have been reported in ELFABRIO-treated patients. In clinical trials, 20 (14%) of ELFABRIO-treated patients experienced hypersensitivity reactions. In these trials, 4 ELFABRIO-treated patients (3%; 1 naïve to enzyme replacement therapy (ERT) and 3 ERT-experienced patients) experienced anaphylaxis during the initial infusion and were positive for anti-pegunigalsidase alfa-iwxj IgE antibodies (referred to as IgE ADA) [see Adverse Reactions ( 6.1 6.
1 ) and Clinical Pharmacology ( 12.6 ) ] . The risk of pegunigalsidase alfa-iwxj-related hypersensitivity may be increased in certain patients with pre-existing ADA from prior ERT [ see Use In Specific Populations ( 8.6 )]. Anaphylaxis (reported as Type I hypersensitivity reaction, hypersensitivity reaction, or bronchospasm) occurred within 5 to 40 minutes of the start of the initial infusion.
Signs and symptoms included headache, nausea, vomiting, throat tightness, facial and oral edema, truncal rash, tachycardia, hypotension, rigors, urticaria, intense pruritus, moderate upper airway obstructions, macroglossia, and mild lip edema. Patients received treatment that included epinephrine, antihistamines and/or systemic corticosteroids. Prior to ELFABRIO administration, consider pretreating with antihistamines, antipyretics, and/or corticosteroids.
Appropriate medical support measures, including cardiopulmonary resuscitation equipment, should be readily available during ELFABRIO administration. If a severe hypersensitivity reaction (e.g., anaphylaxis) occurs, discontinue ELFABRIO immediately and initiate appropriate medical treatment. Consider the risks and benefits of re-administering ELFABRIO following severe hypersensitivity reactions (including anaphylaxis).
Patients may be rechallenged using slower infusion rates. In patients with severe hypersensitivity reaction, desensitization measures to ELFABRIO may be considered. If the decision is made to readminister ELFABRIO, ensure the patient tolerates the infusion.
If the patient tolerates the infusion, the rate may be increased to reach the recommended rate. If a mild or moderate hypersensitivity reaction occurs, consider temporarily holding the infusion or slowing the infusion rate [ see Dosage and Administratio n ( 2.3 ) ] . Consider monitoring patients who demonstrate hypersensitivity reactions during ELFABRIO treatment for the presence of IgG and IgE ADA [see Clinical Pharmacology ( 12.6 )] .
5.2Infusion - Associated Reactions Infusion-associated reactions (IARs) have been reported in ELFABRIO-treated patients. In clinical trials, 41 (29%) of ELFABRIO-treated patients experienced one or more IARs, defined as any adverse reaction with onset after start of the infusion and up to 24 hours after the end of infusion. The risk of pegunigalsidase alfa-iwxj-related IARs may be increased in certain patients with pre-existing ADA from prior ERT [ see Use In Specific Populations ( 8.6 )].
IARs included anaphylaxis reactions during the initial ELFABRIO administration [see Warnings and Precautions ( 5.1 )] . In addition to the hypersensitivity reactions described above [see Warnings and Precautions ( 5.1 )] , other IARs included nausea, chills, pruritus, rash, chest pain, dizziness, vomiting, asthenia, pain, sneezing, dyspnea, nasal congestion, throat irritation, abdominal pain, erythema, diarrhea, burning sensation, neuralgia, headache, paresthesia, tremor, agitation, increased body temperature, flushing, bradycardia, myalgia, hypertension, and hypotension [see Adverse Reaction…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in labeling: Hypersensitivity Reactions Including Anaphylaxis [see Warnings and Precautions ( 5.1 ) ] Infusion-Associated Reactions (IARs) [see Warnings and Precautions ( 5.2 )] Membranoproliferative Glomerulonephritis [see Warnings and Precautions ( 5.3 )] Most common adverse reactions (≥15%) are: infusion-associated reactions, nasopharyngitis, headache, diarrhea, fatigue, nausea, back pain, pain in extremity, and sinusitis.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Chiesi USA, Inc. at 1-888-661-9260 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trial of another drug and may not reflect the rates observed in clinical practice. Adverse Reactions From Trial 2 The safety of ELFABRIO in adults with confirmed Fabry disease who had been previously treated with agalsidase beta was evaluated in Trial 2 which included a total of 52 ELFABRIO-treated patients (29 male, 23 female aged 20 to 60 years old) with Fabry disease [see Clinical Studies ( 14 )] .
Patients received 1 mg/kg of ELFABRIO given intravenously every 2 weeks for at least 104 weeks. The most common adverse reactions (≥15%) reported with ELFABRIO were infusion-associated reactions which occurred in 17 patients (32%); followed by, nasopharyngitis and headache each in 11 patients (21%); diarrhea in 10 patients (19%); fatigue and nausea each in 9 patients (17%); and back pain, pain in extremity, and sinusitis each in 8 patients (15%) . One ELFABRIO-treated patient experienced a severe hypersensitivity reaction during the first infusion.
The patient withdrew from the trial following a moderate hypersensitivity reaction during the second infusion. Table 3 lists adverse reactions reported in at least 5% of ELFABRIO-treated patients in Trial 2. Table 3: Adverse Reactions in Adults With Fabry Disease (Trial 2) 1 Adverse Reaction ELFABRIO N=52 n (%) Agalsidase beta N=25 n (%) Infusion-Associated Reaction 2,4 17 (32) 8 (32) Nasopharyngitis 11 (21) 4 (16) Headache 11 (21) 5 (20) Diarrhea 10 (19) 6 (24) Fatigue 9 (17) 4 (16) Nausea 9 (17) 3 (12) Back pain 8 (15) 5 (20) Pain in Extremity 8 (15) 4 (16) Sinusitis 8 (15) 3 (12) Abdominal Pain 6 (12) 0 (0) Proteinuria 6 (12) 0 (0) Hypersensitivity 3,4 5 (9) 4 (16) Upper Respiratory Tract Congestion 4 (8) 0 (0) Neuralgia 4 (8) 0 (0) Peripheral Neuropathy 3 (6) 0 (0) Sciatica 3 (6) 0 (0) Infusion Site Extravasation 3 (6) 0 (0) Hematuria 3 (6) 0 (0) 1 Adverse reactions were those that occurred in ≥ 5% of ELFABRIO-treated patients.
2 “Infusion-associated reaction” includes nausea, vomiting, abdominal pain, diarrhea, fatigue, chills, malaise, non-cardiac chest pain, hypersensitivity, body temperature increased, burning sensation, neuralgia, agitation, throat irritation, pruritic rash, and flushing. Events occurring within 24 hours. 3 “Hypersensitivity” includes macular rash, pruritic rash, and face swelling.
Events occurring within 24 hours. 4 The events of hypersensitivity and pruritic rash fall in both hypersensitivity and IAR categories. Membranoproliferative Glomerulonephritis A case of membranoproliferative glomerulonephritis with immune depositions in the kidney was reported in an ELFABRIO-treated patient.
Immunogenicity: Anti - D rug Antibody-Associated Adverse Reactions Of the patients who experienced serious hypersensitivity reactions during the first ELFABRIO infusion and had pre-infusion samples and samples available for testing at the time of the event, all but one had pre-existing IgE ADAs and all tested positive for IgE ADAs at the time of the reaction. In the overall clinical program, IARs occurred in 51% (19/37) of patients who were IgG ADA positive at baseline compared to 16% (13/84) in IgG ADA neg…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no available data on ELFABRIO use in pregnant females to evaluate a drug-associated risk of major birth defects, miscarriage or other adverse maternal or fetal outcomes; however, as an enzyme replacement, ELFABRIO is not expected to cause adverse outcomes . Animal reproduction studies have been conducted with pegunigalsidase alfa-iwxj in pregnant rats and rabbits. No adverse effects on embryofetal development were observed in pregnant rats intravenously administered pegunigalsidase alfa-iwxj twice per week at exposures up to 3.6 times that of the maximum recommended human dose (MRHD) (based on area under the concentration-time curve (AUC)).
Maternal toxicity was observed in pregnant rabbits intravenously administered pegunigalsidase alfa-iwxj twice per week at doses that were ≥ 3.2 times the MRHD (based on human equivalent dose) [ see Data ] . The estimated background risk of major birth defects and miscarriage in the indicated population is unknown. All pregnancies have a background risk of birth defect, loss or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. There is a pregnancy safety study for ELFABRIO. If a patient becomes pregnant while receiving ELFABRIO, healthcare providers should report ELFABRIO exposure by calling 1-888-661-9260 or visiting https://chiesirarediseases.com/contact-us/medical-information-form.
Data Animal Data In an embryofetal development study in the rat, pegunigalsidase alfa-iwxj was administered during the period of organogenesis on gestation day 6, 9, 12, and 15. No maternal or fetal adverse effects were noted at exposures that were up to 3.6-fold greater than the recommended dose of 1 mg/kg every two weeks. In an embryofetal development study in the rabbit, administration of pegunigalsidase alfa-iwxj during the period of organogenesis on gestation day 6, 9, 12, 15, and 18, resulted in maternal toxicity, including maternal mortality, decreased body weight, and decreased feed consumption.
These effects were observed at exposures that were ≥ 3.2-fold greater than the recommended dose of 1 mg/kg every two weeks. Adverse embryofetal effects included abortion, increased late resorptions, number of does with resorptions, and increased post-implantation loss at exposures that were 6.5 fold greater than the recommended dose of 1 mg/kg every two weeks. Decreased fetal body weight was observed at exposures that were ≥ 3.2 times greater than the recommended dose of 1 mg/kg every two weeks.
There was no increase in fetal external, skeletal, or visceral malformations.
8.2Lactation Risk Summary There are no data on the presence of pegunigalsidase alfa-iwxj in either human or animal milk, the effects on the breastfed infant, or the effects on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for ELFABRIO and any potential adverse effects on the breastfed infant from pegunigalsidase alfa-iwxj or from the underlying maternal condition. 8.
4 Pediatric Use The safety and effectiveness of ELFABRIO have not been established in pediatric patients. 8. 5 Geriatric Use Clinical trials of ELFABRIO did not include patients 65 years of age and older to determine if they respond differently from younger adult patients.
8.6Patients with Prior Enzyme Replacement Therapy Patients that received prior ERT are more likely to have pre-existing anti-drug antibodies (ADA) to pegunigalsidase alfa-iwxj which could be due to the ADA cross-reactivity to pegunigalsidase alfa-iwxj by prior ERT. When switching from other ERT to ELFABRIO: Pre-existing ADA may reduce the plasma pegunigalsidase alfa-iwxj concentrations, which may reduce ELFABRIO efficacy [see Clinical Pharmacology ( 12.2 , 12.6 ) ]. The risk of ELFABRIO-related hypersensitivity…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no available data on ELFABRIO use in pregnant females to evaluate a drug-associated risk of major birth defects, miscarriage or other adverse maternal or fetal outcomes; however, as an enzyme replacement, ELFABRIO is not expected to cause adverse outcomes . Animal reproduction studies have been conducted with pegunigalsidase alfa-iwxj in pregnant rats and rabbits. No adverse effects on embryofetal development were observed in pregnant rats intravenously administered pegunigalsidase alfa-iwxj twice per week at exposures up to 3.6 times that of the maximum recommended human dose (MRHD) (based on area under the concentration-time curve (AUC)).
Maternal toxicity was observed in pregnant rabbits intravenously administered pegunigalsidase alfa-iwxj twice per week at doses that were ≥ 3.2 times the MRHD (based on human equivalent dose) [ see Data ] . The estimated background risk of major birth defects and miscarriage in the indicated population is unknown. All pregnancies have a background risk of birth defect, loss or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. There is a pregnancy safety study for ELFABRIO. If a patient becomes pregnant while receiving ELFABRIO, healthcare providers should report ELFABRIO exposure by calling 1-888-661-9260 or visiting https://chiesirarediseases.com/contact-us/medical-information-form.
Data Animal Data In an embryofetal development study in the rat, pegunigalsidase alfa-iwxj was administered during the period of organogenesis on gestation day 6, 9, 12, and 15. No maternal or fetal adverse effects were noted at exposures that were up to 3.6-fold greater than the recommended dose of 1 mg/kg every two weeks. In an embryofetal development study in the rabbit, administration of pegunigalsidase alfa-iwxj during the period of organogenesis on gestation day 6, 9, 12, 15, and 18, resulted in maternal toxicity, including maternal mortality, decreased body weight, and decreased feed consumption.
These effects were observed at exposures that were ≥ 3.2-fold greater than the recommended dose of 1 mg/kg every two weeks. Adverse embryofetal effects included abortion, increased late resorptions, number of does with resorptions, and increased post-implantation loss at exposures that were 6.5 fold greater than the recommended dose of 1 mg/kg every two weeks. Decreased fetal body weight was observed at exposures that were ≥ 3.2 times greater than the recommended dose of 1 mg/kg every two weeks.
There was no increase in fetal external, skeletal, or visceral malformations.
🧒 Pediatric Use ▾
8. 4 Pediatric Use The safety and effectiveness of ELFABRIO have not been established in pediatric patients.
🧓 Geriatric Use ▾
8. 5 Geriatric Use Clinical trials of ELFABRIO did not include patients 65 years of age and older to determine if they respond differently from younger adult patients.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Fabry disease is caused by deficiency of the lysosomal enzyme alpha-galactosidase A. ELFABRIO provides an exogenous source of alpha-galactosidase A. ELFABRIO is internalized and transported into lysosomes where it is thought to exert enzymatic activity and reduce accumulated globotriaosylceramide (Gb3).
12.2Pharmacodynamics Plasma globotriaosylsphingosine (lyso-Gb3, a metabolite of Gb3) concentrations are elevated in patients with Fabry disease. In patients with Fabry disease who were [see Clinical Studies ( 14 )] : ERT-naïve or had not received ERT treatment for at least 26 weeks and had a negative test for anti-pegunigalsidase alfa-iwxj antibodies (Trial 1), ELFABRIO treatment resulted in significant reductions in median plasma lyso-Gb3 concentrations compared to baseline of approximately: ○ -43% (Week 4), -57% (Week 26), -68% (Week 52), and -84% (Week 104) in male patients, and ○ -3% (Week 4), -19% (Week 26), -32% (Week 52), and -75% (Week 104) in female patients.
ERT-experienced for at least 104 weeks (Trial 2), switching to ELFABRIO treatment resulted in increases in median plasma lyso-Gb3 concentrations compared to baseline of: ○ Approximately 11% (Week 6), 15% (Week 26), and 18% (Week 104) in male patients, and ○ No significant changes in median plasma lyso-Gb3 concentrations in female patients. Pegunigalsidase alfa-iwxj exposure-response relationship is unknown.
12.3Pharmacokinetics The pharmacokinetics (PK) of pegunigalsidase alfa-iwxj were evaluated in adult patients with Fabry disease and are presented as mean (standard deviation, SD) unless otherwise specified. The pharmacokinetics of pegunigalsidase alfa-iwxj in plasma following intravenous infusion of ELFABRIO 1 mg/kg every 2 weeks in adult treatment-naïve patients with Fabry disease are summarized in Table 4. The maximum plasma concentration (C max ) and area under the concentration-time curve (AUC) of pegunigalsidase alfa-iwxj increased with longer duration of treatment.
In adult ERT-experienced patients with Fabry disease, mean C max ranged from 21.2 to 23.3 μg/mL and mean AUC tau ranged from 958 to 1074 μg·h/mL following intravenous infusion of ELFABRIO 1 mg/kg every 2 weeks. Table 4: Pharmacokinetics of Pegunigalsidase Alfa-iwxj in Adult ERT-Naïve 1 Patients With Fabry Disease Following Intravenous Infusion of ELFABRIO 1 mg/kg Every 2 Weeks PK Parameters Pegunigalsidase Alfa-iwxj Day 1 Week 13 Week 26 Week 52 Mean Infusion Duration (h) 5.5 4.4 3.9
3.3General Information C max (μg/mL) 11.1±2.4 11.9±2.4 13.3±3.0 17.3±6.1 AUC inf (μg·h/mL) 391±136 510±174 748±200 1428±875 Distribution V (mL/kg) 321±71 271±89 226±116 186±91 Elimination t 1/2 (h) 78.9±10.3 85.7±28.4 96.5±31.4 121±22 CL (mL/h/kg) 2.9±0.7 2.3±0.8 1.6±0.6 1.1±0.7 Metabolism Expected metabolism into small peptides by catabolic pathways C max =maximum plasma concentration; AUC=area under the plasma concentration-time curve; V= terminal volume of distribution; t 1/2 =elimination half-life; CL=clearance 1 Includes patients who had not received ERT for at least 26 Weeks and who tested negative for anti-pegunigalsidase alfa-iwxj antibodies at screening.
12.6Immunogenicity The observed incidence of IgG anti-drug antibodies (ADA) is highly dependent on the sensitivity and specificity of the assay. Differences in assay methods preclude meaningful comparisons of the incidence of ADA in the studies described below with the incidence of ADA in other studies, including those of pegunigalsidase alfa-iwxj ELFABRIO or of other pegunigalsidase alfa products. The incidences of IgG ADA in ELFABRIO-treated patients with Fabry disease in Trials 1 and 2 are shown in Table 5.
Immunogenicity in ERT-Naïve Patients or Those Who Did Not Receive ERT for 26 Weeks In Trial 1 (ERT-naïve patients with Fabry disease or those who did not receive ERT for 26 weeks) [see Clinical Studies ( 14 )] : Four of the 14 ELFABRIO-treated who were IgG anti-pegunigalsidase alfa-iwxj antibodies…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Fabry disease is caused by deficiency of the lysosomal enzyme alpha-galactosidase A. ELFABRIO provides an exogenous source of alpha-galactosidase A. ELFABRIO is internalized and transported into lysosomes where it is thought to exert enzymatic activity and reduce accumulated globotriaosylceramide (Gb3).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied ELFABRIO (pegunigalsidase alfa-iwxj) injection is a sterile, preservative-free, clear and colorless solution supplied in a single-dose vial. Each vial contains 20 mg/10 mL or 5 mg/2.5 mL (2 mg/mL) of pegunigalsidase alfa-iwxj. ELFABRIO is available as: One single-dose 20 mg/10 mLvial in a carton (NDC 10122-160-02) One single-dose 5 mg/2.5 mL vial in a carton (NDC 10122-165-02) Five single-dose 20 mg/10 mL vials in a carton (NDC 10122-160-05) Ten single-dose 20 mg/10 mL vials in a carton (NDC 10122-160-10) Storage and Handling Store refrigerated at 2°C to 8°C (36°F to 46°F).
Do not freeze. Do not shake.
📋 Description ▾
11 DESCRIPTION Pegunigalsidase alfa-iwxj, a hydrolytic lysosomal neutral glycosphingolipid-specific enzyme, is a PEGylated and crosslinked, chemically modified, recombinant human alpha-galactosidase A enzyme that is produced by genetically modified Bright Yellow 2 ( Nicotiana tabacum ) plant cells. The amino acid sequence of one subunit of pegunigalsidase alfa-iwxj consists of 405 amino acids, of which 398 amino acids are identical to human alpha-GAL-A with an additional 6 amino acids (SEKDEL) included at the C-terminal to encode an endoplasmic retrieval signal, and an additional glycine at the N-terminus derived from the signal peptide.
Pegunigalsidase alfa-iwxj is a homodimeric glycoprotein covalently crosslinked with an average of nine 2.3 kDa PEG per dimer. The total molecular weight of the cross-linked dimer is approximately 116 kDa. Pegunigalsidase alfa-iwxj has specific activity of approximately 35-62 U/mg (one enzyme unit is defined as the amount of enzyme which catalyzes the hydrolysis of one micromole of synthetic substrate, p-nitrophenyl-α-D-galactopyranoside per minute at 37°C).
ELFABRIO (pegunigalsidase alfa-iwxj) injection is a sterile, preservative-free, 20 mg/10 mL or 5 mg/2.5 mL (2 mg/mL) solution in a single-dose vial for intravenous infusion after dilution. Each mL contains 2 mg of pegunigalsidase alfa-iwxj, anhydrous citric acid (0.2 mg), sodium chloride (7.06 mg), sodium citrate (6.73 mg), and Water for Injection, USP. The pH is approximately 5.9 to 6.4.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Hypersensitivity Reactions Including Anaphylaxis and Infusion-Associated Reactions (IAR s) Advise the patient and/or caregiver that reactions related to the infusion may occur during and after ELFABRIO treatment, including anaphylactic reactions, other serious or severe hypersensitivity reactions, and IARs. Inform the patient and/or caregiver of the signs and symptoms of hypersensitivity reactions and IARs and to seek immediate medical care should these signs and symptoms occur [see Warnings and Precautions ( 5.1 , 5.2 )] .
Preg n ancy Safety Study Advise a patient who is exposed to ELFABRIO during pregnancy that there is a pregnancy safety study that monitors pregnancy outcomes. Encourage the patient to report the pregnancy to Chiesi USA, Inc. at 1-888-661-9260 and https://chiesirarediseases.com/contact-us/medical-information-form [see Use in Specific Populations ( 8.1 ) ]. Manufactured by: Chiesi Farmaceutici S.p.A.
Via Palermo 26/A, 43122 Parma, Italy U.S. License No. 2245 Manufactured at: Chiesi Farmaceutici S.p.A.
43122 Parma, Italy Manufactured for: Chiesi USA, Inc. Cary NC, 27518, USA Product of Israel. ELFABRIO is a registered trademark of Chiesi Farmaceutici S.p.A.
Licensed from Protalix Ltd. CTPA-001-0324-01-W