
Alendronate Sodium 10 mg Tablet, 100-count — NDC 16714-631-02 (Billing 16714-0631-02)
This is a package of 100 tablets of Alendronate Sodium 10 mg Tablet from NorthStar Rx LLC, marketed since Aug 2008 and currently FDA-listed; retail pharmacies pay about $0.1112 per tablet (NADAC).
Other active recalls for Alendronate Sodium (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 024053
- GCN: 21680
- GPI-14 (Medi-Span): 30042010100310
- HICL (First Databank): 010124
- AHFS class code: 92:24.00.00
- RxCUI (RxNorm): 904396
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Bisphosphonate class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It strengthens bone and lowers fracture risk in osteoporosis. Some products are also used for steroid-induced osteoporosis and Paget's disease of bone. Your pharmacy label shows wh...
- Take it first thing in the morning with a full glass of plain water, at least 30 minutes before food, drinks or other medicines. Stay upright for at least 30 minutes and until you...
- Stomach upset, heartburn, nausea, constipation or diarrhea, and some bone or muscle aches can happen. Stop and call your doctor if you have trouble or pain swallowing, chest pain,...
- What side effects are normal, and when should I call?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Alendronate Sodium — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.111 | $11.12 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.3375 | $33.75 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.2763 | $27.63 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 16714-0631-01 16714-631-01 Main listing | 30 TABLET in 1 BOTTLE | $0.1112 / ea | $3.34 | 2008-08-04 | — | Active |
| 16714-0631-02 You're viewing this | 100 TABLET in 1 BOTTLE | $0.1112 / ea | $11.12 | 2008-08-04 | — | Active |
| 16714-0631-11 16714-631-11 | 10 BLISTER PACK in 1 CARTON / 10 TABLET in 1 BLISTER PACK | — | — | 2008-08-04 | — | Active |
This pack effectively ties for the lowest per-ea cost of the 2 priced pack sizes ($0.1112 NADAC).
This pack accounts for about 49% of this product's recent Medicaid fills; most go to the 30 tablets pack. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 16714-0631-01?
What NDC number is used to bill for this package of Alendronate Sodium 10 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Alendronate Sodium 10 mgthis 16714-0631-02 | NorthStar | 100 tablets | $0.111 | AB | Availability likely | — |
| Alendronate Sodium 10 mg 64980-0340-01 | Rising | 100 tablets | $0.111 | AB | Availability likely | — |
| Alendronate Sodium 10 mg 65862-0327-01 | Aurobindo | 100 tablets | — | — | FDA listed | — |
| Alendronate Sodium 10 mg 00115-1678-01 | Amneal | 100 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Alendronate sodium is a bisphosphonate indicated for: Treatment and prevention of osteoporosis in postmenopausal women (1.1 , 1.2) Treatment to increase bone mass in men with osteoporosis (1.3) Treatment of glucocorticoid-induced osteoporosis (1.4) Treatment of Paget's disease of bone (1.5) Limitations of use: Optimal duration of use has not been determined. For patients at low-risk for fracture, consider drug discontinuation after 3 to 5 years of use. (1.6)
1.1Treatment of Osteoporosis in Postmenopausal Women Alendronate sodium tablets are indicated for the treatment of osteoporosis in postmenopausal women. In postmenopausal women, alendronate sodium tablets increases bone mass and reduces the incidence of fractures, including those of the hip and spine (vertebral compression fractures). [See Clinical Studies (14.1) .]
1.2Prevention of Osteoporosis in Postmenopausal Women Alendronate sodium tablets are indicated for the prevention of postmenopausal osteoporosis [see Clinical Studies (14.2) ] .
1.3Treatment to Increase Bone Mass in Men with Osteoporosis Alendronate sodium tablets are indicated for treatment to increase bone mass in men with osteoporosis [see Clinical Studies (14.3) ] .
1.4Treatment of Glucocorticoid-Induced Osteoporosis Alendronate sodium tablets are indicated for the treatment of glucocorticoid-induced osteoporosis in men and women receiving glucocorticoids in a daily dosage equivalent to 7.5 mg or greater of prednisone and who have low bone mineral density [see Clinical Studies (14.4) ] .
1.5Treatment of Paget's Disease of Bone Alendronate sodium tablets are indicated for the treatment of Paget’s disease of bone in men and women. Treatment is indicated in patients with Paget's disease of bone who have alkaline phosphatase at least two times the upper limit of normal, or those who are symptomatic, or those at risk for future complications from their disease. [See Clinical Studies (14.5) .]
1.6Important Limitations of Use The optimal duration of use has not been determined. The safety and effectiveness of alendronate sodium tablets for the treatment of osteoporosis are based on clinical data of four years duration. All patients on bisphosphonate therapy should have the need for continued therapy re-evaluated on a periodic basis.
Patients at low-risk for fracture should be considered for drug discontinuation after 3 to 5 years of use. Patients who discontinue therapy should have their risk for fracture re-evaluated periodically.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Treatment of osteoporosis in postmenopausal women and in men: 10 mg daily or 70 mg tablet once weekly. (2.1 , 2.3) Prevention of osteoporosis in postmenopausal women: 5 mg daily or 35 mg once weekly. (2.2) Glucocorticoid-induced osteoporosis: 5 mg daily; or 10 mg daily in postmenopausal women not receiving estrogen.
(2.4) Paget's disease: 40 mg daily for six months. (2.5) Instruct patients to: (2.6) Swallow tablets whole with 6 to 8 ounces plain water at least 30 minutes before the first food, drink, or medication of the day. Not lie down for at least 30 minutes after taking alendronate sodium tablets and until after food.
2.1Treatment of Osteoporosis in Postmenopausal Women The recommended dosage is: one 70 mg tablet once weekly or one 10 mg tablet once daily
2.2Prevention of Osteoporosis in Postmenopausal Women The recommended dosage is: one 35 mg tablet once weekly or one 5 mg tablet once daily
2.3Treatment to Increase Bone Mass in Men with Osteoporosis The recommended dosage is: one 70 mg tablet once weekly or one 10 mg tablet once daily
2.4Treatment of Glucocorticoid-Induced Osteoporosis The recommended dosage is one 5 mg tablet once daily, except for postmenopausal women not receiving estrogen, for whom the recommended dosage is one 10 mg tablet once daily.
2.5Treatment of Paget's Disease of Bone The recommended treatment regimen is 40 mg once a day for six months. Re-treatment of Paget’s Disease Re-treatment with alendronate sodium tablets may be considered, following a six-month post-treatment evaluation period in patients who have relapsed, based on increases in serum alkaline phosphatase, which should be measured periodically. Re-treatment may also be considered in those who failed to normalize their serum alkaline phosphatase.
2.6Important Administration Instructions Instruct patients to do the following: Take alendronate sodium tablets at least one-half hour before the first food, beverage, or medication of the day with plain water only [see Patient Counseling Information (17) ] . Other beverages (including mineral water), food, and some medications are likely to reduce the absorption of alendronate sodium tablets [see Drug Interactions (7.1) ] . Waiting less than 30 minutes, or taking alendronate sodium tablets with food, beverages (other than plain water) or other medications will lessen the effect of alendronate sodium tablets by decreasing its absorption into the body.
Take alendronate sodium tablets upon arising for the day. To facilitate delivery to the stomach and thus reduce the potential for esophageal irritation, an alendronate sodium tablet should be swallowed with a full glass of water (6 to 8 ounces). Patients should not lie down for at least 30 minutes and until after their first food of the day.
Alendronate sodium tablets should not be taken at bedtime or before arising for the day. Failure to follow these instructions may increase the risk of esophageal adverse experiences [see Warnings and Precautions (5.1) and Patient Counseling Information (17) ] .
2.7Recommendations for Calcium and Vitamin D Supplementation Instruct patients to take supplemental calcium if dietary intake is inadequate [see Warnings and Precautions (5.2) ] . Patients at increased risk for vitamin D insufficiency (e.g., over the age of 70 years, nursing home-bound, or chronically ill) may need vitamin D supplementation. Patients with gastrointestinal malabsorption syndromes may require higher doses of vitamin D supplementation and measurement of 25-hydroxyvitamin D should be considered.
Patients treated with glucocorticoids should receive adequate amounts of calcium and vitamin D.
2.8Administration Instructions for Missed Doses If a once-weekly dose of alendronate sodium tablets is missed, instruct patients to take one dose on the morning after they remember. They should not take two doses on the same day but should return to taking one dose once a week, as originally scheduled on their chosen d… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 10 mg tablets are white to off-white, circular, biconvex, uncoated tablets debossed with ‘F’ on one side and ‘18’ on the other side. 35 mg tablets are white to off-white, oval shaped, biconvex, uncoated tablets debossed with ‘F’ on one side and ‘19’ on the other side. 70 mg tablets are white to off-white, oval shaped, biconvex, uncoated tablets debossed with ‘F’ on one side and ‘21’ on the other side.
Tablets: 10 mg, 35 mg, and 70 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Alendronate sodium tablets are contraindicated in patients with the following conditions: Abnormalities of the esophagus which delay esophageal emptying such as stricture or achalasia [see Warnings and Precautions (5.1) ] Inability to stand or sit upright for at least 30 minutes [see Dosage and Administration (2.6) ; Warnings and Precautions (5.1) ] Hypocalcemia [see Warnings and Precautions (5.2) ] Hypersensitivity to any component of this product. Hypersensitivity reactions including urticaria and angioedema have been reported [see Adverse Reactions (6.2) ] .
Abnormalities of the esophagus which delay emptying such as stricture or achalasia (4 , 5.1) Inability to stand/sit upright for at least 30 minutes (2.6 , 4 , 5.1) Hypocalcemia (4 , 5.2) Hypersensitivity to any component of this product (4 , 6.2)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Upper Gastrointestinal Adverse Reactions can occur. Instruct patients to follow dosing instructions. Discontinue if new or worsening symptoms occur.
(5.1) Hypocalcemia can worsen and must be corrected prior to use. (5.2) Severe Bone, Joint, Muscle Pain may occur. Discontinue use if severe symptoms develop.
(5.3) Osteonecrosis of the Jaw has been reported. (5.4) Atypical Fractures Including Femoral Fractures have been reported. Patients with new thigh or groin pain should be evaluated to rule out a femoral fracture.
Risk/benefit of continuing bisphosphonate therapy should be re-evaluated in these patients and interruption of bisphosphonate therapy should be considered (5.5)
5.1Upper Gastrointestinal Adverse Reactions Alendronate sodium, like other bisphosphonates administered orally, may cause local irritation of the upper gastrointestinal mucosa. Because of these possible irritant effects and a potential for worsening of the underlying disease, caution should be used when alendronate sodium is given to patients with active upper gastrointestinal problems (such as known Barrett's esophagus, dysphagia, other esophageal diseases, gastritis, duodenitis, or ulcers). Esophageal adverse experiences, such as esophagitis, esophageal ulcers and esophageal erosions, occasionally with bleeding and rarely followed by esophageal stricture or perforation, have been reported in patients receiving treatment with oral bisphosphonates including alendronate sodium.
In some cases these have been severe and required hospitalization. Physicians should therefore be alert to any signs or symptoms signaling a possible esophageal reaction and patients should be instructed to discontinue alendronate sodium and seek medical attention if they develop dysphagia, odynophagia, retrosternal pain or new or worsening heartburn. The risk of severe esophageal adverse experiences appears to be greater in patients who lie down after taking oral bisphosphonates including alendronate sodium and/or who fail to swallow oral bisphosphonates including alendronate sodium with the recommended full glass (6 to 8 ounces) of water, and/or who continue to take oral bisphosphonates including alendronate sodium after developing symptoms suggestive of esophageal irritation.
Therefore, it is very important that the full dosing instructions are provided to, and understood by, the patient [see Dosage and Administration (2.6) ] . In patients who cannot comply with dosing instructions due to mental disability, therapy with alendronate sodium should be used under appropriate supervision. There have been post-marketing reports of gastric and duodenal ulcers with oral bisphosphonate use, some severe and with complications, although no increased risk was observed in controlled clinical trials [see Adverse Reactions (6.2) ] .
5.2Mineral Metabolism Hypocalcemia must be corrected before initiating therapy with alendronate sodium [see Contraindications (4) ]. Other disorders affecting mineral metabolism (such as vitamin D deficiency) should also be effectively treated. In patients with these conditions, serum calcium and symptoms of hypocalcemia should be monitored during therapy with alendronate sodium.
Presumably due to the effects of alendronate sodium on increasing bone mineral, small, asymptomatic decreases in serum calcium and phosphate may occur, especially in patients with Paget’s disease, in whom the pretreatment rate of bone turnover may be greatly elevated, and in patients receiving glucocorticoids, in whom calcium absorption may be decreased. Ensuring adequate calcium and vitamin D intake is especially important in patients with Paget’s disease of bone and in patients receiving glucocorticoids.
5.3Musculoskeletal Pain In post-marketing experience, severe and occasionally incapacitating bone, joint, and/or muscle pain has been reported in patients taking bisphosphonates that are approved for the prevention and treatment of osteoporosis [see Adverse Reac… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse drug reactions are described elsewhere in the labeling: Upper Gastrointestinal Adverse Reactions [see Warnings and Precautions (5.1) ] Mineral Metabolism [see Warnings and Precautions (5.2) ] Musculoskeletal Pain [see Warnings and Precautions (5.3) ] Osteonecrosis of the Jaw [see Warnings and Precautions (5.4) ] Atypical Fractures Including Femoral Fractures [see Warnings and Precautions (5.5) ] Renal Impairment [see Warnings and Precautions (5.6) ] Glucocorticoid-Induced Osteoporosis [see Warnings and Precautions (5.7) ] Most common adverse reactions (greater than or equal to 3%) are abdominal pain, acid regurgitation, constipation, diarrhea, dyspepsia, musculoskeletal pain, nausea.
(6.1) To report SUSPECTED ADVERSE REACTIONS, contact Northstar Rx LLC at 1-800-206-7821 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinicalpractice. Treatment of Osteoporosis in Postmenopausal Women Daily Dosing The safety of alendronate sodium in the treatment of postmenopausal osteoporosis was assessed in four clinical trials that enrolled 7453 women aged 44 to 84 years.
Study 1 and Study 2 were identically designed, three-year, placebo-controlled, double-blind, multicenter studies (United States and Multinational n=994); Study 3 was the three-year vertebral fracture cohort of the Fracture Intervention Trial [FIT] (n=2027) and Study 4 was the four-year clinical fracture cohort of FIT (n=4432). Overall, 3620 patients were exposed to placebo and 3432 patients exposed to alendronate sodium. Patients with pre-existing gastrointestinal disease and concomitant use of non-steroidal anti-inflammatory drugs were included in these clinical trials.
In Study 1 and Study 2 all women received 500 mg elemental calcium as carbonate. In Study 3 and Study 4 all women with dietary calcium intake less than 1000 mg per day received 500 mg calcium and 250 international units Vitamin D per day. Among patients treated with alendronate 10 mg or placebo in Study 1 and Study 2, and all patients in Study 3 and Study 4, the incidence of all-cause mortality was 1.8% in the placebo group and 1.8% in the alendronate sodium group.
The incidence of serious adverse event was 30.7% in the placebo group and 30.9% in the alendronate sodium group. The percentage of patients who discontinued the study due to any clinical adverse event was 9.5% in the placebo group and 8.9% in the alendronate sodium group. Adverse reactions from these studies considered by the investigators as possibly, probably, or definitely drug related in greater than or equal to 1% of patients treated with either alendronate sodium or placebo are presented in Table 1.
Table 1: Osteoporosis Treatment Studies in Postmenopausal Women Adverse Reactions Considered Possibly, Probably, or Definitely Drug Related by the Investigators and Reported in Greater Than or Equal to 1% of Patients United States/ Multinational Studies Fracture Intervention Trial Alendronate Sodium* % (n=196) Placebo % (n=397) Alendronate Sodium † % (n=3236) Placebo % (n=3223) * 10 mg/day for three years † 5 mg/day for 2 years and 10 mg/day for either 1 or 2 additional years Gastrointestinal abdominal pain 6.6 4.8 1.5 1.5 nausea 3.6 4 1.1 1.5 dyspepsia 3.6 3.5 1.1 1.2 constipation 3.1 1.8 0 0.2 diarrhea 3.1 1.8 0.6 0.3 flatulence 2.6 0.5 0.2 0.3 acid regurgitation 2 4.3 1.1 0.9 esophageal ulcer 1.5 0 0.1 0.1 vomiting 1 1.5 0.2 0.3 dysphagia 1 0 0.1 0.1 abdominal distention 1 0.8 0 0 gastritis 0.5 1.3 0.6
0.7Musculoskeletal musculoskeletal (bone, muscle or joint) pain 4.1 2.5 0.4 0.3 muscle cramp 0 1 0.2
0.1Nervous System/Psychiatric headache 2.6 1.5 0.2 0.2 dizziness 0 1 0
0.1Special Senses taste… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Calcium supplements, antacids, or oral medications containing multivalent cations interfere with absorption of alendronate. (2.6 , 7.1) Use caution when co-prescribing aspirin/nonsteroidal anti-inflammatory drugs that may worsen gastrointestinal irritation. (7.2 , 7.3)
7.1Calcium Supplements/Antacids Co-administration of alendronate sodium and calcium, antacids, or oral medications containing multivalent cations will interfere with absorption of alendronate sodium. Therefore, instruct patients to wait at least one-half hour after taking alendronate sodium before taking any other oral medications.
7.2Aspirin In clinical studies, the incidence of upper gastrointestinal adverse events was increased in patients receiving concomitant therapy with daily doses of alendronate greater than 10 mg and aspirin-containing products.
7.3Nonsteroidal Anti-Inflammatory Drugs Alendronate sodium may be administered to patients taking nonsteroidal anti-inflammatory drugs (NSAIDs). In a 3-year, controlled, clinical study (n=2027) during which a majority of patients received concomitant NSAIDs, the incidence of upper gastrointestinal adverse events was similar in patients taking alendronate 5 or 10 mg/day compared to those taking placebo. However, since NSAID use is associated with gastrointestinal irritation, caution should be used during concomitant use with alendronate sodium.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Discontinue when pregnancy is recognized. ( 8.1 ) Alendronate sodium is not indicated for use in pediatric patients. ( 8.4 ) Alendronate sodium is not recommended in patients with renal impairment (creatinine clearance less than 35 mL/min). ( 5.6 , 8.6 )
8.1Pregnancy Risk Summary Available data on the use of alendronate sodium in pregnant women are insufficient to inform a drug-associated risk of adverse maternal or fetal outcomes. Discontinue alendronate sodium when pregnancy is recognized. In animal reproduction studies, daily oral administration of alendronate to rats from before mating through the end of gestation or lactation showed decreased postimplantation survival and decreased pup body weight gain starting at doses equivalent to less than half of the highest recommended 40 mg clinical daily dose (based on body surface area, mg/m 2 ).
Oral administration of alendronate to rats during organogenesis resulted in reduced fetal ossification starting at doses 3 times the 40 mg clinical daily dose. No similar fetal effects were observed in pregnant rabbits dosed orally during organogenesis at doses equivalent to approximately 10 times the 40 mg clinical daily dose. Delayed or failed delivery of offspring, protracted parturition, and late pregnancy maternal and fetal deaths due to maternal hypocalcemia occurred in rats at oral doses as low as one tenth the 40 mg clinical daily dose (see Data).
Bisphosphonates are incorporated into the bone matrix, from which they are gradually released over a period of years. The amount of bisphosphonate incorporated into adult bone and available for release into the systemic circulation is directly related to the dose and duration of bisphosphonate use. Consequently, based on the mechanism of action of bisphosphonates, there is a potential risk of fetal harm, predominantly skeletal, if a woman becomes pregnant after completing a course of bisphosphonate therapy.
The impact of variables such as time between cessation of bisphosphonate therapy to conception, the particular bisphosphonate used, and the route of administration (intravenous versus oral) on the risk has not been studied. The estimated background risk of major birth defects and miscarriage for the indicated population(s) is unknown. All pregnancies have a background risk of birth defects, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Reproduction studies in rats dosed orally from before mating to the end of gestation or lactation showed decreased postimplantation survival starting at 2 mg/kg/day and decreased body weight gain starting at 1 mg/kg/day, doses equivalent to less than half the 40 mg clinical daily dose based on body surface area, mg/m 2 . Incidence of incomplete fetal ossification in vertebral, skull, and sternebral bones were increased in rats dosed orally during organogenesis starting at 10 mg/kg/day (approximately 3 times the 40 mg clinical daily dose).
No similar fetal effects were observed in pregnant rabbits dosed orally during organogenesis at up to 35 mg/kg/day (equivalent to approximately 10 times the 40 mg clinical daily dose). Both total and ionized calcium decreased in pregnant rats dosed orally with 15 mg/kg/day alendronate (approximately 4 times the 40 mg clinical daily dose) resulting in delays and failures of delivery. Protracted parturition due to maternal hypocalcemia was observed when rats were treated from before mating through gestation starting at 0.5 mg/kg/day (approximately one tenth the 40 mg clinical daily dose).
Maternotoxicity (late pregnancy deaths) also occurred in female rats treated orally with 15 mg/kg/day (approximately 4 times the 40 mg clinical daily dose) for varying gestational time periods. These maternal deaths were lessened but not eliminated by cessation of… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data on the use of alendronate sodium in pregnant women are insufficient to inform a drug-associated risk of adverse maternal or fetal outcomes. Discontinue alendronate sodium when pregnancy is recognized. In animal reproduction studies, daily oral administration of alendronate to rats from before mating through the end of gestation or lactation showed decreased postimplantation survival and decreased pup body weight gain starting at doses equivalent to less than half of the highest recommended 40 mg clinical daily dose (based on body surface area, mg/m 2 ).
Oral administration of alendronate to rats during organogenesis resulted in reduced fetal ossification starting at doses 3 times the 40 mg clinical daily dose. No similar fetal effects were observed in pregnant rabbits dosed orally during organogenesis at doses equivalent to approximately 10 times the 40 mg clinical daily dose. Delayed or failed delivery of offspring, protracted parturition, and late pregnancy maternal and fetal deaths due to maternal hypocalcemia occurred in rats at oral doses as low as one tenth the 40 mg clinical daily dose (see Data).
Bisphosphonates are incorporated into the bone matrix, from which they are gradually released over a period of years. The amount of bisphosphonate incorporated into adult bone and available for release into the systemic circulation is directly related to the dose and duration of bisphosphonate use. Consequently, based on the mechanism of action of bisphosphonates, there is a potential risk of fetal harm, predominantly skeletal, if a woman becomes pregnant after completing a course of bisphosphonate therapy.
The impact of variables such as time between cessation of bisphosphonate therapy to conception, the particular bisphosphonate used, and the route of administration (intravenous versus oral) on the risk has not been studied. The estimated background risk of major birth defects and miscarriage for the indicated population(s) is unknown. All pregnancies have a background risk of birth defects, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Reproduction studies in rats dosed orally from before mating to the end of gestation or lactation showed decreased postimplantation survival starting at 2 mg/kg/day and decreased body weight gain starting at 1 mg/kg/day, doses equivalent to less than half the 40 mg clinical daily dose based on body surface area, mg/m 2 . Incidence of incomplete fetal ossification in vertebral, skull, and sternebral bones were increased in rats dosed orally during organogenesis starting at 10 mg/kg/day (approximately 3 times the 40 mg clinical daily dose).
No similar fetal effects were observed in pregnant rabbits dosed orally during organogenesis at up to 35 mg/kg/day (equivalent to approximately 10 times the 40 mg clinical daily dose). Both total and ionized calcium decreased in pregnant rats dosed orally with 15 mg/kg/day alendronate (approximately 4 times the 40 mg clinical daily dose) resulting in delays and failures of delivery. Protracted parturition due to maternal hypocalcemia was observed when rats were treated from before mating through gestation starting at 0.5 mg/kg/day (approximately one tenth the 40 mg clinical daily dose).
Maternotoxicity (late pregnancy deaths) also occurred in female rats treated orally with 15 mg/kg/day (approximately 4 times the 40 mg clinical daily dose) for varying gestational time periods. These maternal deaths were lessened but not eliminated by cessation of treatment. Calcium supplementation in the drinking water or by subcutaneous minipump to rats dosed orally with 15 mg/kg/day alendronate could not ameliorate the hypocalcemia or prevent the dystocia-related maternal and neonatal deaths.
However, intravenous calcium supplementation prevented mater… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use Alendronate sodium is not indicated for use in pediatric patients. The safety and efficacy of alendronate sodium were examined in a randomized, double-blind, placebo-controlled two-year study of 139 pediatric patients, aged 4 to 18 years, with severe osteogenesis imperfecta (OI). One-hundred-and-nine patients were randomized to 5 mg alendronate daily (weight less than 40 kg) or 10 mg alendronate daily (weight greater than or equal to 40 kg) and 30 patients to placebo.
The mean baseline lumbar spine BMD Z-score of the patients was -4.5. The mean change in lumbar spine BMD Z-score from baseline to Month 24 was 1.3 in the alendronate sodium-treated patients and 0.1 in the placebo-treated patients. Treatment with alendronate sodium did not reduce the risk of fracture.
Sixteen percent of the alendronate sodium patients who sustained a radiologically-confirmed fracture by Month 12 of the study had delayed fracture healing (callus remodeling) or fracture non-union when assessed radiographically at Month 24 compared with 9% of the placebo-treated patients. In alendronate sodium-treated patients, bone histomorphometry data obtained at Month 24 demonstrated decreased bone turnover and delayed mineralization time; however, there were no mineralization defects. There were no statistically significant differences between the alendronate sodium and placebo groups in reduction of bone pain.
The oral bioavailability in children was similar to that observed in adults. The overall safety profile of alendronate sodium in osteogenesis imperfecta patients treated for up to 24 months was generally similar to that of adults with osteoporosis treated with alendronate sodium. However, there was an increased occurrence of vomiting in osteogenesis imperfecta patients treated with alendronate sodium compared to placebo.
During the 24-month treatment period, vomiting was observed in 32 of 109 (29.4%) patients treated with alendronate sodium and 3 of 30 (10%) patients treated with placebo. In a pharmacokinetic study, 6 of 24 pediatric osteogenesis imperfecta patients who received a single oral dose of alendronate 35 or 70 mg developed fever, flu-like symptoms, and/or mild lymphocytopenia within 24 to 48 hours after administration. These events, lasting no more than 2 to 3 days and responding to acetaminophen, are consistent with an acute-phase response that has been reported in patients receiving bisphosphonates, including alendronate sodium. [See Adverse Reactions (6.2) .]
🧓 Geriatric Use ▾
8.5Geriatric Use Of the patients receiving alendronate sodium in the Fracture Intervention Trial (FIT), 71% (n=2302) were greater than or equal to 65 years of age and 17% (n=550) were greater than or equal to 75 years of age. Of the patients receiving alendronate sodium in the United States and Multinational osteoporosis treatment studies in women, osteoporosis studies in men, glucocorticoid-induced osteoporosis studies, and Paget’s disease studies [see Clinical Studies (14.1) , (14.3) , (14.4) , (14.5) ], 45%, 54%, 37%, and 70%, respectively, were 65 years of age or over.
No overall differences in efficacy or safety were observed between these patients and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE Significant lethality after single oral doses was seen in female rats and mice at 552 mg/kg (3256 mg/m 2 ) and 966 mg/kg (2898 mg/m 2 ), respectively. In males, these values were slightly higher, 626 and 1280 mg/kg, respectively. There was no lethality in dogs at oral doses up to 200 mg/kg (4000 mg/m 2 ).
No specific information is available on the treatment of overdosage with alendronate sodium. Hypocalcemia, hypophosphatemia, and upper gastrointestinal adverse events, such as upset stomach, heartburn, esophagitis, gastritis, or ulcer, may result from oral overdosage. Milk or antacids should be given to bind alendronate.
Due to the risk of esophageal irritation, vomiting should not be induced and the patient should remain fully upright. Dialysis would not be beneficial.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Animal studies have indicated the following mode of action. At the cellular level, alendronate shows preferential localization to sites of bone resorption, specifically under osteoclasts. The osteoclasts adhere normally to the bone surface but lack the ruffled border that is indicative of active resorption.
Alendronate does not interfere with osteoclast recruitment or attachment, but it does inhibit osteoclast activity. Studies in mice on the localization of radioactive [ 3 H]alendronate in bone showed about 10-fold higher uptake on osteoclast surfaces than on osteoblast surfaces. Bones examined 6 and 49 days after [ 3 H]alendronate administration in rats and mice, respectively, showed that normal bone was formed on top of the alendronate, which was incorporated inside the matrix.
While incorporated in bone matrix, alendronate is not pharmacologically active. Thus, alendronate must be continuously administered to suppress osteoclasts on newly formed resorption surfaces. Histomorphometry in baboons and rats showed that alendronate treatment reduces bone turnover (i.e., the number of sites at which bone is remodeled).
In addition, bone formation exceeds bone resorption at these remodeling sites, leading to progressive gains in bone mass.
12.2Pharmacodynamics Alendronate is a bisphosphonate that binds to bone hydroxyapatite and specifically inhibits the activity of osteoclasts, the bone-resorbing cells. Alendronate reduces bone resorption with no direct effect on bone formation, although the latter process is ultimately reduced because bone resorption and formation are coupled during bone turnover. Osteoporosis in Postmenopausal Women Osteoporosis is characterized by low bone mass that leads to an increased risk of fracture.
The diagnosis can be confirmed by the finding of low bone mass, evidence of fracture on x-ray, a history of osteoporotic fracture, or height loss or kyphosis, indicative of vertebral (spinal) fracture. Osteoporosis occurs in both males and females but is most common among women following the menopause, when bone turnover increases and the rate of bone resorption exceeds that of bone formation. These changes result in progressive bone loss and lead to osteoporosis in a significant proportion of women over age 50.
Fractures, usually of the spine, hip, and wrist, are the common consequences. From age 50 to age 90, the risk of hip fracture in white women increases 50-fold and the risk of vertebral fracture 15- to 30-fold. It is estimated that approximately 40% of 50-year-old women will sustain one or more osteoporosis-related fractures of the spine, hip, or wrist during their remaining lifetimes.
Hip fractures, in particular, are associated with substantial morbidity, disability, and mortality. Daily oral doses of alendronate (5, 20, and 40 mg for six weeks) in postmenopausal women produced biochemical changes indicative of dose-dependent inhibition of bone resorption, including decreases in urinary calcium and urinary markers of bone collagen degradation (such as deoxypyridinoline and cross-linked N-telopeptides of type I collagen). These biochemical changes tended to return toward baseline values as early as 3 weeks following the discontinuation of therapy with alendronate and did not differ from placebo after 7 months.
Long-term treatment of osteoporosis with alendronate 10 mg/day (for up to five years) reduced urinary excretion of markers of bone resorption, deoxypyridinoline and cross-linked N-telopeptides of type l collagen, by approximately 50% and 70%, respectively, to reach levels similar to those seen in healthy premenopausal women. Similar decreases were seen in patients in osteoporosis prevention studies who received alendronate 5 mg/day. The decrease in the rate of bone resorption indicated by these markers was evident as early as one month and at three to six months reached a plateau that was maintained for the entire duration of treatment with alen… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Animal studies have indicated the following mode of action. At the cellular level, alendronate shows preferential localization to sites of bone resorption, specifically under osteoclasts. The osteoclasts adhere normally to the bone surface but lack the ruffled border that is indicative of active resorption.
Alendronate does not interfere with osteoclast recruitment or attachment, but it does inhibit osteoclast activity. Studies in mice on the localization of radioactive [ 3 H]alendronate in bone showed about 10-fold higher uptake on osteoclast surfaces than on osteoblast surfaces. Bones examined 6 and 49 days after [ 3 H]alendronate administration in rats and mice, respectively, showed that normal bone was formed on top of the alendronate, which was incorporated inside the matrix.
While incorporated in bone matrix, alendronate is not pharmacologically active. Thus, alendronate must be continuously administered to suppress osteoclasts on newly formed resorption surfaces. Histomorphometry in baboons and rats showed that alendronate treatment reduces bone turnover (i.e., the number of sites at which bone is remodeled).
In addition, bone formation exceeds bone resorption at these remodeling sites, leading to progressive gains in bone mass.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied Alendronate Sodium Tablets USP, 10 mg are white to off-white, circular, biconvex, uncoated tablets debossed with ‘F’ on one side and ‘18’ on the other side. Bottles of 30 NDC 16714-631-01 Bottles of 100 NDC 16714-631-02 10 x 10 Unit-dose Tablets NDC 16714-631-11 Alendronate Sodium Tablets USP, 35 mg are white to off-white, oval shaped, biconvex, uncoated tablets debossed with ‘F’ on one side and ‘19’ on the other side. Unit-of-use blister package of 4 NDC 16714-632-01 Unit-of-use blister package of 20 NDC 16714-632-02 10 x 10 Unit-dose Tablets NDC 16714-632-11 Alendronate Sodium Tablets USP, 70 mg are white to off-white, oval shaped, biconvex, uncoated tablets debossed with ‘F’ on one side and ‘21’ on the other side.
Unit-of-use blister package of 4 NDC 16714-633-01 Unit-of-use blister package of 20 NDC 16714-633-02 10 x 10 Unit-dose Tablets NDC 16714-633-11 Storage Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Store in a well-closed container.
📋 Description ▾
11 DESCRIPTION Alendronate sodium is a bisphosphonate that acts as a specific inhibitor of osteoclast-mediated bone resorption. Bisphosphonates are synthetic analogs of pyrophosphate that bind to the hydroxyapatite found in bone. Alendronate sodium is chemically described as (4-amino-1-hydroxybutylidene) bisphosphonic acid monosodium salt trihydrate.
The molecular formula of alendronate sodium is C 4 H 12 NNaO 7 P 2 •3H 2 O and its formula weight is 325.12. The structural formula is: Alendronate sodium USP is a white, free-flowing powder. It is soluble in water, very slightly soluble in alcohol, and practically insoluble in chloroform.
Alendronate sodium tablets, USP for oral administration contain 13.052, 45.681, or 91.363 mg of alendronate monosodium salt trihydrate, which is the molar equivalent of 10 mg, 35 mg, and 70 mg, respectively, of free acid, and the following inactive ingredients: corn starch, magnesium stearate, microcrystalline cellulose, povidone, and sodium starch glycolate. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide) . Instruct patients to read the Medication Guide before starting therapy with alendronate sodium tablets and to reread it each time the prescription is renewed. Os teoporosis Recommendations, Including Calcium and Vitamin D Supplementation Instruct patients to take supplemental calcium and vitamin D, if daily dietary intake is inadequate.
Weight-bearing exercise should be considered along with the modification of certain behavioral factors, such as cigarette smoking and/or excessive alcohol consumption, if these factors exist. Do sing Instructions Instruct patients that the expected benefits of alendronate sodium tablets may only be obtained when it is taken with plain water the first thing upon arising for the day at least 30 minutes before the first food, beverage, or medication of the day. Even dosing with orange juice or coffee has been shown to markedly reduce the absorption of alendronate sodium tablets [see Clinical Pharmacology (12.3) ] .
Instruct patients not to chew or suck on the tablet because of a potential for oropharyngeal ulceration. Instruct patients to swallow each tablet of alendronate sodium with a full glass of water (6 to 8 ounces) to facilitate delivery to the stomach and thus reduce the potential for esophageal irritation. Instruct patients not to lie down for at least 30 minutes and until after their first food of the day.
Instruct patients not to take alendronate sodium tablets at bedtime or before arising for the day. Patients should be informed that failure to follow these instructions may increase their risk of esophageal problems. Instruct patients that if they develop symptoms of esophageal disease (such as difficulty or pain upon swallowing, retrosternal pain or new or worsening heartburn) they should stop taking alendronate sodium tablets and consult their physician.
If patients miss a dose of once weekly alendronate sodium tablets, instruct patients to take one dose on the morning after they remember. They should not take two doses on the same day but should return to taking one dose once a week, as originally scheduled on their chosen day. Manufactured for: Northstar Rx LLC Memphis, TN 38141.
Manufactured by: Aurobindo Pharma Limited Hyderabad-500 090, India. M.L.No.: 19/HD/AP/95/F/R Revised: 06/2026
💬 Medication Guide ▾
MEDICATION GUIDE Alendronate Sodium (a len' droe nate soe' dee um) Tablets, USP Read the Medication Guide that comes with alendronate sodium tablets before you start taking them and each time you get a refill. There may be new information. This Medication Guide does not take the place of talking with your doctor about your medical condition or treatment.
Talk to your doctor if you have any questions about alendronate sodium tablets. What is the most important information I should know about alendronate sodium tablets? Alendronate sodium tablets c an cause serious side effects including: Esophagus problems Low calcium levels in your blood (hypocalcemia) Bone, joint, or muscle pain Severe jaw bone problems (osteonecrosis) Unusual breaks in thigh and other bones 1.
Esophagus problems. Some people who take alendronate sodium tablets m ay develop problems in the esophagus (the tube that connects the mouth and the stomach). These problems include irritation, inflammation, or ulcers of the esophagus which may sometimes bleed.
It is important that you take alendronate sodium tablets exactly as prescribed to help lower your chance of getting esophagus problems. (See the section “How should I take alendronate sodium tablets?”) Stop taking alendronate sodium tablets and call your doctor right away if you get chest pain, new or worsening heartburn, or have trouble or pain when you swallow. 2.
Low calcium levels in your blood (hypocalcemia). Alendronate sodium tablets may lower the calcium levels in your blood. If you have low blood calcium before you start taking alendronate sodium tablets, they may get worse during treatment.
Your low blood calcium must be treated before you take alendronate sodium tablets. Most people with low blood calcium levels do not have symptoms, but some people may have symptoms. Call your doctor right away if you have symptoms of low blood calcium such as: Spasms, twitches, or cramps in your muscles Numbness or tingling in your fingers, toes, or around your mouth Your doctor may prescribe calcium and vitamin D to help prevent low calcium levels in your blood, while you take alendronate sodium tablets.
Take calcium and vitamin D as your doctor tells you to. 3. Bone, joint, or muscle pain.
Some people who take alendronate sodium tablets develop severe bone, joint, or muscle pain. 4. Severe jaw bone problems (osteonecrosis).
Severe jaw bone problems may happen when you take alendronate sodium tablets. Your doctor should examine your mouth before you start alendronate sodium tablets. Your doctor may tell you to see your dentist before you start alendronate sodium tablets.
It is important for you to practice good mouth care during treatment with alendronate sodium tablets. 5. Unusual breaks in thigh and other bones.
Some people have had unusual bone breaks, including thigh bone when taking alendronate sodium tablets. A break in the thigh bone can feel like a new pain in your hip, groin, or thigh. People taking alendronate sodium tablets can also have breaks in other bones.
Call your doctor right away if you have any of these side effects. What are alendronate sodium tablets? Alendronate sodium tablets are a prescription medicine used to: Treat or prevent osteoporosis in women after menopause.
It helps reduce the chance of having a hip or spinal fracture (break). Increase bone mass in men with osteoporosis. Treat osteoporosis in either men or women who are taking corticosteroid medicines.
Treat certain men and women who have Paget’s disease of the bone. It is not known how long alendronate sodium tablets work for the treatment and prevention of osteoporosis. You should see your doctor regularly to determine if alendronate sodium tablets are still right for you.
Alendronate sodium tablets are not for use in children. Who should not take alendronate sodium tablets? Do not take alendronate sodium tablets i f you: Have certain problems with your esophagus, the tube that connects your mouth with your stomach Cannot stand o… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption Relative to an intravenous reference dose, the mean oral bioavailability of alendronate in women was 0.64% for doses ranging from 5 to 70 mg when administered after an overnight fast and two hours before a standardized breakfast. Oral bioavailability of the 10 mg tablet in men (0.59%) was similar to that in women when administered after an overnight fast and 2 hours before breakfast. Alendronate 70 mg oral solution and alendronate 70 mg tablet are equally bioavailable.
A study examining the effect of timing of a meal on the bioavailability of alendronate was performed in 49 postmenopausal women. Bioavailability was decreased (by approximately 40%) when 10 mg alendronate was administered either 0.5 or 1 hour before a standardized breakfast, when compared to dosing 2 hours before eating. In studies of treatment and prevention of osteoporosis, alendronate was effective when administered at least 30 minutes before breakfast.
Bioavailability was negligible whether alendronate was administered with or up to two hours after a standardized breakfast. Concomitant administration of alendronate with coffee or orange juice reduced bioavailability by approximately 60%. Distribution Preclinical studies (in male rats) show that alendronate transiently distributes to soft tissues following 1 mg/kg intravenous administration but is then rapidly redistributed to bone or excreted in the urine .
The mean steady-state volume of distribution, exclusive of bone, is at least 28 L in humans . Concentrations of drug in plasma following therapeutic oral doses are too low (less than 5 ng/mL) for analytical detection. Protein binding in human plasma is approximately 78%.
Metabolism There is no evidence that alendronate is metabolized in animals or humans. Excretion Following a single intravenous dose of [ 14 C]alendronate, approximately 50% of the radioactivity was excreted in the urine within 72 hours and little or no radioactivity was recovered in the feces. Following a single 10 mg intravenous dose, the renal clearance of alendronate was 71 mL/min (64, 78; 90% confidence interval [CI]), and systemic clearance did not exceed 200 mL/min.
Plasma concentrations fell by more than 95% within 6 hours following intravenous administration. The terminal half-life in humans is estimated to exceed 10 years, probably reflecting release of alendronate from the skeleton. Based on the above, it is estimated that after 10 years of oral treatment with alendronate (10 mg daily) the amount of alendronate released daily from the skeleton is approximately 25% of that absorbed from the gastrointestinal tract.
Specific Populations Gender: Bioavailability and the fraction of an intravenous dose excreted in urine were similar in men and women. Geriatric: Bioavailability and disposition (urinary excretion) were similar in elderly and younger patients. No dosage adjustment is necessary in elderly patients .
Race: Pharmacokinetic differences due to race have not been studied. Renal Impairment: Preclinical studies show that, in rats with kidney failure, increasing amounts of drug are present in plasma, kidney, spleen, and tibia. In healthy controls, drug that is not deposited in bone is rapidly excreted in the urine.
No evidence of saturation of bone uptake was found after 3 weeks dosing with cumulative intravenous doses of 35 mg/kg in young male rats. Although no formal renal impairment pharmacokinetic study has been conducted in patients, it is likely that, as in animals, elimination of alendronate via the kidney will be reduced in patients with impaired renal function. Therefore, somewhat greater accumulation of alendronate in bone might be expected in patients with impaired renal function.
No dosage adjustment is necessary for patients with creatinine clearance 35 to 60 mL/min. Alendronate sodium is not recommended for patients with creatinine clearance less than 35 mL/min due to lack of experience with alendronate in renal failure. Hepatic Impa… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Alendronate is a bisphosphonate that binds to bone hydroxyapatite and specifically inhibits the activity of osteoclasts, the bone-resorbing cells. Alendronate reduces bone resorption with no direct effect on bone formation, although the latter process is ultimately reduced because bone resorption and formation are coupled during bone turnover. Osteoporosis in Postmenopausal Women Osteoporosis is characterized by low bone mass that leads to an increased risk of fracture.
The diagnosis can be confirmed by the finding of low bone mass, evidence of fracture on x-ray, a history of osteoporotic fracture, or height loss or kyphosis, indicative of vertebral (spinal) fracture. Osteoporosis occurs in both males and females but is most common among women following the menopause, when bone turnover increases and the rate of bone resorption exceeds that of bone formation. These changes result in progressive bone loss and lead to osteoporosis in a significant proportion of women over age 50.
Fractures, usually of the spine, hip, and wrist, are the common consequences. From age 50 to age 90, the risk of hip fracture in white women increases 50-fold and the risk of vertebral fracture 15- to 30-fold. It is estimated that approximately 40% of 50-year-old women will sustain one or more osteoporosis-related fractures of the spine, hip, or wrist during their remaining lifetimes.
Hip fractures, in particular, are associated with substantial morbidity, disability, and mortality. Daily oral doses of alendronate (5, 20, and 40 mg for six weeks) in postmenopausal women produced biochemical changes indicative of dose-dependent inhibition of bone resorption, including decreases in urinary calcium and urinary markers of bone collagen degradation (such as deoxypyridinoline and cross-linked N-telopeptides of type I collagen). These biochemical changes tended to return toward baseline values as early as 3 weeks following the discontinuation of therapy with alendronate and did not differ from placebo after 7 months.
Long-term treatment of osteoporosis with alendronate 10 mg/day (for up to five years) reduced urinary excretion of markers of bone resorption, deoxypyridinoline and cross-linked N-telopeptides of type l collagen, by approximately 50% and 70%, respectively, to reach levels similar to those seen in healthy premenopausal women. Similar decreases were seen in patients in osteoporosis prevention studies who received alendronate 5 mg/day. The decrease in the rate of bone resorption indicated by these markers was evident as early as one month and at three to six months reached a plateau that was maintained for the entire duration of treatment with alendronate sodium.
In osteoporosis treatment studies alendronate 10 mg/day decreased the markers of bone formation, osteocalcin and bone specific alkaline phosphatase by approximately 50%, and total serum alkaline phosphatase by approximately 25 to 30% to reach a plateau after 6 to 12 months. In osteoporosis prevention studies alendronate 5 mg/day decreased osteocalcin and total serum alkaline phosphatase by approximately 40% and 15%, respectively. Similar reductions in the rate of bone turnover were observed in postmenopausal women during one-year studies with once weekly alendronate 70 mg for the treatment of osteoporosis and once weekly alendronate 35 mg for the prevention of osteoporosis.
These data indicate that the rate of bone turnover reached a new steady-state, despite the progressive increase in the total amount of alendronate deposited within bone. As a result of inhibition of bone resorption, asymptomatic reductions in serum calcium and phosphate concentrations were also observed following treatment with alendronate sodium. In the long-term studies, reductions from baseline in serum calcium (approximately 2%) and phosphate (approximately 4 to 6%) were evident the first month after the initiation of alendronate 10 mg.
No further decreases in serum calcium were observed for the… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Treatment of Osteoporosis in Postmenopausal Women Daily Dosing The efficacy of alendronate 10 mg daily was assessed in four clinical trials. Study 1, a three-year, multicenter, double-blind, placebo-controlled, U.S. clinical study enrolled 478 patients with a BMD T-score at or below minus 2.5 with or without a prior vertebral fracture; Study 2, a three-year, multicenter, double-blind, placebo-controlled Multinational clinical study enrolled 516 patients with a BMD T-score at or below minus 2.5 with or without a prior vertebral fracture; Study 3, the Three-Year Study of the Fracture Intervention Trial (FIT) a study which enrolled 2027 postmenopausal patients with at least one baseline vertebral fracture; and Study 4, the Four-Year Study of FIT: a study which enrolled 4432 postmenopausal patients with low bone mass but without a baseline vertebral fracture.
Effect on Fracture Incidence To assess the effects of alendronate sodium on the incidence of vertebral fractures (detected by digitized radiography; approximately one third of these were clinically symptomatic), the U.S. and Multinational studies were combined in an analysis that compared placebo to the pooled dosage groups of alendronate (5 or 10 mg for three years or 20 mg for two years followed by 5 mg for one year). There was a statistically significant reduction in the proportion of patients treated with alendronate sodium experiencing one or more new vertebral fractures relative to those treated with placebo (3.2% vs.
6.2%; a 48% relative risk reduction). A reduction in the total number of new vertebral fractures (4.2 vs. 11.3 per 100 patients) was also observed.
In the pooled analysis, patients who received alendronate sodium had a loss in stature that was statistically significantly less than was observed in those who received placebo (-3 mm vs. -4.6 mm). The Fracture Intervention Trial (FIT) consisted of two studies in postmenopausal women: the Three-Year Study of patients who had at least one baseline radiographic vertebral fracture and the Four-Year Study of patients with low bone mass but without a baseline vertebral fracture. In both studies of FIT, 96% of randomized patients completed the studies (i.e., had a closeout visit at the scheduled end of the study); approximately 80% of patients were still taking study medication upon completion.
Fracture Intervention Trial: Three-Year Study (patients with at least one baseline radiographic vertebral fracture) This randomized, double-blind, placebo-controlled, 2027-patient study (alendronate sodium, n=1022; placebo, n=1005) demonstrated that treatment with alendronate sodium resulted in statistically significant reductions in fracture incidence at three years as shown in Table 6. Table 6: Effect of Alendronate Sodium on Fracture Incidence in the Three-Year Study of FIT (patients with vertebral fracture at baseline) Percent of Patients Alendronate Sodium (n=1022) Placebo (n=1005) Absolute Reduction in Fracture Incidence Relative Reduction in Fracture Risk % *Number evaluable for vertebral fractures: alendronate sodium, n=984; placebo, n=966 † p<0.001, ‡ p=0.007, § p<0.01, ¶ p<0.05 Patients with: Vertebral fractures (diagnosed by X-ray)* ≥1 new vertebral fracture 7.9 15 7.1 47 † ≥2 new vertebral fractures 0.5 4.9 4.4 90 † Clinical (symptomatic) fractures Any clinical (symptomatic) fracture 13.8 18.1 4.3 26 ‡ ≥1 clinical (symptomatic) vertebral fracture 2.3 5 2.7 54 § Hip fracture 1.1 2.2 1.1 51 ¶ Wrist (forearm) fracture 2.2 4.1 1.9 48 ¶ Furthermore, in this population of patients with baseline vertebral fracture, treatment with alendronate sodium significantly reduced the incidence of hospitalizations (25% vs.
30.7%). In the Three-Year Study of FIT, fractures of the hip occurred in 22 (2.2%) of 1005 patients on placebo and 11 (1.1%) of 1022 patients on alendronate sodium, p=0.047. Figure 1 displays the cumulative incidence of hip fractures in this study.
Figure 1: Fracture Intervention Trial: Fo… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Harderian gland (a retro-orbital gland not present in humans) adenomas were increased in high-dose female mice (p=0.003) in a 92-week oral carcinogenicity study at doses of alendronate of 1, 3, and 10 mg/kg/day (males) or 1, 2, and 5 mg/kg/day (females). These doses are equivalent to approximately 0.1 to 1 times the highest recommended clinical daily dose of 40 mg based on surface area, mg/m 2 . The relevance of this finding to humans is unknown.
Parafollicular cell (thyroid) adenomas were increased in high-dose male rats (p=0.003) in a 2-year oral carcinogenicity study at doses of 1 and 3.75 mg/kg body weight. These doses are equivalent to approximately 0.3 and 1 times the 40 mg clinical daily dose based on surface area, mg/m 2 . The relevance of this finding to humans is unknown.
Alendronate was not genotoxic in the in vitro microbial mutagenesis assay with and without metabolic activation, in an in vitro mammalian cell mutagenesis assay, in an in vitro alkaline elution assay in rat hepatocytes, and in an in vivo chromosomal aberration assay in mice. In an in vitro chromosomal aberration assay in Chinese hamster ovary cells, however, alendronate gave equivocal results. Alendronate had no effect on fertility (male or female) in rats at oral doses up to 5 mg/kg/day (approximately 1 times the 40 mg clinical daily dose based on surface area, mg/m 2 ).
13.2Animal Toxicology and/or Pharmacology The relative inhibitory activities on bone resorption and mineralization of alendronate and etidronate were compared in the Schenk assay, which is based on histological examination of the epiphyses of growing rats. In this assay, the lowest dose of alendronate that interfered with bone mineralization (leading to osteomalacia) was 6000-fold the antiresorptive dose. The corresponding ratio for etidronate was one to one.
These data suggest that alendronate administered in therapeutic doses is highly unlikely to induce osteomalacia.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Harderian gland (a retro-orbital gland not present in humans) adenomas were increased in high-dose female mice (p=0.003) in a 92-week oral carcinogenicity study at doses of alendronate of 1, 3, and 10 mg/kg/day (males) or 1, 2, and 5 mg/kg/day (females). These doses are equivalent to approximately 0.1 to 1 times the highest recommended clinical daily dose of 40 mg based on surface area, mg/m 2 . The relevance of this finding to humans is unknown.
Parafollicular cell (thyroid) adenomas were increased in high-dose male rats (p=0.003) in a 2-year oral carcinogenicity study at doses of 1 and 3.75 mg/kg body weight. These doses are equivalent to approximately 0.3 and 1 times the 40 mg clinical daily dose based on surface area, mg/m 2 . The relevance of this finding to humans is unknown.
Alendronate was not genotoxic in the in vitro microbial mutagenesis assay with and without metabolic activation, in an in vitro mammalian cell mutagenesis assay, in an in vitro alkaline elution assay in rat hepatocytes, and in an in vivo chromosomal aberration assay in mice. In an in vitro chromosomal aberration assay in Chinese hamster ovary cells, however, alendronate gave equivocal results. Alendronate had no effect on fertility (male or female) in rats at oral doses up to 5 mg/kg/day (approximately 1 times the 40 mg clinical daily dose based on surface area, mg/m 2 ).
📄 Recent Major Changes ▾
Warnings and Precautions, Atypical Fractures Including Femoral Fractures ( 5.5 ) 2/2026
📄 Package Label / Principal Display Panel ▾
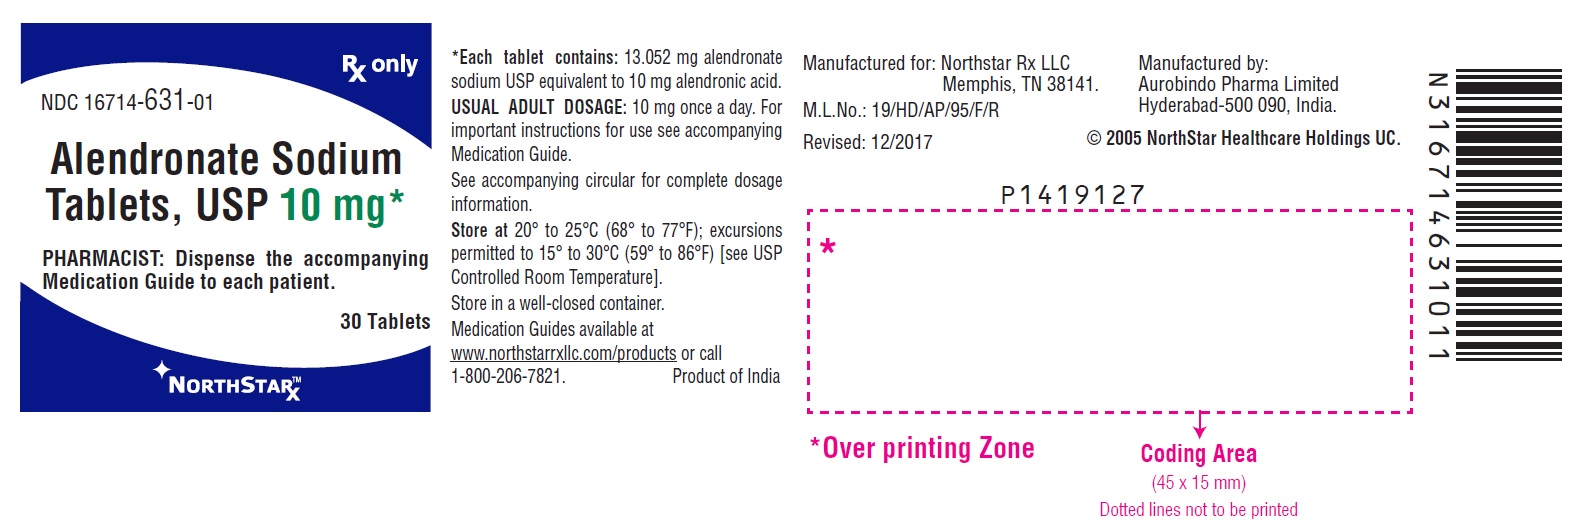
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 10 mg (30 Tablets Bottle) Rx only NDC 16714-631-01 Alendronate Sodium Tablets, USP 10 mg* PHARMACIST: Dispense the accompanying Medication Guide to each patient. 30 Tablets Northstar Rx TM PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 10 mg (30 Tablets Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 10 mg Blister Carton (10 x 10 Unit-dose) Rx only NDC 16714-631-11 Alendronate Sodium Tablets, USP 10 mg* PHARMACIST: Dispense the accompanying Medication Guide to each patient. 100 (10 x 10) Unit-dose Tablets Northstar Rx TM PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 10 mg Blister Carton (10 x 10 Unit-dose)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 35 mg Blister Carton (5 Blister of 4 Tablets each) Rx only NDC 16714-632-02 ONCE WEEKLY Alendronate Sodium Tablets, USP 35 mg* PHARMACIST: Dispense the accompanying Medication Guide to each patient. 20 Tablets (5 Blisters of 4 Tablets each) Northstar Rx TM PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 35 mg Blister Carton (5 Blister of 4 Tablets each)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 70 mg Blister Carton (5 Blister of 4 Tabletseach) Rx only NDC 16714-633-02 ONCE WEEKLY Alendronate Sodium Tablets, USP 70 mg* PHARMACIST: Dispense the accompanying Medication Guide to each patient. 20 Tablets (5 Blisters of 4 Tablets each) Northstar Rx TM PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 70 mg Blister Carton (5 Blister of 4 Tablets each)