
Ezetimibe 10 mg Tablet, 500-count — NDC 16729-433-16 (Billing 16729-0433-16)
This is a package of 500 tablets of Ezetimibe 10 mg Tablet from Accord Healthcare Inc., no longer marketed (first marketed Oct 2019), no longer in the FDA NDC Directory; retail pharmacies pay about $0.0844 per tablet (NADAC).
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 051214
- GCN: 18387
- GPI-14 (Medi-Span): 39300030000320
- HICL (First Databank): 024459
- AHFS class code: 24:06.05.00
- RxCUI (RxNorm): 349556
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Dietary Cholesterol Absorption Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Great question. Ezetimibe works in your intestine — it blocks a protein that absorbs cholesterol from your food and bile, so less cholesterol gets into your bloodstream. Statins, o...
- What exactly does ezetimibe do, and how is it different from a statin?
- You can take it at whatever time of day works best for you — morning, evening, whatever you'll remember. Food doesn't affect how well it's absorbed, so with or without a meal is fi...
- Can I take ezetimibe at any time of day, and does it matter if I eat first?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Ezetimibe — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.084 | $42.20 / 500 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.4563 | $228.15 / 500 tablets |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file · file of Feb 21, 2024
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q4 2025
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 16729-0433-10 16729-433-10 Main listing | 30 TABLET in 1 BOTTLE | $0.0715 / ea | $2.14 | 2019-11-01 | — | Active |
| 16729-0433-15 16729-433-15 | 90 TABLET in 1 BOTTLE | $0.0844 / ea | $7.60 | 2019-10-07 | — | Discontinued by firm |
| 16729-0433-16 You're viewing this | 500 TABLET in 1 BOTTLE | $0.0844 / ea | $42.22 | 2019-10-17 | — | Discontinued by firm |
You're viewing the largest of 3 pack sizes for this product.
Per ea, this pack runs about 18% above the cheapest pack (30-count, $0.0715 vs $0.0844 NADAC).
This pack shows little to no recent Medicaid volume — the 30 tablets pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 16729-0433-10?
What NDC number is used to bill for this package of Ezetimibe 10 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ezetimibe 10 mg 00904-7103-04 | Major | 30 tablets | $0.067 | AB | Availability likely | save 21% |
| Ezetimibe 10 mg 16714-0813-01 | NorthStar | 30 tablets | $0.067 | AB | Availability likely | save 21% |
| Ezetimibe 10 mg 50228-0379-05 | ScieGen | 500 tablets | $0.067 | AB | Availability likely | save 21% |
| Ezetimibe 10 mg 50268-0298-12 | AvPAK | 20 tablets | $0.067 | AB | Availability likely | save 21% |
| Ezetimibe 10 mg 51660-0200-05 | Ohm | 500 tablets | $0.067 | AB | Availability likely | save 21% |
| Ezetimibe 10 mg 59651-0052-05 | Aurobindo | 500 tablets | $0.067 | AB | Availability likely | save 21% |
| Ezetimibe 10 mg 60687-0373-21 | American | 30 tablets | $0.067 | AB | Availability likely | save 21% |
| Ezetimibe 10 mg 68462-0226-05 | Glenmark | 500 tablets | $0.067 | AB | Availability likely | save 21% |
| ezetimibe 10 mg 82009-0024-05 | Quallent | 500 tablets | $0.067 | AB | Availability likely | save 21% |
| Ezetimibe 10 mg 00591-3713-05 | Actavis | 500 tablets | $0.067 | AB | Discontinued | save 20% |
| Ezetimibe 10 mg 00781-5690-05 | Sandoz | 500 tablets | $0.084 | AB | Discontinued | — |
| Ezetimibe 10 mgthis 16729-0433-16 | Accord | 500 tablets | $0.084 | AB | Discontinued | — |
| Zetia 10 mg 78206-0178-01 | Organon | 30 tablets | $13.937 | AB | Availability likely | +16405% |
| Ezetimibe 10 mg 10135-0787-05 | Marlex | 500 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 31722-0628-01 | Camber | 100 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 33342-0373-07 | Macleods | 30 tablets | — | — | FDA listed | — |
| Ezetimibe 10 mg 50090-3422-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 50090-3657-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 50090-6630-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 50090-6631-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 50090-7099-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 50090-7236-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 50090-7338-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 50090-7339-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 50090-7689-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 50090-7690-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 60429-0982-05 | Golden | 500 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 63629-7413-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 67877-0490-01 | Ascend | 100 tablets | — | AB | FDA listed | — |
| ezetimibe 10 mg 68382-0773-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 69238-1154-01 | Amneal | 1000 tablets | — | AB | FDA listed | — |
| ezetimibe 10 mg 70771-1109-00 | Zydus | 1000 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 71205-0145-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 71205-0277-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 71335-0684-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 71335-0933-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 71335-1127-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 71335-2123-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 71335-3092-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 76333-0170-15 | Orient | 30 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 82804-0064-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Ezetimibe 10 mg 82804-0211-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| ezetimibe 10 mg 48433-0161-03 | Safecor | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Feb 21, 2024
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Ezetimibe tablets are indicated: In combination with a statin, or alone when additional low-density lipoprotein cholesterol (LDL-C) lowering therapy is not possible, as an adjunct to diet to reduce elevated LDL-C in adults with primary hyperlipidemia, including heterozygous familial hypercholesterolemia (HeFH). In combination with a statin as an adjunct to diet to reduce elevated LDL-C in pediatric patients 10 years of age and older with HeFH. In combination with fenofibrate as an adjunct to diet to reduce elevated LDL-C in adults with mixed hyperlipidemia.
In combination with a statin, and other LDL-C lowering therapies, to reduce elevated LDL-C levels in adults and in pediatric patients 10 years of age and older with homozygous familial hypercholesterolemia (HoFH). As an adjunct to diet for the reduction of elevated sitosterol and campesterol levels in adults and in pediatric patients 9 years of age and older with homozygous familial sitosterolemia. When ezetimibe tablets are used in combination with a statin, fenofibrate, or other LDL-C lowering therapies, refer to the Prescribing Information of these products for information on the safe and effective use.
Ezetimibe tablets are indicated ( 1 ): In combination with a statin, or alone when additional low density lipoprotein cholesterol (LDL-C) lowering therapy is not possible, as an adjunct to diet to reduce elevated LDL-C in adults with primary hyperlipidemia, including heterozygous familial hypercholesterolemia (HeFH). In combination with a statin as an adjunct to diet to reduce elevated LDL-C in pediatric patients 10 years of age and older with HeFH. In combination with fenofibrate as an adjunct to diet to reduce elevated LDL-C in adults with mixed hyperlipidemia.
In combination with a statin, and other LDL-C lowering therapies, to reduce elevated LDL-C levels in adults and in pediatric patients 10 years of age and older with homozygous familial hypercholesterolemia (HoFH). As an adjunct to diet for the reduction of elevated sitosterol and campesterol levels in adults and in pediatric patients 9 years of age and older with homozygous familial sitosterolemia. When ezetimibe tablets are used in combination with a statin, fenofibrate, or other LDL-C lowering therapies, refer to the Prescribing Information of these products for information on the safe and effective use ( 1 ).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended dose of ezetimibe tablets is 10 mg orally once daily, administered with or without food. If as dose is missed, take the missed dose as soon as possible. Do not double the next dose.
Assess LDL-C when clinically appropriate, as early as 4 weeks after initiating ezetimibe tablets. Administer ezetimibe tablets at least 2 hours before or 4 hours after administration of a bile acid sequestrant [ see Drug Interactions (7) ]. 10-mg orally once daily, with or without food ( 2 ) Administer ezetimibe tablets either ≥2 hours before or ≥4 hours after administration of a bile acid sequestrant.
( 2 ) Assess LDL-C when clinically appropriate, as early as 4 weeks after initiating ezetimibe tablets. ( 2 )
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Ezetimibe tablets, USP 10 mg are white to off white, capsule shaped, flat faced with beveled edge, uncoated tablets, debossed with "10" on one side and plain on other side. Tablets: 10 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Ezetimibe tablets are contraindicated in patients with a known hypersensitivity to ezetimibe or any of the excipients in ezetimibe tablets. Hypersensitivity reactions including anaphylaxis, angioedema, rash, and urticaria have been reported [see Adverse Reactions ( 6.2 )]. When used in combination with a statin, fenofibrate, or other LDL-C lowering therapy, ezetimibe tablets are contraindicated in patients for whom a statin, fenofibrate, or other LDL-C lowering therapy are contraindicated.
Refer to the Prescribing Information of these products for a list of their contraindications [see Warnings and Precautions ( 5.1 )]. Hypersensitivity to ezetimibe or any excipient of ezetimibe tablets. ( 4 ) When used in combination with a statin, fenofibrate, or other LDL-C lowering therapy, ezetimibe tablets are contraindicated in patients for whom a statin, fenofibrate, or other LDL-C lowering therapy are contraindicated.
Refer to the Prescribing Information of these products for a list of their contraindications. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Risks Associated with Combination Treatment with a Statin, Fenofibrate, or Other LDL-C Lowering Therapies: Refer to the Prescribing Information of these products for a description of their risks including, but not limited to, the warnings and precautions. ( 5.1 ) Liver Enzyme Abnormalities and Monitoring: Increases in serum transaminases have been reported with use of ezetimibe. Perform liver enzyme testing as clinically indicated and consider withdrawal of ezetimibe if increases in ALT or AST ≥3 X ULN persist.
( 5.2 ) Skeletal Muscle Effects (e.g., Myopathy and Rhabdomyolysis): Ezetimibe may cause myopathy and rhabdomyolysis. In post-marketing reports, most patients who developed rhabdomyolysis were taking a statin or other agents known to be associated with an increased risk of rhabdomyolysis, such as fibrates. If myopathy is suspected, discontinue ezetimibe and other concomitant medications, as appropriate.
( 5.3 )
5.1Risks Associated with Combination Treatment with a Statin, Fenofibrate, or Other LDL-C Lowering Therapies If ezetimibe is administered with a statin, fenofibrate, or other LDL-C lowering therapies, refer to the Prescribing Information of these products for a description of their risks including, but not limited to, the warnings and precautions [see Contraindications ( 4 )].
5.2Liver Enzymes Increases in serum transaminases have been reported with use of ezetimibe [see Adverse Reactions ( 6.1 )]. In controlled clinical combination studies of ezetimibe initiated concurrently with a statin, the incidence of consecutive elevations (≥3 X ULN) in hepatic transaminase levels was 1.3% for patients treated with ezetimibe administered with statins and 0.4% for patients treated with statins alone. Perform liver enzyme testing as clinically indicated and consider withdrawal of ezetimibe if increases in ALT or AST ≥3 X ULN persist.
5.3Myopathy/Rhabdomyolysis Ezetimibe may cause myopathy [muscle pain, tenderness, or weakness associated with elevated creatine kinase (CK)] and rhabdomyolysis [see Adverse Reactions ( 6.1 )]. In post-marketing reports, most patients who developed rhabdomyolysis were taking a statin or other agents known to be associated with an increased risk of rhabdomyolysis, such as fibrates. If myopathy is suspected, discontinue ezetimibe and other concomitant medications, as appropriate.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed in greater detail in other sections of the label: Liver enzyme abnormalities [see Warnings and Precautions (5.2) ] Rhabdomyolysis and myopathy [see Warnings and Precautions (5.3) ] Common adverse reactions in clinical trials: Ezetimibe administered alone (incidence ≥2% and greater than placebo): upper respiratory tract infection, diarrhea, arthralgia, sinusitis, pain in extremity, fatigue, and influenza. ( 6.1 ) Ezetimibe coadministered with a statin (incidence ≥2% and greater than statin alone): nasopharyngitis, myalgia, upper respiratory tract infection, arthralgia, diarrhea, back pain, influenza, pain in extremity, and fatigue.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Accord Healthcare Inc. at 1-866-941-7875 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in clinical practice. Monotherapy In 10 double-blind, placebo-controlled clinical trials, 2,396 patients with primary hyperlipidemia (age range 9 to 86 years; 50% female, 90% White, 5% Black or African American, 2% Asian, 3% other races; 3% identified as Hispanic or Latino ethnicity) and elevated LDL-C were treated with ezetimibe 10 mg daily for a median treatment duration of 12 weeks (range 0 to 39 weeks).
Adverse reactions reported in ≥2% of patients treated with ezetimibe and at an incidence greater than placebo in placebo-controlled studies of ezetimibe are shown in Table 1 . TABLE 1: Adverse Reactions Occurring ≥2% and Greater than Placebo in Ezetimibe-treated Patients Adverse Reaction Placebo (%) n = 1,159 Ezetimibe 10 mg (%) n = 2,396 Upper respiratory tract infection 2.5
4.3Diarrhea 3.7
4.1Arthralgia 2.2
3.0Sinusitis 2.2
2.8Pain in extremity 2.5
2.7Fatigue 1.5
2.4Influenza 1.5
2.0Combination with a Statin In 28 double-blind, controlled (placebo or active-controlled) clinical trials, 11,308 patients with primary hyperlipidemia (age range 10 to 93 years, 48% female, 85% White, 7% Black or African American, 3% Asian, 5% other races; 4% identified as Hispanic or Latino ethnicity) and elevated LDL-C were treated with ezetimibe 10 mg/day concurrently with or added to on-going statin therapy for a median treatment duration of 8 weeks (range 0 to 112 weeks). The incidence of consecutive increased transaminases (≥3 X ULN) was higher in patients receiving ezetimibe administered with statins (1.3%) than in patients treated with statins alone (0.4%).
Adverse reactions reported in ≥2% of patients treated with ezetimibe + statin and at an incidence greater than statin are shown in Table 2. TABLE 2: Adverse Reactions Occurring ≥2% in Ezetimibe-treated Patients Coadministered with a Statin and at an Incidence Greater than Statin Adverse Reaction All Statins* (%) n = 9,361 Ezetimibe + All Statins* (%) n = 11,308 Nasopharyngitis 3.3
3.7Myalgia 2.7
3.2Upper respiratory tract infection 2.8
2.9Arthralgia 2.4
2.6Diarrhea 2.2
2.5Back pain 2.3
2.4Influenza 2.1
2.2Pain in extremity 1.9
2.1Fatigue 1.6 2.0 * All Statins = all doses of all statins Combination with Fenofibrate This clinical trial involving 625 patients with mixed dyslipidemia (age range 20 to 76 years; 44% female, 79% White, 1% Black or African American, 20% other races; 11% identified as Hispanic or Latino ethnicity) treated for up to 12 weeks and 576 patients treated for up to an additional 48 weeks evaluated coadministration of ezetimibe and fenofibrate. Incidence rates for clinically important elevations (≥3 X ULN, consecutive) in hepatic transaminase levels were 4.5% and 2.7% for fenofibrate monotherapy (n=188) and ezetimibe coadministered with fenofibrate (n=183), respectively, adjusted for treatment exposure.
Corresponding incidence rat… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 3 includes a list of drugs with clinically important drug interactions when administered concomitantly with ezetimibe and instructions for preventing or managing them. Table 3: Clinically Important Drug Interactions with Ezetimibe Cyclosporine Clinical Impact Concomitant use of ezetimibe and cyclosporine increases ezetimibe and cyclosporine concentrations. The degree of increase in ezetimibe exposure may be greater in patients with severe renal insufficiency [see Clinical Pharmacology(12.3) ].
Intervention Monitor cyclosporine concentrations in patients receiving ezetimibe and cyclosporine. In patients treated with cyclosporine, weigh the potential effects of the increased exposure to ezetimibe from concomitant use against the benefits of alterations in lipid levels provided by ezetimibe. Fibrates Clinical Impact Both fenofibrate and ezetimibe may increase cholesterol excretion into the bile, leading to cholelithiasis.
Co-administration of ezetimibe with fibrates other than fenofibrate is not recommended [see Adverse Reactions (6.1) ]. Intervention If cholelithiasis is suspected in a patient receiving ezetimibe and fenofibrate, gallbladder studies are indicated, and alternative lipid-lowering therapy should be considered. Bile Acid Sequestrants Clinical Impact Concomitant cholestyramine administration decreased the mean exposure of total ezetimibe.
This may result in a reduction of efficacy [see Clinical Pharmacology (12.3) ]. Intervention In patients taking a bile acid sequestrant, administer ezetimibe at least 2 hours before or 4 hours after the bile acid sequestrant [see Dosage and Administration (2) ]. Cyclosporine: Combination increases exposure of ezetimibe and cyclosporine.
Cyclosporine concentrations should be monitored in patients taking ezetimibe concomitantly. (7) Fibrates: Coadministration of ezetimibe with fibrates other than fenofibrate is not recommended until use in patients is adequately studied. If cholelithiasis is suspected in a patient receiving ezetimibe and fenofibrate, gallbladder studies are indicated, and alternative lipid-lowering therapy should be considered.
(7) Bile Acid Sequestrants: Cholestyramine combination decreases exposure of ezetimibe. (7)
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are insufficient data on ezetimibe use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. In animal reproduction studies, no adverse developmental effects were observed in pregnant rats and rabbits orally administered ezetimibe during the period of organogenesis at doses that resulted in up to 10 and 150 times, respectively, the human exposure at the MRHD, based on AUC (see Data). Ezetimibe should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
When ezetimibe is administered with a statin, refer to the Prescribing Information for the statin. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data In oral (gavage) embryo-fetal development studies of ezetimibe conducted in rats (gestation days 6 to 15) and rabbits (gestation days 7 to 19), there was no evidence of maternal toxicity or embryolethal effects at the doses tested (250, 500, 1,000 mg/kg/day). In rats, increased incidences of common fetal skeletal findings (extra pair of thoracic ribs, unossified cervical vertebral centra, shortened ribs) were observed at 1,000 mg/kg/day (~10 times the human exposure at 10 mg daily based on AUC 0-24hr for total ezetimibe).
In rabbits treated with ezetimibe, an increased incidence of extra thoracic ribs was observed at 1,000 mg/kg/day (150 times the human exposure at 10 mg daily based on AUC 0-24hr for total ezetimibe). The animal-to-human exposure multiple for total ezetimibe at the no-observed effect level was 6 times for rat and 134 times for rabbit. Fetal exposure to ezetimibe (conjugated and unconjugated) was confirmed in subsequent placental transfer studies conducted using a maternal dose of 1,000 mg/kg/day.
The fetal maternal plasma exposure ratio (total ezetimibe) was 1.5 for rats on gestation day 20 and 0.03 for rabbits on gestation day 22. The effect of ezetimibe on prenatal and postnatal development and maternal function was evaluated in pregnant rats at doses of 100, 300 or 1,000 mg/kg/day from gestation day 6 through lactation day 21. No maternal toxicity or adverse developmental outcomes were observed up to and including the highest dose tested (17 times the human exposure at 10 mg daily based on AUC 0-24hr for total ezetimibe).
Multiple-dose studies of ezetimibe given in combination with statins in rats and rabbits during organogenesis resulted in higher ezetimibe and statin exposures. Reproductive findings occurred at lower doses in combination therapy compared to monotherapy.
8.2Lactation Risk Summary There is no information about the presence of ezetimibe in human milk. Ezetimibe is present in rat milk (see Data). When a drug is present in animal milk, it is likely that the drug will be present in human milk.
There is no information about the effects of ezetimibe on the breastfed infant or the effects of ezetimibe on milk production. Ezetimibe should not be used in nursing mothers unless the potential benefit justifies the potential risk to the infant. Data Ezetimibe was present in the milk of lactating rats.
The pup to maternal plasma ratio for total ezetimibe was 0.5 on lactation day 12.
8.4Pediatric Use The safety and effectiveness of ezetimibe in combination with a statin as an adjunct to diet to reduce LDL-C have been established in pediatric patients 10 years of age and older with HeFH. Use of ezetimibe for this indication is based on a double-blind, placebo-controlled clinical trial in 248 pediatric patients (142 males and 106 postmenarchal females) 10 years of age and older with HeFH [see Clinical Studies (14) ]. In this limited controlled trial, there was no significant effect on gro… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are insufficient data on ezetimibe use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. In animal reproduction studies, no adverse developmental effects were observed in pregnant rats and rabbits orally administered ezetimibe during the period of organogenesis at doses that resulted in up to 10 and 150 times, respectively, the human exposure at the MRHD, based on AUC (see Data). Ezetimibe should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
When ezetimibe is administered with a statin, refer to the Prescribing Information for the statin. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data In oral (gavage) embryo-fetal development studies of ezetimibe conducted in rats (gestation days 6 to 15) and rabbits (gestation days 7 to 19), there was no evidence of maternal toxicity or embryolethal effects at the doses tested (250, 500, 1,000 mg/kg/day). In rats, increased incidences of common fetal skeletal findings (extra pair of thoracic ribs, unossified cervical vertebral centra, shortened ribs) were observed at 1,000 mg/kg/day (~10 times the human exposure at 10 mg daily based on AUC 0-24hr for total ezetimibe).
In rabbits treated with ezetimibe, an increased incidence of extra thoracic ribs was observed at 1,000 mg/kg/day (150 times the human exposure at 10 mg daily based on AUC 0-24hr for total ezetimibe). The animal-to-human exposure multiple for total ezetimibe at the no-observed effect level was 6 times for rat and 134 times for rabbit. Fetal exposure to ezetimibe (conjugated and unconjugated) was confirmed in subsequent placental transfer studies conducted using a maternal dose of 1,000 mg/kg/day.
The fetal maternal plasma exposure ratio (total ezetimibe) was 1.5 for rats on gestation day 20 and 0.03 for rabbits on gestation day 22. The effect of ezetimibe on prenatal and postnatal development and maternal function was evaluated in pregnant rats at doses of 100, 300 or 1,000 mg/kg/day from gestation day 6 through lactation day 21. No maternal toxicity or adverse developmental outcomes were observed up to and including the highest dose tested (17 times the human exposure at 10 mg daily based on AUC 0-24hr for total ezetimibe).
Multiple-dose studies of ezetimibe given in combination with statins in rats and rabbits during organogenesis resulted in higher ezetimibe and statin exposures. Reproductive findings occurred at lower doses in combination therapy compared to monotherapy.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of ezetimibe in combination with a statin as an adjunct to diet to reduce LDL-C have been established in pediatric patients 10 years of age and older with HeFH. Use of ezetimibe for this indication is based on a double-blind, placebo-controlled clinical trial in 248 pediatric patients (142 males and 106 postmenarchal females) 10 years of age and older with HeFH [see Clinical Studies (14) ]. In this limited controlled trial, there was no significant effect on growth or sexual maturation in the adolescent males or females, or on menstrual cycle length in females.
The safety and effectiveness of ezetimibe in combination with a statin, and other LDL-C lowering therapies, to reduce LDL-C have been established in pediatric patients 10 years of age and older with HoFH. Use of ezetimibe for this indication is based on a 12-week double-blind, placebo-controlled clinical trial followed by an uncontrolled extension period in 7 pediatric patients 11 years of age and older with HoFH [see Clinical Studies (14) ]. The safety and effectiveness of ezetimibe as an adjunct to diet for the reduction of elevated sitosterol and campesterol levels have been established in adults and pediatric patients 9 years of age and older with homozygous familial sitosterolemia.
Use of ezetimibe for this indication is based on an 8-week double-blind, placebo-controlled clinical trial in 4 patients 9 years of age and older with homozygous sitosterolemia with elevated plasma sitosterol levels (>5 mg/dL) [see Clinical Studies (14) ]. The safety and effectiveness of ezetimibe have not been established in pediatric patients younger than 10 years of age with HeFH or HoFH, in pediatric patients younger than 9 years of age with homozygous familial sitosterolemia, or in pediatric patients with other types of hyperlipidemia.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 2,396 patients who received ezetimibe in clinical trials, 669 (28%) were 65 years of age and older, and 111 (5%) were 75 years of age and older. Of the 11,308 patients who received ezetimibe in combination with a statin in clinical trials, 3587 (32%) were 65 years of age and older, and 924 (8%) were 75 years of age and older [see Clinical Studies (14) ]. No overall differences in safety or effectiveness of ezetimibe have been observed between patients 65 years of age and older and younger patients.
No clinically meaningful differences in the pharmacokinetics of ezetimibe were observed in geriatric patients compared to younger adult patients [see Clinical Pharmacology (12.3) ] .
🆘 Overdosage ▾
10 OVERDOSAGE In the event of overdose, consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdosage management recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Ezetimibe reduces blood cholesterol by inhibiting the absorption of cholesterol by the small intestine. The molecular target of ezetimibe has been shown to be the sterol transporter, Niemann-Pick C1-Like 1 (NPC1L1), which is involved in the intestinal uptake of cholesterol and phytosterols. Ezetimibe localizes at the brush border of the small intestine and inhibits the absorption of cholesterol, leading to a decrease in the delivery of intestinal cholesterol to the liver.
This causes a reduction of hepatic cholesterol stores and an increase in LDL receptors, resulting in clearance of cholesterol from the blood.
12.2Pharmacodynamics Ezetimibe reduces total cholesterol (total-C), LDL-C, apolipoprotein (Apo) B, and non-high-density lipoprotein cholesterol (non-HDL-C) in patients with hyperlipidemia. In a 2-week clinical trial in 18 hypercholesterolemic patients, ezetimibe inhibited intestinal cholesterol absorption by 54%, compared with placebo. Ezetimibe had no clinically meaningful effect on the plasma concentrations of the fat-soluble vitamins A, D, and E (in a trial of 113 patients) and did not impair adrenocortical steroid hormone production (in a trial of 118 patients).
12.3Pharmacokinetics Absorption After oral administration, ezetimibe is absorbed and extensively conjugated to a pharmacologically active phenolic glucuronide (ezetimibe-glucuronide). After a single 10-mg dose of ezetimibe to fasted adults, mean ezetimibe peak plasma concentrations (C max ) of 3.4 to 5.5 ng/mL were attained within 4 to 12 hours (T max ). Ezetimibe-glucuronide mean C max values of 45 to 71 ng/mL were achieved between 1 and 2 hours (T max ).
There was no substantial deviation from dose proportionality between 5 and 20 mg. The absolute bioavailability of ezetimibe cannot be determined, as the compound is virtually insoluble in aqueous media suitable for injection. Effect of Food Concomitant food administration (high-fat or non-fat meals) had no effect on the extent of absorption of ezetimibe when administered as ezetimibe 10-mg tablets.
The C max value of ezetimibe was increased by 38% with consumption of high-fat meals. Distribution Ezetimibe and ezetimibe-glucuronide are highly bound (>90%) to human plasma proteins. Elimination Metabolism Ezetimibe is primarily metabolized in the small intestine and liver via glucuronide conjugation (a phase II reaction) with subsequent biliary and renal excretion.
Minimal oxidative metabolism (a phase I reaction) has been observed in all species evaluated. In humans, ezetimibe is rapidly metabolized to ezetimibe-glucuronide. Ezetimibe and ezetimibe-glucuronide are the major drug-derived compounds detected in plasma, constituting approximately 10 to 20% and 80 to 90% of the total drug in plasma, respectively.
Both ezetimibe and ezetimibe-glucuronide are eliminated from plasma with a half-life of approximately 22 hours for both ezetimibe and ezetimibe-glucuronide. Plasma concentration-time profiles exhibit multiple peaks, suggesting enterohepatic recycling. Excretion Following oral administration of 14 C-ezetimibe (20 mg) to human subjects, total ezetimibe (ezetimibe + ezetimibe-glucuronide) accounted for approximately 93% of the total radioactivity in plasma.
After 48 hours, there were no detectable levels of radioactivity in the plasma. Approximately 78% and 11% of the administered radioactivity were recovered in the feces and urine, respectively, over a 10-day collection period. Ezetimibe was the major component in feces and accounted for 69% of the administered dose, while ezetimibe-glucuronide was the major component in urine and accounted for 9% of the administered dose.
Specific Populations Geriatric Patients In a multiple-dose trial with ezetimibe given 10 mg once daily for 10 days, plasma concentrations for total ezetimibe were about 2-fold higher in older (≥65 years) healthy subjects compared to younger subjects. However, the difference in plasma co… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Ezetimibe reduces blood cholesterol by inhibiting the absorption of cholesterol by the small intestine. The molecular target of ezetimibe has been shown to be the sterol transporter, Niemann-Pick C1-Like 1 (NPC1L1), which is involved in the intestinal uptake of cholesterol and phytosterols. Ezetimibe localizes at the brush border of the small intestine and inhibits the absorption of cholesterol, leading to a decrease in the delivery of intestinal cholesterol to the liver.
This causes a reduction of hepatic cholesterol stores and an increase in LDL receptors, resulting in clearance of cholesterol from the blood.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Ezetimibe tablets, USP 10 mg are white to off white, capsule shaped, flat faced with beveled edge, uncoated tablets, debossed with "10" on one side and plain on other side and are supplied as follows: Package Size NDC Bottle of 30 tablets with a child resistant closure 16729-433-10 Bottle of 90 tablets with a child resistant closure 16729-433-15 Bottle of 100 tablets with a child resistant closure 16729-433-01 Bottle of 500 tablets 16729-433-16 Bottle of 1,000 tablets 16729-433-17 Store ezetimibe tablets at 25°C (77°F); excursions permitted to 15 to 30°C (59 to 86°F). [See USP Controlled Room Temperature.] Protect from moisture
📦 Storage and Handling ▾
Store ezetimibe tablets at 25°C (77°F); excursions permitted to 15 to 30°C (59 to 86°F). [See USP Controlled Room Temperature.] Protect from moisture
📋 Description ▾
11 DESCRIPTION Ezetimibe is a dietary cholesterol absorption inhibitor. The chemical name of ezetimibe is 1-(4- fluorophenyl)-3(R)-[3-(4-fluorophenyl)-3(S)-hydroxypropyl]-4(S)-(4-hydroxyphenyl)-2-azetidinone. The empirical formula is C 24 H 21 F 2 NO 3 .
Its molecular weight is 409.4 and its structural formula is: Ezetimibe is a white, crystalline powder that is freely to very soluble in ethanol, methanol, and acetone and practically insoluble in water. Ezetimibe has a melting point of about 163°C and is stable at ambient temperature. Ezetimibe tablets, USP are available as a tablet for oral administration containing 10 mg of ezetimibe and the following inactive ingredients: croscarmellose sodium, lactose monohydrate, magnesium stearate, povidone K-30, polysorbate 80 and sodium lauryl sulfate. image of ezetimibe chemical structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-Approved Patient Labeling (Patient Information). Inform patients that ezetimibe tablets may cause liver enzyme elevations [ see Warnings and Precautions (5.2) ]. Muscle Pain Advise patients that ezetimibe tablets may cause myopathy and rhabdomyolysis.
Inform patients that the risk is also increased when taking certain types of medication and they should discuss all medication, both prescription and over the counter, with their healthcare provider. Instruct patients to promptly report any unexplained muscle pain, tenderness or weakness particularly if accompanied by malaise or fever [ see Warnings and Precautions (5.3), and Drug Interactions (7) ]. Pregnancy Advise patients to inform their healthcare provider of a known or suspected pregnancy to discuss if ezetimibe tablets should be discontinued [ see Use in Specific Populations (8.1) ].
Breastfeeding Advise patients who have a lipid disorder and are breastfeeding to discuss the options with their healthcare provider [ see Use in Specific Populations (8.2) ]. Missed Dose Instruct patients to take ezetimibe tablets only as prescribed. If a dose is missed, it should be taken as soon as possible.
Advise patients not to double their next dose. Manufactured For: Accord Healthcare, Inc., 8041 Arco Corporate Drive, Suite 200, Raleigh, NC 27617, USA. Manufactured By: Intas Pharmaceuticals Limited, Plot No. : 457, 458, Village - Matoda, Bavla Road, Ta. - Sanand, Dist. - Ahmedabad - 382 210, INDIA.
10 2599 2 6030239 Issued April 2024
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption After oral administration, ezetimibe is absorbed and extensively conjugated to a pharmacologically active phenolic glucuronide (ezetimibe-glucuronide). After a single 10-mg dose of ezetimibe to fasted adults, mean ezetimibe peak plasma concentrations (C max ) of 3.4 to 5.5 ng/mL were attained within 4 to 12 hours (T max ). Ezetimibe-glucuronide mean C max values of 45 to 71 ng/mL were achieved between 1 and 2 hours (T max ).
There was no substantial deviation from dose proportionality between 5 and 20 mg. The absolute bioavailability of ezetimibe cannot be determined, as the compound is virtually insoluble in aqueous media suitable for injection. Effect of Food Concomitant food administration (high-fat or non-fat meals) had no effect on the extent of absorption of ezetimibe when administered as ezetimibe 10-mg tablets.
The C max value of ezetimibe was increased by 38% with consumption of high-fat meals. Distribution Ezetimibe and ezetimibe-glucuronide are highly bound (>90%) to human plasma proteins. Elimination Metabolism Ezetimibe is primarily metabolized in the small intestine and liver via glucuronide conjugation (a phase II reaction) with subsequent biliary and renal excretion.
Minimal oxidative metabolism (a phase I reaction) has been observed in all species evaluated. In humans, ezetimibe is rapidly metabolized to ezetimibe-glucuronide. Ezetimibe and ezetimibe-glucuronide are the major drug-derived compounds detected in plasma, constituting approximately 10 to 20% and 80 to 90% of the total drug in plasma, respectively.
Both ezetimibe and ezetimibe-glucuronide are eliminated from plasma with a half-life of approximately 22 hours for both ezetimibe and ezetimibe-glucuronide. Plasma concentration-time profiles exhibit multiple peaks, suggesting enterohepatic recycling. Excretion Following oral administration of 14 C-ezetimibe (20 mg) to human subjects, total ezetimibe (ezetimibe + ezetimibe-glucuronide) accounted for approximately 93% of the total radioactivity in plasma.
After 48 hours, there were no detectable levels of radioactivity in the plasma. Approximately 78% and 11% of the administered radioactivity were recovered in the feces and urine, respectively, over a 10-day collection period. Ezetimibe was the major component in feces and accounted for 69% of the administered dose, while ezetimibe-glucuronide was the major component in urine and accounted for 9% of the administered dose.
Specific Populations Geriatric Patients In a multiple-dose trial with ezetimibe given 10 mg once daily for 10 days, plasma concentrations for total ezetimibe were about 2-fold higher in older (≥65 years) healthy subjects compared to younger subjects. However, the difference in plasma concentrations is not clinically meaningful. Gender In a multiple-dose trial with ezetimibe given 10 mg once daily for 10 days, plasma concentrations for total ezetimibe were slightly higher (<20%) in females than in males.
Race Based on a meta-analysis of multiple-dose pharmacokinetic studies, there were no pharmacokinetic differences between Black and White subjects. Studies in Asian subjects indicated that the pharmacokinetics of ezetimibe were similar to those seen in White subjects. Renal Impairment After a single 10-mg dose of ezetimibe in patients with severe renal disease (n=8; mean CrCl ≤30 mL/min/1.73 m 2 ), the mean AUC values for total ezetimibe, ezetimibe-glucuronide, and ezetimibe were increased approximately 1.5-fold, compared to healthy subjects (n=9).
Hepatic Impairment After a single 10-mg dose of ezetimibe, the mean AUC for total ezetimibe was increased approximately 1.7-fold in patients with mild hepatic impairment (Child-Pugh score 5 to 6), compared to healthy subjects. The mean AUC values for total ezetimibe and ezetimibe were increased approximately 3- to 4-fold and 5- to 6-fold, respectively, in patients with moderate (Child-Pugh score 7 to 9) or severe hepatic impairment (Child- Pugh score 10 to 15).… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Ezetimibe reduces total cholesterol (total-C), LDL-C, apolipoprotein (Apo) B, and non-high-density lipoprotein cholesterol (non-HDL-C) in patients with hyperlipidemia. In a 2-week clinical trial in 18 hypercholesterolemic patients, ezetimibe inhibited intestinal cholesterol absorption by 54%, compared with placebo. Ezetimibe had no clinically meaningful effect on the plasma concentrations of the fat-soluble vitamins A, D, and E (in a trial of 113 patients) and did not impair adrenocortical steroid hormone production (in a trial of 118 patients).
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Primary Hyperlipidemia in Adults Ezetimibe reduces total-C, LDL-C, Apo B, and non-HDL-C in patients with hyperlipidemia. Maximal to near maximal response is generally achieved within 2 weeks and maintained during chronic therapy. Monotherapy In two multicenter, double-blind, placebo-controlled, 12-week trials in 1719 patients (age range 18 to 86 years, 52% females; 91% White, 5% Black or African American, 1% Asian, 3% other races mostly identified as Hispanic or Latino ethnicity) with primary hyperlipidemia, ezetimibe significantly lowered total-C, LDL-C, Apo B, and non-HDL-C compared to placebo (see Table 6 ).
Reduction in LDL-C was consistent across age, sex, and baseline LDL-C. TABLE 6: Response to Ezetimibe in Patients with Primary Hyperlipidemia (Mean % Change from Untreated Baseline Baseline- on no lipid-lowering drug. ) Treatment Group N Total-C LDL-C Apo B Non-HDL-C Trial1 ZETIA significantly reduced total-C, LDL-C, Apo B, and non-HDL-C compared to placebo. Placebo 205 +1 +1 -1 +1 Ezetimibe 622 -12 -18 -15 -16 Trial 2 Placebo 226 +1 +1 -1 +2 Ezetimibe 666 -12 -18 -16 -16 Pooled Data (Trials 1 & 2) Placebo 431 0 +1 -2 +1 Ezetimibe 1288 -13 -18 -16 -16 Combination with Statins: Ezetimibe Added to On-going Statin Therapy In a multicenter, double-blind, placebo-controlled, 8-week trial, 769 patients (age range 22 to 85 years, 42% females; 90% White, 6% Black or African American, 1% Asian, 3% other races; and 2% identified as Hispanic or Latino ethnicity) with primary hyperlipidemia, known coronary heart disease or multiple cardiovascular risk factors who were already receiving statin monotherapy but who had not met their NCEP ATP II target LDL-C goal, were randomized to receive either ezetimibe or placebo in addition to their on-going statin.
Ezetimibe, added to on-going statin therapy, significantly lowered total-C, LDL-C, Apo B, and non-HDL-C compared with a statin administered alone (see Table 7 ). LDL-C reductions induced by ezetimibe were generally consistent across all statins. TABLE 7: Response to Addition of Ezetimibe to On-Going Statin Therapy Patients receiving each statin: 40% atorvastatin, 31% simvastatin, 29% others (pravastatin, fluvastatin, cerivastatin, lovastatin). in Patients with Hyperlipidemia (Mean % Change from Treated Baseline Baseline - on a statin alone. ) Treatment (Daily Dose) N Total-C LDL-C Apo B Non-HDL-C On-going Statin + Placebo Ezetimibe + statin significantly reduced total-C, LDL-C, Apo B, and non-HDL-C compared to statin alone.
390 -2 -4 -3 -3 On-going Statin + Ezetimibe 379 -17 -25 -19 -23 Combination with Statins: Ezetimibe Initiated Concurrently with a Statin In four multicenter, double-blind, placebo-controlled, 12-week trials, in 2,382 patients (age range 18 to 87 years, 57% female; 88% White, 5% Black or African American, 2% Asian, 5% other races mostly identified as Hispanic or Latino) with hyperlipidemia, ezetimibe or placebo was administered alone or with various doses of atorvastatin, simvastatin, pravastatin, or lovastatin. When all patients receiving ezetimibe with a statin were compared to all those receiving the corresponding statin alone, ezetimibe significantly lowered total-C, LDL-C, Apo B, and non-HDL-C compared to the statin administered alone.
LDL-C reductions induced by ezetimibe were generally consistent across all statins. (See footnote , Tables 8 to 11. ) TABLE 8: Response to Ezetimibe and Atorvastatin Initiated Concurrently in Patients with Primary Hyperlipidemia (Mean % Change from Untreated Baseline Baseline - on no lipid-lowering drug ) Treatment (Daily Dose) N Total-C LDL-C Apo B Non-HDL-C Placebo 60 +4 +4 +3 +4 Ezetimibe 65 -14 -20 -15 -18 Atorvastatin 10 mg 60 -26 -37 -28 -34 Ezetimibe + Atorvastatin 10 mg 65 -38 -53 -43 -49 Atorvastatin 20 mg 60 -30 -42 -34 -39 Ezetimibe + Atorvastatin 20 mg 62 -39 -54 -44 -50 Atorvastatin 40 mg 66 -32 -45 -37 -41 Ezetimibe + Atorvastatin 40 mg 65 -42 -56 -45 -52 Atorvastatin 80 mg 62 -40 -54 -46 -51 Eze… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility A 104-week dietary carcinogenicity study with ezetimibe was conducted in rats at doses up to 1,500 mg/kg/day (males) and 500 mg/kg/day (females) (~20 X the human exposure at 10 mg daily based on AUC 0–24hr for total ezetimibe). A 104-week dietary carcinogenicity study with ezetimibe was also conducted in mice at doses up to 500 mg/kg/day (>150 X the human exposure at 10 mg daily based on AUC 0–24hr for total ezetimibe). There were no statistically significant increases in tumor incidences in drug-treated rats or mice.
No evidence of mutagenicity was observed in vitro in a microbial mutagenicity (Ames) test with Salmonella typhimurium and Escherichia coli with or without metabolic activation. No evidence of clastogenicity was observed in vitro in a chromosomal aberration assay in human peripheral blood lymphocytes with or without metabolic activation. In addition, there was no evidence of genotoxicity in the in vivo mouse micronucleus test.
In oral (gavage) fertility studies of ezetimibe conducted in rats, there was no evidence of reproductive toxicity at doses up to 1,000 mg/kg/day in male or female rats (~7 X the human exposure at 10 mg daily based on AUC 0–24hr for total ezetimibe).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility A 104-week dietary carcinogenicity study with ezetimibe was conducted in rats at doses up to 1,500 mg/kg/day (males) and 500 mg/kg/day (females) (~20 X the human exposure at 10 mg daily based on AUC 0–24hr for total ezetimibe). A 104-week dietary carcinogenicity study with ezetimibe was also conducted in mice at doses up to 500 mg/kg/day (>150 X the human exposure at 10 mg daily based on AUC 0–24hr for total ezetimibe). There were no statistically significant increases in tumor incidences in drug-treated rats or mice.
No evidence of mutagenicity was observed in vitro in a microbial mutagenicity (Ames) test with Salmonella typhimurium and Escherichia coli with or without metabolic activation. No evidence of clastogenicity was observed in vitro in a chromosomal aberration assay in human peripheral blood lymphocytes with or without metabolic activation. In addition, there was no evidence of genotoxicity in the in vivo mouse micronucleus test.
In oral (gavage) fertility studies of ezetimibe conducted in rats, there was no evidence of reproductive toxicity at doses up to 1,000 mg/kg/day in male or female rats (~7 X the human exposure at 10 mg daily based on AUC 0–24hr for total ezetimibe).
📄 Patient Package Insert ▾
PATIENT INFORMATION Ezetimibe Tablets, for oral use (ĕ-zĕt´-ĕ-mīb) This Patient Information has been approved by the U.S. Food and Drug Administration. Revised: 4/2024 Read this information carefully before you start taking ezetimibe tablets and each time you get more ezetimibe tablets.
There may be new information. This information does not take the place of talking with your doctor about your medical condition or your treatment. If you have any questions about ezetimibe tablets, ask your doctor.
Only your doctor can determine if ezetimibe tablets are right for you. What are Ezetimibe Tablets? Ezetimibe tablets are a medicine used with a cholesterol lowering diet: and with other cholesterol medicines called a statin, or alone (when additional cholesterol lowering treatments are not possible), to lower elevated low-density lipoprotein cholesterol (LDL-C) or bad cholesterol in adults with primary hyperlipidemia (too many fats in your blood), including heterozygous familial hypercholesterolemia (HeFH).
HeFH is an inherited condition that causes high levels of bad cholesterol. and with a statin to lower LDL-C in adults and children 10 years of age and older with HeFH. and with a medicine called fenofibrate to lower elevated LDL-C in adults with mixed hyperlipidemia. to lower elevated sitosterol and campesterol levels in adults and in children 9 years of age and older with homozygous familial sitosterolemia (a rare inherited condition that prevents the body from getting rid of cholesterol from plants). Ezetimibe tablets are also used: with a statin and other cholesterol lowering treatments to lower elevated LDL-C levels in adults and patients 10 years of age and older with homozygous familial hypercholesterolemia (HoFH).
HoFH is an inherited condition that causes high levels of bad cholesterol. The safety and effectiveness of ezetimibe tablets have not been established in children: younger than 10 years of age with HeFH or HoFH. younger than 9 years of age with homozygous familial sitosterolemia. with other types of hyperlipemia. Do not take Ezetimibe Tablets: if you are allergic to ezetimibe or any of the ingredients in ezetimibe tablets.
See the end of this Patient Information leaflet for a complete list of ingredients in ezetimibe tablets. Stop using ezetimibe tablets and get medical help right away if you have symptoms of a serious allergic reaction including: swelling of the face, tongue, or throat difficulty breathing or swallowing fainting or feeling dizzy very fast heartbeat severe skin rash, hives, and itching flu-like symptoms including fever, sore throat, cough, tiredness, and joint pain with certain statins, fenofibrate, or other LDL-C lowering medicines if your healthcare provider has told you not to take them.
Before you take ezetimibe tablets, tell your healthcare provider about all your medical conditions, including if you: have liver problems. Ezetimibe tablets may not be right for you. are pregnant or plan to become pregnant. It is not known if ezetimibe tablets will harm your unborn baby.
You and your healthcare provider should decide if you will take ezetimibe tablets while you are pregnant. are breastfeeding. It is not known if ezetimibe passes into your breast milk. You and your healthcare provider should decide the best way to feed your baby if you take ezetimibe tablets.
Tell your healthcare provider about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements. Talk to your healthcare provider before you start taking any new medicines. Taking ezetimibe tablets with certain other medicines may affect each other causing side effects.
Ezetimibe tablets may affect the way other medicines work, and other medicines may affect how ezetimibe tablets work. Especially tell your healthcare provider if you take: cyclosporine (a medicine for your immune system) fibrates (medicine for lowering cholesterol) bile acid sequestrants (medicine for lowering LDL-C) As… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Indications and Usage ( 1 ) 7/2023 Dosage and Administration ( 2 ) 7/2023 Contraindications( 4 ) 7/2023 Warnings and Precautions ( 5.1 , 5.2 , 5.3 ) 7/2023
📄 Package Label / Principal Display Panel ▾
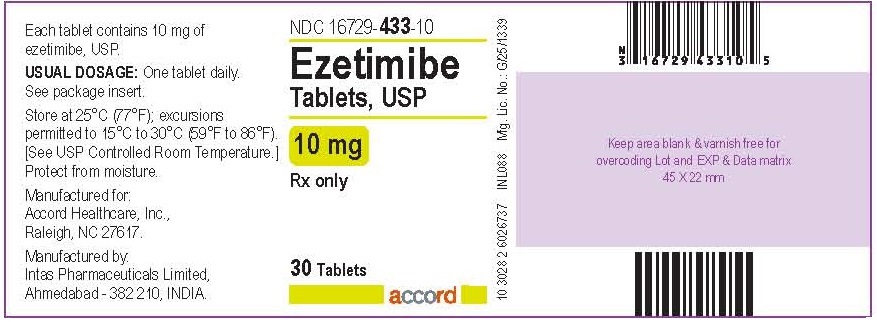
PRINCIPAL DISPLAY PANEL - 30 Tablets Label PRINCIPAL DISPLAY PANEL - 30 tabs Label
Medicaid utilization & spend
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |