
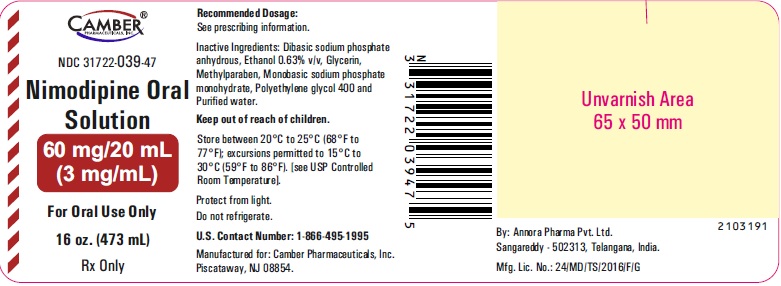
Nimodipine 60 mg/20mL Solution, 473 mL
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Dihydropyridine Calcium Channel Blocker class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Nimodipine is used to decrease brain damage that may be caused by a subarachnoid hemorrhage (bleeding in the space surrounding the brain that occurs when a weakened blood vessel in the brain bursts). Nimodipine is in a class of medications called calcium channel blockers. It works by relaxing blood vessels in the brain to allow more blood to flow to damaged areas.
Read the full MedlinePlus article ↗- Nimodipine is given specifically after a subarachnoid hemorrhage — that's when an aneurysm in the brain ruptures and bleeds into the space around the brain. After that kind of blee...
- What exactly is nimodipine being used for in my (or my family member's) care?
- It's a lot, yes — and there's a real pharmacological reason. Nimodipine is eliminated from the body relatively quickly, so blood levels drop fast between doses. Taking it every 4 h...
- Why does it have to be taken every 4 hours? That's a lot.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Nimodipine — tap one for details:
Nimodipine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII A2I8C7HI9T
Methylparaben is a preservative derived from benzoic acid that prevents growth of bacteria, fungi, and mold in medicines. It extends the product's shelf life and maintains safety during storage.
-
UNII B697894SGQ
Polyethylene glycol 400 is a clear, thick liquid made from petroleum-derived polymers. It acts as a solvent and humectant in medicines, helping dissolve active ingredients and retain moisture in the formulation.
-
UNII 22ADO53M6F
A mineral salt derived from phosphoric acid, used as a buffer to maintain the pH balance of the medication and help stabilize the active ingredients.
-
UNII 593YOG76RN
A salt made from sodium and phosphate that helps regulate acidity and maintain proper pH balance in the medicine. It also acts as a buffer to keep the product stable.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $4.85 | $2,292.44 / 473 ml |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Nimodipine 60 mg/20mLthis 31722-0039-47 | Camber | 473 ml | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 31722-0039-47 You're viewing this | 473 mL in 1 BOTTLE (31722-039-47) | 2024-07-09 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USE Nimodipine oral solution is indicated for the improvement of neurological outcome by reducing the incidence and severity of ischemic deficits in adult patients with subarachnoid hemorrhage (SAH) from ruptured intracranial berry aneurysms regardless of their post-ictus neurological condition (i.e., Hunt and Hess Grades I to V). Nimodipine oral solution is a dihydropyridine calcium channel blocker indicated for the improvement of neurological outcome by reducing the incidence and severity of ischemic deficits in adult patients with subarachnoid hemorrhage (SAH) from ruptured intracranial berry aneurysms regardless of their post-ictus neurological condition (i.e., Hunt and Hess Grades I to V).
(1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Administer only enterally (e.g., oral, nasogastric tube, or gastric tube route). Do not administer intravenously or by other parenteral routes. (2.1) • Give one hour before a meal or two hours after a meal.
(2.1) • Start dosing within 96 hours of the SAH. (2.1) • Recommended dose is 20 mL (60 mg) every 4 hours for 21 consecutive days. (2.2) • Nasogastric or Gastric Tube Administration: Administer 20 mL (60 mg) every 4 hours with an oral syringe.
Refill syringe with 20 mL of 0.9% saline water solution; flush remaining contents from nasogastric or gastric tube into stomach. (2.3) • Patients with Cirrhosis: Reduce dosage to 10 mL (30 mg) every 4 hours. (2.4)
2.1Administration Instructions Administer only enterally (e.g., oral, nasogastric tube, or gastric tube route). Do not administer intravenously or by other parenteral routes. For all routes of administration, begin nimodipine oral solution within 96 hours of the onset of SAH. Administer one hour before a meal or two hours after a meal for all routes of administration [see Clinical Pharmacology (12.3) ].
2.2Administration by Oral Route The recommended oral dosage is 60 mg/20 mL (3 mg/mL) every 4 hours for 21 consecutive days.
2.3Administration Via Nasogastric or Gastric Tube Using the oral syringe, administer 60 mg/20 mL (3 mg/mL) every 4 hours into a nasogastric or gastric tube for 21 consecutive days. For each dose, refill the syringe with 20 mL of 0.9% saline solution and then flush any remaining contents from nasogastric or gastric tube into the stomach.
2.4Dosage Adjustments in Patients with Cirrhosis In patients with cirrhosis, reduce the dosage to 10 mL (30 mg) every 4 hours [see Warnings and Precautions (5.2) , Clinical Pharmacology (12.3) ].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Oral Solution (3 mg per mL): • 60 mg/20 mL (3 mg/mL), pale yellow solution. Nimodipine oral solution (3 mg per mL): • 60 mg per 20 mL (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Hypotension: Monitor blood pressure. (5.1) • Patients with Cirrhosis: Higher risk of adverse reactions. Monitor blood pressure and pulse. (5.2) • CYP3A4 Strong Inhibitors: May significantly increase risk of hypotension. Concomitant use with nimodipine should generally be avoided. (5.3) • CYP3A4 Strong Inducers: May significantly reduce efficacy of nimodipine. Concomitant use with nimodipine should generally be avoided. (5.4)
5.1Hypotension Blood pressure should be carefully monitored during treatment with nimodipine. In clinical studies of patients with subarachnoid hemorrhage, about 5% of nimodipine-treated patients compared to 1% of placebo-treated patients had hypotension and about 1% of nimodipine-treated patients left the study because of this [see Adverse Reactions (6) ].
5.2Possible Increased Risk of Adverse Reactions in Patients with Cirrhosis Given that the plasma levels of nimodipine are increased in patients with cirrhosis, these patients are at higher risk of adverse reactions. Therefore, monitor blood pressure and pulse rate closely and administer a lower dosage [see Dosage and Administration (2.4) , Clinical Pharmacology (12.3) ].
5.3Possible Increased Risk of Hypotension with Strong CYP3A4 Inhibitors Concomitant use of strong inhibitors of CYP3A4, such as some macrolide antibiotics (e.g., clarithromycin, telithromycin), some HIV protease inhibitors (e.g., indinavir, nelfinavir, ritonavir, saquinavir), some HCV protease inhibitors (e.g., boceprevir, telaprevir), some azole antimycotics (e.g., ketoconazole, itraconazole, posaconazole, voriconazole), conivaptan, delavirdine, and nefazodone with nimodipine should generally be avoided because of a risk of significant hypotension [see Drug Interactions (7.2) ].
5.4Possible Reduced Efficacy with Strong CYP3A4 Inducers Concomitant use of strong CYP3A4 inducers (e.g., carbamazepine, phenobarbital, phenytoin, rifampin, St. John’s wort) and nimodipine should generally be avoided, as nimodipine plasma concentration and efficacy may be significantly reduced [see Drug Interactions (7.3) ].
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The safety and efficacy of nimodipine oral solution in the treatment of patients with SAH is based on adequate and well-controlled studies of nimodipine oral capsules in patients with SAH. Nimodipine oral solution has comparable bioavailability to nimodipine oral capsules. The following clinically significant adverse reaction appears in other sections of the labeling: • Hypotension [see Warnings and Precautions (5.1) ].
Most common adverse reactions (incidence ≥1% and ≥1% placebo) were hypotension, headache, nausea, and bradycardia. (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Annora Pharma Private Limited at 1-866-495-1995 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. In clinical trials of nimodipine oral capsules in patients with SAH, eleven percent (92 of 823) of nimodipine-treated patients reported adverse events compared to six percent (29 of 479) of placebo-treated patients. The most common adverse event was decreased blood pressure in 4.4% of nimodipine-treated patients.
The events reported with a frequency greater than 1% are displayed in Table 1 by dose. Table 1: Adverse Events [n (%)] reported with a frequency > 1% in four clinical trials (Study 1, Study 2, Study 3, and Study 4) Placebo (n=479) Nimodipine dose every 4 hours 0.35 mg/kg (n=82) 30 mg (n=71) 60 mg (n=494) 90 mg (n=172) 120 mg (n=4) Decreased Blood Pressure 6 (1.2) 1 (1.2) 0 19 (3.8) 14 (8.1) 2 (50.0) Edema 3 (0.6) 0 0 2 (0.4) 2 (1.2) 0 Diarrhea 3 (0.6) 0 3 (4.2) 0 3 (1.7) 0 Rash 3 (0.6) 2 (2.4) 0 3 (0.6) 2 (1.2) 0 Headache 1 (0.2) 0 1 (1.4) 6 (1.2) 0 0 Gastrointestinal Symptoms 0 2 (2.4) 0 0 2 (1.2) 0 Nausea 0 1 (1.2) 1 (1.4) 6 (1.2) 1 (0.6) 0 Dyspnea 0 1 (1.2) 0 0 0 0 EKG Abnormalities 0 0 1 (1.4) 0 1 (0.6) 0 Tachycardia 0 0 1 (1.4) 0 0 0 Bradycardia 0 0 0 5 (1.0) 1 (0.6) 0 Muscle Pain/Cramp 0 0 1 (1.4) 1 (0.2) 1 (0.6) 0 Acne 0 0 1 (1.4) 0 0 0 Depression 0 0 1 (1.4) 0 0 0 SAH is frequently accompanied by alterations in consciousness that may lead to an under-reporting of adverse experiences.
As a calcium channel blocker, nimodipine may have the potential to exacerbate heart failure in susceptible patients or to interfere with A-V conduction, but these events were not observed in SAH trials.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Anti-Hypertensives : May increase risk of hypotension. Monitor blood pressure. (7.1) • CYP3A4 Moderate and Weak Inhibitors: May increase risk of hypotension. Monitor blood pressure. Dose reduction of nimodipine may be needed. Avoid grapefruit juice. (7.2) • CYP3A4 Moderate and Weak Inducers: May reduce efficacy of nimodipine. Dose increase may be needed. (7.3)
7.1Blood Pressure Lowering Drugs Nimodipine may increase the blood pressure lowering effect of concomitantly administered anti-hypertensives such as diuretics, beta-blockers, ACE inhibitors, angiotensin receptor blockers, other calcium channel blockers, α-adrenergic blockers, PDE5 inhibitors, and α-methyldopa. In Europe, nimodipinewas observed to occasionally intensify the effect of antihypertensive drugs taken concomitantly by hypertensive patients; this phenomenon was not observed in North American clinical trials.
Blood pressure should be carefully monitored, and dose adjustment of the blood pressure lowering drug(s) may be necessary.
7.2CYP3A4 Inhibitors Nimodipine plasma concentration can be significantly increased when concomitantly administered with strong CYP3A4 inhibitors. As a consequence, the blood pressure lowering effect may be increased. Therefore, the concomitant administration of nimodipine and strong CYP3A4 inhibitors should generally be avoided [see Warnings and Precautions (5.3) ].
Strong CYP3A4 inhibitors include some members of the following classes: - macrolide antibiotics (e.g., clarithromycin, telithromycin), - HIV protease inhibitors (e.g., indinavir, nelfinavir, ritonavir, saquinavir), - HCV protease inhibitors (e.g., boceprevir, telaprevir), - azole antimycotics (e.g., ketoconazole, itraconazole, posaconazole, voriconazole), - conivaptan, delavirdine, nefazodone Nimodipine plasma concentration can also be increased in the presence of moderate and weak inhibitors of CYP3A4. If nimodipine is concomitantly administered with these drugs, blood pressure should be monitored, and a reduction of the nimodipine dose may be necessary.
Moderate and weak CYP3A4 inhibitors include alprozalam, ameprenavir, amiodarone, aprepitant, atazanavir, cimetidine, cyclosporine, diltiazem, erythromycin, fluconazole, fluoxetine, isoniazid, oral contraceptives, quinuprestin/dalfopristin, valproic acid, and verapamil. A study in eight healthy volunteers has shown a 50% increase in mean peak nimodipine plasma concentrations and a 90% increase in mean area under the curve, after a one-week course of cimetidine at 1,000 mg/day and nimodipine at 90 mg/day. This effect may be mediated by the known inhibition of hepatic cytochrome P-450 (CYP) by cimetidine, which could decrease first-pass metabolism of nimodipine.
Grapefruit juice inhibits CYP3A4. Ingestion of grapefruit/grapefruit juice is not recommended while taking nimodipine.
7.3CYP3A4 Inducers Nimodipine plasma concentration and efficacy may be significantly reduced when concomitantly administered with strong CYP3A4 inducers. Therefore, concomitant use of nimodipine with strong CYP3A4 inducers (e.g., carbamazepine, phenobarbital, phenytoin, rifampin, St. John’s wort) should generally be avoided [see Warnings and Precautions (5.4) ].
Moderate and weak inducers of CYP3A4 may also reduce the efficacy of nimodipine. Patients on these should be closely monitored for lack of effectiveness, and a nimodipine dosage increase may be required. Moderate and weak CYP3A4 inducers include, for example: amprenavir, aprepitant, armodafinil, bosentan, efavirnenz, etravirine, Echinacea, modafinil, nafcillin, pioglitazone, prednisone, rufinamide, and vemurafenib.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Pregnancy: Based on animal data may cause fetal harm. (8.1)
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with the use of nimodipine in pregnant women. In animal studies, oral administration of nimodipine during pregnancy resulted in adverse effects on development (increased embryofetal mortality, increased incidences of fetal structural abnormalities, decreased fetal growth) at doses equivalent to (rat) or less than (rabbit) those used clinically [see Data] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
The background risk of major birth defects and miscarriage for the indicated population is unknown. Data Animal Data Nimodipine has been shown to have a teratogenic effect in two studies in rabbit. In one study, incidences of malformations and stunted fetuses were increased at oral doses of 1 mg/kg/day and 10 mg/kg/day administered throughout organogenesis but not at 3 mg/kg/day.
In the second study, an increased incidence of stunted fetuses was seen at 1 mg/kg/day but not at higher doses (3 mg/kg/day and 10 mg/kg/day). The lowest effect dose in rabbits (1 mg/kg/day) is less than the recommended human dose (RHD) of 360 mg/day on a body surface area (mg/m 2 ) basis. Nimodipine was embryotoxic, causing resorption and stunted growth of fetuses in rats at 100 mg/kg/day administered orally throughout organogenesis; this dose is approximately 3 times the RHD on a mg/m 2 basis.
In two other studies in rats, nimodipine administered orally at 30 mg/kg/day throughout organogenesis and continued until sacrifice (day 20 of pregnancy or day 21 postpartum) was associated with higher incidences of skeletal variation, stunted fetuses, and stillbirths but no malformations; this dose is similar to the RHD on a mg/m 2 basis.
8.2Lactation Risk Summary Nimodipine has been detected in human milk. There are no data on the effects of nimodipine on the breastfed infant or on milk production. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for nimodipine and any potential adverse effects on the breastfed infant from nimodipine or from the underlying maternal condition.
Data Animal Data [ 14 C]Nimodipine and its radiolabeled metabolites were secreted in milk of orally dosed lactating rats. The milk concentration of nimodipine and/or metabolites was higher than that in plasma, with a milk/plasma ratio of 0.65 to 4.7.
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
8.5Geriatric Use Clinical studies of nimodipine did not include sufficient numbers of subjects aged 65 and over to determine whether they had a different clinical response than younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dosing in elderly patients should be cautious, reflecting the greater frequency of decreased hepatic, renal or cardiac function, and of concomitant disease or other drug therapy [see Clinical Pharmacology (12.3) ].
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with the use of nimodipine in pregnant women. In animal studies, oral administration of nimodipine during pregnancy resulted in adverse effects on development (increased embryofetal mortality, increased incidences of fetal structural abnormalities, decreased fetal growth) at doses equivalent to (rat) or less than (rabbit) those used clinically [see Data] . In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
The background risk of major birth defects and miscarriage for the indicated population is unknown. Data Animal Data Nimodipine has been shown to have a teratogenic effect in two studies in rabbit. In one study, incidences of malformations and stunted fetuses were increased at oral doses of 1 mg/kg/day and 10 mg/kg/day administered throughout organogenesis but not at 3 mg/kg/day.
In the second study, an increased incidence of stunted fetuses was seen at 1 mg/kg/day but not at higher doses (3 mg/kg/day and 10 mg/kg/day). The lowest effect dose in rabbits (1 mg/kg/day) is less than the recommended human dose (RHD) of 360 mg/day on a body surface area (mg/m 2 ) basis. Nimodipine was embryotoxic, causing resorption and stunted growth of fetuses in rats at 100 mg/kg/day administered orally throughout organogenesis; this dose is approximately 3 times the RHD on a mg/m 2 basis.
In two other studies in rats, nimodipine administered orally at 30 mg/kg/day throughout organogenesis and continued until sacrifice (day 20 of pregnancy or day 21 postpartum) was associated with higher incidences of skeletal variation, stunted fetuses, and stillbirths but no malformations; this dose is similar to the RHD on a mg/m 2 basis.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of nimodipine did not include sufficient numbers of subjects aged 65 and over to determine whether they had a different clinical response than younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dosing in elderly patients should be cautious, reflecting the greater frequency of decreased hepatic, renal or cardiac function, and of concomitant disease or other drug therapy [see Clinical Pharmacology (12.3) ].
🆘 Overdosage ▾
10 OVERDOSAGE There have been no reports of overdosage from the oral administration of nimodipine. Symptoms of overdosage would be expected to be related to cardiovascular effects such as excessive peripheral vasodilation with marked systemic hypotension. Clinically significant hypotension due to nimodipine overdosage may require active cardiovascular support with pressor agents and specific treatments for calcium channel blocker overdose.
Since nimodipine is highly protein-bound, dialysis is not likely to be of benefit.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Nimodipine is a dihydropyridine calcium channel blocker. The contractile processes of smooth muscle cells are dependent upon calcium ions, which enter these cells during depolarization as slow ionic transmembrane currents. Nimodipine inhibits calcium ion transfer into these cells and thus inhibits contractions of vascular smooth muscle.
In animal experiments, nimodipine had a greater effect on cerebral arteries than on arteries elsewhere in the body perhaps because it is highly lipophilic, allowing it to cross the blood-brain barrier; concentrations of nimodipine as high as 12.5 ng/mL have been detected in the cerebrospinal fluid of nimodipine-treated SAH patients. The precise mechanism of action of nimodipine in reducing the incidence and severity of ischemic deficits in adult patients with SAH from ruptured intracranial berry aneurysms is unknown.
Although the clinical studies demonstrate a favorable effect of nimodipine on the severity of neurological deficits caused by cerebral vasospasm following SAH, there is no arteriographic evidence that nimodipine either prevents or relieves the spasm of these arteries. However, whether or not the arteriographic methodology utilized was adequate to detect a clinically meaningful effect, if any, on vasospasm is unknown.
12.3Pharmacokinetics After a single 60 mg oral dose of nimodipine, mean (CV%) C max was 69.9 ng/mL (36.1%), AUC inf was 151 h.ng/mL (36.0%) and within subject variability (CV%) was 21.7% and 12.4%, respectively. There were no signs of accumulation when nimodipine was given three times a day for seven days. Absorption In humans, nimodipine was absorbed with a time to maximum concentration (T max ) ranging from 0.25 to 1.05 hours following oral administration.
Because of a high first-pass metabolism, the bioavailability of nimodipine averages 13% after oral administration. Effect of Food In a study of 24 healthy male volunteers, administration of nimodipine capsules following a standard breakfast resulted in a 68% lower peak plasma concentration and 38% lower bioavailability relative to dosing under fasted conditions [see Dosage and Administration (2.1) ]. Distribution Nimodipine is over 95% bound to plasma proteins.
The binding was concentration independent over the range of 10 ng/mL to 10 mcg/mL. Elimination The terminal elimination half-life is approximately 8 to 9 hours but earlier elimination rates are much more rapid, equivalent to a half-life of 1 to 2 hours; a consequence is the need for frequent (every 4 hours) dosing. Metabolism Numerous metabolites, all of which are either inactive or considerably less active than the parent compound, have been identified.
The metabolism of nimodipine is mediated by CYP3A4 [see Drug Interactions (7.2 , 7.3 )]. Excretion Nimodipine is eliminated almost exclusively in the form of metabolites and less than 1% is recovered in the urine as unchanged drug. Specific Populations Patients with Cirrhosis The bioavailability of nimodipine is significantly increased in patients with cirrhosis, with C max approximately double that in normals, which necessitates lowering the dose in this group of patients [see Dosage and Administration (2.4) , Warnings and Precautions (5.2) ].
Geriatric Patients In a single parallel-group study involving 24 elderly subjects (aged 59 to 79 years) and 24 younger subjects (aged 22 to 40 years), the observed AUC and C max of nimodipine was approximately 2-fold higher in the elderly population compared to the younger study subjects following oral administration (given as a single dose of 30 mg and dosed to steady-state with 30 mg three times daily [less than the recommended dosing regimen] for 6 days). The clinical response to these age-related pharmacokinetic differences, however, was not considered significant [see Use in Specific Populations (8.5) ].
🧬 Mechanism of Action ▾
12.1Mechanism of Action Nimodipine is a dihydropyridine calcium channel blocker. The contractile processes of smooth muscle cells are dependent upon calcium ions, which enter these cells during depolarization as slow ionic transmembrane currents. Nimodipine inhibits calcium ion transfer into these cells and thus inhibits contractions of vascular smooth muscle.
In animal experiments, nimodipine had a greater effect on cerebral arteries than on arteries elsewhere in the body perhaps because it is highly lipophilic, allowing it to cross the blood-brain barrier; concentrations of nimodipine as high as 12.5 ng/mL have been detected in the cerebrospinal fluid of nimodipine-treated SAH patients. The precise mechanism of action of nimodipine in reducing the incidence and severity of ischemic deficits in adult patients with SAH from ruptured intracranial berry aneurysms is unknown.
Although the clinical studies demonstrate a favorable effect of nimodipine on the severity of neurological deficits caused by cerebral vasospasm following SAH, there is no arteriographic evidence that nimodipine either prevents or relieves the spasm of these arteries. However, whether or not the arteriographic methodology utilized was adequate to detect a clinically meaningful effect, if any, on vasospasm is unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Nimodipine Oral Solution 3 mg/mL is a pale yellow solution and is supplied as follows: · NDC 31722-039-47: 16 oz. bottle (473 mL) 60 mg/20 mL (3 mg/mL). Store between 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F). [see USP Controlled Room Temperature]. Protect from light. Do not refrigerate.
📋 Description ▾
11 DESCRIPTION Nimodipine oral solution contains nimodipine, a dihydropyridine calcium channel blocker. Nimodipine is isopropyl 2-methoxyethyl 1,4-dihydro-2,6-dimethyl-4-( m -nitrophenyl)-3,5-pyridinedicarboxylate. It has a molecular weight of 418.45 and a molecular formula of C 21 H 26 N 2 O 7 .
The structural formula is: Nimodipine USP is a light yellow or yellow, crystalline powder, freely soluble in ethyl acetate, sparingly soluble in ethanol, practically insoluble in water. Nimodipine oral solution contains 60 mg of nimodipine per 20 mL. In addition, the oral solution contains the following inactive ingredients: dibasic sodium phosphate anhydrous, ethanol 0.63% v/v, glycerin, methylparaben, monobasic sodium phosphate monohydrate, polyethylene glycol 400 and purified water. nimodipinestructure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Inform patients that the most frequent adverse reaction associated with nimodipine is decreased blood pressure [see Warnings and Precautions (5.1) ]. Inform them that use of nimodipine oral solution with anti-hypertensives can cause increased drop in blood pressure [see Drug Interactions (7.1) ] . Patients should be aware that ingestion of grapefruit or grapefruit juice should be avoided when taking nimodipine oral solution due to its ability to increase nimodipine plasma concentrations and potential to increase the risk of hypotension [see Drug Interactions (7.2) ].
Advise patients to notify their healthcare provider if they become pregnant during treatment or plan to become pregnant during therapy [see Use in Specific Populations (8.1) ]. Advise female patients to notify their physicians if they intend to breastfeed or are breastfeeding an infant [see Use in Specific Populations (8.2) ]. For more information, call at 1-866-495-1995.
Manufactured for: Camber Pharmaceuticals, Inc. Piscataway, NJ 08854. By: Annora Pharma Pvt.
Ltd. Sangareddy - 502313, Telangana, India. Revised: 03/2024 camberlogo