
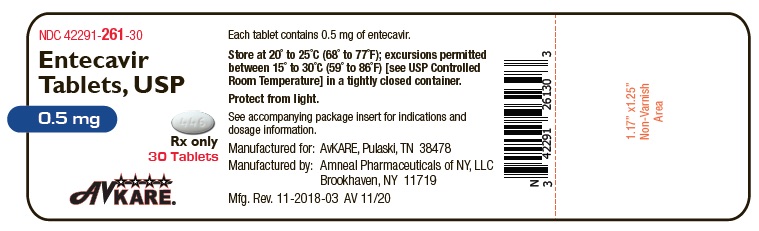
Entecavir .5 mg Tablet, Film Coated, 30-count — NDC 42291-261-30 (Billing 42291-0261-30)
This is a package of 30 tablets of Entecavir .5 mg Tablet, Film Coated from AvKARE, marketed since Nov 2020 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 42291-261-30 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 42291 labeler · 261 product · 30 package
- Package marketed since
- Nov 2, 2020
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 30 EA per package
- Barcode (UPC-A, from the NDC)
- 3 4229126130 3
- FDA record last changed
- Jul 24, 2026
Other active recalls for Entecavir (different manufacturers) — 4 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 058934
- GCN: 24466
- GPI-14 (Medi-Span): 12352030000320
- HICL (First Databank): 032832
- AHFS class code: 08:18.32.00
- RxCUI (RxNorm): 485434
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Hepatitis B Virus Nucleoside Analog Reverse Transcriptase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Entecavir keeps the hepatitis B virus under control by stopping it from copying itself, which protects your liver from ongoing damage. It's not a cure — it doesn't permanently clea...
- What exactly is entecavir treating — is it curing my hepatitis B?
- Yes, timing really does matter here. You need to take entecavir on an empty stomach — at least 2 hours after eating and at least 2 hours before your next meal. Studies showed that...
- Does it matter when I take it — can I take it with breakfast?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Entecavir — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $1.76 | $52.74 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 8, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 42291-0261-30 You're viewing this Main listing | 30 TABLET, FILM COATED in 1 BOTTLE | 2020-11-02 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Entecavir .5 mg 16714-0717-01 | NorthStar | 30 tablets | $0.219 | AB | Availability likely | — |
| Entecavir .5 mg 31722-0833-30 | Camber | 30 tablets | $0.219 | AB | Availability likely | — |
| Entecavir .5 mg 42494-0457-30 | Cameron | 30 tablets | $0.219 | AB | Availability likely | — |
| Entecavir .5 mg 42806-0658-30 | EPIC | 30 tablets | $0.219 | AB | Availability likely | — |
| Entecavir .5 mg 42806-0667-30 | Epic | 30 tablets | $0.219 | AB | Availability likely | — |
| Entecavir .5 mg 43547-0436-03 | Solco | 30 tablets | $0.219 | — | Availability likely | — |
| Entecavir .5 mg 60687-0216-25 | American | 30 tablets | $0.219 | AB | Availability likely | — |
| Entecavir .5 mg 61442-0311-30 | Carlsbad | 30 tablets | $0.219 | AB | Availability likely | — |
| Entecavir .5 mg 65862-0841-30 | Aurobindo | 30 tablets | $0.219 | AB | Availability likely | — |
| Entecavir .5 mg 69097-0426-02 | Cipla | 30 tablets | $0.219 | AB | Availability likely | — |
| Entecavir .5 mg 65162-0446-03 | Amneal | 30 tablets | $1.077 | AB | FDA listed | — |
| Baraclude .5 mg 00003-1611-12 | E.R. | 30 tablets | $44.187 | AB | Availability likely | — |
| Entecavir .5 mgthis 42291-0261-30 | AvKARE | 30 tablets | — | AB | FDA listed | — |
| Entecavir .5 mg 50771-0013-01 | Yaopharma | 30 tablets | — | — | FDA listed | — |
| Entecavir .5 mg 51407-0589-30 | Golden | 30 tablets | — | AB | FDA listed | — |
| Entecavir .5 mg 68382-0920-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Entecavir .5 mg 70771-1019-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Entecavir inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 40UAA97IT9
Crospovidone is a synthetic polymer derived from povidone. It absorbs liquid quickly and swells, helping tablets and capsules break apart and dissolve faster in your stomach.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII Q662QK8M3B
Polyethylene glycol 8000 is a synthetic polymer made from ethylene oxide. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and add bulk to the medicine.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from AvKARE labeler code 42291
- Diclofenac Sodium 75 mg Tablet, Delayed Release NDC 42291-231-10
- Diclofenac Sodium and Misoprostol 50 mg; 200 ug Tablet, Delayed Release NDC 42291-232-60
- Diclofenac Sodium and Misoprostol 75 mg; 200 ug Tablet, Delayed Release NDC 42291-233-60
- Doxazosin 2 mg Tablet NDC 42291-258-10
- Doxazosin 4 mg Tablet NDC 42291-259-01
- Doxazosin 8 mg Tablet NDC 42291-260-01
- Ergocalciferol 1.25 mg Capsule, Liquid Filled NDC 42291-266-01
- Glipizide and Metformin Hydrochloride 2.5 mg; 500 mg Tablet, Film Coated NDC 42291-305-01
- Glipizide and Metformin Hydrochloride 5 mg; 500 mg Tablet, Film Coated NDC 42291-306-01
- Hydroxyurea 500 mg Capsule NDC 42291-321-01
- guanfacine 1 mg Tablet, Extended Release NDC 42291-324-01
- guanfacine 2 mg Tablet, Extended Release NDC 42291-325-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SEVERE ACUTE EXACERBATIONS OF HEPATITIS B, PATIENTS CO-INFECTED WITH HIV AND HBV, AND LACTIC ACIDOSIS AND HEPATOMEGALY Severe acute exacerbations of hepatitis B have been reported in patients who have discontinued anti-hepatitis B therapy, including entecavir. Hepatic function should be monitored closely with both clinical and laboratory follow-up for at least several months in patients who discontinue anti-hepatitis B therapy. If appropriate, initiation of anti-hepatitis B therapy may be warranted [see Warnings and Precautions (5.1) ] .
Limited clinical experience suggests there is a potential for the development of resistance to HIV (human immunodeficiency virus) nucleoside reverse transcriptase inhibitors if entecavir is used to treat chronic hepatitis B virus (HBV) infection in patients with HIV infection that is not being treated. Therapy with entecavir is not recommended for HIV/HBV co-infected patients who are not also receiving highly active antiretroviral therapy (HAART) [see Warnings and Precautions (5.2) ] . Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of nucleoside analogue inhibitors alone or in combination with antiretrovirals [see Warnings and Precautions (5.3) ] .
WARNING: SEVERE ACUTE EXACERBATIONS OF HEPATITIS B, PATIENTS CO-INFECTED WITH HIV AND HBV, AND LACTIC ACIDOSIS AND HEPATOMEGALY See full prescribing information for complete boxed warning. Severe acute exacerbations of hepatitis B have been reported in patients who have discontinued anti-hepatitis B therapy, including entecavir. Hepatic function should be monitored closely for at least several months after discontinuation.
Initiation of anti-hepatitis B therapy may be warranted. (5.1) Entecavir is not recommended for patients co-infected with human immunodeficiency virus (HIV) and hepatitis B virus (HBV) who are not also receiving highly active antiretroviral therapy (HAART), because of the potential for the development of resistance to HIV nucleoside reverse transcriptase inhibitors. (5.2) Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of nucleoside analogue inhibitors.
(5.3)
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Entecavir tablets are indicated for the treatment of chronic hepatitis B virus infection in adults with evidence of active viral replication and either evidence of persistent elevations in serum aminotransferases (ALT or AST) or histologically active disease. The following points should be considered when initiating therapy with entecavir tablets: In adult patients, this indication is based on clinical trial data in nucleoside-inhibitor-treatment-naïve and lamivudine-resistant subjects with HBeAg-positive and HBeAg-negative HBV infection and compensated liver disease and a more limited number of subjects with decompensated liver disease [see Clinical Studies (14.1) ] .
Pediatric use information is approved for Bristol-Myers Squibb Company’s Baraclude ® (entecavir) tablets. However, due to Bristol-Myers Squibb Company’s marketing exclusivity rights, this drug product is not labeled with that information. Entecavir tablets are a Hepatitis B virus nucleoside analogue reverse transcriptase inhibitor indicated for the treatment of chronic hepatitis B virus infection in adults with evidence of active viral replication and either evidence of persistent elevations in serum aminotransferases (ALT or AST) or histologically active disease.
(1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Nucleoside-inhibitor-treatment-naïve with compensated liver disease (greater than or equal to 16 years old): 0.5 mg once daily. (2.2) Lamivudine-refractory or known lamivudine or telbivudine resistance substitutions (greater than or equal to 16 years old): 1 mg once daily. (2.2) Decompensated liver disease (adults): 1 mg once daily.
(2.2) Renal impairment: Dosage adjustment is recommended if creatinine clearance is less than 50 mL/min. (2.4) Entecavir tablets should be administered on an empty stomach. (2.1)
2.1Timing of Administration Entecavir tablets should be administered on an empty stomach (at least 2 hours after a meal and 2 hours before the next meal).
2.2Recommended Dosage in Adults Compensated Liver Disease The recommended dose of entecavir tablets for chronic hepatitis B virus infection in nucleoside-inhibitor-treatment-naïve adults and adolescents 16 years of age and older is 0.5 mg once daily. The recommended dose of entecavir tablets in adults and adolescents (at least 16 years of age) with a history of hepatitis B viremia while receiving lamivudine or known lamivudine or telbivudine resistance substitutions rtM204I/V with or without rtL180M, rtL80I/V, or rtV173L is 1 mg once daily.
Decompensated Liver Disease The recommended dose of entecavir tablets for chronic hepatitis B virus infection in adults with decompensated liver disease is 1 mg once daily.
2.3Recommended Dosage in Pediatric Patients Pediatric use information is approved for Bristol-Myers Squibb Company’s Baraclude ® (entecavir) tablets. However, due to Bristol-Myers Squibb Company’s marketing exclusivity rights, this drug product is not labeled with that information.
2.4Renal Impairment In adult subjects with renal impairment, the apparent oral clearance of entecavir decreased as creatinine clearance decreased [see Clinical Pharmacology (12.3) ] . Dosage adjustment is recommended for patients with creatinine clearance less than 50 mL/min, including patients on hemodialysis or continuous ambulatory peritoneal dialysis (CAPD), as shown in Table 2. The once-daily dosing regimens are preferred.
Table 2: Recommended Dosage of Entecavir Tablets in Adult Patients with Renal Impairment Creatinine Clearance (mL/min) Usual Dose (0.5 mg) Lamivudine-Refractory or Decompensated Liver Disease (1 mg) 50 or greater 0.5 mg once daily 1 mg once daily 30 to less than 50 0.5 mg every 48 hours 0.5 mg once daily OR 1 mg every 48 hours 10 to less than 30 0.5 mg every 72 hours 1 mg every 72 hours less than 10 Hemodialysis* or CAPD 0.5 mg every 7 days 1 mg every 7 days * If administered on a hemodialysis day, administer entecavir tablets after the hemodialysis session.
Pediatric use information is approved for Bristol-Myers Squibb Company’s Baraclude ® (entecavir) tablets. However, due to Bristol-Myers Squibb Company’s marketing exclusivity rights, this drug product is not labeled with that information.
2.5Hepatic Impairment No dosage adjustment is necessary for patients with hepatic impairment.
2.6Duration of Therapy The optimal duration of treatment with entecavir tablets for patients with chronic hepatitis B virus infection and the relationship between treatment and long-term outcomes such as cirrhosis and hepatocellular carcinoma are unknown.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Entecavir tablets 0.5 mg are white to off-white, oval, film-coated, biconvex bevel edged, unscored tablets, debossed with “AN” on one side and “446” on the other side. Entecavir tablets 1 mg are pink, oval, film-coated, biconvex bevel edged, unscored tablets, debossed with “AN” on one side and “449” on the other side. Tablets: 0.5 mg and 1 mg (3, 16)
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Severe acute exacerbations of hepatitis B virus infection after discontinuation: Monitor hepatic function closely for at least several months. (5.1, 6.1) Co-infection with HIV: Entecavir is not recommended unless the patient is also receiving HAART. (5.2) Lactic acidosis and severe hepatomegaly with steatosis: If suspected, treatment should be suspended. (5.3)
5.1Severe Acute Exacerbations of Hepatitis B Severe acute exacerbations of hepatitis B have been reported in patients who have discontinued anti-hepatitis B therapy, including entecavir [see Adverse Reactions (6.1) ] . Hepatic function should be monitored closely with both clinical and laboratory follow-up for at least several months in patients who discontinue anti-hepatitis B therapy. If appropriate, initiation of anti-hepatitis B therapy may be warranted.
5.2Patients Co-infected with HIV and HBV Entecavir has not been evaluated in HIV/HBV co-infected patients who were not simultaneously receiving effective HIV treatment. Limited clinical experience suggests there is a potential for the development of resistance to HIV nucleoside reverse transcriptase inhibitors if entecavir is used to treat chronic hepatitis B virus infection in patients with HIV infection that is not being treated [see Microbiology (12.4) ] . Therefore, therapy with entecavir is not recommended for HIV/HBV co-infected patients who are not also receiving HAART.
Before initiating entecavir therapy, HIV antibody testing should be offered to all patients. Entecavir has not been studied as a treatment for HIV infection and is not recommended for this use.
5.3Lactic Acidosis and Severe Hepatomegaly with Steatosis Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of nucleoside analogue inhibitors, including entecavir, alone or in combination with antiretrovirals. A majority of these cases have been in women. Obesity and prolonged nucleoside inhibitor exposure may be risk factors.
Particular caution should be exercised when administering nucleoside analogue inhibitors to any patient with known risk factors for liver disease; however, cases have also been reported in patients with no known risk factors. Lactic acidosis with entecavir use has been reported, often in association with hepatic decompensation, other serious medical conditions, or drug exposures. Patients with decompensated liver disease may be at higher risk for lactic acidosis.
Treatment with entecavir should be suspended in any patient who develops clinical or laboratory findings suggestive of lactic acidosis or pronounced hepatotoxicity (which may include hepatomegaly and steatosis even in the absence of marked transaminase elevations).
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in other sections of the labeling: Exacerbations of hepatitis after discontinuation of treatment [see Boxed Warning , Warnings and Precautions (5.1) ] . Lactic acidosis and severe hepatomegaly with steatosis [see Boxed Warning , Warnings and Precautions (5.3) ] . Most common adverse reactions (≥3%, all severity grades) are headache, fatigue, dizziness and nausea.
(6.1) To report SUSPECTED ADVERSE REACTIONS, contact AvKARE at 1-855-361-3993; or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trial Experience in Adults Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Compensated Liver Disease Assessment of adverse reactions is based on four studies (AI463014, AI463022, AI463026 and AI463027) in which 1720 subjects with chronic hepatitis B virus infection and compensated liver disease received double-blind treatment with entecavir 0.5 mg/day (n=679), entecavir 1 mg/day (n=183), or lamivudine (n=858) for up to 2 years.
Median duration of therapy was 69 weeks for entecavir-treated subjects and 63 weeks for lamivudine-treated subjects in Studies AI463022 and AI463027 and 73 weeks for entecavir-treated subjects and 51 weeks for lamivudine-treated subjects in Studies AI463026 and AI463014. The safety profiles of entecavir and lamivudine were comparable in these studies. The most common adverse reactions of any severity (≥3%) with at least a possible relation to study drug for entecavir-treated subjects were headache, fatigue, dizziness and nausea.
The most common adverse reactions among lamivudine-treated subjects were headache, fatigue and dizziness. One percent of entecavir-treated subjects in these four studies compared with 4% of lamivudine-treated subjects discontinued for adverse events or abnormal laboratory test results. Clinical adverse reactions of moderate-severe intensity and considered at least possibly related to treatment occurring during therapy in four clinical studies in which entecavir was compared with lamivudine are presented in Table 3.
Table 3: Clinical Adverse Reactions a of Moderate-Severe Intensity (Grades 2 to 4) Reported in Four Entecavir Clinical Trials Through 2 Years Nucleoside-Inhibitor-Naïve b Lamivudine-Refractory c Entecavir Lamivudine Entecavir Lamivudine Body System/ 0.5 mg 100 mg 1 mg 100 mg Adverse Reaction n=679 n=668 n=183 n=190 Any Grade 2 to 4 adverse reaction a 15% 18% 22% 23% Gastrointestinal Diarrhea <1% 0 1% 0 Dyspepsia <1% <1% 1% 0 Nausea <1% <1% <1% 2% Vomiting <1% <1% <1% 0 General Fatigue 1% 1% 3% 3% Nervous System Headache 2% 2% 4% 1% Dizziness <1% <1% 0 1% Somnolence <1% <1% 0 0 Psychiatric Insomnia <1% <1% 0 <1% a Includes events of possible, probable, certain, or unknown relationship to treatment regimen. b Studies AI463022 and AI463027. c Includes Study AI463026 and the entecavir 1 mg and lamivudine treatment arms of Study AI463014, a Phase 2 multinational, randomized, double-blind study of three doses of entecavir (0.1, 0.5 and 1 mg) once daily versus continued lamivudine 100 mg once daily for up to 52 weeks in subjects who experienced recurrent viremia on lamivudine therapy.
Laboratory Abnormalities Frequencies of selected treatment-emergent laboratory abnormalities reported during therapy in four clinical trials of entecavir compared with lamivudine are listed in Table 4. Table 4: Selected Treatment-Emergent a Laboratory Abnormalities Reported in Four Entecavir Clinical Trials Through 2 Years Nucleoside-Inhibitor-Naïve b Lamivudine-Refractory c Entecavir Lamivudine Entecavir Lamivudine 0.5 mg 100 mg 1 mg 100 mg Test n=679 n=668 n=183 n=190 Any Grade 3 to 4 laboratory abnormality d 35% 36% 37% 45% ALT >10 x ULN and >2 x baseline 2% 4% 2% 11% ALT >5 x ULN 11% 16% 12% 24% Albumin <2.5 g/dL <… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Since entecavir is primarily eliminated by the kidneys [see Clinical Pharmacology (12.3) ] , co-administration of entecavir with drugs that reduce renal function or compete for active tubular secretion may increase serum concentrations of either entecavir or the co-administered drug. Co-administration of entecavir with lamivudine, adefovir dipivoxil, or tenofovir disoproxil fumarate did not result in significant drug interactions. The effects of co-administration of entecavir with other drugs that are renally eliminated or are known to affect renal function have not been evaluated, and patients should be monitored closely for adverse events when entecavir is co-administered with such drugs.
To report SUSPECTED ADVERSE REACTIONS contact AvKARE at 1-855-361-3993; email [email protected]; or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Nursing mothers: Discontinue nursing or entecavir taking into consideration the importance of entecavir to the mother. (8.3) Pediatric use information is approved for Bristol-Myers Squibb Company’s Baraclude ® (entecavir) tablets. However, due to Bristol-Myers Squibb Company’s marketing exclusivity rights, this drug product is not labeled with that information.
8.1Pregnancy Pregnancy Category C There are no adequate and well-controlled studies of entecavir in pregnant women. Because animal reproduction studies are not always predictive of human response, entecavir should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Antiretroviral Pregnancy Registry: To monitor fetal outcomes of pregnant women exposed to entecavir, an Antiretroviral Pregnancy Registry has been established.
Healthcare providers are encouraged to register patients by calling 1-800-258-4263. Animal Data Animal reproduction studies with entecavir in rats and rabbits revealed no evidence of teratogenicity. Developmental toxicity studies were performed in rats and rabbits.
There were no signs of embryofetal or maternal toxicity when pregnant animals received oral entecavir at approximately 28 (rat) and 212 (rabbit) times the human exposure achieved at the highest recommended human dose of 1 mg/day. In rats, maternal toxicity, embryofetal toxicity (resorptions), lower fetal body weights, tail and vertebral malformations, reduced ossification (vertebrae, sternebrae and phalanges) and extra lumbar vertebrae and ribs were observed at exposures 3100 times those in humans. In rabbits, embryofetal toxicity (resorptions), reduced ossification (hyoid) and an increased incidence of 13th rib were observed at exposures 883 times those in humans.
In a peripostnatal study, no adverse effects on offspring occurred when rats received oral entecavir at exposures greater than 94 times those in humans.
8.2Labor and Delivery There are no studies in pregnant women and no data on the effect of entecavir on transmission of HBV from mother to infant. Therefore, appropriate interventions should be used to prevent neonatal acquisition of HBV.
8.3Nursing Mothers It is not known whether entecavir is excreted into human milk; however, entecavir is excreted into the milk of rats. Because many drugs are excreted into human milk and because of the potential for serious adverse reactions in nursing infants from entecavir, a decision should be made to discontinue nursing or to discontinue entecavir taking into consideration the importance of continued hepatitis B therapy to the mother and the known benefits of breastfeeding.
8.4Pediatric Use The efficacy and safety of entecavir have not been established in patients less than 2 years of age. Use of entecavir in this age group has not been evaluated because treatment of HBV in this age group is rarely required. Pediatric use information is approved for Bristol-Myers Squibb Company’s Baraclude ® (entecavir) tablets.
However, due to Bristol-Myers Squibb Company’s marketing exclusivity rights, this drug product is not labeled with that information.
8.5Geriatric Use Clinical studies of entecavir did not include sufficient numbers of subjects aged 65 years and over to determine whether they respond differently from younger subjects. Entecavir is substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function [see Dosage and Administration (2.4) ] .
8.6Racial/Ethnic Groups There are no significant racial differences in entecavir pharmacokinetics.
8.7Renal Impairment Dosage adjustment of entecavir is recommended for patients with creatinine clearance less than 50 mL/min, including patients on hemodialysis or CAPD [see Dosage and Administ… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Category C There are no adequate and well-controlled studies of entecavir in pregnant women. Because animal reproduction studies are not always predictive of human response, entecavir should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Antiretroviral Pregnancy Registry: To monitor fetal outcomes of pregnant women exposed to entecavir, an Antiretroviral Pregnancy Registry has been established.
Healthcare providers are encouraged to register patients by calling 1-800-258-4263. Animal Data Animal reproduction studies with entecavir in rats and rabbits revealed no evidence of teratogenicity. Developmental toxicity studies were performed in rats and rabbits.
There were no signs of embryofetal or maternal toxicity when pregnant animals received oral entecavir at approximately 28 (rat) and 212 (rabbit) times the human exposure achieved at the highest recommended human dose of 1 mg/day. In rats, maternal toxicity, embryofetal toxicity (resorptions), lower fetal body weights, tail and vertebral malformations, reduced ossification (vertebrae, sternebrae and phalanges) and extra lumbar vertebrae and ribs were observed at exposures 3100 times those in humans. In rabbits, embryofetal toxicity (resorptions), reduced ossification (hyoid) and an increased incidence of 13th rib were observed at exposures 883 times those in humans.
In a peripostnatal study, no adverse effects on offspring occurred when rats received oral entecavir at exposures greater than 94 times those in humans.
🧒 Pediatric Use ▾
8.4Pediatric Use The efficacy and safety of entecavir have not been established in patients less than 2 years of age. Use of entecavir in this age group has not been evaluated because treatment of HBV in this age group is rarely required. Pediatric use information is approved for Bristol-Myers Squibb Company’s Baraclude ® (entecavir) tablets.
However, due to Bristol-Myers Squibb Company’s marketing exclusivity rights, this drug product is not labeled with that information.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of entecavir did not include sufficient numbers of subjects aged 65 years and over to determine whether they respond differently from younger subjects. Entecavir is substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function [see Dosage and Administration (2.4) ] .
🆘 Overdosage ▾
10 OVERDOSAGE There is limited experience of entecavir overdosage reported in patients. Healthy subjects who received single entecavir doses up to 40 mg or multiple doses up to 20 mg/day for up to 14 days had no increase in or unexpected adverse events. If overdose occurs, the patient must be monitored for evidence of toxicity, and standard supportive treatment applied as necessary.
Following a single 1 mg dose of entecavir, a 4-hour hemodialysis session removed approximately 13% of the entecavir dose.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Entecavir is an antiviral drug [see Microbiology (12.4) ] .
12.3Pharmacokinetics The single- and multiple-dose pharmacokinetics of entecavir were evaluated in healthy subjects and subjects with chronic hepatitis B virus infection. Absorption Following oral administration in healthy subjects, entecavir peak plasma concentrations occurred between 0.5 and 1.5 hours. Following multiple daily doses ranging from 0.1 to 1 mg, C max and area under the concentration-time curve (AUC) at steady-state increased in proportion to dose.
Steady-state was achieved after 6 to 10 days of once-daily administration with approximately 2-fold accumulation. For a 0.5 mg oral dose, C max at steady-state was 4.2 ng/mL and trough plasma concentration (C trough ) was 0.3 ng/mL. For a 1 mg oral dose, C max was 8.2 ng/mL and C trough was 0.5 ng/mL.
Effects of food on oral absorption: Oral administration of 0.5 mg of entecavir with a standard high-fat meal (945 kcal, 54.6 g fat) or a light meal (379 kcal, 8.2 g fat) resulted in a delay in absorption (1 to 1.5 hours fed vs. 0.75 hours fasted), a decrease in C max of 44% to 46% and a decrease in AUC of 18% to 20% [see Dosage and Administration (2) ] . Distribution Based on the pharmacokinetic profile of entecavir after oral dosing, the estimated apparent volume of distribution is in excess of total body water, suggesting that entecavir is extensively distributed into tissues.
Binding of entecavir to human serum proteins in vitro was approximately 13%. Metabolism and Elimination Following administration of 14 C-entecavir in humans and rats, no oxidative or acetylated metabolites were observed. Minor amounts of phase II metabolites (glucuronide and sulfate conjugates) were observed.
Entecavir is not a substrate, inhibitor, or inducer of the cytochrome P450 (CYP450) enzyme system. See Drug Interactions , below . After reaching peak concentration, entecavir plasma concentrations decreased in a bi-exponential manner with a terminal elimination half-life of approximately 128 to 149 hours.
The observed drug accumulation index is approximately 2-fold with once-daily dosing, suggesting an effective accumulation half-life of approximately 24 hours. Entecavir is predominantly eliminated by the kidney with urinary recovery of unchanged drug at steady-state ranging from 62% to 73% of the administered dose. Renal clearance is independent of dose and ranges from 360 to 471 mL/min suggesting that entecavir undergoes both glomerular filtration and net tubular secretion [see Drug Interactions (7) ] .
Special Populations Gender: There are no significant gender differences in entecavir pharmacokinetics. Race: There are no significant racial differences in entecavir pharmacokinetics. Elderly: The effect of age on the pharmacokinetics of entecavir was evaluated following administration of a single 1 mg oral dose in healthy young and elderly volunteers.
Entecavir AUC was 29.3% greater in elderly subjects compared to young subjects. The disparity in exposure between elderly and young subjects was most likely attributable to differences in renal function. Dosage adjustment of entecavir should be based on the renal function of the patient, rather than age [see Dosage and Administration (2.4) ] .
Pediatrics: Pediatric use information is approved for Bristol-Myers Squibb Company’s Baraclude ® (entecavir) tablets. However, due to Bristol-Myers Squibb Company’s marketing exclusivity rights, this drug product is not labeled with that information. Renal impairment: The pharmacokinetics of entecavir following a single 1 mg dose were studied in subjects (without chronic hepatitis B virus infection) with selected degrees of renal impairment, including subjects whose renal impairment was managed by hemodialysis or continuous ambulatory peritoneal dialysis (CAPD).
Results are shown in Table 7 [see Dosage and Administration (2.4) ] . Table 7: Pharmacokinetic Parameters in Subjects with Selected D… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Entecavir is an antiviral drug [see Microbiology (12.4) ] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED Entecavir tablets 0.5 mg, are supplied as white to off-white, oval, film-coated, biconvex bevel edged, unscored tablet, debossed with “AN” on one side and “446” on the other side. They are available as follows: Bottles of 30: NDC 42291-261-30 Entecavir tablets 1 mg, are supplied as pink, oval, film-coated, biconvex bevel edged, unscored tablet, debossed with “AN” on one side and “449” on the other side. They are available as follows: Bottles of 30: NDC 42291-262-30 Storage Entecavir tablets should be stored in a tightly closed container at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30° C (59° to 86°F) [see USP Controlled Room Temperature].
Protect from light.
📋 Description ▾
11 DESCRIPTION Entecavir is a guanosine nucleoside analogue with selective activity against HBV. The chemical name for entecavir is 2-amino-1,9-dihydro-9-[( 1S,3R,4S )-4-hydroxy-3-(hydroxymethyl)-2-methylenecyclopentyl]-6 H -purin-6-one, monohydrate. Its molecular formula is C 12 H 15 N 5 O 3 •H 2 O, which corresponds to a molecular weight of 295.3.
Entecavir has the following structural formula: Entecavir is a white to off-white powder. It is slightly soluble in water (2.4 mg/mL), and the pH of the saturated solution in water is 7.9 at 25° C ± 0.5° C. Entecavir film-coated tablets are available for oral administration in strengths of 0.5 mg and 1 mg of entecavir.
Entecavir 0.5 mg and 1 mg film-coated tablets contain the following inactive ingredients: Crospovidone, lactose monohydrate, magnesium stearate, microcrystalline cellulose and povidone. The tablet coating contains hypromellose, iron oxide red (in 1 mg tablet only), polyethylene glycol 8000 and titanium dioxide. Structural Formula
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-approved patient labeling (Patient Information) . Information about Treatment Physicians should inform their patients of the following important points when initiating entecavir treatment: Patients should remain under the care of a physician while taking entecavir. They should discuss any new symptoms or concurrent medications with their physician.
Patients should be advised that treatment with entecavir has not been shown to reduce the risk of transmission of HBV to others through sexual contact or blood contamination. Patients should be advised to take entecavir on an empty stomach (at least 2 hours after a meal and 2 hours before the next meal). Patients should be advised to take a missed dose as soon as remembered unless it is almost time for the next dose.
Patients should not take two doses at the same time. Patients should be advised that treatment with entecavir will not cure HBV. Patients should be informed that entecavir may lower the amount of HBV in the body, may lower the ability of HBV to multiply and infect new liver cells, and may improve the condition of the liver.
Patients should be informed that it is not known whether entecavir will reduce their chances of getting liver cancer or cirrhosis. Post-treatment Exacerbation of Hepatitis Patients should be informed that deterioration of liver disease may occur in some cases if treatment is discontinued, and that they should discuss any change in regimen with their physician. HIV/HBV Co-infection Patients should be offered HIV antibody testing before starting entecavir therapy.
They should be informed that if they have HIV infection and are not receiving effective HIV treatment, entecavir may increase the chance of HIV resistance to HIV medication. Manufactured for: AvKARE Pulaski, TN 38478 Mfg. Rev.
11-2019-06 AV 11/20 (P) Manufactured by: Amneal Pharmaceuticals of New York, LLC Brookhaven, NY 11719 Mfg. Rev. 11-2019-06
💬 Patient Medication Information ▾
Patient Information Entecavir (en-TEK-a-vir) Tablets Read this Patient Information before you start taking entecavir tablets and each time you get a refill. There may be new information. This information does not take the place of talking with your healthcare provider about your medical condition or treatment.
What is the most important information I should know about Entecavir Tablets? 1. Your hepatitis B virus (HBV) infection may get worse if you stop taking entecavir tablets.
This usually happens within 6 months after stopping entecavir tablets. Take entecavir tablets exactly as prescribed. Do not run out of entecavir tablets.
Do not stop entecavir tablets without talking to your healthcare provider. Your healthcare provider should monitor your health and do regular blood tests to check your liver if you stop taking entecavir tablets. 2.
If you have or get HIV that is not being treated with medicines while taking entecavir tablets, the HIV virus may develop resistance to certain HIV medicines and become harder to treat. You should get an HIV test before you start taking entecavir tablets and anytime after that when there is a chance you were exposed to HIV. Entecavir tablets can cause serious side effects including: 3.
Lactic acidosis (buildup of acid in the blood). Some people who have taken entecavir tablets or medicines like entecavir (a nucleoside analogue) have developed a serious condition called lactic acidosis. Lactic acidosis is a serious medical emergency that can cause death.
Lactic acidosis must be treated in the hospital. Reports of lactic acidosis with entecavir tablets generally involved patients who were seriously ill due to their liver disease or other medical condition. Call your healthcare provider right away if you get any of the following signs or symptoms of lactic acidosis: You feel very weak or tired.
You have unusual (not normal) muscle pain. You have trouble breathing. You have stomach pain with nausea and vomiting.
You feel cold, especially in your arms and legs. You feel dizzy or light-headed. You have a fast or irregular heartbeat.
4. Serious liver problems. Some people who have taken medicines like entecavir tablets have developed serious liver problems called hepatotoxicity, with liver enlargement (hepatomegaly) and fat in the liver (steatosis).
Hepatomegaly with steatosis is a serious medical emergency that can cause death. Call your healthcare provider right away if you get any of the following signs or symptoms of liver problems: Your skin or the white part of your eyes turns yellow (jaundice). Your urine turns dark.
Your bowel movements (stools) turn light in color. You don’t feel like eating food for several days or longer. You feel sick to your stomach (nausea).
You have lower stomach pain. You may be more likely to get lactic acidosis or serious liver problems if you are female, very overweight, or have been taking nucleoside analogue medicines, like entecavir tablets, for a long time. What are Entecavir Tablets?
Entecavir tablets are a prescription medicine used to treat chronic hepatitis B virus (HBV) in adults who have active liver disease. Entecavir tablets will not cure HBV. Entecavir tablets may lower the amount of HBV in the body.
Entecavir tablets may lower the ability of HBV to multiply and infect new liver cells. Entecavir tablets may improve the condition of your liver. It is not known whether entecavir tablets will reduce your chances of getting liver cancer or liver damage (cirrhosis), which may be caused by chronic HBV infection.
It is not known if entecavir tablets are safe and effective for use in children less than 2 years of age. What should I tell my healthcare provider before taking Entecavir Tablets? Before you take entecavir tablets, tell your healthcare provider if you: have kidney problems.
Your entecavir tablets dose or schedule may need to be changed. have received medicine for HBV before. Some people, especially those who have already been treated with certain… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
8.3Nursing Mothers It is not known whether entecavir is excreted into human milk; however, entecavir is excreted into the milk of rats. Because many drugs are excreted into human milk and because of the potential for serious adverse reactions in nursing infants from entecavir, a decision should be made to discontinue nursing or to discontinue entecavir taking into consideration the importance of continued hepatitis B therapy to the mother and the known benefits of breastfeeding.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The single- and multiple-dose pharmacokinetics of entecavir were evaluated in healthy subjects and subjects with chronic hepatitis B virus infection. Absorption Following oral administration in healthy subjects, entecavir peak plasma concentrations occurred between 0.5 and 1.5 hours. Following multiple daily doses ranging from 0.1 to 1 mg, C max and area under the concentration-time curve (AUC) at steady-state increased in proportion to dose.
Steady-state was achieved after 6 to 10 days of once-daily administration with approximately 2-fold accumulation. For a 0.5 mg oral dose, C max at steady-state was 4.2 ng/mL and trough plasma concentration (C trough ) was 0.3 ng/mL. For a 1 mg oral dose, C max was 8.2 ng/mL and C trough was 0.5 ng/mL.
Effects of food on oral absorption: Oral administration of 0.5 mg of entecavir with a standard high-fat meal (945 kcal, 54.6 g fat) or a light meal (379 kcal, 8.2 g fat) resulted in a delay in absorption (1 to 1.5 hours fed vs. 0.75 hours fasted), a decrease in C max of 44% to 46% and a decrease in AUC of 18% to 20% [see Dosage and Administration (2) ] . Distribution Based on the pharmacokinetic profile of entecavir after oral dosing, the estimated apparent volume of distribution is in excess of total body water, suggesting that entecavir is extensively distributed into tissues.
Binding of entecavir to human serum proteins in vitro was approximately 13%. Metabolism and Elimination Following administration of 14 C-entecavir in humans and rats, no oxidative or acetylated metabolites were observed. Minor amounts of phase II metabolites (glucuronide and sulfate conjugates) were observed.
Entecavir is not a substrate, inhibitor, or inducer of the cytochrome P450 (CYP450) enzyme system. See Drug Interactions , below . After reaching peak concentration, entecavir plasma concentrations decreased in a bi-exponential manner with a terminal elimination half-life of approximately 128 to 149 hours.
The observed drug accumulation index is approximately 2-fold with once-daily dosing, suggesting an effective accumulation half-life of approximately 24 hours. Entecavir is predominantly eliminated by the kidney with urinary recovery of unchanged drug at steady-state ranging from 62% to 73% of the administered dose. Renal clearance is independent of dose and ranges from 360 to 471 mL/min suggesting that entecavir undergoes both glomerular filtration and net tubular secretion [see Drug Interactions (7) ] .
Special Populations Gender: There are no significant gender differences in entecavir pharmacokinetics. Race: There are no significant racial differences in entecavir pharmacokinetics. Elderly: The effect of age on the pharmacokinetics of entecavir was evaluated following administration of a single 1 mg oral dose in healthy young and elderly volunteers.
Entecavir AUC was 29.3% greater in elderly subjects compared to young subjects. The disparity in exposure between elderly and young subjects was most likely attributable to differences in renal function. Dosage adjustment of entecavir should be based on the renal function of the patient, rather than age [see Dosage and Administration (2.4) ] .
Pediatrics: Pediatric use information is approved for Bristol-Myers Squibb Company’s Baraclude ® (entecavir) tablets. However, due to Bristol-Myers Squibb Company’s marketing exclusivity rights, this drug product is not labeled with that information. Renal impairment: The pharmacokinetics of entecavir following a single 1 mg dose were studied in subjects (without chronic hepatitis B virus infection) with selected degrees of renal impairment, including subjects whose renal impairment was managed by hemodialysis or continuous ambulatory peritoneal dialysis (CAPD).
Results are shown in Table 7 [see Dosage and Administration (2.4) ] . Table 7: Pharmacokinetic Parameters in Subjects with Selected Degrees of Renal Function Renal Function Group Baseline Creatinine Clearance (mL/min) Unimpaired Mild Moderate… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The safety and efficacy of entecavir were evaluated in three Phase 3 active-controlled trials [see Clinical Studies (14.1 , 14.2) ] . These studies included 1633 subjects 16 years of age or older with chronic hepatitis B virus infection (serum HBsAg-positive for at least 6 months) accompanied by evidence of viral replication (detectable serum HBV DNA, as measured by the bDNA hybridization or PCR assay). Subjects had persistently elevated ALT levels at least 1.3 times ULN and chronic inflammation on liver biopsy compatible with a diagnosis of chronic viral hepatitis.
The safety and efficacy of entecavir were also evaluated in a study of 191 HBV-infected subjects with decompensated liver disease and in a study of 68 subjects co-infected with HBV and HIV [see Clinical Studies (14.1) ] .
14.1Outcomes in Adults At 48 Weeks The safety and efficacy of entecavir in adults were evaluated in three Phase 3 active-controlled trials. These studies included 1633 subjects 16 years of age or older with chronic hepatitis B virus infection (serum HBsAg-positive for at least 6 months) accompanied by evidence of viral replication (detectable serum HBV DNA, as measured by the bDNA hybridization or PCR assay). Subjects had persistently elevated ALT levels at least 1.3 times ULN and chronic inflammation on liver biopsy compatible with a diagnosis of chronic viral hepatitis.
The safety and efficacy of entecavir were also evaluated in a study of 191 HBV-infected subjects with decompensated liver disease and in a study of 68 subjects co-infected with HBV and HIV. Nucleoside-inhibitor-naïve Subjects with Compensated Liver Disease HBeAg-positive: Study AI463022 was a multinational, randomized, double-blind study of entecavir 0.5 mg once daily versus lamivudine 100 mg once daily for a minimum of 52 weeks in 709 (of 715 randomized) nucleoside-inhibitor-naïve subjects with chronic hepatitis B virus infection, compensated liver disease, and detectable HBeAg.
The mean age of subjects was 35 years, 75% were male, 57% were Asian, 40% were Caucasian and 13% had previously received interferon-α. At baseline, subjects had a mean Knodell Necroinflammatory Score of 7.8, mean serum HBV DNA as measured by Roche COBAS Amplicor ® PCR assay was 9.66 log 10 copies/mL, and mean serum ALT level was 143 U/L. Paired, adequate liver biopsy samples were available for 89% of subjects.
HBeAg-negative (anti-HBe-positive/HBV DNA-positive): Study AI463027 was a multinational, randomized, double-blind study of entecavir 0.5 mg once daily versus lamivudine 100 mg once daily for a minimum of 52 weeks in 638 (of 648 randomized) nucleoside-inhibitor-naïve subjects with HBeAg-negative (HBeAb-positive) chronic hepatitis B virus infection and compensated liver disease. The mean age of subjects was 44 years, 76% were male, 39% were Asian, 58% were Caucasian and 13% had previously received interferon-α. At baseline, subjects had a mean Knodell Necroinflammatory Score of 7.8, mean serum HBV DNA as measured by Roche COBAS Amplicor PCR assay was 7.58 log 10 copies/mL, and mean serum ALT level was 142 U/L.
Paired, adequate liver biopsy samples were available for 88% of subjects. In Studies AI463022 and AI463027, entecavir was superior to lamivudine on the primary efficacy endpoint of Histologic Improvement, defined as a 2-point or greater reduction in Knodell Necroinflammatory Score with no worsening in Knodell Fibrosis Score at Week 48, and on the secondary efficacy measures of reduction in viral load and ALT normalization. Histologic Improvement and change in Ishak Fibrosis Score are shown in Table 8.
Selected virologic, biochemical and serologic outcome measures are shown in Table 9. Table 8: Histologic Improvement and Change in Ishak Fibrosis Score at Week 48, Nucleoside-Inhibitor-Naïve Subjects in Studies AI463022 and AI463027 Study AI463022 (HBeAg-Positive) Study AI463027 (HBeAg-Negative) Entecavir Lamivudine Entecavir Lamivudine 0.5 mg 100 mg 0.5 mg 100 mg n=314 a n=31… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Long-term oral carcinogenicity studies of entecavir in mice and rats were carried out at exposures up to approximately 42 times (mice) and 35 times (rats) those observed in humans at the highest recommended dose of 1 mg/day. In mouse and rat studies, entecavir was positive for carcinogenic findings. In mice, lung adenomas were increased in males and females at exposures 3 and 40 times those in humans.
Lung carcinomas in both male and female mice were increased at exposures 40 times those in humans. Combined lung adenomas and carcinomas were increased in male mice at exposures 3 times and in female mice at exposures 40 times those in humans. Tumor development was preceded by pneumocyte proliferation in the lung, which was not observed in rats, dogs, or monkeys administered entecavir, supporting the conclusion that lung tumors in mice may be a species-specific event.
Hepatocellular carcinomas were increased in males and combined liver adenomas and carcinomas were also increased at exposures 42 times those in humans. Vascular tumors in female mice (hemangiomas of ovaries and uterus and hemangiosarcomas of spleen) were increased at exposures 40 times those in humans. In rats, hepatocellular adenomas were increased in females at exposures 24 times those in humans; combined adenomas and carcinomas were also increased in females at exposures 24 times those in humans.
Brain gliomas were induced in both males and females at exposures 35 and 24 times those in humans. Skin fibromas were induced in females at exposures 4 times those in humans. It is not known how predictive the results of rodent carcinogenicity studies may be for humans.
Mutagenesis Entecavir was clastogenic to human lymphocyte cultures. Entecavir was not mutagenic in the Ames bacterial reverse mutation assay using S. typhimurium and E. coli strains in the presence or absence of metabolic activation, a mammalian-cell gene mutation assay, and a transformation assay with Syrian hamster embryo cells. Entecavir was also negative in an oral micronucleus study and an oral DNA repair study in rats.
Impairment of Fertility In reproductive toxicology studies, in which animals were administered entecavir at up to 30 mg/kg for up to 4 weeks, no evidence of impaired fertility was seen in male or female rats at systemic exposures greater than 90 times those achieved in humans at the highest recommended dose of 1 mg/day. In rodent and dog toxicology studies, seminiferous tubular degeneration was observed at exposures 35 times or greater than those achieved in humans. No testicular changes were evident in monkeys.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Long-term oral carcinogenicity studies of entecavir in mice and rats were carried out at exposures up to approximately 42 times (mice) and 35 times (rats) those observed in humans at the highest recommended dose of 1 mg/day. In mouse and rat studies, entecavir was positive for carcinogenic findings. In mice, lung adenomas were increased in males and females at exposures 3 and 40 times those in humans.
Lung carcinomas in both male and female mice were increased at exposures 40 times those in humans. Combined lung adenomas and carcinomas were increased in male mice at exposures 3 times and in female mice at exposures 40 times those in humans. Tumor development was preceded by pneumocyte proliferation in the lung, which was not observed in rats, dogs, or monkeys administered entecavir, supporting the conclusion that lung tumors in mice may be a species-specific event.
Hepatocellular carcinomas were increased in males and combined liver adenomas and carcinomas were also increased at exposures 42 times those in humans. Vascular tumors in female mice (hemangiomas of ovaries and uterus and hemangiosarcomas of spleen) were increased at exposures 40 times those in humans. In rats, hepatocellular adenomas were increased in females at exposures 24 times those in humans; combined adenomas and carcinomas were also increased in females at exposures 24 times those in humans.
Brain gliomas were induced in both males and females at exposures 35 and 24 times those in humans. Skin fibromas were induced in females at exposures 4 times those in humans. It is not known how predictive the results of rodent carcinogenicity studies may be for humans.
Mutagenesis Entecavir was clastogenic to human lymphocyte cultures. Entecavir was not mutagenic in the Ames bacterial reverse mutation assay using S. typhimurium and E. coli strains in the presence or absence of metabolic activation, a mammalian-cell gene mutation assay, and a transformation assay with Syrian hamster embryo cells. Entecavir was also negative in an oral micronucleus study and an oral DNA repair study in rats.
Impairment of Fertility In reproductive toxicology studies, in which animals were administered entecavir at up to 30 mg/kg for up to 4 weeks, no evidence of impaired fertility was seen in male or female rats at systemic exposures greater than 90 times those achieved in humans at the highest recommended dose of 1 mg/day. In rodent and dog toxicology studies, seminiferous tubular degeneration was observed at exposures 35 times or greater than those achieved in humans. No testicular changes were evident in monkeys.
📄 Recent Major Changes ▾
RECENT MAJOR CHANGES Indications and Usage (1) 3/2014 Dosage and Administration Recommended Dosage in Pediatric Patients (2.3) 3/2014 Renal Impairment (2.4) 3/2014 Indications and Usage (1) 3/2014 Dosage and Administration Renal Impairment (2.4) 3/2014
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL .5 1
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |