
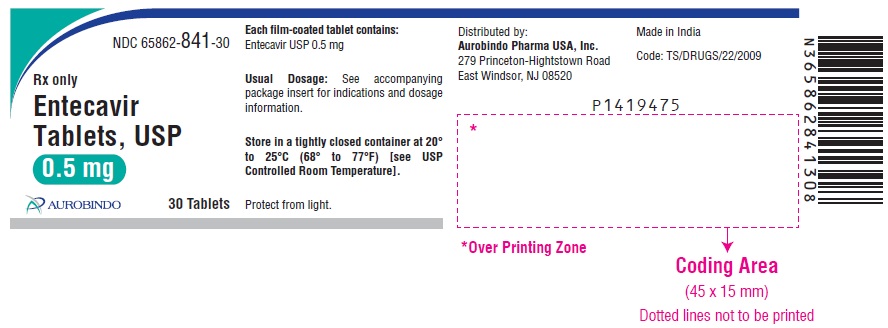
Entecavir .5 mg Tablet, 30-count
Other active recalls for Entecavir (different manufacturers) — 4 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Hepatitis B Virus Nucleoside Analog Reverse Transcriptase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Entecavir is used to treat chronic (long-term) hepatitis B infection (swelling of the liver caused by a virus) in adults and children 2 years of age and older who have liver damage. Entecavir is in a class of medications called nucleoside analogs. It works by decreasing the amount of hepatitis B virus (HBV) in the body. Entecavir does not cure HBV and may not prevent complications of chronic hepatitis B such as cirrhosis of the liver or liver cancer. Entecavir does not prevent the spread of HBV to other people.
Read the full MedlinePlus article ↗- Entecavir treats chronic hepatitis B by suppressing the virus — it keeps the virus from replicating so your liver gets a break and has a chance to recover. It doesn't cure hepatiti...
- What exactly is entecavir treating — does it cure hepatitis B?
- Food — even a light snack — can reduce how much of entecavir your body absorbs and slow it down. To make sure you're getting the full effect of each dose, take it at least 2 hours...
- Why do I have to take it on an empty stomach?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Entecavir — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 68401960MK
Crospovidone is a synthetic polymer made from polyvinylpyrrolidone. It acts as a disintegrant, helping tablets break apart quickly in the stomach so the medicine dissolves and absorbs into the body.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.213 | $6.40 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $2.88 | $86.54 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $1.76 | $52.74 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Entecavir .5 mg 16714-0717-01 | NorthStar | 30 tablets | $0.213 | AB | Availability likely | — |
| Entecavir .5 mg 31722-0833-30 | Camber | 30 tablets | $0.213 | AB | Availability likely | — |
| Entecavir .5 mg 42494-0457-30 | Cameron | 30 tablets | $0.213 | AB | Availability likely | — |
| Entecavir .5 mg 42806-0658-30 | EPIC | 30 tablets | $0.213 | AB | Availability likely | — |
| Entecavir .5 mg 42806-0667-30 | Epic | 30 tablets | $0.213 | AB | Availability likely | — |
| Entecavir .5 mg 43547-0436-03 | Solco | 30 tablets | $0.213 | — | Availability likely | — |
| Entecavir .5 mg 60687-0216-25 | American | 30 tablets | $0.213 | AB | Availability likely | — |
| Entecavir .5 mg 61442-0311-30 | Carlsbad | 30 tablets | $0.213 | AB | Availability likely | — |
| Entecavir .5 mgthis 65862-0841-30 | Aurobindo | 30 tablets | $0.213 | AB | Availability likely | — |
| Entecavir .5 mg 69097-0426-02 | Cipla | 30 tablets | $0.213 | AB | Availability likely | — |
| Entecavir .5 mg 65162-0446-03 | Amneal | 30 tablets | $1.077 | AB | FDA listed | +404% |
| Baraclude .5 mg 00003-1611-12 | E.R. | 30 tablets | $44.187 | AB | Availability likely | +20604% |
| Entecavir .5 mg 42291-0261-30 | AvKARE | 30 tablets | — | AB | FDA listed | — |
| Entecavir .5 mg 50771-0013-01 | Yaopharma | 30 tablets | — | — | FDA listed | — |
| Entecavir .5 mg 51407-0589-30 | Golden | 30 tablets | — | AB | FDA listed | — |
| Entecavir .5 mg 68382-0920-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Entecavir .5 mg 70771-1019-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 65862-0841-30 You're viewing this | 1 BOTTLE in 1 CARTON (65862-841-30) / 30 TABLET in 1 BOTTLE | $0.2134 / ea | $6.40 | 2015-08-26 | Active |
| 65862-0841-90 | 1 BOTTLE in 1 CARTON (65862-841-90) / 90 TABLET in 1 BOTTLE | — | — | 2015-08-26 | Active |
| 65862-0841-99 | 1 BOTTLE in 1 CARTON (65862-841-99) / 1000 TABLET in 1 BOTTLE | — | — | 2015-08-26 | Active |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 65862-0841-30?
What is the difference between NDC 65862-0841-30 and NDC 65862-0841-90?
What NDC number is used to bill for this package of Entecavir .5 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SEVERE ACUTE EXACERBATIONS OF HEPATITIS B, PATIENTS CO-INFECTED WITH HIV AND HBV, and LACTIC ACIDOSIS AND HEPATOMEGALY Severe acute exacerbations of hepatitis B have been reported in patients who have discontinued anti-hepatitis B therapy, including entecavir. Hepatic function should be monitored closely with both clinical and laboratory follow-up for at least several months in patients who discontinue anti-hepatitis B therapy. If appropriate, initiation of anti-hepatitis B therapy may be warranted [see Warnings and Precautions (5.1) ] .
Limited clinical experience suggests there is a potential for the development of resistance to HIV (human immunodeficiency virus) nucleoside reverse transcriptase inhibitors if entecavir is used to treat chronic hepatitis B virus (HBV) infection in patients with HIV infection that is not being treated. Therapy with entecavir is not recommended for HIV/HBV co-infected patients who are not also receiving highly active antiretroviral therapy (HAART) [see Warnings and Precautions (5.2) ] . Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of nucleoside analogue inhibitors alone or in combination with antiretrovirals [see Warnings and Precautions (5.3) ] .
WARNING: SEVERE ACUTE EXACERBATIONS OF HEPATITIS B, PATIENTS CO-INFECTED WITH HIV AND HBV, and LACTIC ACIDOSIS AND HEPATOMEGALY See full prescribing information for complete boxed warning. Severe acute exacerbations of hepatitis B have been reported in patients who have discontinued anti-hepatitis B therapy, including entecavir. Hepatic function should be monitored closely for at least several months after discontinuation.
Initiation of anti-hepatitis B therapy may be warranted. (5.1) Entecavir is not recommended for patients co-infected with human immunodeficiency virus (HIV) and hepatitis B virus (HBV) who are not also receiving highly active antiretroviral therapy (HAART), because of the potential for the development of resistance to HIV nucleoside reverse transcriptase inhibitors. (5.2) Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of nucleoside analogue inhibitors.
(5.3)
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Entecavir tablets are indicated for the treatment of chronic hepatitis B virus infection in adults and pediatric patients 2 years of age and older with evidence of active viral replication and either evidence of persistent elevations in serum aminotransferases (ALT or AST) or histologically active disease. Entecavir is a hepatitis B virus nucleoside analogue reverse transcriptase inhibitor indicated for the treatment of chronic hepatitis B virus infection in adults and children at least 2 years of age with evidence of active viral replication and either evidence of persistent elevations in serum aminotransferases (ALT or AST) or histologically active disease.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Nucleoside-inhibitor-treatment-naïve with compensated liver disease (greater than or equal to 16 years old): 0.5 mg once daily. (2.2) Nucleoside-inhibitor-treatment-naïve and lamivudine-experienced pediatric patients at least 2 years of age and weighing at least 10 kg: dosing is based on weight. ( 2.3 ) Lamivudine-refractory or known lamivudine or telbivudine resistance substitutions (greater than or equal to 16 years old): 1 mg once daily.
(2.2) Decompensated liver disease (adults): 1 mg once daily. ( 2.2) Renal impairment: Dosage adjustment is recommended if creatinine clearance is less than 50 mL/min. (2.4) Entecavir tablets should be administered on an empty stomach.
(2.1)
2.1Timing of Administration Entecavir tablets should be administered on an empty stomach (at least 2 hours after a meal and 2 hours before the next meal).
2.2Recommended Dosage in Adults Compensated Liver Disease The recommended dose of entecavir tablets for chronic hepatitis B virus infection in nucleoside-inhibitor-treatment-naïve adults and adolescents 16 years of age and older is 0.5 mg once daily. The recommended dose of entecavir tablets in adults and adolescents (at least 16 years of age) with a history of hepatitis B viremia while receiving lamivudine or known lamivudine or telbivudine resistance substitutions rtM204I/V with or without rtL180M, rtL80I/V, or rtV173L is 1 mg once daily.
Decompensated Liver Disease The recommended dose of entecavir tablets for chronic hepatitis B virus infection in adults with decompensated liver disease is 1 mg once daily.
2.3Recommended Dosage in Pediatric Patients Table 1 describes the recommended dose of entecavir tablets for pediatric patients 2 years of age or older and weighing at least 10 kg. The oral solution should be used for patients with body weight up to 30 kg. Table 1: Dosing Schedule for Pediatric Patients Recommended Once-Daily Dose of Oral Solution (mL) Body Weight (kg) Treatment-Naïve Patients a Lamivudine-Experienced Patients b 10 to 11 3 6 greater than 11 to 14 4 8 greater than 14 to 17 5 10 greater than 17 to 20 6 12 greater than 20 to 23 7 14 greater than 23 to 26 8 16 greater than 26 to 30 9 18 greater than 30 10 20 a Children with body weight greater than 30 kg should receive 10 mL (0.5 mg) of oral solution or one 0.5 mg tablet once daily. b Children with body weight greater than 30 kg should receive 20 mL (1 mg) of oral solution or one 1 mg tablet once daily.
2.4Renal Impairment In adult subjects with renal impairment, the apparent oral clearance of entecavir decreased as creatinine clearance decreased [see Clinical Pharmacology (12.3) ] . Dosage adjustment is recommended for patients with creatinine clearance less than 50 mL/min, including patients on hemodialysis or continuous ambulatory peritoneal dialysis (CAPD), as shown in Table 2. The once-daily dosing regimens are preferred. b If administered on a hemodialysis day, administer entecavir tablets after the hemodialysis session.
Table 2: Recommended Dosage of Entecavir Tablets in Adult Patients with Renal Impairment Creatinine Clearance (mL/min) Usual Dose (0.5 mg) Lamivudine-Refractory or Decompensated Liver Disease (1 mg) 50 or greater 0.5 mg once daily 1 mg once daily 30 to less than 50 0.5 mg every 48 hours 0.5 mg once daily OR 1 mg every 48 hours 10 to less than 30 0.5 mg every 72 hours 1 mg every 72 hours Less than 10 Hemodialysis b or CAPD 0.5 mg every 7 days 1 mg every 7 days Although there are insufficient data to recommend a specific dose adjustment of entecavir tablets in pediatric patients with renal impairment, a reduction in the dose or an increase in the dosing interval similar to adjustments for adults should be considered.
2.5Hepatic Impairment No dosage adjustment is necessary for patients with hepatic impairment.
2.6Duration of Therapy The optimal duration of treatment with entecavir tablets for patients with chronic hepatitis B virus infection and the relationship between treatment a…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Entecavir Tablets USP 0.5 mg are white, triangular shaped, biconvex, film-coated tablets, debossed with ‘K’ on one side and ‘40’ on the other side. Entecavir Tablets USP 1 mg are white, round shaped, biconvex, film-coated tablets, debossed with ‘K’ on one side and ‘41’ on the other side. Tablets: 0.5 mg and 1 mg (3, 16)
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Severe acute exacerbations of hepatitis B virus infection after discontinuation: Monitor hepatic function closely for at least several months. (5.1, 6.1 ) Co-infection with HIV: Entecavir is not recommended unless the patient is also receiving HAART. (5.2) Lactic acidosis and severe hepatomegaly with steatosis: If suspected, treatment should be suspended. (5.3)
5.1Severe Acute Exacerbations of Hepatitis B Severe acute exacerbations of hepatitis B have been reported in patients who have discontinued anti-hepatitis B therapy, including entecavir [see Adverse Reactions (6.1) ] . Hepatic function should be monitored closely with both clinical and laboratory follow-up for at least several months in patients who discontinue anti-hepatitis B therapy. If appropriate, initiation of anti-hepatitis B therapy may be warranted.
5.2Patients Co-infected with HIV and HBV Entecavir has not been evaluated in HIV/HBV co-infected patients who were not simultaneously receiving effective HIV treatment. Limited clinical experience suggests there is a potential for the development of resistance to HIV nucleoside reverse transcriptase inhibitors if entecavir is used to treat chronic hepatitis B virus infection in patients with HIV infection that is not being treated [see Microbiology (12.4) ] . Therefore, therapy with entecavir is not recommended for HIV/HBV co-infected patients who are not also receiving HAART.
Before initiating entecavir therapy, HIV antibody testing should be offered to all patients. Entecavir has not been studied as a treatment for HIV infection and is not recommended for this use.
5.3Lactic Acidosis and Severe Hepatomegaly with Steatosis Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of nucleoside analogue inhibitors, including entecavir, alone or in combination with antiretrovirals. A majority of these cases have been in women. Obesity and prolonged nucleoside inhibitor exposure may be risk factors.
Particular caution should be exercised when administering nucleoside analogue inhibitors to any patient with known risk factors for liver disease; however, cases have also been reported in patients with no known risk factors. Lactic acidosis with entecavir use has been reported, often in association with hepatic decompensation, other serious medical conditions, or drug exposures. Patients with decompensated liver disease may be at higher risk for lactic acidosis.
Treatment with entecavir should be suspended in any patient who develops clinical or laboratory findings suggestive of lactic acidosis or pronounced hepatotoxicity (which may include hepatomegaly and steatosis even in the absence of marked transaminase elevations).
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in other sections of the labeling: Exacerbations of hepatitis after discontinuation of treatment [see Boxed Warning , Warnings and Precautions (5.1) ] . Lactic acidosis and severe hepatomegaly with steatosis [see Boxed Warning , Warnings and Precautions (5.3) ]. In adults, the most common adverse reactions (≥3%, all severity grades) are headache, fatigue, dizziness, and nausea.
The adverse reactions observed in pediatric patients were consistent with those observed in adults. (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Clinical Trial Experience in Adults Compensated Liver Disease Assessment of adverse reactions is based on four studies (AI463014, AI463022, AI463026, and AI463027) in which 1720 subjects with chronic hepatitis B virus infection and compensated liver disease received double-blind treatment with entecavir 0.5 mg/day (n=679), entecavir 1 mg/day (n=183), or lamivudine (n=858) for up to 2 years.
Median duration of therapy was 69 weeks for entecavir-treated subjects and 63 weeks for lamivudine-treated subjects in Studies AI463022 and AI463027 and 73 weeks for entecavir-treated subjects and 51 weeks for lamivudine-treated subjects in Studies AI463026 and AI463014. The safety profiles of entecavir and lamivudine were comparable in these studies. The most common adverse reactions of any severity (≥3%) with at least a possible relation to study drug for entecavir-treated subjects were headache, fatigue, dizziness, and nausea.
The most common adverse reactions among lamivudine-treated subjects were headache, fatigue, and dizziness. One percent of entecavir-treated subjects in these four studies compared with 4% of lamivudine-treated subjects discontinued for adverse events or abnormal laboratory test results. Clinical adverse reactions of moderate-severe intensity and considered at least possibly related to treatment occurring during therapy in four clinical studies in which entecavir was compared with lamivudine are presented in Table 3.
Table 3: Clinical Adverse Reactions a of Moderate-Severe Intensity (Grades 2 to 4) Reported in Four Entecavir Clinical Trials Through 2 Years a Includes events of possible, probable, certain, or unknown relationship to treatment regimen. b Studies AI463022 and AI463027. c Includes Study AI463026 and the entecavir 1 mg and lamivudine treatment arms of Study AI463014, a Phase 2 multinational, randomized, double-blind study of three doses of entecavir (0.1, 0.5, and 1 mg) once daily versus continued lamivudine 100 mg once daily for up to 52 weeks in subjects who experienced recurrent viremia on lamivudine therapy.
Body System/ Adverse Reaction Nucleoside-Inhibitor-Naïve b Lamivudine-Refractory c Entecavir 0.5 mg n=679 Lamivudine 100 mg n=668 Entecavir 1 mg n=183 Lamivudine 100 mg n=190 Any Grade 2 to 4 adverse reaction a 15% 18% 22% 23% Gastrointestinal Diarrhea <1% 0 1% 0 Dyspepsia <1% <1% 1% 0 Nausea <1% <1% <1% 2% Vomiting <1% <1% <1% 0 General Fatigue 1% 1% 3% 3% Nervous System Headache 2% 2% 4% 1% Dizziness <1% <1% 0 1% Somnolence <1% <1% 0 0 Psychiatric Insomnia <1% <1% 0 <1% Laboratory Abnormalities Frequencies of selected treatment-emergent laboratory abnormalities reported during therapy in four clinical trials of entecavir compared with lamivudine are listed in Table 4.
Table 4: Selected Treatment-Emergent a Laboratory Abnormalities Reported in Four Entecavir Clinical Trials Through 2 Years a On-treatment value worsened from baseline to Grade 3 or Grade 4 for all parameters except albumin (any on-treatment value <2.5 g/dL), con…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Since entecavir is primarily eliminated by the kidneys [see Clinical Pharmacology (12.3) ] , coadministration of entecavir with drugs that reduce renal function or compete for active tubular secretion may increase serum concentrations of either entecavir or the coadministered drug. Coadministration of entecavir with lamivudine, adefovir dipivoxil, or tenofovir disoproxil fumarate did not result in significant drug interactions. The effects of coadministration of entecavir with other drugs that are renally eliminated or are known to affect renal function have not been evaluated, and patients should be monitored closely for adverse events when entecavir is coadministered with such drugs.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Liver transplant recipients: Limited data on safety and efficacy are available. ( 8.8 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to entecavir during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Prospective pregnancy data from the APR are not sufficient to adequately assess the risk of birth defects, miscarriage or adverse maternal or fetal outcomes.
Entecavir use during pregnancy has been evaluated in a limited number of individuals reported to the APR and the number of exposures to entecavir is insufficient to make a risk assessment compared to a reference population. The estimated background rate for major birth defects is 2.7% in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP). The rate of miscarriage is not reported in the APR.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of miscarriage in clinically recognized pregnancies is 15 to 20%. In animal reproduction studies, no adverse developmental effects were observed with entecavir at clinically relevant exposures.
No developmental toxicities were observed at systemic exposures (AUC) approximately 25 (rats) and 200 (rabbits) times the exposure at the maximum recommended human dose (MRHD) of 1 mg/day ( see Data ). Data Animal Data Entecavir was administered orally to pregnant rats (at 2, 20, and 200 mg per kg per day) and rabbits (at 1, 4, and 16 mg per kg per day) during organogenesis (on gestation Days 6 through 15 [rat] and 6 through 18 [rabbit]). In rats, embryofetal toxicity including post-implantation loss, resorptions, tail and vertebral malformations, skeletal variations including reduced ossification (vertebrate, sternebrae, and phalanges) and extra lumbar vertebrae and ribs, and lower fetal body weights were observed at systemic exposures (AUC) 3,100 times those in humans at the MRHD.
Maternal toxicity was also observed at this dose level. In rabbits, embryofetal toxicity including post-implantation loss, resorptions and skeletal variations, including reduced ossification (hyoid) and increased incidence of 13 th rib, were observed at systemic exposures (AUC) 883 times those in humans at the MRHD. There were no signs of embryofetal toxicity when pregnant animals received oral entecavir at 28 (rat) and 212 (rabbit) times the human exposure (AUC) at the MRHD.
In a pre/postnatal development study, entecavir was administered orally to pregnant rats at 0.3, 3, and 30 mg per kg per day from gestation day 6 to lactation/post-partum day 20. No adverse effects on the offspring occurred at up to the highest dose evaluated, resulting in exposures (AUC) greater than 94 times those in humans at the MRHD.
8.2Lactation Risk Summary It is not known whether entecavir is present in human breast milk, affects human milk production, or has effects on the breastfed infant. When administered to lactating rats, entecavir was present in milk ( see Data ). The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for entecavir and any potential adverse effects on the breastfed infant from entecavir or from the underlying maternal condition .
Data Entecavir was excreted into the milk of lactating rats following a single oral dose of 10 mg per kg on lactation day 7. Entecavir in milk was approximately 25% that in maternal plasma (based on AUC).
8.4Pediatric Use Entecavir was evaluated in two clinical trials of pediatric subjects 2 years of age and older with HBeAg-positive chronic HBV infection and compensated liver disease. The exposure of entecavir in nucleoside-inhibitor-treatment-naïve and lamivudine-experienced pediatric subjects 2 years of age and older with…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to entecavir during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Prospective pregnancy data from the APR are not sufficient to adequately assess the risk of birth defects, miscarriage or adverse maternal or fetal outcomes.
Entecavir use during pregnancy has been evaluated in a limited number of individuals reported to the APR and the number of exposures to entecavir is insufficient to make a risk assessment compared to a reference population. The estimated background rate for major birth defects is 2.7% in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP). The rate of miscarriage is not reported in the APR.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of miscarriage in clinically recognized pregnancies is 15 to 20%. In animal reproduction studies, no adverse developmental effects were observed with entecavir at clinically relevant exposures.
No developmental toxicities were observed at systemic exposures (AUC) approximately 25 (rats) and 200 (rabbits) times the exposure at the maximum recommended human dose (MRHD) of 1 mg/day ( see Data ). Data Animal Data Entecavir was administered orally to pregnant rats (at 2, 20, and 200 mg per kg per day) and rabbits (at 1, 4, and 16 mg per kg per day) during organogenesis (on gestation Days 6 through 15 [rat] and 6 through 18 [rabbit]). In rats, embryofetal toxicity including post-implantation loss, resorptions, tail and vertebral malformations, skeletal variations including reduced ossification (vertebrate, sternebrae, and phalanges) and extra lumbar vertebrae and ribs, and lower fetal body weights were observed at systemic exposures (AUC) 3,100 times those in humans at the MRHD.
Maternal toxicity was also observed at this dose level. In rabbits, embryofetal toxicity including post-implantation loss, resorptions and skeletal variations, including reduced ossification (hyoid) and increased incidence of 13 th rib, were observed at systemic exposures (AUC) 883 times those in humans at the MRHD. There were no signs of embryofetal toxicity when pregnant animals received oral entecavir at 28 (rat) and 212 (rabbit) times the human exposure (AUC) at the MRHD.
In a pre/postnatal development study, entecavir was administered orally to pregnant rats at 0.3, 3, and 30 mg per kg per day from gestation day 6 to lactation/post-partum day 20. No adverse effects on the offspring occurred at up to the highest dose evaluated, resulting in exposures (AUC) greater than 94 times those in humans at the MRHD.
🧒 Pediatric Use ▾
8.4Pediatric Use Entecavir was evaluated in two clinical trials of pediatric subjects 2 years of age and older with HBeAg-positive chronic HBV infection and compensated liver disease. The exposure of entecavir in nucleoside-inhibitor-treatment-naïve and lamivudine-experienced pediatric subjects 2 years of age and older with HBeAg-positive chronic HBV infection and compensated liver disease receiving 0.015 mg/kg (up to 0.5 mg once daily) or 0.03 mg/kg (up to 1 mg once daily), respectively, was evaluated in Study AI463028.
Safety and efficacy of the selected dose in treatment-naïve pediatric subjects were confirmed in Study AI463189, a randomized, placebo-controlled treatment trial [see Indications and Usage (1) , Dosage and Administration (2.3) , Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , and Clinical Studies (14.2) ]. There are limited data available on the use of entecavir in lamivudine-experienced pediatric patients; entecavir should be used in these patients only if the potential benefit justifies the potential risk to the child.
Since some pediatric patients may require long-term or even lifetime management of chronic active hepatitis B, consideration should be given to the impact of entecavir on future treatment options [see Microbiology (12.4) ]. The efficacy and safety of entecavir have not been established in patients less than 2 years of age. Use of entecavir in this age group has not been evaluated because treatment of HBV in this age group is rarely required.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of entecavir did not include sufficient numbers of subjects aged 65 years and over to determine whether they respond differently from younger subjects. Entecavir is substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function [see Dosage and Administration (2.4) ] .
🆘 Overdosage ▾
10 OVERDOSAGE There is limited experience of entecavir overdosage reported in patients. Healthy subjects who received single entecavir doses up to 40 mg or multiple doses up to 20 mg/day for up to 14 days had no increase in or unexpected adverse events. If overdose occurs, the patient must be monitored for evidence of toxicity, and standard supportive treatment applied as necessary.
Following a single 1 mg dose of entecavir, a 4-hour hemodialysis session removed approximately 13% of the entecavir dose.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Entecavir is an antiviral drug against hepatitis B virus [see Microbiology (12.4) ].
12.3Pharmacokinetics The single- and multiple-dose pharmacokinetics of entecavir were evaluated in healthy subjects and subjects with chronic hepatitis B virus infection. Absorption Following oral administration in healthy subjects, entecavir peak plasma concentrations occurred between 0.5 and 1.5 hours. Following multiple daily doses ranging from 0.1 to 1 mg, C max and area under the concentration-time curve (AUC) at steady state increased in proportion to dose.
Steady state was achieved after 6 to 10 days of once-daily administration with approximately 2-fold accumulation. For a 0.5 mg oral dose, C max at steady state was 4.2 ng/mL and trough plasma concentration (C trough ) was 0.3 ng/mL. For a 1 mg oral dose, C max was 8.2 ng/mL and C trough was 0.5 ng/mL.
Effects of food on oral absorption: Oral administration of 0.5 mg of entecavir with a standard high-fat meal (945 kcal, 54.6 g fat) or a light meal (379 kcal, 8.2 g fat) resulted in a delay in absorption (1 to 1.5 hours fed vs. 0.75 hours fasted), a decrease in C max of 44% to 46%, and a decrease in AUC of 18% to 20% [see Dosage and Administration (2) ] . Distribution Based on the pharmacokinetic profile of entecavir after oral dosing, the estimated apparent volume of distribution is in excess of total body water, suggesting that entecavir is extensively distributed into tissues.
Binding of entecavir to human serum proteins in vitro was approximately 13%. Metabolism and Elimination Following administration of 14 C-entecavir in humans and rats, no oxidative or acetylated metabolites were observed. Minor amounts of phase II metabolites (glucuronide and sulfate conjugates) were observed.
Entecavir is not a substrate, inhibitor, or inducer of the cytochrome P450 (CYP450) enzyme system. See Drug Interactions, below . After reaching peak concentration, entecavir plasma concentrations decreased in a bi-exponential manner with a terminal elimination half-life of approximately 128 to 149 hours.
The observed drug accumulation index is approximately 2-fold with once-daily dosing, suggesting an effective accumulation half-life of approximately 24 hours. Entecavir is predominantly eliminated by the kidney with urinary recovery of unchanged drug at steady state ranging from 62% to 73% of the administered dose. Renal clearance is independent of dose and ranges from 360 to 471 mL/min suggesting that entecavir undergoes both glomerular filtration and net tubular secretion [see Drug Interactions (7) ] .
Special Populations Gender: There are no significant gender differences in entecavir pharmacokinetics. R ace: There are no significant racial differences in entecavir pharmacokinetics. Elderly: The effect of age on the pharmacokinetics of entecavir was evaluated following administration of a single 1 mg oral dose in healthy young and elderly volunteers.
Entecavir AUC was 29.3% greater in elderly subjects compared to young subjects. The disparity in exposure between elderly and young subjects was most likely attributable to differences in renal function. Dosage adjustment of entecavir should be based on the renal function of the patient, rather than age [see Dosage and Administration (2.4) ] .
Pediatrics: The steady-state pharmacokinetics of entecavir were evaluated in nucleosideinhibitor-naïve and lamivudine-experienced HBeAg-positive pediatric subjects 2 to less than 18 years of age with compensated liver disease. Results are shown in Table 7. Entecavir exposure among nucleoside-inhibitor-naïve subjects was similar to the exposure achieved in adults receiving once-daily doses of 0.5 mg.
Entecavir exposure among lamivudine-experienced subjects was similar to the exposure achieved in adults receiving once-daily doses of 1 mg. a Subjects received once-daily doses of 0.015 mg/kg up to a maximum of 0.5 mg. b Subjects received once-daily doses of 0.030 mg/kg up…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Entecavir is an antiviral drug against hepatitis B virus [see Microbiology (12.4) ].
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Entecavir Tablets USP 0.5 mg are white, triangular shaped, biconvex, film-coated tablets, debossed with ‘K’ on one side and ‘40’ on the other side. Bottles of 30 NDC 65862-841-30 Bottles of 90 NDC 65862-841-90 Bottles of 1,000 NDC 65862-841-99 Entecavir Tablets USP 1 mg are white, round shaped, biconvex, film-coated tablets, debossed with ‘K’ on one side and ‘41’ on the other side. Bottles of 30 NDC 65862-842-30 Bottles of 90 NDC 65862-842-90 Bottles of 1,000 NDC 65862-842-99 Storage Entecavir tablets USP should be stored in a tightly closed container at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
Store in the outer carton to protect from light.
📋 Description ▾
11 DESCRIPTION Entecavir is a guanosine nucleoside analogue with selective activity against HBV. The chemical name for entecavir is 2-amino-1,9-dihydro-9-[( 1S,3R,4S )-4-hydroxy-3-(hydroxymethyl)-2-methylenecyclopentyl]-6 H -purin-6-one, monohydrate. Its molecular formula is C 12 H 15 N 5 O 3 •H 2 O, which corresponds to a molecular weight of 295.3.
Entecavir has the following structural formula: Entecavir USP is a white to off-white powder. It is slightly soluble in water (2.4 mg/mL), and the pH of the saturated solution in water is 7.9 at 25°C ± 0.5°C. Entecavir film-coated tablets are available for oral administration in strengths of 0.5 mg and 1 mg of entecavir USP.
Entecavir 0.5 mg and 1 mg film-coated tablets contain the following inactive ingredients: crospovidone, hypromellose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, polyethylene glycol, and titanium dioxide. Meets USP Dissolution Test 2. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-approved patient labeling (Patient Information). Severe Acute Exacerbation of Hepatitis after Discontinuation of Treatment Inform patients that discontinuation of anti-hepatitis B therapy, including entecavir, may result in severe acute exacerbations of hepatitis B. Advise the patient to not discontinue entecavir without first informing their healthcare provider [see Warnings and Precautions (5.1) ] .
Risk of Development of HIV-1 Resistance in Patients with HIV-1 Coinfection Inform patients that if they have or develop HIV infection and are not receiving effective HIV treatment, entecavir may increase the risk of development of resistance to HIV medication [see Warnings and Precautions (5.2) ] . Lactic Acidosis and Severe Hepatomegaly Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with use of drugs similar to entecavir. Advise patients to contact their healthcare provider immediately and stop entecavir if they develop clinical symptoms suggestive of lactic acidosis or pronounced hepatotoxicity [see Warnings and Precautions (5.3) ] .
Missed Dosage Inform patients that it is important to take entecavir on a regular dosing schedule on an empty stomach (at least 2 hours after a meal and 2 hours before the next meal) and to avoid missing doses as it can result in development of resistance [see Dosage and Administration (2.1) ] . Treatment Duration Advise patients that in the treatment of chronic hepatitis B, the optimal duration of treatment is unknown. The relationship between response and long-term prevention of outcomes such as hepatocellular carcinoma is not known.
Instructions for Use Inform patients using the oral solution to hold the dosing spoon in a vertical position and fill it gradually to the mark corresponding to the prescribed dose. Rinsing of the dosing spoon with water is recommended after each daily dose. Some patients may find it difficult to accurately measure the prescribed dose using the provided dosing spoon; therefore, patients/caregivers should refer to the steps in the Patient Information section that demonstrate the correct technique of using the provided dosing spoon to measure the prescribed entecavir dose.
Pregnancy Registry Advise patients that there is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to entecavir during pregnancy [see Use in Specific Populations (8.1) ] .