
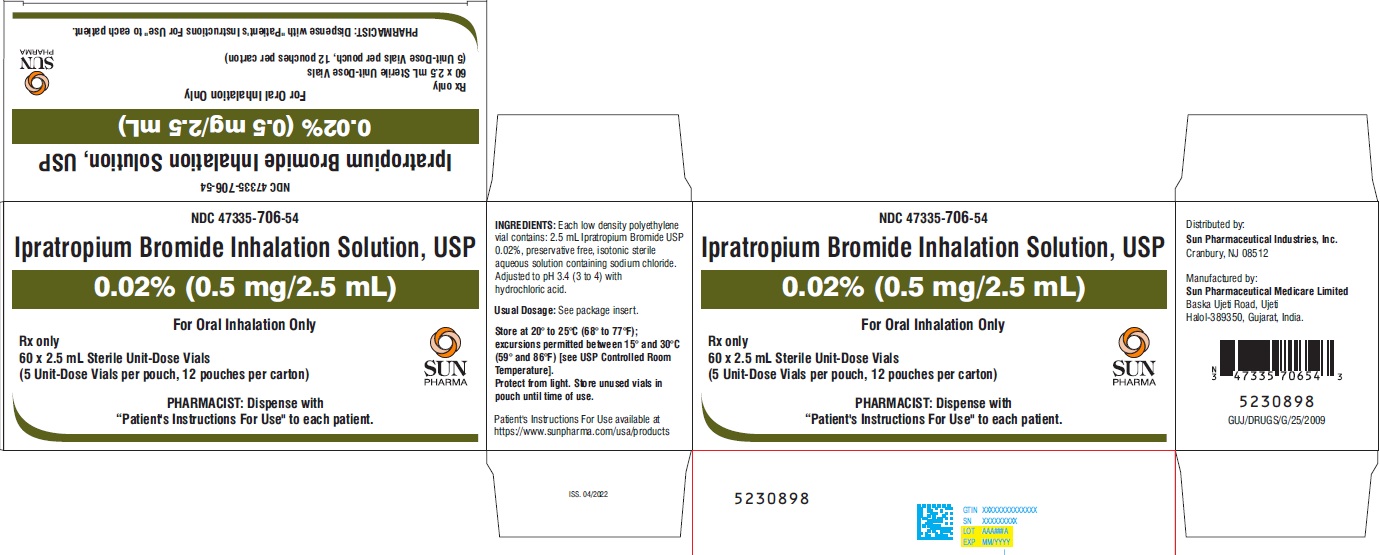
Ipratropium Bromide .5 mg/2.5mL Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Anticholinergic class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Ipratropium oral inhalation is used to prevent wheezing, shortness of breath, coughing, and chest tightness in people with chronic obstructive pulmonary disease (COPD; a group of diseases that affect the lungs and airways) such as chronic bronchitis (swelling of the air passages that lead to the lungs) and emphysema (damage to the air sacs in the lungs). Ipratropium is in a class of medications called bronchodilators. It works by relaxing and opening the air passages to the lungs to make breathing easier.
Read the full MedlinePlus article ↗- It depends on the form you were prescribed. The inhaler (like Atrovent HFA) and the nebulizer solution are used every day to help keep the airways open if you have COPD — condition...
- What is ipratropium actually used for — is it for my COPD or my runny nose?
- No — the inhaler is a maintenance medication, meaning it's meant to be used on a regular schedule to prevent breathing problems, not to rescue you during a sudden flare-up. If you'...
- Can I use my ipratropium inhaler during a sudden asthma or COPD attack when I can't breathe?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.104 | $7.80 / 75 ml |
| Medicaid paysCMS SDUD · 12 mo | $0.1074 | $8.06 / 75 ml |
| Medicare drug plans payPart D · Q2 2026 | $0.1185 | $8.89 / 75 ml |
| Medicare Part B allowsASP · J7644 | $0.444 / J7644 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ipratropium Bromide .5 mg/2.5mLthis 47335-0706-52 | Sun | 6 pouches | $0.104 | — | FDA listed | — |
| Ipratropium Bromide .5 mg/2.5mL 00378-7970-52 | Mylan | 1 pouch | $0.106 | AN | Availability likely | +2% |
| Ipratropium Bromide .5 mg/2.5mL 64980-0640-02 | Rising | 1 pouch | $0.106 | AN | Availability likely | +2% |
| Ipratropium Bromide .5 mg/2.5mL 00487-9801-01 | Nephron | 30 pouches | $0.114 | AN | Availability likely | +10% |
| Ipratropium Bromide .5 mg/2.5mL 60687-0394-83 | American | 30 pouches | $0.114 | AN | Availability likely | +10% |
| Ipratropium Bromide .5 mg/2.5mL 62135-0830-84 | Chartwell | 6 pouches | $0.114 | AN | Availability likely | +10% |
| Ipratropium Bromide .5 mg/2.5mL 76204-0100-01 | Ritedose | 30 pouches | $0.114 | AN | Availability likely | +10% |
| Ipratropium Bromide .5 mg/2.5mL 50090-0668-00 | A-S | 1 pouch | — | AN | FDA listed | — |
| Ipratropium Bromide .5 mg/2.5mL 50090-6373-00 | A-S | 25 pouches | — | AN | FDA listed | — |
| Ipratropium Bromide .5 mg/2.5mL 55154-2134-05 | Cardinal | 5 pouches | — | AN | FDA listed | — |
| Ipratropium bromide .5 mg/2.5mL 65862-0905-03 | Aurobindo | 30 pouches | — | AN | FDA listed | — |
| Ipratropium Bromide .5 mg/2.5mL 67296-2246-01 | Redpharm | 1 pouch | — | AN | FDA listed | — |
| Ipratropium Bromide .5 mg/2.5mL 68071-3769-02 | NuCare | 25 ampules | — | AN | FDA listed | — |
| Ipratropium Bromide .5 mg/2.5mL 55154-4411-05 | Cardinal | 5 pouches | — | AN | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 47335-0706-49 | 5 POUCH in 1 CARTON (47335-706-49) / 5 VIAL in 1 POUCH (47335-706-48) / 2.5 mL in 1 VIAL | $0.0950 / mL | $5.94 | 2020-02-04 | Active |
| 47335-0706-52 You're viewing this | 6 POUCH in 1 CARTON (47335-706-52) / 5 VIAL in 1 POUCH / 2.5 mL in 1 VIAL | $0.1040 / mL | $7.80 | 2020-02-04 | Active |
| 47335-0706-54 | 12 POUCH in 1 CARTON (47335-706-54) / 5 VIAL in 1 POUCH / 2.5 mL in 1 VIAL | $0.1012 / mL | $15.19 | 2020-02-04 | Active |
Per mL, this pack runs about 9% above the cheapest pack (NDC 47335-0706-49, $0.0950 vs $0.1040 NADAC).
This pack accounts for about 36% of this product's recent Medicaid fills; the largest share goes to a different pack size. See all packs ↓
Pack size FAQ
What quantity is in NDC 47335-0706-52?
What NDC number is used to bill for this package of Ipratropium Bromide .5 mg/2.5mL Solution?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Ipratropium Bromide Inhalation Solution administered either alone or with other bronchodilators, especially beta adrenergics, is indicated as a bronchodilator for maintenance treatment of bronchospasm associated with chronic obstructive pulmonary disease, including chronic bronchitis and emphysema.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The usual dosage of Ipratropium Bromide Inhalation Solution is 500 mcg (1 Unit-Dose Vial) administered three to four times a day by oral nebulization, with doses 6 to 8 hours apart. Ipratropium Bromide Inhalation Solution Unit-Dose Vials contain 500 mcg ipratropium bromide, USP anhydrous in 2.5 mL normal saline. Ipratropium Bromide Inhalation Solution can be mixed in the nebulizer with albuterol or metaproterenol if used within one hour.
Drug stability and safety of Ipratropium Bromide Inhalation Solution when mixed with other drugs in a nebulizer have not been established.
⛔ Contraindications ▾
CONTRAINDICATIONS Ipratropium bromide is contraindicated in known or suspected cases of hypersensitivity to ipratropium bromide, or to atropine and its derivatives.
⚠️ Warnings ▾
WARNINGS The use of Ipratropium Bromide Inhalation Solution as a single agent for the relief of bronchospasm in acute COPD exacerbation has not been adequately studied. Drugs with faster onset of action may be preferable as initial therapy in this situation. Combination of Ipratropium Bromide Inhalation Solution and beta agonists has not been shown to be more effective than either drug alone in reversing the bronchospasm associated with acute COPD exacerbation.
Immediate hypersensitivity reactions may occur after administration of ipratropium bromide, as demonstrated by rare cases of urticaria, angioedema, rash, bronchospasm and oropharyngeal edema.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Adverse reaction information concerning Ipratropium Bromide Inhalation Solution is derived from 12-week active-controlled clinical trials. Additional information is derived from foreign postmarketing experience and the published literature. All adverse events, regardless of drug relationship, reported by three percent or more patients in the 12-week controlled clinical trials appear in the table.
Additional adverse reactions reported in less than three percent of the patients treated with ipratropium bromide include tachycardia, palpitations, eye pain, urinary retention, urinary tract infection and urticaria. Cases of precipitation or worsening of narrow-angle glaucoma, mydriasis, and acute eye pain have been reported. Lower respiratory adverse reactions (bronchitis, dyspnea and bronchospasm) were the most common events leading to discontinuation of ipratropium bromide therapy in the 12-week trials.
Headache, mouth dryness and aggravation of COPD symptoms are more common when the total daily dose of ipratropium bromide equals or exceeds 2,000 mcg. Allergic-type reactions such as skin rash, angioedema of tongue, lips and face, urticaria, laryngospasm and anaphylactic reaction have been reported. Many of the patients had a history of allergies to other drugs and/or foods.
All Adverse Events, From a Double-blind, Parallel, 12-week Study of Patients with COPD All adverse events, regardless of drug relationship, reported by the three percent or more patients in the 12-week controlled clinical trials. PERCENT OF PATIENTS Ipratropium Bromide (500 mcg t.i.d.) n = 219 Metaproterenol (15 mg t.i.d.) n = 212 Ipratropium Bromide/ Metaproterenol (500 mcg t.i.d./15 mg t.i.d.) n = 108 Albuterol (2.5 mg t.i.d.) n = 205 Ipratropium Bromide/ Albuterol (500 mcg t.i.d./2.5 mg t.i.d.) n = 100 Body as a Whole-General Disorders Headache 6.4 5.2 6.5 6.3 9 Pain 4.1 3.3 0.9 2.9 5 Influenza-like symptoms 3.7 4.7 6.5 0.5 1 Back Pain 3.2 1.9 1.9 2.4 0 Chest Pain 3.2 4.2 5.6 2 1 Cardiovascular Disorders Hypertension/hypertension Aggravated 0.9 1.9 0.9 1.5 4 Central & Peripheral Nervous System Dizziness 2.3 3.3 1.9 3.9 4 Insomnia 0.9 0.5 4.6 1 1 Tremor 0.9 7.1 8.3 1 0 Nervousness 0.5 4.7 6.5 1 1 Gastrointestinal System Disorders Mouth Dryness 3.2 0 1.9 2 3 Nausea 4.1 3.8 1.9 2.9 2 Constipation 0.9 0 3.7 1 1 Musculo-skeletal System Disorders Arthritis 0.9 1.4 0.9 0.5 3 Respiratory System Disorders (Lower) Coughing 4.6 8 6.5 5.4 6 Dyspnea 9.6 13.2 16.7 12.7 9 Bronchitis 14.6 24.5 15.7 16.6 20 Bronchospasm 2.3 2.8 4.6 5.4 5 Sputum Increased 1.4 1.4 4.6 3.4 0 Respiratory Disorder 0 6.1 6.5 2 4 Respiratory System Disorders (Upper) Upper Respiratory Tract Infection 13.2 11.3 9.3 12.2 16 Pharyngitis 3.7 4.2 5.6 2.9 4 Rhinitis 2.3 4.2 1.9 2.4 0 Sinusitis 2.3 2.8 0.9 5.4 4
🔄 Drug Interactions ▾
Drug Interactions Ipratropium bromide has been shown to be a safe and effective bronchodilator when used in conjunction with beta adrenergic bronchodilators. Ipratropium bromide has also been used with other pulmonary medications, including methylxanthines and corticosteroids, without adverse drug interactions.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Oral reproduction studies performed in mice, rats and rabbits at doses of 10, 100, and 125 mg/kg respectively and inhalation reproduction studies in rats and rabbits at doses of 1.5 and 1.8 mg/kg (or approximately 38 and 45 times the recommended human daily dose) respectively, have demonstrated no evidence of teratogenic effects as a result of ipratropium bromide. However, no adequate or well controlled studies have been conducted in pregnant women. Because animal reproduction studies are not always predictive of human response, ipratropium bromide should be used during pregnancy only if clearly needed.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in pediatric patients below the age of 12 have not been established.
🆘 Overdosage ▾
OVERDOSAGE Acute systemic overdosage by inhalation is unlikely since ipratropium bromide is not well absorbed after inhalation at up to four-fold the recommended dose, or after oral administration at up to forty-fold the recommended dose. The oral LD 50 of ipratropium bromide ranged between 1,001 and 2,010 mg/kg in mice; between 1,667 and 4,000 mg/kg in rats; and between 400 and 1,300 mg/kg in dogs.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Ipratropium Bromide Inhalation Solution is an anticholinergic (parasympatholytic) agent that, based on animal studies, appears to inhibit vagally-mediated reflexes by antagonizing the action of acetylcholine, the transmitter agent released from the vagus nerve. Anticholinergics prevent the increases in intracellular concentration of cyclic guanosine monophosphate (cyclic GMP) which are caused by interaction of acetylcholine with the muscarinic receptor on bronchial smooth muscle. The bronchodilation following inhalation of Ipratropium Bromide Inhalation Solution is primarily a local, site-specific effect, not a systemic one.
Much of an administered dose is swallowed but not absorbed as shown by fecal excretion studies. Following nebulization of a 2 mg dose, a mean 7% of the dose was absorbed into the systemic circulation either from the surface of the lung or from the gastrointestinal tract. The half-life of elimination is about 1.6 hours after intravenous administration.
Ipratropium bromide is minimally (0 to 9% in vitro) bound to plasma albumin and α 1 –acid glycoproteins. It is partially metabolized. Autoradiographic studies in rats have shown that ipratropium bromide does not penetrate the blood-brain barrier.
Ipratropium Bromide Inhalation Solution has not been studied in patients with hepatic or renal insufficiency. It should be used with caution in those patient populations. In controlled twelve-week studies in patients with bronchospasm associated with chronic obstructive pulmonary disease (chronic bronchitis and emphysema) significant improvements in pulmonary function (FEV 1 increases of 15% or more) occurred within 15 to 30 minutes, reached a peak in 1 to 2 hours and persisted for periods of 4 to 5 hours in the majority of patients, with about 25 to 38% of the patients demonstrating increases of 15% or more for at least 7 to 8 hours.
Continued effectiveness of ipratropium bromide was demonstrated throughout the 12-week period. In addition, significant increases in forced vital capacity (FVC) have been demonstrated. However, ipratropium bromide did not consistently produce significant improvement in subjective symptom scores nor in quality of life scores over the 12-week duration of study.
Additional controlled 12-week studies were conducted to evaluate the safety and effectiveness of Ipratropium Bromide Inhalation Solution administered concomitantly with the beta adrenergic bronchodilator solutions metaproterenol and albuterol compared with the administration of each of the beta agonists alone. Combined therapy produced significant additional improvement in FEV 1 and FVC. On combined therapy, the median duration of 15% improvement in FEV 1 was 5 to 7 hours, compared with 3 to 4 hours in patients receiving a beta agonist alone.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Ipratropium Bromide Inhalation Solution, USP is a clear, colorless solution supplied in a unit-dose vial containing 2.5 mL. Supplied in cartons as listed below: NDC 47335-706-49 carton of 25 vials (5 vials per foil pouch) NDC 47335-706-52 carton of 30 vials (5 vials per foil pouch) NDC 47335-706-54 carton of 60 vials (5 vials per foil pouch) Each vial is made from a low density polyethylene (LDPE) resin. Store at 20° to 25°C (68° to 77°F); excursions permitted between 15° and 30°C (59° and 86°F) [see USP Controlled Room Temperature].
Protect from light. Store in pouch until time of use. Dispense with Patient's Instructions For Use available at: https://www.sunpharma.com/usa/products
📋 Description ▾
DESCRIPTION The active ingredient in Ipratropium Bromide Inhalation Solution, USP is ipratropium bromide monohydrate, USP. It is an anticholinergic bronchodilator chemically described as 8-azoniabicyclo[3.2.1]-octane,3-(3-hydroxy-1-oxo-2-phenylpropoxy)-8-methyl-8-(1- methylethyl)-, bromide, monohydrate (endo, syn)-,(±)-; a synthetic quaternary ammonium compound, chemically related to atropine. Ipratropium bromide is a white crystalline substance, freely soluble in water and lower alcohols.
It is a quaternary ammonium compound and thus exists in an ionized state in aqueous solutions. It is relatively insoluble in non-polar media. Ipratropium Bromide Inhalation Solution, USP is administered by oral inhalation with the aid of a nebulizer.
Each mL contains ipratropium bromide, USP 0.02% (anhydrous basis) in a sterile, preservative-free, isotonic saline solution, pH adjusted to 3.4 (3 to 4) with hydrochloric acid. structure
💬 Information for Patients ▾
Information for Patients Patients should be advised that mydriasis, temporary blurring of vision, precipitation or worsening of narrow-angle glaucoma or eye pain may result if the solution comes into direct contact with the eyes. Use of a nebulizer with mouthpiece rather than face mask may be preferable, to reduce the likelihood of the nebulizer solution reaching the eyes. Patients should be advised that Ipratropium Bromide Inhalation Solution can be mixed in the nebulizer with albuterol or metaproterenol if used within one hour.
Drug stability and safety of Ipratropium Bromide inhalation solution when mixed with other drugs in a nebulizer have not been established. Patients should be reminded that Ipratropium Bromide Inhalation Solution should be used consistently as prescribed throughout the course of therapy.