
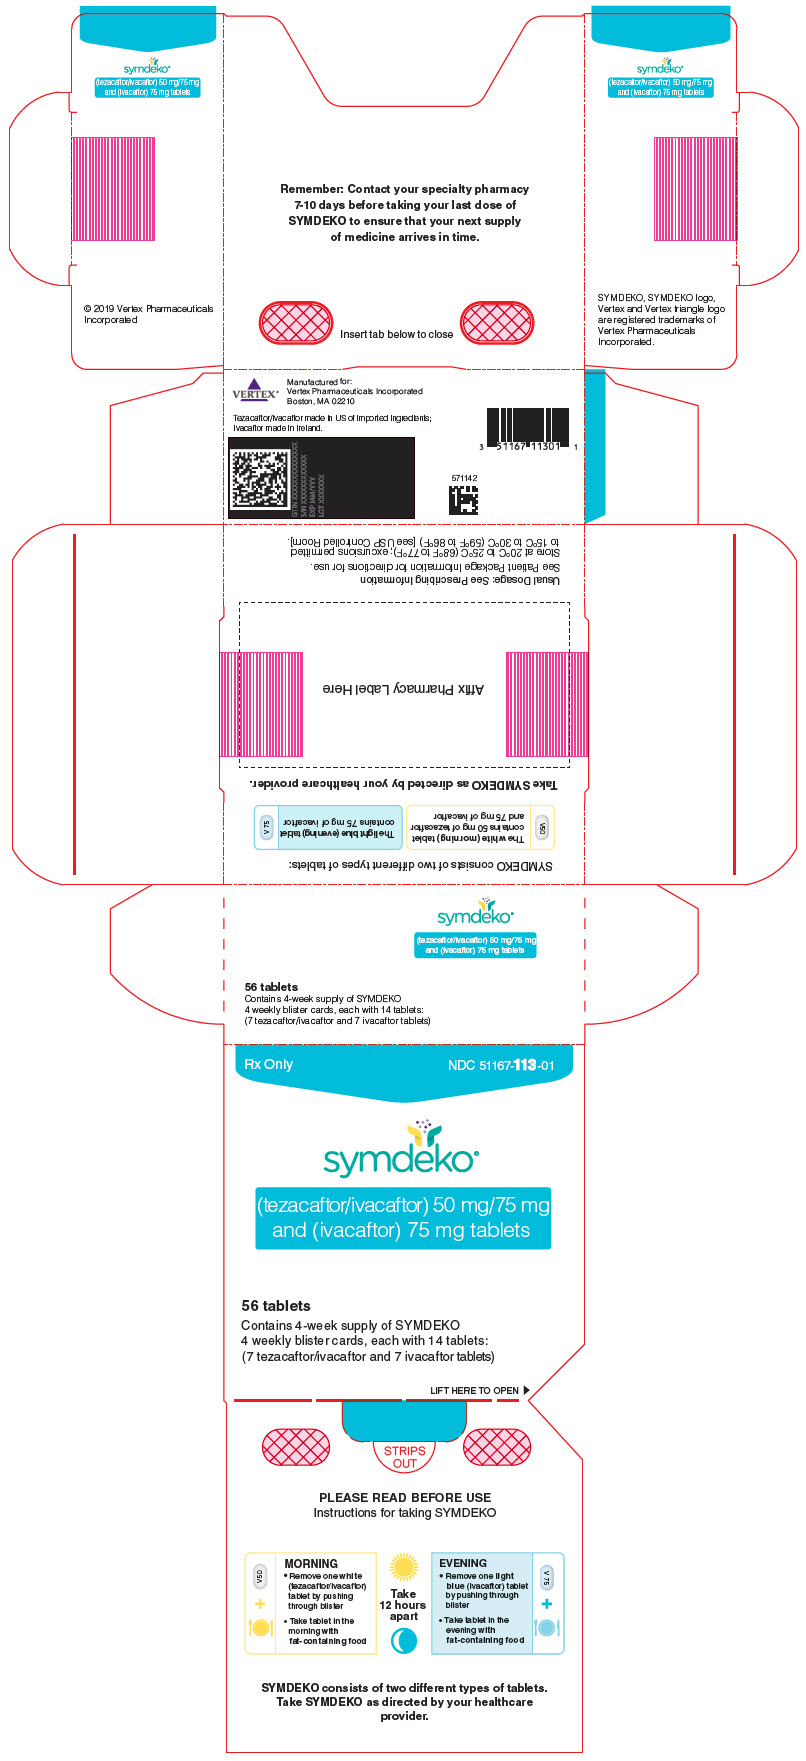
SYMDEKO Tezacaftor and Ivacaftor Kit — NDC 51167-113-01 (Billing 51167-0113-01)
This is a package of SYMDEKO Tezacaftor and Ivacaftor Kit from Vertex Pharmaceuticals Incorporated, marketed since Jun 2019 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 51167-113-01 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 51167 labeler · 113 product · 01 package
- Package marketed since
- Jun 21, 2019
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 5116711301 1
- Medicaid fills, this package
- 16 prescriptions in the last four reported quarters
- FDA record last changed
- Sep 10, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 079924
- GCN: 46553
- HICL (First Databank): 044771
- AHFS class code: 48:14.04.00
- RxCUI (RxNorm): 1243046
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Cystic Fibrosis Transmembrane Conductance Regulator Potentiator class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats cystic fibrosis in people aged 6 and older with two copies of the F508del mutation or another responsive CFTR mutation. Your care team will confirm your genetic type.
- Take one tablet in the morning and a different tablet in the evening, about 12 hours apart. Swallow them whole, with fat-containing food such as eggs, cheese, nuts or foods made wi...
- The most common are headache, nausea, sinus congestion and dizziness. Call your doctor for an allergic reaction, an unusual headache or vision changes, new mood or sleep problems,...
- This medicine can raise liver enzymes. Tests are done before you start, every 3 months in the first year, and yearly after that. If levels get too high, your doctor may pause it.
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $444.53 | — |
| Medicare drug plans payPart D · Q2 2026 | $451.48 | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 51167-0113-01 You're viewing this Main listing | 1 KIT in 1 CARTON * 7 TABLET, FILM COATED in 1 BLISTER PACK * 7 TABLET, FILM COATED in 1 BLISTER PACK | 2019-06-21 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Symdekothis 51167-0113-01 | Vertex | 7 tablets | — | — | FDA listed | — |
| Symdeko 51167-0661-01 | Vertex | 7 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9670163 ↗ | Method of use | U-2246 | Dec 28, 2026 |
| US 10239867 ↗ | Drug substance | U-2569 | Apr 9, 2027 |
| US 10022352 ↗ | Method of use | U-2573 | Apr 9, 2027 |
| US 10022352 ↗ | Method of use | U-2343 | Apr 9, 2027 |
| US 9974781 ↗ | Method of use | U-2318 | Apr 9, 2027 |
| US 8598181 ↗ | Method of use | U-2246 | May 1, 2027 |
| US 8324242 ↗ | Method of use | U-2246 | Aug 5, 2027 |
| US 9670163 ↗ | Method of use | U-2246 | Dec 28, 2026 |
| US 8415387 ↗ | Method of use | U-2246 | Nov 12, 2027 |
| US 9931334 ↗ | Method of use | U-2575 | Dec 28, 2026 |
| US 9931334 ↗ | Method of use | U-2275 | Dec 28, 2026 |
| US 9931334 ↗ | Method of use | U-2575 | Dec 28, 2026 |
| US 9931334 ↗ | Method of use | U-2275 | Dec 28, 2026 |
| US 10239867 ↗ | Drug substance | U-2512 | Apr 9, 2027 |
| US 10022352 ↗ | Method of use | U-2343 | Apr 9, 2027 |
| US 8415387 ↗ | Method of use | U-2246 | Nov 12, 2027 |
| US 8598181 ↗ | Method of use | U-2246 | May 1, 2027 |
| US 8324242 ↗ | Method of use | U-2246 | Aug 5, 2027 |
| US 9012496 ↗ | Method of use | U-2248 | Jul 15, 2033 |
| US 12458635 ↗ | Method of use | U-4336 | Aug 13, 2029 |
| US 12458635 ↗ | Method of use | U-4336 | Aug 13, 2029 |
| US 11578062 ↗ | Method of use | U-3545 | Mar 25, 2031 |
| US 11578062 ↗ | Method of use | U-3545 | Mar 25, 2031 |
| US 11639347 ↗ | Drug substance | U-2569 | Apr 9, 2027 |
| US 11639347 ↗ | Drug substance | U-2569 | Apr 9, 2027 |
| US 8354427 ↗ | Method of use | U-3021 | Jul 6, 2026 |
| US 8354427 ↗ | Method of use | U-3021 | Jul 6, 2026 |
| US 10081621 ↗ | Method of use | U-3024 | Mar 25, 2031 |
| US 10081621 ↗ | Method of use | U-3025 | Mar 25, 2031 |
| US 10081621 ↗ | Method of use | U-3024 | Mar 25, 2031 |
| US 10081621 ↗ | Method of use | U-3025 | Mar 25, 2031 |
| US 10206877 ↗ | Method of use | U-3027 | Apr 14, 2035 |
| US 10206877 ↗ | Method of use | U-3026 | Apr 14, 2035 |
| US 10206877 ↗ | Method of use | U-3026 | Apr 14, 2035 |
| US 10206877 ↗ | Method of use | U-3027 | Apr 14, 2035 |
| US 10058546 ↗ | Method of use | U-3023 | Jul 15, 2033 |
| US 10058546 ↗ | Method of use | U-3022 | Jul 15, 2033 |
| US 10058546 ↗ | Method of use | U-3022 | Jul 15, 2033 |
| US 10058546 ↗ | Method of use | U-3023 | Jul 15, 2033 |
| US 11564916 ↗ | Method of use | U-3527 | Aug 13, 2029 |
| US 11564916 ↗ | Method of use | U-3527 | Aug 13, 2029 |
| US 11951212 ↗ | Method of use | U-3894 | Apr 14, 2035 |
| US 9974781 ↗ | Method of use | U-2574 | Apr 9, 2027 |
| US 10239867 ↗ | Drug substance | U-2569 | Apr 9, 2027 |
| US 10239867 ↗ | Drug substance | U-2512 | Apr 9, 2027 |
| US 9974781 ↗ | Method of use | U-2574 | Apr 9, 2027 |
| US 10022352 ↗ | Method of use | U-2573 | Apr 9, 2027 |
| US 9012496 ↗ | Method of use | U-2248 | Jul 15, 2033 |
| US 9974781 ↗ | Method of use | U-2318 | Apr 9, 2027 |
| US 8410274 ↗ | Drug product | — | Dec 28, 2026 |
| US 7776905 ↗ | Drug substance | — | Jun 3, 2027 |
| US 7495103 ↗ | Drug substance | — | May 20, 2027 |
| US 7645789 ↗ | Drug substance | — | May 1, 2027 |
| US 7645789 ↗ | Drug substance | — | May 1, 2027 |
| US 8623905 ↗ | Drug substance | — | May 1, 2027 |
| US 8410274 ↗ | Drug product | — | Dec 28, 2026 |
| US 8754224 ↗ | Drug substance | — | Dec 28, 2026 |
| US 7776905 ↗ | Drug substance | — | Jun 3, 2027 |
| US RE50453 ↗ | Drug substance | — | Jul 10, 2031 |
| US 10646481 ↗ | Drug product | — | Aug 13, 2029 |
| US 8623905 ↗ | Drug substance | — | May 1, 2027 |
| US RE50453 ↗ | Drug substance | — | Jul 10, 2031 |
| US 8754224 ↗ | Drug substance | — | Dec 28, 2026 |
| US 10646481 ↗ | Drug product | — | Aug 13, 2029 |
| US 7495103 ↗ | Drug substance | — | May 20, 2027 |
| Code | What it grants | Expires |
|---|---|---|
| ODE-247 | Orphan Drug Exclusivity (7-year) | Jun 21, 2026 |
| ODE-335 | Orphan Drug Exclusivity (7-year) | Dec 21, 2027 |
| ODE-247 | Orphan Drug Exclusivity (7-year) | Jun 21, 2026 |
| ODE-335 | Orphan Drug Exclusivity (7-year) | Dec 21, 2027 |
Is there a generic version of SYMDEKO 50/75 MG-75 MG TABLETS?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Tezacaftor and Ivacaftor inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Vertex Pharmaceuticals Incorporated labeler code 51167
- Trikafta Elexacaftor, Tezacaftor, and Ivacaftor Kit NDC 51167-106-02
- Alyftrek vanzacaftor, tezacaftor, and deutivacaftor 10 mg; 50 mg; 125 mg Tablet, Film Coated NDC 51167-121-01
- Orkambi lumacaftor and ivacaftor 75 mg; 94 mg Granule NDC 51167-122-01
- Alyftrek vanzacaftor, tezacaftor, and deutivacaftor 4 mg; 20 mg; 50 mg Tablet, Film Coated NDC 51167-135-01
- Kalydeco ivacaftor 150 mg Tablet, Film Coated NDC 51167-200-01
- CASGEVY exagamglogene autotemcel 13000000 1/mL Injection, Suspension NDC 51167-290-09
- Kalydeco ivacaftor 50 mg Granule NDC 51167-300-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE SYMDEKO is indicated for the treatment of cystic fibrosis (CF) in patients aged 6 years and older who are homozygous for the F508del mutation or who have at least one mutation in the cystic fibrosis transmembrane conductance regulator ( CFTR ) gene that is responsive to tezacaftor/ivacaftor based on in vitro data and/or clinical evidence [see Clinical Pharmacology (12.1) and Clinical Studies (14) ] . If the patient's genotype is unknown, an FDA-cleared CF mutation test should be used to detect the presence of a CFTR mutation followed by verification with bi-directional sequencing when recommended by the mutation test instructions for use.
SYMDEKO is a combination of tezacaftor and ivacaftor, indicated for the treatment of cystic fibrosis (CF) in patients aged 6 years and older who are homozygous for the F508del mutation or who have at least one mutation in the cystic fibrosis transmembrane conductance regulator ( CFTR ) gene that is responsive to tezacaftor/ivacaftor based on in vitro data and/or clinical evidence. ( 12.1 , 14 ) If the patient's genotype is unknown, an FDA-cleared CF mutation test should be used to detect the presence of a CFTR mutation followed by verification with bi-directional sequencing when recommended by the mutation test instructions for use.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Pediatric patients aged 6 to less than 12 years weighing less than 30 kg: one tablet (containing tezacaftor 50 mg/ivacaftor 75 mg) in the morning and one tablet (containing ivacaftor 75 mg) in the evening, approximately 12 hours apart. SYMDEKO should be taken with fat-containing food. ( 2.1 , 2.2 , 12.3 ) Adults and pediatric patients aged 12 years and older or pediatric patients aged 6 to less than 12 years weighing 30 kg or more: one tablet (containing tezacaftor 100 mg/ivacaftor 150 mg) in the morning and one tablet (containing ivacaftor 150 mg) in the evening, approximately 12 hours apart.
SYMDEKO should be taken with fat-containing food. ( 2.1 , 2.2 , 12.3 ) Reduce dosage in patients with moderate and severe hepatic impairment. ( 2.3 , 8.6 , 12.3 ) See full prescribing information for dosage modifications due to drug interactions with SYMDEKO.
( 2.4 , 7.2 , 12.3 )
2.1General Dosage Information Swallow the tablets whole. SYMDEKO should be taken with fat-containing food, such as food recommended in standard nutritional guidelines. Examples of meals or snacks that contain fat are those prepared with butter or oils or those containing eggs, cheeses, nuts, whole milk, or meats, etc. [see Clinical Pharmacology (12.3) ] .
2.2Recommended Dosage in Adults, Adolescents, and Children Aged 6 Years and Older Adults, adolescents, and children aged 6 years and older should be dosed according to Table 1. The morning and the evening doses should be taken approximately 12 hours apart. Table 1: Recommended Dosage for Patients Aged 6 Years and Older Age Morning (one tablet) Evening (one tablet) 6 to <12 years weighing <30 kg tezacaftor 50 mg/ivacaftor 75 mg ivacaftor 75 mg 6 to <12 years weighing ≥30 kg tezacaftor 100 mg/ivacaftor 150 mg ivacaftor 150 mg ≥12 years tezacaftor 100 mg/ivacaftor 150 mg ivacaftor 150 mg Information for Missed Doses: If 6 hours or less have passed since the missed morning or evening dose, the patient should take the missed dose as soon as possible and continue on the original schedule.
If more than 6 hours have passed since the missed morning or evening dose, the patient should not take the missed dose. The next scheduled dose can be taken at the usual time. More than one dose should not be taken at the same time.
2.3Recommended Dosage for Patients with Hepatic Impairment For dosage adjustment for patients with hepatic impairment, refer to Table 2. Studies have not been conducted in patients with severe hepatic impairment (Child-Pugh Class C), but exposure of tezacaftor and ivacaftor is expected to be higher than in patients with moderate hepatic impairment. Therefore, SYMDEKO should be used with caution at an adjusted dosage after weighing the risks and benefits of treatment in these patients [see Use in Specific Populations (8.6) , Clinical Pharmacology (12.3) , and Patient Counseling Information (17) ].
Table 2: Recommended Dosage for Patients with Hepatic Impairment Hepatic Impairment Morning Evening Patients Aged 6 to <12 Years Weighing <30 kg Patients Aged 6 to <12 Years Weighing ≥30 kg and Patients Age ≥12 Years All Patients Mild (Child-Pugh Class A) No dose adjustment No dose adjustment No dose adjustment Moderate (Child-Pugh Class B) One tablet of tezacaftor 50 mg/ivacaftor 75 mg once daily One tablet of tezacaftor 100 mg/ivacaftor 150 mg once daily No ivacaftor dose Severe (Child-Pugh Class C) One tablet of tezacaftor 50 mg/ivacaftor 75 mg once daily (or less frequently) One tablet of tezacaftor 100 mg/ivacaftor 150 mg once daily (or less frequently)
2.4Dosage Adjustment for Patients Taking Drugs that are CYP3A Inhibitors The dosing regimen of SYMDEKO should be adjusted when co-administered with moderate and strong CYP3A inhibitors. Moderate CYP3A inhibitors: When co-administered with moderate CYP3A inhibitors (e.g., fluconazole, erythromycin), the dosing regimen should be adjusted as in Table 3 [see Drug Interactions (7.2) , Clinical Pharmacology (12.3) , and Patient Coun… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: Tezacaftor 50 mg/ivacaftor 75 mg fixed-dose combination tablets co-packaged with ivacaftor 75 mg tablets Tezacaftor 50 mg/ivacaftor 75 mg tablets are white, oblong-shaped, and debossed with "V50" on one side and plain on the other. Ivacaftor 75 mg tablets are light blue, oblong-shaped, and printed with "V 75" in black ink on one side and plain on the other. Tablets: Tezacaftor 100 mg/ivacaftor 150 mg fixed-dose combination tablets co-packaged with ivacaftor 150 mg tablets Tezacaftor 100 mg/ivacaftor 150 mg tablets are yellow, oblong-shaped, and debossed with "V100" on one side and plain on the other.
Ivacaftor 150 mg tablets are light blue, oblong-shaped, and printed with "V 150" in black ink on one side and plain on the other. Tablets: tezacaftor 50 mg/ivacaftor 75 mg fixed-dose combination tablets co-packaged with ivacaftor 75 mg tablets. ( 3 ) Tablets: tezacaftor 100 mg/ivacaftor 150 mg fixed-dose combination tablets co-packaged with ivacaftor 150 mg tablets.
( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Elevated transaminases (ALT or AST): Transaminases (ALT and AST) should be assessed prior to initiating SYMDEKO, every 3 months during the first year of treatment, and annually thereafter. In patients with a history of transaminase elevations, more frequent monitoring should be considered. Dosing should be interrupted in patients with significant elevations of transaminases, e.g., patients with ALT or AST >5 × upper limit of normal (ULN), or ALT or AST >3 × ULN with bilirubin >2 × ULN.
Following resolution of transaminase elevations, consider the benefits and risks of resuming treatment. ( 5.1 , 6 ) Hypersensitivity reactions: Anaphylaxis has been reported with SYMDEKO in the postmarketing setting. Initiate appropriate therapy in the event of a hypersensitivity reaction.
( 5.2 ) Intracranial hypertension : Intracranial hypertension (IH) has been reported in the postmarketing setting with the use of drugs containing the same or similar active ingredients as SYMDEKO. If an unusual headache or visual disturbances occur during treatment, and IH is suspected, interrupt SYMDEKO and refer for prompt medical evaluation. ( 5.3 ) Neuropsychiatric events, including suicidal thoughts and behaviors : Serious neuropsychiatric events, including symptoms of anxiety, depression, suicidal ideation and behavior, and sleep disturbances, have been reported in the postmarketing setting for SYMDEKO or drugs containing the same or similar active ingredients.
Monitor patients closely for new or worsening symptoms. Consider the risks and benefits for the individual patient to determine if therapy with SYMDEKO should be interrupted at the occurrence of neuropsychiatric symptoms. ( 5.4 ) Use with CYP3A inducers: Concomitant use with strong CYP3A inducers (e.g., rifampin, St.
John's wort) substantially decrease exposure of ivacaftor and may decrease the exposure of tezacaftor, which may reduce therapeutic effectiveness. Therefore, co-administration is not recommended. ( 5.5 , 7.1 , 12.3 ) Cataracts: Non-congenital lens opacities/cataracts have been reported in pediatric patients treated with SYMDEKO.
Baseline and follow-up examinations are recommended in pediatric patients initiating SYMDEKO treatment. ( 5.6 , 8.4 )
5.1Transaminase (AST/ALT) Elevations Elevated transaminases have been observed in patients with CF treated with SYMDEKO, as well as with ivacaftor monotherapy. Assessments of transaminases (ALT and AST) are recommended for all patients prior to initiating SYMDEKO, every 3 months during the first year of treatment, and annually thereafter. For patients with a history of transaminase elevations more frequent monitoring should be considered.
In the event of significant elevations of transaminases, e.g., patients with ALT or AST >5 × upper limit of normal (ULN), or ALT or AST >3 × ULN with bilirubin >2 × ULN, dosing should be interrupted and laboratory tests closely followed until the abnormalities resolve. Following the resolution of transaminase elevations consider the benefits and risks of resuming treatment [see Adverse Reactions (6) ] .
5.2Hypersensitivity Reactions, Including Anaphylaxis Hypersensitivity reactions, including cases of anaphylaxis, have been reported in the postmarketing setting [see Adverse Reactions (6.2) ] . If signs or symptoms of serious hypersensitivity reactions develop during treatment, discontinue SYMDEKO and institute appropriate therapy. Consider the benefits and risks for the individual patient to determine whether to resume treatment with SYMDEKO.
5.3Intracranial Hypertension Cases of intracranial hypertension (IH) have been reported in the postmarketing setting with the use of drugs containing the same or similar active ingredients as SYMDEKO [see Adverse Reactions (6.2) ] . Clinical manifestations of IH include headache, blurred vision, diplopia, and potential vision loss; papilledema can be found on fundoscopy. If an unusual headache or visual disturbances occur during treatment, a… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the label: Transaminase Elevations [see Warnings and Precautions (5.1) ] Hypersensitivity Reactions, Including Anaphylaxis [see Warnings and Precautions (5.2) ] Intracranial Hypertension [see Warnings and Precautions (5.3) ] Neuropsychiatric Events, Including Suicidal Thoughts and Behaviors [see Warnings and Precautions (5.4) ] Cataracts [see Warnings and Precautions (5.6) ] The most common adverse drug reactions to SYMDEKO (occurring in ≥3% of patients) were headache, nausea, sinus congestion, and dizziness.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Vertex Pharmaceuticals Incorporated at 1-877-634-8789 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. The overall safety profile of SYMDEKO is based on data from 1001 patients in three double-blind, placebo-controlled, clinical trials: two parallel-group trials of 12 and 24-week duration and one cross-over design trial of 8 weeks duration.
Eligible patients were also able to participate in an open-label extension safety study (up to 96 weeks of SYMDEKO). In the three placebo-controlled trials (Trials 1, 2, and 3), a total of 496 patients with CF aged 12 years and older received at least one dose of SYMDEKO. The proportion of patients who discontinued study drug prematurely due to adverse reactions was 1.6% for SYMDEKO-treated patients and 2.0% for placebo-treated patients.
Serious adverse reactions, whether considered drug-related or not by the investigators, that occurred more frequently in SYMDEKO-treated patients compared to placebo included distal intestinal obstruction syndrome, 3 (0.6%) SYMDEKO-treated patients vs. 0 placebo. There were no deaths in the placebo-controlled trials, and one death in the open-label extension study due to respiratory failure and influenza infection in a patient who had discontinued SYMDEKO seven weeks prior.
The safety profile of SYMDEKO was generally similar across all subgroups of patients, including analysis by age, sex, baseline percent predicted FEV 1 (ppFEV 1 ), and geographic regions. Table 5 shows adverse reactions occurring in ≥3% of SYMDEKO-treated patients that also occurred at a higher rate than in the placebo-treated patients in the 12- and 24-week placebo-controlled, parallel-group trials (Trials 1 and 3). Table 5: Incidence of Adverse Drug Reactions in ≥3% of SYMDEKO-Treated Patients and Greater than Placebo Adverse Reactions (Preferred Term) SYMDEKO N=334 n (%) Placebo N=343 n (%) Headache 49 (15) 44 (13) Nausea 29 (9) 24 (7) Sinus congestion 13 (4) 6 (2) Dizziness 12 (4) 8 (2) The safety data from the following trials are similar to that observed in Trials 1 and 3: an 8-week randomized, double-blind, placebo-controlled crossover study in 244 patients with CF aged 12 years and older who were heterozygous for the F508del mutation and a second mutation predicted to be responsive to tezacaftor/ivacaftor (Trial 2). a 24-week open-label study in 70 patients with CF aged 6 to less than 12 years who were either homozygous for the F508del mutation or heterozygous for the F508del mutation and a second mutation predicted to be responsive to tezacaftor/ivacaftor (Trial 4).
Laboratory Abnormalities Transaminase elevations During the placebo-controlled trials in patients aged 12 years and older, the incidence of maximum transaminase (ALT or AST) >8, >5, and >3 × the upper limit of normal (ULN) was similar between SYMDEKO-treated patients and placebo-treated patients; 0.2%, 1.0%, and 3.4% in SYMDEKO-treated patients, and 0.4%, 1.0%, and 3.4% in placebo-treated patients. One patient (0.2%) on SYMDEKO and 2 patients (0.4%) on pla… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Potential for other drugs to affect tezacaftor/ivacaftor CYP3A inhibitors: Reduce SYMDEKO dosage when co-administered with strong (e.g., ketoconazole) or moderate (e.g., fluconazole) CYP3A inhibitors. Avoid food containing grapefruit. ( 2.4 , 7.2 , 12.3 )
7.1Inducers of CYP3A Tezacaftor and ivacaftor are substrates of CYP3A (ivacaftor is a sensitive substrate of CYP3A). Concomitant use of CYP3A inducers may result in reduced exposures and thus reduced SYMDEKO efficacy. Co-administration of ivacaftor with rifampin, a strong CYP3A inducer, significantly decreased ivacaftor exposure (area under the curve [AUC]) by 89%.
Tezacaftor exposures can also be expected to decrease significantly during co-administration with strong CYP3A inducers. Therefore, co-administration of SYMDEKO with strong CYP3A inducers is not recommended [see Warnings and Precautions (5.5) , Clinical Pharmacology (12.3) , and Patient Counseling Information (17) ] . Examples of strong CYP3A inducers include: rifampin, rifabutin, phenobarbital, carbamazepine, phenytoin, and St.
John's wort (Hypericum perforatum)
7.2Inhibitors of CYP3A Co-administration with itraconazole, a strong CYP3A inhibitor, increased tezacaftor exposure (AUC) by 4.0-fold and ivacaftor by 15.6-fold. When co-administered with strong CYP3A inhibitors, the dosing regimen of SYMDEKO should be adjusted [see Dosage and Administration (2.4) , Clinical Pharmacology (12.3) , and Patient Counseling Information (17) ] . Examples of strong CYP3A inhibitors include: ketoconazole, itraconazole, posaconazole, and voriconazole telithromycin and clarithromycin Co-administration of fluconazole increased ivacaftor exposure (AUC) by 3.0-fold.
Simulation suggested co-administration with fluconazole, a moderate CYP3A inhibitor, may increase tezacaftor exposure (AUC) by approximately 2.0-fold. When co-administered with moderate CYP3A inhibitors, the dosing regimen of SYMDEKO should be adjusted [see Dosage and Administration (2.4) , Clinical Pharmacology (12.3) , and Patient Counseling Information (17) ] . Examples of moderate CYP3A inhibitors include: fluconazole erythromycin Co-administration of SYMDEKO with grapefruit juice, which contains one or more components that moderately inhibit CYP3A, may increase exposure of tezacaftor and ivacaftor; therefore, food or drink containing grapefruit should be avoided during treatment with SYMDEKO [see Dosage and Administration (2.4) , Clinical Pharmacology (12.3) , and Patient Counseling Information (17) ] .
7.3Ciprofloxacin Co-administration of SYMDEKO with ciprofloxacin had no significant effect on the exposure of tezacaftor or ivacaftor. Therefore, no dosage adjustment is necessary during concomitant administration of SYMDEKO with ciprofloxacin [see Clinical Pharmacology (12.3) ] . Potential for tezacaftor/ivacaftor to affect other drugs
7.4CYP3A Substrates Co-administration of SYMDEKO with midazolam (oral), a sensitive CYP3A substrate, did not affect midazolam exposure. No dosage adjustment of CYP3A substrates is required when co-administered with SYMDEKO [see Clinical Pharmacology (12.3) ] .
7.5CYP2C9 Substrates Ivacaftor may inhibit CYP2C9; therefore, monitoring of the international normalized ratio (INR) during co-administration of SYMDEKO with warfarin is recommended. Other medicinal products for which exposure may be increased by SYMDEKO include glimepiride and glipizide; these medicinal products should be used with caution [see Clinical Pharmacology (12.3) ] .
7.6Digoxin and Other P-gp Substrates Co-administration of SYMDEKO with digoxin, a sensitive P-gp substrate, increased digoxin exposure by 1.3-fold consistent with weak inhibition of P-gp by ivacaftor. Administration of SYMDEKO may increase systemic exposure of medicinal products that are sensitive substrates of P-gp, which may increase or prolong their therapeutic effect and adverse reactions. When used concomitantly with digoxin or other substrates of P-gp with a narrow therapeutic… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are limited and incomplete human data from clinical trials and postmarketing reports on the use of SYMDEKO or its individual components, tezacaftor and ivacaftor, in pregnant women to inform a drug-associated risk. Although there are no animal reproduction studies with the concomitant administration of tezacaftor and ivacaftor, separate reproductive and developmental studies were conducted with tezacaftor and ivacaftor in pregnant rats and rabbits. In animal reproduction studies, oral administration of tezacaftor to pregnant rats and rabbits during organogenesis demonstrated no teratogenicity or adverse developmental effects at doses that produced maternal exposures up to approximately 3 times the exposure at the maximum recommended human dose (MRHD) in rats and 0.2 times the MRHD in rabbits (based on summed AUCs for tezacaftor and M1 metabolite).
Oral administration of ivacaftor to pregnant rats and rabbits during organogenesis demonstrated no teratogenicity or adverse developmental effects at doses that produced maternal exposures up to approximately 6 and 16 times the exposure at the MRHD, respectively. No adverse developmental effects were observed after oral administration of either tezacaftor or ivacaftor to pregnant rats from the period of organogenesis through lactation at doses that produced maternal exposures approximately 1 and 4 times the exposures at the MRHD, respectively ( see Data ).
The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Tezacaftor In an embryo-fetal development study in pregnant rats dosed during the period of organogenesis from gestation Days 6-17, tezacaftor was not teratogenic and did not affect fetal development or survival at exposures up to 3 times the MRHD (based on summed AUCs for tezacaftor and M1 metabolite at maternal oral doses up to 100 mg/kg/day).
In an embryo-fetal development study in pregnant rabbits dosed during the period of organogenesis from gestation Days 7-20, tezacaftor was not teratogenic and did not affect fetal development or survival at exposures up to 0.2 times the MRHD (based on summed AUCs for tezacaftor and M1 metabolite at maternal oral doses up to 25 mg/kg/day). Lower fetal body weights were observed in rabbits at a maternally toxic dose that produced exposures approximately 1 times the MRHD (at a maternal dose of 50 mg/kg/day). In a pre- and postnatal development (PPND) study in pregnant rats dosed from gestation Day 6 through lactation Day 18, tezacaftor had no adverse developmental effects on pups at an exposure of approximately 1 times the MRHD (based on summed AUCs for tezacaftor and M1 metabolite at a maternal dose of 25 mg/kg/day).
Decreased fetal body weights and early developmental delays in pinna detachment, eye opening, and righting reflex occurred at a maternally toxic dose (based on maternal weight loss) that produced exposures approximately 2 times the exposure at the MRHD (based on summed AUCs for tezacaftor and M1 metabolite at a maternal oral dose of 50 mg/kg/day). Placental transfer of tezacaftor was observed in pregnant rats. Ivacaftor In an embryo-fetal development study in pregnant rats dosed during the period of organogenesis from gestation Days 7-17, ivacaftor was not teratogenic and did not affect fetal survival at exposures up to 6 times the MRHD (based on summed AUCs for ivacaftor and its metabolites at a maternal oral dose of 200 mg/kg/day).
In an embryo-fetal development study in pregnant rabbits dosed during the period of organogenesis from gestation Days 7-19, ivacaftor was not teratogenic and did not affect fetal development or survival at exposures up to 16 times the MRHD (on an ivacaftor AUC basis at maternal oral doses up to 10… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are limited and incomplete human data from clinical trials and postmarketing reports on the use of SYMDEKO or its individual components, tezacaftor and ivacaftor, in pregnant women to inform a drug-associated risk. Although there are no animal reproduction studies with the concomitant administration of tezacaftor and ivacaftor, separate reproductive and developmental studies were conducted with tezacaftor and ivacaftor in pregnant rats and rabbits. In animal reproduction studies, oral administration of tezacaftor to pregnant rats and rabbits during organogenesis demonstrated no teratogenicity or adverse developmental effects at doses that produced maternal exposures up to approximately 3 times the exposure at the maximum recommended human dose (MRHD) in rats and 0.2 times the MRHD in rabbits (based on summed AUCs for tezacaftor and M1 metabolite).
Oral administration of ivacaftor to pregnant rats and rabbits during organogenesis demonstrated no teratogenicity or adverse developmental effects at doses that produced maternal exposures up to approximately 6 and 16 times the exposure at the MRHD, respectively. No adverse developmental effects were observed after oral administration of either tezacaftor or ivacaftor to pregnant rats from the period of organogenesis through lactation at doses that produced maternal exposures approximately 1 and 4 times the exposures at the MRHD, respectively ( see Data ).
The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data Tezacaftor In an embryo-fetal development study in pregnant rats dosed during the period of organogenesis from gestation Days 6-17, tezacaftor was not teratogenic and did not affect fetal development or survival at exposures up to 3 times the MRHD (based on summed AUCs for tezacaftor and M1 metabolite at maternal oral doses up to 100 mg/kg/day).
In an embryo-fetal development study in pregnant rabbits dosed during the period of organogenesis from gestation Days 7-20, tezacaftor was not teratogenic and did not affect fetal development or survival at exposures up to 0.2 times the MRHD (based on summed AUCs for tezacaftor and M1 metabolite at maternal oral doses up to 25 mg/kg/day). Lower fetal body weights were observed in rabbits at a maternally toxic dose that produced exposures approximately 1 times the MRHD (at a maternal dose of 50 mg/kg/day). In a pre- and postnatal development (PPND) study in pregnant rats dosed from gestation Day 6 through lactation Day 18, tezacaftor had no adverse developmental effects on pups at an exposure of approximately 1 times the MRHD (based on summed AUCs for tezacaftor and M1 metabolite at a maternal dose of 25 mg/kg/day).
Decreased fetal body weights and early developmental delays in pinna detachment, eye opening, and righting reflex occurred at a maternally toxic dose (based on maternal weight loss) that produced exposures approximately 2 times the exposure at the MRHD (based on summed AUCs for tezacaftor and M1 metabolite at a maternal oral dose of 50 mg/kg/day). Placental transfer of tezacaftor was observed in pregnant rats. Ivacaftor In an embryo-fetal development study in pregnant rats dosed during the period of organogenesis from gestation Days 7-17, ivacaftor was not teratogenic and did not affect fetal survival at exposures up to 6 times the MRHD (based on summed AUCs for ivacaftor and its metabolites at a maternal oral dose of 200 mg/kg/day).
In an embryo-fetal development study in pregnant rabbits dosed during the period of organogenesis from gestation Days 7-19, ivacaftor was not teratogenic and did not affect fetal development or survival at exposures up to 16 times the MRHD (on an ivacaftor AUC basis at maternal oral doses up to 100 mg/kg/day). In a PPND study… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of SYMDEKO for the treatment of CF have been established in pediatric patients aged 6 to less than 18 years who are homozygous for the F508del mutation or who have at least one mutation in the CFTR gene that is responsive to tezacaftor/ivacaftor based on in vitro data and/or clinical evidence [see Clinical Pharmacology (12.1) and Clinical Studies (14) ]. Clinical trials included the following patients with CF: 12 to less than 18 years of age who are homozygous for the F508del mutation [see Adverse Reactions (6) and Clinical Studies (14) ] .
12 to less than 18 years of age who are heterozygous for the F508del mutation and a second mutation predicted to be responsive to tezacaftor/ivacaftor [see Adverse Reactions (6) and Clinical Studies (14) ] . 6 to less than 12 years of age who are either homozygous for the F508del mutation or heterozygous for the F508del mutation and a second mutation predicted to be responsive to tezacaftor/ivacaftor [see Adverse Reactions (6) and Clinical Pharmacology (12) ]. The effectiveness of SYMDEKO in patients aged 6 to less than 12 years was extrapolated from patients aged 12 years and older with support from population pharmacokinetic analyses showing similar tezacaftor and ivacaftor exposure levels in patients aged 6 to less than 12 years and in patients aged 12 years and older [see Clinical Pharmacology (12.3) ] .
Safety of SYMDEKO in this population was derived from a 24-week, open-label, clinical trial in 70 patients aged 6 to less than 12 years (mean age at screening 8.1 years) administered either tezacaftor 50 mg/ivacaftor 75 mg and ivacaftor 75 mg or tezacaftor 100 mg/ivacaftor 150 mg and ivacaftor 150 mg, 12 hours apart (Trial 4). The safety profile for patients in this trial was similar to that observed in Trials 1 and 3 [see Adverse Reactions (6.1) ]. The safety and effectiveness of SYMDEKO in patients with CF younger than 6 years of age have not been studied.
Juvenile Animal Toxicity Data Findings of cataracts were observed in juvenile rats dosed from postnatal Day 7 through 35 with ivacaftor dose levels of 10 mg/kg/day and higher (0.25 times the MRHD based on systemic exposure of ivacaftor and its metabolites). This finding has not been observed in older animals.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of SYMDEKO did not include sufficient numbers of patients 65 years of age and over to determine whether they respond differently from younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE No specific antidote is available for overdose with SYMDEKO. Treatment of overdosage consists of general supportive measures including monitoring of vital signs and observation of the clinical status of the patient.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Tezacaftor facilitates the cellular processing and trafficking of select mutant forms of CFTR (including F508del-CFTR) to increase the amount of mature CFTR protein delivered to the cell surface. Ivacaftor is a CFTR potentiator that facilitates increased chloride transport by potentiating the channel-open probability (or gating) of the CFTR protein at the cell surface. For ivacaftor to function CFTR protein must be present at the cell surface.
Ivacaftor can potentiate the CFTR protein delivered to the cell surface by tezacaftor, leading to a further enhancement of chloride transport than either agent alone. The combined effect of tezacaftor and ivacaftor is increased quantity and function of CFTR at the cell surface, resulting in increases in chloride transport. CFTR Chloride Transport Assay in Fischer Rat Thyroid (FRT) cells expressing mutant CFTR The chloride transport response of mutant CFTR protein to tezacaftor/ivacaftor was determined in Ussing chamber electrophysiology studies using a panel of FRT cell lines transfected with individual CFTR mutations.
Tezacaftor/ivacaftor increased chloride transport in FRT cells expressing CFTR mutations that result in CFTR protein being delivered to the cell surface. The in vitro chloride transport response threshold was designated as a net increase of at least 10% of normal over baseline because it is predictive or reasonably expected to predict clinical benefit. For individual mutations, the magnitude of the net change over baseline in CFTR-mediated chloride transport in vitro is not correlated with the magnitude of clinical response.
Note that splice site mutations cannot be studied in the FRT assay. Table 6 lists responsive CFTR mutations based on (1) a clinical FEV 1 response and/or (2) in vitro data in FRT cells, indicating that tezacaftor/ivacaftor increases chloride transport to at least 10% of normal over baseline. CFTR gene mutations that are not responsive to ivacaftor alone are not expected to respond to SYMDEKO except for F508del homozygotes.
Table 6: List of CFTR Gene Mutations that Produce CFTR Protein and are Responsive to SYMDEKO 546insCTA E92K G576A L346P R117G S589N 711+3A→G Clinical data for these mutations in Clinical Studies [see Clinical Studies (14.1 and 14.2) ] . E116K G576A;R668C Complex/compound mutations where a single allele of the CFTR gene has multiple mutations; these exist independent of the presence of mutations on the other allele. L967S R117H S737F 2789+5G→A E193K G622D L997F R117L S912L 3272-26A→G E403D G970D L1324P R117P S945L 3849+10kbC→T E588V G1069R L1335P R170H S977F A120T E822K G1244E L1480P R258G S1159F A234D E831X G1249R M152V R334L S1159P A349V F191V G1349D M265R R334Q S1251N A455E F311del H939R M952I R347H S1255P A554E F311L H1054D M952T R347L T338I A1006E F508C H1375P P5L R347P T1036N A1067T F508C;S1251N I148T P67L R352Q T1053I D110E F508del A patient must have two copies of the F508del mutation or at least one copy of a responsive mutation presented in Table 6 to be indicated.
I175V P205S R352W V201M D110H F575Y I336K Q98R R553Q V232D D192G F1016S I601F Q237E R668C V562I D443Y F1052V I618T Q237H R751L V754M D443Y;G576A;R668C F1074L I807M Q359R R792G V1153E D579G F1099L I980K Q1291R R933G V1240G D614G G126D I1027T R31L R1066H V1293G D836Y G178E I1139V R74Q R1070Q W1282R D924N G178R I1269N R74W R1070W Y109N D979V G194R I1366N R74W;D1270N R1162L Y161S D1152H G194V K1060T R74W;V201M R1283M Y1014C D1270N G314E L15P R74W;V201M;D1270N R1283S Y1032C E56K G551D L206W R75Q S549N E60K G551S L320V R117C S549R
12.2Pharmacodynamics Effects on Sweat Chloride In Trial 1 (patients aged 12 years and older who were homozygous for the F508del mutation), the treatment difference between SYMDEKO and placebo in mean absolute change from baseline in sweat chloride through Week 24 was -10.1 mmol/L (95% CI: -11.4, -8.8). In Trial 2 (patients aged 12 years and older who were heterozygous for the F508del mutation… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Tezacaftor facilitates the cellular processing and trafficking of select mutant forms of CFTR (including F508del-CFTR) to increase the amount of mature CFTR protein delivered to the cell surface. Ivacaftor is a CFTR potentiator that facilitates increased chloride transport by potentiating the channel-open probability (or gating) of the CFTR protein at the cell surface. For ivacaftor to function CFTR protein must be present at the cell surface.
Ivacaftor can potentiate the CFTR protein delivered to the cell surface by tezacaftor, leading to a further enhancement of chloride transport than either agent alone. The combined effect of tezacaftor and ivacaftor is increased quantity and function of CFTR at the cell surface, resulting in increases in chloride transport. CFTR Chloride Transport Assay in Fischer Rat Thyroid (FRT) cells expressing mutant CFTR The chloride transport response of mutant CFTR protein to tezacaftor/ivacaftor was determined in Ussing chamber electrophysiology studies using a panel of FRT cell lines transfected with individual CFTR mutations.
Tezacaftor/ivacaftor increased chloride transport in FRT cells expressing CFTR mutations that result in CFTR protein being delivered to the cell surface. The in vitro chloride transport response threshold was designated as a net increase of at least 10% of normal over baseline because it is predictive or reasonably expected to predict clinical benefit. For individual mutations, the magnitude of the net change over baseline in CFTR-mediated chloride transport in vitro is not correlated with the magnitude of clinical response.
Note that splice site mutations cannot be studied in the FRT assay. Table 6 lists responsive CFTR mutations based on (1) a clinical FEV 1 response and/or (2) in vitro data in FRT cells, indicating that tezacaftor/ivacaftor increases chloride transport to at least 10% of normal over baseline. CFTR gene mutations that are not responsive to ivacaftor alone are not expected to respond to SYMDEKO except for F508del homozygotes.
Table 6: List of CFTR Gene Mutations that Produce CFTR Protein and are Responsive to SYMDEKO 546insCTA E92K G576A L346P R117G S589N 711+3A→G Clinical data for these mutations in Clinical Studies [see Clinical Studies (14.1 and 14.2) ] . E116K G576A;R668C Complex/compound mutations where a single allele of the CFTR gene has multiple mutations; these exist independent of the presence of mutations on the other allele. L967S R117H S737F 2789+5G→A E193K G622D L997F R117L S912L 3272-26A→G E403D G970D L1324P R117P S945L 3849+10kbC→T E588V G1069R L1335P R170H S977F A120T E822K G1244E L1480P R258G S1159F A234D E831X G1249R M152V R334L S1159P A349V F191V G1349D M265R R334Q S1251N A455E F311del H939R M952I R347H S1255P A554E F311L H1054D M952T R347L T338I A1006E F508C H1375P P5L R347P T1036N A1067T F508C;S1251N I148T P67L R352Q T1053I D110E F508del A patient must have two copies of the F508del mutation or at least one copy of a responsive mutation presented in Table 6 to be indicated.
I175V P205S R352W V201M D110H F575Y I336K Q98R R553Q V232D D192G F1016S I601F Q237E R668C V562I D443Y F1052V I618T Q237H R751L V754M D443Y;G576A;R668C F1074L I807M Q359R R792G V1153E D579G F1099L I980K Q1291R R933G V1240G D614G G126D I1027T R31L R1066H V1293G D836Y G178E I1139V R74Q R1070Q W1282R D924N G178R I1269N R74W R1070W Y109N D979V G194R I1366N R74W;D1270N R1162L Y161S D1152H G194V K1060T R74W;V201M R1283M Y1014C D1270N G314E L15P R74W;V201M;D1270N R1283S Y1032C E56K G551D L206W R75Q S549N E60K G551S L320V R117C S549R
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING SYMDEKO (tezacaftor 50 mg/ivacaftor 75 mg fixed-dose combination tablets co-packaged with ivacaftor 75 mg tablet): Tezacaftor 50 mg/ivacaftor 75 mg fixed-dose combination tablets are supplied as white, oblong-shaped tablets containing 50 mg of tezacaftor and 75 mg of ivacaftor. Each tablet is debossed with "V50" on one side and plain on the other. Ivacaftor 75 mg tablets are supplied as light blue, film-coated, oblong-shaped tablets containing 75 mg of ivacaftor.
Each tablet is printed with the characters "V 75" on one side and plain on the other. 56-count tablet carton containing a 4-week supply (4 weekly wallets, each with 14 tablets) NDC 51167-113-01 SYMDEKO (tezacaftor 100 mg/ivacaftor 150 mg fixed-dose combination tablets co-packaged with ivacaftor 150 mg tablet): Tezacaftor 100 mg/ivacaftor 150 mg fixed-dose combination tablets are supplied as yellow, oblong-shaped tablets containing 100 mg of tezacaftor and 150 mg of ivacaftor. Each tablet is debossed with "V100" on one side and plain on the other.
Ivacaftor 150 mg tablets are supplied as light blue, film-coated, oblong-shaped tablets containing 150 mg of ivacaftor. Each tablet is printed with the characters "V 150" on one side and plain on the other. 56-count tablet carton containing a 4-week supply (4 weekly wallets, each with 14 tablets) NDC 51167-661-01 Store at 68°F to 77°F (20°C to 25°C); excursions permitted to 59°F to 86°F (15°C to 30°C) [see USP Controlled Room Temperature].
📦 Storage and Handling ▾
Store at 68°F to 77°F (20°C to 25°C); excursions permitted to 59°F to 86°F (15°C to 30°C) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION SYMDEKO is co-packaged as a tezacaftor/ivacaftor fixed-dose combination tablet and an ivacaftor tablet. Both tablets are for oral administration. Tezacaftor 50 mg/ivacaftor 75 mg fixed-dose combination tablets and ivacaftor 75 mg tablets : The tezacaftor/ivacaftor fixed-dose combination tablet is available as a white, oblong-shaped, film-coated tablet containing 50 mg of tezacaftor, 75 mg of ivacaftor, and the following inactive ingredients: croscarmellose sodium, hypromellose, hypromellose acetate succinate, magnesium stearate, microcrystalline cellulose and sodium lauryl sulfate.
The tablet film coat contains HPMC/hypromellose 2910, hydroxypropyl cellulose, talc and titanium dioxide. The ivacaftor tablet is available as a light blue, oblong-shaped, film-coated tablet containing 75 mg of ivacaftor and the following inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, hypromellose acetate succinate, lactose monohydrate, magnesium stearate, microcrystalline cellulose, and sodium lauryl sulfate. The tablet film coat contains carnauba wax, FD&C Blue #2, PEG 3350, polyvinyl alcohol, talc, and titanium dioxide.
The printing ink contains ammonium hydroxide, iron oxide black, propylene glycol, and shellac. Tezacaftor 100 mg/ivacaftor 150 mg fixed-dose combination tablets and ivacaftor 150 mg tablets : The tezacaftor/ivacaftor fixed-dose combination tablet is available as a yellow, oblong-shaped, film-coated tablet containing 100 mg of tezacaftor, 150 mg of ivacaftor, and the following inactive ingredients: croscarmellose sodium, hypromellose, hypromellose acetate succinate, magnesium stearate, microcrystalline cellulose and sodium lauryl sulfate.
The tablet film coat contains HPMC/hypromellose 2910, hydroxypropyl cellulose, iron oxide yellow, talc and titanium dioxide. The ivacaftor tablet is available as a light blue, oblong-shaped, film-coated tablet containing 150 mg of ivacaftor and the following inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, hypromellose acetate succinate, lactose monohydrate, magnesium stearate, microcrystalline cellulose, and sodium lauryl sulfate. The tablet film coat contains carnauba wax, FD&C Blue #2, PEG 3350, polyvinyl alcohol, talc, and titanium dioxide.
The printing ink contains ammonium hydroxide, iron oxide black, propylene glycol, and shellac. The active ingredients of SYMDEKO are described below. Tezacaftor Tezacaftor is a white to off-white powder that is practically insoluble in water (<5 microgram/mL).
Its chemical name of tezacaftor is 1-(2,2-difluoro-2H-1,3-benzodioxol-5-yl)-N-{1-[(2R)-2,3-dihydroxypropyl]-6-fluoro-2-(1-hydroxy-2-methylpropan-2-yl)-1Hindol-5-yl}cyclopropane-1-carboxamide. Its molecular formula is C 26 H 27 N 2 F 3 O 6 and its molecular weight is 520.50. Tezacaftor has the following structural formula: Chemical Structure Ivacaftor Ivacaftor is a white to off-white powder that is practically insoluble in water (<0.05 microgram/mL).
Pharmacologically it is a CFTR potentiator. Its chemical name is N -(2,4-di-tert-butyl-5-hydroxyphenyl)-1,4-dihydro-4-oxoquinoline-3-carboxamide. Its molecular formula is C 24 H 28 N 2 O 3 and its molecular weight is 392.49.
Ivacaftor has the following structural formula: Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Transaminase (ALT or AST) Elevations and Monitoring Inform patients that elevation in liver tests has occurred in patients treated with SYMDEKO or with ivacaftor alone. Transaminases (ALT and AST) should be assessed prior to initiating SYMDEKO, every 3 months during the first year of treatment, and annually thereafter.
More frequent monitoring should be considered in patients with a history of transaminase elevations [see Warnings and Precautions (5.1) ] . Hypersensitivity Reactions, Including Anaphylaxis Hypersensitivity reactions including anaphylaxis are possible with use of SYMDEKO. Inform patients of the early signs of hypersensitivity reactions including rash, hives, itching, facial swelling, tightness of the chest and wheezing.
Advise patients to discontinue use of SYMDEKO immediately and contact their physician or go to the emergency department if these symptoms occur. Intracranial Hypertension Inform patients that intracranial hypertension has occurred in patients who received drugs containing the same or similar active ingredients as SYMDEKO. Instruct patients to notify their healthcare provider right away if they experience signs and symptoms of intracranial hypertension, including headache, blurred vision, diplopia, and vision loss [see Warnings and Precautions (5.3) ] .
Neuropsychiatric Events, Including Suicidal Thoughts and Behaviors Inform patients that neuropsychiatric symptoms, including anxiety, depression, suicidal thoughts and behaviors, and sleep disturbances (e.g., insomnia), have been reported with the use of SYMDEKO or drugs containing the same or similar active ingredients as SYMDEKO. The symptoms have been observed in patients with and without a history of similar symptoms and may occur within three months of SYMDEKO initiation. Instruct patients to contact their healthcare provider immediately if changes in behavior or thinking that are not typical for the patient occur, or if the patient develops suicidal ideation or behavior [see Warnings and Precautions (5.4) ] .
Drug Interactions with CYP3A Inducers and Inhibitors Ask patients to tell you all the medications they are taking including any herbal supplements or vitamins. Co-administration of SYMDEKO with strong CYP3A inducers (e.g., rifampin, St. John's wort) is not recommended, as they may reduce the therapeutic effectiveness of SYMDEKO.
Adjustment of the dosage to one tablet of tezacaftor/ivacaftor twice a week, taken approximately 3 to 4 days apart is recommended when co-administered with strong CYP3A inhibitors, such as ketoconazole. Advise the patient not to take the evening dose of ivacaftor. Dosage reduction to one tablet of tezacaftor/ivacaftor or ivacaftor, taken on alternate days in the morning is recommended when co-administered with moderate CYP3A inhibitors, such as fluconazole.
Advise the patient not to take the evening dose of ivacaftor. Food or drink containing grapefruit should be avoided [see Warnings and Precautions (5.5) , Drug Interactions (7) , and Clinical Pharmacology (12.3) ] . Cataracts Inform patients that abnormality of the eye lens (cataract) has been noted in some children and adolescents receiving SYMDEKO or with ivacaftor alone.
Baseline and follow-up ophthalmological examinations should be performed in pediatric patients initiating treatment with SYMDEKO [see Warnings and Precautions (5.6) ] . Use in Patients with Hepatic Impairment Inquire and/or assess whether patients have liver impairment. Adjust the dosage in patients with moderately impaired hepatic function (Child-Pugh Class B, score 7-9) to one tablet of tezacaftor/ivacaftor once daily in the morning and advise the patient not to take the evening dose of ivacaftor.
SYMDEKO has not been studied in patients with severe hepatic impairment (Child-Pugh Class C, score 10-15); however, exposure is expected to be substantially higher than that obser… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetics of tezacaftor and ivacaftor are similar between healthy adult volunteers and patients with CF. Following once-daily dosing of tezacaftor and twice-daily dosing of ivacaftor in patients with CF, plasma concentrations of tezacaftor and ivacaftor reach steady-state within 8 days and within 3 to 5 days, respectively, after starting treatment. At steady-state, the accumulation ratio is approximately 1.5 for tezacaftor and 2.2 for ivacaftor.
Exposures of tezacaftor (administered alone or in combination with ivacaftor) increase in an approximately dose-proportional manner with increasing doses from 10 mg to 300 mg once daily. Key pharmacokinetic parameters for tezacaftor and ivacaftor at steady state are shown in Table 7. Table 7: Mean (SD) Pharmacokinetic Parameters of Tezacaftor and Ivacaftor at Steady State in Patients with CF Drug C max (mcg/mL) Effective t ½ (h) AUC 0-24h or AUC 0-12h (mcg∙h/mL) AUC 0-24h for tezacaftor and AUC 0-12h for ivacaftor Tezacaftor 100 mg once daily/ivacaftor 150 mg every 12 hours Tezacaftor 5.95 (1.50) 15.0 (3.44) 84.5 (27.8) Ivacaftor 1.17 (0.424) 13.7 (6.06) 11.3 (4.60) Absorption After a single dose in healthy subjects in the fed state, tezacaftor was absorbed with a median (range) time to maximum concentration (t max ) of approximately 4 hours (2 to 6 hours).
The median (range) t max of ivacaftor was approximately 6 hours (3 to 10 hours) in the fed state. When a single dose of tezacaftor/ivacaftor was administered with fat-containing foods, tezacaftor exposure was similar and ivacaftor exposure was approximately 3 times higher than when taken in a fasting state. Distribution Tezacaftor is approximately 99% bound to plasma proteins, primarily to albumin.
Ivacaftor is approximately 99% bound to plasma proteins, primarily to alpha 1-acid glycoprotein and albumin. After oral administration of tezacaftor 100 mg once daily/ivacaftor 150 mg every 12 hours in patients with CF in the fed state, the mean (±SD) for apparent volume of distribution of tezacaftor and ivacaftor was 271 (157) L and 206 (82.9) L, respectively. Neither tezacaftor nor ivacaftor partition preferentially into human red blood cells.
Elimination After oral administration of tezacaftor 100 mg once daily/ivacaftor 150 mg every 12 hours in patients with CF in the fed state, the mean (±SD) for apparent clearance values of tezacaftor and ivacaftor were 1.31 (0.41) and 15.7 (6.38) L/h, respectively. After steady-state dosing of tezacaftor in combination with ivacaftor in patients with CF, the effective half-lives of tezacaftor and ivacaftor were approximately 15 (3.44) and 13.7 (6.06) hours, respectively. Metabolism Tezacaftor is metabolized extensively in humans.
In vitro data suggested that tezacaftor is metabolized mainly by CYP3A4 and CYP3A5. Following oral administration of a single dose of 100 mg 14 C-tezacaftor to healthy male subjects, M1, M2, and M5 were the three major circulating metabolites of tezacaftor in humans. M1 has the similar potency to that of tezacaftor and is considered pharmacologically active.
M2 is much less pharmacologically active than tezacaftor or M1, and M5 is not considered pharmacologically active. Another minor circulating metabolite, M3, is formed by direct glucuronidation of tezacaftor. Ivacaftor is also metabolized extensively in humans.
In vitro and in vivo data indicate that ivacaftor is metabolized primarily by CYP3A4 and CYP3A5. M1 and M6 are the two major metabolites of ivacaftor in humans. M1 has approximately one-sixth the potency of ivacaftor and is considered pharmacologically active.
M6 is not considered pharmacologically active. Excretion Following oral administration of 14 C-tezacaftor, the majority of the dose (72%) was excreted in the feces (unchanged or as the M2 metabolite) and about 14% was recovered in urine (mostly as M2 metabolite), resulting in a mean overall recovery of 86% up to 21 days after the dose. Less than 1% of the administrated dose… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Effects on Sweat Chloride In Trial 1 (patients aged 12 years and older who were homozygous for the F508del mutation), the treatment difference between SYMDEKO and placebo in mean absolute change from baseline in sweat chloride through Week 24 was -10.1 mmol/L (95% CI: -11.4, -8.8). In Trial 2 (patients aged 12 years and older who were heterozygous for the F508del mutation and a second mutation predicted to be responsive to tezacaftor/ivacaftor), the treatment difference in mean absolute change from baseline in sweat chloride through Week 8 was -9.5 mmol/L (95% CI: -11.7, -7.3) between SYMDEKO and placebo, and -4.5 mmol/L (95% CI: -6.7, -2.3) between ivacaftor and placebo.
In Trial 4 (patients aged 6 to less than 12 years) a reduction in sweat chloride was observed from baseline through Week 4 and sustained throughout the 24-week treatment period. Mean absolute change in sweat chloride from baseline through Week 24 was -14.5 mmol/L (95% CI: -17.4, -11.6). Cardiac Electrophysiology At a dose 3 times the maximum approved recommended dose, tezacaftor does not prolong the QT interval to any clinically relevant extent.
In a separate study of ivacaftor evaluating doses up to 3 times the maximum approved recommended dose, ivacaftor does not prolong the QT interval to any clinically relevant extent.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Dose Ranging : Dose selection for the clinical program primarily consisted of one double-blind, placebo-controlled, multiple-cohort trial which included 176 patients with CF (homozygous for the F508del mutation) 18 years of age and older with a screening ppFEV1≥40. In the study, 34 and 106 patients, respectively, received tezacaftor at once-daily doses of 10 mg, 30 mg, 100 mg, or 150 mg alone or in combination with ivacaftor 150 mg q12h, and 33 patients received placebo. During the 28-day treatment period, dose-dependent increases in mean ppFEV 1 change from baseline were observed with tezacaftor in combination with ivacaftor.
Tezacaftor/ivacaftor in general had a greater mean treatment effect than tezacaftor alone. No additional benefit was observed at tezacaftor doses greater than 100 mg daily. Efficacy : The efficacy of SYMDEKO in patients with CF aged 12 years and older was evaluated in three double-blind, placebo-controlled trials (Trials1, 2, and 3).
Trial 1 was a 24-week randomized, double-blind, placebo-controlled, two-arm study in patients with CF who were homozygous for the F508del mutation in the CFTR gene. Trial 2 was a randomized, double-blind, placebo-controlled, 2-period, 3-treatment, 8-week crossover study in patients with CF who were heterozygous for the F508del mutation and a second mutation predicted to be responsive to tezacaftor/ivacaftor. Mutations predicted to be responsive were selected for the study based on the clinical phenotype (pancreatic sufficiency), biomarker data (sweat chloride), and in vitro responsiveness to tezacaftor/ivacaftor [see Clinical Studies (14.2) ] .
Patients were randomized to and received sequences of treatment that included SYMDEKO, ivacaftor, and placebo. Trial 3 was a 12-week randomized, double-blind, placebo-controlled, two-arm study in patients with CF who were heterozygous for the F508del mutation and a second CFTR mutation predicted to be unresponsive to tezacaftor/ivacaftor. Mutations predicted to be non-responsive were selected for the study based on biologic plausibility (mutation class), clinical phenotype (pancreatic insufficiency), biomarker data (sweat chloride), and in vitro testing to tezacaftor and/or ivacaftor.
Patients in all trials continued on their standard-of-care CF therapies (e.g . , bronchodilators, inhaled antibiotics, dornase alfa, and hypertonic saline) and were eligible to roll over into a 96-week open-label extension. Patients had a ppFEV 1 at screening between 40-90%. Patients with a history of colonization with organisms associated with a more rapid decline in pulmonary status such as Burkholderia cenocepacia , Burkholderia dolosa , or Mycobacterium abscessus , or who had 2 or more abnormal liver function tests at screening (ALT, AST, AP, GGT ≥3 × ULN or total bilirubin ≥2 × ULN) or AST or ALT ≥5 × ULN, were excluded from the trials.
14.1Trial in Patients with CF Who Were Homozygous for the F508del Mutation in the CFTR Gene (Trial 1) Trial 1 evaluated 504 patients (248 SYMDEKO, 256 placebo) with CF aged 12 years and older (mean age 26.3 years). The mean ppFEV 1 at baseline was 60.0% (range: 27.8% to 96.2%). The primary efficacy endpoint was change in lung function as determined by absolute change from baseline in ppFEV 1 through Week 24.
Treatment with SYMDEKO resulted in a statistically significant improvement in ppFEV 1 . The treatment difference between SYMDEKO and placebo for the mean absolute change in ppFEV 1 from baseline through Week 24 was 4.0 percentage points (95% CI: 3.1, 4.8; P< 0.0001). These changes persisted throughout the 24-week treatment period (Figure 1).
Improvements in ppFEV 1 were observed regardless of age, sex, baseline ppFEV 1 , colonization with Pseudomonas , concomitant use of standard-of-care medications for CF, and geographic region. Key secondary efficacy variables included relative change from baseline in ppFEV 1 through Week 24; number of pulmonary exacerbations from baseline through Week 24;… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No studies of carcinogenicity, mutagenicity, or impairment of fertility were conducted with the combination of tezacaftor and ivacaftor, however, separate studies of tezacaftor and ivacaftor are described below. Tezacaftor A 2-year study in Sprague-Dawley rats and a 6-month study in Tg.rasH2 transgenic mice were conducted to assess the carcinogenic potential of tezacaftor. No evidence of tumorigenicity from tezacaftor was observed in male and female rats at oral doses up to 50 and 75 mg/kg/day (approximately 2 and 3 times the MRHD based on summed AUCs of tezacaftor and its metabolites in males and females, respectively).
No evidence of tumorigenicity was observed in male and female Tg.rasH2 transgenic mice at tezacaftor doses up to 500 mg/kg/day. Tezacaftor was negative for genotoxicity in the following assays: Ames test for bacterial gene mutation, in vitro chromosomal aberration assay in Chinese hamster ovary cells, and in vivo mouse micronucleus test. There were no effects on male or female fertility and early embryonic development in rats at oral tezacaftor doses up to 100 mg/kg/day (approximately 3 times the MRHD based on summed AUC of tezacaftor and M1 metabolite).
Ivacaftor Two-year studies were conducted in CD-1 mice and Sprague-Dawley rats to assess the carcinogenic potential of ivacaftor. No evidence of tumorigenicity from ivacaftor was observed in mice or rats at oral doses up to 200 mg/kg/day and 50 mg/kg/day, respectively (approximately equivalent to 2 and 9 times the MRHD, respectively, based on summed AUCs of ivacaftor and its metabolites). Ivacaftor was negative for genotoxicity in the following assays: Ames test for bacterial gene mutation, in vitro chromosomal aberration assay in Chinese hamster ovary cells, and in vivo mouse micronucleus test.
Ivacaftor impaired fertility and reproductive performance indices in male and female rats at 200 mg/kg/day (approximately 9 and 6 times, respectively, the MRHD based on summed AUCs of ivacaftor and its metabolites). Increases in prolonged diestrus were observed in females at 200 mg/kg/day. Ivacaftor also increased the number of females with all nonviable embryos and decreased corpora lutea, implantations, and viable embryos in rats at 200 mg/kg/day (approximately 6 times the MRHD based on summed AUCs of ivacaftor and its metabolites) when dams were dosed prior to and during early pregnancy.
These impairments of fertility and reproductive performance in male and female rats at 200 mg/kg/day were attributed to severe toxicity. No effects on male or female fertility and reproductive performance indices were observed at ≤100 mg/kg/day (approximately 6 and 4 times, respectively, the MRHD based on summed AUCs of ivacaftor and its metabolites).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No studies of carcinogenicity, mutagenicity, or impairment of fertility were conducted with the combination of tezacaftor and ivacaftor, however, separate studies of tezacaftor and ivacaftor are described below. Tezacaftor A 2-year study in Sprague-Dawley rats and a 6-month study in Tg.rasH2 transgenic mice were conducted to assess the carcinogenic potential of tezacaftor. No evidence of tumorigenicity from tezacaftor was observed in male and female rats at oral doses up to 50 and 75 mg/kg/day (approximately 2 and 3 times the MRHD based on summed AUCs of tezacaftor and its metabolites in males and females, respectively).
No evidence of tumorigenicity was observed in male and female Tg.rasH2 transgenic mice at tezacaftor doses up to 500 mg/kg/day. Tezacaftor was negative for genotoxicity in the following assays: Ames test for bacterial gene mutation, in vitro chromosomal aberration assay in Chinese hamster ovary cells, and in vivo mouse micronucleus test. There were no effects on male or female fertility and early embryonic development in rats at oral tezacaftor doses up to 100 mg/kg/day (approximately 3 times the MRHD based on summed AUC of tezacaftor and M1 metabolite).
Ivacaftor Two-year studies were conducted in CD-1 mice and Sprague-Dawley rats to assess the carcinogenic potential of ivacaftor. No evidence of tumorigenicity from ivacaftor was observed in mice or rats at oral doses up to 200 mg/kg/day and 50 mg/kg/day, respectively (approximately equivalent to 2 and 9 times the MRHD, respectively, based on summed AUCs of ivacaftor and its metabolites). Ivacaftor was negative for genotoxicity in the following assays: Ames test for bacterial gene mutation, in vitro chromosomal aberration assay in Chinese hamster ovary cells, and in vivo mouse micronucleus test.
Ivacaftor impaired fertility and reproductive performance indices in male and female rats at 200 mg/kg/day (approximately 9 and 6 times, respectively, the MRHD based on summed AUCs of ivacaftor and its metabolites). Increases in prolonged diestrus were observed in females at 200 mg/kg/day. Ivacaftor also increased the number of females with all nonviable embryos and decreased corpora lutea, implantations, and viable embryos in rats at 200 mg/kg/day (approximately 6 times the MRHD based on summed AUCs of ivacaftor and its metabolites) when dams were dosed prior to and during early pregnancy.
These impairments of fertility and reproductive performance in male and female rats at 200 mg/kg/day were attributed to severe toxicity. No effects on male or female fertility and reproductive performance indices were observed at ≤100 mg/kg/day (approximately 6 and 4 times, respectively, the MRHD based on summed AUCs of ivacaftor and its metabolites).
📄 Patient Package Insert ▾
PATIENT INFORMATION SYMDEKO (SIM-deh-koh) (tezacaftor/ivacaftor tablets; ivacaftor tablets) for oral use What is SYMDEKO? SYMDEKO is a prescription medicine used for the treatment of cystic fibrosis (CF) in patients aged 6 years and older who have two copies of the F508del mutation, or who have at least one mutation in the CF gene that is responsive to treatment with SYMDEKO. Talk to your doctor to learn if you have an indicated CF gene mutation.
It is not known if SYMDEKO is safe and effective in children under 6 years of age. Before taking SYMDEKO, tell your doctor about all of your medical conditions, including if you: have or have had liver problems. are allergic to SYMDEKO or any ingredients in SYMDEKO. See the end of this patient information leaflet for a complete list of ingredients in SYMDEKO. have kidney problems. have or have had mental health problems. are pregnant or plan to become pregnant.
It is not known if SYMDEKO will harm your unborn baby. You and your doctor should decide if you will take SYMDEKO while you are pregnant. are breastfeeding or planning to breastfeed. It is not known if SYMDEKO passes into your breast milk.
You and your doctor should decide if you will take SYMDEKO while you are breastfeeding. Tell your doctor about all the medicines you take , including prescription and over-the-counter medicines, vitamins, and herbal supplements, SYMDEKO may affect the way other medicines work and other medicines may affect how SYMDEKO works. The dosage of SYMDEKO may need to be adjusted when taken with certain medicines.
Ask your doctor or pharmacist for a list of these medicines if you are not sure. Especially tell your doctor if you take: antibiotics such as rifampin (RIFAMATE ® , RIFATER ® ) or rifabutin (MYCOBUTIN ® ) seizure medicines such as phenobarbital, carbamazepine (TEGRETOL ® , CARBATROL ® , EQUETRO ® ), or phenytoin (DILANTIN ® , PHENYTEK ® ) St. John's wort antifungal medicines such as ketoconazole, itraconazole (such as SPORANOX ® ), posaconazole (such as NOXAFIL ® ), voriconazole (such as VFEND ® ), or fluconazole (such as DIFLUCAN ® ) antibiotics such as telithromycin, clarithromycin ( e.g. , BIAXIN ® ), or erythromycin (such as ERY-TAB ® ) Know the medicines you take.
Keep a list of them to show your doctor and pharmacist when you get a new medicine. How should I take SYMDEKO? Take SYMDEKO exactly as your doctor tells you to take it.
Take SYMDEKO by mouth only. Always take SYMDEKO with food that contains fat . Examples of fat-containing foods include eggs, butter, peanut butter, cheese pizza, and whole-milk dairy products such as whole milk, cheese, and yogurt.
SYMDEKO consists of 2 different tablets. SYMDEKO Tablets (age 6 to less than 12 years weighing less than 30 kg): The white tablet is marked with 'V50' and contains the medicines tezacaftor and ivacaftor. Take 1 white tablet in the morning.
The light blue tablet is marked with 'V 75' and contains the medicine ivacaftor. Take 1 light blue tablet in the evening. SYMDEKO Tablets (age 6 to less than 12 years weighing 30 kg or more and age 12 years and older): The yellow tablet is marked with 'V100' and contains the medicines tezacaftor and ivacaftor.
Take 1 yellow tablet in the morning. The light blue tablet is marked with 'V 150' and contains the medicine ivacaftor. Take 1 light blue tablet in the evening.
Take the morning and the evening tablet about 12 hours apart. If you miss a dose of SYMDEKO and: it is 6 hours or less from the time you usually take the yellow tablet in the morning or the light blue tablet in the evening, take the missed dose with food that contains fat as soon as you can. Then take your next dose at your usual time. it is more than 6 hours from the time you usually take the yellow tablet in the morning or the light blue tablet in the evening, do not take the missed dose .
Take your next dose at the usual time with food that contains fat. Do not take more than your recommended dose of SYMDEKO to make up for a missed d… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Warnings and Precautions, Intracranial Hypertension ( 5.3 ) 09/2025 Warnings and Precautions, Neuropsychiatric Events, Including Suicidal Thoughts and Behaviors ( 5.4 ) 03/2026
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - Kit Carton Rx Only NDC 51167-661-01 symdeko ® (tezacaftor/ivacaftor) 100 mg/150 mg and (ivacaftor) 150 mg tablets 56 tablets Contains 4-week supply of SYMDEKO 4 weekly blister cards, each with 14 tablets: (7 tezacaftor/ivacaftor and 7 ivacaftor tablets) LIFT HERE TO OPEN ▶ PRINCIPAL DISPLAY PANEL - Kit Carton
PRINCIPAL DISPLAY PANEL - Kit Carton - 113 Rx Only NDC 51167-113-01 symdeko ® (tezacaftor/ivacaftor) 50 mg/75 mg and (ivacaftor) 75 mg tablets 56 tablets Contains 4-week supply of SYMDEKO 4 weekly blister cards, each with 14 tablets: (7 tezacaftor/ivacaftor and 7 ivacaftor tablets) LIFT HERE TO OPEN ▶ PRINCIPAL DISPLAY PANEL - Kit Carton - 113
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |