
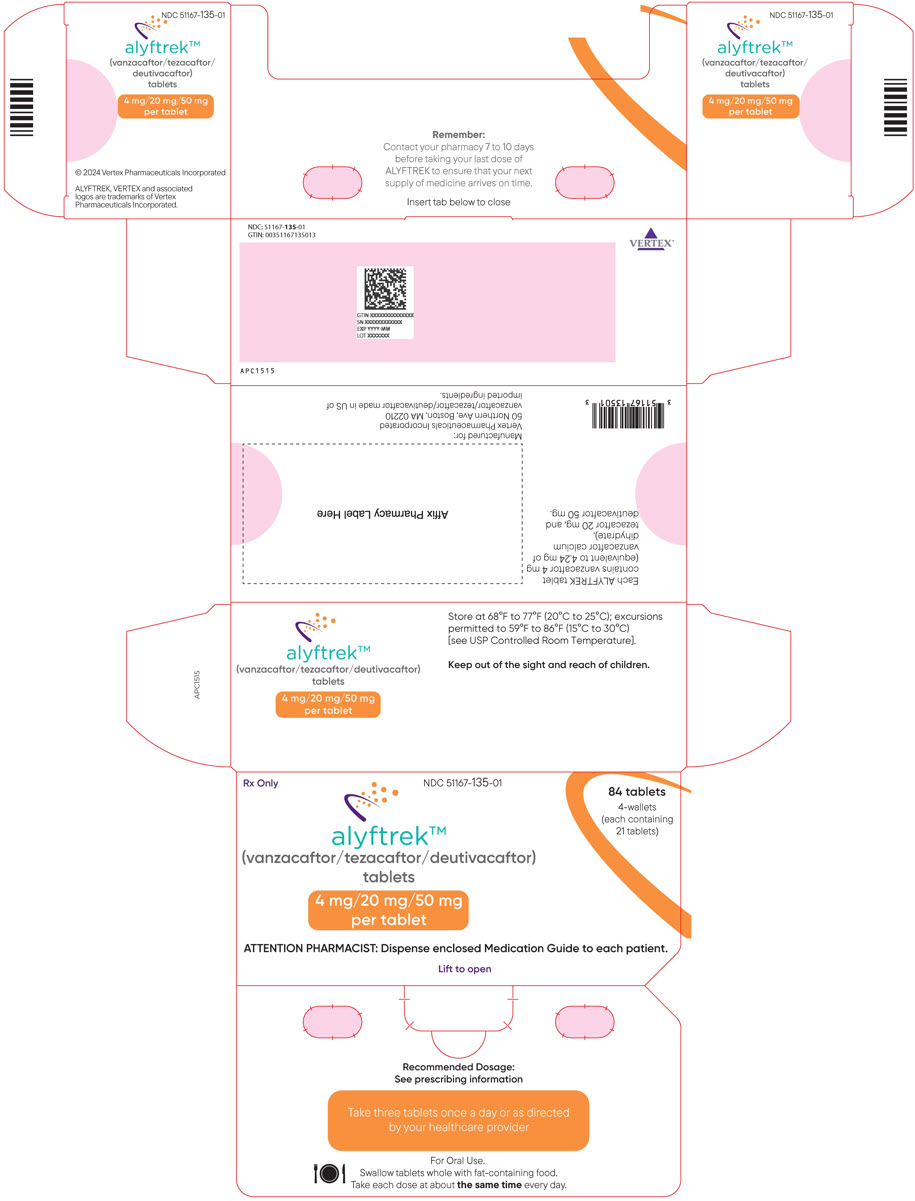
ALYFTREK vanzacaftor, tezacaftor, and deutivacaftor 4 mg; 20 mg; 50 mg Tablet, Film Coated
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Other respiratory system products class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Vanzacaftor, tezacaftor, and deutivacaftor is used to treat certain types of cystic fibrosis (CF; an inherited condition that affects the lungs and other parts of the body). Vanzacaftor and tezacaftor are in a class of medications called cystic fibrosis transmembrane conductance regulator (CFTR) correctors. Deutivacaftor is in a class of medications called cystic fibrosis transmembrane conductance regulator (CFTR) potentiators. These medications work together to improve the function of a protein in the body to help decrease the build-up of thick mucus in the lungs and manage other CF symptoms...
Read the full MedlinePlus article ↗Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII 9XZ8H6N6OH
A plant-based cellulose derivative used as a binder to hold tablet ingredients together, a thickener in liquids, and a coating agent to control how fast the medicine dissolves.
-
UNII 36SFW2JZ0W
Hypromellose 2910 is a plant-based thickening agent derived from cellulose. In medicines, it forms a protective coating on tablets or capsules and controls how quickly the drug dissolves and releases into your body.
-
UNII 6N003M473W
Hypromellose acetate succinate is a modified cellulose polymer that dissolves in the small intestine. It's used as a coating material to protect the medicine from stomach acid and control where and when the drug is released in the digestive tract.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
12 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $330.13 | $27,730.82 / 84 tablets |
| Medicare drug plans payPart D · Q2 2026 | $343.96 | $28,892.62 / 84 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Alyftrek 4 mg/1; 20 mg/1; 50 mgthis 51167-0135-01 | Vertex | 21 tablets | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9670163 ↗ | Method of use | U-4080 | Dec 28, 2026 |
| US 9670163 ↗ | Method of use | U-4080 | Dec 28, 2026 |
| US 10022352 ↗ | Method of use | U-4081 | Apr 9, 2027 |
| US 10022352 ↗ | Method of use | U-4081 | Apr 9, 2027 |
| US 9974781 ↗ | Method of use | U-4082 | Apr 9, 2027 |
| US 9974781 ↗ | Method of use | U-4082 | Apr 9, 2027 |
| US 11873300 ↗ | Drug substance | U-4083 | Aug 13, 2040 |
| US 11873300 ↗ | Drug substance | U-4083 | Aug 13, 2040 |
| US 8415387 ↗ | Method of use | U-4082 | Nov 12, 2027 |
| US 8415387 ↗ | Method of use | U-4082 | Nov 12, 2027 |
| US 10081621 ↗ | Method of use | U-4087 | Mar 25, 2031 |
| US 10081621 ↗ | Method of use | U-4087 | Mar 25, 2031 |
| US 12186306 ↗ | Method of use | U-4088 | Jan 10, 2043 |
| US 11951212 ↗ | Method of use | U-4089 | Apr 14, 2035 |
| US 11866450 ↗ | Method of use | U-4082 | Feb 14, 2039 |
| US 11866450 ↗ | Method of use | U-4082 | Feb 14, 2039 |
| US 8598181 ↗ | Method of use | U-4090 | May 1, 2027 |
| US 8598181 ↗ | Method of use | U-4090 | May 1, 2027 |
| US 8354427 ↗ | Method of use | U-4091 | Jul 6, 2026 |
| US 8354427 ↗ | Method of use | U-4091 | Jul 6, 2026 |
| US 10206877 ↗ | Method of use | U-4092 | Apr 14, 2035 |
| US 9181192 ↗ | Drug substance | U-4094 | May 17, 2032 |
| US 9181192 ↗ | Drug substance | U-4094 | May 17, 2032 |
| US 8324242 ↗ | Method of use | U-4090 | Aug 5, 2027 |
| US 8324242 ↗ | Method of use | U-4090 | Aug 5, 2027 |
| US 10239867 ↗ | Drug substance | U-4090 | Apr 9, 2027 |
| US 10239867 ↗ | Drug substance | U-4090 | Apr 9, 2027 |
| US 11564916 ↗ | Method of use | U-4095 | Aug 13, 2029 |
| US 11564916 ↗ | Method of use | U-4095 | Aug 13, 2029 |
| US 11639347 ↗ | Drug substance | U-4090 | Apr 9, 2027 |
| US 11639347 ↗ | Drug substance | U-4090 | Apr 9, 2027 |
| US 11578062 ↗ | Method of use | U-4096 | Mar 25, 2031 |
| US 11578062 ↗ | Method of use | U-4096 | Mar 25, 2031 |
| US 9012496 ↗ | Method of use | U-4097 | Jul 15, 2033 |
| US 9512079 ↗ | Drug substance | U-4098 | May 17, 2032 |
| US 9512079 ↗ | Drug substance | U-4098 | May 17, 2032 |
| US 9931334 ↗ | Method of use | U-4080 | Dec 28, 2026 |
| US 9931334 ↗ | Method of use | U-4080 | Dec 28, 2026 |
| US 10058546 ↗ | Method of use | U-4218 | Jul 15, 2033 |
| US 11873300 ↗ | Drug substance | U-4462 | Aug 13, 2040 |
| US 11873300 ↗ | Drug substance | U-4462 | Aug 13, 2040 |
| US 11866450 ↗ | Method of use | U-4463 | Feb 14, 2039 |
| US 11866450 ↗ | Method of use | U-4463 | Feb 14, 2039 |
| US 11639347 ↗ | Drug substance | U-4464 | Apr 9, 2027 |
| US 11639347 ↗ | Drug substance | U-4464 | Apr 9, 2027 |
| US 11578062 ↗ | Method of use | U-4465 | Mar 25, 2031 |
| US 11578062 ↗ | Method of use | U-4465 | Mar 25, 2031 |
| US 11564916 ↗ | Method of use | U-4466 | Aug 13, 2029 |
| US 11564916 ↗ | Method of use | U-4466 | Aug 13, 2029 |
| US 10239867 ↗ | Drug substance | U-4464 | Apr 9, 2027 |
| US 10239867 ↗ | Drug substance | U-4464 | Apr 9, 2027 |
| US 10206877 ↗ | Method of use | U-4467 | Apr 14, 2035 |
| US 10081621 ↗ | Method of use | U-4468 | Mar 25, 2031 |
| US 10081621 ↗ | Method of use | U-4468 | Mar 25, 2031 |
| US 9974781 ↗ | Method of use | U-4463 | Apr 9, 2027 |
| US 9974781 ↗ | Method of use | U-4463 | Apr 9, 2027 |
| US 9931334 ↗ | Method of use | U-4469 | Dec 28, 2026 |
| US 9931334 ↗ | Method of use | U-4469 | Dec 28, 2026 |
| US 9670163 ↗ | Method of use | U-4470 | Dec 28, 2026 |
| US 9670163 ↗ | Method of use | U-4470 | Dec 28, 2026 |
| US 9512079 ↗ | Drug substance | U-4471 | May 17, 2032 |
| US 9512079 ↗ | Drug substance | U-4471 | May 17, 2032 |
| US 9181192 ↗ | Drug substance | U-4472 | May 17, 2032 |
| US 9181192 ↗ | Drug substance | U-4472 | May 17, 2032 |
| US 8598181 ↗ | Method of use | U-4463 | May 1, 2027 |
| US 8598181 ↗ | Method of use | U-4463 | May 1, 2027 |
| US 8415387 ↗ | Method of use | U-4463 | Nov 12, 2027 |
| US 8415387 ↗ | Method of use | U-4463 | Nov 12, 2027 |
| US 8324242 ↗ | Method of use | U-4464 | Aug 5, 2027 |
| US 8324242 ↗ | Method of use | U-4464 | Aug 5, 2027 |
| US 12186306 ↗ | Method of use | U-4460 | Jan 10, 2043 |
| US 11951212 ↗ | Method of use | U-4461 | Apr 14, 2035 |
| US 10646481 ↗ | Drug product | — | Aug 13, 2029 |
| US 8623905 ↗ | Drug substance | — | May 1, 2027 |
| US 11066417 ↗ | Drug substance | — | Feb 14, 2039 |
| US 8865902 ↗ | Drug substance | — | May 17, 2032 |
| US 8754224 ↗ | Drug substance | — | Dec 28, 2026 |
| US 7776905 ↗ | Drug substance | — | Jun 3, 2027 |
| US RE50453 ↗ | Drug substance | — | Jul 10, 2031 |
| US 7776905 ↗ | Drug substance | — | Jun 3, 2027 |
| US 7645789 ↗ | Drug substance | — | May 1, 2027 |
| US 7495103 ↗ | Drug substance | — | May 20, 2027 |
| US 7645789 ↗ | Drug substance | — | May 1, 2027 |
| US 8623905 ↗ | Drug substance | — | May 1, 2027 |
| US 10646481 ↗ | Drug product | — | Aug 13, 2029 |
| US 10047053 ↗ | Drug substance | — | May 17, 2032 |
| US 8865902 ↗ | Drug substance | — | May 17, 2032 |
| US 11066417 ↗ | Drug substance | — | Feb 14, 2039 |
| US 10047053 ↗ | Drug substance | — | May 17, 2032 |
| US 8410274 ↗ | Drug product | — | Dec 28, 2026 |
| US 7495103 ↗ | Drug substance | — | May 20, 2027 |
| US RE50453 ↗ | Drug substance | — | Jul 10, 2031 |
| US 8754224 ↗ | Drug substance | — | Dec 28, 2026 |
| US 8410274 ↗ | Drug product | — | Dec 28, 2026 |
| Code | What it grants | Expires |
|---|---|---|
| NCE | New Chemical Entity (5-year) | Dec 20, 2029 |
| ODE-526 | Orphan Drug Exclusivity (7-year) | Dec 20, 2031 |
| ODE-536 | Orphan Drug Exclusivity (7-year) | Mar 27, 2033 |
| NCE | New Chemical Entity (5-year) | Dec 20, 2029 |
| ODE-526 | Orphan Drug Exclusivity (7-year) | Dec 20, 2031 |
| ODE-536 | Orphan Drug Exclusivity (7-year) | Mar 27, 2033 |
Is there a generic version of ALYFTREK 4-20-50 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 51167-0135-01 You're viewing this | 4 BLISTER PACK in 1 CARTON (51167-135-01) / 21 TABLET, FILM COATED in 1 BLISTER PACK | 2024-12-20 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: DRUG-INDUCED LIVER INJURY AND LIVER FAILURE Elevated transaminases have been observed in patients treated with ALYFTREK. Cases of serious and potentially fatal drug-induced liver injury and liver failure were reported in patients who were taking a fixed-dose combination drug containing elexacaftor, tezacaftor, and ivacaftor, which contains the same or similar active ingredients as ALYFTREK. Liver injury has been reported within the first month of therapy and up to 15 months following initiation of elexacaftor/tezacaftor/ivacaftor [see Warnings and Precautions (5.1) and Adverse Reactions (6) ].
Assess liver function tests (ALT, AST, alkaline phosphatase, and bilirubin) in all patients prior to initiating ALYFTREK, every month during the first 6 months of treatment, then every 3 months for the next 12 months, then at least annually thereafter. Consider more frequent monitoring for patients with a history of liver disease or elevated liver function tests at baseline [see Dosage and Administration (2.1) , Warnings and Precautions (5.1) , Adverse Reactions (6) , and Use in Specific Populations (8.7) ] . Interrupt ALYFTREK for significant elevations in liver function tests or in the event of signs or symptoms of liver injury.
Consider referral to a hepatologist. Follow patients closely with clinical and laboratory monitoring until abnormalities resolve. If abnormalities resolve, resume treatment only if the benefit is expected to outweigh the risk.
Closer monitoring is advised after resuming ALYFTREK [see Warnings and Precautions (5.1) ] . ALYFTREK should not be used in patients with severe hepatic impairment (Child-Pugh Class C). ALYFTREK is not recommended in patients with moderate hepatic impairment (Child-Pugh Class B) and should only be considered when there is a clear medical need, and the benefit outweighs the risk.
If used, monitor patients closely [see Dosage and Administration (2.4) , Warnings and Precautions (5.1) , Adverse Reactions (6) , Use in Specific Populations (8.7) , and Clinical Pharmacology (12.3) ] . WARNING: DRUG-INDUCED LIVER INJURY AND LIVER FAILURE See full prescribing information for complete boxed warning. Elevated transaminases have been observed in patients treated with ALYFTREK ( 5.1 , 6 ).
Cases of serious and potentially fatal drug-induced liver injury and liver failure leading to transplantation and death were reported in patients who were taking ELX/TEZ/IVA, a drug containing the same or similar active ingredients as ALYFTREK ( 5.1 ). Assess liver function tests (ALT, AST, alkaline phosphatase, bilirubin) in all patients prior to initiating ALYFTREK, every month for first 6 months, every 3 months for next 12 months, then at least annually ( 2.1 , 5.1 ). Interrupt ALYFTREK for significant elevations in LFTs or signs or symptoms of liver injury.
Follow patients closely with clinical and laboratory monitoring until abnormalities resolve ( 5.1 ). Resume ALYFTREK if abnormalities resolve and only if the benefit is expected to outweigh the risk ( 5.1 ). ALYFTREK should not be used in patients with severe hepatic impairment (Child-Pugh Class C).
ALYFTREK is not recommended in patients with moderate hepatic impairment (Child-Pugh Class B) ( 2.4 , 5.1 , 8.7 , 12.3 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ALYFTREK is indicated for the treatment of cystic fibrosis (CF) in adult and pediatric patients 6 years of age and older who have a clinical diagnosis of CF and who have at least one variant in the cystic fibrosis transmembrane conductance regulator ( CFTR ) gene that is either responsive based on clinical and/or in vitro data (see Table 5 ) or results in production of CFTR protein [see Clinical Pharmacology (12.1) ]. If the patient's genotype is unknown, an FDA-cleared CF genetic test should be used to confirm the presence of at least one variant in the CFTR gene that is either responsive based on clinical and/or in vitro data or results in production of CFTR protein.
ALYFTREK is a combination of deutivacaftor, a CFTR potentiator, tezacaftor, and vanzacaftor indicated for the treatment of cystic fibrosis (CF) in adult and pediatric patients aged 6 years and older who have a clinical diagnosis of CF and who have at least one variant in the CFTR gene that is either responsive based on clinical and/or in vitro data or results in production of CFTR protein. ( 1 , 12.1 ) If the patient's genotype is unknown, an FDA-cleared CF genetic test should be used to confirm the presence of at least one variant in the CFTR gene that is either responsive based on clinical and/or in vitro data or results in production of CFTR protein.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Prior to initiating ALYFTREK obtain liver function tests (ALT, AST, alkaline phosphatase, and bilirubin) in all patients. Monitor liver function tests every month during the first 6 months of treatment, then every 3 months during the next 12 months, then at least annually thereafter. ( 2.1 , 5.1 ) Recommended Dosage for Adult and Pediatric Patients Aged 6 Years and Older (with fat-containing food) ( 2.2 ) Age Weight Once Daily Oral Dosage 6 to less than 12 years old Less than 40 kg Three tablets of vanzacaftor 4 mg/tezacaftor 20 mg/deutivacaftor 50 mg Greater than or equal to 40 kg Two tablets of vanzacaftor 10 mg/tezacaftor 50 mg/deutivacaftor 125 mg 12 years and older Any Weight Two tablets of vanzacaftor 10 mg/tezacaftor 50 mg/deutivacaftor 125 mg Should not be used in patients with severe hepatic impairment.
Use not recommended in patients with moderate hepatic impairment unless the benefit outweighs the risk. If used, no dose adjustment is recommended. Liver function tests should be closely monitored.
( 2.4 , 5.1 , 6.1 , 8.7 ) See full prescribing information for dosage modifications for concomitant use of ALYFTREK with strong or moderate CYP3A inhibitors. ( 2.3 , 5.7 , 7.1 )
2.1Recommended Laboratory Testing Prior to ALYFTREK Initiation and During Treatment Prior to initiating ALYFTREK, obtain liver function tests (ALT, AST, alkaline phosphatase, and bilirubin) for all patients. Monitor liver function tests every month during the first 6 months of treatment, then every 3 months for the next 12 months, then at least annually thereafter. Consider more frequent monitoring for patients with a history of liver disease, elevated liver function tests at baseline, or a history of elevated liver function tests with drugs containing elexacaftor, tezacaftor, and/or ivacaftor [see Warnings and Precautions (5.1) and Use in Specific Populations (8.7) ].
2.2Recommended Dosage The recommended ALYFTREK dosage in adult and pediatric patients aged 6 years and older is provided in Table 1. Administer ALYFTREK orally (swallow the tablets whole) with fat-containing food, once daily, at approximately the same time each day [see Clinical Pharmacology (12.3) ]. Examples of meals or snacks that contain fat are those prepared with butter or oils or those containing eggs, peanut butter, cheeses, nuts, whole milk, or meats.
Table 1: Recommended Dosage of ALYFTREK in Adult and Pediatric Patients Aged 6 Years and Older Age Weight Once Daily Oral Dosage 6 to less than 12 years old Less than 40 kg Three tablets of vanzacaftor 4 mg/tezacaftor 20 mg/deutivacaftor 50 mg (total dose of vanzacaftor 12 mg/tezacaftor 60 mg/ deutivacaftor 150 mg) Greater than or equal to 40 kg Two tablets of vanzacaftor 10 mg/tezacaftor 50 mg/deutivacaftor 125 mg (total dose of vanzacaftor 20 mg/tezacaftor 100 mg/ deutivacaftor 250 mg) 12 years and older Any weight Two tablets of vanzacaftor 10 mg/tezacaftor 50 mg/deutivacaftor 125 mg (total dose of vanzacaftor 20 mg/tezacaftor 100 mg/ deutivacaftor 250 mg)
2.3Dosage Modification for Strong or Moderate CYP3A Inhibitors Table 2 describes the recommended dosage modification for ALYFTREK when used concomitantly with strong or moderate CYP3A inhibitors [see Warnings and Precautions (5.7) ] . Administer ALYFTREK orally (swallow the tablets whole) with fat-containing food, once daily, at approximately the same time each day [see Clinical Pharmacology (12.3) ]. Table 2: Dosage Modification for Concomitant Use of ALYFTREK with Strong or Moderate CYP3A Inhibitors in Adult and Pediatric Patients Aged 6 Years and Older Age Weight Moderate CYP3A Inhibitors Strong CYP3A Inhibitors 6 to less than 12 years old Less than 40 kg Two tablets of vanzacaftor 4 mg/tezacaftor 20 mg/deutivacaftor 50 mg every other day (total dose of vanzacaftor 8 mg/tezacaftor 40 mg/deutivacaftor 100 mg) Two tablets of vanzacaftor 4 mg/tezacaftor 20 mg/deutivacaftor 50 mg once a week (total dose of vanzacaftor 8 mg/tezacaftor 40 mg/deuti…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: Fixed-dose combination containing vanzacaftor 4 mg, tezacaftor 20 mg, and deutivacaftor 50 mg. ( 3 ) Fixed-dose combination containing vanzacaftor 10 mg, tezacaftor 50 mg, and deutivacaftor 125 mg. ( 3 ) Tablets: Fixed-dose combination containing vanzacaftor 4 mg (equivalent to 4.24 mg of vanzacaftor calcium dihydrate), tezacaftor 20 mg, and deutivacaftor 50 mg.
Each tablet is purple, round-shaped, film-coated, debossed with "V4" on one side and plain on the other. Fixed-dose combination containing vanzacaftor 10 mg (equivalent to 10.6 mg of vanzacaftor calcium dihydrate), tezacaftor 50 mg, and deutivacaftor 125 mg. Each tablet is purple, oblong-shaped, film-coated, debossed with "V10" on one side and plain on the other.
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Drug-Induced Liver Injury and Liver Failure : Elevated transaminases have been observed in patients treated with ALYFTREK. Cases of serious and potentially fatal drug-induced liver injury and liver failure have been reported with a drug that contains the same or similar active ingredients as ALYFTREK. Assess liver function tests (ALT, AST, alkaline phosphatase, and bilirubin) in all patients prior to initiating and throughout treatment with ALYFTREK.
Interrupt ALYFTREK in the event of significant elevations in liver function tests or signs or symptoms of liver injury. ALYFTREK should not be used in patients with severe hepatic impairment (Child-Pugh Class C). ALYFTREK is not recommended in patients with moderate hepatic impairment (Child-Pugh Class B).
( 2.4 , 5.1 , 8.7 ) Hypersensitivity Reactions : Hypersensitivity reactions, including anaphylaxis, have been reported in the postmarketing setting for drugs containing elexacaftor, tezacaftor, and/or ivacaftor. If signs or symptoms of serious hypersensitivity reactions develop during ALYFTREK treatment, discontinue ALYFTREK and initiate appropriate therapy. ( 5.2 ) Patients Who Discontinued or Interrupted Elexacaftor-, Tezacaftor-, or Ivacaftor-Containing Drugs Due to Adverse Reactions : Consider benefits and risks before using ALYFTREK in patients who discontinued or interrupted elexacaftor-, tezacaftor-, or ivacaftor-containing drugs due to adverse reactions.
If ALYFTREK is used, closely monitor for adverse reactions as clinically appropriate. ( 5.3 ) Intracranial Hypertension : Intracranial hypertension (IH) has been reported in the postmarketing setting with use of drugs containing the same or similar active ingredients as ALYFTREK. If an unusual headache or visual disturbances occur during treatment, and IH is suspected, interrupt ALYFTREK and refer for prompt medical evaluation.
( 5.4 ) Neuropsychiatric Events, Including Suicidal Thoughts and Behaviors: Serious neuropsychiatric events, including symptoms of anxiety, depression, suicidal ideation and behavior, and sleep disturbances, have been reported in the postmarketing setting for ALYFTREK or drugs containing the same or similar active ingredients. Monitor patients closely for new or worsening symptoms. Consider the risks and benefits for the individual patient to determine if therapy with ALYFTREK should be interrupted at the occurrence of neuropsychiatric symptoms.
( 5.5 ) Reduced Effectiveness in Patients with Concomitant Use with CYP3A Inducers : Concomitant use with strong and moderate CYP3A inducers decreased vanzacaftor, tezacaftor, and deutivacaftor exposure, which may reduce ALYFTREK efficacy. Therefore, concomitant use is not recommended. ( 5.6 , 7.1 ) Adverse Reactions with Concomitant Use with CYP3A Inhibitors : Concomitant use with strong or moderate CYP3A inhibitors increased vanzacaftor, tezacaftor, and deutivacaftor exposure, which may increase the risk of ALYFTREK associated adverse reactions.
Reduce the ALYFTREK dosage with concomitant use. ( 2.3 , 5.7 , 7.1 ) Cataracts : Non-congenital lens opacities/cataracts have been reported in patients with CF aged 18 years or less treated with drugs containing ivacaftor. Baseline and follow up ophthalmological examinations are recommended in pediatric patients treated with ALYFTREK.
( 5.8 , 8.4 )
5.1Drug-Induced Liver Injury and Liver Failure Elevated transaminases have been observed in patients treated with ALYFTREK [see Adverse Reactions (6.1) ] . Cases of serious and potentially fatal drug-induced liver injury and liver failure have been reported in patients with and without a history of liver disease who were taking a fixed-dose combination drug containing elexacaftor, tezacaftor, and ivacaftor (ELX/TEZ/IVA), which contains the same or similar active ingredients as ALYFTREK. Liver injury has been reported within the first month of therapy and up to 15 months following initiation of ELX/TEZ/IVA.
Assess liver function tests (ALT, A…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are discussed in greater detail in other sections of the labeling: Drug-Induced Liver Injury and Liver Failure [see Warnings and Precautions (5.1) ] Hypersensitivity Reactions, Including Anaphylaxis [see Warnings and Precautions (5.2) ] Patients Who Discontinued or Interrupted Elexacaftor-, Tezacaftor-, or Ivacaftor-Containing Drugs Due to Adverse Reactions [see Warnings and Precautions (5.3) ] Intracranial Hypertension [see Warnings and Precautions (5.4) ] Neuropsychiatric Events, Including Suicidal Thoughts and Behaviors [see Warnings and Precautions (5.5) ] Cataracts [see Warnings and Precautions (5.8) ] Most common adverse reactions to ALYFTREK (≥5% of patients and at a frequency higher than ELX/TEZ/IVA by ≥1%) were cough, nasopharyngitis, upper respiratory tract infection, headache, oropharyngeal pain, influenza, fatigue, increased ALT, rash, increased AST, and sinus congestion.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Vertex Pharmaceuticals Incorporated at 1-877-634-8789 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. The adverse reactions data below are from clinical trials of ALYFTREK in patients 6 years of age and older with CF with at least one responsive CFTR variant who were able to tolerate ELX/TEZ/IVA. Adverse reactions data in patients who previously discontinued or interrupted ELX/TEZ/IVA due to adverse reactions are not available .
Adverse Reactions in Patients Aged 12 Years and Older with CF The safety of ALYFTREK is based on 480 patients with CF aged 12 years and older who have at least one F508del variant or another responsive variant in the CFTR gene in two, 52-week, active-controlled trials (Trials 1 and 2) [see Clinical Studies (14) ]. In both trials, patients received a fixed-dose combination drug containing elexacaftor, tezacaftor, and ivacaftor (ELX/TEZ/IVA) in a 4-week run-in period and then were subsequently randomized to continue ELX/TEZ/IVA (elexacaftor 200 mg/tezacaftor 100 mg/ivacaftor 150 mg in the morning and ivacaftor 150 mg in the evening) or receive ALYFTREK (vanzacaftor 20 mg/tezacaftor 100 mg/deutivacaftor 250 mg) once daily.
Patients with a history of prior intolerance to ELX/TEZ/IVA (i.e., patients who discontinued or interrupted treatment due to adverse reactions) were excluded. Trials 1 and 2 were not designed to evaluate meaningful comparisons of the incidence of adverse reactions between the ALYFTREK and ELX/TEZ/IVA treatment groups. For additional information regarding ELX/TEZ/IVA adverse reactions, refer to ELX/TEZ/IVA Prescribing Information.
In Trial 1 and Trial 2 combined, the proportion of patients who discontinued treatment prematurely due to adverse reactions were 3.8% and 3.7% in ALYFTREK and ELX/TEZ/IVA treatment groups, respectively. Serious adverse reactions that occurred more frequently with ALYFTREK treatment than with ELX/TEZ/IVA treatment that occurred in 2 or more patients (≥0.4%) were influenza (1.5%), increased AST (0.4%), increased GGT (0.4%), depression (0.4%), and syncope (0.4%). Table 3: Adverse Reactions Occurring in ≥5% of ALYFTREK-Treated Patients and ≥1% Higher than ELX/TEZ/IVA-Treated Patients Aged 12 Years and Older with CF Who Had at Least One F508del Variant or Responsive Variant in the CFTR Gene (Trials 1 and 2) Adverse Reactions ALYFTREK N=480 ELX/TEZ/IVA N=491 Abbreviations: ALT, alanine aminotransferase; AST, aspartate aminotransferase; ELX, elexacaftor; IVA, ivacaftor; TEZ, tezacaftor Cough Cough is composed of several similar terms including productive cough.
120 (25%) 116 (24%) Nasopharyngitis 102 (21%) 95 (19%) Upper respiratory tract infection Upper respir…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Strong or moderate CYP3A inducers : Concomitant use with ALYFTREK is not recommended. ( 5.6 , 7.1 ) Strong or moderate CYP3A inhibitors : Reduce ALYFTREK dosage with concomitant use. Avoid food or drink containing grapefruit. ( 2.3 , 5.7 , 7.1 )
7.1Effect of Other Drugs and Grapefruit on ALYFTREK Strong or Moderate CYP3A Inducers Concomitant use of ALYFTREK with strong or moderate CYP3A inducers is not recommended. Vanzacaftor, tezacaftor, and deutivacaftor are substrates of CYP3A. Concomitant use of ALYFTREK with a strong or moderate CYP3A inducer decreases vanzacaftor, tezacaftor, and deutivacaftor exposure [see Clinical Pharmacology (12.3) ] which may reduce ALYFTREK effectiveness [see Warnings and Precautions (5.6) ] .
Strong or Moderate CYP3A Inhibitors Reduce the ALYFTREK dosage when used concomitantly with a strong or moderate CYP3A inhibitor [see Dosage and Administration (2.3) ] . Vanzacaftor, tezacaftor, and deutivacaftor are CYP3A substrates. Concomitant use with a strong CYP3A inhibitor increases vanzacaftor, tezacaftor, and deutivacaftor exposure [see Clinical Pharmacology (12.3) ] , which may increase the risk of ALYFTREK adverse reactions [see Warnings and Precautions (5.7) ].
Concomitant use with a moderate CYP3A inhibitor is predicted to increase vanzacaftor, tezacaftor, and deutivacaftor exposure [see Clinical Pharmacology (12.3) ] , which may increase the risk of ALYFTREK adverse reactions [see Warnings and Precautions (5.7) ]. Grapefruit Food or drink containing grapefruit should be avoided during treatment with ALYFTREK. Concomitant use of ALYFTREK with grapefruit juice which contains one or more components that moderately inhibit CYP3A may increase exposure of vanzacaftor, tezacaftor and deutivacaftor.
7.2Effect of ALYFTREK on Other Drugs P-glycoprotein (P-gp) Substrates Unless otherwise recommended in the P-gp substrate Prescribing Information, monitor more frequently for adverse reactions with concomitant use of ALYFTREK with P-gp substrates where minimal concentration changes may lead to serious adverse reactions related to P-gp substrates. Tezacaftor and deutivacaftor (components of ALYFTREK) are P-gp inhibitors. Administration of tezacaftor/ivacaftor increases exposure of P-gp substrates [see Clinical Pharmacology (12.3) ] , which may increase the risk of adverse reactions related to these substrates.
Breast Cancer Resistance Protein (BCRP) Substrates Unless otherwise recommended in the BCRP substrate Prescribing Information, monitor more frequently for adverse reactions with concomitant use of ALYFTREK with BCRP substrates where minimal concentration changes may lead to serious adverse reactions related to BCRP substrates. Vanzacaftor (VNZ) and deutivacaftor (D-IVA) (components of ALYFTREK) are inhibitors of BCRP in vitro. Concomitant use of ALYFTREK with BCRP substrates may increase exposure of these substrates; however, this has not been studied clinically [see Clinical Pharmacology (12.3) ].
CYP2C9 Substrates Use caution when ALYFTREK is used concomitantly with CYP2C9 substrates. Monitor the international normalized ratio (INR) more frequently with concomitant use of ALYFTREK with warfarin. This recommendation is based upon a mechanistic understanding of deutivacaftor pharmacokinetics (it is an inhibitor of CYP2C9 in vitro) [see Clinical Pharmacology (12.3) ] .
Concomitant use of ALYFTREK with CYP2C9 substrates may increase exposure of these substrates; however, this has not been studied clinically.
7.3Drugs with No Clinically Significant Interactions with ALYFTREK Ciprofloxacin No clinically relevant effect on the exposure of tezacaftor was observed when tezacaftor/ivacaftor was used concomitantly with ciprofloxacin [see Clinical Pharmacology (12.3) ] . Hormonal Contraceptives No clinically significant differences in the pharmacokinetics of ethinyl estradiol/norethindrone containing hormonal contraceptives were observed when used concomitantly with tezacaftor in combinatio…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no available data on ALYFTREK use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes. Although there are no animal reproduction studies with the concomitant administration of vanzacaftor, tezacaftor, and deutivacaftor, separate reproductive and developmental studies were conducted with vanzacaftor and tezacaftor in pregnant rats and rabbits. Deutivacaftor is a deuterated isotopologue of ivacaftor with a toxicity profile similar to ivacaftor.
Reproductive and development studies were conducted with ivacaftor in pregnant rats and rabbits. In animal embryo fetal development (EFD) studies, oral administration of vanzacaftor to pregnant rats and rabbits during organogenesis demonstrated no adverse developmental effects at doses that produced maternal exposures up to approximately 30 times the exposure at the maximum recommended human dose (MRHD) in rats and 22 times the MRHD in rabbits. Oral administration of tezacaftor to pregnant rats and rabbits during organogenesis demonstrated no adverse developmental effects at doses that produced maternal exposures up to approximately 3 times the exposure at the MRHD in rats and 0.2 times the MRHD in rabbits (based on summed AUCs of tezacaftor and the metabolite M1-TEZ).
Oral administration of ivacaftor to pregnant rats and rabbits during organogenesis demonstrated no adverse developmental effects at doses that produced maternal exposures up to approximately 8 and 9 times the exposure at the MRHD, respectively (based on AUC of ivacaftor for rats and rabbits). No adverse developmental effects were observed after oral administration of vanzacaftor, tezacaftor, or ivacaftor to pregnant rats from the period of organogenesis through lactation at doses that produced maternal exposures approximately 18 times, 1 time, and 8 times the exposures at the MRHD, respectively (based on AUCs of vanzacaftor, tezacaftor and M1-TEZ, and ivacaftor) ( see Data ).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data Vanzacaftor : In an EFD study, pregnant rats were administered vanzacaftor at oral doses of 2.5, 5, and 10 mg/kg/day during the period of organogenesis from gestation Days 6-17. Vanzacaftor did not cause adverse effects to the fetus at exposures up to 30 times the MRHD (based on AUC for vanzacaftor at maternal doses up to 10 mg/kg/day). In an EFD study, pregnant rabbits were administered vanzacaftor at oral doses of 10, 40, and 70 mg/kg/day during the period of organogenesis from gestation Days 7-20.
Vanzacaftor did not cause adverse effects to the fetus at exposures up to 22 times the MRHD (based on AUC of vanzacaftor at maternal doses up to 40 mg/kg/day). The high dose of 70 mg/kg/day (71 times the exposure at the MRHD) produced maternal toxicity (i.e., mortality, abortion, decreased mean body weight or body weight gains) and was associated with findings of increased post-implantation loss, decreased live fetuses, decreased fetal body weight, and increased kidney malformations. In a pre- and postnatal development (PPND) study in pregnant rats administered vanzacaftor at oral doses of 2.5, 5, and 10 mg/kg/day from gestation Day 6 through lactation Day 18, vanzacaftor did not cause adverse developmental effects in pups at maternal doses up to 10 mg/kg/day (approximately 18 times the exposure at the MRHD).
Placental transfer of vanzacaftor was observed in pregnant rats. Tezacaftor: In an EFD study, pregnant rats were administered tezacaftor at oral doses of 25, 50, and 100 mg/kg/day during the period of organogenes…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no available data on ALYFTREK use in pregnant women to evaluate for a drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes. Although there are no animal reproduction studies with the concomitant administration of vanzacaftor, tezacaftor, and deutivacaftor, separate reproductive and developmental studies were conducted with vanzacaftor and tezacaftor in pregnant rats and rabbits. Deutivacaftor is a deuterated isotopologue of ivacaftor with a toxicity profile similar to ivacaftor.
Reproductive and development studies were conducted with ivacaftor in pregnant rats and rabbits. In animal embryo fetal development (EFD) studies, oral administration of vanzacaftor to pregnant rats and rabbits during organogenesis demonstrated no adverse developmental effects at doses that produced maternal exposures up to approximately 30 times the exposure at the maximum recommended human dose (MRHD) in rats and 22 times the MRHD in rabbits. Oral administration of tezacaftor to pregnant rats and rabbits during organogenesis demonstrated no adverse developmental effects at doses that produced maternal exposures up to approximately 3 times the exposure at the MRHD in rats and 0.2 times the MRHD in rabbits (based on summed AUCs of tezacaftor and the metabolite M1-TEZ).
Oral administration of ivacaftor to pregnant rats and rabbits during organogenesis demonstrated no adverse developmental effects at doses that produced maternal exposures up to approximately 8 and 9 times the exposure at the MRHD, respectively (based on AUC of ivacaftor for rats and rabbits). No adverse developmental effects were observed after oral administration of vanzacaftor, tezacaftor, or ivacaftor to pregnant rats from the period of organogenesis through lactation at doses that produced maternal exposures approximately 18 times, 1 time, and 8 times the exposures at the MRHD, respectively (based on AUCs of vanzacaftor, tezacaftor and M1-TEZ, and ivacaftor) ( see Data ).
The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data Vanzacaftor : In an EFD study, pregnant rats were administered vanzacaftor at oral doses of 2.5, 5, and 10 mg/kg/day during the period of organogenesis from gestation Days 6-17. Vanzacaftor did not cause adverse effects to the fetus at exposures up to 30 times the MRHD (based on AUC for vanzacaftor at maternal doses up to 10 mg/kg/day). In an EFD study, pregnant rabbits were administered vanzacaftor at oral doses of 10, 40, and 70 mg/kg/day during the period of organogenesis from gestation Days 7-20.
Vanzacaftor did not cause adverse effects to the fetus at exposures up to 22 times the MRHD (based on AUC of vanzacaftor at maternal doses up to 40 mg/kg/day). The high dose of 70 mg/kg/day (71 times the exposure at the MRHD) produced maternal toxicity (i.e., mortality, abortion, decreased mean body weight or body weight gains) and was associated with findings of increased post-implantation loss, decreased live fetuses, decreased fetal body weight, and increased kidney malformations. In a pre- and postnatal development (PPND) study in pregnant rats administered vanzacaftor at oral doses of 2.5, 5, and 10 mg/kg/day from gestation Day 6 through lactation Day 18, vanzacaftor did not cause adverse developmental effects in pups at maternal doses up to 10 mg/kg/day (approximately 18 times the exposure at the MRHD).
Placental transfer of vanzacaftor was observed in pregnant rats. Tezacaftor: In an EFD study, pregnant rats were administered tezacaftor at oral doses of 25, 50, and 100 mg/kg/day during the period of organogenesis from gestation Days 6-17. T…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of ALYFTREK for the treatment of CF have been established in pediatric patients aged 6 years and older who have a clinical diagnosis of CF and who have at least one variant in the CFTR gene that is either responsive based on clinical and/or in vitro data or results in production of CFTR protein. Use of ALYFTREK for this indication was supported by evidence from two adequate and well-controlled trials (Trials 1 and 2) in patients with CF aged 12 years and older who had at least one F508del variant or another responsive variant in the CFTR gene and additional pharmacokinetic and safety data in pediatric patients with CF aged 6 to less than 12 years who had at least one F508del variant or another responsive variant in the CFTR gene (Trial 3).
In these trials, a total of 145 patients with CF aged 6 to less than 18 years received ALYFTREK including: In Trial 1, 26 adolescents aged 12 to less than 18 years who were heterozygous for F508del and a CFTR variant that is not responsive to ivacaftor or tezacaftor/ivacaftor (minimal function variant) [see Adverse Reactions (6.1) and Clinical Studies (14) ]. In Trial 2, 41 adolescents aged 12 to less than 18 years who were homozygous for F508del variant, heterozygous for F508del variant and either a gating or a residual function variant, or with at least one variant responsive to ELX/TEZ/IVA with no F508del variant [see Adverse Reactions (6.1) and Clinical Studies (14) ].
In Trial 3, 78 pediatric patients with CF aged 6 to less than 12 years (mean age 9.1 years) with at least one variant that is responsive to ELX/TEZ/IVA [see Adverse Reactions (6.1) ] . In Trial 3, patients who weighed less than 40 kg patients received ALYFTREK (vanzacaftor 12 mg/tezacaftor 60 mg/deutivacaftor 150 mg once daily) and patients who weighed 40 kg or more received ALYFTREK (vanzacaftor 20 mg/tezacaftor 100 mg/deutivacaftor 250 mg once daily). The efficacy of ALYFTREK in patients aged 6 to less than 12 years for this indication was extrapolated from patients aged 12 years and older with support from population pharmacokinetic analyses showing vanzacaftor, tezacaftor, and deutivacaftor exposure levels in patients aged 6 to less than 12 years to be within the range of exposures observed in patients aged 12 years and older [see Clinical Pharmacology (12.3) ] .
Safety of ALYFTREK in patients aged 6 to less than 12 years for this indication was based on Trial 3. The overall safety profile of patients in Trial 3 was generally similar to the safety data in adult and pediatric patients 12 years of age and older observed in Trials 1 and 2 [see Adverse Reactions (6.1) ]. There is a risk of cataracts in pediatric patients treated with ALYFTREK.
Perform baseline and follow-up ophthalmological examination in pediatric patients prior to and during treatment with ALYFTREK [see Warnings and Precautions (5.8) ]. The safety and effectiveness of ALYFTREK in patients younger than 6 years of age have not been established. Juvenile Animal Toxicity Data Findings of cataracts were observed in juvenile rats dosed from postnatal Day 7 through 35 with ivacaftor dose levels of 10 mg/kg/day and higher (0.21 times the MRHD based on systemic exposure of ivacaftor and its metabolites).
This finding has not been observed in older animals [see Warnings and Precautions (5.8) ]. Studies were conducted with tezacaftor in juvenile rats starting at postnatal day (PND) 21 and ranging up to PNDs 35 to 49. Findings of convulsions and death were observed in juvenile rats that received a tezacaftor dose level of 100 mg/kg/day (approximately equivalent to 1.9 times the MRHD based on summed AUCs of tezacaftor and its metabolite, M1-TEZ).
A no effect dose level was identified at 30 mg/kg/day (approximately equivalent to 0.8 times the MRHD based on summed AUCs of tezacaftor and its metabolite, M1-TEZ). Findings were dose related and generally more severe when dosing with tezacaftor was initiated earlier in the pos…
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of ALYFTREK did not include a sufficient number of patients with CF aged 65 years and older (n=2, 0.4% of patients treated with ALYFTREK in Trials 1 and 2) to determine whether they respond differently from younger adult patients with CF.
🆘 Overdosage ▾
10 OVERDOSAGE Treatment of overdosage consists of general supportive measures including monitoring of vital signs and observation of the clinical status.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Vanzacaftor and tezacaftor bind to different sites on the CFTR protein and have an additive effect in facilitating the cellular processing and trafficking of select mutant forms of CFTR (including F508del- CFTR) to increase the amount of CFTR protein delivered to the cell surface compared to either molecule alone. Deutivacaftor potentiates the channel open probability (or gating) of the CFTR protein at the cell surface. The combined effect of vanzacaftor, tezacaftor and deutivacaftor is increased quantity and function of CFTR at the cell surface, resulting in increased CFTR activity as measured both by CFTR-mediated chloride transport in vitro and by sweat chloride in patients with CF.
CFTR Chloride Transport Assay in Fischer Rat Thyroid Cells Expressing Mutant CFTR Protein Effects of vanzacaftor/tezacaftor/deutivacaftor on chloride transport for mutant CFTR protein was determined in Ussing chamber electrophysiology studies using a panel of Fischer Rat Thyroid (FRT) cell lines stably expressing CFTR protein from individual variants. Vanzacaftor/tezacaftor/deutivacaftor increased chloride transport in FRT cells expressing select CFTR variants, as identified in Table 5. The threshold that the treatment-induced increase in chloride transport must exceed for the mutant CFTR protein to be considered responsive is ≥10% of normal over baseline.
This threshold was used because it is expected to predict clinical benefit. For individual variants, the magnitude of the net change over baseline in CFTR-mediated chloride transport in vitro is not correlated with the magnitude of clinical response. CFTR Chloride Transport Assay in Human Bronchial Epithelial Cells Expressing Mutant CFTR Protein Homozygous and heterozygous N1303K- Human Bronchial Epithelial (HBE) cells showed greater chloride transport in the presence of vanzacaftor/tezacaftor/deutivacaftor than F508del/F508del- HBE cells treated with tezacaftor/ivacaftor which has shown clinical benefit in people homozygous for F508del .
Patient Selection Select adult and pediatric patients 6 years of age and older for the treatment of CF with ALYFTREK based on a clinical diagnosis of CF and the presence of at least one variant in the CFTR gene that is either responsive based on clinical and/or in vitro data or results in production of CFTR protein [see Indications and Usage (1) ]. ALYFTREK should only be used in patients with a clinical diagnosis of CF. The presence of eligible CFTR variant(s) should not be the sole determinant for using ALYFTREK.
Table 5 lists CFTR variants responsive to ALYFTREK based on clinical and/or in vitro data in FRT or HBE cells [see Clinical Studies (14) ]. Table 5: List of CFTR Gene Variants Responsive to ALYFTREK The list of responsive CFTR variants is non-exhaustive. There may be protein-producing CFTR variants not listed that respond to treatment with ALYFTREK.
Based on Clinical Data Clinical data is obtained from Trials 1 and 2. A455E G551D This variant is also predicted to be responsive by FRT assay with ALYFTREK. L1077P R352Q S1251N S945L W1098C D1152H G85E L206W R75Q S549N V562I W1282R F508del H1054D M1101K S1159F S549R V754M Y563N G1244E I336K R1066H Based on in vitro Data The N1303K variant is predicted to be responsive only by HBE assay.
All other variants predicted to be responsive with in vitro data are supported by FRT assay. 1140-1151dup D443Y G1265V I1398S M150R R1283M S977F 1461insGAT D443Y;G576A;R668C Complex/compound variants where a single allele of the CFTR gene has multiple variants; these exist independent of the presence of variants on the other allele. G126D I148L M152L R1283S S977F;R1438W 1507_1515del9 D513G G1298V I148N M152V R1438W T1036N 2055del9 D529G G1349D I148T M265R R170H T1053I 2183A→G D565G G149R I148T;H609R M348K R248K T1057R 2851A/G D567N G149R;G576A;R668C I175V M394L R258G T1086A 293A→G D572N G178E I331N M469V R297Q T1086I 3007del6 D579G G178R I336L M498I R31C T1246I 3131del15…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Vanzacaftor and tezacaftor bind to different sites on the CFTR protein and have an additive effect in facilitating the cellular processing and trafficking of select mutant forms of CFTR (including F508del- CFTR) to increase the amount of CFTR protein delivered to the cell surface compared to either molecule alone. Deutivacaftor potentiates the channel open probability (or gating) of the CFTR protein at the cell surface. The combined effect of vanzacaftor, tezacaftor and deutivacaftor is increased quantity and function of CFTR at the cell surface, resulting in increased CFTR activity as measured both by CFTR-mediated chloride transport in vitro and by sweat chloride in patients with CF.
CFTR Chloride Transport Assay in Fischer Rat Thyroid Cells Expressing Mutant CFTR Protein Effects of vanzacaftor/tezacaftor/deutivacaftor on chloride transport for mutant CFTR protein was determined in Ussing chamber electrophysiology studies using a panel of Fischer Rat Thyroid (FRT) cell lines stably expressing CFTR protein from individual variants. Vanzacaftor/tezacaftor/deutivacaftor increased chloride transport in FRT cells expressing select CFTR variants, as identified in Table 5. The threshold that the treatment-induced increase in chloride transport must exceed for the mutant CFTR protein to be considered responsive is ≥10% of normal over baseline.
This threshold was used because it is expected to predict clinical benefit. For individual variants, the magnitude of the net change over baseline in CFTR-mediated chloride transport in vitro is not correlated with the magnitude of clinical response. CFTR Chloride Transport Assay in Human Bronchial Epithelial Cells Expressing Mutant CFTR Protein Homozygous and heterozygous N1303K- Human Bronchial Epithelial (HBE) cells showed greater chloride transport in the presence of vanzacaftor/tezacaftor/deutivacaftor than F508del/F508del- HBE cells treated with tezacaftor/ivacaftor which has shown clinical benefit in people homozygous for F508del .
Patient Selection Select adult and pediatric patients 6 years of age and older for the treatment of CF with ALYFTREK based on a clinical diagnosis of CF and the presence of at least one variant in the CFTR gene that is either responsive based on clinical and/or in vitro data or results in production of CFTR protein [see Indications and Usage (1) ]. ALYFTREK should only be used in patients with a clinical diagnosis of CF. The presence of eligible CFTR variant(s) should not be the sole determinant for using ALYFTREK.
Table 5 lists CFTR variants responsive to ALYFTREK based on clinical and/or in vitro data in FRT or HBE cells [see Clinical Studies (14) ]. Table 5: List of CFTR Gene Variants Responsive to ALYFTREK The list of responsive CFTR variants is non-exhaustive. There may be protein-producing CFTR variants not listed that respond to treatment with ALYFTREK.
Based on Clinical Data Clinical data is obtained from Trials 1 and 2. A455E G551D This variant is also predicted to be responsive by FRT assay with ALYFTREK. L1077P R352Q S1251N S945L W1098C D1152H G85E L206W R75Q S549N V562I W1282R F508del H1054D M1101K S1159F S549R V754M Y563N G1244E I336K R1066H Based on in vitro Data The N1303K variant is predicted to be responsive only by HBE assay.
All other variants predicted to be responsive with in vitro data are supported by FRT assay. 1140-1151dup D443Y G1265V I1398S M150R R1283M S977F 1461insGAT D443Y;G576A;R668C Complex/compound variants where a single allele of the CFTR gene has multiple variants; these exist independent of the presence of variants on the other allele. G126D I148L M152L R1283S S977F;R1438W 1507_1515del9 D513G G1298V I148N M152V R1438W T1036N 2055del9 D529G G1349D I148T M265R R170H T1053I 2183A→G D565G G149R I148T;H609R M348K R248K T1057R 2851A/G D567N G149R;G576A;R668C I175V M394L R258G T1086A 293A→G D572N G178E I331N M469V R297Q T1086I 3007del6 D579G G178R I336L M498I R31C T1246I 3131del15 D58H G194R I444S M952I R…
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING ALYFTREK (vanzacaftor, tezacaftor, and deutivacaftor) tablets are supplied as follows: Table 10: ALYFTREK Tablets and Package Configuration Strengths Tablet Description Package Configuration NDC 4 mg of vanzacaftor/ 20 mg of tezacaftor / 50 mg of deutivacaftor purple, round-shaped, film-coated, debossed with "V4" on one side and plain on the other 84-count carton containing 4 wallets, each wallet containing 21 tablets in blister packs NDC 51167-135-01 10 mg of vanzacaftor/ 50 mg of tezacaftor / 125 mg of deutivacaftor purple, oblong-shaped, film-coated, debossed with "V10" on one side and plain on the other 56-count carton containing 4 wallets, each wallet containing 14 tablets in blister packs NDC 51167-121-01 Store at 20°C - 25°C (68°F - 77°F); excursions permitted to 15°C - 30°C (59°F - 86°F) [see USP Controlled Room Temperature].
📦 Storage and Handling ▾
Store at 20°C - 25°C (68°F - 77°F); excursions permitted to 15°C - 30°C (59°F - 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION ALYFTREK (vanzacaftor, tezacaftor, and deutivacaftor tablets) are fixed-dose combination tablets for oral use available as: 10 mg of vanzacaftor (equivalent to 10.6 mg of vanzacaftor calcium dihydrate), 50 mg of tezacaftor, 125 mg of deutivacaftor or 4 mg of vanzacaftor (equivalent to 4.24 mg of vanzacaftor calcium dihydrate), 20 mg of tezacaftor, 50 mg of deutivacaftor. The tablets contain the following inactive ingredients: croscarmellose sodium, hypromellose, hypromellose acetate succinate, magnesium stearate, microcrystalline cellulose, and sodium lauryl sulfate.
The tablet film coating contains Brilliant Blue FCF aluminum lake/FD&C Blue #1, carmine, hydroxypropyl cellulose, hypromellose, iron oxide red, talc, and titanium dioxide. The active ingredients of ALYFTREK are described below: Vanzacaftor Vanzacaftor is provided as a calcium salt. Vanzacaftor calcium dihydrate is a white solid that is practically insoluble in water (< 0.1 mg/mL).
Its chemical name is calcium bis((14 S )-8-[3-(2-{dispiro[2.0.2 4 .1 3 ]heptan-7-yl}ethoxy)pyrazol-1-yl]-12,12-dimethyl-2,2,4-trioxo-2λ 6 -thia-3,9,11,18,23-pentaazatetracyclo[17.3.1.1 11,14 .0 5,10 ]tetracosa-1(23),5,7,9,19,21-hexaen-3-ide) dihydrate. Its molecular formula is C 32 H 38 N 7 O 4 S∙Ca 0.5 ∙H 2 O and its molecular weight is 654.82. Vanzacaftor calcium dihydrate has the following structural formula: Chemical Structure Tezacaftor Tezacaftor is a white to off-white solid that is practically insoluble in water (< 5 microgram/mL).
Its chemical name is 1-(2,2-difluoro-2H-1,3-benzodioxol-5-yl)-N-{1-[(2R)-2,3-dihydroxypropyl]-6-fluoro-2-(1-hydroxy-2-methylpropan-2-yl)-1H-indol-5-yl}cyclopropane-1-carboxamide. Its molecular formula is C 26 H 27 N 2 F 3 O 6 and its molecular weight is 520.50. Tezacaftor has the following structural formula: Chemical Structure Deutivacaftor Deutivacaftor is a white to off-white solid that is practically insoluble in water (< 0.1 mg/mL).
Pharmacologically, it is a CFTR potentiator. Its chemical name is N -(2-( tert -butyl)-5-hydroxy-4-(2-(methyl- d 3 )propan-2-yl-1,1,1,3,3,3- d 6 )phenyl)-4-oxo-1,4-dihydroquinoline-3-carboxamide. Its molecular formula is C 24 H 19 D 9 N 2 O 3 and its molecular weight is 401.55.
Deutivacaftor has the following structural formula: Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Drug-Induced Liver Injury and Liver Failure Inform patients that elevations of transaminases have occurred in patients with CF treated with ALYFTREK and that cases of drug-induced liver injury and failure have been observed with fixed-dose combination drug containing elexacaftor, tezacaftor, and ivacaftor, which contains the same or similar active ingredients as ALYFTREK. Advise all patients that liver function tests should be assessed prior to initiating ALYFTREK, and then assessed every month during the first 6 months of treatment, then every 3 months for the next 12 months, then at least annually thereafter.
Inform patients with a history of liver disease or liver function test elevations at baseline that more frequent monitoring may be necessary. Instruct patients to interrupt treatment with ALYFTREK if symptoms of liver injury occur (e.g., jaundice, right upper quadrant pain, nausea, vomiting, altered mental status, ascites) and notify their healthcare provider immediately [see Dosage and Administration (2.1) , Warnings and Precautions (5.1) , Adverse Reactions (6.1) , Use in Specific Populations (8.7) and Clinical Pharmacology (12.3) ] .
Hypersensitivity Reactions, Including Anaphylaxis Inform patients that hypersensitivity reactions including anaphylaxis have been reported in patients who received drugs containing elexacaftor, tezacaftor, and/or ivacaftor (the same or similar active ingredients as ALYFTREK). Instruct patients to discontinue ALYFTREK and notify their healthcare provider if they experience signs and symptoms of a hypersensitivity reaction, including rash, hives, itching, facial swelling, tightness of the chest and wheezing [see Warnings and Precautions (5.2) ] .
Patients Who Discontinued or Interrupted Elexacaftor-, Tezacaftor-, or Ivacaftor-Containing Drugs Due to Adverse Reactions Inform patients that there is no available safety data for ALYFTREK in patients who previously discontinued or interrupted treatment with elexacaftor-, tezacaftor-, or ivacaftor-containing drugs due to adverse reactions. These patients who start treatment with ALYFTREK may require closer and more frequent monitoring [see Warnings and Precautions (5.3) ] . Intracranial Hypertension Inform patients that intracranial hypertension has occurred in patients who received drugs containing the same or similar active ingredients as ALYFTREK.
Instruct patients to notify their healthcare provider right away if they experience signs and symptoms of intracranial hypertension, including headache, blurred vision, diplopia, and vision loss [see Warnings and Precautions (5.4) ] . Neuropsychiatric Events, Including Suicidal Thoughts and Behaviors Inform patients that neuropsychiatric symptoms, including anxiety, depression, suicidal thoughts and behaviors, and sleep disturbances (e.g., insomnia), have been reported with the use of ALYFTREK or drugs containing the same or similar active ingredients as ALYFTREK.
The symptoms have been observed in patients with and without a history of similar symptoms and may occur within three months of ALYFTREK initiation. Instruct patients to contact their healthcare provider immediately if changes in behavior or thinking that are not typical for the patient occur, or if the patient develops suicidal ideation or behavior [see Warnings and Precautions (5.5) ] . Drug Interactions with CYP3A Inducers and Inhibitors Inform patients that certain medications, herbal supplements, or vitamins, when used concomitantly with ALYFTREK, may reduce the effectiveness of ALYFTREK or increase the risk of adverse reactions associated with ALYFTREK.
Instruct patients to report all concomitant medications, herbal supplements, or vitamins, to their healthcare providers while taking ALYFTREK [see Dosage and Administration (2.3) , Warnings and Precautions (5.6 , 5.7) and Drug Interactions (7.1) ] . Instruct patients to a…
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: 03/2026 MEDICATION GUIDE ALYFTREK™ (ah-LIF-trek) (vanzacaftor, tezacaftor, and deutivacaftor tablets), tablets for oral use What is the most important information I should know about ALYFTREK?
Elevated liver enzymes have been observed in patients taking ALYFTREK . Cases of serious liver damage and liver failure leading to transplantation and death have been seen in some people with or without a history of liver problems taking elexacaftor/tezacaftor/ivacaftor (TRIKAFTA), a medicine which has the same or similar active ingredients as ALYFTREK. Your healthcare provider will do blood tests to check your liver: before you start ALYFTREK every month during your first 6 months of taking ALYFTREK then every 3 months during the next 12 months of taking ALYFTREK then at least every year while you are taking ALYFTREK Your healthcare provider may do blood tests to check the liver more often if you have had high liver enzymes in your blood in the past or are experiencing signs or symptoms of liver injury.
Stop taking ALYFTREK and call your healthcare provider right away if you have any of the following symptoms of liver problems: pain, swelling, or discomfort in the upper right stomach (abdominal) area yellowing of your skin or the white part of your eyes mental changes nausea or vomiting dark, amber-colored urine loss of appetite have fluid in your stomach area (ascites) What is ALYFTREK? ALYFTREK is a prescription medicine for people aged 6 years and older who have a diagnosis of cystic fibrosis (CF) and who have at least one genetic change (variant) in the cystic fibrosis transmembrane conductance regulator ( CFTR ) gene that is either responsive to ALYFTREK or results in the production of protein.
Talk to your healthcare provider to learn if you have an indicated CF gene variant. It is not known if ALYFTREK is safe and effective in children under 6 years of age. What should I tell my healthcare provider before taking ALYFTREK?
Before taking ALYFTREK, tell your healthcare provider about all of your medical conditions, including if you: have or have had liver problems. are allergic to ALYFTREK or any ingredients in ALYFTREK. See the end of this medication guide for a complete list of ingredients in ALYFTREK. have taken another medicine with elexacaftor, tezacaftor, or ivacaftor before and temporarily or permanently stopped because of side effects. Your healthcare provider may want to see you more often. have kidney problems. have or have had mental health problems. are pregnant or plan to become pregnant.
It is not known if ALYFTREK will harm your unborn baby. You and your healthcare provider should decide if you will take ALYFTREK while you are pregnant. are breastfeeding or planning to breastfeed. It is not known if ALYFTREK passes into your breast milk.
You and your healthcare provider should decide if you will take ALYFTREK while you are breastfeeding. Tell your healthcare provider about all the medicines you take , including prescription and over-the-counter medicines, vitamins, and herbal supplements. ALYFTREK may affect the way other medicines work and other medicines may affect how ALYFTREK works.
The dose of ALYFTREK may need to be adjusted when taken with certain medicines. Ask your healthcare provider or pharmacist for a list of these medicines if you are not sure. Know the medicines you take.
Keep a list of them to show your healthcare provider and pharmacist when you get a new medicine. How should I take ALYFTREK? Take ALYFTREK exactly as your healthcare provider tells you to take it.
Take ALYFTREK by mouth only. Always take ALYFTREK tablets with food that contains fat . Examples of fat-containing foods include butter, oil, eggs, peanut butter, nuts, meat, and whole-milk dairy products such as whole milk, cheese, and yogurt.
ALYFTREK tablets (age 6 to less than 12 years weighing less than 88 pounds (40 kg)): The purple round-shaped ta…