
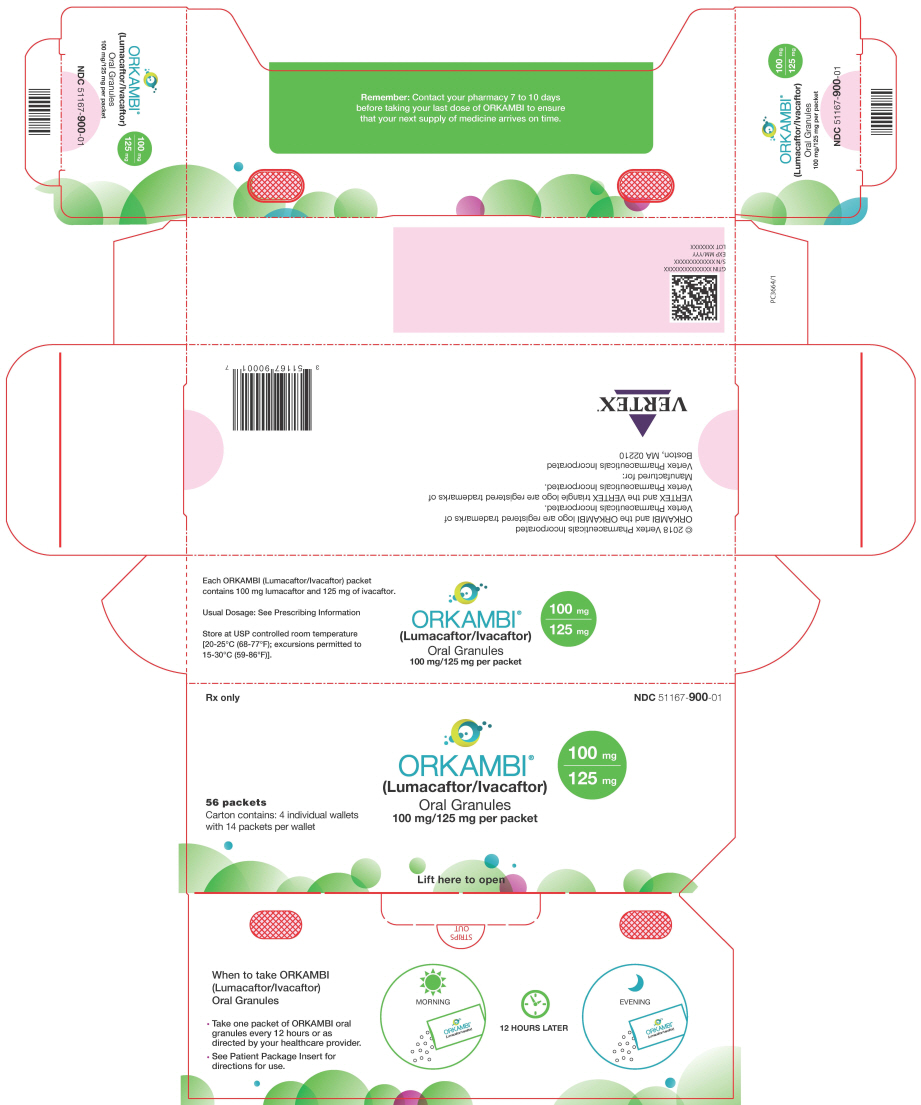
Orkambi lumacaftor and ivacaftor 100 mg; 125 mg Granule, 56-count — NDC 51167-900-01 (Billing 51167-0900-01)
This is a package of 56 granules of Orkambi lumacaftor and ivacaftor 100 mg; 125 mg Granule from Vertex Pharmaceuticals Incorporated, marketed since Aug 2018 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 51167-900-01 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 51167 labeler · 900 product · 01 package
- Package marketed since
- Aug 7, 2018
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Billing quantity
- 56 EA per package
- Barcode (UPC-A, from the NDC)
- 3 5116790001 7
- Medicaid fills, this package
- 241 prescriptions in the last four reported quarters
- FDA record last changed
- Oct 8, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 078704
- GCN: 36937
- GPI-14 (Medi-Span): 45309902303010
- HICL (First Databank): 042235
- AHFS class code: 48:14.04.00
- RxCUI (RxNorm): 1655928
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Cystic Fibrosis Transmembrane Conductance Regulator Potentiator class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Orkambi treats cystic fibrosis in people aged 1 and older who have two copies of the F508del mutation. It will not be used if you have a different CF mutation. Your doctor can conf...
- Take it by mouth about every 12 hours, with food that contains fat. Food helps your body absorb it better. Follow the amount your prescriber gave you for your age and weight.
- Common ones include shortness of breath, cold-like symptoms, nausea, diarrhea, tiredness and rash. Breathing symptoms such as chest tightness are most common in the first week. Cal...
- Orkambi can raise liver enzymes and, rarely, cause serious liver problems. Liver tests are done before you start, every 3 months in the first year, then yearly. Tell your doctor ri...
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $405.45 | — |
| Medicare drug plans payPart D · Q2 2026 | $422.12 | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 51167-0900-01 You're viewing this Main listing | 56 PACKET in 1 CARTON / 1 GRANULE in 1 PACKET | 2018-08-07 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Orkambi 100 mg/1; 125 mgthis 51167-0900-01 | Vertex | 56 granules | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8324242 ↗ | Method of use | U-2374 | Aug 5, 2027 |
| US 7973038 ↗ | Method of use | U-2374 | Nov 8, 2026 |
| US 9931334 ↗ | Method of use | U-2376 | Dec 28, 2026 |
| US 8741933 ↗ | Method of use | U-2374 | Nov 8, 2026 |
| US 8716338 ↗ | Method of use | U-2396 | Sep 20, 2030 |
| US 8846718 ↗ | Method of use | U-2375 | Jul 2, 2029 |
| US 9150552 ↗ | Method of use | U-2375 | Dec 4, 2028 |
| US 9670163 ↗ | Method of use | U-2376 | Dec 28, 2026 |
| US 8716338 ↗ | Method of use | U-2396 | Sep 20, 2030 |
| US 9931334 ↗ | Method of use | U-2376 | Dec 28, 2026 |
| US 8741933 ↗ | Method of use | U-2374 | Nov 8, 2026 |
| US 9192606 ↗ | Method of use | U-2397 | Sep 29, 2029 |
| US 9192606 ↗ | Method of use | U-2397 | Sep 29, 2029 |
| US 12458635 ↗ | Method of use | U-4335 | Aug 13, 2029 |
| US 12458635 ↗ | Method of use | U-4335 | Aug 13, 2029 |
| US 12458635 ↗ | Method of use | U-4335 | Aug 13, 2029 |
| US 8324242 ↗ | Method of use | U-3424 | Aug 5, 2027 |
| US 7973038 ↗ | Method of use | U-3424 | Nov 8, 2026 |
| US 8716338 ↗ | Method of use | U-3426 | Sep 20, 2030 |
| US 8741933 ↗ | Method of use | U-3424 | Nov 8, 2026 |
| US 8846718 ↗ | Method of use | U-3427 | Jul 2, 2029 |
| US 9150552 ↗ | Method of use | U-3427 | Dec 4, 2028 |
| US 11564916 ↗ | Method of use | U-3526 | Aug 13, 2029 |
| US 11564916 ↗ | Method of use | U-3526 | Aug 13, 2029 |
| US 11564916 ↗ | Method of use | U-3526 | Aug 13, 2029 |
| US 10597384 ↗ | Drug substance | U-2778 | Dec 4, 2028 |
| US 10597384 ↗ | Drug substance | U-2778 | Dec 4, 2028 |
| US 7973038 ↗ | Method of use | U-2374 | Nov 8, 2026 |
| US 9150552 ↗ | Method of use | U-2375 | Dec 4, 2028 |
| US 8324242 ↗ | Method of use | U-2374 | Aug 5, 2027 |
| US 8846718 ↗ | Method of use | U-2375 | Jul 2, 2029 |
| US 12065432 ↗ | Method of use | U-3983 | Dec 4, 2028 |
| US 12065432 ↗ | Method of use | U-3983 | Dec 4, 2028 |
| US 12065432 ↗ | Method of use | U-3983 | Dec 4, 2028 |
| US 9670163 ↗ | Method of use | U-2376 | Dec 28, 2026 |
| US 9192606 ↗ | Method of use | U-3428 | Sep 29, 2029 |
| US 9670163 ↗ | Method of use | U-3429 | Dec 28, 2026 |
| US 9931334 ↗ | Method of use | U-3429 | Dec 28, 2026 |
| US 10597384 ↗ | Drug substance | U-3430 | Dec 4, 2028 |
| US 9216969 ↗ | Drug product | — | Nov 8, 2026 |
| US 8653103 ↗ | Drug product | — | Dec 4, 2028 |
| US 7495103 ↗ | Drug substance | — | May 20, 2027 |
| US 8653103 ↗ | Drug product | — | Dec 4, 2028 |
| US 8754224 ↗ | Drug substance | — | Dec 28, 2026 |
| US 7495103 ↗ | Drug substance | — | May 20, 2027 |
| US 10646481 ↗ | Drug product | — | Aug 13, 2029 |
| US 8410274 ↗ | Drug product | — | Dec 28, 2026 |
| US 7495103 ↗ | Drug substance | — | May 20, 2027 |
| US 8507534 ↗ | Drug substance | — | Sep 20, 2030 |
| US 8507534 ↗ | Drug substance | — | Sep 20, 2030 |
| US 8754224 ↗ | Drug substance | — | Dec 28, 2026 |
| US 8993600 ↗ | Drug product | — | Dec 11, 2030 |
| US 9216969 ↗ | Drug product | — | Nov 8, 2026 |
| US 9216969 ↗ | Drug product | — | Nov 8, 2026 |
| US 8507534 ↗ | Drug substance | — | Sep 20, 2030 |
| US 10646481 ↗ | Drug product | — | Aug 13, 2029 |
| US 8410274 ↗ | Drug product | — | Dec 28, 2026 |
| US 8653103 ↗ | Drug product | — | Dec 4, 2028 |
| US 8410274 ↗ | Drug product | — | Dec 28, 2026 |
| US 8754224 ↗ | Drug substance | — | Dec 28, 2026 |
| US 10646481 ↗ | Drug product | — | Aug 13, 2029 |
| US 8993600 ↗ | Drug product | — | Dec 11, 2030 |
| US 8993600 ↗ | Drug product | — | Dec 11, 2030 |
| US 8716338*PED ↗ | Drug product | — | Mar 20, 2031 |
| US 8716338*PED ↗ | Drug product | — | Mar 20, 2031 |
| US 7973038*PED ↗ | Drug product | — | May 8, 2027 |
| US 8410274*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8324242*PED ↗ | Drug product | — | Feb 5, 2028 |
| US 7495103*PED ↗ | Drug product | — | Nov 20, 2027 |
| US 7495103*PED ↗ | Drug product | — | Nov 20, 2027 |
| US 8324242*PED ↗ | Drug product | — | Feb 5, 2028 |
| US 7973038*PED ↗ | Drug product | — | May 8, 2027 |
| US 8410274*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8507534*PED ↗ | Drug product | — | Mar 20, 2031 |
| US 8653103*PED ↗ | Drug product | — | Jun 4, 2029 |
| US 8741933*PED ↗ | Drug product | — | May 8, 2027 |
| US 8653103*PED ↗ | Drug product | — | Jun 4, 2029 |
| US 8507534*PED ↗ | Drug product | — | Mar 20, 2031 |
| US 8741933*PED ↗ | Drug product | — | May 8, 2027 |
| US 9150552*PED ↗ | Drug product | — | Jun 4, 2029 |
| US 8754224*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8993600*PED ↗ | Drug product | — | Jun 11, 2031 |
| US 8846718*PED ↗ | Drug product | — | Jan 2, 2030 |
| US 8993600*PED ↗ | Drug product | — | Jun 11, 2031 |
| US 8754224*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8846718*PED ↗ | Drug product | — | Jan 2, 2030 |
| US 9150552*PED ↗ | Drug product | — | Jun 4, 2029 |
| US 9931334*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 9670163*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 9216969*PED ↗ | Drug product | — | May 8, 2027 |
| US 9670163*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 9216969*PED ↗ | Drug product | — | May 8, 2027 |
| US 9931334*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 9192606*PED ↗ | Drug product | — | Mar 29, 2030 |
| US 9192606*PED ↗ | Drug product | — | Mar 29, 2030 |
| US 10597384*PED ↗ | Drug product | — | Jun 4, 2029 |
| US 9192606*PED ↗ | Drug product | — | Mar 29, 2030 |
| US 9216969*PED ↗ | Drug product | — | May 8, 2027 |
| US 9670163*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 9931334*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 10646481*PED ↗ | Drug product | — | Feb 13, 2030 |
| US 12065432*PED ↗ | Drug product | — | Jun 4, 2029 |
| US 12065432*PED ↗ | Drug product | — | Jun 4, 2029 |
| US 12065432*PED ↗ | Drug product | — | Jun 4, 2029 |
| US 10597384*PED ↗ | Drug product | — | Jun 4, 2029 |
| US 10597384*PED ↗ | Drug product | — | Jun 4, 2029 |
| US 10646481*PED ↗ | Drug product | — | Feb 13, 2030 |
| US 10646481*PED ↗ | Drug product | — | Feb 13, 2030 |
| US 12458635*PED ↗ | Drug product | — | Feb 13, 2030 |
| US 12458635*PED ↗ | Drug product | — | Feb 13, 2030 |
| US 12458635*PED ↗ | Drug product | — | Feb 13, 2030 |
| US 7495103*PED ↗ | Drug product | — | Nov 20, 2027 |
| US 8324242*PED ↗ | Drug product | — | Feb 5, 2028 |
| US 7973038*PED ↗ | Drug product | — | May 8, 2027 |
| US 8410274*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8507534*PED ↗ | Drug product | — | Mar 20, 2031 |
| US 8653103*PED ↗ | Drug product | — | Jun 4, 2029 |
| US 8716338*PED ↗ | Drug product | — | Mar 20, 2031 |
| US 8741933*PED ↗ | Drug product | — | May 8, 2027 |
| US 8754224*PED ↗ | Drug product | — | Jun 28, 2027 |
| US 8846718*PED ↗ | Drug product | — | Jan 2, 2030 |
| US 8993600*PED ↗ | Drug product | — | Jun 11, 2031 |
| US 9150552*PED ↗ | Drug product | — | Jun 4, 2029 |
| US 11564916*PED ↗ | Drug product | — | Feb 13, 2030 |
| US 11564916*PED ↗ | Drug product | — | Feb 13, 2030 |
| US 11564916*PED ↗ | Drug product | — | Feb 13, 2030 |
| Code | What it grants | Expires |
|---|---|---|
| M-14 | New indication / labeling change (3-year) | Dec 13, 2027 |
| ODE-408 | Orphan Drug Exclusivity (7-year) | Sep 2, 2029 |
| M-14 | New indication / labeling change (3-year) | Dec 13, 2027 |
| ODE-408 | Orphan Drug Exclusivity (7-year) | Sep 2, 2029 |
| M-14 | New indication / labeling change (3-year) | Dec 13, 2027 |
| ODE-408 | Orphan Drug Exclusivity (7-year) | Sep 2, 2029 |
| PED | Pediatric Exclusivity (+6 months) | Mar 2, 2030 |
| PED | Pediatric Exclusivity (+6 months) | Mar 2, 2030 |
| PED | Pediatric Exclusivity (+6 months) | Mar 2, 2030 |
| PED | Pediatric Exclusivity (+6 months) | Jun 13, 2028 |
| PED | Pediatric Exclusivity (+6 months) | Jun 13, 2028 |
| PED | Pediatric Exclusivity (+6 months) | Jun 13, 2028 |
Is there a generic version of ORKAMBI 100-125 MG GRANULE PKT?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Lumacaftor and Ivacaftor inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 6N003M473W
Hypromellose acetate succinate is a modified cellulose polymer that dissolves in the small intestine. It's used as a coating material to protect the medicine from stomach acid and control where and when the drug is released in the digestive tract.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Vertex Pharmaceuticals Incorporated labeler code 51167
- Kalydeco ivacaftor 25 mg Granule NDC 51167-600-01
- SYMDEKO Tezacaftor and Ivacaftor Kit NDC 51167-661-01
- Orkambi lumacaftor and ivacaftor 100 mg; 125 mg Tablet, Film Coated NDC 51167-700-02
- Kalydeco ivacaftor 13.4 mg Granule NDC 51167-770-01
- Kalydeco ivacaftor 5.8 mg Granule NDC 51167-785-01
- Orkambi lumacaftor and ivacaftor 200 mg; 125 mg Tablet, Film Coated NDC 51167-809-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ORKAMBI is indicated for the treatment of cystic fibrosis (CF) in patients aged 1 year and older who are homozygous for the F508del mutation in the CFTR gene. If the patient's genotype is unknown, an FDA-cleared CF mutation test should be used to detect the presence of the F508del mutation on both alleles of the CFTR gene. ORKAMBI is a combination of ivacaftor, a cystic fibrosis transmembrane conductance regulator (CFTR) potentiator, and lumacaftor, indicated for the treatment of cystic fibrosis (CF) in patients aged 1 year and older who are homozygous for the F508del mutation in the CFTR gene.
If the patient's genotype is unknown, an FDA-cleared CF mutation test should be used to detect the presence of the F508del mutation on both alleles of the CFTR gene. ( 1 ) Limitations of Use: The efficacy and safety of ORKAMBI have not been established in patients with CF other than those homozygous for the F508del mutation. ( 1 ) Limitations of Use The efficacy and safety of ORKAMBI have not been established in patients with CF other than those homozygous for the F508del mutation .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Age Group Weight Dose Administration 1 through 2 years 7 kg to <9 kg 1 packet of lumacaftor 75 mg/ivacaftor 94 mg granules Mixed with one teaspoon (5 mL) of soft food or liquid and administered orally every 12 hours with fat-containing food 9 kg to <14 kg 1 packet of lumacaftor 100 mg/ivacaftor 125 mg granules ≥14 kg 1 packet of lumacaftor 150 mg/ivacaftor 188 mg granules 2 through 5 years <14 kg 1 packet of lumacaftor 100 mg/ivacaftor 125 mg granules ≥14 kg 1 packet of lumacaftor 150 mg/ivacaftor 188 mg granules 6 through 11 years - 2 tablets of lumacaftor 100 mg/ivacaftor 125 mg (lumacaftor 200 mg/ivacaftor 250 mg per dose) Taken orally every 12 hours with fat-containing food 12 years and older - 2 tablets of lumacaftor 200 mg/ivacaftor 125 mg (lumacaftor 400 mg/ivacaftor 250 mg per dose) Reduce dosage in patients with moderate or severe hepatic impairment.
( 2.2 , 8.6 , 12.3 ) When initiating ORKAMBI in patients taking strong CYP3A inhibitors, reduce ORKAMBI dosage for the first week of treatment. ( 2.3 , 7.1 , 12.3 )
2.1Recommended Dosage in Adults and Pediatric Patients Aged 1 Year and Older The recommended dosage of ORKAMBI in adults and pediatric patients aged one year and older is based on patient's age and weight as described in Table 1. Table 1: Recommended Oral Dosage of ORKAMBI in Patients Aged 1 Year and Older Age Group Weight ORKAMBI Daily Dose (every 12 hours) Morning Dose Evening Dose 1 through 2 years 7 kg to <9 kg 1 packet of lumacaftor 75 mg/ivacaftor 94 mg oral granules 1 packet of lumacaftor 75 mg/ivacaftor 94 mg oral granules 9 kg to <14 kg 1 packet of lumacaftor 100 mg/ivacaftor 125 mg oral granules 1 packet of lumacaftor 100 mg/ivacaftor 125 mg oral granules ≥14 kg 1 packet of lumacaftor 150 mg/ivacaftor 188 mg oral granules 1 packet of lumacaftor 150 mg/ivacaftor 188 mg oral granules 2 through 5 years <14 kg 1 packet of lumacaftor 100 mg/ivacaftor 125 mg oral granules 1 packet of lumacaftor 100 mg/ivacaftor 125 mg oral granules ≥14 kg 1 packet of lumacaftor 150 mg/ivacaftor 188 mg oral granules 1 packet of lumacaftor 150 mg/ivacaftor 188 mg oral granules 6 through 11 years - 2 tablets of lumacaftor 100 mg/ivacaftor 125 mg (lumacaftor 200 mg/ivacaftor 250 mg per dose) 2 tablets of lumacaftor 100 mg/ivacaftor 125 mg (lumacaftor 200 mg/ivacaftor 250 mg per dose) 12 years and older - 2 tablets of lumacaftor 200 mg/ivacaftor 125 mg (lumacaftor 400 mg/ivacaftor 250 mg per dose) 2 tablets of lumacaftor 200 mg/ivacaftor 125 mg (lumacaftor 400 mg/ivacaftor 250 mg per dose) Administration Instructions for ORKAMBI Oral Granules The entire content of each packet of oral granules should be mixed with one teaspoon (5 mL) of age-appropriate soft food or liquid and the mixture completely consumed.
Some examples of soft foods or liquids include puréed fruits or vegetables, flavored yogurt or pudding, applesauce, water, milk, breast milk, infant formula or juice. Food should be at room temperature or below. Each packet is for single use only.
Once mixed, the product has been shown to be stable for one hour, and therefore should be ingested during this period. Administration with Fat-Containing Food for ORKAMBI Tablets and Oral Granules A fat-containing meal or snack should be consumed just before or just after dosing for all formulations. Examples of appropriate fat-containing foods include eggs, avocados, nuts, butter, peanut butter, cheese pizza, breast milk, infant formula, whole-milk dairy products (such as whole milk, cheese, and yogurt), etc.
Missed Dose If a patient misses a dose and remembers the missed dose within 6 hours, the patient should take the dose with fat-containing food. If more than 6 hours elapsed after the recommended dosing time, the patient should skip that dose and resume the normal schedule for the following dose. A double dose should not be taken to make up for the forgotten dose [see Clinical Pharmacology (12.3) and Patient Counseling Information (17) ] .
2.2Dosa… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 100 mg lumacaftor and 125 mg ivacaftor; supplied as pink, oval-shaped, film-coated, fixed-dose combination tablets containing 100 mg of lumacaftor and 125 mg of ivacaftor. Each tablet is printed with the characters "1V125" in black ink on one side and plain on the other. Tablets: 200 mg lumacaftor and 125 mg ivacaftor; supplied as pink, oval-shaped, film-coated, fixed-dose combination tablets containing 200 mg of lumacaftor and 125 mg of ivacaftor.
Each tablet is printed with the characters "2V125" in black ink on one side and plain on the other. Oral granules: Unit-dose packets containing lumacaftor 75 mg/ivacaftor 94 mg or lumacaftor 100 mg/ivacaftor 125 mg or lumacaftor 150 mg/ivacaftor 188 mg per packet; supplied as small, white to off-white granules in unit-dose packets. Tablets: lumacaftor 100 mg and ivacaftor 125 mg; lumacaftor 200 mg and ivacaftor 125 mg.
( 3 ) Oral granules: Unit-dose packets of lumacaftor 75 mg and ivacaftor 94 mg; lumacaftor 100 mg and ivacaftor 125 mg; lumacaftor 150 mg and ivacaftor 188 mg. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Use in patients with advanced liver disease: ORKAMBI should be used with caution in these patients and only if the benefits are expected to outweigh the risks. If ORKAMBI is used in these patients, they should be closely monitored after the initiation of treatment and the dosage should be reduced. Liver function decompensation, including liver failure leading to death, has been reported in CF patients with pre-existing cirrhosis with portal hypertension.
( 2.2 , 5.1 , 6.1 ) Liver-related events: Elevated transaminases (ALT/AST) have been observed in some cases associated with elevated bilirubin. Measure serum transaminases and bilirubin before initiating ORKAMBI, every 3 months during the first year of treatment, and annually thereafter. For patients with a history of ALT, AST, or bilirubin elevations, more frequent monitoring should be considered.
Interrupt dosing in patients with ALT or AST >5 × upper limit of normal (ULN), or ALT or AST >3 × ULN with bilirubin >2 × ULN. Following resolution, consider the benefits and risks of resuming dosing. ( 5.2 , 6.1 ) Hypersensitivity reactions: Angioedema and anaphylaxis have been reported with ORKAMBI in the postmarketing setting.
Initiate appropriate therapy in the event of a hypersensitivity reaction. ( 5.3 ) Intracranial hypertension: Intracranial hypertension (IH) has been reported in the postmarketing setting with the use of ORKAMBI. If an unusual headache or visual disturbances occur during treatment, and IH is suspected, interrupt ORKAMBI and refer for prompt medical evaluation.
( 5.4 ) Neuropsychiatric events, including suicidal thoughts and behaviors : Serious neuropsychiatric events, including symptoms of anxiety, depression, suicidal ideation and behavior, and sleep disturbances, have been reported in the postmarketing setting for ORKAMBI or drugs containing the same or similar active ingredients. Monitor patients closely for new or worsening symptoms. Consider the risks and benefits for the individual patient to determine if therapy with ORKAMBI should be interrupted at the occurrence of neuropsychiatric symptoms.
( 5.5 ) Respiratory events: Chest discomfort, dyspnea, and respiration abnormal were observed more commonly during initiation of ORKAMBI. Clinical experience in patients with percent predicted FEV 1 (ppFEV 1 ) <40 is limited, and additional monitoring of these patients is recommended during initiation of therapy. ( 5.6 , 6.1 ) Blood pressure: Increased blood pressure has been observed in some patients.
Periodically monitor blood pressure in all patients. ( 5.7 , 6.1 ) Drug interactions: Use with sensitive CYP3A substrates or CYP3A substrates with a narrow therapeutic index may decrease systemic exposure of the medicinal products and co-administration is not recommended. Hormonal contraceptives should not be relied upon as an effective method of contraception and their use is associated with increased menstruation-related adverse reactions.
Use with strong CYP3A inducers may diminish exposure of ivacaftor, which may diminish its effectiveness; therefore, co-administration is not recommended. ( 5.8 , 6.1 , 7 , 12.3 ) Cataracts: Non-congenital lens opacities/cataracts have been reported in pediatric patients treated with ORKAMBI and ivacaftor, a component of ORKAMBI. Baseline and follow-up examinations are recommended in pediatric patients initiating ORKAMBI.
( 5.9 )
5.1Use in Patients with Advanced Liver Disease Worsening of liver function, including hepatic encephalopathy, in patients with advanced liver disease has been reported. Liver function decompensation, including liver failure leading to death, has been reported in CF patients with pre-existing cirrhosis with portal hypertension while receiving ORKAMBI. Use ORKAMBI with caution in patients with advanced liver disease and only if the benefits are expected to outweigh the risks.
If ORKAMBI is used in these patients, they should be closely monitored after the initiation of treatme… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the label: Use in Patients with Advanced Liver Disease [see Warnings and Precautions (5.1) ] Liver-related Events [see Warnings and Precautions (5.2) ] Hypersensitivity Reactions, Including Anaphylaxis [see Warnings and Precautions (5.3) ] Intracranial Hypertension [see Warnings and Precautions (5.4) ] Neuropsychiatric Events, Including Suicidal Thoughts and Behaviors [see Warnings and Precautions (5.5) ] Respiratory Events [see Warnings and Precautions (5.6) ] Effect on Blood Pressure [see Warnings and Precautions (5.7) ] Cataracts [see Warnings and Precautions (5.9) ] The most common adverse reactions to ORKAMBI (occurring in ≥5% of patients with CF homozygous for the F508del mutation in the CFTR gene) were dyspnea, nasopharyngitis, nausea, diarrhea, upper respiratory tract infection, fatigue, respiration abnormal, blood creatine phosphokinase increased, rash, flatulence, rhinorrhea, influenza.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Vertex Pharmaceuticals Incorporated at 1-877-634-8789 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The overall safety profile of ORKAMBI is based on the pooled data from 1108 patients with CF aged 12 years and older who are homozygous for the F508del mutation in the CFTR gene and who received at least one dose of study drug in two double-blind, placebo-controlled, Phase 3 clinical trials, each with 24 weeks of treatment (Trials 1 and 2).
In addition, the following clinical trials have been conducted: A 24-week, open-label trial (Trial 3) in 58 patients with CF aged 6 through 11 years homozygous for the F508del-CFTR mutation. A 24-week, placebo-controlled trial (Trial 4) in 204 patients aged 6 through 11 years homozygous for the F508del-CFTR mutation. A 24-week, open-label trial (Trial 5) in 46 patients aged 12 years and older homozygous for the F508del-CFTR mutation and with advanced lung disease (ppFEV 1 <40).
A 24-week, open-label trial (Trial 6) in 60 patients aged 2 through 5 years homozygous for the F508del-CFTR mutation. A 24-week, open-label trial (Trial 7) in 46 patients aged 1 through 2 years homozygous for the F508del - CFTR mutation. Of the 1108 patients, in the pooled analyses of Trial 1 and Trial 2, 49% were female and 99% were Caucasian; 369 patients received ORKAMBI every 12 hours and 370 patients received placebo.
The proportion of patients who prematurely discontinued study drug due to adverse events was 5% for patients treated with ORKAMBI and 2% for patients who received placebo. Serious adverse reactions, whether considered drug-related or not by the investigators, that occurred more frequently in patients treated with ORKAMBI included pneumonia, hemoptysis, cough, increased blood creatine phosphokinase, and transaminase elevations. These occurred in 1% or less of patients.
Table 3 shows adverse reactions occurring in ≥5% of patients with CF aged 12 years and older treated with ORKAMBI who are homozygous for the F508del mutation in the CFTR gene that also occurred at a higher rate than in patients who received placebo in the two double-blind, placebo-controlled trials. Table 3: Incidence of Adverse Drug Reactions in ≥5% of ORKAMBI-Treated Patients Aged 12 Years and Older Who are Homozygous for the F508del Mutation in the CFTR Gene in 2 Placebo-Controlled Phase 3 Clinical Trials of 24 Weeks Duration Adverse Reaction (Preferred Term) ORKAMBI N=369 (%) Placebo N=370 (%) Dyspnea 48 (13) 29 (8) Nasopharyngitis 48 (13) 40 (11) Nausea 46 (13) 28 (8) Diarrhea 45 (12) 31 (8) Upper respiratory tract infection 37 (10) 20 (5) Fatigue 34 (9) 29 (8) Respiration abnormal 32 (9)… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
5.8Drug Interactions Substrates of CYP3A Lumacaftor is a strong inducer of CYP3A. Administration of ORKAMBI may decrease systemic exposure of medicinal products that are substrates of CYP3A, which may decrease therapeutic effect. Co-administration with sensitive CYP3A substrates or CYP3A substrates with a narrow therapeutic index is not recommended.
ORKAMBI may substantially decrease hormonal contraceptive exposure, reducing their effectiveness and increasing the incidence of menstruation-associated adverse reactions, e.g., amenorrhea, dysmenorrhea, menorrhagia, menstrual irregular (27% in women using hormonal contraceptives compared with 3% in women not using hormonal contraceptives). Hormonal contraceptives, including oral, injectable, transdermal, and implantable, should not be relied upon as an effective method of contraception when co-administered with ORKAMBI [see Adverse Reactions (6.1) , Drug Interactions (7.3 , 7.11) , and Clinical Pharmacology (12.3) ] .
Strong CYP3A Inducers Ivacaftor is a substrate of CYP3A4 and CYP3A5 isoenzymes. Use of ORKAMBI with strong CYP3A inducers, such as rifampin, significantly reduces ivacaftor exposure, which may reduce the therapeutic effectiveness of ORKAMBI. Therefore, co-administration with strong CYP3A inducers (e.g., rifampin, St.
John's wort [ Hypericum perforatum ]) is not recommended [see Drug Interactions (7.2) and Clinical Pharmacology (12.3) ] .
7 DRUG INTERACTIONS See Full Prescribing Information for a complete list. ( 2.3 , 7 , 12.3 ) Potential for Other Drugs to Affect Lumacaftor/Ivacaftor
7.1Inhibitors of CYP3A Co-administration of lumacaftor/ivacaftor with itraconazole, a strong CYP3A inhibitor, did not impact the exposure of lumacaftor, but increased ivacaftor exposure by 4.3-fold. Due to the induction effect of lumacaftor on CYP3A, at steady-state, the net exposure of ivacaftor is not expected to exceed that when given in the absence of lumacaftor at a dose of 150 mg every 12 hours (the approved dose of ivacaftor monotherapy). Therefore, no dosage adjustment is necessary when CYP3A inhibitors are initiated in patients currently taking ORKAMBI.
However, when initiating ORKAMBI in patients taking strong CYP3A inhibitors, reduce the ORKAMBI dosage as recommended for the first week of treatment to allow for the steady-state induction effect of lumacaftor. Following this period, continue with the recommended daily dose [see Dosage and Administration (2.3) ] . Examples of strong CYP3A inhibitors include: ketoconazole, itraconazole, posaconazole, and voriconazole. telithromycin, clarithromycin.
No dosage adjustment is recommended when used with moderate or weak CYP3A inhibitors.
7.2Inducers of CYP3A Co-administration of lumacaftor/ivacaftor with rifampin, a strong CYP3A inducer, had minimal effect on the exposure of lumacaftor, but decreased ivacaftor exposure (AUC) by 57%. This may reduce the effectiveness of ORKAMBI. Therefore, co-administration with strong CYP3A inducers, such as rifampin, rifabutin, phenobarbital, carbamazepine, phenytoin, and St.
John's wort ( Hypericum perforatum ), is not recommended [see Warnings and Precautions (5.8) and Clinical Pharmacology (12.3) ] . No dosage adjustment is recommended when used with moderate or weak CYP3A inducers. Potential for Lumacaftor/Ivacaftor to Affect Other Drugs
7.3CYP3A Substrates Lumacaftor is a strong inducer of CYP3A. Co-administration of lumacaftor with ivacaftor, a sensitive CYP3A substrate, decreased ivacaftor exposure by approximately 80%. Administration of ORKAMBI may decrease systemic exposure of medicinal products which are substrates of CYP3A, thereby decreasing the therapeutic effect of the medicinal product.
Co-administration of ORKAMBI is not recommended with sensitive CYP3A substrates or CYP3A substrates with a narrow therapeutic index [see Warnings and Precautions (5.8) and Clinical Pharmacology (12.3) ] such as: Benzodiazepines : midazolam, triazolam (consider an alternative to these benzodiazepin… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are limited and incomplete human data from clinical trials and postmarketing reports on use of ORKAMBI or its individual components, lumacaftor or ivacaftor, in pregnant women to inform a drug-associated risk. In animal reproduction studies, oral administration of lumacaftor to pregnant rats and rabbits during organogenesis demonstrated no adverse effects on fetal development at doses that produced maternal exposures up to approximately 8 (rats) and 5 (rabbits) times the exposure at the maximum recommended human dose (MRHD).
Oral administration of ivacaftor to pregnant rats and rabbits during organogenesis demonstrated no adverse effects on fetal development at doses that produced maternal exposures up to approximately 7 (rats) and 45 (rabbits) times the exposure at the MRHD. No adverse developmental effects were observed after oral administration of either lumacaftor or ivacaftor to pregnant rats from organogenesis through lactation at doses that produced maternal exposures approximately 8 and 5 times the exposures at the MRHD, respectively (see Data ) .
There are no animal reproduction studies with concomitant administration of lumacaftor and ivacaftor. The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data Lumacaftor In an embryo-fetal development (EFD) study, pregnant rats were administered lumacaftor at oral doses of 500, 1000, or 2000 mg/kg/day during the period of organogenesis from gestation days 7-17. Lumacaftor did not affect fetal development or survival at exposures up to 8 times the MRHD (on an AUC basis at maternal oral doses up to 2000 mg/kg/day). In an EFD study, pregnant rabbits were administered lumacaftor at oral doses of 50, 100, or 200 mg/kg/day during the period of organogenesis from gestation days 7-19.
Lumacaftor did not affect fetal development or survival at exposures up to 5 times the MRHD (on an AUC basis at maternal oral doses up to 200 mg/kg/day). Maternal toxicity as evidenced by decreased body weight, decreased food consumption, and clinical signs was observed at 100 and 200 mg/kg/day without any adverse fetal effects. In a pre- and post-natal development study in pregnant female rats administered lumacaftor at 250, 500, or 1000 mg/kg/day from gestation day 6 through lactation day 20, lumacaftor had no effects on delivery or growth and development of offspring at exposures up to 8 times the MRHD (on an AUC basis at maternal oral doses up to 1000 mg/kg/day).
Placental transfer of lumacaftor was observed in pregnant rats and rabbits. Ivacaftor In an EFD study, pregnant rats were administered ivacaftor at oral doses of 50, 100, or 200 mg/kg/day during the period of organogenesis from gestation days 7-17. Ivacaftor did not affect fetal survival at exposures up to 7 times the MRHD (based on summed AUCs for ivacaftor and its metabolites at maternal oral doses up to 200 mg/kg/day).
Maternal toxicity (i.e., decreased mean body weight and body weight gain) was observed at 100 and 200 mg/kg/day (5 and 7 times the exposure at the MRHD, respectively) and was associated with a decrease in fetal body weights at a maternal dose of 200 mg/kg/day (7 times the MRHD). In an EFD study, pregnant rabbits were administered ivacaftor at oral doses of 25, 50, or 100 mg/kg/day during the period of organogenesis from gestation days 7-19. Ivacaftor did not affect fetal development or survival at exposures up to 45 times the MRHD (on an ivacaftor AUC basis at maternal oral doses up to 100 mg/kg/day).
Maternal toxicity (i.e., death, decreased food consumption, decreased mean body weight and body weight gain, decreased clinical condition, abortions) was observed at doses greater than or equal to 50 mg/kg/day (approximately 15… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are limited and incomplete human data from clinical trials and postmarketing reports on use of ORKAMBI or its individual components, lumacaftor or ivacaftor, in pregnant women to inform a drug-associated risk. In animal reproduction studies, oral administration of lumacaftor to pregnant rats and rabbits during organogenesis demonstrated no adverse effects on fetal development at doses that produced maternal exposures up to approximately 8 (rats) and 5 (rabbits) times the exposure at the maximum recommended human dose (MRHD).
Oral administration of ivacaftor to pregnant rats and rabbits during organogenesis demonstrated no adverse effects on fetal development at doses that produced maternal exposures up to approximately 7 (rats) and 45 (rabbits) times the exposure at the MRHD. No adverse developmental effects were observed after oral administration of either lumacaftor or ivacaftor to pregnant rats from organogenesis through lactation at doses that produced maternal exposures approximately 8 and 5 times the exposures at the MRHD, respectively (see Data ) .
There are no animal reproduction studies with concomitant administration of lumacaftor and ivacaftor. The background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Data Animal Data Lumacaftor In an embryo-fetal development (EFD) study, pregnant rats were administered lumacaftor at oral doses of 500, 1000, or 2000 mg/kg/day during the period of organogenesis from gestation days 7-17. Lumacaftor did not affect fetal development or survival at exposures up to 8 times the MRHD (on an AUC basis at maternal oral doses up to 2000 mg/kg/day). In an EFD study, pregnant rabbits were administered lumacaftor at oral doses of 50, 100, or 200 mg/kg/day during the period of organogenesis from gestation days 7-19.
Lumacaftor did not affect fetal development or survival at exposures up to 5 times the MRHD (on an AUC basis at maternal oral doses up to 200 mg/kg/day). Maternal toxicity as evidenced by decreased body weight, decreased food consumption, and clinical signs was observed at 100 and 200 mg/kg/day without any adverse fetal effects. In a pre- and post-natal development study in pregnant female rats administered lumacaftor at 250, 500, or 1000 mg/kg/day from gestation day 6 through lactation day 20, lumacaftor had no effects on delivery or growth and development of offspring at exposures up to 8 times the MRHD (on an AUC basis at maternal oral doses up to 1000 mg/kg/day).
Placental transfer of lumacaftor was observed in pregnant rats and rabbits. Ivacaftor In an EFD study, pregnant rats were administered ivacaftor at oral doses of 50, 100, or 200 mg/kg/day during the period of organogenesis from gestation days 7-17. Ivacaftor did not affect fetal survival at exposures up to 7 times the MRHD (based on summed AUCs for ivacaftor and its metabolites at maternal oral doses up to 200 mg/kg/day).
Maternal toxicity (i.e., decreased mean body weight and body weight gain) was observed at 100 and 200 mg/kg/day (5 and 7 times the exposure at the MRHD, respectively) and was associated with a decrease in fetal body weights at a maternal dose of 200 mg/kg/day (7 times the MRHD). In an EFD study, pregnant rabbits were administered ivacaftor at oral doses of 25, 50, or 100 mg/kg/day during the period of organogenesis from gestation days 7-19. Ivacaftor did not affect fetal development or survival at exposures up to 45 times the MRHD (on an ivacaftor AUC basis at maternal oral doses up to 100 mg/kg/day).
Maternal toxicity (i.e., death, decreased food consumption, decreased mean body weight and body weight gain, decreased clinical condition, abortions) was observed at doses greater than or equal to 50 mg/kg/day (approximately 15 times the MRHD). In a pre- and… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of ORKAMBI in pediatric patients aged one year and older have been established. Use of ORKAMBI in these age groups is supported by evidence from adequate and well-controlled studies of ORKAMBI in patients aged 12 years and older [see Clinical Studies (14) and Adverse Reactions (6.1) ] with additional data as follows: Extrapolation of efficacy in patients aged 12 years and older homozygous for the F508del mutation in the CFTR gene to pediatric patients aged 1 through 11 years with support from population pharmacokinetic analyses showing similar drug exposure levels in patients aged 12 years and older and in patients aged 1 through 11 years [see Clinical Pharmacology (12.3) ] .
Safety data were obtained from a 24-week, open-label, clinical trial in 58 patients aged 6 through 11 years, mean age 9 years (Trial 3) and a 24-week, placebo-controlled, clinical trial in 204 patients aged 6 through 11 years (Trial 4). Trial 3 evaluated subjects with a screening ppFEV 1 ≥40 [mean ppFEV 1 91.4 at baseline (range: 55 to 122.7)]. Trial 4 evaluated subjects with a screening ppFEV 1 ≥70 [mean ppFEV 1 89.8 at baseline (range: 48.6 to 119.6)].
The safety profile of ORKAMBI in pediatric patients 6 through 11 years of age was similar to that in patients aged 12 years and older [see Adverse Reactions (6.1) ] . In Trial 3, spirometry (ppFEV 1 ) was assessed as a planned safety endpoint. The within-group LS mean absolute change from baseline in ppFEV 1 at Week 24 was 2.5 percentage points.
At the Week 26 safety follow-up visit (following a planned discontinuation) ppFEV 1 was also assessed. The within-group LS mean absolute change in ppFEV 1 from Week 24 at Week 26 was -3.2 percentage points. Additional safety data were obtained from Trial 6, a 24-week, open-label, clinical trial in 60 patients aged 2 through 5 years at screening (mean age at baseline 3.7 years).
The safety profile in Trial 6 was similar to that in patients aged 6 years and older [see Adverse Reactions (6.1) ] . Additional safety data were obtained from Trial 7, a 24-week, open-label, clinical trial in 46 patients aged 1 to 2 years at screening (mean age at baseline 18.1 months). The safety profile in Trial 7 was similar to that in patients aged 2 years and older [see Adverse Reactions (6.1) ] .
Safety was evaluated in a 96-week open-label clinical trial (Trial 8) in 52 patients (39 rolled over from Trial 7 and 13 ORKAMBI naïve) aged 1 to 2 years. Adverse reactions from trial 8 were generally similar to those reported in Trial 7. The safety and effectiveness of ORKAMBI in patients with CF younger than 1 year of age have not been established.
Cases of non-congenital lens opacities have been reported in pediatric patients treated with ORKAMBI and ivacaftor, a component of ORKAMBI. Although other risk factors were present in some cases (such as corticosteroid use and exposure to radiation), a possible risk attributable to ivacaftor cannot be excluded [see Warnings and Precautions (5.9) ] . Juvenile Animal Toxicity Data In a juvenile toxicology study in which ivacaftor was administered to rats from post-natal days 7 to 35, cataracts were observed at all dose levels, ranging from 0.3 to 2 times the MRHD (based on summed AUCs for ivacaftor and its metabolites at oral doses of 10-50 mg/kg/day).
This finding has not been observed in older animals.
🧓 Geriatric Use ▾
8.5Geriatric Use CF is largely a disease of children and young adults. Clinical trials of ORKAMBI did not include sufficient numbers of patients 65 years of age and over to determine whether they respond differently from younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE There have been no reports of overdose with ORKAMBI. The highest repeated dose was lumacaftor 1000 mg once daily/ivacaftor 450 mg q12h administered to 49 healthy subjects for 7 days in a trial evaluating the effect of ORKAMBI on electrocardiograms (ECGs). Adverse events reported at an increased incidence of ≥5% compared to the lumacaftor 600 mg/ivacaftor 250 mg dosing period and placebo included: headache (29%), transaminase increased (18%), and generalized rash (10%).
No specific antidote is available for overdose with ORKAMBI. Treatment of overdose consists of general supportive measures including monitoring of vital signs and observation of the clinical status of the patient.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The CFTR protein is a chloride channel present at the surface of epithelial cells in multiple organs. The F508del mutation results in protein misfolding, causing a defect in cellular processing and trafficking that targets the protein for degradation and therefore reduces the quantity of CFTR at the cell surface. The small amount of F508del-CFTR that reaches the cell surface is less stable and has low channel-open probability (defective gating activity) compared to wild-type CFTR protein.
Lumacaftor improves the conformational stability of F508del-CFTR, resulting in increased processing and trafficking of mature protein to the cell surface. Ivacaftor is a CFTR potentiator that facilitates increased chloride transport by potentiating the channel-open probability (or gating) of the CFTR protein at the cell surface. In vitro studies have demonstrated that both lumacaftor and ivacaftor act directly on the CFTR protein in primary human bronchial epithelial cultures and other cell lines harboring the F508del-CFTR mutation to increase the quantity, stability, and function of F508del-CFTR at the cell surface, resulting in increased chloride ion transport.
In vitro responses do not necessarily correspond to in vivo pharmacodynamic response or clinical benefit.
12.2Pharmacodynamics Sweat Chloride Evaluation Changes in sweat chloride in response to relevant doses of lumacaftor alone or in combination with ivacaftor were evaluated in a double-blind, placebo-controlled, Phase 2 clinical trial in patients with CF aged 18 years and older either homozygous or heterozygous for the F508del mutation. In that trial, 10 patients (homozygous for F508del ) completed dosing with lumacaftor alone 400 mg q12h for 28 days followed by the addition of ivacaftor 250 mg q12h for an additional 28 days and 25 patients (homozygous or heterozygous for F508del ) completed dosing with placebo.
The treatment difference between lumacaftor 400 mg q12h alone and placebo evaluated as mean change in sweat chloride from baseline to Day 28 compared to placebo was -8.2 mmol/L (95% CI: -14, -2). The treatment difference between the combination of lumacaftor 400 mg/ivacaftor 250 mg q12h and placebo evaluated as mean change in sweat chloride from baseline to Day 56 compared to placebo was -11 mmol/L (95% CI: -18, -4). Changes in sweat chloride in response to lumacaftor/ivacaftor were also evaluated in a 24-week, open-label, clinical trial (Trial 3) in 58 patients with CF, aged 6 through 11 years (homozygous for F508del ) who received lumacaftor 200 mg/ivacaftor 250 mg q12h for 24 weeks.
Patients treated with lumacaftor/ivacaftor had a reduction in sweat chloride at Day 15 that was sustained through Week 24. The within-group LS mean absolute change from baseline in sweat chloride was -20.4 mmol/L at Day 15 and -24.8 mmol/L at Week 24. In addition, sweat chloride was also assessed after a 2-week washout period to evaluate the off-drug response.
The within-group LS mean absolute change in sweat chloride from Week 24 at Week 26 following the 2-week washout period was 21.3 mmol/L. Changes in sweat chloride in response to lumacaftor/ivacaftor were also evaluated in a 24-week, open-label, clinical trial (Trial 6) in 60 patients with CF, aged 2 through 5 years (homozygous for F508del ) who received either lumacaftor 100 mg/ivacaftor 125 mg every 12 hours or lumacaftor 150 mg/ivacaftor 188 mg every 12 hours for 24 weeks. Treatment with lumacaftor/ivacaftor demonstrated a reduction in sweat chloride at Week 4 that was sustained through Week 24.
The mean absolute change from baseline in sweat chloride was –31.7 mmol/L (95% CI: -35.7, -27.6) at Week 24. In addition, sweat chloride was also assessed after a 2-week washout period to evaluate the off-drug response. The mean absolute change in sweat chloride from Week 24 at Week 26 following the 2-week washout period was an increase of 33.0 mmol/L (95% CI: 28.9, 37.1; P <0.0001).
Changes in… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action The CFTR protein is a chloride channel present at the surface of epithelial cells in multiple organs. The F508del mutation results in protein misfolding, causing a defect in cellular processing and trafficking that targets the protein for degradation and therefore reduces the quantity of CFTR at the cell surface. The small amount of F508del-CFTR that reaches the cell surface is less stable and has low channel-open probability (defective gating activity) compared to wild-type CFTR protein.
Lumacaftor improves the conformational stability of F508del-CFTR, resulting in increased processing and trafficking of mature protein to the cell surface. Ivacaftor is a CFTR potentiator that facilitates increased chloride transport by potentiating the channel-open probability (or gating) of the CFTR protein at the cell surface. In vitro studies have demonstrated that both lumacaftor and ivacaftor act directly on the CFTR protein in primary human bronchial epithelial cultures and other cell lines harboring the F508del-CFTR mutation to increase the quantity, stability, and function of F508del-CFTR at the cell surface, resulting in increased chloride ion transport.
In vitro responses do not necessarily correspond to in vivo pharmacodynamic response or clinical benefit.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING ORKAMBI (lumacaftor 200 mg/ivacaftor 125 mg) is supplied as pink, oval-shaped tablets; each tablet contains 200 mg of lumacaftor and 125 mg of ivacaftor, printed with "2V125" in black ink on one side and plain on the other, and is packaged as follows: 112–count tablet box containing a 4-week supply (4 weekly cartons of 7 daily blister strips with 4 tablets per strip). NDC 51167-809-01 ORKAMBI (lumacaftor 100 mg/ivacaftor 125 mg) is supplied as pink, oval-shaped tablets; each tablet contains 100 mg of lumacaftor and 125 mg of ivacaftor, printed with "1V125" in black ink on one side and plain on the other, and is packaged as follows: 112–count tablet box containing a 4-week supply (4 weekly cartons of 7 daily blister strips with 4 tablets per strip).
NDC 51167-700-02 ORKAMBI (lumacaftor/ivacaftor) oral granules are supplied as small white to off-white granules and enclosed in unit-dose packets as follows: 56-count carton (contains 56 unit-dose packets of lumacaftor 75 mg/ivacaftor 94 mg per packet) NDC 51167-122-01 56-count carton (contains 56 unit-dose packets of lumacaftor 100 mg/ivacaftor 125 mg per packet) NDC 51167-900-01 56-count carton (contains 56 unit-dose packets of lumacaftor 150 mg/ivacaftor 188 mg per packet) NDC 51167-500-02 Store at 20°C - 25°C (68°F - 77°F); excursions permitted to 15°C - 30°C (59°F - 86°F) [see USP Controlled Room Temperature].
📦 Storage and Handling ▾
Store at 20°C - 25°C (68°F - 77°F); excursions permitted to 15°C - 30°C (59°F - 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION The active ingredients in ORKAMBI tablets are lumacaftor, which has the following chemical name: 3-[6-({[1-(2,2-difluoro-1,3-benzodioxol-5-yl)cyclopropyl]carbonyl}amino)-3-methylpyridin-2-yl]benzoic acid, and ivacaftor, a CFTR potentiator, which has the following chemical name: N -(2,4-di-tert-butyl-5-hydroxyphenyl)-1,4-dihydro-4-oxoquinoline-3-carboxamide. The molecular formula for lumacaftor is C 24 H 18 F 2 N 2 O 5 and for ivacaftor is C 24 H 28 N 2 O 3 . The molecular weights for lumacaftor and ivacaftor are 452.41 and 392.49, respectively.
The structural formulas are: lumacaftor ivacaftor Lumacaftor is a white to off-white powder that is practically insoluble in water (0.02 mg/mL). Ivacaftor is a white to off-white powder that is practically insoluble in water (<0.05 µg/mL). ORKAMBI is available as a pink, oval-shaped, film-coated tablet for oral administration containing 200 mg of lumacaftor and 125 mg of ivacaftor.
Each ORKAMBI tablet contains 200 mg of lumacaftor and 125 mg of ivacaftor, and the following inactive ingredients: cellulose, microcrystalline; croscarmellose sodium; hypromellose acetate succinate; magnesium stearate; povidone; and sodium lauryl sulfate. The tablet film coat contains carmine, FD&C Blue #1, FD&C Blue #2, polyethylene glycol, polyvinyl alcohol, talc, and titanium dioxide. The printing ink contains ammonium hydroxide, iron oxide black, propylene glycol, and shellac.
ORKAMBI is also available as a pink, oval-shaped, film-coated tablet for oral administration containing 100 mg of lumacaftor and 125 mg of ivacaftor. Each ORKAMBI tablet contains 100 mg of lumacaftor and 125 mg of ivacaftor, and the following inactive ingredients: cellulose, microcrystalline; croscarmellose sodium; hypromellose acetate succinate; magnesium stearate; povidone; and sodium lauryl sulfate. The tablet film coat contains carmine, FD&C Blue #1, FD&C Blue #2, polyethylene glycol, polyvinyl alcohol, talc, and titanium dioxide.
The printing ink contains ammonium hydroxide, iron oxide black, propylene glycol, and shellac. ORKAMBI is also available as white to off-white granules for oral administration and enclosed in a unit-dose packet containing lumacaftor 75 mg/ivacaftor 94 mg, lumacaftor 100 mg/ivacaftor 125 mg or lumacaftor 150 mg/ivacaftor 188 mg per packet. Each unit-dose packet of ORKAMBI oral granules contains lumacaftor 75 mg/ivacaftor 94 mg, lumacaftor 100 mg/ivacaftor 125 mg or lumacaftor 150 mg/ivacaftor 188 mg per packet and the following inactive ingredients: cellulose, microcrystalline; croscarmellose sodium; hypromellose acetate succinate; povidone; and sodium lauryl sulfate.
Chemical Structure Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Advanced Liver Disease Inform patients that worsening of liver function, including hepatic encephalopathy, in patients with advanced liver disease occurred in some patients treated with ORKAMBI. Liver function decompensation, including liver failure leading to death, has been reported in CF patients with pre-existing cirrhosis with portal hypertension while receiving ORKAMBI [see Warnings and Precautions (5.1) ] .
Abnormalities in Liver Function and Testing Inform patients that abnormalities in liver function have occurred in patients treated with ORKAMBI. Blood tests to measure transaminases (ALT and AST) and bilirubin will be performed prior to initiating ORKAMBI, every 3 months during the first year of therapy, and annually thereafter. Advise patients to contact their healthcare provider if they develop symptoms consistent with hepatotoxicity [see Warnings and Precautions (5.2) ] .
Hypersensitivity Reactions, Including Anaphylaxis Hypersensitivity reactions including angioedema and anaphylaxis are possible with use of ORKAMBI. Inform patients of the early signs of hypersensitivity reactions including rash, hives, itching, facial swelling, tightness of the chest and wheezing. Advise patients to discontinue use of ORKAMBI immediately and contact their physician or go to the emergency department if these symptoms occur.
Intracranial Hypertension Inform patients that intracranial hypertension has occurred with the use of ORKAMBI. Instruct patients to notify their healthcare provider right away if they experience signs and symptoms of intracranial hypertension, including headache, blurred vision, diplopia, and vision loss [see Warnings and Precautions (5.4) ] . Neuropsychiatric Events, Including Suicidal Thoughts and Behaviors Inform patients that neuropsychiatric symptoms, including anxiety, depression, suicidal thoughts and behaviors, and sleep disturbances (e.g., insomnia), have been reported with the use of ORKAMBI or drugs containing the same or similar active ingredients as ORKAMBI.
The symptoms have been observed in patients with and without a history of similar symptoms and may occur within three months of ORKAMBI initiation. Instruct patients to contact their healthcare provider immediately if changes in behavior or thinking that are not typical for the patient occur, or if the patient develops suicidal ideation or behavior [see Warnings and Precautions (5.5) ] . Respiratory Events Inform patients that chest discomfort, dyspnea, and respiration abnormal were more common during initiation of ORKAMBI therapy, especially in patients with advanced lung disease and to contact their healthcare provider if they develop any of these symptoms [see Warnings and Precautions (5.6) ] .
Effect on Blood Pressure Inform patients that increased blood pressure has been observed in some patients treated with ORKAMBI and that periodic monitoring of their blood pressure during treatment is recommended and to contact their healthcare provider if they develop elevated blood pressure or notice elevations in pre-existing high blood pressure [see Warnings and Precautions (5.7) ] . Drug Interactions with CYP3A Inhibitors and Inducers Advise patients to inform their healthcare providers of all concomitant medications, herbal and dietary supplements.
Advise patients to avoid grapefruit products during the first week after treatment initiation with ORKAMBI [see Dosage and Administration (2.3) , Warnings and Precautions (5.8) , and Drug Interactions (7) ] . Instruct post-menarchal patients including females of reproductive potential on alternative methods of birth control because hormonal contraceptives should not be relied upon as an effective method of contraception. ORKAMBI may decrease the effectiveness of hormonal contraceptives and there is an increased incidence of menstruation-related adverse reactions when co-administered wit… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The exposure (AUC) of lumacaftor is approximately 2-fold higher in healthy adult volunteers compared to exposure in patients with CF. The exposure of ivacaftor is similar between healthy adult volunteers and patients with CF. After twice daily dosing, steady-state plasma concentrations of lumacaftor and ivacaftor in healthy subjects were generally reached after approximately 7 days of treatment, with an accumulation ratio of approximately 1.9 for lumacaftor.
The steady-state exposure of ivacaftor is lower than that of Day 1 due to the CYP3A induction effect of lumacaftor. Table 4: Mean (SD) Pharmacokinetic Parameters of Lumacaftor and Ivacaftor at Steady-State in Subjects with CF Drug C max (μg/mL) t ½ Based on lumacaftor 200 mg q12h/ivacaftor 250 mg q12h studied in healthy subjects. (h) AUC 0-12h (μg∙h/mL) Lumacaftor 400 mg q12h/ Ivacaftor 250 mg q12h Lumacaftor 25.0 (7.96) 25.2 (9.94) 198 (64.8) Ivacaftor 0.602 (0.304) 9.34 (3.81) 3.66 (2.25) Absorption When a single dose of lumacaftor/ivacaftor was administered with fat-containing foods, lumacaftor exposure was approximately 2 times higher and ivacaftor exposure was approximately 3 times higher than when taken in a fasting state.
Following multiple oral dose administration of lumacaftor in combination with ivacaftor, the exposure of lumacaftor generally increased proportional to dose over the range of 200 mg every 24 hours to 400 mg every 12 hours. The median (range) t max of lumacaftor is approximately 4.0 hours (2.0; 9.0) in the fed state. Following multiple oral dose administration of ivacaftor in combination with lumacaftor, the exposure of ivacaftor generally increased with dose from 150 mg every 12 hours to 250 mg every 12 hours.
The median (range) t max of ivacaftor is approximately 4.0 hours (2.0; 6.0) in the fed state. Distribution Lumacaftor is approximately 99% bound to plasma proteins, primarily to albumin. After oral administration of 200 mg every 24 hours for 28 days to patients with CF in a fed state, the mean (±SD) for apparent volumes of distribution was 86.0 (69.8) L.
Ivacaftor is approximately 99% bound to plasma proteins, primarily to alpha 1-acid glycoprotein and albumin. Elimination The half-life of lumacaftor is approximately 26 hours in patients with CF. The typical apparent clearance, CL/F (CV), of lumacaftor was estimated to be
2.38L/hr (29.4%) for patients with CF. The half-life of ivacaftor when given with lumacaftor is approximately 9 hours in healthy subjects. The typical CL/F (CV), of ivacaftor when given in combination with lumacaftor was estimated to be
25.1L/hr (40.5%) for patients with CF. Metabolism Lumacaftor is not extensively metabolized in humans with the majority of lumacaftor excreted unchanged in the feces. In vitro and in vivo data indicate that lumacaftor is mainly metabolized via oxidation and glucuronidation.
Ivacaftor is extensively metabolized in humans. In vitro and in vivo data indicate that ivacaftor is primarily metabolized by CYP3A. M1 and M6 are the two major metabolites of ivacaftor in humans.
Excretion Following oral administration of lumacaftor, the majority of lumacaftor (51%) is excreted unchanged in the feces. There was minimal elimination of lumacaftor and its metabolites in urine (only 8.6% of total radioactivity was recovered in the urine with 0.18% as unchanged parent). Following oral administration of ivacaftor alone, the majority of ivacaftor (87.8%) is eliminated in the feces after metabolic conversion.
There was minimal elimination of ivacaftor and its metabolites in urine (only 6.6% of total radioactivity was recovered in the urine). Specific Populations Pediatric Patients The following conclusions about exposures between adults and the pediatric population are based on population pharmacokinetics (PK) analyses: Table 5: Mean (SD) Lumacaftor and Ivacaftor Exposure by Age Group Age Group Weight Dose Mean Lumacaftor (SD) The mean lumacaftor (SD) AUC ss is comparable to the mean AUC s… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Sweat Chloride Evaluation Changes in sweat chloride in response to relevant doses of lumacaftor alone or in combination with ivacaftor were evaluated in a double-blind, placebo-controlled, Phase 2 clinical trial in patients with CF aged 18 years and older either homozygous or heterozygous for the F508del mutation. In that trial, 10 patients (homozygous for F508del ) completed dosing with lumacaftor alone 400 mg q12h for 28 days followed by the addition of ivacaftor 250 mg q12h for an additional 28 days and 25 patients (homozygous or heterozygous for F508del ) completed dosing with placebo.
The treatment difference between lumacaftor 400 mg q12h alone and placebo evaluated as mean change in sweat chloride from baseline to Day 28 compared to placebo was -8.2 mmol/L (95% CI: -14, -2). The treatment difference between the combination of lumacaftor 400 mg/ivacaftor 250 mg q12h and placebo evaluated as mean change in sweat chloride from baseline to Day 56 compared to placebo was -11 mmol/L (95% CI: -18, -4). Changes in sweat chloride in response to lumacaftor/ivacaftor were also evaluated in a 24-week, open-label, clinical trial (Trial 3) in 58 patients with CF, aged 6 through 11 years (homozygous for F508del ) who received lumacaftor 200 mg/ivacaftor 250 mg q12h for 24 weeks.
Patients treated with lumacaftor/ivacaftor had a reduction in sweat chloride at Day 15 that was sustained through Week 24. The within-group LS mean absolute change from baseline in sweat chloride was -20.4 mmol/L at Day 15 and -24.8 mmol/L at Week 24. In addition, sweat chloride was also assessed after a 2-week washout period to evaluate the off-drug response.
The within-group LS mean absolute change in sweat chloride from Week 24 at Week 26 following the 2-week washout period was 21.3 mmol/L. Changes in sweat chloride in response to lumacaftor/ivacaftor were also evaluated in a 24-week, open-label, clinical trial (Trial 6) in 60 patients with CF, aged 2 through 5 years (homozygous for F508del ) who received either lumacaftor 100 mg/ivacaftor 125 mg every 12 hours or lumacaftor 150 mg/ivacaftor 188 mg every 12 hours for 24 weeks. Treatment with lumacaftor/ivacaftor demonstrated a reduction in sweat chloride at Week 4 that was sustained through Week 24.
The mean absolute change from baseline in sweat chloride was –31.7 mmol/L (95% CI: -35.7, -27.6) at Week 24. In addition, sweat chloride was also assessed after a 2-week washout period to evaluate the off-drug response. The mean absolute change in sweat chloride from Week 24 at Week 26 following the 2-week washout period was an increase of 33.0 mmol/L (95% CI: 28.9, 37.1; P <0.0001).
Changes in sweat chloride in response to lumacaftor/ivacaftor were evaluated in a 24-week, open-label, clinical trial (Trial 7) in 46 patients with CF, aged 1 through 2 years (homozygous for F508del ) who received lumacaftor 75 mg/ivacaftor 94 mg (patient weighing 7 kg to <9 kg at screening), lumacaftor 100 mg/ivacaftor 125 mg (patient weighing 9 kg to <14 kg at screening), lumacaftor 150 mg/ivacaftor 188 mg (patient weighing ≥14 kg at screening), every 12 hours for 24 weeks. Treatment with lumacaftor/ivacaftor demonstrated a reduction in sweat chloride at Week 4 which was sustained through Week 24.
The mean absolute change from baseline in sweat chloride at Week 24 was -29.1 mmol/L (95% CI: -34.8, -23.4). In addition, sweat chloride was also assessed after a 2-week washout period to evaluate the off-drug response. The mean absolute change in sweat chloride from Week 24 at Week 26 following the 2-week washout period was 27.3 mmol/L (95% CI: 22.3, 32.3).
There was no direct correlation between decrease in sweat chloride levels and improvement in lung function (ppFEV 1 ). Cardiac Electrophysiology The effect of multiple doses of lumacaftor 600 mg once daily/ivacaftor 250 mg q12h and lumacaftor 1000 mg once daily/ivacaftor 450 mg q12h on QTc interval was evaluated in a randomized, placebo- and active-controlled (4… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES Dose Ranging Dose ranging for the clinical program consisted primarily of one double-blind, placebo-controlled, multiple-cohort trial which included 97 Caucasian patients with CF (homozygous for the F508del mutation) aged 18 years and older with a screening ppFEV 1 ≥40. In the trial, 76 patients (homozygous for the F508del mutation) were randomized to receive lumacaftor alone at once daily doses of 200 mg, 400 mg, or 600 mg or 400 mg q12h for 28 days followed by the addition of ivacaftor 250 mg q12h and 27 patients (homozygous or heterozygous for the F508del mutation) received placebo.
During the initial 28-day lumacaftor monotherapy period, treatment with lumacaftor demonstrated a dose-dependent decrease in ppFEV 1 compared to placebo. Changes from Day 1 at Day 28 in ppFEV 1 compared to placebo were 0.24, -1.4, -2.7, and -4.6 for the 200 mg once daily, 400 mg once daily, 600 mg once daily, and 400 mg q12h lumacaftor doses, respectively. Following the addition of ivacaftor 250 mg q12h, the changes from Day 1 at Day 56 in ppFEV 1 compared to placebo were 3.8, 2.7, 5.6, and 4.2, respectively.
Sweat chloride was also assessed in this trial. Following the initial 28 days of lumacaftor monotherapy, the changes from Day 1 at Day 28 in sweat chloride compared to placebo were -4.9, -8.3, -6.1, and -8.2 mmol/L for the 200 mg once daily, 400 mg once daily, 600 mg once daily, and 400 mg q12h lumacaftor doses, respectively. Following the addition of ivacaftor 250 mg q12h, the changes from Day 1 at Day 56 in sweat chloride compared to placebo were -5.0, -9.8, -9.5, and -11 mmol/L, respectively.
These data supported the evaluation of lumacaftor 400 mg/ivacaftor 250 mg q12h (ORKAMBI) and lumacaftor 600 mg once daily/ivacaftor 250 mg q12h in the confirmatory trials. Confirmatory The efficacy of ORKAMBI in patients with CF who are homozygous for the F508del mutation in the CFTR gene was evaluated in two randomized, double-blind, placebo-controlled, 24-week clinical trials (Trials 1 and 2) in 1108 clinically stable patients with CF of whom 369 patients received ORKAMBI twice daily. Trial 1 evaluated 549 patients with CF who were aged 12 years and older (mean age 25.1 years) with ppFEV 1 at screening between 40-90 [mean ppFEV 1 60.7 at baseline (range: 31.1 to 94.0)].
Trial 2 evaluated 559 patients aged 12 years and older (mean age 25.0 years) with ppFEV 1 at screening between 40-90 [mean ppFEV 1 60.5 at baseline (range: 31.3 to 99.8)]. Patients with a history of colonization with organisms such as Burkholderia cenocepacia , Burkholderia dolosa , or Mycobacterium abscessus , or who had 3 or more abnormal liver function tests (ALT, AST, AP, GGT ≥3 × the ULN or total bilirubin ≥2 × the ULN) were excluded. Patients in both trials were randomized 1:1:1 to receive either ORKAMBI (lumacaftor 400 mg q12h/ivacaftor 250 mg q12h; or lumacaftor 600 mg once daily/ivacaftor 250 mg q12h) or placebo.
Patients took the study drug with fat-containing food for 24 weeks in addition to their prescribed CF therapies (e.g., bronchodilators, inhaled antibiotics, dornase alfa, and hypertonic saline). The primary efficacy endpoint in both trials was change in lung function as determined by absolute change from baseline in ppFEV 1 at Week 24, assessed as the average of the treatment effects at Week 16 and at Week 24. In both trials, treatment with ORKAMBI resulted in a statistically significant improvement in ppFEV 1 .
The treatment difference between ORKAMBI and placebo for the mean absolute change in ppFEV 1 from baseline at Week 24 (assessed as the average of the treatment effects at Week 16 and at Week 24) was 2.6 percentage points [95% CI (1.2, 4.0)] in Trial 1 ( P =0.0003) and 3.0 percentage points [95% CI (1.6, 4.4)] in Trial 2 ( P <0.0001). These changes persisted throughout the 24-week treatment period (see Figure 1 ). Improvements in ppFEV 1 were observed regardless of age, disease severity, sex, and geographic region.
Figure 1. Absolute Cha… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No studies of carcinogenicity, mutagenicity, or impairment of fertility were conducted with ORKAMBI; however, studies are available for individual components, lumacaftor and ivacaftor, as described below. Lumacaftor A two-year study in Sprague-Dawley rats and a 26-week study in transgenic Tg.rasH2 mice were conducted to assess carcinogenic potential of lumacaftor. No evidence of tumorigenicity was observed in rats at lumacaftor oral doses up to 1000 mg/kg/day (approximately 5 and 13 times the MRHD on a lumacaftor AUC basis in males and females, respectively).
No evidence of tumorigenicity was observed in Tg.rasH2 mice at lumacaftor oral doses up to 1500 and 2000 mg/kg/day in female and male mice, respectively. Lumacaftor was negative for genotoxicity in the following assays: Ames test for bacterial gene mutation, in vitro chromosomal aberration assay in Chinese hamster ovary cells, and in vivo mouse micronucleus test. Lumacaftor had no effects on fertility and reproductive performance indices in male and female rats at an oral dose of 1000 mg/kg/day (approximately 3 and 8 times, respectively, the MRHD on a lumacaftor AUC basis).
Ivacaftor Two-year studies were conducted in mice and rats to assess carcinogenic potential of ivacaftor. No evidence of tumorigenicity was observed in mice and rats at ivacaftor oral doses up to 200 mg/kg/day and 50 mg/kg/day, respectively (approximately equivalent to 3 and 10 times the MRHD based on summed AUCs of ivacaftor and its metabolites). Ivacaftor was negative for genotoxicity in the following assays: Ames test for bacterial gene mutation, in vitro chromosomal aberration assay in Chinese hamster ovary cells, and in vivo mouse micronucleus test.
Ivacaftor impaired fertility and reproductive performance indices in male and female rats at an oral dose of 200 mg/kg/day (approximately 15 and 7 times the MRHD based on summed AUCs of ivacaftor and its metabolites). Increases in prolonged diestrus were observed in females at 200 mg/kg/day. Ivacaftor also increased the number of females with all nonviable embryos and decreased corpora lutea, implantations, and viable embryos in rats at 200 mg/kg/day (approximately 7 times the MRHD based on summed AUCs of ivacaftor and its metabolites) when dams were dosed prior to and during early pregnancy.
These impairments of fertility and reproductive performance in male and female rats at 200 mg/kg/day were attributed to severe toxicity. No effects on male or female fertility and reproductive performance indices were observed at an oral dose of ≤100 mg/kg/day (approximately 8 and 5 times the MRHD based on summed AUCs of ivacaftor and its metabolites).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No studies of carcinogenicity, mutagenicity, or impairment of fertility were conducted with ORKAMBI; however, studies are available for individual components, lumacaftor and ivacaftor, as described below. Lumacaftor A two-year study in Sprague-Dawley rats and a 26-week study in transgenic Tg.rasH2 mice were conducted to assess carcinogenic potential of lumacaftor. No evidence of tumorigenicity was observed in rats at lumacaftor oral doses up to 1000 mg/kg/day (approximately 5 and 13 times the MRHD on a lumacaftor AUC basis in males and females, respectively).
No evidence of tumorigenicity was observed in Tg.rasH2 mice at lumacaftor oral doses up to 1500 and 2000 mg/kg/day in female and male mice, respectively. Lumacaftor was negative for genotoxicity in the following assays: Ames test for bacterial gene mutation, in vitro chromosomal aberration assay in Chinese hamster ovary cells, and in vivo mouse micronucleus test. Lumacaftor had no effects on fertility and reproductive performance indices in male and female rats at an oral dose of 1000 mg/kg/day (approximately 3 and 8 times, respectively, the MRHD on a lumacaftor AUC basis).
Ivacaftor Two-year studies were conducted in mice and rats to assess carcinogenic potential of ivacaftor. No evidence of tumorigenicity was observed in mice and rats at ivacaftor oral doses up to 200 mg/kg/day and 50 mg/kg/day, respectively (approximately equivalent to 3 and 10 times the MRHD based on summed AUCs of ivacaftor and its metabolites). Ivacaftor was negative for genotoxicity in the following assays: Ames test for bacterial gene mutation, in vitro chromosomal aberration assay in Chinese hamster ovary cells, and in vivo mouse micronucleus test.
Ivacaftor impaired fertility and reproductive performance indices in male and female rats at an oral dose of 200 mg/kg/day (approximately 15 and 7 times the MRHD based on summed AUCs of ivacaftor and its metabolites). Increases in prolonged diestrus were observed in females at 200 mg/kg/day. Ivacaftor also increased the number of females with all nonviable embryos and decreased corpora lutea, implantations, and viable embryos in rats at 200 mg/kg/day (approximately 7 times the MRHD based on summed AUCs of ivacaftor and its metabolites) when dams were dosed prior to and during early pregnancy.
These impairments of fertility and reproductive performance in male and female rats at 200 mg/kg/day were attributed to severe toxicity. No effects on male or female fertility and reproductive performance indices were observed at an oral dose of ≤100 mg/kg/day (approximately 8 and 5 times the MRHD based on summed AUCs of ivacaftor and its metabolites).
📄 Patient Package Insert ▾
This Patient Information has been approved by the U.S. Food and Drug Administration. Revised: 03/2026 PATIENT INFORMATION ORKAMBI (or-KAM-bee) (lumacaftor and ivacaftor) tablets for oral use (lumacaftor and ivacaftor) oral granules What is ORKAMBI?
ORKAMBI is a prescription medicine used for the treatment of cystic fibrosis (CF) in people aged 1 year and older who have two copies of the F508del mutation ( F508del/F508del ) in their CFTR gene. ORKAMBI should not be used in people other than those who have two copies of the F508del mutation in their CFTR gene. It is not known if ORKAMBI is safe and effective in children under 1 year of age.
Before taking ORKAMBI, tell your doctor about all of your medical conditions, including if you: have or have had liver problems. are allergic to ORKAMBI or any ingredients in ORKAMBI. See the end of this patient information leaflet for a complete list of ingredients in ORKAMBI. have kidney problems. have lung problems. have had an organ transplant. have or have had mental health problems. are using birth control (hormonal contraceptives, including oral, injectable, transdermal, or implantable forms). Hormonal contraceptives should not be used as a method of birth control when taking ORKAMBI.
Talk to your doctor about the best birth control method you should use while taking ORKAMBI. are pregnant or plan to become pregnant. It is not known if ORKAMBI will harm your unborn baby. You and your doctor should decide if you will take ORKAMBI while you are pregnant. are breastfeeding or planning to breastfeed.
It is not known if ORKAMBI passes into your breast milk. You and your doctor should decide if you will take ORKAMBI while you are breastfeeding. Tell your doctor about all the medicines you take, including prescription and over-the-counter medicines, vitamins, and herbal supplements.
ORKAMBI may affect the way other medicines work, and other medicines may affect how ORKAMBI works. The dose of ORKAMBI may need to be adjusted when taken with certain medicines. Ask your doctor or pharmacist for a list of these medicines if you are not sure.
Especially tell your doctor if you take : antibiotics: rifampin (RIFAMATE ® , RIFATER ® ) or rifabutin (MYCOBUTIN ® ). seizure medicines: phenobarbital, carbamazepine (TEGRETOL ® , CARBATROL ® , EQUETRO ® ), or phenytoin (DILANTIN ® , PHENYTEK ® ). sedatives and anti-anxiety medicines: triazolam (HALCION ® ) or midazolam (DORMICUM ® , HYPNOVEL ® , and VERSED ® ). immunosuppressant medicines: cyclosporine, everolimus (ZORTRESS ® ), sirolimus (RAPAMUNE ® ), or tacrolimus (ASTAGRAF XL ® , ENVARSUS ® XR, PROGRAF ® , and PROTOPIC ® ).
St. John's wort (Hypericum perforatum). antifungal medicines including ketoconazole, itraconazole (such as SPORANOX ® ), posaconazole (such as NOXAFIL ® ), or voriconazole (such as VFEND ® ). antibiotics including telithromycin, clarithromycin (such as BIAXIN ® ), or erythromycin (such as ERY-TAB ® ). Know the medicines you take.
Keep a list of them to show your doctor and pharmacist when you get a new medicine. How should I take ORKAMBI? Take ORKAMBI exactly as your doctor tells you to take it.
Always take ORKAMBI tablets or granules with foods that contain fat . Examples of fat-containing foods include eggs, avocados, nuts, butter, peanut butter, cheese pizza, breast milk, infant formula, whole-milk dairy products (such as whole milk, cheese, and yogurt). Take your doses of ORKAMBI 12 hours apart.
ORKAMBI tablets (aged 6 years and older): Each ORKAMBI box contains 4 weekly cartons. Each carton contains 7 daily blister strips. Each blister strip contains 4 tablets so you can take 2 tablets for the morning and 2 tablets for the evening.
You may cut along the dotted line to separate your morning dose from your evening dose. To take your morning dose, unpeel the paper backing from a blister strip (do not push tablet through backing) to remove 2 ORKAMBI tablets and take them with fat-containing food. 12 hours after your previous dose, ope… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Warnings and Precautions, Intracranial Hypertension ( 5.4 ) 09/2025 Warnings and Precautions, Neuropsychiatric Events, Including Suicidal Thoughts and Behaviors ( 5.5 ) 03/2026
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 200 mg/125 mg Tablet Blister Pack Carton Box Rx only NDC 51167-809-01 ORKAMBI ® (Lumacaftor/Ivacaftor) tablets 200 mg/125 mg per tablet 112 tablets PRINCIPAL DISPLAY PANEL - 200 mg/125 mg Tablet Blister Pack Carton Box
PRINCIPAL DISPLAY PANEL - 100 mg/125 mg Tablet Blister Pack Carton Box Rx only NDC 51167-700-02 ORKAMBI ® (Lumacaftor/Ivacaftor) tablets 100 mg/125 mg per tablet 112 tablets PRINCIPAL DISPLAY PANEL - 100 mg/125 mg Tablet Blister Pack Carton Box
PRINCIPAL DISPLAY PANEL - 100 mg/125 mg Granule Packet Carton Rx only NDC 51167-900-01 ORKAMBI ® (Lumacaftor/Ivacaftor) 100 mg 125 mg Oral Granules 100 mg/125 mg per packet 56 packets Carton contains: 4 individual wallets with 14 packets per wallet Lift here to open PRINCIPAL DISPLAY PANEL - 100 mg/125 mg Granule Packet Carton
PRINCIPAL DISPLAY PANEL - 150 mg/188 mg Granule Packet Carton Rx only NDC 51167-500-02 ORKAMBI ® (Lumacaftor/Ivacaftor) 150 mg 188 mg Oral Granules 150 mg/188 mg per packet 56 packets Carton contains: 4 individual wallets with 14 packets per wallet Lift here to open PRINCIPAL DISPLAY PANEL - 150 mg/188 mg Granule Packet Carton
PRINCIPAL DISPLAY PANEL - 75 mg/94 mg Granule Packet Carton Rx only NDC 51167-122-01 ORKAMBI ® (Lumacaftor/Ivacaftor) 75 mg 94 mg Oral Granules 75 mg/94 mg per packet 56 packets Carton contains: 4 individual wallets with 14 packets per wallet Lift here to open PRINCIPAL DISPLAY PANEL - 75 mg/94 mg Granule Packet Carton
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2025 (Q1-Q4)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |