
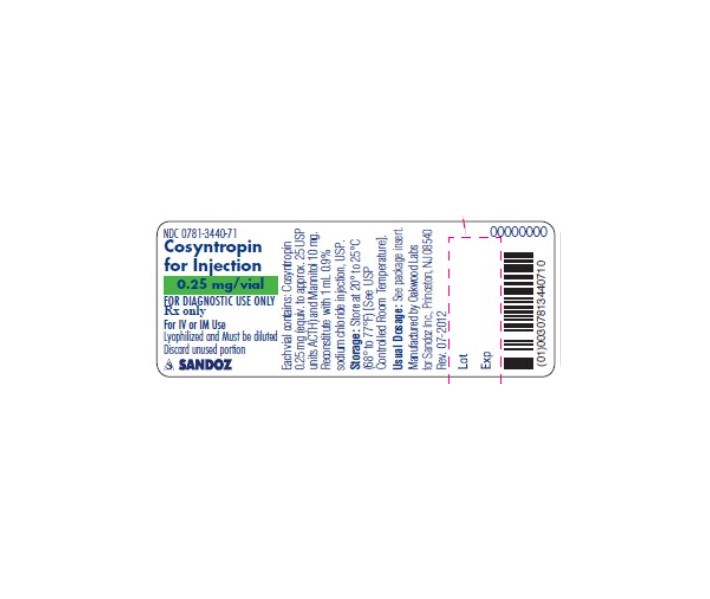
COSYNTROPIN .25 mg/mL Injection, Powder, Lyophilized, For Solution, 1 mL — NDC 51662-1567-1 (Billing 51662-1567-01)
This is a package of 1 mL of COSYNTROPIN .25 mg/mL Injection, Powder, Lyophilized, For Solution from HF Acquisition Co LLC, DBA HealthFirst, marketed since Jul 2021 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 51662-1567-1 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 51662 labeler · 1567 product · 1 package
- Package marketed since
- Jul 10, 2021
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 5166215671 1
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J0834 | $18.384 / J0834 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 4, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 51662-1567-01 You're viewing this Main listing | 1 mL in 1 VIAL | 2021-07-10 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Cosyntropin .25 mg/mL 71872-7313-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Cosyntropin .25 mg/mLthis 51662-1567-01 | HF | 1 ml | — | AP | FDA listed | — |
| Cosyntropin .25 mg/mL 00781-3440-95 | Sandoz | 10 vials | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
10 mg / 1 mL
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
1 inactive ingredient listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from HF Acquisition Co LLC, DBA HealthFirst labeler code 51662
- Ampicillin 2 g Injection, Powder, For Solution NDC 51662-1560-3
- SODIUM TETRADECYL SULFATE 10 mg/mL Injection, Solution NDC 51662-1562-1
- (SOTRADECOL) SODIUM TETRADECYL SULFATE 30 mg/mL Injection, Solution NDC 51662-1563-1
- ZIPRASIDONE MESYLATE 20 mg/mL Injection, Powder, Lyophilized, For Solution NDC 51662-1564-3
- LIDOCAINE HCI AND DEXTROSE 5 g/100mL; .8 g/100mL Injection, Solution NDC 51662-1565-1
- DOBUTAMINE HYDROCHLORIDE 100 mg/100mL Injection NDC 51662-1566-1
- VENOFER (IRON SUCROSE) 20 mg/mL Injection, Solution NDC 51662-1568-1
- FUROSEMIDE 10 mg/mL Injection, Solution NDC 51662-1572-1
- SODIUM BICARBONATE 84 mg/mL Injection, Solution NDC 51662-1573-1
- FUROSEMIDE 10 mg/mL Injection, Solution NDC 51662-1574-1
- FUROSEMIDE 10 mg/mL Injection, Solution NDC 51662-1575-1
- PHENYLEPHRINE HYDROCHLORIDE 10 mg/mL Injection NDC 51662-1576-1
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS & USAGE Cosyntropin for Injection is intended for use as a diagnostic agent in the screening of patients presumed to have adrenocortical insufficiency. Because of its rapid effect on the adrenal cortex it may be utilized to perform a 30-minute test of adrenal function (plasma cortisol response) as an office or outpatient procedure, using only 2 venipunctures (see DOSAGE AND ADMINISTRATION section). Severe hypofunction of the pituitary - adrenal axis is usually associated with subnormal plasma cortisol values but a low basal level is not per se evidence of adrenal insufficiency and does not suffice to make the diagnosis.
Many patients with proven insufficiency will have normal basal levels and will develop signs of insufficiency only when stressed. For this reason a criterion which should be used in establishing the diagnosis is the failure to respond to adequate corticotropin stimulation. When presumptive adrenal insufficiency is diagnosed by a subnormal Cosyntropin for Injection test, further studies are indicated to determine if it is primary or secondary.
Primary adrenal insufficiency (Addison's disease) is the result of an intrinsic disease process, such as tuberculosis within the gland. The production of adrenocortical hormones is deficient despite high ACTH levels (feedback mechanism). Secondary or relative insufficiency arises as the result of defective production of ACTH leading in turn to disuse atrophy of the adrenal cortex.
It is commonly seen, for example, as result of corticosteroid therapy, Sheehan's syndrome and pituitary tumors or ablation. The differentiation of both types is based on the premise that a primarily defective gland cannot be stimulated by ACTH whereas a secondarily defective gland is potentially functional and will respond to adequate stimulation with ACTH. Patients selected for further study as the result of a subnormal Cosyntropin for Injection test should be given a 3 or 4 day course of treatment with Repository Corticotropin Injection USP and then retested.
Suggested doses are 40 USP units twice daily for 4 days or 60 USP units twice daily for 3 days. Under these conditions little or no increase in plasma cortisol levels will be seen in Addison's disease whereas higher or even normal levels will be seen in cases with secondary adrenal insufficiency.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Cosyntropin for Injection may be administered intramuscularly or as a direct intravenous injection when used as a rapid screening test of adrenal function. It may also be given as an intravenous infusion over a 4 to 8 hour period to provide a greater stimulus to the adrenal glands. Doses of Cosyntropin for Injection 0.25 to 0.75 mg have been used in clinical studies and a maximal response noted with the smallest dose.
A suggested method for a rapid screening test of adrenal function has been described by Wood and Associates (1). A control blood sample of 6 to 7 mL is collected in a heparinized tube. Reconstitute 0.25 mg of Cosyntropin for Injection with 1mL of 0.9% Sodium Chloride Injection, USP and inject intramuscularly.
The reconstituted drug product should be inspected visually for particulate matter and discoloration prior to injection. Reconstituted Cosyntropin for Injection should not be retained. In the pediatric population, aged 2 years or less, a dose of 0.125 mg will often suffice.
A second blood sample is collected exactly 30 minutes later. Both blood samples should be refrigerated until sent to the laboratory for determination of the plasma cortisol response by some appropriate method. If it is not possible to send them to the laboratory or perform the fluorimetric procedure within 12 hours, then the plasma should be separated and refrigerated or frozen according to need.
Two alternative methods of administration are intravenous injection and infusion. Cosyntropin for Injection can be injected intravenously in 2 to 5 mL of saline over a 2-minute period. When given as an intravenous infusion: Cosyntropin for Injection, 0.25 mg may be added to glucose or saline solutions and given at the rate of approximately 40 micrograms per hour over a 6-hour period.
It should not be added to blood or plasma as it is apt to be inactivated by enzymes. Adrenal response may be measured in the usual manner by determining urinary steroid excretion before and after treatment or by measuring plasma cortisol levels before and at the end of the infusion. The latter is preferable because the urinary steroid excretion does not always accurately reflect the adrenal or plasma cortisol response to ACTH.
The usual normal response in most cases is an approximate doubling of the basal level, provided that the basal level does not exceed the normal range. Patients receiving cortisone, hydrocortisone or spironolactone should omit their pre-test doses on the day selected for testing. Patients taking inadvertent doses of cortisone or hydrocortisone on the test day and patients taking spironolactone or women taking drugs which contain estrogen may exhibit abnormally high basal plasma cortisol levels.
A paradoxical response may be noted in the cortisone or hydrocortisone group as seen in a decrease in plasma cortisol values following a stimulating dose of Cosyntropin for Injection. In the spironolactone or estrogen group only a normal incremental response is to be expected. Many patients with normal adrenal function, however, do not respond to the expected degree so that the following criteria have been established to denote a normal response: 1.
The control plasma cortisol level should exceed 5 micrograms/100 mL. 2. The 30-minute level should show an increment of at least 7 micrograms/100 mL above the basal level.
3. The 30-minute level should exceed 18 micrograms/100 mL. Comparable figures have been reported by Greig and co-workers (2).
Plasma cortisol levels usually peak about 45 to 60 minutes after an injection of Cosyntropin for Injection and some prefer the 60-minute interval for testing for this reason. While it is true that the 60-minute values are usually higher than the 30-minute values, the difference may not be significant enough in most cases to outweigh the disadvantage of a longer testing period. If the 60-minute test period is used, the criterion for a normal response is an approximate doubling of the basal pla… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATION The only contraindication to Cosyntropin for Injection is a history of a previous adverse reaction to it.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Since Cosyntropin for Injection is intended for diagnostic and not therapeutic use, adverse reactions other than a rare hypersensitivity reaction are not anticipated. A rare hypersensitivity reaction usually associated with a pre-existing allergic disease and/or a previous reaction to natural ACTH is possible. Symptoms may include slight whealing with splotchy erythema at the injection site.
There have been rare reports of anaphylactic reaction. The following adverse reactions have been reported in patients after the administration of Cosyntropin for Injection and the association has been neither confirmed nor refuted: • bradycardia • tachycardia • hypertension • peripheral edema • rash
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Cosyntropin for Injection exhibits the full corticosteroidogenic activity of natural ACTH. Various studies have shown that the biologic activity of ACTH resides in the N-terminal portion of the molecule and that the 1 to 20 amino acid residue is the minimal sequence retaining full activity. Partial or complete loss of activity is noted with progressive shortening of the chain beyond 20 amino acid residues.
For example, the decrement from 20 to 19 results in a 70% loss of potency. The pharmacologic profile of Cosyntropin for Injection is similar to that of purified natural ACTH. It has been established that 0.25 mg of will stimulate the adrenal cortex maximally and to the same extent as 25 units of natural ACTH.
This dose of Cosyntropin for Injection will produce maximal secretion of 17-OH corticosteroids, 17- ketosteroids and / or 17 - ketogenic steroids. The extra-adrenal effects which natural ACTH and Cosyntropin for Injection have in common include increased melanotropic activity, increased growth hormone secretion and an adipokinetic effect. These are considered to be without physiological or clinical significance.
Animal, human and synthetic ACTH (1 to 39) which all contain 39 amino acids exhibit similar immunologic activity. This activity resides in the C-terminal portion of the molecule and the 22 to 39 amino acid residues exhibit the greatest degree of antigenicity. In contrast, synthetic polypeptides containing 1 to 19 or fewer amino acids have no detectable immunologic activity.
Those containing 1 to 26, 1 to 24 or 1 to 23 amino acids have very little immunologic although full biologic activity. This property of Cosyntropin for Injection assumes added importance in view of the known antigenicity of natural ACTH.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Cosyntropin for Injection 0.25 mg is supplied as under: NDC # 0781-3440-95 Box of 10 vials Storage Store at 20° to 25°C (68° to 77°F); [See USP Controlled Room Temperature]. Excursions permitted to 15° to 30°C (59° to 86°F). Cosyntropin for Injection is lyophilized, single dose vial for diagnostic use only. It contains no antimicrobial preservative. Any unused portion should be discarded. Rx only
📋 Description ▾
DESCRIPTION Cosyntropin for Injection is a sterile lyophilized powder in vials containing 0.25 mg of Cosyntropin and 10 mg of mannitol to be reconstituted with 1 mL of 0.9% Sodium Chloride Injection, USP. Administration is by intravenous or intramuscular injection. Cosyntropin is a 1 to 24 corticotropin, a synthetic subunit of ACTH.
It is an open chain polypeptide containing, from the N terminus, the first 24 of the 39 amino acids of natural ACTH. The sequence of amino acids in the 1 to 24 compounds is as follows: DESCRIPTION
⚠️ Precautions ▾
PRECAUTIONS General Cosyntropin for Injection exhibits slight immunologic activity, does not contain animal protein and is therefore less risky to use than natural ACTH. Patients known to be sensitized to natural ACTH with markedly positive skin tests will, with few exceptions, react negatively when tested intradermally with Cosyntropin for Injection. Most patients with a history of a previous hypersensitivity reaction to natural ACTH or a pre-existing allergic disease will tolerate Cosyntropin for Injection.
Despite this however, Cosyntropin for Injection is not completely devoid of immunologic activity and hypersensitivity reactions including rare anaphylaxis are possible. Therefore, the physician should be prepared, prior to injection, to treat any possible acute hypersensitivity reaction. Drug Interactions Corticotropin may accentuate the electrolyte loss associated with diuretic therapy.
Carcinogenesis, Mutagenesis, Impairment of Fertility Long term studies in animals have not been performed to evaluate carcinogenic or mutagenic potential or impairment of fertility. A study in rats noted inhibition of reproductive function like natural ACTH. Pregnancy Pregnancy Category C.
Animal reproduction studies have not been conducted with Cosyntropin for Injection. It is also not known whether Cosyntropin for Injection can cause fetal harm when administered to a pregnant woman or can affect reproduction capacity. Cosyntropin for Injection should be given to a pregnant woman only if clearly needed.
Nursing Mothers It is not known whether this drug is excreted in human milk. Because many drugs are excreted in human milk, caution should be exercised when Cosyntropin for Injection is administered to a nursing woman. Pediatric Use (See DOSAGE AND ADMINISTRATION section.)
📚 References ▾
REFERENCES 1. Wood, J.B. et al. LANCET 1.243, 1965. 2. Greig, W.R. et al. J. ENDOCR 34.411, 1966. 3. McGill, P.E. et al. ANN RHEUM DIS 26.123, 1967. Manufactured by Oakwood Labs, Solon, Ohio for Sandoz Inc., Princeton, NJ Rev. July 2012
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 51662-1567-1 - VIAL AND SERIALIZED VIAL LABELING RFID Label Vial Labeling
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |