
Fenofibrate 130 mg Capsule, 90-count
Other active recalls for Fenofibrate (different manufacturers) — 2 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Peroxisome Proliferator-activated Receptor alpha Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Fenofibrate helps bring your blood lipid levels into a healthier range. Depending on your situation, that might mean lowering your triglycerides, bringing down your LDL (bad) chole...
- What exactly is fenofibrate supposed to do for me?
- It depends on which form you have. Lipofen capsules should be taken with food. Antara capsules and most fenofibrate tablets can be taken with or without food. Some film-coated feno...
- Does it matter if I take this with food or on an empty stomach?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Fenofibrate — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.4788 | $43.09 / 90 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Fenofibrate 130 mg 68180-0131-06 | Lupin | 30 capsules | $0.702 | AB | Availability likely | — |
| Antara 130 mg 27437-0110-01 | Lupin | 100 capsules | — | AB | Discontinued | — |
| Fenofibrate 130 mgthis 55111-0395-90 | Dr. | 90 capsules | — | AB | FDA listed | — |
| Fenofibrate 130 mg 60505-3121-01 | Apotex | 100 capsules | — | AB | FDA listed | — |
| Fenofibrate 130 mg 63304-0444-05 | Sun | 500 capsules | — | — | FDA listed | — |
| Fenofibrate 130 mg 72789-0310-30 | PD-Rx | 30 capsules | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 55111-0395-01 | 100 CAPSULE in 1 BOTTLE (55111-395-01) | 2014-04-07 | Active |
| 55111-0395-30 | 30 CAPSULE in 1 BOTTLE (55111-395-30) | 2014-04-07 | Active |
| 55111-0395-90 You're viewing this | 90 CAPSULE in 1 BOTTLE (55111-395-90) | 2014-04-07 | Active |
You're viewing one of 3 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 55111-0395-90?
What is the difference between NDC 55111-0395-90 and NDC 55111-0395-30?
What NDC number is used to bill for this package of Fenofibrate 130 mg Capsule?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Fenofibrate capsule is a peroxisome proliferator receptor alpha (PPARα) activator indicated as an adjunct to diet: to reduce elevated LDL-C, Total-C, triglycerides, and Apo B, and to increase HDL-C in adult patients with primary hypercholesterolemia or mixed dyslipidemia (1.1) . to reduce triglyceride (TG) levels in adult patients with severe hypertriglyceridemia (1.2) . Important Limitations of Use: Fenofibrate was not shown to reduce coronary heart disease morbidity and mortality in patients with type 2 diabetes mellitus ( 5.1) .
1.1Primary Hypercholesterolemia and Mixed Dyslipidemia Fenofibrate capsules are indicated as adjunctive therapy to diet to reduce elevated low-density lipoprotein cholesterol (LDL-C), total cholesterol (Total-C), triglycerides (TG), and apolipoprotein B (Apo B), and to increase high-density lipoprotein cholesterol (HDL-C) in adult patients with primary hypercholesterolemia or mixed dyslipidemia.
1.2Severe Hypertriglyceridemia Fenofibrate capsules are also indicated as adjunctive therapy to diet for treatment of adult patients with severe hypertriglyceridemia. Improving glycemic control in diabetic patients showing fasting chylomicronemia will usually reduce fasting triglycerides and eliminate chylomicronemia thereby obviating the need for pharmacologic intervention. Markedly elevated levels of serum triglycerides (e.g > 2,000 mg/dL) may increase the risk of developing pancreatitis.
The effect of fenofibrate capsules therapy on reducing this risk has not been adequately studied.
1.3Important Limitations of Use Fenofibrate capsules were not shown to reduce coronary heart disease morbidity and mortality in patients with type 2 diabetes mellitus [see Warnings and Precautions (5.1 ) ].
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Fenofibrate capsules can be taken without regard to meals (2.1) . Primary hypercholesterolemia and mixed dyslipidemia: 130 mg per day (2.2) . Severe Hypertriglyceridemia: 43 to 130 mg per day; the dose should be adjusted according to patient response (2.3). Renally impaired patients: Initial dose of 43 mg per day (2.4) . Geriatric patients: Select the dose on the basis of renal function (2.5) .
2.1General Considerations Patients should be placed on an appropriate lipid-lowering diet before receiving fenofibrate capsules, and should continue this diet during treatment with fenofibrate capsules. Fenofibrate capsules can be given without regard to meals. Patients should be advised to swallow fenofibrate capsules whole.
Do not open, crush, dissolve or chew capsules. The initial treatment for dyslipidemia is dietary therapy specific for the type of lipoprotein abnormality. Excess body weight and excess alcoholic intake may be important factors in hypertriglyceridemia and should be addressed prior to any drug therapy.
Physical exercise can be an important ancillary measure. Diseases contributory to hyperlipidemia, such as hypothyroidism or diabetes mellitus should be looked for and adequately treated. Estrogen therapy, thiazide diuretics and beta-blockers are sometimes associated with massive rises in plasma triglycerides, especially in subjects with familial hypertriglyceridemia.
In such cases, discontinuation of the specific etiologic agent may obviate the need for specific drug therapy of hypertriglyceridemia. Lipid levels should be monitored periodically and consideration should be given to reducing the dosage of fenofibrate if lipid levels fall significantly below the targeted range. Therapy should be withdrawn in patients who do not have an adequate response after two months of treatment with the maximum recommended dose of 130 mg once daily.
2.2Primary Hypercholesterolemia and Mixed Dyslipidemia The initial dose of fenofibrate capsules is 130 mg per day.
2.3Severe Hypertriglyceridemia The initial dose is 43 to 130 mg per day. Dosage should be individualized according to patient response, and should be adjusted if necessary following repeat lipid determinations at 4 to 8 week intervals. The maximum dose is 130 mg per day.
2.4Impaired Renal Function Treatment with fenofibrate capsules should be initiated at a dose of 43 mg per day in patients having mild to moderately impaired renal function, and increased only after evaluation of the effects on renal function and lipid levels at this dose. The use of fenofibrate capsules should be avoided in patients with severe renal impairment [see Use in Specific Populations (8.6) and Clinical Pharmacology ( 12.3 ) ].
2.5Geriatric Patients Dose selection for the elderly should be made on the basis of renal function [see Use in Specific Populations ( 8.6 ) and Clinical Pharmacology ( 12.3 ) ].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Fenofibrate Capsules USP 43 mg are size “4” capsules with light green cap and off white body imprinted in black ink with “LU” on cap and “C21” on body containing white to off white pellets. Fenofibrate Capsules USP 130 mg are size “1” capsules with dark green cap and white body imprinted in black ink with “LU” on cap and “C22” on body containing white to off white pellets. Oral capsules: 43 mg and 130 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Fenofibrate is contraindicated in: patients with severe renal impairment, including those receiving dialysis [see Clinical Pharmacology ( 12.3 ) ]. patients with active liver disease, including those with primary biliary cirrhosis and unexplained persistent liver function abnormalities [see Warnings and Precautions (5.3 ) ]. patients with pre-existing gallbladder disease [see Warnings and Precautions (5.5 ) ]. nursing mothers [see Use in Specific Populations ( 8.3 ) ]. patients with known hypersensitivity to fenofibric acid or fenofibrate [see Warnings and Precautions (5.9) ].
Severe renal dysfunction, including patients receiving dialysis ( 4 , 12.3 ) Active liver disease ( 4 , 5.3 ) Gallbladder disease ( 4 , 5.5 ) Nursing mothers ( 4 , 8.3 ) Known hypersensitivity to fenofibrate ( 4 , 5.9 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Myopathy and rhabdomyolysis have been reported in patients taking fenofibrate. The risk for serious muscle toxicity appears to be increased when fenofibrate is co-administered with a statin (with a significantly higher rate observed with gemfibrozil), particularly in elderly patients and in patients with diabetes, renal failure, or hypothyroidism (5.2) . Fenofibrate can increase serum transaminases.
Monitor liver tests, including ALT. periodically during therapy (5.3) . Fenofibrate can reversibly increase serum creatinine levels. Monitor renal function periodically in patients with renal impairment (5.4) .
Fenofibrate increases cholesterol excretion into the bile, leading to risk of cholelithiasis. If cholelithiasis is suspected, gallbladder studies are indicated (5.5 ). Exercise caution in concomitant treatment with coumarin anticoagulants.
Reduce the dosage of coumarin to maintain the PT/INR at the desired level to prevent bleeding complications (5.6). Acute hypersensitivity reactions, including anaphylaxis and angioedema, and delayed hypersensitivity reactions, including severe cutaneous adverse drug reactions have been reported postmarketing. Some cases were life-threatening and required emergency treatment.
Discontinue fibrate and treat patients appropriately if reactions occur (5.9).
5.1Mortality and Coronary Heart Disease Morbidity The effects of fenofibrate on coronary heart disease morbidity and mortality and non-cardiovascular mortality have not been established. The Action to Control Cardiovascular Risk in Diabetes Lipid (ACCORD Lipid) trial was a randomized placebo-controlled study of 5518 patients with type 2 diabetes mellitus on background statin therapy treated with fenofibrate. The mean duration of follow-up was 4.7 years.
Fenofibrate plus statin combination therapy showed a nonsignificant 8% relative risk reduction in the primary outcome of major adverse cardiovascular events (MACE), a composite of non-fatal myocardial infarction, nonfatal stroke, and cardiovascular disease death (hazard ratio [HR] 0.92, 95% CI 0.79-1.08) (p=0.32) as compared to statin monotherapy. In a gender subgroup analysis, the hazard ratio for MACE in men receiving combination therapy versus statin monotherapy was 0.82 (95% CI 0.69-0.99), and the hazard ratio for MACE in women receiving combination therapy versus statin monotherapy was 1.38 (95% CI 0.98-1.94) (interaction p=0.01).
The clinical significance of this subgroup finding is unclear. The Fenofibrate Intervention and Event Lowering in Diabetes (FIELD) study was a 5 year randomized, placebo-controlled study of 9795 patients with type 2 diabetes mellitus treated with fenofibrate. Fenofibrate demonstrated a non-significant 11% relative reduction in the primary outcome of coronary heart disease events (hazard ratio [HR] 0.89, 95% CI 0.75-1.05, p=0.16) and a significant 11% reduction in the secondary outcome of total cardiovascular disease events (HR 0.89 [0.80 to 0.99], p=0.04).
There was a non-significant 11% (HR 1.11 [0.95, 1.29], p=0.18) and 19% (HR 1.19 [0.90, 1.57], p=0.22) increase in total and coronary heart disease mortality, respectively, with fenofibrate as compared to placebo. Because of chemical, pharmacological, and clinical similarities between TRICOR (fenofibrate tablets), clofibrate, and gemfibrozil, the adverse findings in 4 large randomized, placebo-controlled clinical studies with these other fibrate drugs may also apply to fenofibrate. In the Coronary Drug Project, a large study of post myocardial infarction of patients treated for 5 years with clofibrate, there was no difference in mortality seen between the clofibrate group and the placebo group.
There was however, a difference in the rate of cholelithiasis and cholecystitis requiring surgery between the two groups (3% vs. 1.8%). In a study conducted by the World Health Organization (WHO), 5000 subjects without known coronary artery disease were treated with placebo or clofibrate for…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (> 2% and greater than 1% in placebo) are abnormal liver tests, increased AST, increased ALT, increased CPK, and rhinitis (6.1). To report SUSPECTED ADVERSE REACTIONS, contact Dr. Reddy’s Laboratories Inc., at 1-888-375-3784 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect rates observed in clinical practice. Adverse events reported by 2% or more of patients treated with fenofibrate and greater than placebo during double-blind, placebo-controlled trials, regardless of causality, are listed in Table 1. Adverse reactions led to discontinuation of treatment in 5% of patients treated with fenofibrate and in 3% treated with placebo.
Increases in liver function tests were the most frequent events, causing discontinuation of fenofibrate treatment in 1.6% of patients in double-blind trials. Table 1 Adverse Reactions Reported by 2% or More of Patients Treated with Fenofibrate and Greater than Placebo During the Double-Blind, Placebo-Controlled Trials Body System Adverse Reaction Fenofibrate* (N=439) Placebo (N=365) Body As A Whole Abdominal Pain 4.6% 4.4% Back Pain 3.4% 2.5% Headache 3.2% 2.7% Digestive Abnormal Liver Function Tests 7.5%** 1.4% Nausea 2.3% 1.9% Constipation 2.1% 1.4% Metabolic and Nutritional Disorders Increased AST 3.4%** 0.5% Increased ALT 3% 1.6% Increased Creatine Phosphokinase 3% 1.4% Respiratory Respiratory Disorder 6.2% 5.5% Rhinitis 2.3% 1.1% * Dosage equivalent to 130 mg fenofibrate **Significantly different from placebo Urticaria was seen in 1.1 vs.
0%, and rash in 1.4 vs. 0.8% of fenofibrate and placebo patients, respectively, in controlled trials.
6.2Postmarketing Experience The following adverse reactions have been identified during post approval use of fenofibrate: Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure: myalgia, rhabdomyolysis, pancreatitis, renal failure, muscle spasms, acute renal failure, hepatitis, cirrhosis, anemia, arthralgia, asthenia, and severely depressed HDL-cholesterol levels. Photosensitivity reactions have occurred days to months after initiation; in some of these cases, patients reported a prior photosensitivity reaction to ketoprofen.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Coumarin Anticoagulants (7.1) Immunosuppressants (7.2) Bile-Acid Binding Resins (7.3)
7.1Coumarin Anticoagulants Potentiation of coumarin-type anticoagulant effects has been observed with prolongation of the PT/INR. Caution should be exercised when coumarin anticoagulants are given in conjunction with fenofibrate. The dosage of the anticoagulants should be reduced to maintain the PT/INR at the desired level to prevent bleeding complications.
Frequent PT/INR determinations are advisable until it has been definitely determined that the PT/INR has stabilized [see Warnings and Precautions ( 5.6 ) ].
7.2Immunosuppressants Immunosuppressants such as cyclosporine and tacrolimus can produce nephrotoxicity with decrease in creatinine clearance and because renal excretion is the primary elimination route of fibrate drugs including fenofibrate, there is a risk that an interaction will lead to deterioration of renal function. The benefits and risks of using fenofibrate with immunosuppressants and other potentially nephrotoxic agents should be carefully considered, and the lowest effective dose employed.
7.3Bile-Acid Binding Resins Since bile acid binding resins may bind other drugs given concurrently, patients should take fenofibrate at least 1 hour before or 4 to 6 hours after a bile acid binding resin to avoid impeding its absorption.
7.4Colchicine Cases of myopathy, including rhabdomyolysis, have been reported with fenofibrates co-administered with colchicine, and caution should be exercised when prescribing fenofibrate with colchicine.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Geriatric use: Determine dose selection based on renal function (8.5) . Renal impairment: Avoid in patients with severe renal impairment; dose reduction required in patients with mild to moderate renal impairment (8.6) .
8.1Pregnancy Pregnancy Category: C Safety in pregnant women has not been established. There are no adequate and well controlled studies of fenofibrate in pregnant women. Fenofibrate should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
In female rats given oral dietary doses of 15, 75, and 300 mg/kg/day of fenofibrate from 15 days prior to mating through weaning, maternal toxicity was observed at 0.3 times the maximum recommended human dose (MRHD), based on body surface area comparisons; mg/m 2 . In pregnant rats given oral dietary doses of 14, 127, and 361 mg/kg/day from gestation day 6 to 15 during the period of organogenesis, adverse developmental findings were not observed at 14 mg/kg/day (less than 1 times the MRHD, based on body surface area comparisons; mg/ m 2 ).
At higher multiples of human doses, evidence of maternal toxicity was observed. In pregnant rabbits given oral gavage doses of 15, 150, and 300 mg/kg/day from gestation day 6 to 18 during the period of organogenesis and allowed to deliver, aborted litters were observed at 150 mg/kg/day (10 times the MRHD, based on body surface area comparisons; mg/ m 2 ). No developmental findings were observed at 15 mg/kg/day (at less than 1 times the MRHD, based on body surface area comparisons; mg/ m 2 ).
In pregnant rats given oral dietary doses of 15, 75, and 300 mg/kg/day from gestation day 15 through lactation day 21 (weaning), maternal toxicity was observed at less than 1 times the MRHD, based on body surface area comparisons; mg/ m 2 .
8.3Nursing Mothers Fenofibrate should not be used in nursing mothers. A decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
8.4Pediatric Use Safety and effectiveness have not been established in pediatric patients.
8.5Geriatric Use Fenofibric acid is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Fenofibric acid exposure is not influenced by age. Since elderly patients have a higher incidence of renal impairment, dose selection for the elderly should be made on the basis of renal function [see Dosage and Administration (2.5) and Clinical Pharmacology ( 12.3 ) ].
Elderly patients with normal renal function should require no dose modifications. Consider monitoring renal function in elderly patients taking fenofibrate.
8.6Renal Impairment Fenofibrate should be avoided in patients with severe renal impairment [see Contraindications (4 ) ]. Dose reduction is required in patients with mild to moderate renal impairment [see Dosage and Administration (2.4) and Clinical Pharmacology (12.3 ) ]. Monitoring renal function in patients with renal impairment is recommended.
8.7Hepatic Impairment The use of fenofibrate has not been evaluated in subjects with hepatic impairment [see Contraindications (4) and Clinical Pharmacology (12.3 ) ].
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Category: C Safety in pregnant women has not been established. There are no adequate and well controlled studies of fenofibrate in pregnant women. Fenofibrate should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
In female rats given oral dietary doses of 15, 75, and 300 mg/kg/day of fenofibrate from 15 days prior to mating through weaning, maternal toxicity was observed at 0.3 times the maximum recommended human dose (MRHD), based on body surface area comparisons; mg/m 2 . In pregnant rats given oral dietary doses of 14, 127, and 361 mg/kg/day from gestation day 6 to 15 during the period of organogenesis, adverse developmental findings were not observed at 14 mg/kg/day (less than 1 times the MRHD, based on body surface area comparisons; mg/ m 2 ).
At higher multiples of human doses, evidence of maternal toxicity was observed. In pregnant rabbits given oral gavage doses of 15, 150, and 300 mg/kg/day from gestation day 6 to 18 during the period of organogenesis and allowed to deliver, aborted litters were observed at 150 mg/kg/day (10 times the MRHD, based on body surface area comparisons; mg/ m 2 ). No developmental findings were observed at 15 mg/kg/day (at less than 1 times the MRHD, based on body surface area comparisons; mg/ m 2 ).
In pregnant rats given oral dietary doses of 15, 75, and 300 mg/kg/day from gestation day 15 through lactation day 21 (weaning), maternal toxicity was observed at less than 1 times the MRHD, based on body surface area comparisons; mg/ m 2 .
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness have not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use Fenofibric acid is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Fenofibric acid exposure is not influenced by age. Since elderly patients have a higher incidence of renal impairment, dose selection for the elderly should be made on the basis of renal function [see Dosage and Administration (2.5) and Clinical Pharmacology ( 12.3 ) ].
Elderly patients with normal renal function should require no dose modifications. Consider monitoring renal function in elderly patients taking fenofibrate.
🆘 Overdosage ▾
10 OVERDOSAGE There is no specific treatment for overdose with fenofibrate. General supportive care of the patient is indicated, including monitoring of vital signs and observation of clinical status, should an overdose occur. If indicated, elimination of unabsorbed drug should be achieved by emesis or gastric lavage; usual precautions should be observed to maintain the airway.
Because fenofibrate is highly bound to plasma proteins, hemodialysis should not be considered.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The active moiety of fenofibrate is fenofibric acid. The pharmacological effects of fenofibric acid in both animals and humans have been extensively studied through oral administration of fenofibrate. The lipid-lowering effects of fenofibric acid seen in clinical practice have been explained in vivo in transgenic mice and in vitro in human hepatocyte cultures by the activation of peroxisome proliferator activated receptor α (PPARα).
Through this mechanism, fenofibrate increases lipolysis and elimination of triglyceride-rich particles from plasma by activating lipoprotein lipase and reducing production of apoprotein C-III (an inhibitor of lipoprotein lipase activity). The resulting decrease in triglycerides produces an alteration in the size and composition of LDL from small, dense particles (which are thought to be atherogenic due to their susceptibility to oxidation) to large buoyant particles. These larger particles have a greater affinity for cholesterol receptors and are catabolized rapidly.
Activation of PPARα also induces an increase in the synthesis of apoproteins A-I, A-II and HDL-cholesterol. Fenofibrate also reduces serum uric acid levels in hyperuricemic and normal individuals by increasing the urinary excretion of uric acid.
12.2Pharmacodynamics A variety of clinical studies have demonstrated that elevated levels of total-C, DL-C, and Apo B, an LDL membrane complex, are associated with human atherosclerosis. Similarly, decreased levels of HDL-C and its transport complex, apolipoprotein A (Apo AI and Apo All) are associated with the development of atherosclerosis. Epidemiologic investigations have established that cardiovascular morbidity and mortality vary directly with the level of total-C, LDL-C, and triglycerides, and inversely with the level of HDL-C.
The independent effect of raising HDL-C or lowering TG on the risk of cardiovascular morbidity and mortality has not been determined. Fenofibric acid, the active metabolite of fenofibrate, produces reductions in total cholesterol, LDL cholesterol, apolipoprotein B, total triglycerides, and triglyceride-rich lipoprotein in treated patients. In addition, treatment with fenofibrate results in increases in high density lipoprotein (HDL) and apoproteins Apo AI and Apo AII.
12.3Pharmacokinetics Fenofibrate is a pro-drug of the active chemical moiety fenofibric acid. Fenofibrate is converted by ester hydrolysis in the body to fenofibric acid which is the active constituent measurable in the circulation. • Absorption: The absolute bioavailability of fenofibrate cannot be determined as the compound is virtually insoluble in aqueous media suitable for injection. However, fenofibrate is well absorbed from the gastrointestinal tract.
Following oral administration in healthy volunteers, approximately 60% of a single dose of radio-labeled fenofibrate appeared in urine, primarily as fenofibric acid and its glucuronate conjugate, and 25% was excreted in the feces. Peak plasma levels of fenofibric acid from fenofibrate occur within 4 to 8 hours after administration. There was less than dose-proportional increase in the systemic exposure of fenofibric acid from 43 mg and 130 mg of fenofibrate under fasting conditions.
Doses of three-capsules of 43 mg fenofibrate given concurrently were dose equivalent to single-capsule doses of 130 mg. The extent of absorption of fenofibric acid was unaffected when fenofibrate was taken either in fasted state or with a low-fat meal. However, the C max of fenofibrate increased in the presence of a low-fat meal.
T max was unaffected in the presence of a low-fat meal. In the presence of a high-fat meal, there was a 26% increase in AUC and 108% increase in C max of fenofibric acid from fenofibrate relative to fasting state. • Distribution: In healthy volunteers, steady-state plasma levels of fenofibric acid were shown to be achieved within a week of dosing and did not demonstrate accumulation across t…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The active moiety of fenofibrate is fenofibric acid. The pharmacological effects of fenofibric acid in both animals and humans have been extensively studied through oral administration of fenofibrate. The lipid-lowering effects of fenofibric acid seen in clinical practice have been explained in vivo in transgenic mice and in vitro in human hepatocyte cultures by the activation of peroxisome proliferator activated receptor α (PPARα).
Through this mechanism, fenofibrate increases lipolysis and elimination of triglyceride-rich particles from plasma by activating lipoprotein lipase and reducing production of apoprotein C-III (an inhibitor of lipoprotein lipase activity). The resulting decrease in triglycerides produces an alteration in the size and composition of LDL from small, dense particles (which are thought to be atherogenic due to their susceptibility to oxidation) to large buoyant particles. These larger particles have a greater affinity for cholesterol receptors and are catabolized rapidly.
Activation of PPARα also induces an increase in the synthesis of apoproteins A-I, A-II and HDL-cholesterol. Fenofibrate also reduces serum uric acid levels in hyperuricemic and normal individuals by increasing the urinary excretion of uric acid.
📦 How Supplied / Storage and Handling ▾
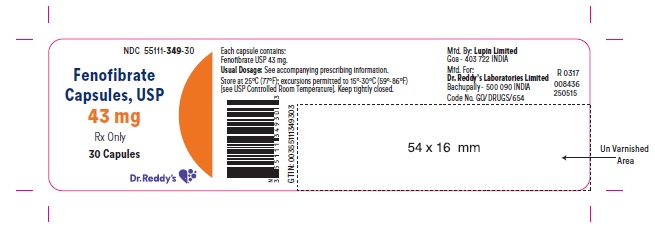
16 HOW SUPPLIED/STORAGE AND HANDLING Fenofibrate Capsules, are available in two strengths: Fenofibrate Capsules USP 43 mg are size “4” capsules with light green cap and off white body imprinted in black ink with “LU” on cap and “C21” on body containing white to off white pellets .They are supplied as follows: Bottles of 30 NDC 55111-349-30 Bottles of 100 NDC 55111-349-01 Fenofibrate Capsules USP 130 mg are size “1” capsules with dark green cap and white body imprinted in black ink with “LU” on cap and “C22” on body containing white to off white pellets.
They are supplied as follows: Bottles of 30 NDC 55111-395-30 Bottles of 90 NDC 55111-395-90 Bottles of 100 NDC 55111-395-01 Store at 25°C (77°F); excursions permitted to 15°-30°C (59°-86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Fenofibrate capsules USP, is a lipid regulating agent available as capsules for oral administration. Each capsule contains 43 mg or 130 mg of micronized fenofibrate USP. The chemical name for fenofibrate USP is 2-[4-(4-chlorobenzoyl) phenoxy]-2-methyl-propanoic acid, 1-methylethyl ester with the following structural formula: The molecular formula is C 20 H 21 O 4 CI and the molecular weight is 360.83; fenofibrate is insoluble in water.
The melting point is 79° to 82°C. Fenofibrate USP is a white or almost white crystalline powder which is sparingly soluble in methanol, ethanol and dimethylformamide. Each capsule contains the labeled amount of fenofibrate USP and the inactive ingredients: ammonio metha copolymer dispersion, D & C yellow No.10, FD & C Blue No.
2, gelatin, hypromellose, iron oxide yellow, iron oxide black, potasium hydroxide, shellac, simethicone emulsion, sodium lauryl sulphate, sugar spheres, talc, titanium dioxide and triethyl citrate. Fenofibrate capsules meets USP Dissolution Test 3.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Patients should be advised: of the potential benefits and risks of fenofibrate. not to use fenofibrate if there is a known hypersensitivity to fenofibrate capsules or fenofibric acid. that if they are taking coumarin anticoagulants, fenofibrate may increase their anticoagulant effect, and increased monitoring may be necessary. of medications that should not be taken in combination with fenofibrate. to continue to follow an appropriate lipid-modifying diet while taking fenofibrate. to take fenofibrate once daily, without regard to food, at the prescribed dose, swallowing each capsule whole. to inform their physician of all medications, supplements, and herbal preparations they are taking and any change to their medical condition.
Patients should also be advised to inform their physicians prescribing a new medication that they are taking fenofibrate. to inform their physician of any muscle pain, tenderness or weakness; onset of abdominal pain; or any other new symptoms. to return to their physician’s office for routine monitoring. R X Only Manufactured for: Dr. Reddy’s Laboratories Limited Bachupally – 500 090 INDIA Manufactured by: Lupin Limited Goa – 403 722 INDIA Revised: 1218