
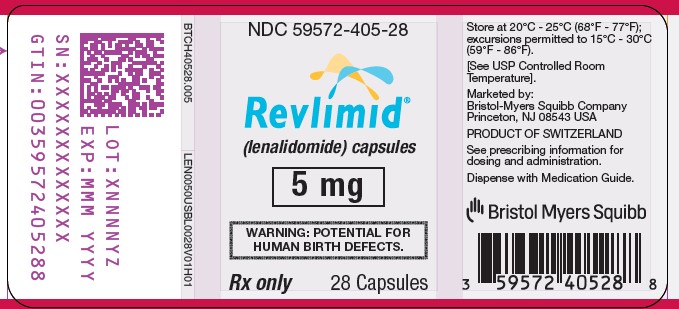
Revlimid Lenalidomide 5 mg Capsule, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Thalidomide Analog class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Lenalidomide is used to treat a certain type of myelodysplastic syndrome (a group of conditions in which the bone marrow produces blood cells that are misshapen and does not produce enough healthy blood cells). Lenalidomide is also used along with dexamethasone to treat people with multiple myeloma (a type of cancer of the bone marrow). It is also used to treat people with multiple myeloma after a hematopoietic stem-cell transplant (HSCT; procedure in which certain blood cells are removed from the body and then returned to the body). Lenalidomide is also used to treat people with mantle cell l...
Read the full MedlinePlus article ↗- Lenalidomide is the active ingredient in both Revlimid and the generic version called Lenalidomide — they are the same medicine. Depending on your diagnosis, your doctor may prescr...
- What exactly is lenalidomide used for — and do I need both Revlimid and the generic?
- Because lenalidomide can cause severe birth defects or kill an unborn baby, it's only available through a strictly controlled program called the Lenalidomide REMS program. Everyone...
- I heard this drug is really hard to get — why do I have to jump through so many hoops just to fill my prescription?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Lenalidomide — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $952.40 | $95,240.11 / 100 capsules |
| Medicare drug plans payPart D · Q2 2026 | $867.25 | $86,725.00 / 100 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lenalidomide 5 mg 00378-1936-01 | Mylan | 100 capsules | — | AB | FDA listed | — |
| Lenalidomide 5 mg 00480-1242-28 | Teva | 28 capsules | — | AB | FDA listed | — |
| Lenalidomide 5 mg 00574-1405-28 | Padagis | 28 capsules | — | AB | FDA listed | — |
| Lenalidomide 5 mg 16729-0693-09 | Accord | 28 capsules | — | AB | FDA listed | — |
| Lenalidomide 5 mg 31722-0258-01 | Camber | 100 capsules | — | AB | FDA listed | — |
| Lenalidomide 5 mg 43598-0511-01 | Dr. | 100 capsules | — | AB | FDA listed | — |
| Lenalidomide 5 mg 47781-0484-01 | Alvogen, | 100 capsules | — | AB | FDA listed | — |
| Revlimid 5 mgthis 59572-0405-00 | Celgene | 100 capsules | — | AB | FDA listed | — |
| Lenalidomide 5 mg 59651-0343-01 | Aurobindo | 100 capsules | — | AB | FDA listed | — |
| Lenalidomide 5 mg 60219-1715-01 | Amneal | 28 capsules | — | AB | FDA listed | — |
| Lenalidomide 5 mg 60505-4533-01 | Apotex | 100 capsules | — | AB | Discontinued | — |
| Lenalidomide 5 mg 63304-0042-01 | Sun | 100 capsules | — | AB | FDA listed | — |
| lenalidomide 5 mg 69097-0381-73 | Cipla | 28 capsules | — | AB | FDA listed | — |
| Lenalidomide 5 mg 70377-0050-12 | BIOCON | 100 capsules | — | AB | FDA listed | — |
| Lenalidomide 5 mg 70710-1031-01 | Zydus | 100 capsules | — | AB | FDA listed | — |
| Lenalidomide 5 mg 70771-1677-01 | Zydus | 100 capsules | — | AB | FDA listed | — |
| Lenalidomide 5 mg 73043-0039-01 | Devatis | 100 capsules | — | AB | FDA listed | — |
| lenalidomide 5 mg 76282-0697-48 | EXELAN | 28 capsules | — | AB | FDA listed | — |
| Lenalidomide 5 mg 82293-0007-10 | Novugen | 28 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8741929 ↗ | Method of use | U-1983 | Mar 8, 2028 |
| US 8741929 ↗ | Method of use | U-1983 | Mar 8, 2028 |
| US 8741929 ↗ | Method of use | U-1983 | Mar 8, 2028 |
| US 8741929 ↗ | Method of use | U-1983 | Mar 8, 2028 |
| US 8741929 ↗ | Method of use | U-1983 | Mar 8, 2028 |
| US 8741929 ↗ | Method of use | U-1983 | Mar 8, 2028 |
| US 7465800 ↗ | Drug substance | — | Apr 27, 2027 |
| US 7465800 ↗ | Drug substance | — | Apr 27, 2027 |
| US 7465800 ↗ | Drug substance | — | Apr 27, 2027 |
| US 7465800 ↗ | Drug substance | — | Apr 27, 2027 |
| US 7465800 ↗ | Drug substance | — | Apr 27, 2027 |
| US 7465800 ↗ | Drug substance | — | Apr 27, 2027 |
| Code | What it grants | Expires |
|---|---|---|
| ODE-241 | Orphan Drug Exclusivity (7-year) | May 28, 2026 |
| ODE-245 | Orphan Drug Exclusivity (7-year) | May 28, 2026 |
| ODE-241 | Orphan Drug Exclusivity (7-year) | May 28, 2026 |
| ODE-245 | Orphan Drug Exclusivity (7-year) | May 28, 2026 |
| ODE-241 | Orphan Drug Exclusivity (7-year) | May 28, 2026 |
| ODE-245 | Orphan Drug Exclusivity (7-year) | May 28, 2026 |
| ODE-241 | Orphan Drug Exclusivity (7-year) | May 28, 2026 |
| ODE-245 | Orphan Drug Exclusivity (7-year) | May 28, 2026 |
| ODE-241 | Orphan Drug Exclusivity (7-year) | May 28, 2026 |
| ODE-245 | Orphan Drug Exclusivity (7-year) | May 28, 2026 |
| ODE-241 | Orphan Drug Exclusivity (7-year) | May 28, 2026 |
| ODE-245 | Orphan Drug Exclusivity (7-year) | May 28, 2026 |
Is there a generic version of REVLIMID 5 MG CAPSULE?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 59572-0405-00 You're viewing this | 100 CAPSULE in 1 BOTTLE (59572-405-00) | 2005-12-27 | Active |
| 59572-0405-28 | 28 CAPSULE in 1 BOTTLE (59572-405-28) | 2009-03-03 | Active |
You're viewing the largest of 2 pack sizes for this product.
This pack accounts for about 15% of this product's recent Medicaid fills; most go to the 28 capsules pack. See all packs ↓
Pack size FAQ
What quantity is in NDC 59572-0405-00?
What is the difference between NDC 59572-0405-00 and NDC 59572-0405-28?
What NDC number is used to bill for this package of Revlimid Lenalidomide 5 mg Capsule?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: EMBRYO-FETAL TOXICITY, HEMATOLOGIC TOXICITY, and VENOUS and ARTERIAL THROMBOEMBOLISM Embryo-Fetal Toxicity Do not use REVLIMID during pregnancy. Lenalidomide, a thalidomide analogue, caused limb abnormalities in a developmental monkey study. Thalidomide is a known human teratogen that causes severe life-threatening human birth defects.
If lenalidomide is used during pregnancy, it may cause birth defects or embryo-fetal death. In females of reproductive potential, obtain 2 negative pregnancy tests before starting REVLIMID ® treatment. Females of reproductive potential must use 2 forms of contraception or continuously abstain from heterosexual sex during and for 4 weeks after REVLIMID treatment [see Warnings and Precautions ( 5.1 ), and Medication Guide ( 17 )].
To avoid embryo-fetal exposure to lenalidomide, REVLIMID is only available through a restricted distribution program, the Lenalidomide REMS program ( 5.2 ). Information about the Lenalidomide REMS program is available at www.lenalidomiderems.com or by calling the REMS Call Center at 1-888-423-5436. Hematologic Toxicity (Neutropenia and Thrombocytopenia) REVLIMID can cause significant neutropenia and thrombocytopenia.
Eighty percent of patients with del 5q myelodysplastic syndromes had to have a dose delay/reduction during the major study. Thirty-four percent of patients had to have a second dose delay/reduction. Grade 3 or 4 hematologic toxicity was seen in 80% of patients enrolled in the study.
Patients on therapy for del 5q myelodysplastic syndromes should have their complete blood counts monitored weekly for the first 8 weeks of therapy and at least monthly thereafter. Patients may require dose interruption and/or reduction. Patients may require use of blood product support and/or growth factors [see Dosage and Administration ( 2.2 )] .
Venous and Arterial Thromboembolism REVLIMID has demonstrated a significantly increased risk of deep vein thrombosis (DVT) and pulmonary embolism (PE), as well as risk of myocardial infarction and stroke in patients with multiple myeloma who were treated with REVLIMID and dexamethasone therapy. Monitor for and advise patients about signs and symptoms of thromboembolism. Advise patients to seek immediate medical care if they develop symptoms such as shortness of breath, chest pain, or arm or leg swelling.
Thromboprophylaxis is recommended and the choice of regimen should be based on an assessment of the patient’s underlying risks [see Warnings and Precautions ( 5.4 )]. WARNING: EMBRYO-FETAL TOXICITY, HEMATOLOGIC TOXICITY, and VENOUS and ARTERIAL THROMBOEMBOLISM See full prescribing information for complete boxed warning. EMBRYO-FETAL TOXICITY • Lenalidomide, a thalidomide analogue, caused limb abnormalities in a developmental monkey study similar to birth defects caused by thalidomide in humans.
If lenalidomide is used during pregnancy, it may cause birth defects or embryo-fetal death. • Pregnancy must be excluded before start of treatment. Prevent pregnancy during treatment by the use of two reliable methods of contraception ( 5.1 ). REVLIMID is available only through a restricted distribution program, called the Lenalidomide REMS program ( 5.2 , 17 ).
HEMATOLOGIC TOXICITY. REVLIMID can cause significant neutropenia and thrombocytopenia ( 5.3 ). VENOUS AND ARTERIAL THROMBOEMBOLISM Significantly increased risk of deep vein thrombosis (DVT) and pulmonary embolism (PE), as well as risk of myocardial infarction and stroke in patients with multiple myeloma receiving REVLIMID with dexamethasone.
Anti-thrombotic prophylaxis is recommended ( 5.4 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE REVLIMID is a thalidomide analogue indicated for the treatment of adult patients with: • Multiple myeloma (MM), in combination with dexamethasone ( 1.1 ). • MM, as maintenance following autologous hematopoietic stem cell transplantation (auto-HSCT) ( 1.1 ). • Transfusion-dependent anemia due to low- or intermediate-1-risk myelodysplastic syndromes (MDS) associated with a deletion 5q abnormality with or without additional cytogenetic abnormalities ( 1.2 ). • Mantle cell lymphoma (MCL) whose disease has relapsed or progressed after two prior therapies, one of which included bortezomib ( 1.3 ). • Previously treated follicular lymphoma (FL), in combination with a rituximab product ( 1.4 ). • Previously treated marginal zone lymphoma (MZL), in combination with a rituximab product ( 1.5 ).
Limitations of Use: • REVLIMID is not indicated and is not recommended for the treatment of patients with chronic lymphocytic leukemia (CLL) outside of controlled clinical trials ( 1.4 ).
1.1Multiple Myeloma REVLIMID in combination with dexamethasone is indicated for the treatment of adult patients with multiple myeloma (MM). REVLIMID is indicated as maintenance therapy in adult patients with MM following autologous hematopoietic stem cell transplantation (auto-HSCT).
1.2Myelodysplastic Syndromes REVLIMID is indicated for the treatment of adult patients with transfusion-dependent anemia due to low- or intermediate-1-risk myelodysplastic syndromes (MDS) associated with a deletion 5q cytogenetic abnormality with or without additional cytogenetic abnormalities.
1.3Mantle Cell Lymphoma REVLIMID is indicated for the treatment of adult patients with mantle cell lymphoma (MCL) whose disease has relapsed or progressed after two prior therapies, one of which included bortezomib.
1.4Follicular Lymphoma REVLIMID in combination with a rituximab product, is indicated for the treatment of adult patients with previously treated follicular lymphoma (FL).
1.5Marginal Zone Lymphoma REVLIMID in combination with a rituximab product, is indicated for the treatment of adult patients with previously treated marginal zone lymphoma (MZL).
1.6Limitations of Use REVLIMID is not indicated and is not recommended for the treatment of patients with CLL outside of controlled clinical trials [see Warnings and Precautions (5.5) ] .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • MM combination therapy: 25 mg once daily orally on Days 1-21 of repeated 28-day cycles. ( 2.1 ). • MM maintenance therapy following auto-HSCT: 10 mg once daily continuously on Days 1-28 of repeated 28-day cycles ( 2.1 ). • MDS: 10 mg once daily ( 2.2 ). • MCL: 25 mg once daily orally on Days 1-21 of repeated 28-day cycles ( 2.3 ). • FL or MZL: 20 mg once daily orally on Days 1-21 of repeated 28-day cycles for up to 12 cycles ( 2.4 ). • Renal impairment: Adjust starting dose based on the creatinine clearance value ( 2.6 ). • For concomitant therapy doses, see Full Prescribing Information ( 2.1 , 2.4 , 14.1 , 14.4 ).
2.1Recommended Dosage for Multiple Myeloma REVLIMID Combination Therapy The recommended starting dose of REVLIMID is 25 mg orally once daily on Days 1-21 of repeated 28-day cycles in combination with dexamethasone. Refer to Section 14.1 for specific dexamethasone dosing. For patients greater than 75 years old, the starting dose of dexamethasone may be reduced [see Clinical Studies (14.1) ] .
Treatment should be continued until disease progression or unacceptable toxicity. In patients who are not eligible for auto-HSCT, treatment should continue until disease progression or unacceptable toxicity. For patients who are auto-HSCT-eligible, hematopoietic stem cell mobilization should occur within 4 cycles of a REVLIMID-containing therapy [see Warnings and Precautions (5.12) ].
Dose Adjustments for Hematologic Toxicities During MM Treatment Dose modification guidelines, as summarized in Table 1 below, are recommended to manage Grade 3 or 4 neutropenia or thrombocytopenia or other Grade 3 or 4 toxicity judged to be related to REVLIMID. Table 1: Dose Adjustments for Hematologic Toxicities for MM Platelet counts Thrombocytopenia in MM When Platelets Recommended Course Days 1-21 of repeated 28-day cycle Fall below 30,000/mcL Interrupt REVLIMID treatment, follow CBC weekly Return to at least 30,000/mcL Resume REVLIMID at next lower dose.
Do not dose below 2.5 mg daily For each subsequent drop below 30,000/mcL Interrupt REVLIMID treatment Return to at least 30,000/mcL Resume REVLIMID at next lower dose. Do not dose below 2.5 mg daily Absolute Neutrophil counts (ANC) Neutropenia in MM When Neutrophils Recommended Course Days 1-21 of repeated 28-day cycle Fall below 1,000/mcL Interrupt REVLIMID treatment, follow CBC weekly Return to at least 1,000/mcL and neutropenia is the only toxicity Resume REVLIMID at 25 mg daily or initial starting dose Return to at least 1,000/mcL and if other toxicity Resume REVLIMID at next lower dose.
Do not dose below 2.5 mg daily For each subsequent drop below 1,000/mcL Interrupt REVLIMID treatment Return to at least 1,000/mcL Resume REVLIMID at next lower dose. Do not dose below 2.5 mg daily REVLIMID Maintenance Therapy Following Auto-HSCT Following auto-HSCT, initiate REVLIMID maintenance therapy after adequate hematologic recovery (ANC at least 1,000/mcL and/or platelet counts at least 75,000/mcL). The recommended starting dose of REVLIMID is 10 mg once daily continuously (Days 1-28 of repeated 28-day cycles) until disease progression or unacceptable toxicity.
After 3 cycles of maintenance therapy, the dose can be increased to 15 mg once daily if tolerated. Dose Adjustments for Hematologic Toxicities During MM Treatment Dose modification guidelines, as summarized in Table 2 below, are recommended to manage Grade 3 or 4 neutropenia or thrombocytopenia or other Grade 3 or 4 toxicity judged to be related to REVLIMID. Table 2: Dose Adjustments for Hematologic Toxicities for MM Platelet counts Thrombocytopenia in MM When Platelets Recommended Course Fall below 30,000/mcL Interrupt REVLIMID treatment, follow CBC weekly Return to at least 30,000/mcL Resume REVLIMID at next lower dose, continuously for Days 1-28 of repeated 28-day cycle If at the 5 mg daily dose, For a subsequent drop below 30,000/mcL Interrupt REVLIMID treatment.
Do not dose below 5 mg daily for Day 1 to 21…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Capsules: • 2.5 mg, white and blue-green opaque hard capsules imprinted "REV" on one half and "2.5 mg" on the other half in black ink • 5 mg, white opaque capsules imprinted "REV" on one half and "5 mg" on the other half in black ink • 10 mg, blue/green and pale yellow opaque capsules imprinted "REV" on one half and "10 mg" on the other half in black ink • 15 mg, powder blue and white opaque capsules imprinted "REV" on one half and "15 mg" on the other half in black ink • 20 mg, powder blue and blue-green opaque hard capsules imprinted "REV" on one half and "20 mg" on the other half in black ink • 25 mg, white opaque capsules imprinted "REV" on one half and "25 mg" on the other half in black ink Capsules: 2.5 mg, 5 mg, 10 mg, 15 mg, 20 mg, and 25 mg ( 3 ).
⛔ Contraindications ▾
4 CONTRAINDICATIONS • Pregnancy ( Boxed Warning , 4.1 , 5.1 , 8.1 ). • Demonstrated severe hypersensitivity to lenalidomide ( 4.2 , 5.9 , 5.15 ).
4.1Pregnancy REVLIMID can cause fetal harm when administered to a pregnant female. Limb abnormalities were seen in the offspring of monkeys that were dosed with lenalidomide during organogenesis. This effect was seen at all doses tested.
Due to the results of this developmental monkey study, and lenalidomide's structural similarities to thalidomide, a known human teratogen, lenalidomide is contraindicated in females who are pregnant [see Boxed Warning ]. If this drug is used during pregnancy or if the patient becomes pregnant while taking this drug, the patient should be apprised of the potential risk to a fetus [see Warnings and Precautions (5.1 , 5.2) , Use in Special Populations (8.1 , 8.3) ] .
4.2Severe Hypersensitivity Reactions REVLIMID is contraindicated in patients who have demonstrated severe hypersensitivity (e.g., angioedema, Stevens-Johnson syndrome, toxic epidermal necrolysis) to lenalidomide [see Warnings and Precautions (5.9 , 5.15 )].
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Increased Mortality: serious and fatal cardiac adverse reactions occurred in patients with CLL treated with REVLIMID ( 5.5 ). • Second Primary Malignancies (SPM): Higher incidences of SPM were observed in controlled trials of patients with MM receiving REVLIMID ( 5.6 ). • Increased Mortality: Observed in patients with MM when pembrolizumab was added to dexamethasone and a thalidomide analogue ( 5.7 ). • Hepatotoxicity: Hepatic failure including fatalities; monitor liver function. Stop REVLIMID and evaluate if hepatotoxicity is suspected ( 5.8 ). • Severe Cutaneous Reactions: Discontinue REVLIMID for severe reactions ( 5.9 ). • Tumor lysis syndrome (TLS) including fatalities: Monitor patients at risk of TLS (i.e., those with high tumor burden) and take appropriate precautions ( 5.10 ). • Tumor flare reaction: Serious tumor flare reactions, including fatal reactions, have occurred during investigational use of REVLIMID for chronic lymphocytic leukemia and lymphoma ( 5.11 ). • Impaired Stem Cell mobilization: A decrease in the number of CD34+ cells collected after treatment (> 4 cycles) with REVLIMID has been reported.
Consider early referral to transplant center ( 5.12 ). • Early mortality in MCL: Higher rate of early deaths have occurred in patients with MCL ( 5.14 ). • Hypersensitivity: Monitor patients for potential hypersensitivity. Discontinue REVLIMID for angioedema and anaphylaxis ( 5.15 ).
5.1Embryo-Fetal Toxicity REVLIMID is a thalidomide analogue and is contraindicated for use during pregnancy. Thalidomide is a known human teratogen that causes life-threatening human birth defects or embryo-fetal death [see Use in Specific Populations (8.1) ]. An embryo-fetal development study in monkeys indicates that lenalidomide produced malformations in the offspring of female monkeys who received the drug during pregnancy, similar to birth defects observed in humans following exposure to thalidomide during pregnancy.
REVLIMID is only available through the Lenalidomide REMS program [see Warnings and Precautions (5.2) ] . Females of Reproductive Potential Females of reproductive potential must avoid pregnancy for at least 4 weeks before beginning REVLIMID therapy, during therapy, during dose interruptions and for at least 4 weeks after completing therapy. Females must commit either to abstain continuously from heterosexual sexual intercourse or to use two methods of reliable birth control, beginning 4 weeks prior to initiating treatment with REVLIMID, during therapy, during dose interruptions and continuing for 4 weeks following discontinuation of REVLIMID therapy.
Two negative pregnancy tests must be obtained prior to initiating therapy. The first test should be performed within 10-14 days and the second test within 24 hours prior to prescribing REVLIMID therapy and then weekly during the first month, then monthly thereafter in females with regular menstrual cycles or every 2 weeks in females with irregular menstrual cycles [see Use in Specific Populations (8.3) ] . Males Lenalidomide is present in the semen of patients receiving the drug.
Therefore, males must always use a latex or synthetic condom during any sexual contact with females of reproductive potential while taking REVLIMID and for up to 4 weeks after discontinuing REVLIMID, even if they have undergone a successful vasectomy. Male patients taking REVLIMID must not donate sperm and for up to 4 weeks after discontinuing REVLIMID [see Use in Specific Populations (8.3) ]. Blood Donation Patients must not donate blood during treatment with REVLIMID and for 4 weeks following discontinuation of the drug because the blood might be given to a pregnant female patient whose fetus must not be exposed to REVLIMID.
5.2Lenalidomide REMS Program Because of the embryo-fetal risk [see Warnings and Precautions (5.1) ] , REVLIMID is available only through a restricted program under a Risk Evaluation and Mitigation Strategy (REMS), the Lenalidomide REMS program…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described in detail in other sections of the prescribing information: o Embryo-Fetal Toxicity [see Boxed Warning , Warnings and Precautions (5.1 , 5.2) ] o Hematologic Toxicity [see Boxed Warning , Warnings and Precautions (5.3) ] o Venous and Arterial Thromboembolism [see Boxed Warning , Warnings and Precautions (5.4) ] o Increased Mortality in Patients with CLL [see Warnings and Precautions (5.5) ] o Second Primary Malignancies [see Warnings and Precautions (5.6) ] o Increased Mortality in Patients with MM When Pembrolizumab Is Added to a Thalidomide Analogue and Dexamethasone [see Warnings and Precautions (5.7) ] o Hepatotoxicity [see Warnings and Precautions (5.8) ] o Severe Cutaneous Reactions [see Warnings and Precautions (5.9) ] o Tumor Lysis Syndrome [see Warnings and Precautions (5.10) ] o Tumor Flare Reactions [see Warnings and Precautions (5.11) ] o Impaired Stem Cell Mobilization [see Warnings and Precautions (5.12) ] o Thyroid Disorders [see Warnings and Precautions (5.13) ] o Early Mortality in Patients with MCL [see Warnings and Precautions (5.14) ] o Hypersensitivity [see Warnings and Precautions (5.15) ] • MM: Most common adverse reactions (≥20%) include diarrhea, fatigue, anemia, constipation, neutropenia, leukopenia, peripheral edema, insomnia, muscle cramp/spasms, abdominal pain, back pain, nausea, asthenia, pyrexia, upper respiratory tract infection, bronchitis, nasopharyngitis, gastroenteritis, cough, rash, dyspnea, dizziness, decreased appetite, thrombocytopenia, and tremor ( 6.1 ). • MDS: Most common adverse reactions (>15%) include thrombocytopenia, neutropenia, diarrhea, pruritus, rash, fatigue, constipation, nausea, nasopharyngitis, arthralgia, pyrexia, back pain, peripheral edema, cough, dizziness, headache, muscle cramp, dyspnea, pharyngitis, and epistaxis ( 6.1 ). • Non-Hodgkin's Lymphoma (NHL: MCL, FL or MZL): Most common adverse reactions (≥15%) included neutropenia, thrombocytopenia, anemia, leukopenia, diarrhea, constipation, nausea, fatigue, pyrexia, cough, upper respiratory tract infection, and rash ( 6.1 ).
To report SUSPECTED ADVERSE REACTIONS, contact Bristol-Myers Squibb at 1-800-721-5072 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Newly Diagnosed MM – REVLIMID Combination Therapy: Data were evaluated from 1613 patients in a large phase 3 study who received at least one dose of REVLIMID with low dose dexamethasone (Rd) given for 2 different durations of time (i.e., until progressive disease [Arm Rd Continuous; N=532] or for up to eighteen 28-day cycles [72 weeks, Arm Rd18; N=540] or who received melphalan, prednisone and thalidomide (Arm MPT; N=541) for a maximum of twelve 42-day cycles (72 weeks).
The median treatment duration in the Rd Continuous arm was 80.2 weeks (range 0.7 to 246.7) or 18.4 months (range 0.16 to 56.7). In general, the most frequently reported adverse reactions were comparable in Arm Rd Continuous and Arm Rd18, and included diarrhea, anemia, constipation, peripheral edema, neutropenia, fatigue, back pain, nausea, asthenia, and insomnia. The most frequently reported Grade 3 or 4 reactions included neutropenia, anemia, thrombocytopenia, pneumonia, asthenia, fatigue, back pain, hypokalemia, rash, cataract, lymphopenia, dyspnea, DVT, hyperglycemia, and leukopenia.
The highest frequency of infections occurred in Arm Rd Continuous (75%) compared to Arm MPT (56%). There were more grade 3 and 4 and serious adverse reactions of infection in Arm Rd Continuous than either Arm MPT or Rd18. In the Rd Continuous arm, the most common adverse reactions leading to dose interruption of REVLIMID were infection ev…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Digoxin: Monitor digoxin plasma levels periodically due to increased C max and AUC with concomitant REVLIMID therapy ( 7.1 ). • Concomitant use of erythropoietin stimulating agents or estrogen containing therapies with REVLIMID may increase the risk of thrombosis ( 7.2 ).
7.1Digoxin When digoxin was co-administered with multiple doses of REVLIMID (10 mg/day) the digoxin C max and AUC inf were increased by 14%. Periodically monitor digoxin plasma levels, in accordance with clinical judgment and based on standard clinical practice in patients receiving this medication, during administration of REVLIMID.
7.2Concomitant Therapies That May Increase the Risk of Thrombosis Erythropoietic agents, or other agents that may increase the risk of thrombosis, such as estrogen containing therapies, should be used with caution after making a benefit-risk assessment in patients receiving REVLIMID [see Warnings and Precautions (5.4) ] .
7.3Warfarin Co-administration of multiple doses of REVLIMID (10 mg/day) with a single dose of warfarin (25 mg) had no effect on the pharmacokinetics of lenalidomide or R- and S-warfarin. Expected changes in laboratory assessments of PT and INR were observed after warfarin administration, but these changes were not affected by concomitant REVLIMID administration. It is not known whether there is an interaction between dexamethasone and warfarin.
Close monitoring of PT and INR is recommended in patients with MM taking concomitant warfarin.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Lactation: Advise not to breastfeed ( 8.2 ).
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in females exposed to REVLIMID during pregnancy as well as female partners of male patients who are exposed to REVLIMID. This registry is also used to understand the root cause for the pregnancy. Report any suspected fetal exposure to REVLIMID to the FDA via the MedWatch program at 1-800-FDA-1088 and also to the REMS Call Center at 1-888-423-5436.
Risk Summary Based on the mechanism of action [see Clinical Pharmacology (12.1) ] and findings from animal studies [see Data] , REVLIMID can cause embryo-fetal harm when administered to a pregnant female and is contraindicated during pregnancy [see Boxed Warning , Contraindications (4.1) , and Use in Specific Populations (5.1) ] . REVLIMID is a thalidomide analogue. Thalidomide is a human teratogen, inducing a high frequency of severe and life-threatening birth defects such as amelia (absence of limbs), phocomelia (short limbs), hypoplasticity of the bones, absence of bones, external ear abnormalities (including anotia, micropinna, small or absent external auditory canals), facial palsy, eye abnormalities (anophthalmos, microphthalmos), and congenital heart defects.
Alimentary tract, urinary tract, and genital malformations have also been documented and mortality at or shortly after birth has been reported in about 40% of infants. Lenalidomide caused thalidomide-type limb defects in monkey offspring. Lenalidomide crossed the placenta after administration to pregnant rabbits and pregnant rats [see Data ] .
If this drug is used during pregnancy, or if the patient becomes pregnant while taking this drug, the patient should be apprised of the potential risk to a fetus. If pregnancy does occur during treatment, immediately discontinue the drug. Under these conditions, refer patient to an obstetrician/gynecologist experienced in reproductive toxicity for further evaluation and counseling.
Report any suspected fetal exposure to REVLIMID to the FDA via the MedWatch program at 1-800-FDA-1088 and also to the REMS Call Center at 1-888-423-5436. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
The estimated background risk in the U.S. general population of major birth defects is 2%-4% and of miscarriage is 15%-20% of clinically recognized pregnancies. Data Animal data In an embryo-fetal developmental toxicity study in monkeys, teratogenicity, including thalidomide-like limb defects, occurred in offspring when pregnant monkeys received oral lenalidomide during organogenesis. Exposure (AUC) in monkeys at the lowest dose was 0.17 times the human exposure at the maximum recommended human dose (MRHD) of 25 mg.
Similar studies in pregnant rabbits and rats at 20 times and 200 times the MRHD respectively, produced embryo lethality in rabbits and no adverse reproductive effects in rats. In a pre- and post-natal development study in rats, animals received lenalidomide from organogenesis through lactation. The study revealed a few adverse effects on the offspring of female rats treated with lenalidomide at doses up to 500 mg/kg (approximately 200 times the human dose of 25 mg based on body surface area).
The male offspring exhibited slightly delayed sexual maturation and the female offspring had slightly lower body weight gains during gestation when bred to male offspring. As with thalidomide, the rat model may not adequately address the full spectrum of potential human embryo-fetal developmental effects for lenalidomide. Following daily oral administration of lenalidomide from Gestation Day 7 through Gestation Day 20 in pregnant rabbits, fetal plasma lenalidomide concentrations were approximately 20-40% of the maternal C max.
Following a single oral dose to pregnant rats…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in females exposed to REVLIMID during pregnancy as well as female partners of male patients who are exposed to REVLIMID. This registry is also used to understand the root cause for the pregnancy. Report any suspected fetal exposure to REVLIMID to the FDA via the MedWatch program at 1-800-FDA-1088 and also to the REMS Call Center at 1-888-423-5436.
Risk Summary Based on the mechanism of action [see Clinical Pharmacology (12.1) ] and findings from animal studies [see Data] , REVLIMID can cause embryo-fetal harm when administered to a pregnant female and is contraindicated during pregnancy [see Boxed Warning , Contraindications (4.1) , and Use in Specific Populations (5.1) ] . REVLIMID is a thalidomide analogue. Thalidomide is a human teratogen, inducing a high frequency of severe and life-threatening birth defects such as amelia (absence of limbs), phocomelia (short limbs), hypoplasticity of the bones, absence of bones, external ear abnormalities (including anotia, micropinna, small or absent external auditory canals), facial palsy, eye abnormalities (anophthalmos, microphthalmos), and congenital heart defects.
Alimentary tract, urinary tract, and genital malformations have also been documented and mortality at or shortly after birth has been reported in about 40% of infants. Lenalidomide caused thalidomide-type limb defects in monkey offspring. Lenalidomide crossed the placenta after administration to pregnant rabbits and pregnant rats [see Data ] .
If this drug is used during pregnancy, or if the patient becomes pregnant while taking this drug, the patient should be apprised of the potential risk to a fetus. If pregnancy does occur during treatment, immediately discontinue the drug. Under these conditions, refer patient to an obstetrician/gynecologist experienced in reproductive toxicity for further evaluation and counseling.
Report any suspected fetal exposure to REVLIMID to the FDA via the MedWatch program at 1-800-FDA-1088 and also to the REMS Call Center at 1-888-423-5436. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
The estimated background risk in the U.S. general population of major birth defects is 2%-4% and of miscarriage is 15%-20% of clinically recognized pregnancies. Data Animal data In an embryo-fetal developmental toxicity study in monkeys, teratogenicity, including thalidomide-like limb defects, occurred in offspring when pregnant monkeys received oral lenalidomide during organogenesis. Exposure (AUC) in monkeys at the lowest dose was 0.17 times the human exposure at the maximum recommended human dose (MRHD) of 25 mg.
Similar studies in pregnant rabbits and rats at 20 times and 200 times the MRHD respectively, produced embryo lethality in rabbits and no adverse reproductive effects in rats. In a pre- and post-natal development study in rats, animals received lenalidomide from organogenesis through lactation. The study revealed a few adverse effects on the offspring of female rats treated with lenalidomide at doses up to 500 mg/kg (approximately 200 times the human dose of 25 mg based on body surface area).
The male offspring exhibited slightly delayed sexual maturation and the female offspring had slightly lower body weight gains during gestation when bred to male offspring. As with thalidomide, the rat model may not adequately address the full spectrum of potential human embryo-fetal developmental effects for lenalidomide. Following daily oral administration of lenalidomide from Gestation Day 7 through Gestation Day 20 in pregnant rabbits, fetal plasma lenalidomide concentrations were approximately 20-40% of the maternal C max.
Following a single oral dose to pregnant rats, lenalidomide was detected in fetal plasma and tissues; concentrations of ra…
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness have not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use MM In Combination : Overall, of the 1613 patients in the NDMM study who received study treatment, 94% (1521 /1613) were 65 years of age or older, while 35% (561/1613) were over 75 years of age. The percentage of patients over age 75 was similar between study arms (Rd Continuous: 33%; Rd18: 34%; MPT: 33%). Overall, across all treatment arms, the frequency in most of the adverse reaction categories (eg, all adverse reactions, grade 3/4 adverse reactions, serious adverse reactions) was higher in older (> 75 years of age) than in younger (≤ 75 years of age) subjects.
Grade 3 or 4 adverse reactions in the General Disorders and Administration Site Conditions body system were consistently reported at a higher frequency (with a difference of at least 5%) in older subjects than in younger subjects across all treatment arms. Grade 3 or 4 adverse reactions in the Infections and Infestations, Cardiac Disorders (including cardiac failure and congestive cardiac failure), Skin and Subcutaneous Tissue Disorders, and Renal and Urinary Disorders (including renal failure) body systems were also reported slightly, but consistently, more frequently (<5% difference), in older subjects than in younger subjects across all treatment arms.
For other body systems (e.g., Blood and Lymphatic System Disorders, Infections and Infestations, Cardiac Disorders, Vascular Disorders), there was a less consistent trend for increased frequency of grade 3/4 adverse reactions in older vs younger subjects across all treatment arms Serious adverse reactions were generally reported at a higher frequency in the older subjects than in the younger subjects across all treatment arms. MM Maintenance Therapy : Overall, 10% (106/1018) of patients were 65 years of age or older, while no patients were over 75 years of age.
Grade 3 or 4 adverse reactions were higher in the REVLIMID arm (more than 5% higher) in the patients 65 years of age or older versus younger patients. The frequency of Grade 3 or 4 adverse reactions in the Blood and Lymphatic System Disorders were higher in the REVLIMID arm (more than 5% higher) in the patients 65 years of age or older versus younger patients. There were not a sufficient number of patients 65 years of age or older in REVLIMID maintenance studies who experienced either a serious adverse reaction, or discontinued therapy due to an adverse reaction to determine whether elderly patients respond relative to safety differently from younger patients.
MM After At Least One Prior Therapy : Of the 703 MM patients who received study treatment in Studies 1 and 2, 45% were age 65 or over while 12% of patients were age 75 and over. The percentage of patients age 65 or over was not significantly different between the REVLIMID/dexamethasone and placebo/dexamethasone groups. Of the 353 patients who received REVLIMID/dexamethasone, 46% were age 65 and over.
In both studies, patients > 65 years of age were more likely than patients ≤ 65 years of age to experience DVT, pulmonary embolism, atrial fibrillation, and renal failure following use of REVLIMID. No differences in efficacy were observed between patients over 65 years of age and younger patients. Of the 148 patients with del 5q MDS enrolled in the major study, 38% were age 65 and over, while 33% were age 75 and over.
Although the overall frequency of adverse reactions (100%) was the same in patients over 65 years of age as in younger patients, the frequency of serious adverse reactions was higher in patients over 65 years of age than in younger patients (54% vs. 33%). A greater proportion of patients over 65 years of age discontinued from the clinical studies because of adverse reactions than the proportion of younger patients (27% vs.
16%). No differences in efficacy were observed between patients over 65 years of age and younger patients. Of the 134 patients with MCL enrolled in the MCL trial, 63% were age 65 and over, while 22% of patients were age 75 and over.
The overall frequency of…
🆘 Overdosage ▾
10 OVERDOSAGE There is no specific experience in the management of REVLIMID overdose in patients with MM, MDS, MCL, FL, or MZL. In dose-ranging studies in healthy subjects, some were exposed to up to 200 mg (administered 100 mg BID) and in single-dose studies, some subjects were exposed to up to 400 mg. Pruritus, urticaria, rash, and elevated liver transaminases were the primary reported AEs.
In clinical trials, the dose-limiting toxicity was neutropenia and thrombocytopenia.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Lenalidomide is an analogue of thalidomide with immunomodulatory, antiangiogenic, and antineoplastic properties. Cellular activities of lenalidomide are mediated through its target cereblon, a component of a cullin ring E3 ubiquitin ligase enzyme complex. In vitro, in the presence of drug, substrate proteins (including Aiolos, Ikaros, and CK1α) are targeted for ubiquitination and subsequent degradation leading to direct cytotoxic and immunomodulatory effects.
Lenalidomide inhibits proliferation and induces apoptosis of certain hematopoietic tumor cells including MM, mantle cell lymphoma, and del (5q) myelodysplastic syndromes, follicular lymphoma and marginal zone lymphoma in vitro . Lenalidomide causes a delay in tumor growth in some in vivo nonclinical hematopoietic tumor models including MM. Immunomodulatory properties of lenalidomide include increased number and activation of T cells and natural killer (NK) cells leading to direct and enhanced antibody-dependent cell-mediated cytotoxicity (ADCC) via increased secretion of interleukin-2 and interferon-gamma, increased numbers of NKT cells, and inhibition of pro-inflammatory cytokines (e.g., TNF-α and IL-6) by monocytes.
In MM cells, the combination of lenalidomide and dexamethasone synergizes the inhibition of cell proliferation and the induction of apoptosis. The combination of lenalidomide and rituximab increases ADCC and direct tumor apoptosis in follicular lymphoma cells and increases ADCC in marginal zone lymphoma cells compared to rituximab alone in vitro .
12.2Pharmacodynamics Cardiac Electrophysiology The effect of lenalidomide on the QTc interval was evaluated in 60 healthy male subjects in a thorough QT study. At a dose two times the maximum recommended dose, lenalidomide did not prolong the QTc interval. The largest upper bound of the two-sided 90% CI for the mean differences between lenalidomide and placebo was below 10 ms.
12.3Pharmacokinetics Absorption Following single and multiple doses of REVLIMID in patients with MM or MDS, the maximum plasma concentrations occurred between 0.5 and 6 hours post-dose. The single and multiple dose pharmacokinetic disposition of lenalidomide is linear with AUC and C max values increasing proportionally with dose. Multiple doses of REVLIMID at the recommended dosage does not result in drug accumulation.
Administration of a single 25 mg dose of REVLIMID with a high-fat meal in healthy subjects reduces the extent of absorption, with an approximate 20% decrease in AUC and 50% decrease in C max . In the trials where the efficacy and safety were established for REVLIMID, the drug was administered without regard to food intake. REVLIMID can be administered with or without food.
The oral absorption rate of lenalidomide in patients with MCL is similar to that observed in patients with MM or MDS. Distribution In vitro [ 14 C]-lenalidomide binding to plasma proteins is approximately 30%. Lenalidomide is present in semen at 2 hours (1379 ng/ejaculate) and 24 hours (35 ng/ejaculate) after the administration of REVLIMID 25 mg daily.
Elimination The mean half-life of lenalidomide is 3 hours in healthy subjects and 3 to 5 hours in patients with MM, MDS or MCL. Metabolism Lenalidomide undergoes limited metabolism. Unchanged lenalidomide is the predominant circulating component in humans.
Two identified metabolites are 5-hydroxy-lenalidomide and N-acetyl-lenalidomide; each constitutes less than 5% of parent levels in circulation. Excretion Elimination is primarily renal. Following a single oral administration of [ 14 C]-lenalidomide 25 mg to healthy subjects, approximately 90% and 4% of the radioactive dose was eliminated within ten days in urine and feces, respectively.
Approximately 82% of the radioactive dose was excreted as lenalidomide in the urine within 24 hours. Hydroxy-lenalidomide and N-acetyl-lenalidomide represented 4.6% and 1.8% of the excreted dose, respectively. The renal clear…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Lenalidomide is an analogue of thalidomide with immunomodulatory, antiangiogenic, and antineoplastic properties. Cellular activities of lenalidomide are mediated through its target cereblon, a component of a cullin ring E3 ubiquitin ligase enzyme complex. In vitro, in the presence of drug, substrate proteins (including Aiolos, Ikaros, and CK1α) are targeted for ubiquitination and subsequent degradation leading to direct cytotoxic and immunomodulatory effects.
Lenalidomide inhibits proliferation and induces apoptosis of certain hematopoietic tumor cells including MM, mantle cell lymphoma, and del (5q) myelodysplastic syndromes, follicular lymphoma and marginal zone lymphoma in vitro . Lenalidomide causes a delay in tumor growth in some in vivo nonclinical hematopoietic tumor models including MM. Immunomodulatory properties of lenalidomide include increased number and activation of T cells and natural killer (NK) cells leading to direct and enhanced antibody-dependent cell-mediated cytotoxicity (ADCC) via increased secretion of interleukin-2 and interferon-gamma, increased numbers of NKT cells, and inhibition of pro-inflammatory cytokines (e.g., TNF-α and IL-6) by monocytes.
In MM cells, the combination of lenalidomide and dexamethasone synergizes the inhibition of cell proliferation and the induction of apoptosis. The combination of lenalidomide and rituximab increases ADCC and direct tumor apoptosis in follicular lymphoma cells and increases ADCC in marginal zone lymphoma cells compared to rituximab alone in vitro .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied White and blue-green opaque hard capsules imprinted "REV" on one half and "2.5 mg" on the other half in black ink: 2.5 mg bottles of 28 (NDC 59572-402-28) 2.5 mg bottles of 100 (NDC 59572-402-00) White opaque capsules imprinted "REV" on one half and "5 mg" on the other half in black ink: 5 mg bottles of 28 (NDC 59572-405-28) 5 mg bottles of 100 (NDC 59572-405-00) Blue/green and pale yellow opaque capsules imprinted "REV" on one half and "10 mg" on the other half in black ink: 10 mg bottles of 28 (NDC 59572-410-28) 10 mg bottles of 100 (NDC 59572-410-00) Powder blue and white opaque capsules imprinted "REV" on one half and "15 mg" on the other half in black ink: 15 mg bottles of 21 (NDC 59572-415-21) 15 mg bottles of 100 (NDC 59572-415-00) Powder blue and blue-green opaque hard capsules imprinted "REV" on one half and "20 mg" on the other half in black ink.
20 mg bottles of 21 (NDC 59572-420-21) 20 mg bottles of 100 (NDC 59572-420-00) White opaque capsules imprinted "REV" on one half and "25 mg" on the other half in black ink: 25 mg bottles of 21 (NDC 59572-425-21) 25 mg bottles of 100 (NDC 59572-425-00)
16.2Storage Store at 20°C - 25°C (68°F - 77°F); excursions permitted to 15°C - 30°C (59°F - 86°F) [See USP Controlled Room Temperature].
16.3Handling and Disposal Care should be exercised in the handling of REVLIMID. REVLIMID capsules should not be opened or broken. If powder from REVLIMID contacts the skin, wash the skin immediately and thoroughly with soap and water.
If REVLIMID contacts the mucous membranes, flush thoroughly with water. Procedures for the proper handling and disposal of anticancer drugs should be considered. Several guidelines on the subject have been published.
1 Dispense no more than a 28-day supply.
📦 Storage and Handling ▾
16.2Storage Store at 20°C - 25°C (68°F - 77°F); excursions permitted to 15°C - 30°C (59°F - 86°F) [See USP Controlled Room Temperature].
16.3Handling and Disposal Care should be exercised in the handling of REVLIMID. REVLIMID capsules should not be opened or broken. If powder from REVLIMID contacts the skin, wash the skin immediately and thoroughly with soap and water.
If REVLIMID contacts the mucous membranes, flush thoroughly with water. Procedures for the proper handling and disposal of anticancer drugs should be considered. Several guidelines on the subject have been published.
1 Dispense no more than a 28-day supply.
📋 Description ▾
11 DESCRIPTION REVLIMID, a thalidomide analogue, is an immunomodulatory agent with antiangiogenic and antineoplastic properties. The chemical name is 3-(4-amino-1-oxo 1,3-dihydro-2 H -isoindol-2-yl) piperidine-2,6-dione and it has the following chemical structure: 3-(4-amino-1-oxo 1,3-dihydro-2 H -isoindol-2-yl) piperidine-2,6-dione The empirical formula for lenalidomide is C 13 H 13 N 3 O 3, and the gram molecular weight is 259.3. Lenalidomide is an off-white to pale-yellow solid powder.
It is soluble in organic solvent/water mixtures, and buffered aqueous solvents. Lenalidomide is more soluble in organic solvents and low pH solutions. Solubility was significantly lower in less acidic buffers, ranging from about 0.4 to 0.5 mg/ml.
Lenalidomide has an asymmetric carbon atom and can exist as the optically active forms S(-) and R(+), and is produced as a racemic mixture with a net optical rotation of zero. REVLIMID is available in 2.5 mg, 5 mg, 10 mg, 15 mg, 20 mg and 25 mg capsules for oral administration. Each capsule contains lenalidomide as the active ingredient and the following inactive ingredients: lactose anhydrous, microcrystalline cellulose, croscarmellose sodium, and magnesium stearate.
The 5 mg and 25 mg capsule shell contains gelatin, titanium dioxide and black ink. The 2.5 mg and 10 mg capsule shell contains gelatin, FD&C blue #2, yellow iron oxide, titanium dioxide and black ink. The 15 mg capsule shell contains gelatin, FD&C blue #2, titanium dioxide and black ink.
The 20 mg capsule shell contains gelatin, FD&C blue #2, yellow iron oxide, titanium dioxide and black ink. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved Patient labeling (Medication Guide) Embryo-Fetal Toxicity Advise patients that REVLIMID is contraindicated in pregnancy [see Boxed Warning and Contraindications (4.1) ]. REVLIMID is a thalidomide analogue and can cause serious birth defects or death to a developing baby [see Warnings and Precautions (5.1) and Use in Specific Populations (8.1) ] . • Advise females of reproductive potential that they must avoid pregnancy while taking REVLIMID and for at least 4 weeks after completing therapy. • Initiate REVLIMID treatment in females of reproductive potential only following a negative pregnancy test. • Advise females of reproductive potential of the importance of monthly pregnancy tests and the need to use 2 different forms of contraception including at least 1 highly effective form, simultaneously during REVLIMID therapy, during dose interruption and for 4 weeks after she has completely finished taking REVLIMID.
Highly effective forms of contraception other than tubal ligation include IUD and hormonal (birth control pills, injections, patch or implants) and a partner's vasectomy. Additional effective contraceptive methods include latex or synthetic condom, diaphragm and cervical cap. • Instruct patient to immediately stop taking REVLIMID and contact her healthcare provider if she becomes pregnant while taking this drug, if she misses her menstrual period, or experiences unusual menstrual bleeding, if she stops taking birth control, or if she thinks FOR ANY REASON that she may be pregnant. • Advise patient that if her healthcare provider is not available, she should call the REMS Call Center at 1-888-423-5436 [see Warnings and Precautions (5.1) and Use in Specific Populations (8.3) ]. • Advise males to always use a latex or synthetic condom during any sexual contact with females of reproductive potential while taking REVLIMID and for up to 4 weeks after discontinuing REVLIMID, even if they have undergone a successful vasectomy. • Advise male patients taking REVLIMID that they must not donate sperm and for up to 4 weeks after discontinuation of REVLIMID [see Warnings and Precautions (5.1) and Use in Specific Populations (8.3) ] . • All patients must be instructed to not donate blood while taking REVLIMID, during dose interruptions and for 4 weeks following discontinuation of REVLIMID [see Warnings and Precautions (5.1) ] .
Lenalidomide REMS program Because of the risk of embryo-fetal toxicity, REVLIMID is only available through a restricted program called the Lenalidomide REMS program [see Warnings and Precautions (5.2) ] . • Patients must sign a Patient-Physician agreement form and comply with the requirements to receive REVLIMID. In particular, females of reproductive potential must comply with the pregnancy testing, contraception requirements and participate in monthly telephone surveys. Males must comply with the contraception requirements [see Use in Specific Populations (8.3) ] . • REVLIMID is available only from pharmacies that are certified in the Lenalidomide REMS program.
Provide patients with the telephone number and website for information on how to obtain the product. Pregnancy Exposure Registry Inform females there is a Pregnancy Exposure Registry that monitors pregnancy outcomes in females exposed to REVLIMID during pregnancy and that they can contact the Pregnancy Exposure Registry by calling 1-888-423-5436 [see Use in Specific Populations (8.1) ] . Hematologic Toxicity Inform patients that REVLIMID is associated with significant neutropenia and thrombocytopenia [see Boxed Warning and Warnings and Precautions (5.3) ] .
Venous and Arterial Thromboembolism Inform patients of the risk of thrombosis including DVT, PE, MI, and stroke and to report immediately any signs and symptoms suggestive of these events for evaluation [see Boxed Warning and Warnings and Precautions (5.4) ] . Increased Mortality in Patients with CLL Inform patients that RE…
💬 Medication Guide ▾
Medication Guide REVLIMID ® (rev-li-mid) (lenalidomide) capsules What is the most important information I should know about REVLIMID? Before you begin taking REVLIMID, you must read and agree to all of the instructions in the Lenalidomide REMS program. For more information, call 1-888-423-5436 or go to www.lenalidomiderems.com.
Before prescribing REVLIMID, your healthcare provider will explain the Lenalidomide REMS program to you and have you sign the Patient-Physician Agreement Form. REVLIMID may cause serious side effects including: • Possible birth defects (deformed babies) or death of an unborn baby . Females who are pregnant or who plan to become pregnant must not take REVLIMID.
REVLIMID is similar to the medicine thalidomide. We know thalidomide can cause severe life-threatening birth defects. REVLIMID has not been tested in pregnant females.
REVLIMID has harmed unborn animals in animal testing. Females must not get pregnant: o For at least 4 weeks before starting REVLIMID o While taking REVLIMID o During any breaks (interruptions) in your treatment with REVLIMID o For at least 4 weeks after stopping REVLIMID Females who can become pregnant: o Will have pregnancy tests weekly for 4 weeks, then every 4 weeks if your menstrual cycle is regular, or every 2 weeks if your menstrual cycle is irregular. o If you miss your period or have unusual bleeding, you will need to have a pregnancy test and receive counseling. o Must agree to use two acceptable forms of birth control at the same time, for at least 4 weeks before, while taking, during any breaks (interruptions) in your treatment, and for at least 4 weeks after stopping REVLIMID. o Talk with your healthcare provider to find out about options for acceptable forms of birth control that you may use to prevent pregnancy before, during, and after treatment with REVLIMID. o If you had unprotected sex or if you think your birth control has failed, stop taking REVLIMID immediately and call your healthcare provider right away.
If you become pregnant while taking REVLIMID, stop taking it right away and call your healthcare provider. If your healthcare provider is not available, you can call the REMS Call Center at 1-888-423-5436. Healthcare providers and patients should report all cases of pregnancy to: o FDA MedWatch at 1-800-FDA-1088, and o REMS Call Center at 1-888-423-5436 There is a pregnancy exposure registry that monitors the outcomes of females who take REVLIMID during pregnancy, or if their male partner takes REVLIMID and they are exposed during pregnancy.
You can enroll in this registry by calling the REMS Call Center at the phone number listed above. REVLIMID can pass into human semen: o Males, including those who have had a vasectomy, must always use a latex or synthetic condom during any sexual contact with a pregnant female or a female that can become pregnant while taking REVLIMID, during any breaks (interruptions) in your treatment with REVLIMID, and for up to 4 weeks after stopping REVLIMID. o Do not have unprotected sexual contact with a female who is or could become pregnant.
Tell your healthcare provider if you do have unprotected sexual contact with a female who is or could become pregnant. o Do not donate sperm while taking REVLIMID, during any breaks (interruptions) in your treatment, and for up to 4 weeks after stopping REVLIMID. If a female becomes pregnant with your sperm, the baby may be exposed to REVLIMID and may be born with birth defects. Men, if your female partner becomes pregnant, you should call your healthcare provider right away. • Low white blood cells (neutropenia) and low platelets (thrombocytopenia).
REVLIMID causes low white blood cells and low platelets in most people. You may need a blood transfusion or certain medicines if your blood counts drop too low. Your healthcare provider should check your blood counts often especially during the first several months of treatment with REVLIMID, and then at least monthly.
Tell your healthcare provide…