
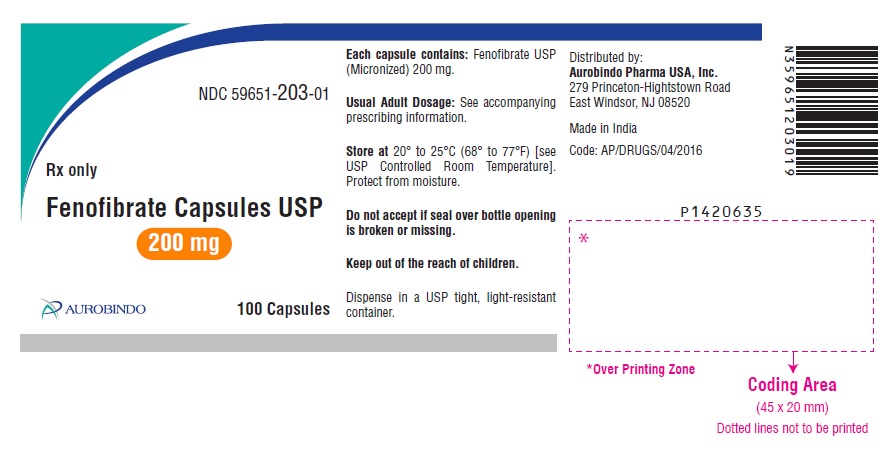
Fenofibrate 200 mg Capsule, 100-count
Other active recalls for Fenofibrate (different manufacturers) — 2 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Peroxisome Proliferator-activated Receptor alpha Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Fenofibrate is used to reduce the amount of cholesterol (a fat-like substance that can build up in blood vessels leading to heart attack or strokes or other medical conditions) and triglycerides (other fatty substances) in the blood. Fenofibrate is in a class of medications called fibrates. It works by speeding the natural processes that remove cholesterol from the body.
Read the full MedlinePlus article ↗- Fenofibrate helps bring your blood lipid levels into a healthier range. Depending on your situation, that might mean lowering your triglycerides, bringing down your LDL (bad) chole...
- What exactly is fenofibrate supposed to do for me?
- It depends on which form you have. Lipofen capsules should be taken with food. Antara capsules and most fenofibrate tablets can be taken with or without food. Some film-coated feno...
- Does it matter if I take this with food or on an empty stomach?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Fenofibrate — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 767IP0Y5NH
A synthetic red colorant used to give medicines their color. It helps patients identify their medication and makes the product visually appealing.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII TUF2IVW3M2
Poloxamer 407 is a synthetic polymer made from ethylene oxide and propylene oxide. In medicines, it acts as a thickener, emulsifier, and solubilizer to help mix ingredients and create the right texture.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII K0KQV10C35
Povidone K25 is a synthetic polymer made from vinyl pyrrolidone. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach for better absorption.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
15 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.173 | $17.31 / 100 capsules |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.2819 | $28.19 / 100 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Fenofibrate 200 mg 13668-0438-01 | Torrent | 100 capsules | $0.173 | AB | Availability likely | — |
| Fenofibrate 200 mg 27241-0120-04 | Ajanta | 100 capsules | $0.173 | AB | Availability likely | — |
| Fenofibrate 200 mg 42858-0200-01 | Rhodes | 100 capsules | $0.173 | AB | Discontinued | — |
| Fenofibrate 200 mg 43975-0306-10 | ANI | 100 capsules | $0.173 | AB | Availability likely | — |
| Fenofibrate 200 mgthis 59651-0203-01 | Aurobindo | 100 capsules | $0.173 | AB | Availability likely | — |
| Fenofibrate 200 mg 60687-0713-21 | American | 30 capsules | $0.173 | AB | Availability likely | — |
| fenofibrate 200 mg 62135-0899-90 | Chartwell | 90 capsules | $0.173 | AB | Availability likely | — |
| fenofibrate 200 mg 68462-0582-01 | Glenmark | 100 capsules | $0.173 | AB | Availability likely | — |
| Fenofibrate 200 mg 35561-0347-11 | Bostal | 90 capsules | — | AB | FDA listed | — |
| Fenofibrate 200 mg 46708-0086-30 | Alembic | 30 capsules | — | AB | FDA listed | — |
| Fenofibrate 200 mg 50090-7994-00 | A-S | 90 capsules | — | AB | FDA listed | — |
| Fenofibrate 200 mg 62332-0086-30 | Alembic | 30 capsules | — | AB | FDA listed | — |
| Fenofibrate 200 mg 69097-0896-02 | Cipla | 30 capsules | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 59651-0203-01 You're viewing this | 100 CAPSULE in 1 BOTTLE (59651-203-01) | 2021-09-20 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Treatment of Hypercholesterolemia Fenofibrate capsules are indicated as adjunctive therapy to diet for the reduction of LDL-C, Total-C, Triglycerides and Apo B in adult patients with primary hypercholesterolemia or mixed dyslipidemia (Fredrickson Types IIa and IIb). Lipid-altering agents should be used in addition to a diet restricted in saturated fat and cholesterol when response to diet and non-pharmacological interventions alone has been inadequate (see National Cholesterol Education Program [NCEP] Treatment Guidelines, below).
Treatment of Hypertriglyceridemia Fenofibrate capsules are also indicated as adjunctive therapy to diet for treatment of adult patients with hypertriglyceridemia (Fredrickson Types IV and V hyperlipidemia). Improving glycemic control in diabetic patients showing fasting chylomicronemia will usually reduce fasting triglycerides and eliminate chylomicronemia thereby obviating the need for pharmacologic intervention. Markedly elevated levels of serum triglycerides (e.g. > 2,000 mg/dL) may increase the risk of developing pancreatitis.
The effect of fenofibrate capsules therapy on reducing this risk has not been adequately studied. Drug therapy is not indicated for patients with Type I hyperlipoproteinemia, who have elevations of chylomicrons and plasma triglycerides, but who have normal levels of very low density lipoprotein (VLDL). Inspection of plasma refrigerated for 14 hours is helpful in distinguishing Types I, IV and V hyperlipoproteinemia 2 .
The initial treatment for dyslipidemia is dietary therapy specific for the type of lipoprotein abnormality. Excess body weight and excess alcoholic intake may be important factors in hypertriglyceridemia and should be addressed prior to any drug therapy. Physical exercise can be an important ancillary measure.
Diseases contributory to hyperlipidemia, such as hypothyroidism or diabetes mellitus should be looked for and adequately treated. Estrogen therapy, like thiazide diuretics and beta-blockers, is sometimes associated with massive rises in plasma triglycerides, especially in subjects with familial hypertriglyceridemia. In such cases, discontinuation of the specific etiologic agent may obviate the need for specific drug therapy of hypertriglyceridemia.
The use of drugs should be considered only when reasonable attempts have been made to obtain satisfactory results with non-drug methods. If the decision is made to use drugs, the patient should be instructed that this does not reduce the importance of adhering to diet (See WARNINGS and PRECAUTIONS ). Fredrickson Classification of Hyperlipoproteinemias C = cholesterol TG = triglycerides LDL = low density lipoprotein VLDL = very low density lipoprotein IDL = intermediate density lipoprotein Lipid Elevation Type Lipoprotein Elevated Major Minor I (rare) chylomicrons TG ↑ ↔ C IIa LDL C — IIb LDL, VLDL C TG III (rare) IDL C, TG — IV VLDL TG ↑ ↔ C V (rare) chylomicrons, VLDL TG ↑ ↔ The NCEP Treatment Guidelines a) Coronary heart disease or peripheral vascular disease (including symptomatic carotid artery disease) b) Other risk factors for coronary heart disease (CHD) include age (males: ≥45 years females: ≥55 years or premature menopause without estrogen replacement therapy); family history of premature CHD, current cigarette smoking; hypertension; confirmed HDL-C is <35 mg/dL (< 0.91 mmol/L), and diabetes mellitus.
Subtract 1 risk factor if HDL-C is >60 mg/dL (≥1.6 mmol/L) c) in CHD patients with LDL-C levels 100 to 129 mg/dL the physician should exercise clinical judgment in deciding whether to initiate drug treatment Definite Athlerosclerotic Disease a Two or More Other Risk Factors b LDL-Cholesterol mg/dL (mmol/L) Initiation Level Goal No No ≥ 190 (≥ 4.9) < 160 (< 4.1) No Yes ≥ 160 (≥ 4.1) < 130 (< 3.4) Yes Yes or No ≥ 130 c (≥ 3.4) < 100 (< 2.6)
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Patients should be placed on an appropriate lipid-lowering diet before receiving fenofibrate capsules, and should continue this diet during treatment with fenofibrate capsules. Fenofibrate capsules should be given with meals, thereby optimizing the bioavailability of the medication. For the treatment of adult patients with primary hypercholesterolemia or mixed hyperlipidemia, the initial dose of fenofibrate capsules is 200 mg per day.
For adult patients with hypertriglyceridemia, the initial dose is 67 to 200 mg per day. Dosage should be individualized according to patient response, and should be adjusted if necessary following repeat lipid determinations at 4 to 8 week intervals. The maximum dose is 200 mg per day.
Treatment with fenofibrate capsules should be initiated at a dose of 67 mg/day in patients having impaired renal function, and increased only after evaluation of the effects on renal function and lipid levels at this dose. In the elderly, the initial dose should likewise be limited to 67 mg/day. Lipid levels should be monitored periodically and consideration should be given to reducing the dosage of fenofibrate capsules if lipid levels fall significantly below the targeted range.
⛔ Contraindications ▾
CONTRAINDICATIONS Fenofibrate capsules are contraindicated in patients who exhibit hypersensitivity to fenofibrate. Fenofibrate capsules are contraindicated in patients with hepatic or severe renal dysfunction, including primary biliary cirrhosis, and patients with unexplained persistent liver function abnormality. Fenofibrate capsules are contraindicated in patients with preexisting gallbladder disease (see WARNINGS ).
⚠️ Warnings ▾
WARNINGS Hepatotoxicity: Serious drug-induced liver injury (DILI), including liver transplantation and death, have been reported postmarketing with fenofibrate. DILI has been reported within the first few weeks of treatment or after several months of therapy and in some cases has reversed with discontinuation of fenofibrate treatment. Patients with DILI have experienced signs and symptoms including dark urine, abnormal stool, jaundice, malaise, abdominal pain, myalgia, weight loss, pruritus, and nausea.
Many patients had concurrent elevations of total bilirubin, serum alanine transaminase (ALT), and aspartate transaminase (AST). DILI has been characterized as hepatocellular, chronic active, and cholestatic hepatitis, and cirrhosis has occurred in association with chronic active hepatitis. In clinical trials, fenofibrate at doses equivalent to 134 mg to 200 mg fenofibrate daily has been associated with increases in serum AST or ALT.
The incidence of increases in transaminases may be dose-related. Fenofibrate is contraindicated in patients with active liver disease, including those with primary biliary cirrhosis and unexplained persistent liver function abnormalities (see CONTRAINDICATIONS). Monitor patient’s liver function, including serum ALT, AST, and total bilirubin, at baseline and periodically for the duration of therapy with fenofibrate.
Discontinue fenofibrate if signs or symptoms of liver injury develop or if elevated enzyme levels persist (ALT or AST > 3 times the upper limit of normal, or if accompanied by elevation of bilirubin). Do not restart fenofibrate in these patients if there is no alternative explanation for the liver injury. Cholelithiasis: Fenofibrate, like clofibrate and gemfibrozil, may increase cholesterol excretion into the bile, leading to cholelithiasis.
If cholelithiasis is suspected, gallbladder studies are indicated. Fenofibrate therapy should be discontinued if gallstones are found. Concomitant Oral Anticoagulants: Caution should be exercised when anticoagulants are given in conjunction with fenofibrate because of the potentiation of coumarin-type anticoagulants in prolonging the prothrombin time/INR.
The dosage of the anticoagulant should be reduced to maintain the prothrombin time/INR at the desired level to prevent bleeding complications. Frequent prothrombin time/INR determinations are advisable until it has been definitely determined that the prothrombin time/INR has stabilized. Concomitant HMG-CoA reductase inhibitors: The combined use of fenofibrate and HMG-CoA reductase inhibitors should be avoided unless the benefit of further alterations in lipid levels is likely to outweigh the increased risk of this drug combination.
Concomitant administration of fenofibrate (equivalent to fenofibrate 200 mg) and pravastatin (40 mg) once daily for 10 days increased the mean C max and AUC values for pravastatin by 36% (range from 69% decrease to 321% increase) and 28% (range from 54% decrease to 128% increase), respectively, and for 3α-hydroxy-iso-pravastatin by 55% (range from 32% decrease to 314% increase) and 39% (range from 24% decrease to 261% increase), respectively. (See also CLINICAL PHARMACOLOGY, Drug-drug Interactions). The combined use of fibric acid derivatives and HMG-CoA reductase inhibitors has been associated, in the absences of a marked pharmacokinetic interaction, in numerous case reports, with rhabdomyolysis, markedly elevated creatine kinase (CK) levels and myoglobinuria, leading in a high proportion of cases to acute renal failure.
The use of fibrates alone, including fenofibrate, may occasionally be associated with myositis, myopathy, or rhabdomyolysis. Patients receiving fenofibrate and complaining of muscle pain, tenderness, or weakness should have prompt medical evaluation for myopathy, including serum creatine kinase level determination. If myopathy/myositis is suspected or diagnosed, fenofibrate therapy should be stopped.
Mortality: The effect of fenofibrate on coronary heart…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Clinical Studies Experience: Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. Adverse events reported by 2% or more of patients treated with fenofibrate (and greater than placebo) during the double-blind, placebo-controlled trials, regardless of causality, are listed in Table 3 below.
Adverse events led to discontinuation of treatment in 5% of patients treated with fenofibrate and in 3% treated with placebo. Increases in liver function tests were the most frequent events, causing discontinuation of fenofibrate treatment in 1.6% of patients in double-blind trials. Photosensitivity reactions have occurred days to months after initiation; in some of these cases, patients reported a prior photosensitivity reaction to ketoprofen.
Table 3. Adverse Reactions Reported by 2% or More of Patients Treated with Fenofibrate and Greater than Placebo During the Double-Blind, Placebo- controlled Trials * Dosage equivalent to 145 mg fenofibrate ** Significantly different from Placebo BODY SYSTEM Fenofibrate* Placebo Adverse Reaction (N=439) (N=365) BODY AS A WHOLE Abdominal Pain 4.6% 4.4% Back Pain 3.4% 2.5% Headache 3.2% 2.7% DIGESTIVE Abnormal Liver Function Tests 7.5%** 1.4% Nausea 2.3% 1.9% Constipation 2.1% 1.4% METABOLIC AND NUTRITIONAL DISORDERS Increased ALT 3% 1.6% Increased CPK 3% 1.4% Increased AST 3.4%** 0.5% RESPIRATORY Respiratory Disorder 6.2% 5.5% Rhinitis 2.3% 1.1% Increases in Liver Enzymes: In a pooled analysis of 10 placebo-controlled trials, increases to > 3 times the upper limit of normal in ALT occurred in 5.3% of patients taking fenofibrate versus 1.1% of patients treated with placebo.
In an 8-week study, the incidence of ALT or AST elevations ≥ 3 times the upper limit of normal was 13% in patients receiving dosages equivalent to 134 mg to 200 mg fenofibrate daily and was 0% in those receiving dosages equivalent to 34 mg to 67 mg fenofibrate daily or placebo. Post-Marketing Experience: The following adverse reactions have been identified during post-approval use of fenofibrate: myalgia, rhabdomyolysis, pancreatitis, acute renal failure, muscle spasm, hepatitis, cirrhosis, increased total bilirubin, anemia, arthralgia, decreases in hemoglobin, decreases in hematocrit, white blood cell decreases, asthenia and interstitial lung disease.
Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
🔄 Drug Interactions ▾
Drug Interactions Oral Anticoagulants: CAUTION SHOULD BE EXERCISED WHEN COUMARIN ANTICOAGULANTS ARE GIVEN IN CONJUNCTION WITH FENOFIBRATE. THE DOSAGE OF THE ANTICOAGULANTS SHOULD BE REDUCED TO MAINTAIN THE PROTHROMBIN TIME/INR AT THE DESIRED LEVEL TO PREVENT BLEEDING COMPLICATIONS. FREQUENT PROTHROMBIN TIME/INR DETERMINATIONS ARE ADVISABLE UNTIL IT HAS BEEN DEFINITELY DETERMINED THAT THE PROTHROMBIN TIME/INR HAS STABILIZED.
HMG-CoA reductase inhibitors: The combined use of fenofibrate and HMG-CoA reductase inhibitors should be avoided unless the benefit of further alterations in lipid levels is likely to outweigh the increased risk of this drug combination (see WARNINGS ). Resins: Since bile acid sequestrants may bind other drugs given concurrently, patients should take fenofibrate at least 1 hour before or 4 to 6 hours after a bile acid binding resin to avoid impeding its absorption. Cyclosporine: Because cyclosporine can produce nephrotoxicity with decreases in creatinine clearance and rises in serum creatinine, and because renal excretion is the primary elimination route of fibrate drugs including fenofibrate, there is a risk that an interaction will lead to deterioration.
The benefits and risks of using fenofibrate with immunosuppressants and other potentially nephrotoxic agents should be carefully considered, and the lowest effective dose employed.
🤰 Pregnancy ▾
Teratogenic Effects: Safety in pregnant women has not been established. There are no adequate and well controlled studies of fenofibrate in pregnant women. Fenofibrate should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
In female rats given oral dietary doses of 15, 75 and 300 mg/kg/day of fenofibrate from 15 days prior to mating through weaning, maternal toxicity was observed at 0.3 times the MRHD, based on body surface area comparisons; mg/m 2 . In pregnant rats given oral dietary doses of 14, 127 and 361 mg/kg/day from gestation day 6 to 15 during the period of organogenesis, adverse developmental findings were not observed at 14 mg/kg/day (less than 1 times the MRHD, based on body surface area comparisons; mg/m 2 ). At higher multiples of human doses evidence of maternal toxicity was observed.
In pregnant rabbits given oral gavage doses of 15, 150 and 300 mg/kg/day from gestation day 6 to 18 during the period of organogenesis and allowed to deliver, aborted litters were observed at 150 mg/kg/day (10 times the MRHD, based on body surface area comparisons: mg/m 2 ). No developmental findings were observed at 15 mg/kg/day (at less than 1 times the MRHD, based on body surface area comparisons; mg/m 2 ). In pregnant rats given oral dietary doses of 15, 75 and 300 mg/kg/day from gestation Day 15 through lactation Day 21 (weaning), maternal toxicity was observed at less than 1 times the MRHD, based on body surface area comparisons; mg/m 2 .
🧒 Pediatric Use ▾
Pediatric Use : Safety and efficacy in pediatric patients have not been established.
🧓 Geriatric Use ▾
Geriatric Use: Fenofibric acid is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Fenofibric acid exposure is not influenced by age. However, elderly patients have a higher incidence of renal impairment, such that dose selection for the elderly should be made on the basis of renal function (see CLINICAL PHARMACOLOGY, Special Populations, Renal Insufficiency ).
Elderly patients with normal renal function should require no dose modifications.
🆘 Overdosage ▾
OVERDOSAGE There is no specific treatment for overdose with fenofibrate. General supportive care of the patient is indicated, including monitoring of vital signs and observation of clinical status, should an overdose occur. If indicated, elimination of unabsorbed drug should be achieved by emesis or gastric lavage; usual precautions should be observed to maintain the airway.
Because fenofibrate is highly bound to plasma proteins, hemodialysis should not be considered.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY A variety of clinical studies have demonstrated that elevated levels of total cholesterol (total-C), low density lipoprotein cholesterol (LDL-C), and apolipoprotein B (apo B), an LDL membrane complex, are associated with human atherosclerosis. Similarly, decreased levels of high density lipoprotein cholesterol (HDL-C) and its transport complex, apolipoprotein A (apo AI and apo AII) are associated with the development of atherosclerosis. Epidemiologic investigations have established that cardiovascular morbidity and mortality vary directly with the level of total-C, LDL-C, and triglycerides, and inversely with the level of HDL-C.
The independent effect of raising HDL-C or lowering triglycerides (TG) on the risk of cardiovascular morbidity and mortality has not been determined. Fenofibric acid, the active metabolite of fenofibrate, produces reductions in total cholesterol, LDL cholesterol, apolipoprotein B, total triglycerides and triglyceride rich lipoprotein (VLDL) in treated patients. In addition, treatment with fenofibrate results in increases in high density lipoprotein (HDL) and apoproteins apo AI and apo AII).
The effects of fenofibric acid seen in clinical practice have been explained in vivo in transgenic mice and in vitro in human hepatocyte cultures by the activation of peroxisome proliferator activated receptor α (PPARα). Through this mechanism, fenofibrate increases lipolysis and elimination of triglyceride-rich particles from plasma by activating lipoprotein lipase and reducing production of apoprotein C-III (an inhibitor of lipoprotein lipase activity). The resulting fall in triglycerides produces an alteration in the size and composition of LDL from small, dense particles (which are thought to be atherogenic due to their susceptibility to oxidation), to large buoyant particles.
These larger particles have a greater affinity for cholesterol receptors and are catabolized rapidly. Activation of PPARα also induces an increase in the synthesis of apoproteins A-I, A-II and HDL-cholesterol. Fenofibrate also reduces serum uric acid levels in hyperuricemic and normal individuals by increasing the urinary excretion of uric acid.
Pharmacokinetics/Metabolism Clinical experience has been obtained with two different formulations of fenofibrate: a "micronized" and "non-micronized" formulation, which have been demonstrated to be bioequivalent. Comparisons of blood levels following oral administration of both formulations in healthy volunteers demonstrate that a single capsule containing 67 mg of the "micronized" formulation is bioequivalent to 100 mg of the "non-micronized" formulation. Three capsules containing 67 mg fenofibrate are bioequivalent to a single 200 mg fenofibrate capsule.
Absorption The absolute bioavailability of fenofibrate cannot be determined as the compound is virtually insoluble in aqueous media suitable for injection. However, fenofibrate is well absorbed from the gastrointestinal tract. Following oral administration in healthy volunteers, approximately 60% of a single dose of radiolabelled fenofibrate appeared in urine, primarily as fenofibric acid and its glucuronate conjugate, and 25% was excreted in the feces.
Peak plasma levels of fenofibric acid occur within 6 to 8 hours after administration. The absorption of fenofibrate is increased when administered with food. With micronized fenofibrate, the absorption is increased by approximately 35% under fed as compared to fasting conditions.
Distribution In healthy volunteers, steady-state plasma levels of fenofibric acid were shown to be achieved within 5 days of dosing with single oral doses equivalent to 67 mg of fenofibrate and did not demonstrate accumulation across time following multiple dose administration. Serum protein binding was approximately 99% in normal and hyperlipidemic subjects. Metabolism Following oral administration, fenofibrate is rapidly hydrolyzed by esterases to the active metabolite, fenofibric acid; no unchange…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Fenofibrate capsules USP, are available as hard gelatin capsules in three strengths: Fenofibrate Capsules USP, 67 mg are pink opaque cap/pink opaque body hard gelatin capsules imprinted with "FBT" on” the cap and "67" on body with black ink filled with white to off white powder. Bottle of 100 NDC 59651-201-01 Fenofibrate Capsules USP, 134 mg are light blue opaque cap/light blue opaque body hard gelatin capsules imprinted with "FBT" on the cap and "134" on body with black ink filled with white to off white powder.
Bottle of 100 NDC 59651-202-01 Fenofibrate Capsules USP, 200 mg are orange opaque cap/ orange opaque body hard gelatin capsules imprinted with "FBT" on the cap and "200" on body with black ink filled with white to off white powder. Bottle of 100 NDC 59651-203-01 Storage Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature]. Keep out of the reach of children.
Protect from moisture.
📋 Description ▾
DESCRIPTION Fenofibrate capsules USP, is a lipid regulating agent available as capsules for oral administration. Each capsule contains 67 mg, 134 mg or 200 mg of micronized fenofibrate USP. The chemical name for fenofibrate is 2-[4-(4-chlorobenzoyl) phenoxy]-2-methyl-propanoic acid, 1- methylethyl ester with the following structural formula: The molecular formula is C 20 H 21 O 4 Cl and the molecular weight is 360.83; fenofibrate is very soluble in methylene chloride, slightly soluble in alcohol, practically insoluble in water.
The melting point is 79 to 82°C. Fenofibrate USP is a white or almost white, crystalline powder which is stable under ordinary conditions. Inactive Ingredients: Each capsule also contains colloidal silicon dioxide, croscarmellose sodium, D&C red 28, gelatin, magnesium stearate, microcrystalline cellulose, poloxamer, povidone, sodium lauryl sulphate and titanium dioxide.
In addition, 67 mg and 134 mg capsule contains FD&C blue 1 and 67 mg and 200 mg capsules contains FD&C red 40 and 200 mg contains iron oxide yellow. The capsules are imprinted with black ink containing black iron oxide, potassium hydroxide and shellac. Meets USP Dissolution Test 7.
Chemical Structure