
Clomipramine Hydrochloride 50 mg Capsule, 100-count — NDC 59651-382-01 (Billing 59651-0382-01)
This is a package of 100 capsules of Clomipramine Hydrochloride 50 mg Capsule from Aurobindo Pharma Limited, marketed since Mar 2023 and currently FDA-listed; retail pharmacies pay about $0.2582 per capsule (NADAC). It is the main listing for this product, which comes in 4 package sizes.
Other active recalls for Clomipramine Hydrochloride (different manufacturers) — 3 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 046121
- GCN: 16603
- GPI-14 (Medi-Span): 58200025100130
- HICL (First Databank): 004744
- AHFS class code: 28:16.04.28
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
Clinical
Clomipramine is used to treat people with obsessive-compulsive disorder (a condition that causes repeated unwanted thoughts and the need to perform certain behaviors over and over). Clomipramine is in a group of medications called tricyclic antidepressants. It works by increasing the amount of serotonin, a natural substance in the brain that is needed to maintain mental balance.
Read the full MedlinePlus article ↗- It treats obsessive-compulsive disorder (OCD) in adults and in children and adolescents. It helps with obsessions and compulsions that cause distress or interfere with daily life.
- At first, you'll usually take it in divided doses with meals to ease stomach upset. Later your prescriber may switch you to a single dose at bedtime to cut down daytime sleepiness....
- Dry mouth, constipation, sleepiness, dizziness, tremor, sweating and weight gain are common. Sexual side effects can also happen. Many ease as your body adjusts, but tell your doct...
- Call right away for new or worse depression, suicidal thoughts, unusual behavior changes, seizures, fainting or a racing heartbeat. A severe rash or eye pain also needs prompt atte...
Patient education
Supplement & herbal interactions
Clomipramine may be associated with lower levels of 3 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.258 | $25.82 / 100 capsules |
| Medicaid paysCMS SDUD · 12 mo | $0.5192 | $51.92 / 100 capsules |
| Medicare drug plans payPart D · Q2 2026 | $0.6012 | $60.12 / 100 capsules |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 59651-0382-01 You're viewing this Main listing | 100 CAPSULE in 1 BOTTLE | $0.2582 / ea | $25.82 | 2023-03-20 | — | Active |
| 59651-0382-30 59651-382-30 | 30 CAPSULE in 1 BOTTLE | $0.2582 / ea | $7.74 | 2023-03-20 | — | Active |
| 59651-0382-90 59651-382-90 | 90 CAPSULE in 1 BOTTLE | $0.2582 / ea | $23.23 | 2023-03-20 | — | Active |
| 59651-0382-29 59651-382-29 | 1500 CAPSULE in 1 BAG | — | — | — | — | Active |
You're viewing one of 4 pack sizes for this product.
This pack has the lowest per-ea cost of the 3 priced pack sizes ($0.2582 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 91% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 59651-0382-30?
What NDC number is used to bill for this package of Clomipramine Hydrochloride 50 mg Capsule?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Clomipramine Hydrochloride 50 mg 00406-8807-01 | SpecGx | 100 capsules | $0.258 | AB | Availability likely | — |
| Clomipramine Hydrochloride 50 mg 00904-7039-07 | Major | 30 capsules | $0.258 | AB | Availability likely | — |
| Clomipramine Hydrochloride 50 mg 16714-0850-01 | Northstar | 30 capsules | $0.258 | AB | Availability likely | — |
| Clomipramine Hydrochloride 50 mg 42571-0343-01 | Micro | 100 capsules | $0.258 | AB | Availability likely | — |
| Clomipramine Hydrochloride 50 mgthis 59651-0382-01 | Aurobindo | 100 capsules | $0.258 | — | Availability likely | — |
| Clomipramine Hydrochloride 50 mg 68084-0818-25 | American | 30 capsules | $0.258 | AB | Availability likely | — |
| Clomipramine Hydrochloride 50 mg 68180-0493-01 | Lupin | 100 capsules | $0.258 | AB | Availability likely | — |
| Clomipramine Hydrochloride 50 mg 69315-0166-01 | Leading | 100 capsules | $0.258 | AB | Availability likely | — |
| Clomipramine Hydrochloride 50 mg 70756-0406-11 | Lifestar | 100 capsules | $0.258 | AB | Availability likely | — |
| Clomipramine hydrochloride 50 mg 27241-0211-01 | Ajanta | 100 capsules | $0.302 | — | FDA listed | +17% |
| Anafranil 50 mg 00406-9907-03 | SpecGx | 30 capsules | — | AB | FDA listed | — |
| Clomipramine Hydrochloride 50 mg 16571-0684-01 | Rising | 100 capsules | — | AB | FDA listed | — |
| Clomipramine Hydrochloride 50 mg 46708-0408-30 | Alembic | 30 capsules | — | AB | FDA listed | — |
| Clomipramine Hydrochloride 50 mg 51407-0758-01 | Golden | 100 capsules | — | AB | FDA listed | — |
| Clomipramine Hydrochloride 50 mg 51672-4012-01 | Sun | 100 capsules | — | AB | FDA listed | — |
| Clomipramine Hydrochloride 50 mg 62332-0408-30 | Alembic | 30 capsules | — | AB | FDA listed | — |
| Clomipramine Hydrochloride 50 mg 71205-0911-00 | Proficient | 100 capsules | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full FDA label FDA SPL
🚨 Boxed Warning ▾
Suicidality and Antidepressant Drugs Antidepressants increased the risk compared to placebo of suicidal thinking and behavior (suicidality) in children, adolescents, and young adults in short-term studies of major depressive disorder (MDD) and other psychiatric disorders. Anyone considering the use of clomipramine hydrochloride or any other antidepressant in a child, adolescent, or young adult must balance this risk with the clinical need. Short-term studies did not show an increase in the risk of suicidality with antidepressants compared to placebo in adults beyond age 24; there was a reduction in risk with antidepressants compared to placebo in adults aged 65 and older.
Depression and certain other psychiatric disorders are themselves associated with increases in the risk of suicide. Patients of all ages who are started on antidepressant therapy should be monitored appropriately and observed closely for clinical worsening, suicidality, or unusual changes in behavior. Families and caregivers should be advised of the need for close observation and communication with the prescriber.
Clomipramine hydrochloride is not approved for use in pediatric patients except for patients with obsessive compulsive disorder (OCD) ( see WARNINGS, Clinical Worsening and Suicide Risk ; PRECAUTIONS, Information for Patients ; and PRECAUTIONS, Pediatric Use ).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Clomipramine hydrochloride capsules are indicated for the treatment of obsessions and compulsions in patients with Obsessive-Compulsive Disorder (OCD). The obsessions or compulsions must cause marked distress, be time-consuming, or significantly interfere with social or occupational functioning, in order to meet the DSM-III-R (circa 1989) diagnosis of OCD. Obsessions are recurrent, persistent ideas, thoughts, images, or impulses that are ego-dystonic.
Compulsions are repetitive, purposeful, and intentional behaviors performed in response to an obsession or in a stereotyped fashion, and are recognized by the person as excessive or unreasonable. The effectiveness of clomipramine hydrochloride capsules for the treatment of OCD was demonstrated in multicenter, placebo-controlled, parallel-group studies, including two 10-week studies in adults and one 8-week study in children and adolescents 10 to 17 years of age. Patients in all studies had moderate-to-severe OCD (DSM-III), with mean baseline ratings on the Yale-Brown Obsessive Compulsive Scale (YBOCS) ranging from 26 to 28 and a mean baseline rating of 10 on the NIMH Clinical Global Obsessive Compulsive Scale (NIMH-OC).
Patients taking CMI experienced a mean reduction of approximately 10 on the YBOCS, representing an average improvement on this scale of 35% to 42% among adults and 37% among children and adolescents. CMI-treated patients experienced a 3.5 unit decrement on the NIMH-OC. Patients on placebo showed no important clinical response on either scale.
The maximum dose was 250 mg/day for most adults and 3 mg/kg/day (up to 200 mg) for all children and adolescents. The effectiveness of clomipramine hydrochloride capsules for long-term use (i.e., for more than 10 weeks) has not been systematically evaluated in placebo-controlled trials. The physician who elects to use clomipramine hydrochloride capsules for extended periods should periodically reevaluate the long-term usefulness of the drug for the individual patient ( see DOSAGE AND ADMINISTRATION ).
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The treatment regimens described below are based on those used in controlled clinical trials of clomipramine hydrochloride capsules in 520 adults, and 91 children and adolescents with OCD. During initial titration, clomipramine hydrochloride capsules should be given in divided doses with meals to reduce gastrointestinal side effects. The goal of this initial titration phase is to minimize side effects by permitting tolerance to side effects to develop or allowing the patient time to adapt if tolerance does not develop.
Because both CMI and its active metabolite, DMI, have long elimination half-lives, the prescriber should take into consideration the fact that steady-state plasma levels may not be achieved until 2 to 3 weeks after dosage change ( see CLINICAL PHARMACOLOGY ). Therefore, after initial titration, it may be appropriate to wait 2 to 3 weeks between further dosage adjustments. Initial Treatment/Dose Adjustment (Adults) Treatment with clomipramine hydrochloride capsules should be initiated at a dosage of 25 mg daily and gradually increased, as tolerated, to approximately 100 mg during the first 2 weeks.
During initial titration, clomipramine hydrochloride capsules should be given in divided doses with meals to reduce gastrointestinal side effects. Thereafter, the dosage may be increased gradually over the next several weeks, up to a maximum of 250 mg daily. After titration, the total daily dose may be given once daily at bedtime to minimize daytime sedation.
Initial Treatment/Dose Adjustment (Children and Adolescents) As with adults, the starting dose is 25 mg daily and should be gradually increased (also given in divided doses with meals to reduce gastrointestinal side effects) during the first 2 weeks, as tolerated, up to a daily maximum of 3 mg/kg or 100 mg, whichever is smaller. Thereafter, the dosage may be increased gradually over the next several weeks up to a daily maximum of 3 mg/kg or 200 mg, whichever is smaller ( see PRECAUTIONS, Pediatric Use ). As with adults, after titration, the total daily dose may be given once daily at bedtime to minimize daytime sedation.
Maintenance/Continuation Treatment (Adults, Children, and Adolescents) While there are no systematic studies that answer the question of how long to continue clomipramine hydrochloride capsules, OCD is a chronic condition and it is reasonable to consider continuation for a responding patient. Although the efficacy of clomipramine hydrochloride capsules after 10 weeks has not been documented in controlled trials, patients have been continued in therapy under double-blind conditions for up to 1 year without loss of benefit.
However, dosage adjustments should be made to maintain the patient on the lowest effective dosage, and patients should be periodically reassessed to determine the need for treatment. During maintenance, the total daily dose may be given once daily at bedtime. Switching a Patient To or From a Monoamine Oxidase Inhibitor (MAOI) Intended to Treat Psychiatric Disorders At least 14 days should elapse between discontinuation of an MAOI intended to treat psychiatric disorders and initiation of therapy with clomipramine hydrochloride capsules.
Conversely, at least 14 days should be allowed after stopping clomipramine hydrochloride capsules before starting an MAOI intended to treat psychiatric disorders ( see CONTRAINDICATIONS ). Use of Clomipramine Hydrochloride Capsules With Other MAOIs, Such as Linezolid or Methylene Blue Do not start clomipramine hydrochloride capsules in a patient who is being treated with linezolid or intravenous methylene blue because there is increased risk of serotonin syndrome. In a patient who requires more urgent treatment of a psychiatric condition, other interventions, including hospitalization, should be considered ( see CONTRAINDICATIONS ).
In some cases, a patient already receiving clomipramine hydrochloride capsules therapy may require urgent treatment with linezolid or intraven… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Clomipramine hydrochloride capsules are contraindicated in patients with a history of hypersensitivity to clomipramine hydrochloride capsules or other tricyclic antidepressants. Monoamine Oxidase Inhibitors (MAOIs) The use of MAOIs intended to treat psychiatric disorders with clomipramine hydrochloride capsules or within 14 days of stopping treatment with clomipramine hydrochloride capsules is contraindicated because of an increased risk of serotonin syndrome. The use of clomipramine hydrochloride capsules within 14 days of stopping an MAOI intended to treat psychiatric disorders is also contraindicated ( see WARNINGS and DOSAGE AND ADMINISTRATION ).
Starting clomipramine hydrochloride capsules in a patient who is being treated with linezolid or intravenous methylene blue is also contraindicated because of an increased risk of serotonin syndrome ( see WARNINGS and DOSAGE AND ADMINISTRATION ). Myocardial Infarction Clomipramine hydrochloride capsules are contraindicated during the acute recovery period after a myocardial infarction.
⚠️ Warnings ▾
WARNINGS Clinical Worsening and Suicide Risk Patients with major depressive disorder (MDD), both adult and pediatric, may experience worsening of their depression and/or the emergence of suicidal ideation and behavior (suicidality) or unusual changes in behavior, whether or not they are taking antidepressant medications, and this risk may persist until significant remission occurs. Suicide is a known risk of depression and certain other psychiatric disorders, and these disorders themselves are the strongest predictors of suicide.
There has been a long-standing concern, however, that antidepressants may have a role in inducing worsening of depression and the emergence of suicidality in certain patients during the early phases of treatment. Pooled analyses of short- term placebo-controlled trials of antidepressant drugs (SSRIs and others) showed that these drugs increase the risk of suicidal thinking and behavior (suicidality) in children, adolescents, and young adults (ages 18 to 24) with major depressive disorder (MDD) and other psychiatric disorders.
Short-term studies did not show an increase in the risk of suicidality with antidepressants compared to placebo in adults beyond age 24; there was a reduction with antidepressants compared to placebo in adults aged 65 and older. The pooled analyses of placebo-controlled trials in children and adolescents with MDD, obsessive compulsive disorder (OCD), or other psychiatric disorders included a total of 24 short-term trials of 9 antidepressant drugs in over 4400 patients. The pooled analyses of placebo-controlled trials in adults with MDD or other psychiatric disorders included a total of 295 short-term trials (median duration of 2 months) of 11 antidepressant drugs in over 77,000 patients.
There was considerable variation in risk of suicidality among drugs, but a tendency toward an increase in the younger patients for almost all drugs studied. There were differences in absolute risk of suicidality across the different indications, with the highest incidence in MDD. The risk differences (drug vs placebo), however, were relatively stable within age strata and across indications.
These risk differences (drug-placebo difference in the number of cases of suicidality per 1000 patients treated) are provided in Table 1 . Table 1 Age Range Drug-Placebo Difference in Number of Cases of Suicidality per 1000 Patients Treated Increases Compared to Placebo <18 18 to 24 14 additional cases 5 additional cases Decreases Compared to Placebo 25 to 64 ≥65 1 fewer case 6 fewer cases No suicides occurred in any of the pediatric trials. There were suicides in the adult trials, but the number was not sufficient to reach any conclusion about drug effect on suicide.
It is unknown whether the suicidality risk extends to longer-term use, i.e., beyond several months. However, there is substantial evidence from placebo-controlled maintenance trials in adults with depression that the use of antidepressants can delay the recurrence of depression. All patients being treated with antidepressants for any indication should be monitored appropriately and observed closely for clinical worsening, suicidality, and unusual changes in behavior, especially during the initial few months of a course of drug therapy, or at times of dose changes, either increases or decreases.
The following symptoms, anxiety, agitation, panic attacks, insomnia, irritability, hostility, aggressiveness, impulsivity, akathisia (psychomotor restlessness), hypomania, and mania, have been reported in adult and pediatric patients being treated with antidepressants for major depressive disorder as well as for other indications, both psychiatric and nonpsychiatric. Although a causal link between the emergence of such symptoms and either the worsening of depression and/or the emergence of suicidal impulses has not been established, there is concern that such symptoms may represent precursors to emerging suicidality.
Consideration should be given to chang… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Commonly Observed The most commonly observed adverse events associated with the use of clomipramine hydrochloride and not seen at an equivalent incidence among placebo-treated patients were gastrointestinal complaints, including dry mouth, constipation, nausea, dyspepsia, and anorexia; nervous system complaints, including somnolence, tremor, dizziness, nervousness, and myoclonus; genitourinary complaints, including changed libido, ejaculatory failure, impotence, and micturition disorder; and other miscellaneous complaints, including fatigue, sweating, increased appetite, weight gain, and visual changes.
Leading to Discontinuation of Treatment Approximately 20% of 3616 patients who received clomipramine hydrochloride in U.S. premarketing clinical trials discontinued treatment because of an adverse event. Approximately one-half of the patients who discontinued (9% of the total) had multiple complaints, none of which could be classified as primary. Where a primary reason for discontinuation could be identified, most patients discontinued because of nervous system complaints (5.4%), primarily somnolence.
The second-most-frequent reason for discontinuation was digestive system complaints (1.3%), primarily vomiting and nausea. There was no apparent relationship between the adverse events and elevated plasma drug concentrations. Incidence in Controlled Clinical Trials The following table enumerates adverse events that occurred at an incidence of 1% or greater among patients with OCD who received clomipramine hydrochloride in adult or pediatric placebo-controlled clinical trials.
The frequencies were obtained from pooled data of clinical trials involving either adults receiving clomipramine hydrochloride (N=322) or placebo (N=319) or children treated with clomipramine hydrochloride (N=46) or placebo (N=44). The prescriber should be aware that these figures cannot be used to predict the incidence of side effects in the course of usual medical practice, in which patient characteristics and other factors differ from those that prevailed in the clinical trials. Similarly, the cited frequencies cannot be compared with figures obtained from other clinical investigations involving different treatments, uses, and investigators.
The cited figures, however, provide the physician with a basis for estimating the relative contribution of drug and nondrug factors to the incidence of side effects in the populations studied. Incidence of Treatment-Emergent Adverse Experience in Placebo-Controlled Clinical Trials (Percentage of Patients Reporting Event) Body System/ Adverse Event* Adults Children and Adolescents Clomipramine hydrochloride (N=322) Placebo (N=319) Clomipramine hydrochloride (N=46) Placebo (N=44) *Events reported by at least 1% of clomipramine hydrochloride patients are included.
Nervous System Somnolence 54 16 46 11 Tremor 54 2 33 2 Dizziness 54 14 41 14 Headache 52 41 28 34 Insomnia 25 15 11 7 Libido change 21 3 - - Nervousness 18 2 4 2 Myoclonus 13 - 2 - Increased appetite 11 2 - 2 Paresthesia 9 3 2 2 Memory impairment 9 1 7 2 Anxiety 9 4 2 - Twitching 7 1 4 5 Impaired concentration 5 2 - - Depression 5 1 - - Hypertonia 4 1 2 - Sleep disorder 4 - 9 5 Psychosomatic disorder 3 - - - Yawning 3 - - - Confusion 3 - 2 - Speech disorder 3 - - - Abnormal dreaming 3 - - 2 Agitation 3 - - - Migraine 3 - - - Depersonalization 2 - 2 - Irritability 2 2 2 - Emotional lability 2 - - 2 Panic reaction 1 - 2 - Aggressive reaction - - 2 - Paresis - - 2 - Skin and Appendages Increased sweating 29 3 9 - Rash 8 1 4 2 Pruritus 6 - 2 2 Dermatitis 2 - - 2 Acne 2 2 - 5 Dry skin 2 - - 5 Urticaria 1 - - - Abnormal skin odor - - 2 - Digestive System Dry mouth 84 17 63 16 Constipation 47 11 22 9 Nausea 33 14 9 11 Dyspepsia 22 10 13 2 Diarrhea 13 9 7 5 Anorexia 12 - 22 2 Abdominal pain 11 9 13 16 Vomiting 7 2 7 - Flatulence 6 3 - 2 Tooth disorder 5 - - - Gastrointestinal disorder 2 - - 2 Dysphagia 2 - - - Esophagitis 1 - - - Eructation - - 2 2 Ulc… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
Drug Interactions The risks of using clomipramine hydrochloride in combination with other drugs have not been systematically evaluated. Given the primary CNS effects of clomipramine hydrochloride, caution is advised in using it concomitantly with other CNS-active drugs ( see Information for Patients ). Clomipramine hydrochloride should not be used with MAO inhibitors ( see CONTRAINDICATIONS ).
Close supervision and careful adjustment of dosage are required when clomipramine hydrochloride is administered with anticholinergic or sympathomimetic drugs. Several tricyclic antidepressants have been reported to block the pharmacologic effects of guanethidine, clonidine, or similar agents, and such an effect may be anticipated with CMI because of its structural similarity to other tricyclic antidepressants. The plasma concentration of CMI has been reported to be increased by the concomitant administration of haloperidol; plasma levels of several closely related tricyclic antidepressants have been reported to be increased by the concomitant administration of methylphenidate or hepatic enzyme inhibitors (e.g., cimetidine, fluoxetine) and decreased by the concomitant administration of hepatic enzyme inducers (e.g., barbiturates, phenytoin), and such an effect may be anticipated with CMI as well.
Administration of CMI has been reported to increase the plasma levels of phenobarbital, if given concomitantly ( see CLINICAL PHARMACOLOGY, Interactions ). Drugs Metabolized by P450 2D6 – The biochemical activity of the drug metabolizing isozyme cytochrome P450 2D6 (debrisoquin hydroxylase) is reduced in a subset of the Caucasian population (about 7% to 10% of Caucasians are so-called “poor metabolizers”); reliable estimates of the prevalence of reduced P450 2D6 isozyme activity among Asian, African and other populations are not yet available.
Poor metabolizers have higher than expected plasma concentrations of tricyclic antidepressants (TCAs) when given usual doses. Depending on the fraction of drug metabolized by P450 2D6, the increase in plasma concentration may be small, or quite large (8 fold increase in plasma AUC of the TCA). In addition, certain drugs inhibit the activity of this isozyme and make normal metabolizers resemble poor metabolizers.
An individual who is stable on a given dose of TCA may become abruptly toxic when given one of these inhibiting drugs as concomitant therapy. The drugs that inhibit cytochrome P450 2D6 include some that are not metabolized by the enzyme (quinidine; cimetidine) and many that are substrates for P450 2D6 (many other antidepressants, phenothiazines, and the Type 1C antiarrhythmics propafenone and flecainide). While all the selective serotonin reuptake inhibitors (SSRIs), e.g., fluoxetine, sertraline, paroxetine, and fluvoxamine, inhibit P450 2D6, they may vary in the extent of inhibition.
Fluvoxamine has also been shown to inhibit P450 1A2, an isoform also involved in TCA metabolism. The extent to which SSRI-TCA interactions may pose clinical problems will depend on the degree of inhibition and the pharmacokinetics of the SSRI involved. Nevertheless, caution is indicated in the co-administration of TCAs with any of the SSRIs and also in switching from one class to the other.
Of particular importance, sufficient time must elapse before initiating TCA treatment in a patient being withdrawn from fluoxetine, given the long half-life of the parent and active metabolite (at least 5 weeks may be necessary). Concomitant use of agents in the tricyclic antidepressant class (which includes clomipramine hydrochloride) with drugs that can inhibit cytochrome P450 2D6 may require lower doses than usually prescribed for either the tricyclic antidepressant agent or the other drug. Furthermore, whenever one of these drugs is withdrawn from co-therapy, an increased dose of tricyclic antidepressant agent may be required.
It is desirable to monitor TCA plasma levels whenever an agent of the tricyclic antidepressant class in… [Excerpted — this section continues on DailyMed.]
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in the pediatric population other than pediatric patients with OCD have not been established ( see BOX WARNING and WARNINGS, Clinical Worsening and Suicide Risk ). Anyone considering the use of clomipramine hydrochloride in a child or adolescent must balance the potential risks with the clinical need. In a controlled clinical trial in children and adolescents (10 to 17 years of age), 46 outpatients received clomipramine hydrochloride for up to 8 weeks.
In addition, 150 adolescent patients have received clomipramine hydrochloride in open-label protocols for periods of several months to several years. Of the 196 adolescents studied, 50 were 13 years of age or less and 146 were 14 to 17 years of age. The adverse reaction profile in this age group ( see ADVERSE REACTIONS ) is similar to that observed in adults.
The risks, if any, that may be associated with clomipramine hydrochloride’s extended use in children and adolescents with OCD have not been systematically assessed. The evidence supporting the conclusion that clomipramine hydrochloride is safe for use in children and adolescents is derived from relatively short term clinical studies and from extrapolation of experience gained with adult patients. In particular, there are no studies that directly evaluate the effects of long term clomipramine hydrochloride use on the growth, development, and maturation of children and adolescents.
Although there is no evidence to suggest that clomipramine hydrochloride adversely affects growth, development or maturation, the absence of such findings is not adequate to rule out a potential for such effects in chronic use. The safety and effectiveness in pediatric patients below the age of 10 have not been established. Therefore, specific recommendations cannot be made for the use of clomipramine hydrochloride in pediatric patients under the age of 10.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of clomipramine hydrochloride did not include sufficient numbers of subjects age 65 and over to determine whether they respond differently from younger subjects; 152 patients at least 60 years of age participating in various U.S. clinical trials received clomipramine hydrochloride for periods of several months to several years. No unusual agerelated adverse events were identified in this population. Other reported clinical experience has not identified differences in responses between the elderly and younger patients.
In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function and of concomitant disease or other drug therapy. Clomipramine hydrochloride has been associated with cases of clinically significant hyponatremia. Elderly patients may be at greater risk for this adverse reaction ( see PRECAUTIONS, Hyponatremia ).
🆘 Overdosage ▾
OVERDOSAGE Deaths may occur from overdosage with this class of drugs. Multiple drug ingestion (including alcohol) is common in deliberate tricyclic overdose. As the management is complex and changing, it is recommended that the physician contact a poison control center for current information on treatment.
Signs and symptoms of toxicity develop rapidly after tricyclic overdose. Therefore, hospital monitoring is required as soon as possible. Human Experience In U.S. clinical trials, 2 deaths occurred in 12 reported cases of acute overdosage with clomipramine hydrochloride either alone or in combination with other drugs.
One death involved a patient suspected of ingesting a dose of 7000 mg. The second death involved a patient suspected of ingesting a dose of 5750 mg. The 10 nonfatal cases involved doses of up to 5000 mg, accompanied by plasma levels of up to 1010 ng/mL.
All 10 patients completely recovered. Among reports from other countries of clomipramine hydrochloride overdose, the lowest dose associated with a fatality was 750 mg. Based upon postmarketing reports in the United Kingdom, CMI’s lethality in overdose is considered to be similar to that reported for closely related tricyclic compounds marketed as antidepressants.
Manifestations Signs and symptoms vary in severity depending upon factors such as the amount of drug absorbed, the age of the patient, and the time elapsed since drug ingestion. Critical manifestations of overdose include cardiac dysrhythmias, severe hypotension, convulsions, and CNS depression including coma. Changes in the electrocardiogram, particularly in QRS axis or width, are clinically significant indicators of tricyclic toxicity.
Other CNS manifestations may include drowsiness, stupor, ataxia, restlessness, agitation, delirium, severe perspiration, hyperactive reflexes, muscle rigidity, and athetoid and choreiform movements. Cardiac abnormalities may include tachycardia, signs of congestive heart failure, and in very rare cases, cardiac arrest. Respiratory depression, cyanosis, shock, vomiting, hyperpyrexia, mydriasis, and oliguria or anuria may also be present.
Management Obtain an ECG and immediately initiate cardiac monitoring. Protect the patient’s airway, establish an intravenous line, and initiate gastric decontamination. A minimum of 6 hours of observation with cardiac monitoring and observation for signs of CNS or respiratory depression, hypotension, cardiac dysrhythmias and/or conduction blocks, and seizures is necessary.
If signs of toxicity occur at any time during this period, extended monitoring is required. There are case reports of patients succumbing to fatal dysrhythmias late after overdose; these patients had clinical evidence of significant poisoning prior to death and most received inadequate gastrointestinal decontamination. Monitoring of plasma drug levels should not guide management of the patient.
Gastrointestinal Decontamination – All patients suspected of tricyclic overdose should receive gastrointestinal decontamination. This should include large volume gastric lavage followed by activated charcoal. If consciousness is impaired, the airway should be secured prior to lavage.
Emesis is contraindicated. Cardiovascular – A maximal limb-lead QRS duration of ≥ 0.10 seconds may be the best indication of the severity of the overdose. Intravenous sodium bicarbonate should be used to maintain the serum pH in the range of 7.45 to 7.55.
If the pH response is inadequate, hyperventilation may also be used. Concomitant use of hyperventilation and sodium bicarbonate should be done with extreme caution, with frequent pH monitoring. A pH >7.60 or a pCO2 <20 mmHg is undesirable.
Dysrhythmias unresponsive to sodium bicarbonate therapy/hyperventilation may respond to lidocaine, bretylium, or phenytoin. Type 1A and 1C antiarrhythmics are generally contraindicated (e.g., quinidine, disopyramide, and procainamide). In rare instances, hemoperfusion may be beneficial in acute refractory cardiova… [Excerpted — this section continues on DailyMed.]
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Pharmacodynamics Clomipramine (CMI) is presumed to influence obsessive and compulsive behaviors through its effects on serotonergic neuronal transmission. The actual neurochemical mechanism is unknown, but CMI’s capacity to inhibit the reuptake of serotonin (5-HT) is thought to be important. Pharmacokinetics Absorption/Bioavailability – CMI from clomipramine hydrochloride capsules is as bioavailable as CMI from a solution.
The bioavailability of CMI from capsules is not significantly affected by food. In a dose proportionality study involving multiple CMI doses, steady-state plasma concentrations (C ss ) and area-under-plasma-concentration-time curves (AUC) of CMI and CMI’s major active metabolite, desmethylclomipramine (DMI), were not proportional to dose over the ranges evaluated, i.e., between 25 to 100 mg/day and between 25 to 150 mg/day, although C ss and AUC are approximately linearly related to dose between 100 to 150 mg/day. The relationship between dose and CMI/DMI concentrations at higher daily doses has not been systematically assessed, but if there is significant dose dependency at doses above 150 mg/day, there is the potential for dramatically higher C ss and AUC even for patients dosed within the recommended range.
This may pose a potential risk to some patients ( see WARNINGS and PRECAUTIONS, Drug Interactions ). After a single 50 mg oral dose, maximum plasma concentrations of CMI occur within 2 to 6 hours (mean, 4.7 hr) and range from 56 ng/mL to 154 ng/mL (mean, 92 ng/mL). After multiple daily doses of 150 mg of clomipramine hydrochloride, steady-state maximum plasma concentrations range from 94 ng/mL to 339 ng/mL (mean, 218 ng/mL) for CMI and from 134 ng/mL to 532 ng/mL (mean, 274 ng/mL) for DMI.
Additional information from a rising dose study of doses up to 250 mg suggests that DMI may exhibit nonlinear pharmacokinetics over the usual dosing range. At a dose of clomipramine hydrochloride 200 mg, subjects who had a single blood sample taken approximately 9 to 22 hours, (median 16 hours), after the dose had plasma concentrations of up to 605 ng/mL for CMI, 781 ng/mL for DMI, and 1386 ng/mL for both. Distribution - CMI distributes into cerebrospinal fluid (CSF) and brain and into breast milk.
DMI also distributes into CSF, with a mean CSF/plasma ratio of 2.6. The protein binding of CMI is approximately 97%, principally to albumin, and is independent of CMI concentration. The interaction between CMI and other highly protein-bound drugs has not been fully evaluated, but may be important ( see PRECAUTIONS, Drug Interactions ).
Metabolism – CMI is extensively biotransformed to DMI and other metabolites and their glucuronide conjugates. DMI is pharmacologically active, but its effects on OCD behaviors are unknown. These metabolites are excreted in urine and feces, following biliary elimination.
After a 25 mg radiolabeled dose of CMI in two subjects, 60% and 51%, respectively, of the dose were recovered in the urine and 32% and 24%, respectively, in feces. In the same study, the combined urinary recoveries of CMI and DMI were only about 0.8% to 1.3% of the dose administered. CMI does not induce drug-metabolizing enzymes, as measured by antipyrine half-life.
Elimination – Evidence that the C ss and AUC for CMI and DMI may increase disproportionately with increasing oral doses suggests that the metabolism of CMI and DMI may be capacity limited. This fact must be considered in assessing the estimates of the pharmacokinetic parameters presented below, as these were obtained in individuals exposed to doses of 150 mg. If the pharmacokinetics of CMI and DMI are nonlinear at doses above 150 mg, their elimination half-lives may be considerably lengthened at doses near the upper end of the recommended dosing range (i.e., 200 mg/day to 250 mg/day).
Consequently, CMI and DMI may accumulate, and this accumulation may increase the incidence of any dose- or plasma- concentration-dependent adverse reactions, in… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Clomipramine Hydrochloride Capsules USP, 25 mg are orange opaque cap and white opaque body, hard gelatin capsule shells imprinted with 'CO' on cap and '25' on body in black ink filled with white to off-white powder. Bottles of 30 NDC 59651-381-30 Bottles of 90 NDC 59651-381-90 Bottles of 100 NDC 59651-381-01 Clomipramine Hydrochloride Capsules USP, 50 mg are blue opaque cap and white opaque body, hard gelatin capsule shells imprinted with 'CO' on cap and '50' on body in black ink filled with white to off-white powder.
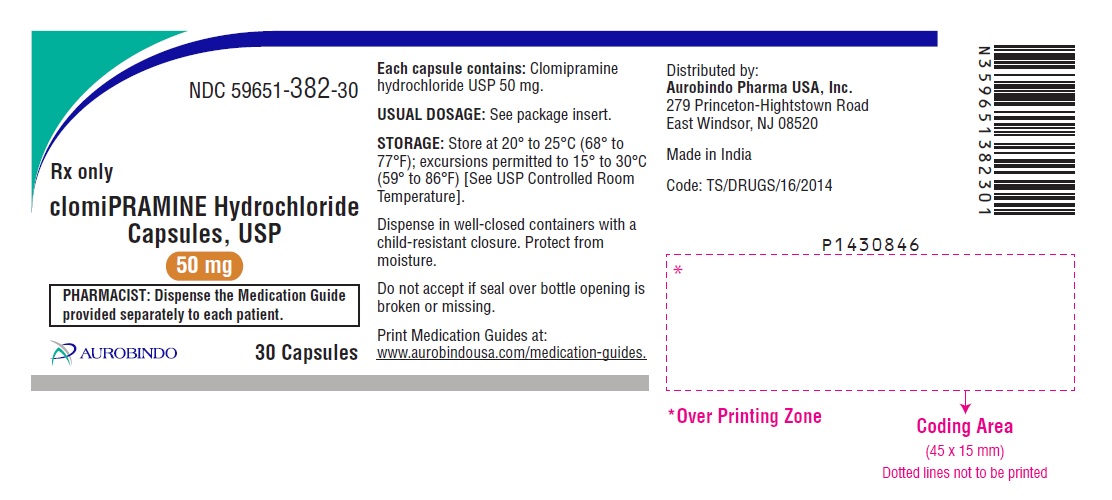
Bottles of 30 NDC 59651-382-30 Bottles of 90 NDC 59651-382-90 Bottles of 100 NDC 59651-382-01 Clomipramine Hydrochloride Capsules USP, 75 mg are dark yellow opaque cap and white opaque body, hard gelatin capsule shells imprinted with 'CO' on cap and '75' on body in black ink filled with white to off-white powder. Bottles of 30 NDC 59651-383-30 Bottles of 90 NDC 59651-383-90 Bottles of 100 NDC 59651-383-01 Storage – Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature].
Dispense in well-closed containers with a child-resistant closure. Protect from moisture.
📋 Description ▾
DESCRIPTION Clomipramine hydrochloride capsules, USP is an antiobsessional drug that belongs to the class (dibenzazepine) of pharmacologic agents known as tricyclic antidepressants. Clomipramine hydrochloride is available as capsules of 25 mg, 50 mg, and 75 mg for oral administration. Clomipramine hydrochloride USP is 3-chloro-5-[3-(dimethylamino)propyl]-10,11-dihydro-5 H -dibenz[ b,f ]azepine monohydrochloride, and its structural formula is: Clomipramine hydrochloride USP is a white or faintly yellow crystalline powder.
It is very soluble in water, freely soluble in methylene chloride, soluble in ethanol (96%) Inactive Ingredients : magnesium stearate and pregelatinized starch (maize). The hard gelatin capsule shells contains the following inactive ingredients: gelatin, titanium dioxide. In addition the 25 mg hard gelatin capsule shell contains D&C red 33, D&C yellow 10 and FD&C yellow 6, 50 mg hard gelatin capsule shell contains FD&C blue 1, 75 mg hard gelatin capsule shell contains D&C yellow 10 and FD&C yellow 6.
The capsules are imprinted with black ink containing black iron oxide, potassium hydroxide and shellac. Chemical Structure
💬 Information for Patients ▾
Information for Patients Prescribers or other health professionals should inform patients, their families, and their caregivers about the benefits and risks associated with treatment with clomipramine hydrochloride and should counsel them in its appropriate use. A patient Medication Guide about “Antidepressant Medicines, Depression and other Serious Mental Illness, and Suicidal Thoughts or Actions” is available for clomipramine hydrochloride. The prescriber or health professional should instruct patients, their families, and their caregivers to read the Medication Guide and should assist them in understanding its contents.
Patients should be given the opportunity to discuss the contents of the Medication Guide and to obtain answers to any questions they may have. The complete text of the Medication Guide is reprinted at the end of this document. Patients should be advised of the following issues and asked to alert their prescriber if these occur while taking clomipramine hydrochloride.
Clinical Worsening and Suicide Risk – Patients, their families, and their caregivers should be encouraged to be alert to the emergence of anxiety, agitation, panic attacks, insomnia, irritability, hostility, aggressiveness, impulsivity, akathisia (psychomotor restlessness), hypomania, mania, other unusual changes in behavior, worsening of depression, and suicidal ideation, especially early during antidepressant treatment and when the dose is adjusted up or down. Families and caregivers of patients should be advised to look for the emergence of such symptoms on a day-to-day basis, since changes may be abrupt.
Such symptoms should be reported to the patient’s prescriber or health professional, especially if they are severe, abrupt in onset, or were not part of the patient’s presenting symptoms. Symptoms such as these may be associated with an increased risk for suicidal thinking and behavior and indicate a need for very close monitoring and possibly changes in the medication. Physicians are advised to discuss the following issues with patients for whom they prescribe clomipramine hydrochloride: (1) The risk of seizure ( see WARNINGS ); (2) The relatively high incidence of sexual dysfunction among males ( see Sexual Dysfunction ); (3) Since clomipramine hydrochloride may impair the mental and/or physical abilities required for the performance of complex tasks, and since clomipramine hydrochloride is associated with a risk of seizures, patients should be cautioned about the performance of complex and hazardous tasks ( see WARNINGS ); (4) Patients should be cautioned about using alcohol, barbiturates, or other CNS depressants concurrently, since clomipramine hydrochloride may exaggerate their response to these drugs; (5) Patients should notify their physician if they become pregnant or intend to become pregnant during therapy; (6) Patients should notify their physician if they are breast-feeding.
Patients should be advised that taking clomipramine hydrochloride can cause mild pupillary dilation, which in susceptible individuals, can lead to an episode of angle-closure glaucoma. Pre-existing glaucoma is almost always open-angle glaucoma because angle-closure glaucoma, when diagnosed, can be treated definitively with iridectomy. Open-angle glaucoma is not a risk factor for angle-closure glaucoma.
Patients may wish to be examined to determine whether they are susceptible to angle closure, and have a prophylactic procedure (e.g., iridectomy), if they are susceptible.
💬 Medication Guide ▾
Medication Guide Clomipramine Hydrochloride Capsules, USP (kloe mip’ ra meen hye’’ droe klor’ ide) Antidepressant Medicines, Depression and other Serious Mental Illnesses, and Suicidal Thoughts or Actions Read the Medication Guide that comes with you or your family member’s antidepressant medicine. This Medication Guide is only about the risk of suicidal thoughts and actions with antidepressant medicines. Talk to your, or your family member’s, healthcare provider about: all risks and benefits of treatment with antidepressant medicines all treatment choices for depression or other serious mental illness What is the most important information I should know about antidepressant medicines, depression and other serious mental illnesses, and suicidal thoughts or actions?
1. Antidepressant medicines may increase suicidal thoughts or actions in some children, teenagers, and young adults within the first few months of treatment. 2.
Depression and other serious mental illnesses are the most important causes of suicidal thoughts and actions. Some people may have a particularly high risk of having suicidal thoughts or actions. These include people who have (or have a family history of) bipolar illness (also called manic-depressive illness) or suicidal thoughts or actions.
3. How can I watch for and try to prevent suicidal thoughts and actions in myself or a family member? Pay close attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings.
This is very important when an antidepressant medicine is started or when the dose is changed. Call the healthcare provider right away to report new or sudden changes in mood, behavior, thoughts, or feelings. Keep all follow-up visits with the healthcare provider as scheduled.
Call the healthcare provider between visits as needed, especially if you have concerns about symptoms. Call a healthcare provider right away if you or your family member has any of the following symptoms, especially if they are new, worse, or worry you: thoughts about suicide or dying attempts to commit suicide new or worse depression new or worse anxiety feeling very agitated or restless panic attacks trouble sleeping (insomnia) new or worse irritability acting aggressive, being angry, or violent acting on dangerous impulses an extreme increase in activity and talking (mania) other unusual changes in behavior or mood Low salt (sodium) levels in the blood.
Elderly people may be at greater risk for this. Symptoms may include: headache weakness or feeling unsteady confusion, problems concentrating or thinking or memory problems Visual problems eye pain changes in vision swelling or redness in or around the eye Only some people are at risk for these problems. You may want to undergo an eye examination to see if you are at risk and receive preventative treatment if you are.
Who should not take clomipramine hydrochloride capsules? Do not take clomipramine hydrochloride capsules if you: take a monoamine oxidase inhibitor (MAOI). Ask your healthcare provider or pharmacist if you are not sure if you take an MAOI, including the antibiotic linezolid.
Do not take an MAOI within 2 weeks of stopping clomipramine hydrochloride capsules unless directed to do so by your physician. Do not start clomipramine hydrochloride capsules if you stopped taking an MAOI in the last 2 weeks unless directed to do so by your physician. What else do I need to know about antidepressant medicines?
Never stop an antidepressant medicine without first talking to a healthcare provider. Stopping an antidepressant medicine suddenly can cause other symptoms. Antidepressants are medicines used to treat depression and other illnesses.
It is important to discuss all the risks of treating depression and also the risks of not treating it. Patients and their families or other caregivers should discuss all treatment choices with the healthcare provider, not just the use of antidepressants. Antidepressant medicines have other side effects.
Ta… [Excerpted — this section continues on DailyMed.]
⚠️ Precautions ▾
PRECAUTIONS General Suicide – Since depression is a commonly associated feature of OCD, the risk of suicide must be considered. Prescriptions for clomipramine hydrochloride should be written for the smallest quantity of capsules consistent with good patient management, in order to reduce the risk of overdose. Cardiovascular Effects – Modest orthostatic decreases in blood pressure and modest tachycardia were each seen in approximately 20% of patients taking clomipramine hydrochloride in clinical trials; but patients were frequently asymptomatic.
Among approximately 1400 patients treated with CMI in the premarketing experience who had ECGs, 1.5% developed abnormalities during treatment, compared with 3.1% of patients receiving active control drugs and 0.7% of patients receiving placebo. The most common ECG changes were PVCs, ST-T wave changes, and intraventricular conduction abnormalities. These changes were rarely associated with significant clinical symptoms.
Nevertheless, caution is necessary in treating patients with known cardiovascular disease, and gradual dose titration is recommended. Psychosis, Confusion, and Other Neuropsychiatric Phenomena – Patients treated with clomipramine hydrochloride have been reported to show a variety of neuropsychiatric signs and symptoms including delusions, hallucinations, psychotic episodes, confusion, and paranoia. Because of the uncontrolled nature of many of the studies, it is impossible to provide a precise estimate of the extent of risk imposed by treatment with clomipramine hydrochloride.
As with tricyclic antidepressants to which it is closely related, clomipramine hydrochloride may precipitate an acute psychotic episode in patients with unrecognized schizophrenia. Mania/Hypomania – During premarketing testing of clomipramine hydrochloride in patients with affective disorder, hypomania or mania was precipitated in several patients. Activation of mania or hypomania has also been reported in a small proportion of patients with affective disorder treated with marketed tricyclic antidepressants, which are closely related to clomipramine hydrochloride.
Hepatic Changes – During premarketing testing, clomipramine hydrochloride was occasionally associated with elevations in SGOT and SGPT (pooled incidence of approximately 1% and 3%, respectively) of potential clinical importance (i.e., values greater than 3 times the upper limit of normal). In the vast majority of instances, these enzyme increases were not associated with other clinical findings suggestive of hepatic injury; moreover, none were jaundiced. Rare reports of more severe liver injury, some fatal, have been recorded in foreign postmarketing experience.
Caution is indicated in treating patients with known liver disease, and periodic monitoring of hepatic enzyme levels is recommended in such patients. Hematologic Changes – Although no instances of severe hematologic toxicity were seen in the premarketing experience with clomipramine hydrochloride, there have been postmarketing reports of leukopenia, agranulocytosis, thrombocytopenia, anemia, and pancytopenia in association with clomipramine hydrochloride use. As is the case with tricyclic antidepressants to which clomipramine hydrochloride is closely related, leukocyte and differential blood counts should be obtained in patients who develop fever and sore throat during treatment with clomipramine hydrochloride.
Central Nervous System – More than 30 cases of hyperthermia have been recorded by nondomestic postmarketing surveillance systems. Most cases occurred when clomipramine hydrochloride was used in combination with other drugs. When clomipramine hydrochloride and a neuroleptic were used concomitantly, the cases were sometimes considered to be examples of a neuroleptic malignant syndrome.
Sexual Dysfunction – The rate of sexual dysfunction in male patients with OCD who were treated with clomipramine hydrochloride in the premarketing experience was markedly increased compared with… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Clomipramine hydrochloride has been found in human milk. Because of the potential for adverse reactions, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
🔒 Drug Abuse and Dependence ▾
DRUG ABUSE AND DEPENDENCE Clomipramine hydrochloride has not been systematically studied in animals or humans for its potential for abuse, tolerance, or physical dependence. While a variety of withdrawal symptoms have been described in association with clomipramine hydrochloride discontinuation ( see PRECAUTIONS, Withdrawal Symptoms ), there is no evidence for drug-seeking behavior, except for a single report of potential clomipramine hydrochloride abuse by a patient with a history of dependence on codeine, benzodiazepines, and multiple psychoactive drugs.
The patient received clomipramine hydrochloride for depression and panic attacks and appeared to become dependent after hospital discharge. Despite the lack of evidence suggesting an abuse liability for clomipramine hydrochloride in foreign marketing, it is not possible to predict the extent to which clomipramine hydrochloride might be misused or abused once marketed in the U.S. Consequently, physicians should carefully evaluate patients for a history of drug abuse and follow such patients closely.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility No evidence of carcinogenicity was found in two 2-year bioassays in rats at doses up to 100 mg/kg, which is 24 and 4 times the maximum recommended human daily dose (MRHD) on a mg/kg and mg/m 2 basis, respectively, or in a 2-year bioassay in mice at doses up to 80 mg/kg, which is 20 and 1.5 times the MRHD on a mg/kg and mg/m 2 basis, respectively. In reproduction studies, no effects on fertility were found in rats given up to 24 mg/kg, which is 6 times, and approximately equal to, the MRHD on a mg/kg and mg/m 2 basis, respectively.
No teratogenic effects were observed in studies performed in rats and mice at doses up to 100 mg/kg, which is 24 times the maximum recommended human daily dose (MRHD) on a mg/kg basis and 4 times (rats) and 2 times (mice) the MRHD on a mg/m 2 basis. Slight nonspecific embryo/fetotoxic effects were seen in the offspring of treated rats given 50 and 100 mg/kg and of treated mice given 100 mg/kg. There are no adequate or well-controlled studies in pregnant women.
Withdrawal symptoms, including jitteriness, tremor, and seizures, have been reported in neonates whose mothers had taken clomipramine hydrochloride until delivery. Clomipramine hydrochloride should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL - 25 mg (30 Capsules Bottle) NDC 59651-381-30 Rx only clomiPRAMINE Hydrochloride Capsules, USP 25 mg PHARMACIST; Dispense the Medication Guide provided separately to each patient. AUROBINDO 30 Capsules PACKAGE LABEL.PRINCIPAL DISPLAY PANEL - 25 mg (30 Capsules Bottle)
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL - 50 mg (30 Capsules Bottle) NDC 59651-382-30 Rx only clomiPRAMINE Hydrochloride Capsules, USP 50 mg PHARMACIST; Dispense the Medication Guide provided separately to each patient. AUROBINDO 30 Capsules PACKAGE LABEL.PRINCIPAL DISPLAY PANEL - 50 mg (30 Capsules Bottle)
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL - 75 mg (30 Capsules Bottle) NDC 59651-383-30 Rx only clomiPRAMINE Hydrochloride Capsules, USP 75 mg PHARMACIST; Dispense the Medication Guide provided separately to each patient. AUROBINDO 30 Capsules PACKAGE LABEL.PRINCIPAL DISPLAY PANEL - 75 mg (30 Capsules Bottle)
Medicaid utilization & spend
Medicaid utilization by pack size
About this NDC listing & data coverage
What "drug for further processing" means
FDA lists this package under the "drug for further processing" marketing category: Aurobindo Pharma Limited supplies it to other companies for further processing or repackaging (blister cards that are later repackaged or co-packaged are a common example). The units themselves are a finished dosage form — which is why pricing or Medicaid data can still appear — but this exact package code may not be the presentation a retail pharmacy dispenses.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |