
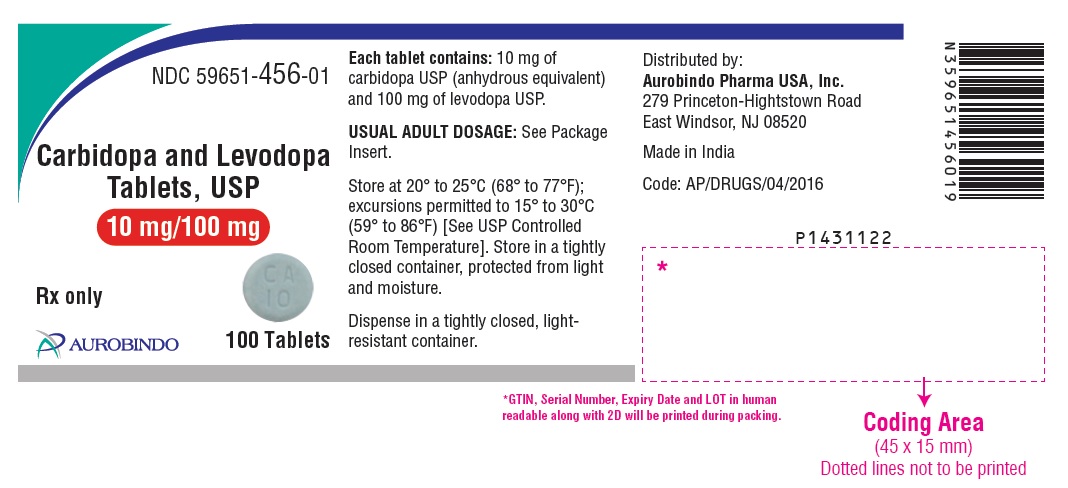
Carbidopa and Levodopa 10 mg; 100 mg Tablet, 100-count — NDC 59651-456-01 (Billing 59651-0456-01)
This is a package of 100 tablets of Carbidopa and Levodopa 10 mg; 100 mg Tablet from Aurobindo Pharma Limited, marketed since Nov 2022 and currently FDA-listed; retail pharmacies pay about $0.0683 per tablet (NADAC). It is the main listing for this product, which comes in 2 package sizes.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 002537
- GCN: 62740
- GPI-14 (Medi-Span): 73209902100310
- HICL (First Databank): 013894
- AHFS class code: 28:36.16.00
- RxCUI (RxNorm): 197443
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Sep 24, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Aromatic Amino Acid Decarboxylation Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Sep 24, 2026
Clinical
- It treats Parkinson’s disease and related parkinsonism, including parkinsonism after brain inflammation or carbon monoxide or manganese poisoning. Duopa is specifically for motor f...
- Follow your prescription exactly, since your doctor adjusts the dose slowly. Extended-release forms shouldn’t be chewed or crushed. Rytary and Crexont can be taken with or without...
- Nausea, dizziness, headache, vivid dreams, and uncontrolled movements called dyskinesia are common. Tell your doctor if these bother you, because a dose change may help.
- Be careful. Some people fall asleep suddenly with no warning, even after being on it a long time. If that happens, don’t drive or do risky activities, and tell your doctor.
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.068 | $6.83 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.1579 | $15.79 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.1325 | $13.25 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 59651-0456-01 You're viewing this Main listing | 100 TABLET in 1 BOTTLE | $0.0683 / ea | $6.83 | 2022-11-28 | — | Active |
| 59651-0456-05 59651-456-05 | 500 TABLET in 1 BOTTLE | — | — | 2022-11-28 | — | Active |
You're viewing the smallest of 2 pack sizes for this product.
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 59651-0456-05?
What NDC number is used to bill for this package of Carbidopa and Levodopa 10 mg; 100 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Carbidopa and levodopa 10 mg/1; 100 mg 00093-9701-01 | Teva | 100 tablets | $0.068 | AB | Availability likely | — |
| Carbidopa And Levodopa 10 mg/1; 100 mg 31722-0381-01 | Camber | 100 tablets | $0.068 | AB | Availability likely | — |
| Carbidopa and Levodopa 10 mg/1; 100 mg 50228-0457-01 | ScieGen | 100 tablets | $0.068 | AB | Availability likely | — |
| Carbidopa-levodopa 10 mg/1; 100 mg 52817-0390-10 | TruPharma, | 100 tablets | $0.068 | AB | Availability likely | — |
| Carbidopa and Levodopa 10 mg/1; 100 mgthis 59651-0456-01 | Aurobindo | 100 tablets | $0.068 | AB | Availability likely | — |
| Carbidopa-levodopa 10 mg/1; 100 mg 68002-0100-04 | American | 30 tablets | $0.068 | AB | Availability likely | — |
| Carbidopa and Levodopa 10 mg/1; 100 mg 69367-0338-01 | Westminster | 100 tablets | $0.068 | AB | Availability likely | — |
| Carbidopa-levodopa 10 mg/1; 100 mg 72888-0106-00 | Advagen | 1000 tablets | $0.068 | AB | Availability likely | — |
| Carbidopa and Levodopa 10 mg/1; 100 mg 75907-0022-01 | Dr. | 100 tablets | $0.068 | AB | Availability likely | — |
| Carbidopa and Levodopa 10 mg/1; 100 mg 00615-8555-39 | NCS | 30 tablets | — | AB | FDA listed | — |
| Carbidopa and levodopa 10 mg/1; 100 mg 42291-0471-01 | AvKARE | 100 tablets | — | AB | FDA listed | — |
| Carbidopa and Levodopa 10 mg/1; 100 mg 50090-7186-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Carbidopa And Levodopa 10 mg/1; 100 mg 62756-0517-08 | Sun | 100 tablets | — | AB | FDA listed | — |
| Carbidopa and Levodopa 10 mg/1; 100 mg 67046-1614-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Carbidopa and Levodopa 10 mg/1; 100 mg 71205-0877-00 | Proficient | 100 tablets | — | AB | FDA listed | — |
| Carbidopa And Levodopa 10 mg/1; 100 mg 72865-0361-01 | XLCare | 100 tablets | — | AB | FDA listed | — |
| Sinemet 10 mg/1; 100 mg 78206-0166-01 | Organon | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 40UAA97IT9
Crospovidone is a synthetic polymer derived from povidone. It absorbs liquid quickly and swells, helping tablets and capsules break apart and dissolve faster in your stomach.
-
UNII 4AQJ3LG584
A synthetic blue dye combined with aluminum to create a stable colorant. It's used in medicines and supplements to add blue color or create specific shades for product identification and appearance.
-
UNII 5Y0974F5PW
Hydroxypropyl cellulose is a plant-derived thickener and binder made by chemically treating cellulose. In medicines, it helps hold tablets together, thickens liquids, and can form a protective coating on capsules.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Carbidopa and levodopa tablets are indicated in the treatment of Parkinson's disease, post-encephalitic parkinsonism, and symptomatic parkinsonism that may follow carbon monoxide intoxication or manganese intoxication. Carbidopa allows patients treated for Parkinson's disease to use much lower doses of levodopa. Some patients who responded poorly to levodopa have improved on carbidopa and levodopa tablets.
This is most likely due to decreased peripheral decarboxylation of levodopa caused by administration of carbidopa rather than by a primary effect of carbidopa on the nervous system. Carbidopa has not been shown to enhance the intrinsic efficacy of levodopa. Carbidopa may also reduce nausea and vomiting and permit more rapid titration of levodopa.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The optimum daily dosage of carbidopa and levodopa tablets must be determined by careful titration in each patient. Carbidopa and levodopa tablets are available in a 1:4 ratio of carbidopa to levodopa (carbidopa and levodopa tablets 25 mg/100 mg) as well as 1:10 ratio (carbidopa and levodopa tablets 25 mg/250 mg and carbidopa and levodopa tablets 10 mg/100 mg). Tablets of the two ratios may be given separately or combined as needed to provide the optimum dosage.
Studies show that peripheral dopa decarboxylase is saturated by carbidopa at approximately 70 to 100 mg a day. Patients receiving less than this amount of carbidopa are more likely to experience nausea and vomiting. Management of Vitamin B 6 Levels Evaluate vitamin B 6 levels prior to initiating carbidopa/levodopa therapies, including carbidopa and levodopa tablets, periodically during treatment, and as clinically indicated (See WARNINGS, Vitamin B6 Deficiency and Seizures ).
If vitamin B 6 levels are low, supplement to sufficient levels per standard of care. Patients may initiate and continue treatment with carbidopa and levodopa tablets while supplementing vitamin B 6 . Usual Initial Dosage Dosage is best initiated with one tablet of carbidopa and levodopa 25 mg/100 mg three times a day.
This dosage schedule provides 75 mg of carbidopa per day. Dosage may be increased by one tablet every day or every other day, as necessary, until a dosage of eight tablets of carbidopa and levodopa 25 mg/100 mg a day is reached. If carbidopa and levodopa tablets 10 mg/100 mg is used, dosage may be initiated with one tablet three or four times a day.
However, this will not provide an adequate amount of carbidopa for many patients. Dosage may be increased by one tablet every day or every other day until a total of eight tablets (2 tablets q.i.d.) is reached. How to Transfer Patients from Levodopa Levodopa must be discontinued at least twelve hours before starting carbidopa and levodopa tablets.
A daily dosage of carbidopa and levodopa should be chosen that will provide approximately 25% of the previous levodopa dosage. Patients who are taking less than 1500 mg of levodopa a day should be started on one tablet of carbidopa and levodopa 25 mg/100 mg three or four times a day. The suggested starting dosage for most patients taking more than 1500 mg of levodopa is one tablet of carbidopa and levodopa 25 mg/250 mg three or four times a day.
Maintenance Therapy should be individualized and adjusted according to the desired therapeutic response. At least 70 to 100 mg of carbidopa per day should be provided. When a greater proportion of carbidopa is required, one tablet of carbidopa and levodopa 25 mg/100 mg may be substituted for each tablet of carbidopa and levodopa 10 mg/100 mg.
When more levodopa is required, carbidopa and levodopa tablets 25 mg/250 mg should be substituted for carbidopa and levodopa tablets 25 mg/100 mg or carbidopa and levodopa tablets 10 mg/100 mg. If necessary, the dosage of carbidopa and levodopa 25 mg/250 mg may be increased by one-half or one tablet every day or every other day to a maximum of eight tablets a day. Experience with total daily dosages of carbidopa greater than 200 mg is limited.
Because both therapeutic and adverse responses occur more rapidly with carbidopa and levodopa than with levodopa alone, patients should be monitored closely during the dose adjustment period. Specifically, involuntary movements will occur more rapidly with carbidopa and levodopa than with levodopa. The occurrence of involuntary movements may require dosage reduction.
Blepharospasm may be a useful early sign of excess dosage in some patients. Addition of Other Antiparkinsonian Medications Standard drugs for Parkinson's disease, other than levodopa without a decarboxylase inhibitor, may be used concomitantly while carbidopa and levodopa tablets are being administered, although dosage adjustments may be required. Interruption of Therapy Sporadic cases of… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Nonselective monoamine oxidase (MAO) inhibitors are contraindicated for use with carbidopa and levodopa tablets. These inhibitors must be discontinued at least two weeks prior to initiating therapy with carbidopa and levodopa tablets. Carbidopa and levodopa tablets may be administered concomitantly with the manufacturer's recommended dose of an MAO inhibitor with selectivity for MAO type B (e.g., selegiline HCl) (see PRECAUTIONS , Drug Interactions ).
Carbidopa and levodopa tablets are contraindicated in patients with known hypersensitivity to any component of this drug, and in patients with narrow-angle glaucoma.
⚠️ Warnings ▾
WARNINGS When carbidopa and levodopa is to be given to patients who are being treated with levodopa, levodopa must be discontinued at least twelve hours before therapy with carbidopa and levodopa is started. In order to reduce adverse reactions, it is necessary to individualize therapy. See DOSAGE AND ADMINISTRATION section before initiating therapy.
The addition of carbidopa with levodopa in the form of carbidopa and levodopa tablets reduces the peripheral effects (nausea, vomiting) due to decarboxylation of levodopa; however, carbidopa does not decrease the adverse reactions due to the central effects of levodopa. Because carbidopa permits more levodopa to reach the brain and more dopamine to be formed, certain adverse central nervous system (CNS) effects, e.g., dyskinesias (involuntary movements), may occur at lower dosages and sooner with carbidopa and levodopa than with levodopa alone.
All patients should be observed carefully for the development of depression with concomitant suicidal tendencies. Carbidopa and levodopa should be administered cautiously to patients with severe cardiovascular or pulmonary disease, bronchial asthma, renal, hepatic or endocrine disease. As with levodopa, care should be exercised in administering carbidopa and levodopa to patients with a history of myocardial infarction who have residual atrial, nodal, or ventricular arrhythmias.
In such patients, cardiac function should be monitored with particular care during the period of initial dosage adjustment, in a facility with provisions for intensive cardiac care. As with levodopa, treatment with carbidopa and levodopa may increase the possibility of upper gastrointestinal hemorrhage in patients with a history of peptic ulcer. Vitamin B 6 Deficiency and Seizures Treatment with carbidopa and levodopa may contribute to reduced vitamin B 6 levels.
Higher doses of carbidopa/levodopa may increase the risk of vitamin B 6 deficiency. Seizures associated with vitamin B 6 deficiency have been reported in the postmarketing setting in patients taking carbidopa and levodopa. In these reported cases, seizures were refractory to traditional anti-seizure medications and only resolved after vitamin B 6 administration.
Other symptoms of vitamin B 6 deficiency may occur, including depression, confusion, cheilosis, glossitis, dermatitis, anemia, and/or neuropathy. Evaluate vitamin B 6 levels prior to initiation of carbidopa and levodopa and periodically while on treatment or if symptoms associated with vitamin B 6 deficiency are identified. Supplement with vitamin B 6 as necessary.
Falling Asleep During Activities of Daily Living and Somnolence Patients taking carbidopa and levodopa alone or with other dopaminergic drugs have reported suddenly falling asleep without prior warning of sleepiness while engaged in activities of daily living (includes operation of motor vehicles). Road traffic accidents attributed to sudden sleep onset have been reported. Although many patients reported somnolence while on dopaminergic medications, there have been reports of road traffic accidents attributed to sudden onset of sleep in which the patient did not perceive any warning signs, such as excessive drowsiness, and believed that they were alert immediately prior to the event.
Sudden onset of sleep has been reported to occur as long as one year after the initiation of treatment. Falling asleep while engaged in activities of daily living usually occurs in patients experiencing pre-existing somnolence, although some patients may not give such a history. For this reason, prescribers should reassess patients for drowsiness or sleepiness especially since some of the events occur well after the start of treatment.
Prescribers should be aware that patients may not acknowledge drowsiness or sleepiness until directly questioned about drowsiness or sleepiness during specific activities. Patients should be advised to exercise caution while driving or operating machines during treatment with ca… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The most common adverse reactions reported with carbidopa and levodopa have included dyskinesias, such as choreiform, dystonic, and other involuntary movements, and nausea. The following other adverse reactions have been reported with carbidopa and levodopa: Body as a Whole Chest pain, asthenia. Cardiovascular Cardiac irregularities, hypotension, orthostatic effects including orthostatic hypotension, hypertension, syncope, phlebitis, palpitation.
Gastrointestinal Dark saliva, gastrointestinal bleeding, development of duodenal ulcer, anorexia, vomiting, diarrhea, constipation, dyspepsia, dry mouth, taste alterations. Hematologic Agranulocytosis, hemolytic and non-hemolytic anemia, thrombocytopenia, leukopenia. Hypersensitivity Angioedema, urticaria, pruritus, Henoch-Schönlein purpura, bullous lesions (including pemphigus-like reactions).
Musculoskeletal Back pain, shoulder pain, muscle cramps. Nervous System/Psychiatric Psychotic episodes including delusions, hallucinations, and paranoid ideation, bradykinetic episodes ("on-off" phenomenon), confusion, agitation, dizziness, somnolence, dream abnormalities including nightmares, insomnia, paresthesia, headache, depression with or without development of suicidal tendencies, dementia, pathological gambling, increased libido including hypersexuality, impulse control symptoms, seizures (including convulsions).
Respiratory Dyspnea, upper respiratory infection. Skin Rash, increased sweating, alopecia, dark sweat. Urogenital Urinary tract infection, urinary frequency, dark urine.
Laboratory Tests Decreased hemoglobin and hematocrit; abnormalities in alkaline phosphatase, SGOT (AST), SGPT (ALT), LDH, bilirubin, BUN, Coombs test; elevated serum glucose; white blood cells, bacteria, and blood in the urine. Other adverse reactions that have been reported with levodopa alone and with various carbidopa and levodopa formulations, and may occur with carbidopa and levodopa are: Body as a Whole Abdominal pain and distress, fatigue. Cardiovascular Myocardial infarction.
Gastrointestinal Gastrointestinal pain, dysphagia, sialorrhea, flatulence, bruxism, burning sensation of the tongue, heartburn, hiccups. Metabolic Edema, weight gain, weight loss. Musculoskeletal Leg pain.
Nervous System/Psychiatric Ataxia, extrapyramidal disorder, falling, anxiety, gait abnormalities, nervousness, decreased mental acuity, memory impairment, disorientation, euphoria, blepharospasm (which may be taken as an early sign of excess dosage; consideration of dosage reduction may be made at this time), trismus, increased tremor, numbness, muscle twitching, activation of latent Horner's syndrome, peripheral neuropathy. Respiratory Pharyngeal pain, cough. Skin Malignant melanoma, flushing.
Special Senses Oculogyric crises, diplopia, blurred vision, dilated pupils. Urogenital Urinary retention, urinary incontinence, priapism. Miscellaneous Bizarre breathing patterns, faintness, hoarseness, malaise, hot flashes, sense of stimulation.
Laboratory Tests Decreased white blood cell count and serum potassium; increased serum creatinine and uric acid; protein and glucose in urine; decreased vitamin B 6 levels.
🔄 Drug Interactions ▾
Drug Interactions Caution should be exercised when the following drugs are administered concomitantly with carbidopa and levodopa. Symptomatic postural hypotension occurred when carbidopa and levodopa was added to the treatment of a patient receiving antihypertensive drugs. Therefore, when therapy with carbidopa and levodopa is started, dosage adjustment of the antihypertensive drug may be required.
For patients receiving MAO inhibitors (Type A or B), see CONTRAINDICATIONS . Concomitant therapy with selegiline and carbidopa and levodopa may be associated with severe orthostatic hypotension not attributable to carbidopa and levodopa alone (see CONTRAINDICATIONS ). There have been rare reports of adverse reactions, including hypertension and dyskinesia, resulting from the concomitant use of tricyclic antidepressants and carbidopa and levodopa.
Dopamine D 2 receptor antagonists (e.g., phenothiazines, butyrophenones, risperidone) and isoniazid may reduce the therapeutic effects of levodopa. In addition, the beneficial effects of levodopa in Parkinson's disease have been reported to be reversed by phenytoin and papaverine. Patients taking these drugs with carbidopa and levodopa should be carefully observed for loss of therapeutic response.
Use of carbidopa and levodopa with dopamine-depleting agents (e.g., reserpine and tetrabenazine) or other drugs known to deplete monoamine stores is not recommended. Carbidopa and levodopa and iron salts or multivitamins containing iron salts should be coadministered with caution. Iron salts can form chelates with levodopa and carbidopa and consequently reduce the bioavailability of carbidopa and levodopa.
Although metoclopramide may increase the bioavailability of levodopa by increasing gastric emptying, metoclopramide may also adversely affect disease control by its dopamine receptor antagonistic properties.
🤰 Pregnancy ▾
Pregnancy No teratogenic effects were observed in a study in mice receiving up to 20 times the maximum recommended human dose of carbidopa and levodopa. There was a decrease in the number of live pups delivered by rats receiving approximately two times the maximum recommended human dose of carbidopa and approximately five times the maximum recommended human dose of levodopa during organogenesis. Carbidopa and levodopa caused both visceral and skeletal malformations in rabbits at all doses and ratios of carbidopa/levodopa tested, which ranged from 10 times/5 times the maximum recommended human dose of carbidopa/levodopa to 20 times/10 times the maximum recommended human dose of carbidopa/levodopa.
There are no adequate or well-controlled studies in pregnant women. It has been reported from individual cases that levodopa crosses the human placental barrier, enters the fetus, and is metabolized. Carbidopa concentrations in fetal tissue appeared to be minimal.
Use of carbidopa and levodopa in women of childbearing potential requires that the anticipated benefits of the drug be weighed against possible hazards to mother and child.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in pediatric patients have not been established. Use of the drug in patients below the age of 18 is not recommended.
🧓 Geriatric Use ▾
Geriatric Use In the clinical efficacy trials for carbidopa and levodopa, almost half of the patients were older than 65, but few were older than 75. No overall meaningful differences in safety or effectiveness were observed between these subjects and younger subjects, but greater sensitivity of some older individuals to adverse drug reactions such as hallucinations cannot be ruled out. There is no specific dosing recommendation based upon clinical pharmacology data as carbidopa and levodopa is titrated as tolerated for clinical effect.
🆘 Overdosage ▾
OVERDOSAGE Management of acute overdosage with carbidopa and levodopa is the same as management of acute overdosage with levodopa. Pyridoxine is not effective in reversing the actions of carbidopa and levodopa. General supportive measures should be employed, along with immediate gastric lavage.
Intravenous fluids should be administered judiciously and an adequate airway maintained. Electrocardiographic monitoring should be instituted and the patient carefully observed for the development of arrhythmias; if required, appropriate antiarrhythmic therapy should be given. The possibility that the patient may have taken other drugs as well as carbidopa and levodopa should be taken into consideration.
To date, no experience has been reported with dialysis; hence, its value in overdosage is not known. Based on studies in which high doses of levodopa and/or carbidopa were administered, a significant proportion of rats and mice given single oral doses of levodopa of approximately 1500 to 2000 mg/kg are expected to die. A significant proportion of infant rats of both sexes are expected to die at a dose of 800 mg/kg.
A significant proportion of rats are expected to die after treatment with similar doses of carbidopa. The addition of carbidopa in a 1:10 ratio with levodopa increases the dose at which a significant proportion of mice are expected to die to 3360 mg/kg.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Parkinson's disease is a progressive, neurodegenerative disorder of the extrapyramidal nervous system affecting the mobility and control of the skeletal muscular system. Its characteristic features include resting tremor, rigidity, and bradykinetic movements. Symptomatic treatments, such as levodopa therapies, may permit the patient better mobility.
Current evidence indicates that symptoms of Parkinson's disease are related to depletion of dopamine in the corpus striatum. Administration of dopamine is ineffective in the treatment of Parkinson's disease apparently because it does not cross the blood-brain barrier. However, levodopa, the metabolic precursor of dopamine, does cross the blood-brain barrier, and presumably is converted to dopamine in the brain.
This is thought to be the mechanism whereby levodopa relieves symptoms of Parkinson's disease. Pharmacodynamics When levodopa is administered orally, it is rapidly decarboxylated to dopamine in extracerebral tissues so that only a small portion of a given dose is transported unchanged to the central nervous system. For this reason, large doses of levodopa are required for adequate therapeutic effect, and these may often be accompanied by nausea and other adverse reactions, some of which are attributable to dopamine formed in extracerebral tissues.
Since levodopa competes with certain amino acids for transport across the gut wall, the absorption of levodopa may be impaired in some patients on a high protein diet. Carbidopa inhibits decarboxylation of peripheral levodopa. It does not cross the blood-brain barrier and does not affect the metabolism of levodopa within the central nervous system.
The incidence of levodopa-induced nausea and vomiting is less with carbidopa and levodopa than with levodopa. In many patients, this reduction in nausea and vomiting will permit more rapid dosage titration. Since its decarboxylase inhibiting activity is limited to extracerebral tissues, administration of carbidopa with levodopa makes more levodopa available for transport to the brain.
Pharmacokinetics Carbidopa reduces the amount of levodopa required to produce a given response by about 75% and, when administered with levodopa, increases both plasma levels and the plasma half-life of levodopa, and decreases plasma and urinary dopamine and homovanillic acid. The plasma half-life of levodopa is about 50 minutes, without carbidopa. When carbidopa and levodopa are administered together, the half-life of levodopa is increased to about 1.5 hours.
At steady state, the bioavailability of carbidopa from carbidopa and levodopa tablets is approximately 99% relative to the concomitant administration of carbidopa and levodopa. In clinical pharmacologic studies, simultaneous administration of carbidopa and levodopa produced greater urinary excretion of levodopa in proportion to the excretion of dopamine than administration of the two drugs at separate times. Pyridoxine hydrochloride (vitamin B 6 ), in oral doses of 10 mg to 25 mg, may reverse the effects of levodopa by increasing the rate of aromatic amino acid decarboxylation.
Carbidopa inhibits this action of pyridoxine; therefore, carbidopa and levodopa can be given to patients receiving supplemental pyridoxine (vitamin B 6 ). Special Populations Geriatric: A study in eight young healthy subjects (21 to 22 yr) and eight elderly healthy subjects (69 to 76 yr) showed that the absolute bioavailability of levodopa was similar between young and elderly subjects following oral administration of levodopa and carbidopa. However, the systemic exposure (AUC) of levodopa was increased by 55% in elderly subjects compared to young subjects.
Based on another study in forty patients with Parkinson’s disease, there was a correlation between age of patients and the increase of AUC of levodopa following administration of levodopa and an inhibitor of peripheral dopa decarboxylase. AUC of levodopa was increased by 28% in elder… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Carbidopa and Levodopa Tablets USP, 25 mg/100 mg are yellow to light yellow color, round shaped, uncoated tablets debossed with “CA 25” on one side and “LT I00” on the other side. They are supplied as follows: Bottles of 100 NDC 59651-457-01 Bottles of 500 NDC 59651-457-05 Bottles of 1000 NDC 59651-457-99 Carbidopa and Levodopa Tablets USP, 10 mg/100 mg are blue to light blue color, round shaped, uncoated tablets debossed with “CA I0” on one side and “LT I00” on the other side. They are supplied as follows: Bottles of 100 NDC 59651-456-01 Bottles of 500 NDC 59651-456-05 Carbidopa and Levodopa Tablets USP, 25 mg/250 mg are blue to light blue color, round shaped, uncoated tablets debossed with “CA 25” on one side and “LT 250” on the other side.
They are supplied as follows: Bottles of 100 NDC 59651-458-01 Bottles of 500 NDC 59651-458-05 Bottles of 1000 NDC 59651-458-99 Storage and Handling Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature]. Store in a tightly closed container, protected from light and moisture. Dispense in a tightly closed, light-resistant container.
Distributed by: Aurobindo Pharma USA, Inc. 279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 032, India Revised: 04/2026
📋 Description ▾
DESCRIPTION Carbidopa and levodopa tablets, USP are a combination of carbidopa and levodopa for the treatment of Parkinson's disease and syndrome. Carbidopa USP, an inhibitor of aromatic amino acid decarboxylation, is a white to creamy white powder, freely soluble in 3N hydrochloric acid, slightly soluble in water and methanol, practically insoluble in alcohol, acetone, ether and chloroform, with a molecular weight of 244.3. It is designated chemically as (—)-L-α-hydrazino-α-methyl-β-(3,4-dihydroxybenzene) propanoic acid monohydrate.
Its molecular formula is C 10 H 14 N 2 O 4 •H 2 O, and its structural formula is: Tablet content is expressed in terms of anhydrous carbidopa which has a molecular weight of 226.3. Levodopa USP, an aromatic amino acid, is a white to off-white, crystalline powder, slightly soluble in water, freely soluble in 3N hydrochloric acid, insoluble in alcohol, with a molecular weight of 197.2. It is designated chemically as (—)-L-α-amino-β-(3,4-dihydroxybenzene) propanoic acid.
Its molecular formula is C 9 H 11 NO 4 , and its structural formula is: Carbidopa and levodopa is supplied as tablets for oral administration in three strengths: Carbidopa and levodopa tablets USP, 25 mg/100 mg containing 25 mg of carbidopa USP and 100 mg of levodopa USP. Carbidopa and levodopa tablets USP, 10 mg/100 mg containing 10 mg of carbidopa USP and 100 mg of levodopa USP. Carbidopa and levodopa tablets USP, 25 mg/250 mg containing 25 mg of carbidopa USP and 250 mg of levodopa USP.
Inactive ingredients are crospovidone, hydroxypropyl cellulose, magnesium stearate, microcrystalline cellulose, and pregelatinized starch (maize). Carbidopa and levodopa tablets USP, 10 mg/100 mg and 25 mg/250 mg also contain FD&C Blue No.2 Aluminum Lake. Carbidopa and levodopa tablets USP, 25 mg/100 mg also contain D&C Yellow No.10.
FDA approved dissolution test specifications differ from USP. chemical structure 1 chemical structure 2
💬 Information for Patients ▾
Information for Patients The patient should be informed that carbidopa and levodopa is an immediate-release formulation of carbidopa and levodopa that is designed to begin release of ingredients within 30 minutes. It is important that carbidopa and levodopa be taken at regular intervals according to the schedule outlined by the physician. The patient should be cautioned not to change the prescribed dosage regimen and not to add any additional antiparkinson medications, including other carbidopa and levodopa preparations, without first consulting the physician.
Patients should be advised that sometimes a ‘wearing-off’ effect may occur at the end of the dosing interval. The physician should be notified if such response poses a problem to lifestyle. Patients should be advised that occasionally, dark color (red, brown, or black) may appear in saliva, urine, or sweat after ingestion of carbidopa and levodopa.
Although the color appears to be clinically insignificant, garments may become discolored. The patient should be advised that a change in diet to foods that are high in protein may delay the absorption of levodopa and may reduce the amount taken up in the circulation. Excessive acidity also delays stomach emptying, thus delaying the absorption of levodopa.
Iron salts (such as in multivitamin tablets) may also reduce the amount of levodopa available to the body. The above factors may reduce the clinical effectiveness of the levodopa or carbidopa and levodopa therapy. Patients should be alerted to the possibility of sudden onset of sleep during daily activities, in some cases without awareness or warning signs, when they are taking dopaminergic agents, including levodopa.
Patients should be advised to exercise caution while driving or operating machinery and that if they have experienced somnolence and/or sudden sleep onset, they must refrain from these activities. (See WARNINGS , Falling Asleep During Activities of Daily Living and Somnolence .) There have been reports of patients experiencing intense urges to gamble, increased sexual urges, and other intense urges, and the inability to control these urges while taking one or more of the medications that increase central dopaminergic tone and that are generally used for the treatment of Parkinson’s disease, including carbidopa and levodopa.
Although it is not proven that the medications caused these events, these urges were reported to have stopped in some cases when the dose was reduced or the medication was stopped. Prescribers should ask patients about the development of new or increased gambling urges, sexual urges or other urges while being treated with carbidopa and levodopa. Patients should inform their physician if they experience new or increased gambling urges, increased sexual urges, or other intense urges while taking carbidopa and levodopa.
Physicians should consider dose reduction or stopping the medication if a patient develops such urges while taking carbidopa and levodopa (See PRECAUTIONS , Impulse Control / Compulsive Behaviors ). Inform patients that vitamin B 6 deficiency may develop during treatment with carbidopa/levodopa therapies, including carbidopa and levodopa. Tell patients to inform their healthcare provider if they develop symptoms such as depression, confusion, cheilosis, glossitis, dermatitis, anemia, neuropathy, and/or seizures (See WARNINGS, Vitamin B6 Deficiency and Seizures ).
⚠️ Precautions ▾
PRECAUTIONS General As with levodopa, periodic evaluations of hepatic, hematopoietic, cardiovascular, and renal function are recommended during extended therapy. Patients with chronic wide-angle glaucoma may be treated cautiously with carbidopa and levodopa provided the intraocular pressure is well-controlled and the patient is monitored carefully for changes in intraocular pressure during therapy. Dyskinesia Levodopa alone, as well as carbidopa and levodopa, is associated with dyskinesias.
The occurrence of dyskinesias may require dosage reduction. Hallucinations / Psychotic-Like Behavior Hallucinations and psychotic-like behavior have been reported with dopaminergic medications. In general, hallucinations present shortly after the initiation of therapy and may be responsive to dose reduction in levodopa.
Hallucinations may be accompanied by confusion and to a lesser extent sleep disorder (insomnia) and excessive dreaming. Carbidopa and levodopa may have similar effects on thinking and behavior. This abnormal thinking and behavior may present with one or more symptoms, including paranoid ideation, delusions, hallucinations, confusion, psychotic-like behavior, disorientation, aggressive behavior, agitation, and delirium.
Ordinarily, patients with a major psychotic disorder should not be treated with carbidopa and levodopa, because of the risk of exacerbating psychosis. In addition, certain medications used to treat psychosis may exacerbate the symptoms of Parkinson’s disease and may decrease the effectiveness of carbidopa and levodopa. Impulse Control / Compulsive Behaviors Reports of patients taking dopaminergic medications (medications that increase central dopaminergic tone), suggest that patients may experience an intense urge to gamble, increased sexual urges, intense urges to spend money, binge eating, and/or other intense urges, and the inability to control these urges.
In some cases, although not all, these urges were reported to have stopped when the dose was reduced or the medication was discontinued. Because patients may not recognize these behaviors as abnormal, it is important for prescribers to specifically ask patients or the caregivers about the development of new or increased gambling urges, sexual urges, uncontrolled spending or other urges while being treated with carbidopa and levodopa. Physicians should consider dose reduction or stopping the medication if a patient develops such urges while taking carbidopa and levodopa [see Information for Patients ].
Melanoma Epidemiological studies have shown that patients with Parkinson’s disease have a higher risk (2- to approximately 6-fold higher) of developing melanoma than the general population. Whether the increased risk observed was due to Parkinson’s disease or other factors, such as drugs used to treat Parkinson’s disease, is unclear. For the reasons stated above, patients and providers are advised to monitor for melanomas frequently and on a regular basis when using carbidopa and levodopa for any indication.
Ideally, periodic skin examinations should be performed by appropriately qualified individuals (e.g., dermatologists). Information for Patients The patient should be informed that carbidopa and levodopa is an immediate-release formulation of carbidopa and levodopa that is designed to begin release of ingredients within 30 minutes. It is important that carbidopa and levodopa be taken at regular intervals according to the schedule outlined by the physician.
The patient should be cautioned not to change the prescribed dosage regimen and not to add any additional antiparkinson medications, including other carbidopa and levodopa preparations, without first consulting the physician. Patients should be advised that sometimes a ‘wearing-off’ effect may occur at the end of the dosing interval. The physician should be notified if such response poses a problem to lifestyle.
Patients should be advised that occasionally, dark color (red, brown, or black) may appear… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Levodopa has been detected in human milk. Caution should be exercised when carbidopa and levodopa is administered to a nursing woman.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility In a two-year bioassay of carbidopa and levodopa, no evidence of carcinogenicity was found in rats receiving doses of approximately two times the maximum daily human dose of carbidopa and four times the maximum daily human dose of levodopa. In reproduction studies with carbidopa and levodopa, no effects on fertility were found in rats receiving doses of approximately two times the maximum daily human dose of carbidopa and four times the maximum daily human dose of levodopa.
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 10 mg/100 mg (100 Tablets Bottle) NDC 59651-456-01 Carbidopa and Levodopa Tablets, USP 10 mg/100 mg Rx only 100 Tablets AUROBINDO PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 10 mg/100 mg (100 Tablets Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 25 mg/100 mg (100 Tablets Bottle) NDC 59651-457-01 Carbidopa and Levodopa Tablets, USP 25 mg/100 mg Rx only 100 Tablets AUROBINDO PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 25 mg/100 mg (100 Tablets Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 25 mg/250 mg (100 Tablets Bottle) NDC 59651-458-01 Carbidopa and Levodopa Tablets, USP 25 mg/250 mg Rx only 100 Tablets AUROBINDO PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 25 mg/250 mg (100 Tablets Bottle)