
ambrisentan 10 mg Tablet, Film Coated, 30-count — NDC 59651-495-30 (Billing 59651-0495-30)
This is a package of 30 tablets of ambrisentan 10 mg Tablet, Film Coated from Aurobindo Pharma Limited, marketed since Jul 2022 and currently FDA-listed; retail pharmacies pay about $8.02 per tablet (NADAC). It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 062793
- GCN: 98567
- GPI-14 (Medi-Span): 40160007000320
- HICL (First Databank): 034849
- AHFS class code: 24:12.92.00
- RxCUI (RxNorm): 722116
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Endothelin Receptor Antagonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Ambrisentan won't cure PAH, but it can make a real difference in how you feel and function. It works by blocking a protein called ET-1 that causes the blood vessels in your lungs t...
- What exactly does ambrisentan do, and will it cure my PAH?
- Good news — food doesn't affect how well your body absorbs ambrisentan, so you can take it with or without a meal, whichever works best for your routine. Pick a time of day you can...
- Can I take ambrisentan with food, and does it matter what time of day I take it?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Ambrisentan — tap one for details:
Ambrisentan may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $8.025 | $240.74 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | $17.61 | $528.38 / 30 tablets |
| Medicare drug plans payPart D · Q2 2026 | $87.47 | $2,624.22 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 59651-0495-30 You're viewing this Main listing | 30 TABLET, FILM COATED in 1 BOTTLE | 2022-07-21 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ambrisentan 10 mg 00378-4271-93 | Mylan | 30 tablets | $8.025 | AB | Availability likely | — |
| Ambrisentan 10 mg 00591-2406-30 | Actavis | 30 tablets | $8.025 | AB | Availability likely | — |
| Ambrisentan 10 mg 42794-0052-08 | Sigmapharm | 30 tablets | $8.025 | AB | Availability likely | — |
| ambrisentan 10 mgthis 59651-0495-30 | Aurobindo | 30 tablets | $8.025 | AB | Availability likely | — |
| Ambrisentan 10 mg 60505-4553-03 | Apotex | 30 tablets | $8.025 | AB | Availability likely | — |
| Ambrisentan 10 mg 69097-0387-02 | Cipla | 30 tablets | $8.025 | AB | Availability likely | — |
| Ambrisentan 10 mg 82009-0142-30 | Quallent | 30 tablets | $8.025 | AB | Availability likely | — |
| ambrisentan 10 mg 47335-0237-64 | Sun | 10 tablets | — | — | FDA listed | — |
| ambrisentan 10 mg 50090-7670-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Ambrisentan 10 mg 51407-0595-30 | Golden | 30 tablets | — | AB | FDA listed | — |
| Letairis 10 mg 61958-0802-01 | Gilead | 30 tablets | — | AB | FDA listed | — |
| Ambrisentan 10 mg 70710-1180-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Ambrisentan 10 mg 70771-1364-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: EMBRYO-FETAL TOXICITY Ambrisentan is contraindicated for use during pregnancy because it may cause major birth defects if used by pregnant patients, based on studies in animals [see Contraindications (4.1) , Warnings and Precautions (5.1) , and Use in Specific Populations (8.1) ]. Therefore, for females of reproductive potential, exclude pregnancy before the initiation of treatment with ambrisentan. Advise use of effective contraception before initiation, during treatment, and for one month after treatment with ambrisentan [see Dosage and Administration (2.2) Contraindications (4.1) , Warnings and Precautions (5.1) , and Use in Specific Populations (8.1 , 8.3) ].
When pregnancy is detected, discontinue ambrisentan as soon as possible ( 5.1 ). WARNING: EMBRYO-FETAL TOXICITY See full prescribing information for complete boxed warning. Based on animal data ambrisentan may cause fetal harm if used during pregnancy ( 4.1 , 5.1 , 8.1 ).
Females of reproductive potential: Exclude pregnancy before the start of treatment. Use effective contraception prior to initiation of treatment, during treatment, and for one month after treatment with ambrisentan ( 2.2 , 4.1 , 5.1 , 8.1 , 8.3 ) When pregnancy is detected, discontinue ambrisentan as soon as possible ( 5.1 ).
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Ambrisentan tablets are indicated for the treatment of pulmonary arterial hypertension (PAH) (WHO Group 1) in adult patients: To improve exercise ability and delay clinical worsening. Studies establishing effectiveness included predominantly patients with WHO Functional Class II to III symptoms and etiologies of idiopathic or heritable PAH (60%) or PAH associated with connective tissue diseases (34%). Ambrisentan is an endothelin receptor antagonist indicated for the treatment of pulmonary arterial hypertension (PAH) (WHO Group 1) in adult patients: To improve exercise ability and delay clinical worsening.
Studies establishing effectiveness included trials predominantly in patients with WHO Functional Class II to III symptoms and etiologies of idiopathic or heritable PAH (60%) or PAH associated with connective tissue diseases (34%) ( 1 ).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Initiate treatment at 5 mg once daily ( 2.1 ). • Titrate at 4-week intervals as needed and tolerated ( 2.1 ). • Do not split, crush, or chew tablets ( 2.1 ).
2.1Adult Dosage Initiate treatment at 5 mg once daily. At 4-week intervals, the dose of ambrisentan tablets can be increased, as needed and tolerated, to 10 mg. Do not split, crush, or chew tablets.
2.2Pregnancy Testing in Females of Reproductive Potential Exclude pregnancy before initiating treatment with ambrisentan tablets in females of reproductive potential [see Warnings and Precautions (5.1), Use in Specific Populations (8.1 , 8.3) ].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 5 mg and 10 mg film-coated tablets for oral administration • Each 5 mg tablet is pale pink, square shaped convex tablet debossed with “AS” on one side and “5” on other side. • Each 10 mg tablet is deep pink, oval shaped convex tablet debossed with “AS” on one side and “10” on other side. Tablet: 5 mg and 10 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Pregnancy ( 4.1 ) Idiopathic Pulmonary Fibrosis ( 4.2 )
4.1Pregnancy Ambrisentan tablets may cause fetal harm when administered to a pregnant female. Ambrisentan tablets are contraindicated in females who are pregnant. Ambrisentan tablets were consistently shown to have teratogenic effects when administered to animals.
If this drug is used during pregnancy, or if the patient becomes pregnant while taking this drug, the patient should be apprised of the potential hazard to a fetus [see Dosage and Administration (2.2) , Warnings and Precautions (5.1) , and Use in Specific Populations (8.1) ].
4.2Idiopathic Pulmonary Fibrosis Ambrisentan tablets are contraindicated in patients with Idiopathic Pulmonary Fibrosis (IPF), including IPF patients with pulmonary hypertension (WHO Group 3) [see Clinical Studies (14.4) ] .
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Fluid retention may require intervention ( 5.2 ). If patients develop acute pulmonary edema during initiation of therapy with ambrisentan, consider underlying pulmonary veno-occlusive disease and discontinue treatment if necessary ( 5.3 ). Decreases in sperm count have been observed in patients taking endothelin receptor antagonists ( 5.4 ).
Decreases in hemoglobin have been observed within the first few weeks; measure hemoglobin at initiation, at 1 month, and periodically thereafter ( 5.5 ).
5.1Embryo-fetal Toxicity Based on data from animal reproduction studies, ambrisentan may cause fetal harm when administered during pregnancy and is contraindicated during pregnancy. The available human data for endothelin receptor antagonists do not establish the presence or absence of major birth defects related to the use of ambrisentan. Advise patients who can become pregnant of the potential risk to a fetus.
Obtain a pregnancy test prior to initiation of treatment with ambrisentan. Advise patients who can become pregnant to use effective contraception prior to initiation of treatment, during treatment, and for one month after discontinuation of treatment with ambrisentan. When pregnancy is detected, discontinue use as soon as possible [see Dosage and Administration (2.2) , and Use in Specific Populations (8.1 , 8.3) ].
5.2Fluid Retention Peripheral edema is a known class effect of endothelin receptor antagonists, and is also a clinical consequence of PAH and worsening PAH. In the placebo-controlled studies, there was an increased incidence of peripheral edema in patients treated with doses of 5 mg or 10 mg ambrisentan compared to placebo [see Adverse Reactions (6.1) ] . Most edema was mild to moderate in severity.
In addition, there have been postmarketing reports of fluid retention in patients with pulmonary hypertension, occurring within weeks after starting ambrisentan. Patients required intervention with a diuretic, fluid management, or, in some cases, hospitalization for decompensating heart failure. If clinically significant fluid retention develops, with or without associated weight gain, further evaluation should be undertaken to determine the cause, such as ambrisentan or underlying heart failure, and the possible need for specific treatment or discontinuation of ambrisentan therapy.
5.3Pulmonary Edema with Pulmonary Veno-occlusive Disease (PVOD) If patients develop acute pulmonary edema during initiation of therapy with vasodilating agents such as ambrisentan, the possibility of PVOD should be considered, and if confirmed ambrisentan should be discontinued.
5.4Decreased Sperm Counts Decreased sperm counts have been observed in human and animal studies with another endothelin receptor antagonist and in animal fertility studies with ambrisentan. Ambrisentan may have an adverse effect on spermatogenesis [see Use in Specific Populations (8.6) and Nonclinical Toxicology (13.1) ] .
5.5Hematological Changes Decreases in hemoglobin concentration and hematocrit have followed administration of other endothelin receptor antagonists and were observed in clinical studies with ambrisentan. These decreases were observed within the first few weeks of treatment with ambrisentan, and stabilized thereafter. The mean decrease in hemoglobin from baseline to end of treatment for those patients receiving ambrisentan in the 12-week placebo-controlled studies was 0.8 g/dL.
Marked decreases in hemoglobin (>15% decrease from baseline resulting in a value below the lower limit of normal) were observed in 7% of all patients receiving ambrisentan (and 10% of patients receiving 10 mg) compared to 4% of patients receiving placebo. The cause of the decrease in hemoglobin is unknown, but it does not appear to result from hemorrhage or hemolysis. In the long-term open-label extension of the two pivotal clinical studies, mean decreases from baseline (ranging from 0.9 to 1.2 g/dL) in hemoglobin concentrations persisted for up to… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Clinically significant adverse reactions that appear in other sections of the labeling include: Embryo-fetal Toxicity [see Warnings and Precautions (5.1) , Use in Specific Populations (8.1) ] Fluid Retention [see Warnings and Precautions (5.2) ] Pulmonary Edema with PVOD [see Warnings and Precautions (5.3) ] Decreased Sperm Count [see Warnings and Precautions (5.4) ] Hematologic Changes [see Warnings and Precautions (5.5) ] Most common adverse reactions (>3% compared to placebo) are peripheral edema, nasal congestion, sinusitis, and flushing ( 6.1 ).
To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Safety data for ambrisentan are presented from two 12-week, placebo-controlled studies (ARIES-1 and ARIES-2) in patients with pulmonary arterial hypertension (PAH). The exposure to ambrisentan in these studies ranged from 6 days to 100 days.
In ARIES-1 and ARIES-2, a total of 261 patients received ambrisentan at doses of 2.5 mg, 5 mg, or 10 mg once daily and 132 patients received placebo. The adverse reactions that occurred in >3% more patients receiving ambrisentan than receiving placebo are shown in Table 1. Table 1 Adverse Reactions with Placebo-Adjusted Rates >3% in ARIES-1 and ARIES-2 Placebo (N=132) Ambrisentan (N=261) Adverse Reaction n (%) n (%) Placebo-adjusted (%) Peripheral edema 14 (11) 45 (17) 6 Nasal congestion 2 (2) 15 (6) 4 Sinusitis 0 (0) 8 (3) 3 Flushing 1 (1) 10 (4) 3 Most adverse drug reactions were mild to moderate and only nasal congestion was dose-dependent.
Few notable differences in the incidence of adverse reactions were observed for patients by age or sex. Peripheral edema was similar in younger patients (<65 years) receiving ambrisentan (14%; 29/205) or placebo (13%; 13/104), and was greater in elderly patients ( > 65 years) receiving ambrisentan (29%; 16/56) compared to placebo (4%; 1/28). The results of such subgroup analyses must be interpreted cautiously.
The incidence of treatment discontinuations due to adverse events other than those related to PAH during the clinical trials in patients with PAH was similar for ambrisentan (2%; 5/261 patients) and placebo (2%; 3/132 patients). The incidence of patients with serious adverse events other than those related to PAH during the clinical trials in patients with PAH was similar for placebo (7%; 9/132 patients) and for ambrisentan (5%; 13/261 patients). During 12-week controlled clinical trials, the incidence of aminotransferase elevations >3 x upper limit of normal (ULN) were 0% on ambrisentan and 2.3% on placebo.
In practice, cases of hepatic injury should be carefully evaluated for cause. Use in Patients with Prior Endothelin Receptor Antagonist (ERA) Related Serum Liver Enzyme Abnormalities In an uncontrolled, open-label study, 36 patients who had previously discontinued endothelin receptor antagonists (ERAs: bosentan, an investigational drug, or both) due to aminotransferase elevations >3 x ULN were treated with ambrisentan. Prior elevations were predominantly moderate, with 64% of the ALT elevations <5 x ULN, but 9 patients had elevations >8 x ULN.
Eight patients had been re-challenged with bosentan and/or the investigational ERA and all eight had a recurrence of aminotransferase abnormalities that required discontinuation of ERA therapy. All patients had to have normal aminotransferase levels on entry to this study. Twenty-five of the 36 patients were also receiving prostanoid and/or phosphodiesterase type 5 (PDE5) inhibitor therapy.
Two patients discontinued early (including one of the patients with a prior 8 x ULN elevation). Of the remaining 34 p… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Multiple dose coadministration of ambrisentan and cyclosporine resulted in an approximately 2-fold increase in ambrisentan exposure in healthy volunteers; therefore, limit the dose of ambrisentan to 5 mg once daily when coadministered with cyclosporine [see Clinical Pharmacology (12.3) ] . Cyclosporine increases ambrisentan exposure; limit ambrisentan dose to 5 mg once daily ( 7 ).
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Breastfeeding: Choose ambrisentan or breastfeeding ( 8.2 ). Not recommended in patients with moderate or severe hepatic impairment ( 8.7 ).
8.1Pregnancy Risk Summary Based on data from animal reproduction studies, ambrisentan may cause fetal harm, including birth defects and fetal death, when administered to a pregnant woman and is contraindicated during pregnancy. There are limited data on ambrisentan use in pregnant women. Available data from postmarketing reports and published literature over decades of use with endothelin receptor antagonists in the same class as ambrisentan have not identified an increased risk of major birth defects; however, these data are limited.
Methodological limitations of these postmarketing reports and published literature include lack of a control group; limited information regarding dose, duration, and timing of drug exposure; and missing data. These limitations preclude establishing a reliable estimate of the risk of adverse fetal and neonatal outcomes with maternal endothelin receptor antagonist use. In animal reproduction studies, ambrisentan was teratogenic in rats and rabbits at doses which resulted in exposures of 3.5 and 1.7 times, respectively, the human dose of 10 mg per day [see Animal Data] .
If this drug is used during pregnancy, or if the patient becomes pregnant while taking this drug, advise the patient of the potential hazard to a fetus [see Contraindications (4.1) , Warnings and Precautions (5.1) ] . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Ambrisentan was teratogenic at oral dosages of ≥15 mg/kg/day (AUC 51.7 h•mcg/mL) in rats and ≥7 mg/kg/day (24.7 h•mcg/mL) in rabbits; it was not studied at lower dosages. These dosages are of 3.5 and 1.7 times, respectively, the human dose of 10 mg per day (14.8 h•mcg/mL) based on AUC.
In both species, there were abnormalities of the lower jaw and hard and soft palate, malformation of the heart and great vessels, and failure of formation of the thymus and thyroid. A preclinical study in rats has shown decreased survival of newborn pups (mid and high dosages) and effects on testicle size and fertility of pups (high dosage) following maternal treatment with ambrisentan from late gestation through weaning. The mid and high dosages were 51 x, and 170 x (on a mg/m 2 body surface area basis) the maximum oral human dose of 10 mg and an average adult body weight of 70 kg.
These effects were absent at a maternal dosage 17 x the human dose based on mg/m 2 .
8.2Lactation Risk Summary It is not known whether ambrisentan is present in human milk. Because many drugs are present in human milk and because of the potential for serious adverse reactions in breastfed infants from ambrisentan, a decision should be made whether to discontinue breastfeeding or discontinue ambrisentan, taking into account the importance of the drug to the mother.
8.3Females and Males of Reproductive Potential Based on data from animal reproductive toxicity studies, ambrisentan may cause fetal harm, including birth defects and fetal death, when administered to a pregnant patient and is contraindicated during pregnancy [see Contraindications (4.1) , Use in Specific Populations (8.1) ]. Pregnancy Testing Verify that patients who can become pregnant are not pregnant prior to initiating ambrisentan. The patient should contact their physician immediately for pregnancy testing if onset of menses is delayed or pregnancy is suspected.
If the pregnancy test is positive, the physician and patient should discuss the risks to the pregnancy and the fetus. Contraception Patients who can become pregnant who are using… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on data from animal reproduction studies, ambrisentan may cause fetal harm, including birth defects and fetal death, when administered to a pregnant woman and is contraindicated during pregnancy. There are limited data on ambrisentan use in pregnant women. Available data from postmarketing reports and published literature over decades of use with endothelin receptor antagonists in the same class as ambrisentan have not identified an increased risk of major birth defects; however, these data are limited.
Methodological limitations of these postmarketing reports and published literature include lack of a control group; limited information regarding dose, duration, and timing of drug exposure; and missing data. These limitations preclude establishing a reliable estimate of the risk of adverse fetal and neonatal outcomes with maternal endothelin receptor antagonist use. In animal reproduction studies, ambrisentan was teratogenic in rats and rabbits at doses which resulted in exposures of 3.5 and 1.7 times, respectively, the human dose of 10 mg per day [see Animal Data] .
If this drug is used during pregnancy, or if the patient becomes pregnant while taking this drug, advise the patient of the potential hazard to a fetus [see Contraindications (4.1) , Warnings and Precautions (5.1) ] . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Ambrisentan was teratogenic at oral dosages of ≥15 mg/kg/day (AUC 51.7 h•mcg/mL) in rats and ≥7 mg/kg/day (24.7 h•mcg/mL) in rabbits; it was not studied at lower dosages. These dosages are of 3.5 and 1.7 times, respectively, the human dose of 10 mg per day (14.8 h•mcg/mL) based on AUC.
In both species, there were abnormalities of the lower jaw and hard and soft palate, malformation of the heart and great vessels, and failure of formation of the thymus and thyroid. A preclinical study in rats has shown decreased survival of newborn pups (mid and high dosages) and effects on testicle size and fertility of pups (high dosage) following maternal treatment with ambrisentan from late gestation through weaning. The mid and high dosages were 51 x, and 170 x (on a mg/m 2 body surface area basis) the maximum oral human dose of 10 mg and an average adult body weight of 70 kg.
These effects were absent at a maternal dosage 17 x the human dose based on mg/m 2 .
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of ambrisentan in pediatric patients have not been established. Juvenile Animal Data In juvenile rats administered ambrisentan orally once daily during postnatal day 7 to 26, 36, or 62, a decrease in brain weight (−3% to −8%) with no morphologic or neurobehavioral changes occurred after breathing sounds, apnea, and hypoxia were observed, at exposures approximately 1.8 to 7.0 times human pediatric exposures at 10 mg, based on AUC.
🧓 Geriatric Use ▾
8.5Geriatric Use In the two placebo-controlled clinical studies of ambrisentan, 21% of patients were ≥65 years old and 5% were ≥75 years old. The elderly (age ≥65 years) showed less improvement in walk distances with ambrisentan than younger patients did, but the results of such subgroup analyses must be interpreted cautiously. Peripheral edema was more common in the elderly than in younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE There is no experience with overdosage of ambrisentan. The highest single dose of ambrisentan administered to healthy volunteers was 100 mg, and the highest daily dose administered to patients with PAH was 10 mg once daily. In healthy volunteers, single doses of 50 mg and 100 mg (5 to 10 times the maximum recommended dose) were associated with headache, flushing, dizziness, nausea, and nasal congestion.
Massive overdosage could potentially result in hypotension that may require intervention.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Endothelin-1 (ET-1) is a potent autocrine and paracrine peptide. Two receptor subtypes, ET A and ET B , mediate the effects of ET-1 in the vascular smooth muscle and endothelium. The primary actions of ET A are vasoconstriction and cell proliferation, while the predominant actions of ET B are vasodilation, antiproliferation, and ET-1 clearance.
In patients with PAH, plasma ET-1 concentrations are increased as much as 10-fold and correlate with increased mean right atrial pressure and disease severity. ET-1 and ET-1 mRNA concentrations are increased as much as 9-fold in the lung tissue of patients with PAH, primarily in the endothelium of pulmonary arteries. These findings suggest that ET-1 may play a critical role in the pathogenesis and progression of PAH.
Ambrisentan is a high-affinity (K i =0.011 nM) ET A receptor antagonist with a high selectivity for the ET A versus ET B receptor (>4000-fold). The clinical impact of high selectivity for ET A is not known.
12.2Pharmacodynamics Cardiac Electrophysiology In a randomized, positive- and placebo-controlled, parallel-group study, healthy subjects received either ambrisentan 10 mg daily followed by a single dose of 40 mg, placebo followed by a single dose of moxifloxacin 400 mg, or placebo alone. Ambrisentan 10 mg daily had no significant effect on the QTc interval. The 40 mg dose of ambrisentan increased mean QTc at t max by 5 ms with an upper 95% confidence limit of 9 ms.
For patients receiving ambrisentan 5 mg to 10 mg daily and not taking metabolic inhibitors, no significant QT prolongation is expected.
12.3Pharmacokinetics The pharmacokinetics of ambrisentan (S-ambrisentan) in healthy subjects is dose proportional. The absolute bioavailability of ambrisentan is not known. Ambrisentan is absorbed with peak concentrations occurring approximately 2 hours after oral administration in healthy subjects and PAH patients.
Food does not affect its bioavailability. In vitro studies indicate that ambrisentan is a substrate of P-gp. Ambrisentan is highly bound to plasma proteins (99%).
The elimination of ambrisentan is predominantly by non-renal pathways, but the relative contributions of metabolism and biliary elimination have not been well characterized. In plasma, the AUC of 4-hydroxymethyl ambrisentan accounts for approximately 4% relative to parent ambrisentan AUC. The in vivo inversion of S-ambrisentan to R-ambrisentan is negligible.
The mean oral clearance of ambrisentan is 38 mL/min and 19 mL/min in healthy subjects and in PAH patients, respectively. Although ambrisentan has a 15-hour terminal half-life, the mean trough concentration of ambrisentan at steady-state is about 15% of the mean peak concentration and the accumulation factor is about 1.2 after long-term daily dosing, indicating that the effective half-life of ambrisentan is about 9 hours. Drug Interactions In Vitro Studies Studies with human liver tissue indicate that ambrisentan is metabolized by CYP3A, CYP2C19, and uridine 5’-diphosphate glucuronosyltransferases (UGTs) 1A9S, 2B7S, and 1A3S.
In vitro studies suggest that ambrisentan is a substrate of the Organic Anion Transporting Polypeptides OATP1B1 and OATP1B3, and P-glycoprotein (P-gp). Drug interactions might be expected because of these factors; however, a clinically relevant interaction has been demonstrated only with cyclosporine [see Drug Interactions (7) ] . In vitro studies found ambrisentan to have little to no inhibition of human hepatic transporters.
Ambrisentan demonstrated weak dose-dependent inhibition of OATP1B1, OATP1B3, and NTCP (IC 50 of 47 μM, 45 μM, and approximately 100 μM, respectively) and no transporter-specific inhibition of BSEP, BRCP, P-gp, or MRP2. Ambrisentan does not inhibit or induce drug metabolizing enzymes at clinically relevant concentrations. In Vivo Studies The effects of other drugs on ambrisentan pharmacokinetics and the effects of ambrisentan on the exposure to other drugs a… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Endothelin-1 (ET-1) is a potent autocrine and paracrine peptide. Two receptor subtypes, ET A and ET B , mediate the effects of ET-1 in the vascular smooth muscle and endothelium. The primary actions of ET A are vasoconstriction and cell proliferation, while the predominant actions of ET B are vasodilation, antiproliferation, and ET-1 clearance.
In patients with PAH, plasma ET-1 concentrations are increased as much as 10-fold and correlate with increased mean right atrial pressure and disease severity. ET-1 and ET-1 mRNA concentrations are increased as much as 9-fold in the lung tissue of patients with PAH, primarily in the endothelium of pulmonary arteries. These findings suggest that ET-1 may play a critical role in the pathogenesis and progression of PAH.
Ambrisentan is a high-affinity (K i =0.011 nM) ET A receptor antagonist with a high selectivity for the ET A versus ET B receptor (>4000-fold). The clinical impact of high selectivity for ET A is not known.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Ambrisentan Tablets 5 mg are pale pink, film-coated, square shaped convex tablets debossed with “AS” on one side and “5” on other side and are supplied as follows: Bottles of 30 NDC 59651-494-30 Ambrisentan Tablets 10 mg are deep pink, film-coated, oval shaped convex tablets debossed with “AS” on one side and “10” on other side and are supplied as follows: Bottles of 30 NDC 59651-495-30 Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature].
Store ambrisentan tablets in its original packaging.
📋 Description ▾
11 DESCRIPTION Ambrisentan tablets contain ambrisentan, an endothelin receptor antagonist. The chemical name of ambrisentan is (+)-(2 S )-2-[(4,6-dimethylpyrimidin-2-yl)oxy]-3-methoxy-3,3-diphenylpropanoic acid. It has a molecular formula of C 22 H 22 N 2 O 4 and a molecular weight of 378.42 and has the following structural formula: Figure 1 Ambrisentan Structural Formula Ambrisentan is a white to light yellow crystalline powder.
It is a carboxylic acid with a pKa of 4.0. Ambrisentan is freely soluble in THF, sparingly soluble in ethyl acetate, slightly soluble in ethanol, practically insoluble in n-hexane and water. In the solid state ambrisentan is very stable, is not hygroscopic, and is not light sensitive.
Ambrisentan is available as 5 mg and 10 mg film-coated tablets for once daily oral administration. The tablets include the following inactive ingredients: croscarmellose sodium, lactose monohydrate, magnesium stearate and microcrystalline cellulose. The tablets are film-coated with a coating material containing FD&C Red #40, lecithin (soya), polyethylene glycol, polyvinyl alcohol-part hydrolyzed, talc, and titanium dioxide.
Each square, pale pink ambrisentan tablet contains 5 mg of ambrisentan. Each oval, deep pink ambrisentan tablet contains 10 mg of ambrisentan. Ambrisentan tablets are unscored. ambrisentan-str.jpg
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients to read the FDA-approved patient labeling ( Medication Guide ). Embryo-fetal Toxicity Instruct patients on the risk of fetal harm when ambrisentan is used in pregnancy [see Warnings and Precautions (5.1) and Use in Specific Populations (8.1) ] . Instruct females of reproductive potential to immediately contact their physician if they suspect they may be pregnant.
Educate and counsel patients who can become pregnant about the need to use effective contraception prior to treatment with ambrisentan tablets, during treatment, and for one month after treatment discontinuation [see Warnings and Precautions (5.1) and Use in Specific Populations (8.1 , 8.3) ] . Patients who can become pregnant should have a negative pregnancy test prior to treatment with ambrisentan tablets [see Dosage and Administration (2.2) , Contraindications (4.1) , Warnings and Precautions (5.1) , Use in Specific Populations (8.1 , 8.3) ] .
Counsel patients who can become pregnant about pregnancy planning and prevention, including emergency contraception, or designate counseling by another healthcare provider trained in contraceptive counseling [see Boxed Warning ]. Hepatic Effects Advise patients of the symptoms of potential liver injury and instruct them to report any of these symptoms to their physician. Hematological Change Advise patients of the importance of hemoglobin testing.
Other Risks Associated with Ambrisentan Instruct patients that the risks associated with ambrisentan also include the following: Decreases in sperm count Fluid overload Administration Advise patients not to split, crush, or chew tablets. Distributed by: Aurobindo Pharma USA, Inc. 279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 032, India Revised: 04/2025 The brands listed are trademarks of their respective owners and are not trademarks of Aurobindo Pharma Limited.
💬 Medication Guide ▾
Medication Guide Ambrisentan (am" bri sen' tan) Tablets Read this Medication Guide before you start taking ambrisentan tablets and each time you get a refill. There may be new information. This Medication Guide does not take the place of talking with your doctor about your medical condition or your treatment.
What is the most important information I should know about ambrisentan tablets? Serious birth defects. Ambrisentan tablets can cause serious birth defects if taken during pregnancy.
Females should not be pregnant when they start taking ambrisentan tablets or become pregnant during treatment with ambrisentan tablets . Females who are able to get pregnant should have a negative pregnancy test before beginning treatment with ambrisentan tablets. Talk to your doctor about your menstrual cycle.
Your doctor will decide when to do a pregnancy test, and will order a pregnancy test for you depending on your menstrual cycle. Females who are able to get pregnant are females who: have entered puberty, even if they have not started their menstrual period, and have a uterus, and have not gone through menopause. Menopause means that you have not had a menstrual period for at least 12 months for natural reasons, or that you have had your ovaries removed.
Females who are not able to get pregnant are females who: have not yet entered puberty, or do not have a uterus, or have gone through menopause. Menopause means that you have not had a menstrual period for at least 12 months for natural reasons, or that you have had your ovaries removed, or who are infertile for any other medical reason and this infertility is permanent and cannot be reversed Females who are able to get pregnant should use effective contraception before beginning ambrisentan tablets, during treatment with ambrisentan tablets, and for one month after stopping ambrisentan tablets because the medicine may still be in the body.
Talk with your doctor or gynecologist (a doctor who specializes in female reproduction) to find out about options for acceptable forms of birth control that you may use to prevent pregnancy during treatment with ambrisentan tablets. If you decide that you want to change the form of birth control that you use, talk with your doctor or gynecologist to be sure that you choose another acceptable form of birth control. Do not have unprotected sex.
Talk to your doctor or pharmacist right away if you have unprotected sex or if you think your birth control has failed. Your doctor may tell you to use emergency birth control. Tell your doctor right away if you miss a menstrual period or think you may be pregnant for any reason.
If you are the parent or caregiver of a female child who started taking ambrisentan tablets before reaching puberty, you should check your child regularly to see if she is developing signs of puberty. Tell your doctor right away if you notice that she is developing breast buds or pubic hair. Your doctor should decide if your child has reached puberty.
Your child may reach puberty before having her first menstrual period. What are ambrisentan tablets? Ambrisentan tablets are a prescription medicine used to treat pulmonary arterial hypertension (PAH), which is high blood pressure in the arteries of your lungs.
Ambrisentan tablets can improve your ability to exercise and it can help slow down the worsening of your physical condition and symptoms. It is not known if ambrisentan tablets are safe and effective in children. Who should not take ambrisentan tablets?
Do not take ambrisentan tablets if: you are pregnant, plan to become pregnant, or become pregnant during treatment with ambrisentan tablets. Ambrisentan tablets can cause serious birth defects . (See “What is the most important information I should know about ambrisentan tablets?”) you have a condition called Idiopathic Pulmonary Fibrosis (IPF) What should I tell my doctor before taking ambrisentan tablets?
Before you take ambrisentan tablets, tell your doctor if you : have been told… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
8.3Females and Males of Reproductive Potential Based on data from animal reproductive toxicity studies, ambrisentan may cause fetal harm, including birth defects and fetal death, when administered to a pregnant patient and is contraindicated during pregnancy [see Contraindications (4.1) , Use in Specific Populations (8.1) ]. Pregnancy Testing Verify that patients who can become pregnant are not pregnant prior to initiating ambrisentan. The patient should contact their physician immediately for pregnancy testing if onset of menses is delayed or pregnancy is suspected.
If the pregnancy test is positive, the physician and patient should discuss the risks to the pregnancy and the fetus. Contraception Patients who can become pregnant who are using ambrisentan should use effective contraception prior to initiation of treatment, during treatment, and for one month after discontinuation of treatment with ambrisentan to prevent pregnancy [see Warnings and Precautions (5.1) ]. Infertility Males In a 6-month study of another endothelin receptor antagonist, bosentan, 25 male patients with WHO functional class III and IV PAH and normal baseline sperm count were evaluated for effects on testicular function.
There was a decline in sperm count of at least 50% in 25% of the patients after 3 or 6 months of treatment with bosentan. One patient developed marked oligospermia at 3 months, and the sperm count remained low with 2 follow-up measurements over the subsequent 6 weeks. Bosentan was discontinued and after 2 months the sperm count had returned to baseline levels.
In 22 patients who completed 6 months of treatment, sperm count remained within the normal range and no changes in sperm morphology, sperm motility, or hormone levels were observed. Based on these findings and preclinical data [see Nonclinical Toxicology (13.1) ] from endothelin receptor antagonists, it cannot be excluded that endothelin receptor antagonists such as ambrisentan have an adverse effect on spermatogenesis. Counsel patients about the potential effects on fertility [see Warnings and Precautions (5.5) ] .
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetics of ambrisentan (S-ambrisentan) in healthy subjects is dose proportional. The absolute bioavailability of ambrisentan is not known. Ambrisentan is absorbed with peak concentrations occurring approximately 2 hours after oral administration in healthy subjects and PAH patients.
Food does not affect its bioavailability. In vitro studies indicate that ambrisentan is a substrate of P-gp. Ambrisentan is highly bound to plasma proteins (99%).
The elimination of ambrisentan is predominantly by non-renal pathways, but the relative contributions of metabolism and biliary elimination have not been well characterized. In plasma, the AUC of 4-hydroxymethyl ambrisentan accounts for approximately 4% relative to parent ambrisentan AUC. The in vivo inversion of S-ambrisentan to R-ambrisentan is negligible.
The mean oral clearance of ambrisentan is 38 mL/min and 19 mL/min in healthy subjects and in PAH patients, respectively. Although ambrisentan has a 15-hour terminal half-life, the mean trough concentration of ambrisentan at steady-state is about 15% of the mean peak concentration and the accumulation factor is about 1.2 after long-term daily dosing, indicating that the effective half-life of ambrisentan is about 9 hours. Drug Interactions In Vitro Studies Studies with human liver tissue indicate that ambrisentan is metabolized by CYP3A, CYP2C19, and uridine 5’-diphosphate glucuronosyltransferases (UGTs) 1A9S, 2B7S, and 1A3S.
In vitro studies suggest that ambrisentan is a substrate of the Organic Anion Transporting Polypeptides OATP1B1 and OATP1B3, and P-glycoprotein (P-gp). Drug interactions might be expected because of these factors; however, a clinically relevant interaction has been demonstrated only with cyclosporine [see Drug Interactions (7) ] . In vitro studies found ambrisentan to have little to no inhibition of human hepatic transporters.
Ambrisentan demonstrated weak dose-dependent inhibition of OATP1B1, OATP1B3, and NTCP (IC 50 of 47 μM, 45 μM, and approximately 100 μM, respectively) and no transporter-specific inhibition of BSEP, BRCP, P-gp, or MRP2. Ambrisentan does not inhibit or induce drug metabolizing enzymes at clinically relevant concentrations. In Vivo Studies The effects of other drugs on ambrisentan pharmacokinetics and the effects of ambrisentan on the exposure to other drugs are shown in Figure 2 and Figure 3, respectively.
Figure 2 Effects of Other Drugs on Ambrisentan Pharmacokinetics * Omeprazole: based on population pharmacokinetic analysis in PAH patients ** Rifampin: AUC and C max were measured at steady-state. On Day 3 of coadministration a transient 2-fold increase in AUC was noted that was no longer evident by Day 7. Day 7 results are presented.
Figure 3 Effects of Ambrisentan on Other Drugs * Active metabolite of mycophenolate mofetil ** GMR (95% CI) for INR ambrisentan-fig1.jpg ambrisentan-fig2.jpg
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Cardiac Electrophysiology In a randomized, positive- and placebo-controlled, parallel-group study, healthy subjects received either ambrisentan 10 mg daily followed by a single dose of 40 mg, placebo followed by a single dose of moxifloxacin 400 mg, or placebo alone. Ambrisentan 10 mg daily had no significant effect on the QTc interval. The 40 mg dose of ambrisentan increased mean QTc at t max by 5 ms with an upper 95% confidence limit of 9 ms.
For patients receiving ambrisentan 5 mg to 10 mg daily and not taking metabolic inhibitors, no significant QT prolongation is expected.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Pulmonary Arterial Hypertension (PAH) Two 12-week, randomized, double-blind, placebo-controlled, multicenter studies were conducted in 393 patients with PAH (WHO Group 1). The two studies were identical in design except for the doses of ambrisentan and the geographic region of the investigational sites. ARIES-1 compared once-daily doses of 5 mg and 10 mg ambrisentan to placebo, while ARIES-2 compared once-daily doses of 2.5 mg and 5 mg ambrisentan to placebo.
In both studies, ambrisentan or placebo was added to current therapy, which could have included a combination of anticoagulants, diuretics, calcium channel blockers, or digoxin, but not epoprostenol, treprostinil, iloprost, bosentan, or sildenafil. The primary study endpoint was 6-minute walk distance. In addition, clinical worsening, WHO functional class, dyspnea, and SF-36 ® Health Survey were assessed.
Patients had idiopathic or heritable PAH (64%) or PAH associated with connective tissue diseases (32%), HIV infection (3%), or anorexigen use (1%). There were no patients with PAH associated with congenital heart disease. Patients had WHO functional class I (2%), II (38%), III (55%), or IV (5%) symptoms at baseline.
The mean age of patients was 50 years, 79% of patients were female, and 77% were Caucasian. Submaximal Exercise Ability Results of the 6-minute walk distance at 12 weeks for the ARIES-1 and ARIES-2 studies are shown in Table 3 and Figure 4. Table 3 Changes from Baseline in 6-Minute Walk Distance (meters) (ARIES-1 and ARIES-2) ARIES-1 ARIES-2 Placebo (N=67) 5 mg (N=67) 10 mg (N=67) Placebo (N=65) 2.5 mg (N=64) 5 mg (N=63) Baseline 342 ± 73 340 ± 77 342 ± 78 343 ± 86 347 ± 84 355 ± 84 Mean change from baseline -8 ± 79 23 ± 83 44 ± 63 -10 ± 94 22 ± 83 49 ± 75 Placebo-adjusted mean change from baseline _ 31 51 _ 32 59 Placebo-adjusted median change from baseline _ 27 39 _ 30 45 p-value a _ 0.008 <0.001 _ 0.022 <0.001 Mean ± standard deviation a p-values are Wilcoxon rank sum test comparisons of ambrisentan to placebo at Week 12 stratified by idiopathic or heritable PAH and non-idiopathic, non-heritable PAH patients Figure 4 Mean Change in 6-Minute Walk Distance (ARIES-1 and ARIES-2) Mean change from baseline in 6-minute walk distance in the placebo and ambrisentan groups.
Values are expressed as mean ± standard error of the mean. In both studies, treatment with ambrisentan resulted in a significant improvement in 6-minute walk distance for each dose of ambrisentan and the improvements increased with dose. An increase in 6-minute walk distance was observed after 4 weeks of treatment with ambrisentan, with a dose-response observed after 12 weeks of treatment.
Improvements in walk distance with ambrisentan were smaller for elderly patients (age > 65) than younger patients and for patients with secondary PAH than for patients with idiopathic or heritable PAH. The results of such subgroup analyses must be interpreted cautiously. Clinical Worsening Time to clinical worsening of PAH was defined as the first occurrence of death, lung transplantation, hospitalization for PAH, atrial septostomy, study withdrawal due to the addition of other PAH therapeutic agents, or study withdrawal due to early escape.
Early escape was defined as meeting two or more of the following criteria: a 20% decrease in the 6-minute walk distance; an increase in WHO functional class; worsening right ventricular failure; rapidly progressing cardiogenic, hepatic, or renal failure; or refractory systolic hypotension. The clinical worsening events during the 12-week treatment period of the ambrisentan clinical trials are shown in Table 4 and Figure 5. Table 4 Time to Clinical Worsening (ARIES-1 and ARIES-2) ARIES-1 ARIES-2 Placebo (N=67) Ambrisentan (N=134) Placebo (N=65) Ambrisentan (N=127) Clinical worsening, no.
(%) 7 (10%) 4 (3%) 13 (22%) 8 (6%) Hazard ratio - 0.28 - 0.30 p-value, Log-rank test - 0.030 - 0.005 Intention-to-treat population. Note: Patients may have had more… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Oral carcinogenicity studies of up to two years duration were conducted at starting doses of 10, 30, and 60 mg/kg/day in rats (8 to 48 times the maximum recommended human dose [MRHD] on a mg/m 2 basis) and at 50, 150, and 250 mg/kg/day in mice (28 to 140 times the MRHD). In the rat study, the high- and mid-dose male and female groups had their doses lowered to 40 and 20 mg/kg/day, respectively, in week 51 because of effects on survival. The high-dose males and females were taken off drug completely in weeks 69 and 93, respectively.
The only evidence of ambrisentan-related carcinogenicity was a positive trend in male rats, for the combined incidence of benign basal cell tumor and basal cell carcinoma of skin/subcutis in the mid-dose group (high-dose group excluded from analysis), and the occurrence of mammary fibroadenomas in males in the high-dose group. In the mouse study, high-dose male and female groups had their doses lowered to 150 mg/kg/day in week 39 and were taken off drug completely in week 96 (males) or week 76 (females). In mice, ambrisentan was not associated with excess tumors in any dosed group.
Positive findings of clastogenicity were detected, at drug concentrations producing moderate to high toxicity, in the chromosome aberration assay in cultured human lymphocytes. There was no evidence for genetic toxicity of ambrisentan when tested in vitro in bacteria (Ames test) or in vivo in rats (micronucleus assay, unscheduled DNA synthesis assay). The development of testicular tubular atrophy and impaired fertility has been linked to the chronic administration of endothelin receptor antagonists in rodents.
Testicular tubular degeneration was observed in rats treated with ambrisentan for two years at doses > 10 mg/kg/day (8-fold MRHD). Increased incidences of testicular findings were also observed in mice treated for two years at doses > 50 mg/kg/day (28-fold MRHD). Effects on sperm count, sperm morphology, mating performance, and fertility were observed in fertility studies in which male rats were treated with ambrisentan at oral doses of 300 mg/kg/day (236-fold MRHD).
At doses of > 10 mg/kg/day, observations of testicular histopathology in the absence of fertility and sperm effects were also present.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Oral carcinogenicity studies of up to two years duration were conducted at starting doses of 10, 30, and 60 mg/kg/day in rats (8 to 48 times the maximum recommended human dose [MRHD] on a mg/m 2 basis) and at 50, 150, and 250 mg/kg/day in mice (28 to 140 times the MRHD). In the rat study, the high- and mid-dose male and female groups had their doses lowered to 40 and 20 mg/kg/day, respectively, in week 51 because of effects on survival. The high-dose males and females were taken off drug completely in weeks 69 and 93, respectively.
The only evidence of ambrisentan-related carcinogenicity was a positive trend in male rats, for the combined incidence of benign basal cell tumor and basal cell carcinoma of skin/subcutis in the mid-dose group (high-dose group excluded from analysis), and the occurrence of mammary fibroadenomas in males in the high-dose group. In the mouse study, high-dose male and female groups had their doses lowered to 150 mg/kg/day in week 39 and were taken off drug completely in week 96 (males) or week 76 (females). In mice, ambrisentan was not associated with excess tumors in any dosed group.
Positive findings of clastogenicity were detected, at drug concentrations producing moderate to high toxicity, in the chromosome aberration assay in cultured human lymphocytes. There was no evidence for genetic toxicity of ambrisentan when tested in vitro in bacteria (Ames test) or in vivo in rats (micronucleus assay, unscheduled DNA synthesis assay). The development of testicular tubular atrophy and impaired fertility has been linked to the chronic administration of endothelin receptor antagonists in rodents.
Testicular tubular degeneration was observed in rats treated with ambrisentan for two years at doses > 10 mg/kg/day (8-fold MRHD). Increased incidences of testicular findings were also observed in mice treated for two years at doses > 50 mg/kg/day (28-fold MRHD). Effects on sperm count, sperm morphology, mating performance, and fertility were observed in fertility studies in which male rats were treated with ambrisentan at oral doses of 300 mg/kg/day (236-fold MRHD).
At doses of > 10 mg/kg/day, observations of testicular histopathology in the absence of fertility and sperm effects were also present.
📄 Recent Major Changes ▾
Box Warning 4/2025 Indications and Usage ( 1 ) 4/2025 Dosage and Administration, Pregnancy Testing in Females of Reproductive Potential ( 2.2 ) 4/2025 Warnings and Precautions for Use Embryo-fetal Toxicity ( 5.1 ) 4/2025 Ambrisentan Risk Evaluation and Mitigation Strategy (REMS) ( 5.2 ) (removed) 4/2025
📄 Package Label / Principal Display Panel ▾
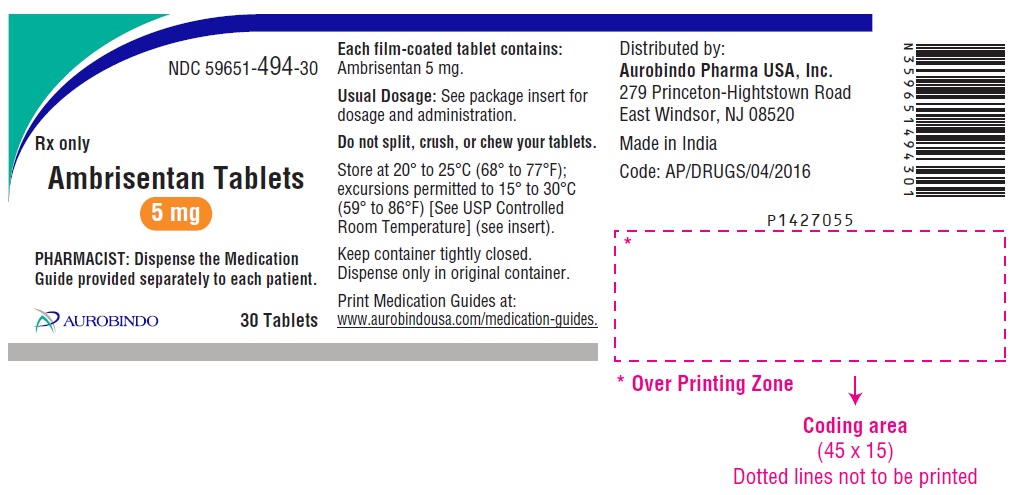
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 5 mg Container Label (30 Tablets Bottle) NDC 59651-494-30 Rx only Ambrisentan Tablets 5 mg PHARMACIST: Dispense the Medication Guide provided separately to each patient. AUROBINDO 30 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 5 mg Container Label (30 Tablets Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 10 mg Container Label (30 Tablets Bottle) NDC 59651-495-30 Rx only Ambrisentan Tablets 10 mg PHARMACIST: Dispense the Medication Guide provided separately to each patient. AUROBINDO 30 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 10 mg Container Label (30 Tablets Bottle)