
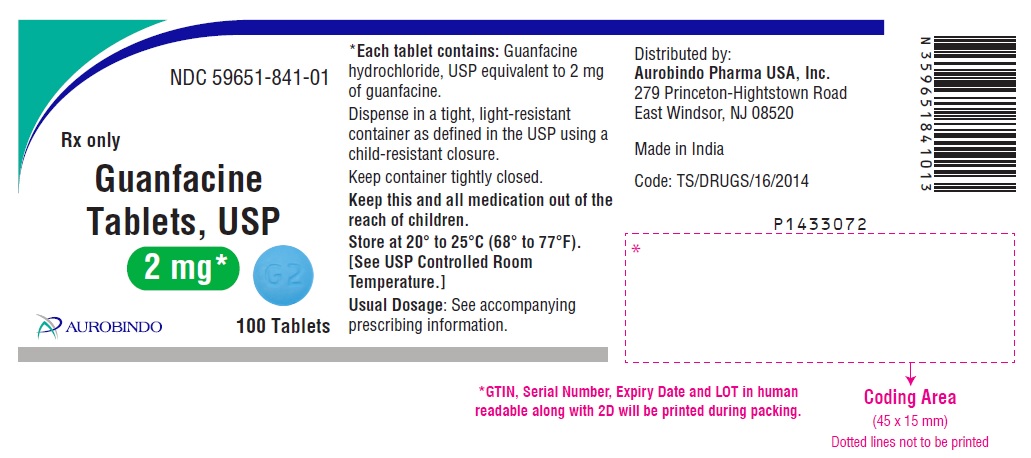
Guanfacine 2 mg Tablet, 100-count — NDC 59651-841-01 (Billing 59651-0841-01)
This is a package of 100 tablets of Guanfacine 2 mg Tablet from Aurobindo Pharma Limited, marketed since Aug 2023 and currently FDA-listed; retail pharmacies pay about $0.2673 per tablet (NADAC). It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 011984
- GCN: 32481
- GPI-14 (Medi-Span): 36201025100330
- HICL (First Databank): 000120
- AHFS class code: 24:24.00.00
- RxCUI (RxNorm): 197745
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Central alpha-2 Adrenergic Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It's used for both, depending on which form you have. The regular (immediate-release) tablet is prescribed for high blood pressure. The extended-release version — brand name Intuni...
- What is guanfacine actually used for — is it for ADHD or blood pressure?
- No, Intuniv is not a stimulant at all. It works on a different part of the brain than medications like Adderall or Ritalin. That's actually one reason it's sometimes used alongside...
- My child takes Intuniv for ADHD — is it a stimulant?
Patient education
Supplement & herbal interactions
Guanfacine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.267 | $26.73 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.4548 | $45.48 / 100 tablets |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 59651-0841-01 You're viewing this Main listing | 100 TABLET in 1 BOTTLE | 2023-08-07 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Guanfacine 2 mg 00591-0453-01 | Actavis | 100 tablets | $0.267 | — | Availability likely | — |
| Guanfacine Hydrochloride 2 mg 24979-0199-01 | TWi | 100 tablets | $0.267 | AB | Availability likely | — |
| Guanfacine 2 mg 27241-0243-01 | Ajanta | 100 tablets | $0.267 | AB | Availability likely | — |
| Guanfacine Hydrochloride 2 mg 29300-0459-01 | Unichem | 100 tablets | $0.267 | AB | Availability likely | — |
| Guanfacine 2 mg 42806-0296-01 | Epic | 100 tablets | $0.267 | AB | Availability likely | — |
| Guanfacine Hydrochloride 2 mg 50268-0374-15 | AvPAK | 50 tablets | $0.267 | AB | Availability likely | — |
| Guanfacine Hydrochloride 2 mg 53746-0713-01 | Amneal | 100 tablets | $0.267 | AB | Availability likely | — |
| Guanfacine 2 mgthis 59651-0841-01 | Aurobindo | 100 tablets | $0.267 | AB | Availability likely | — |
| Guanfacine Hydrochloride 2 mg 62135-0728-90 | Chartwell | 90 tablets | $0.267 | AB | Availability likely | — |
| Guanfacine Hydrochloride 2 mg 70700-0302-01 | XIROMED, | 100 tablets | $0.267 | AB | Availability likely | — |
| Guanfacine 2 mg 72319-0019-04 | i3 | 100 tablets | $0.267 | AB | Availability likely | — |
| Guanfacine Hydrochloride 2 mg 65162-0713-03 | Amneal | 30 tablets | — | AB | FDA listed | — |
| Guanfacine 2 mg 67046-1655-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Guanfacine Hydrochloride 2 mg 70518-3516-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Guanfacine 2 mg 70518-4488-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Guanfacine 2 mg 70518-4564-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Guanfacine Hydrochloride 2 mg 72603-0269-01 | NORTHSTAR | 100 tablets | — | AB | FDA listed | — |
| Guanfacine 2 mg 72888-0124-00 | Advagen | 1000 tablets | — | AB | FDA listed | — |
| Guanfacine 2 mg 73141-0019-04 | A2A | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Guanfacine tablets are indicated in the management of hypertension. Guanfacine tablets may be given alone or in combination with other antihypertensive agents, especially thiazide-type diuretics.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The recommended initial dose of guanfacine tablets when given alone or in combination with another antihypertensive drug is 1 mg daily given at bedtime to minimize somnolence. If after 3 to 4 weeks of therapy 1 mg does not give a satisfactory result, a dose of 2 mg may be given, although most of the effect of guanfacine tablets are seen at 1 mg (see CLINICAL PHARMACOLOGY ). Higher daily doses have been used, but adverse reactions increase significantly with doses above 3 mg/day.
The frequency of rebound hypertension is low, but it can occur. When rebound occurs, it does so after 2 to 4 days, which is delayed compared with clonidine hydrochloride. This is consistent with the longer half-life of guanfacine.
In most cases, after abrupt withdrawal of guanfacine, blood pressure returns to pretreatment levels slowly (within 2 to 4 days) without ill effects.
⛔ Contraindications ▾
CONTRAINDICATIONS Guanfacine tablets are contraindicated in patients with known hypersensitivity to guanfacine hydrochloride.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Adverse reactions noted with guanfacine hydrochloride are similar to those of other drugs of the central α 2 -adrenoreceptor agonist class: dry mouth, sedation (somnolence), weakness (asthenia), dizziness, constipation, and impotence. While the reactions are common, most are mild and tend to disappear on continued dosing. Skin rash with exfoliation has been reported in a few cases; although clear cause and effect relationships to guanfacine could not be established, should a rash occur, guanfacine should be discontinued and the patient monitored appropriately.
In the dose-response monotherapy study described under CLINICAL PHARMACOLOGY , the frequency of the most commonly observed adverse reactions showed a dose relationship from 0.5 mg to 3 mg as follows: Adverse Reaction Placebo n = 59 0.5 mg n = 60 1 mg n = 61 2 mg n = 60 3 mg n = 59 Dry Mouth 0% 10% 10% 42% 54% Somnolence 8% 5% 10% 13% 39% Asthenia 0% 2% 3% 7% 3% Dizziness 8% 12% 2% 8% 15% Headache 8% 13% 7% 5% 3% Impotence 0% 0% 0% 7% 3% Constipation 0% 2% 0% 5% 15% Fatigue 2% 2% 5% 8% 10% The percent of patients who dropped out because of adverse reactions are shown below for each dosage group.
Placebo 0.5 mg 1 mg 2 mg 3 mg Percent dropouts 0% 2% 5% 13% 32% The most common reasons for dropouts among patients who received guanfacine were dry mouth, somnolence, dizziness, fatigue, weakness, and constipation. In the 12-week, placebo-controlled, dose-response study of guanfacine administered with 25 mg chlorthalidone at bedtime, the frequency of the most commonly observed adverse reactions showed a clear dose relationship from 0.5 mg to 3 mg as follows: Adverse Reaction Placebo n = 73 0.5 mg n = 72 1 mg n = 72 2 mg n = 72 3 mg n = 72 Dry Mouth 5 (7%) 4 (5%) 6 (8%) 8 (11%) 20 (28%) Somnolence 1 (1%) 3 (4%) 0 (0%) 1 (1%) 10 (14%) Asthenia 0 (0%) 2 (3%) 0 (0%) 2 (2%) 7 (10%) Dizziness 2 (2%) 1 (1%) 3 (4%) 6 (8%) 3 (4%) Headache 3 (4%) 4 (3%) 3 (4%) 1 (1%) 2 (2%) Impotence 1 (1%) 1 (0%) 0 (0%) 1 (1%) 3 (4%) Constipation 0 (0%) 0 (0%) 0 (0%) 1 (1%) 1 (1%) Fatigue 3 (3%) 2 (3%) 2 (3%) 5 (6%) 3 (4%) There were 41 premature terminations because of adverse reactions in this study.
The percent of patients who dropped out and the dose at which the dropout occurred were as follows: Dose Placebo 0.5 mg 1 mg 2 mg 3 mg Percent dropouts 6.9% 4.2% 3.2% 6.9% 8.3% Reasons for dropouts among patients who received guanfacine were: somnolence, headache, weakness, dry mouth, dizziness, impotence, insomnia, constipation, syncope, urinary incontinence, conjunctivitis, paresthesia, and dermatitis. In a second 12-week, placebo-controlled combination therapy study in which the dose could be adjusted upward to 3 mg per day in 1 mg increments at 3-week intervals, i.e., a setting more similar to ordinary clinical use, the most commonly recorded reactions were: dry mouth, 47%; constipation, 16%; fatigue, 12%; somnolence, 10%; asthenia, 6%; dizziness, 6%; headache, 4%; and insomnia, 4%.
Reasons for dropouts among patients who received guanfacine were: somnolence, dry mouth, dizziness, impotence, constipation, confusion, depression, and palpitations. In the clonidine/guanfacine comparison described in CLINICAL PHARMACOLOGY , the most common adverse reactions noted were as follows: Adverse Reactions Guanfacine (n = 279) Clonidine (n = 278) Dry Mouth 30% 37% Somnolence 21% 35% Dizziness 11% 8% Constipation 10% 5% Fatigue 9% 8% Headache 4% 4% Insomnia 4% 3% Adverse reactions occurring in 3% or less of patients in the three controlled trials of guanfacine hydrochloride with a diuretic were: Cardiovascular: bradycardia, palpitations, substernal pain Gastrointestinal: abdominal pain, diarrhea, dyspepsia, dysphagia, nausea CNS: amnesia, confusion, depression, insomnia, libido decrease ENT disorders: rhinitis, taste perversion, tinnitus Eye disorders: conjunctivitis, iritis, vision disturbance Musculoskeletal: leg cramps, hypokinesia Respiratory: dyspnea Dermatologic: dermatitis, pruritus, purpura,… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
Drug Interactions The potential for increased sedation when guanfacine is given with other CNS-depressant drugs should be appreciated. The administration of guanfacine concomitantly with a known microsomal enzyme inducer (phenobarbital or phenytoin) to two patients with renal impairment reportedly resulted in significant reductions in elimination half-life and plasma concentration. In such cases, therefore, more frequent dosing may be required to achieve or maintain the desired hypotensive response.
Further, if guanfacine is to be discontinued in such patients, careful tapering of the dosage may be necessary in order to avoid rebound phenomena (see Rebound above). Anticoagulants: Ten patients who were stabilized on oral anticoagulants were given guanfacine, 1 to 2 mg/day, for 4 weeks. No changes were observed in the degree of anticoagulation.
In several well-controlled studies, guanfacine was administered together with diuretics with no drug interactions reported. In the long-term safety studies, guanfacine was given concomitantly with many drugs without evidence of any interactions. The principal drugs given (number of patients in parentheses) were: cardiac glycosides (115), sedatives and hypnotics (103), coronary vasodilators (52), oral hypoglycemics (45), cough and cold preparations (45), NSAIDs (38), antihyperlipidemics (29), antigout drugs (24), oral contraceptives (18), bronchodilators (13), insulin (10), and beta blockers (10).
🔄 Drug / Laboratory Test Interactions ▾
Drug/Laboratory Test Interactions No laboratory test abnormalities related to the use of guanfacine hydrochloride have been identified.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects. Pregnancy Category B: Administration of guanfacine to rats at 70 times the maximum recommended human dose and to rabbits at 20 times the maximum recommended human dose resulted in no evidence of harm to the fetus. Higher doses (100 and 200 times the maximum recommended human dose in rabbits and rats respectively) were associated with reduced fetal survival and maternal toxicity.
Rat experiments have shown that guanfacine crosses the placenta. There are, however, no adequate and well-controlled studies in pregnant women. Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in children under 12 years of age have not been demonstrated. Therefore, the use of guanfacine in this age group is not recommended. There have been spontaneous postmarketing reports of mania and aggressive behavioral changes in pediatric patients with attention-deficit hyperactivity disorder (ADHD) receiving guanfacine.
The reported cases were from a single center. All patients had medical or family risk factors for bipolar disorder. All patients recovered upon discontinuation of guanfacine hydrochloride.
Hallucinations have been reported in pediatric patients receiving guanfacine for treatment of attention-deficit hyperactivity disorder.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of guanfacine did not include sufficient numbers of subjects aged 65 and over to determine whether they responded differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal or cardiac function, and of concomitant disease or other drug therapy (see CLINICAL PHARMACOLOGY: Pharmacokinetics ).
🆘 Overdosage ▾
OVERDOSAGE Signs and Symptoms: Drowsiness, lethargy, bradycardia and hypotension have been observed following overdose with guanfacine. A 25-year-old female intentionally ingested 60 mg. She presented with severe drowsiness and bradycardia of 45 beats/minute.
Gastric lavage was performed and an infusion of isoproterenol (0.8 mg in 12 hours) was administered. She recovered quickly and without sequelae. A 28-year-old female who ingested 30 mg to 40 mg developed only lethargy, was treated with activated charcoal and a cathartic, was monitored for 24 hours, and was discharged in good health.
A 2-year-old male weighing 12 kg who ingested up to 4 mg of guanfacine developed lethargy. Gastric lavage (followed by activated charcoal and sorbitol slurry via NG tube) removed some tablet fragments within 2 hours after ingestion, and vital signs were normal. During 24-hour observation in ICU, systolic pressure was 58 and heart rate 70 at 16 hours post-ingestion.
No intervention was required, and the child was discharged fully recovered the next day. Treatment of Overdosage: Gastric lavage and supportive therapy as appropriate. Guanfacine is not dialyzable in clinically significant amounts (2.4%).
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Guanfacine hydrochloride is an orally active antihypertensive agent whose principal mechanism of action appears to be stimulation of central α 2 -adrenergic receptors. By stimulating these receptors, guanfacine reduces sympathetic nerve impulses from the vasomotor center to the heart and blood vessels. This results in a decrease in peripheral vascular resistance and a reduction in heart rate.
The dose-response relationship for blood pressure and adverse effects of guanfacine given once a day as monotherapy has been evaluated in patients with mild to moderate hypertension. In this study patients were randomized to placebo or to 0.5 mg, 1 mg, 2 mg, 3 mg or 5 mg of guanfacine. Results are shown in the following table.
A useful effect was not observed overall until doses of 2 mg were reached, although responses in white patients were seen at 1 mg; 24 hour effectiveness of 1 mg to 3 mg doses was documented using 24 hour ambulatory monitoring. While the 5 mg dose added an increment of effectiveness, it caused an unacceptable increase in adverse reactions. Mean Changes (mm Hg) from Baseline in Seated Systolic and Diastolic Blood Pressure for Patients Completing 4 to 8 Weeks of Treatment with Guanfacine Monotherapy Mean Change S/D* Seated n = (range) Placebo 0.5 mg 1 mg 2 mg 3 mg 5 mg White Patients 11 to 30 -1/-5 -6/-8 -8/-9 -12/-11 -15/-12 -18/-16 Black Patients 8 to 28 -3/-5 0/-2 -3/-5 -7/-7 -8/-9 -19/-15 *S/D = Systolic/diastolic blood pressure Controlled clinical trials in patients with mild to moderate hypertension who were receiving a thiazide-type diuretic have defined the dose-response relationship for blood pressure response and adverse reactions of guanfacine given at bedtime and have shown that the blood pressure response to guanfacine can persist for 24 hours after a single dose.
In the 12-week, placebo-controlled dose-response study, patients were randomized to placebo or to doses of 0.5 mg, 1 mg, 2 mg and 3 mg of guanfacine, in addition to 25 mg chlorthalidone, each given at bedtime. The observed mean changes from baseline, tabulated below, indicate the similarity of response for placebo and the 0.5 mg dose. Doses of 1 mg, 2 mg and 3 mg resulted in decreased blood pressure in the sitting position with no real differences among the three doses.
In the standing position, there was some increase in response with dose. Mean Decreases (mm Hg) in Seated and Standing Blood Pressure for Patients Treated with Guanfacine in Combination with Chlorthalidone Mean Change n = Placebo 63 0.5 mg 63 1 mg 64 2 mg 58 3 mg 59 SD* Seated -5/-7 -5/-6 -14/-13 -12/-13 -16/-13 SD* Standing -3/-5 -5/-4 -11/-9 -9/-10 -15/-12 *S/D = Systolic/diastolic blood pressure While most of the effectiveness of guanfacine in combination (and as monotherapy in white patients) was present at 1 mg, adverse reactions at this dose were not clearly distinguishable from those associated with placebo.
Adverse reactions were clearly present at 2 mg and 3 mg (see ADVERSE REACTIONS ). In a second 12-week placebo-controlled study of 1 mg, 2 mg or 3 mg of guanfacine hydrochloride administered with 25 mg of chlorthalidone once daily, a significant decrease in blood pressure was maintained for a full 24 hours after dosing. While there was no significant difference between the 12 and 24 hour blood pressure readings, the fall in blood pressure at 24 hours was numerically smaller, suggesting possible escape of blood pressure in some patients and the need for individualization of therapy.
In a double-blind, randomized trial, either guanfacine or clonidine was given at recommended doses with 25 mg chlorthalidone for 24 weeks and then abruptly discontinued. Results showed equal degrees of blood pressure reduction with the two drugs and there was no tendency for blood pressures to increase despite maintenance of the same daily dose of the two drugs. Signs and symptoms of rebound phenomena were infrequent upon discontinuation of either drug.
Abrupt withdrawal… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Guanfacine Tablets, USP are available containing guanfacine hydrochloride, USP equivalent to 1 mg or 2 mg of guanfacine. The 1 mg tablets are a white, round biconvex tablet debossed with “G1” on one side of the tablet and plain on the other side. They are available as follows: Bottles of 100 NDC 59651-840-01 The 2 mg tablets are a blue, round biconvex tablet debossed with “G2” on one side of the tablet and plain on the other side.
They are available as follows: Bottles of 100 NDC 59651-841-01 Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure. Distributed by: Aurobindo Pharma USA, Inc. 279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 032, India Revised: 07/2023
📋 Description ▾
DESCRIPTION Guanfacine hydrochloride is a centrally acting antihypertensive with α 2 -adrenoceptor agonist properties in tablet form for oral administration. The chemical name of guanfacine hydrochloride is N-amidino-2-(2,6-dichlorophenyl) acetamide hydrochloride and its molecular weight is 282.56. Its structural formula is: Guanfacine hydrochloride, USP is a white or off-white crystalline powder; sparingly soluble in water and alcohol and slightly soluble in acetone.
Each tablet, for oral administration, contains guanfacine hydrochloride equivalent to 1 mg or 2 mg of guanfacine and the following inactive ingredients: anhydrous lactose, colloidal silicon dioxide, magnesium stearate, microcrystalline cellulose and sodium lauryl sulfate. In addition, the 2 mg tablets contain the following ingredient: FD&C Blue No. 1 Aluminum Lake.
Chemical Structure
💬 Information for Patients ▾
Information for Patients Patients who receive guanfacine should be advised to exercise caution when operating dangerous machinery or driving motor vehicles until it is determined that they do not become drowsy or dizzy from the medication. Patients should be warned that their tolerance for alcohol and other CNS depressants may be diminished. Patients should be advised not to discontinue therapy abruptly.
⚠️ Precautions ▾
PRECAUTIONS General Like other antihypertensive agents, guanfacine hydrochloride should be used with caution in patients with severe coronary insufficiency, recent myocardial infarction, cerebrovascular disease, or chronic renal or hepatic failure. Sedation: Guanfacine, like other orally active central α 2 -adrenergic agonists, causes sedation or drowsiness, especially when beginning therapy. These symptoms are dose-related (see ADVERSE REACTIONS ).
When guanfacine is used with other centrally active depressants (such as phenothiazines, barbiturates, or benzodiazepines), the potential for additive sedative effects should be considered. Rebound: Abrupt cessation of therapy with orally active central α 2 -adrenergic agonists may be associated with increases (from depressed on-therapy levels) in plasma and urinary catecholamines, symptoms of “nervousness and anxiety” and, less commonly, increases in blood pressure to levels significantly greater than those prior to therapy.
Information for Patients Patients who receive guanfacine should be advised to exercise caution when operating dangerous machinery or driving motor vehicles until it is determined that they do not become drowsy or dizzy from the medication. Patients should be warned that their tolerance for alcohol and other CNS depressants may be diminished. Patients should be advised not to discontinue therapy abruptly.
Laboratory Tests In clinical trials, no clinically relevant laboratory test abnormalities were identified as causally related to drug during short-term treatment with guanfacine hydrochloride. Drug Interactions The potential for increased sedation when guanfacine is given with other CNS-depressant drugs should be appreciated. The administration of guanfacine concomitantly with a known microsomal enzyme inducer (phenobarbital or phenytoin) to two patients with renal impairment reportedly resulted in significant reductions in elimination half-life and plasma concentration.
In such cases, therefore, more frequent dosing may be required to achieve or maintain the desired hypotensive response. Further, if guanfacine is to be discontinued in such patients, careful tapering of the dosage may be necessary in order to avoid rebound phenomena (see Rebound above). Anticoagulants: Ten patients who were stabilized on oral anticoagulants were given guanfacine, 1 to 2 mg/day, for 4 weeks.
No changes were observed in the degree of anticoagulation. In several well-controlled studies, guanfacine was administered together with diuretics with no drug interactions reported. In the long-term safety studies, guanfacine was given concomitantly with many drugs without evidence of any interactions.
The principal drugs given (number of patients in parentheses) were: cardiac glycosides (115), sedatives and hypnotics (103), coronary vasodilators (52), oral hypoglycemics (45), cough and cold preparations (45), NSAIDs (38), antihyperlipidemics (29), antigout drugs (24), oral contraceptives (18), bronchodilators (13), insulin (10), and beta blockers (10). Drug/Laboratory Test Interactions No laboratory test abnormalities related to the use of guanfacine hydrochloride have been identified. Carcinogenesis, Mutagenesis, Impairment of Fertility No carcinogenic effect was observed in studies of 78 weeks in mice at doses more than 150 times the maximum recommended human dose and 102 weeks in rats at doses more than 100 times the maximum recommended human dose.
In a variety of test models, guanfacine was not mutagenic. No adverse effects were observed in fertility studies in male and female rats. Pregnancy Teratogenic Effects.
Pregnancy Category B: Administration of guanfacine to rats at 70 times the maximum recommended human dose and to rabbits at 20 times the maximum recommended human dose resulted in no evidence of harm to the fetus. Higher doses (100 and 200 times the maximum recommended human dose in rabbits and rats respectively) were associated with reduced fetal survival and maternal toxici… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers It is not known whether guanfacine hydrochloride is excreted in human milk. Because many drugs are excreted in human milk, caution should be exercised when guanfacine is administered to a nursing woman. Experiments with rats have shown that guanfacine is excreted in the milk.
🔒 Drug Abuse and Dependence ▾
DRUG ABUSE AND DEPENDENCE No reported abuse or dependence has been associated with the administration of guanfacine hydrochloride.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility No carcinogenic effect was observed in studies of 78 weeks in mice at doses more than 150 times the maximum recommended human dose and 102 weeks in rats at doses more than 100 times the maximum recommended human dose. In a variety of test models, guanfacine was not mutagenic. No adverse effects were observed in fertility studies in male and female rats.
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 1 mg (100 Tablets Bottle) NDC 59651-840-01 Rx only Guanfacine Tablets, USP 1 mg* G1 AUROBINDO 100 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 1 mg (100 Tablets Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 2 mg (100 Tablets Bottle) NDC 59651-841-01 Rx only Guanfacine Tablets, USP 2 mg* G2 AUROBINDO 100 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 2 mg (100 Tablets Bottle)