
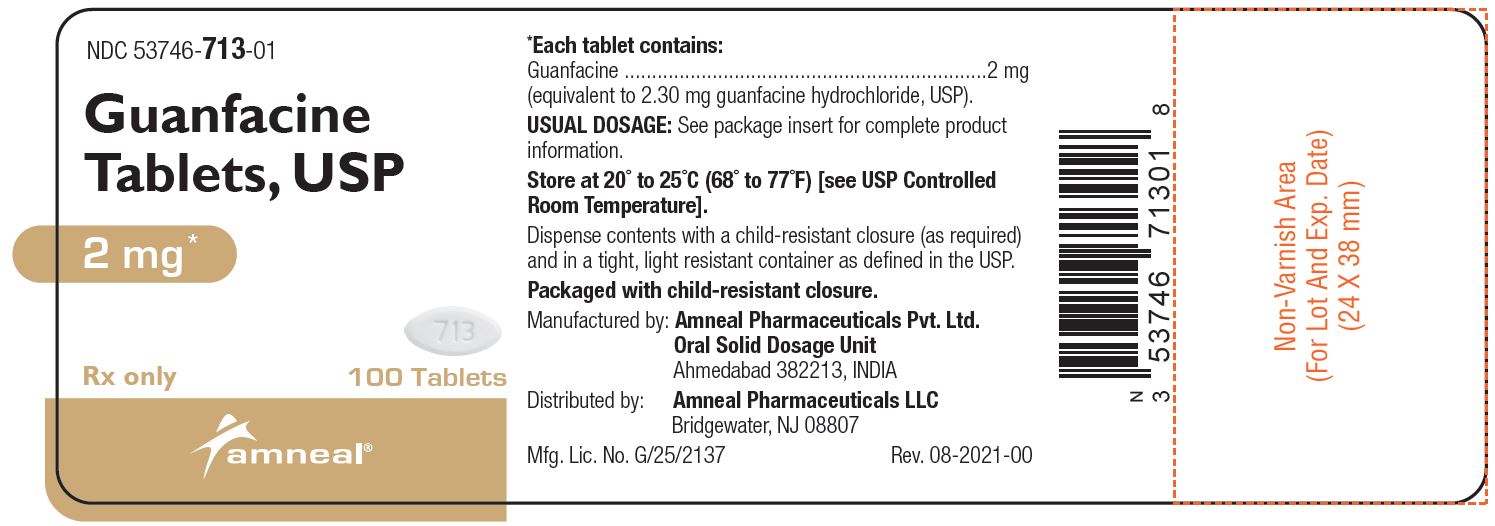
Guanfacine Hydrochloride 2 mg Tablet, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Central alpha-2 Adrenergic Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- It's used for both, depending on which form you have. The regular (immediate-release) tablet is prescribed for high blood pressure. The extended-release version — brand name Intuni...
- What is guanfacine actually used for — is it for ADHD or blood pressure?
- No, Intuniv is not a stimulant at all. It works on a different part of the brain than medications like Adderall or Ritalin. That's actually one reason it's sometimes used alongside...
- My child takes Intuniv for ADHD — is it a stimulant?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Guanfacine — tap one for details:
Guanfacine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 4ELV7Z65AP
Stearic acid is a fatty acid derived from plant or animal sources. It acts as a binder and lubricant in tablets and capsules, helping them hold together and flow smoothly during manufacturing.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.272 | $27.21 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.4903 | $49.03 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.4250 | $42.50 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Guanfacine 2 mg 00591-0453-01 | Actavis | 100 tablets | $0.272 | — | Availability likely | — |
| Guanfacine Hydrochloride 2 mg 24979-0199-01 | TWi | 100 tablets | $0.272 | AB | Availability likely | — |
| Guanfacine 2 mg 27241-0243-01 | Ajanta | 100 tablets | $0.272 | AB | Availability likely | — |
| Guanfacine Hydrochloride 2 mg 29300-0459-01 | Unichem | 100 tablets | $0.272 | AB | Availability likely | — |
| Guanfacine 2 mg 42806-0296-01 | Epic | 100 tablets | $0.272 | AB | Availability likely | — |
| Guanfacine Hydrochloride 2 mg 50268-0374-15 | AvPAK | 50 tablets | $0.272 | AB | Availability likely | — |
| Guanfacine Hydrochloride 2 mgthis 53746-0713-01 | Amneal | 100 tablets | $0.272 | AB | Availability likely | — |
| Guanfacine 2 mg 59651-0841-01 | Aurobindo | 100 tablets | $0.272 | AB | Availability likely | — |
| Guanfacine Hydrochloride 2 mg 62135-0728-90 | Chartwell | 90 tablets | $0.272 | AB | Availability likely | — |
| Guanfacine Hydrochloride 2 mg 70700-0302-01 | XIROMED, | 100 tablets | $0.272 | AB | Availability likely | — |
| Guanfacine 2 mg 72319-0019-04 | i3 | 100 tablets | $0.272 | AB | Availability likely | — |
| Guanfacine Hydrochloride 2 mg 65162-0713-03 | Amneal | 30 tablets | — | AB | FDA listed | — |
| Guanfacine 2 mg 67046-1655-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Guanfacine Hydrochloride 2 mg 70518-3516-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Guanfacine 2 mg 70518-4488-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Guanfacine 2 mg 70518-4564-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Guanfacine Hydrochloride 2 mg 72603-0269-01 | NORTHSTAR | 100 tablets | — | AB | FDA listed | — |
| Guanfacine 2 mg 72888-0124-00 | Advagen | 1000 tablets | — | AB | FDA listed | — |
| Guanfacine 2 mg 73141-0019-04 | A2A | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 53746-0713-01 You're viewing this | 100 TABLET in 1 BOTTLE (53746-713-01) | 2022-04-15 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS & USAGE Guanfacine tablets are indicated in the management of hypertension. Guanfacine may be given alone or in combination with other antihypertensive agents, especially thiazide-type diuretics.
⏱️ Dosage and Administration ▾
DOSAGE & ADMINISTRATION The recommended initial dose of guanfacine tablets when given alone or in combination with another antihypertensive drug is 1 mg daily given at bedtime to minimize somnolence. If after 3 to 4 weeks of therapy 1 mg does not give a satisfactory result, a dose of 2 mg may be given, although most of the effect of guanfacine is seen at 1 mg (see CLINICAL PHARMACOLOGY ). Higher daily doses have been used, but adverse reactions increase significantly with doses above 3 mg/day.
The frequency of rebound hypertension is low, but it can occur. When rebound occurs, it does so after 2 to 4 days, which is delayed compared with clonidine hydrochloride. This is consistent with the longer half-life of guanfacine.
In most cases, after abrupt withdrawal of guanfacine, blood pressure returns to pretreatment levels slowly (within 2 to 4 days) without ill effects.
⛔ Contraindications ▾
CONTRAINDICATIONS Guanfacine tablets are contraindicated in patients with known hypersensitivity to guanfacine hydrochloride.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Adverse reactions noted with guanfacine hydrochloride are similar to those of other drugs of the central α 2 -adrenoreceptor agonist class: dry mouth, sedation (somnolence), weakness (asthenia), dizziness, constipation, and impotence. While the reactions are common, most are mild and tend to disappear on continued dosing. Skin rash with exfoliation has been reported in a few cases; although clear cause and effect relationships to guanfacine could not be established, should a rash occur, guanfacine should be discontinued and the patient monitored appropriately.
In the dose-response monotherapy study described under CLINICAL PHARMACOLOGY, the frequency of the most commonly observed adverse reactions showed a dose relationship from 0.5 mg to 3 mg as follows: Adverse Reaction Placebo n=59 0.5 mg n=60 1 mg n=61 2 mg n=60 3 mg n=59 Dry Mouth 0% 10% 10% 42% 54% Somnolence 8% 5% 10% 13% 39% Asthenia 0% 2% 3% 7% 3% Dizziness 8% 12% 2% 8% 15% Headache 8% 8% 13% 7% 3% Impotence 0% 0% 0% 7% 3% Constipation 0% 2% 0% 5% 15% Fatigue 2% 2% 5% 8% 10% The percent of patients who dropped out because of adverse reactions are shown below for each dosage group.
Placebo 0.5 mg 1 mg 2 mg 3 mg Percent Dropouts 0% 2% 5% 13% 32% The most common reasons for dropouts among patients who received guanfacine were dry mouth, somnolence, dizziness, fatigue, weakness and constipation. In the 12-week, placebo-controlled, dose-response study of guanfacine administered with 25 mg chlorthalidone at bedtime, the frequency of the most commonly observed adverse reactions showed a clear dose relationship from 0.5 mg to 3 mg as follows: Adverse Reaction Placebo n=73 0.5 mg n=72 1 mg n=72 2 mg n=72 3 mg n=72 Dry Mouth 5 (7%) 4 (5%) 6 (8%) 8 (11%) 20 (28%) Somnolence 1 (1%) 3 (4%) 0 (0%) 1 (1%) 10 (14%) Asthenia 0 (0%) 2 (3%) 0 (0%) 2 (2%) 7 (10%) Dizziness 2 (2%) 1 (1%) 3 (4%) 6 (8%) 3 (4%) Headache 3 (4%) 4 (3%) 3 (4%) 1 (1%) 2 (2%) Impotence 1 (0%) 1 (0%) 0 (0%) 1 (1%) 3 (4%) Constipation 0 (0%) 1 (0%) 0 (0%) 1 (1%) 1 (1%) Fatigue 3 (3%) 0 (0%) 2 (3%) 5 (6%) 3 (4%) There were 41 premature terminations because of adverse reactions in this study.
The percent of patients who dropped out and the dose at which the dropout occurred were as follows: Dose Placebo 0.5 mg 1 mg 2 mg 3 mg Percent Dropouts 6.9% 4.2% 3.2% 6.9% 8.3% Reasons for dropouts among patients who received guanfacine were: somnolence, headache, weakness, dry mouth, dizziness, impotence, insomnia, constipation, syncope, urinary incontinence, conjunctivitis, paresthesia and dermatitis. In a second 12-week placebo-controlled combination therapy study in which the dose could be adjusted upward to 3 mg per day in 1 mg increments at 3-week intervals, i.e., a setting more similar to ordinary clinical use, the most commonly recorded reactions were: dry mouth, 47%; constipation, 16%; fatigue, 12%; somnolence, 10%; asthenia, 6%; dizziness, 6%; headache, 4%; and insomnia, 4%.
Reasons for dropouts among patients who received guanfacine were: somnolence, dry mouth, dizziness, impotence, constipation, confusion, depression and palpitations. In the clonidine/guanfacine comparison described in CLINICAL PHARMACOLOGY, the most common adverse reactions noted were as follows: Adverse Reactions Guanfacine (n=279) Clonidine (n=278) Dry Mouth 30 % 37% Somnolence 21% 35% Dizziness 11% 8% Constipation 10% 5% Fatigue 9% 8% Headache 4% 4% Insomnia 4% 3% Adverse reactions occurring in 3% or less of patients in the three controlled trials of guanfacine hydrochloride with a diuretic were: • Cardiovascular: bradycardia, palpitations, substernal pain • Gastrointestinal: abdominal pain, diarrhea, dyspepsia, dysphagia, nausea • CNS: amnesia, confusion, depression, insomnia, libido decrease • ENT disorders: rhinitis, taste perversion, tinnitus • Eye disorders: conjunctivitis, iritis, vision disturbance • Musculoskeletal: leg cramps, hypokinesia • Respiratory: dyspnea • Dermatologic: dermatitis, pruritus, purpura, sweating • U…
🆘 Overdosage ▾
OVERDOSAGE Signs and Symptoms Drowsiness, lethargy, bradycardia and hypotension have been observed following overdose with guanfacine. A 25-year-old female intentionally ingested 60 mg. She presented with severe drowsiness and bradycardia of 45 beats/minute.
Gastric lavage was performed and an infusion of isoproterenol (0.8 mg in 12 hours) was administered. She recovered quickly and without sequelae. A 28-year-old female who ingested 30 mg to 40 mg developed only lethargy, was treated with activated charcoal and a cathartic, was monitored for 24 hours, and was discharged in good health.
A 2-year-old male weighing 12 kg who ingested up to 4 mg of guanfacine developed lethargy. Gastric lavage (followed by activated charcoal and sorbitol slurry via NG tube) removed some tablet fragments within 2 hours after ingestion, and vital signs were normal. During 24-hour observation in ICU, systolic pressure was 58 mmHg and heart rate 70 beats per minute, at 16 hours post-ingestion.
No intervention was required, and child was discharged fully recovered the next day. Treatment of Overdosage Gastric lavage and supportive therapy as appropriate. Guanfacine is not dialyzable in clinically significant amounts (2.4%).
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Guanfacine hydrochloride is an orally active antihypertensive agent whose principal mechanism of action appears to be stimulation of central α 2 -adrenergic receptors. By stimulating these receptors, guanfacine reduces sympathetic nerve impulses from the vasomotor center to the heart and blood vessels. This results in a decrease in peripheral vascular resistance and a reduction in heart rate.
The dose-response relationship for blood pressure and adverse effects of guanfacine given once a day as monotherapy has been evaluated in patients with mild to moderate hypertension. In this study patients were randomized to placebo or to 0.5 mg, 1 mg, 2 mg, 3 mg or 5 mg of guanfacine. Results are shown in the following table.
A useful effect was not observed overall until doses of 2 mg were reached, although responses in white patients were seen at 1 mg; 24 hour effectiveness of 1 mg to 3 mg doses was documented using 24 hour ambulatory monitoring. While the 5 mg dose added an increment of effectiveness, it caused an unacceptable increase in adverse reactions. Mean Changes (mm Hg) from Baseline in Seated Systolic and Diastolic Blood Pressure for Patients Completing 4 to 8 Weeks of Treatment with Guanfacine Monotherapy Mean Change S/D* Seate d n= (range) Placebo 0.5 mg 1 mg 2 mg 3 mg 5 mg White Patients Black Patients 11 to 30 8 to 28 -1/-5 -3/-5 -6/-8 0/-2 -8/-9 -3/-5 -12/-11 -7/-7 -15/-12 -8/-9 -18/-16 -19/-15 * S/D = Systolic/diastolic blood pressure Controlled clinical trials in patients with mild to moderate hypertension who were receiving a thiazide-type diuretic have defined the dose-response relationship for blood pressure response and adverse reactions of guanfacine given at bedtime and have shown that the blood pressure response to guanfacine can persist for 24 hours after a single dose.
In the 12-week placebo-controlled dose-response study, patients were randomized to placebo or to doses of 0.5 mg, 1 mg, 2 mg and 3 mg of guanfacine, in addition to 25 mg chlorthalidone, each given at bedtime. The observed mean changes from baseline, tabulated below, indicate the similarity of response for placebo and the 0.5 mg dose. Doses of 1 mg, 2 mg and 3 mg resulted in decreased blood pressure in the sitting position with no real differences among the three doses.
In the standing position, there was some increase in response with dose. Mean Decreases (mm Hg) in Seated and Standing Blood Pressure for Patients Treated with Guanfacine in Combination with Chlorthalidone Mean Change n = Placebo 63 0.5 mg 63 1 mg 64 2 mg 58 3 mg 59 S/D* Seated S/D* Standing -5/-7 -3/-5 -5/-6 -5/-4 -14/-13 -11/-9 -12/-13 -9/-10 -16/-13 -15/-12 * S/D = Systolic/diastolic blood pressure While most of the effectiveness of guanfacine in combination (and as monotherapy in white patients) was present at 1 mg, adverse reactions at this dose were not clearly distinguishable from those associated with placebo.
Adverse reactions were clearly present at 2 mg and 3 mg (see ADVERSE REACTIONS ). In a second 12-week placebo-controlled study of 1 mg, 2 mg or 3 mg of guanfacine hydrochloride administered with 25 mg of chlorthalidone once daily, a significant decrease in blood pressure was maintained for a full 24 hours after dosing. While there was no significant difference between the 12 and 24 hour blood pressure readings, the fall in blood pressure at 24 hours was numerically smaller, suggesting possible escape of blood pressure in some patients and the need for individualization of therapy.
In a double-blind, randomized trial, either guanfacine or clonidine was given at recommended doses with 25 mg chlorthalidone for 24 weeks and then abruptly discontinued. Results showed equal degrees of blood pressure reduction with the two drugs and there was no tendency for blood pressures to increase despite maintenance of the same daily dose of the two drugs. Signs and symptoms of rebound phenomena were infrequent upon discontinuation of either drug.
Abrupt withdraw…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Guanfacine tablets, USP are available in 2 tablet strengths of guanfacine (as the hydrochloride salt) as follows: Guanfacine tablets USP, 1 mg : white, oval, flat faced, beveled edge tablet with “AN” on one side and “711” on the other side. They are available as follows: Bottles of 100: NDC 53746-711-01 Guanfacine tablets USP, 2 mg : white, oval, flat faced, beveled edge tablet with “AN” on one side and “713” on the other side. They are available as follows: Bottles of 100: NDC 53746-713-01 Store at 20º to 25 ºC (68 º to 77 ºF) [see USP Controlled Room Temperature].
Dispense contents with a child-resistant closure (as required) and in a tight, light resistant container as defined in the USP. Packaged with child-resistant closure. To report SUSPECTED ADVERSE REACTIONS, contact Amneal Pharmaceuticals at 1-877-835-5472 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch Manufactured by: Amneal Pharmaceuticals Pvt.
Ltd. Oral Solid Dosage Unit Ahmedabad 382213, INDIA Distributed by: Amneal Pharmaceuticals LLC Bridgewater, NJ 08807 Rev. 08-2021-00
📋 Description ▾
DESCRIPTION Guanfacine hydrochloride, USP is a centrally acting antihypertensive with α 2 -adrenoceptor agonist properties in tablet form for oral administration. The chemical name of guanfacine hydrochloride, USP is N-amidino-2-(2,6-dichlorophenyl) acetamide hydrochloride and its molecular weight is 282.55. Its structural formula is: Guanfacine hydrochloride, USP is a white or almost white crystalline powder; sparingly soluble in water and alcohol and slightly soluble in acetone.
Each tablet contains 1.15 mg or 2.30 mg of guanfacine hydrochloride, USP equivalent to 1 mg or 2 mg of guanfacine respectively for oral administration. In addition, each tablet contains the following inactive ingredients: microcrystalline cellulose, pregelatinized starch, and stearic acid. 1