
Acebutolol Hydrochloride 200 mg Capsule, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the beta-Adrenergic Blocker class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Acebutolol is used to treat high blood pressure and irregular heart rhythms. Acebutolol is in a class of medications called beta blockers. It works by relaxing blood vessels and slowing heart rate to improve blood flow and decrease blood pressure.
Read the full MedlinePlus article ↗- Acebutolol is most commonly prescribed for one of two things: high blood pressure (hypertension) or abnormal heartbeats called ventricular premature beats. For blood pressure, it w...
- What exactly is acebutolol being used to treat in my case?
- Please don't stop it suddenly — this is one of the most important things to know about acebutolol. Stopping abruptly, especially if you have any heart or artery disease, can cause...
- Can I just stop taking acebutolol if I feel fine or don't like the side effects?
Patient education
Supplement & herbal interactions
Acebutolol may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
1 inactive ingredient listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.616 | $61.64 / 100 capsules |
| Medicaid paysCMS SDUD · 12 mo | $0.6456 | $64.56 / 100 capsules |
| Medicare drug plans payPart D · Q2 2026 | $0.5695 | $56.95 / 100 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Acebutolol Hydrochloride 200 mg 50268-0050-15 | AvPAK | 50 capsules | $0.616 | AB | Availability likely | — |
| Acebutolol Hydrochloride 200 mgthis 53746-0669-01 | Amneal | 100 capsules | $0.616 | AB | Availability likely | — |
| Acebutolol Hydrochloride 200 mg 62559-0255-01 | ANI | 100 capsules | $0.616 | AB | Availability likely | — |
| Acebutolol Hydrochloride 200 mg 42291-0010-01 | AvKARE | 100 capsules | — | AB | FDA listed | — |
| Acebutolol Hydrochloride 200 mg 51407-0666-01 | Golden | 100 capsules | — | AB | FDA listed | — |
| Acebutolol Hydrochloride 200 mg 65162-0669-10 | Amneal | 100 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 53746-0669-01 You're viewing this | 100 CAPSULE in 1 BOTTLE (53746-669-01) | $0.6164 / ea | $61.64 | 2009-12-01 | Active |
| 53746-0669-05 | 500 CAPSULE in 1 BOTTLE (53746-669-05) | — | — | 2009-12-01 | Active |
You're viewing the smallest of 2 pack sizes for this product.
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 53746-0669-01?
What is the difference between NDC 53746-0669-01 and NDC 53746-0669-05?
What NDC number is used to bill for this package of Acebutolol Hydrochloride 200 mg Capsule?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Hypertension Acebutolol hydrochloride capsules are indicated for the management of hypertension in adults. It may be used alone or in combination with other antihypertensive agents, especially thiazide-type diuretics. Ventricular Arrhythmias Acebutolol hydrochloride capsules are indicated in the management of ventricular premature beats; it reduces the total number of premature beats, as well as the number of paired and multiform ventricular ectopic beats, and R-on-T beats.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Hypertension The initial dosage of acebutolol in uncomplicated mild-to-moderate hypertension is 400 mg. This can be given as a single daily dose, but in occasional patients twice daily dosing may be required for adequate 24-hour blood-pressure control. An optimal response is usually achieved with dosages of 400 mg to 800 mg per day, although some patients have been maintained on as little as 200 mg per day.
Patients with more severe hypertension or who have demonstrated inadequate control may respond to a total of 1200 mg daily (administered b.i.d.), or to the addition of a second antihypertensive agent. Beta-1 selectivity diminishes as dosage is increased. Ventricular Arrhythmia The usual initial dose of acebutolol is 400 mg daily given as 200 mg b.i.d.
Dosage should be increased gradually until an optimal clinical response is obtained, generally at 600 to 1200 mg per day. If treatment is to be discontinued, the dosage should be reduced gradually over a period of about two weeks. Use in Older Patients Older patients have an approximately 2-fold increase in bioavailability and may require lower maintenance doses.
Doses above 800 mg/day should be avoided in the elderly.
⛔ Contraindications ▾
CONTRAINDICATIONS Acebutolol hydrochloride is contraindicated in: 1) persistently severe bradycardia; 2) second- and third-degree heart block; 3) overt cardiac failure; and 4) cardiogenic shock (see WARNINGS ).
⚠️ Warnings ▾
WARNINGS Cardiac Failure Sympathetic stimulation may be essential for support of the circulation in individuals with diminished myocardial contractility, and its inhibition by β-adrenergic receptor blockade may precipitate more severe failure. Although β-blockers should be avoided in overt cardiac failure, acebutolol can be used with caution in patients with a history of heart failure who are controlled with digitalis and/or diuretics. Both digitalis and acebutolol impair AV conduction.
If cardiac failure persists, therapy with acebutolol should be withdrawn. In Patients Without a History of Cardiac Failure In patients with aortic or mitral valve disease or compromised left ventricular function, continued depression of the myocardium with β-blocking agents over a period of time may lead to cardiac failure. At the first signs of failure, patients should be digitalized and/or be given a diuretic and the response observed closely.
If cardiac failure continues despite adequate digitalization and/or diuretic, acebutolol therapy should be withdrawn. Exacerbation of Ischemic Heart Disease Following Abrupt Withdrawal Following abrupt cessation of therapy with certain β-blocking agents in patients with coronary artery disease, exacerbation of angina pectoris and, in some cases, myocardial infarction and death have been reported. Therefore, such patients should be cautioned against interruption of therapy without a physician’s advice.
Even in the absence of overt ischemic heart disease, when discontinuation of acebutolol is planned, the patient should be carefully observed, and should be advised to limit physical activity to a minimum while acebutolol is gradually withdrawn over a period of about two weeks. (If therapy with an alternative β-blocker is desired, the patient may be transferred directly to comparable doses of another agent without interruption of β-blocking therapy.) If an exacerbation of angina pectoris occurs, antianginal therapy should be restarted immediately in full doses and the patient hospitalized until his condition stabilizes.
Peripheral Vascular Disease Treatment with β-antagonists reduces cardiac output and can precipitate or aggravate the symptoms of arterial insufficiency in patients with peripheral or mesenteric vascular disease. Caution should be exercised with such patients, and they should be observed closely for evidence of progression of arterial obstruction. Bronchospastic Disease PATIENTS WITH BRONCHOSPASTIC DISEASE SHOULD, IN GENERAL, NOT RECEIVE A β-BLOCKER.
Because of its relative β 1 -selectivity, however, low doses of acebutolol may be used with caution in patients with bronchospastic disease who do not respond to, or who cannot tolerate, alternative treatment. Since β 1 -selectivity is not absolute and is dose-dependent, the lowest possible dose of acebutolol should be used initially, preferably in divided doses to avoid the higher plasma levels associated with the longer dose-interval. A bronchodilator, such as theophylline or a β 2 -stimulant, should be made available in advance with instructions concerning its use.
WARNINGS, Major Surgery Chronically administered beta-blocking therapy should not be routinely withdrawn prior to major surgery; however, the impaired ability of the heart to respond to reflex adrenergic stimuli may augment the risks of general anesthesia and surgical procedures. Diabetes and Hypoglycemia β-blockers may potentiate insulin-induced hypoglycemia and mask some of its manifestations such as tachycardia; however, dizziness and sweating are usually not significantly affected. Diabetic patients should be warned of the possibility of masked hypoglycemia.
Thyrotoxicosis β-adrenergic blockade may mask certain clinical signs (tachycardia) of hyperthyroidism. Abrupt withdrawal of β-blockade may precipitate a thyroid storm; therefore, patients suspected of developing thyrotoxicosis from whom acebutolol therapy is to be withdrawn should be monitored closely.
🤒 Adverse Reactions ▾
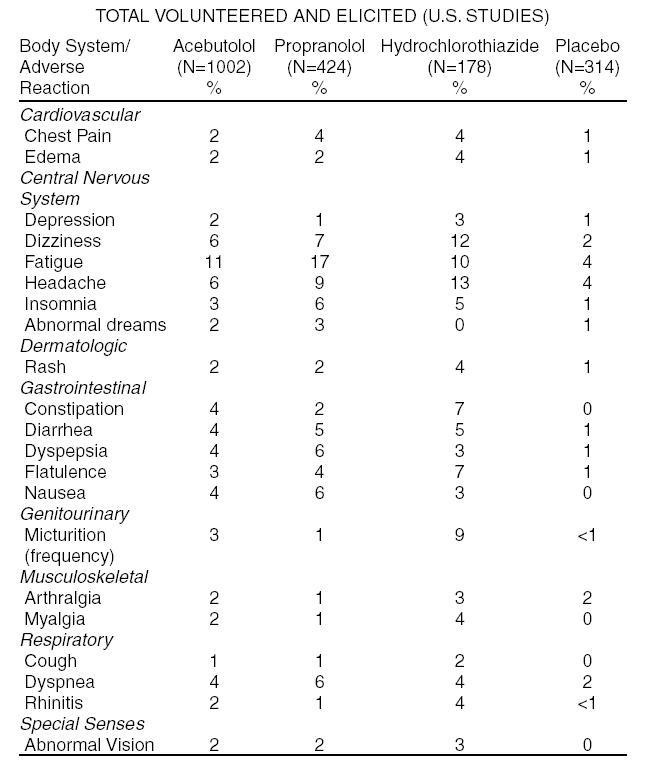
ADVERSE REACTIONS Acebutolol is well tolerated in properly selected patients. Most adverse reactions have been mild, not required discontinuation of therapy, and tended to decrease as duration of treatment increases. The following table shows the frequency of treatment-related side effects derived from controlled clinical trials in patients with hypertension, angina pectoris, and arrhythmia.
These patients received acebutolol, propranolol, or hydrochlorothiazide as monotherapy, or placebo. TOTAL VOLUNTEERED AND ELICITED (U.S. STUDIES) Body System/ Adverse Reaction Acebutolol (N=1002) % Propranolol (N=424) % Hydrochlorthiazide (n=178) % Placebo (N=314) % Cardiovascular Chest Pain 2 4 4 1 Edema 2 2 4 1 Central Nervous System Depression 2 1 3 1 Dizziness 6 7 12 2 Fatigue 11 17 10 4 Headache 6 9 13 4 Insomnia 3 6 5 1 Abnormal dreams 2 3 0 1 Dermatologic Rash 2 2 4 1 Gastrointestinal Constipation 4 2 7 0 Diarrhea 4 5 5 1 Dyspepsia 4 6 3 1 Flatulence 3 4 7 1 Nausea 4 6 3 0 Genitourinary Micturition (frequency) 3 1 9 < 1 Musculoskeletal Arthralgia 2 1 3 2 Myalgia 2 1 4 0 Respiratory Cough 1 1 2 0 Dyspnea 4 6 4 2 Rhinitis 2 1 4 < 1 Special Senses Abnormal Vision 2 2 3 0 The following selected (potentially important) side effects were seen in up to 2% of acebutolol patients: Cardiovascular: hypotension, bradycardia, heart failure.
Central Nervous System: anxiety, hyper/hypoesthesia, impotence. Dermatological: pruritus. Gastrointestinal: vomiting, abdominal pain.
Genitourinary: dysuria, nocturia. Liver and Biliary System: A small number of cases of liver abnormalities (increased SGOT, SGPT, LDH) have been reported in association with acebutolol therapy. In some cases increased bilirubin or alkaline phosphatase, fever, malaise, dark urine, anorexia, nausea, headache, and/or other symptoms have been reported.
In some of the reported cases, the symptoms and signs were confirmed by rechallenge with acebutolol. The abnormalities were reversible upon cessation of acebutolol therapy. Musculoskeletal: back pain, joint pain.
Respiratory: pharyngitis, wheezing. Special Senses: conjunctivitis, dry eye, eye pain. Autoimmune: In extremely rare instances, systemic lupus erythematosus has been reported.
The incidence of drug-related adverse effects (volunteered and solicited) according to acebutolol dose is shown below. (Data from 266 hypertensive patients treated for 3 months on a constant dose.) Body System 400 mg/day (N=132) 800 mg/day (N=63) 1200 mg/day (N=71) Cardiovascular 5% 2% 1% Gastrointestinal 3% 3% 1% Musculoskeletal 2% 3% 4% Central Nervous system 9% 13% 17% Respiratory 1% 5% 6% Skin 1% 2% 1% Special Senses 2% 2% 6% Genitourinary 2% 3% 1% Potential Adverse Events In addition, certain adverse effects not listed above have been reported with other β-blocking agents and should also be considered as potential adverse effects of acebutolol.
Central Nervous System: Reversible mental depression progressing to catatonia (an acute syndrome characterized by disorientation for time and place), short-term memory loss, emotional lability, slightly clouded sensorium, and decreased performance (neuropsychometrics). Cardiovascular: Intensification of AV block (see CONTRAINDICATIONS ). Allergic: Erythematous rash, fever combined with aching and sore throat, laryngospasm, and respiratory distress.
Hematologic: Agranulocytosis, nonthrombocytopenic, and thrombocytopenic purpura. Gastrointestinal: Mesenteric arterial thrombosis and ischemic colitis. Miscellaneous: Reversible alopecia and Peyronie’s disease.
The oculomucocutaneous syndrome associated with the β-blocker practolol has not been reported with acebutolol during investigational use and extensive foreign clinical experience.
🆘 Overdosage ▾
OVERDOSAGE No specific information on emergency treatment of overdosage is available for acebutolol. However, overdosage with other β-blocking agents has been accompanied by extreme bradycardia, advanced atrioventricular block, intraventricular conduction defects, hypotension, severe congestive heart failure, seizures, and in susceptible patients, bronchospasm and hypoglycemia. Although specific information on the emergency treatment of acebutolol overdose is not available on the basis of the pharmacological actions and the observations in treating overdoses with other β-blockers, the following general measures should be considered: Empty stomach by emesis or lavage.
Bradycardia: IV atropine (1 mg to 3 mg in divided doses). If antivagal response is inadequate, administer isoproterenol cautiously since larger than usual doses of isoproterenol may be required. Persistent hypotension in spite of correction of bradycardia: Administer vasopressor (e.g., epinephrine, norepinephrine, dopamine, or dobutamine) with frequent monitoring of blood pressure and pulse rate.
Bronchospasm: A theophylline derivative, such as aminophylline and/or parenteral β 2 -stimulant, such as terbutaline. Cardiac failure: Digitalize the patient and/or administer a diuretic. It has been reported that glucagon is useful in this situation.
Acebutolol is dialyzable.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Acebutolol is a cardioselective, β-adrenoreceptor blocking agent, which possesses mild intrinsic sympathomimetic activity (ISA) in its therapeutically effective dose range. Pharmacodynamics β 1 -cardioselectivity has been demonstrated in experimental animal studies. In anesthetized dogs and cats, acebutolol is more potent in antagonizing isoproterenol-induced tachycardia (β 1 ) than in antagonizing isoproterenol-induced vasodilatation (β 2 ).
In guinea pigs and cats, it is more potent in antagonizing this tachycardia than in antagonizing isoproterenol-induced bronchodilatation (β 2 ). ISA of acebutolol has been demonstrated in catecholamine-depleted rats by tachycardia induced by intravenous administration of this agent. A membrane-stabilizing effect has been detected in animals, but only with high concentrations of acebutolol.
Clinical studies have demonstrated β 1 -blocking activity at the recommended doses by: a) reduction in the resting heart rate and decrease in exercise-induced tachycardia; b) reduction in cardiac output at rest and after exercise; c) reduction of systolic and diastolic blood pressures at rest and post exercise; d) inhibition of isoproterenol-induced tachycardia. The β 1 -selectivity of acebutolol has also been demonstrated on the basis of the following vascular and bronchial effects: Vascular Effects: Acebutolol has less antagonistic effects on peripheral vascular β 2 -receptors at rest and after epinephrine stimulation than nonselective β-antagonists.
Bronchial Effects: In single-dose studies in asthmatics examining effects of various beta-blockers on pulmonary function, low doses of acebutolol produce less evidence of bronchoconstriction and less reduction of beta 2 agonist, bronchodilating effects, than nonselective agents like propranolol but more than atenolol. ISA has been observed with acebutolol in man, as shown by a slightly smaller (about 3 beats per minute) decrease in resting heart rate when compared to equivalent β-blocking doses of propranolol, metoprolol or atenolol.
Chronic therapy with acebutolol induced no significant alteration in the blood lipid profile. Acebutolol has been shown to delay AV conduction time and to increase the refractoriness of the AV node without significantly affecting sinus node recovery time, atrial refractory period, or the HV conduction time. The membrane-stabilizing effect of acebutolol is not manifest at the doses used clinically.
Significant reductions in resting and exercise heart rates and systolic blood pressures have been observed 1.5 hours after acebutolol administration with maximal effects occurring between 3 and 8 hours post-dosing in normal volunteers. Acebutolol has demonstrated a significant effect on exercise-induced tachycardia 24 to 30 hours after drug administration. There are significant correlations between plasma levels of acebutolol and both the reduction in resting heart rate and the percent of β-blockade of exercise-induced tachycardia.
The antihypertensive effect of acebutolol has been shown in double-blind controlled studies to be superior to placebo and similar to propranolol and hydrochlorothiazide. In addition, patients responding to acebutolol administered twice daily had a similar response whether the dosage regimen was changed to once daily administration or continued on a b.i.d. regimen. Most patients responded to 400 mg to 800 mg per day in divided doses.
The antiarrhythmic effect of acebutolol was compared with placebo, propranolol, and quinidine. Compared with placebo, acebutolol significantly reduced mean total ventricular ectopic beats (VEB), paired VEB, multiform VEB, R-on-T beats, and ventricular tachycardia (VT). Both acebutolol and propranolol significantly reduced mean total and paired VEB and VT.
Acebutolol and quinidine significantly reduced resting total and complex VEB; the antiarrhythmic efficacy of acebutolol was also observed during exercise. Pharmacokinetics and Metabolism Acebutolol is we…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Acebutolol hydrochloride capsules, USP are available as follows: 200 mg: Hard gelatin capsules with bright orange opaque body printed radially “669” with black ink and lavender opaque cap printed radially “AMNEAL” with black ink, which contains white granular powder. Bottles of 100 NDC 53746-669-01 Bottles of 500 NDC 53746-669-05 400 mg: Hard gelatin capsules with bright orange opaque body printed radially “670” with black ink and lavender opaque cap printed radially “AMNEAL” with black ink, which contains white granular powder.
Bottles of 30 NDC 53746-670-30 Bottles of 100 NDC 53746-670-01 Bottles of 500 NDC 53746-670-05 Keep tightly closed. Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature]. Protect from light.
Dispense in a tight, light-resistant container. Manufactured by: Amneal Pharmaceuticals Pvt. Ltd.
Oral Solid Dosage Unit Ahmedabad, 382213 INDIA Distributed by: Amneal Pharmaceuticals LLC Bridgewater, NJ 08807 Rev. 10-2024-01
📋 Description ▾
DESCRIPTION Acebutolol hydrochloride, USP is a selective, hydrophilic beta-adrenoreceptor blocking agent with mild intrinsic sympathomimetic activity for use in treating patients with hypertension and ventricular arrhythmias. It is marketed in capsule form for oral administration. Acebutolol hydrochloride capsules, USP are provided in two dosage strengths which contain 200 mg or 400 mg of acebutolol as the hydrochloride salt.
The inactive ingredients present are D&C Red 28, D&C Yellow 10, FD&C Blue 1, FD&C Red 40, gelatin, maize starch, povidone, stearic acid and titanium dioxide. Acebutolol hydrochloride, USP has the following structural formula: C 18 H 28 N 2 O 4 •HCl M.W. 372.89 Acebutolol hydrochloride, USP is a white or slightly off-white powder freely soluble in water, and less soluble in alcohol.
Chemically it is defined as the hydrochloride salt of (±) N-[3-Acetyl-4-[2-hydroxy-3-[(1-methylethyl) amino]propoxy]phenyl] butanamide. f1931f84-figure-01