
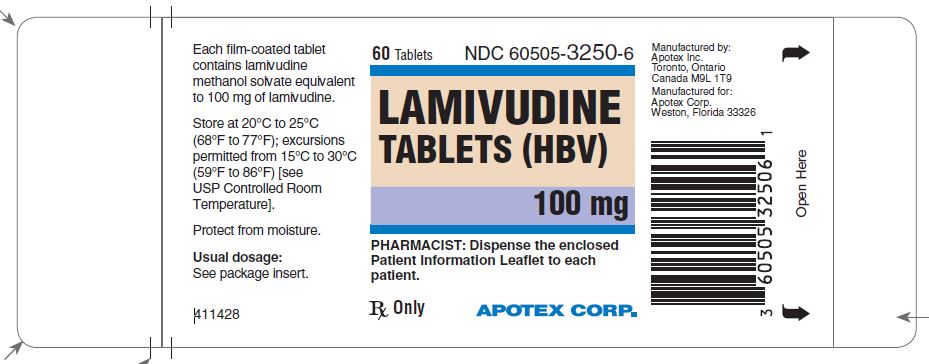
Lamivudine 100 mg Tablet, Film Coated, 60-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Human Immunodeficiency Virus Nucleoside Analog Reverse Transcriptase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Lamivudine is used to treat human immunodeficiency virus (HIV) infection. Lamivudine is in a class of medications called nucleoside reverse transcriptase inhibitors (NRTIs). It works by decreasing the amount of HIV in the blood. Although lamivudine will not cure HIV, it may decrease your chance of developing acquired immunodeficiency syndrome (AIDS) and HIV-related illnesses. Taking these medications and making other lifestyle changes may also decrease the risk of giving the HIV virus to other people.
Read the full MedlinePlus article ↗- It can be used for both, but here's the important thing: there are two different products, and they are not the same. The higher-dose tablets and oral solution (like Epivir) are us...
- What exactly is lamivudine used for — is it for HIV or hepatitis B?
- Please don't stop without talking to your doctor first. If you have HIV-1, stopping can allow the virus to rebound. If you're also infected with hepatitis B, stopping lamivudine ca...
- Can I stop taking lamivudine if I feel fine?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Lamivudine — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII 68401960MK
Crospovidone is a synthetic polymer made from polyvinylpyrrolidone. It acts as a disintegrant, helping tablets break apart quickly in the stomach so the medicine dissolves and absorbs into the body.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII RFW2ET671P
Hydroxypropyl cellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a film-former to coat tablets or control how fast the medicine releases.
-
UNII R75537T0T4
Hypromellose 2910 is a plant-derived thickening agent made from cellulose. It serves as a binder that holds tablet ingredients together, a film-coating for pills, and a viscosity controller in liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII Q662QK8M3B
Polyethylene glycol 8000 is a synthetic polymer made from ethylene oxide. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and add bulk to the medicine.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $9.904 | $594.26 / 60 tablets |
| Medicaid paysCMS SDUD · 12 mo | $8.12 | $487.44 / 60 tablets |
| Medicare drug plans payPart D · Q2 2026 | $9.11 | $546.63 / 60 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lamivudine 100 mgthis 60505-3250-06 | Apotex | 60 tablets | $9.904 | AB | Availability likely | — |
| lamivudine 100 mg 31722-0001-02 | Camber | 10 tablets | — | AB | FDA listed | — |
| Lamivudine 100 mg 31722-0752-06 | Camber | 600 tablets | — | AB | FDA listed | — |
| Lamivudine 100 mg 51407-0866-60 | Golden | 60 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 60505-3250-06 You're viewing this | 60 TABLET, FILM COATED in 1 BOTTLE (60505-3250-6) | 2014-01-03 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: EXACERBATIONS OF HEPATITIS B, AND RISK OF HIV-1 RESISTANCE IF LAMIVUDINE TABLETS (HBV) IS USED IN PATIENTS WITH UNRECOGNIZED OR UNTREATED HIV-1 INFECTION Severe acute exacerbations of hepatitis B have been reported in patients who have discontinued anti-hepatitis B therapy [including lamivudine tablets (HBV)]. Hepatic function should be monitored closely with both clinical and laboratory follow-up for at least several months in patients who discontinue anti-hepatitis B therapy. If appropriate, initiation of anti-hepatitis B therapy may be warranted [ see Warnings and Precautions ( 5.1 )] Lamivudine tablets (HBV) is not approved for the treatment of human immunodeficiency virus type 1 (HIV-1) infection because the lamivudine dosage in lamivudine tablets (HBV) is subtherapeutic and monotherapy is inappropriate for the treatment of HIV-1 infection.
HIV-1 resistance may emerge in chronic hepatitis B-infected patients with unrecognized or untreated HIV-1 infection. HIV counseling and testing should be offered to all patients before beginning treatment with lamivudine tablets (HBV) and periodically during treatment [see Warnings and Precaution ( 5.1 ) ] W A RN I N G: EXACERBATIONS OF HEPATITIS B, and RISK OF HIV-1 RESISTANCE IF LAMIVUDINE TABLETS (HBV) I S USED IN PATIENTS WITH UNRECOGNIZED OR UNTREATED HIV-1 INFECTION See full prescribing information for complete boxed warning S e v er e acute exacerbations of hepatitis B have been reported in patients who have discontinued anti-hepatitis B therapy [including lamivudine tablets (HBV)].
Monitor hepatic function closely in these patients and, if appropriate, initiate anti-hepatitis B treatment. ( 5.1 ) Lamivudine tablets (HBV) contain a lower dose of the same active ingredient (lamivudine) as Epivir tablets and oral solution used to treat human immunodeficiency virus type 1 (HIV-1) infection. HIV-1 resistance may emerge in chronic hepatitis B patients with unrecognized or untreated HIV-1 infection because the lamivudine dosage in lamivudine tablets (HBV) is subtherapeutic and monotherapy is inappropriate for the treatment of HIV-1 infection.
HIV counseling and testing should be offered to all patients before beginning treatment with lamivudine tablets (HBV) and periodically during treatment. ( 5.2 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Lamivudine tablets (HBV) are indicated for the treatment of chronic hepatitis B virus (HBV) infection associated with evidence of hepatitis B viral replication and active liver inflammation [ see Clinical Studies ( 14.1 , 14.2 ) ]. The following points should be considered when initiating therapy with lamivudine tablets (HBV): Due to high rates of resistance development in treated patients, initiation of treatment with lamivudine tablets (HBV) should only be considered when the use of an alternative antiviral agent with a higher genetic barrier to resistance is not available or appropriate.
Lamivudine tablets (HBV) have not been evaluated in patients co-infected with human immunodeficiency virus (HIV), hepatitis C virus (HCV), or hepatitis delta virus. Lamivudine tablets (HBV) have not been evaluated in liver transplant recipients or in patients with chronic hepatitis B virus infection with decompensated liver disease. Lamivudine tablets (HBV) are a nucleoside analogue reverse transcriptase inhibitor indicated for the treatment of chronic hepatitis B virus (HBV) infection associated with evidence of hepatitis B viral replication and active liver inflammation.
(1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Adults: 100 mg, once daily. ( 2.2 ) Pediatric Patients aged 2 to 17 years: 3 mg per kg once daily up to 100 mg once daily. Prescribe oral solution for pediatric patients requiring less than 100 mg daily.
( 2.3 ) Patients with Renal Impairment: Doses of lamivudine tablets (HBV) must be adjusted in accordance with renal function. ( 2.4 ) Lamivudine tablets (HBV) should not be used with other medications that contain lamivudine or emtricitabine. ( 2.5 )
2.1HIV Counseling and Testing HIV counseling and testing should be offered to all patients before beginning treatment with Lamivudine tablets (HBV) and periodically during treatment because of the risk of emergence of resistant human immunodeficiency virus type 1 (HIV-1) and limitation of treatment options if lamivudine tablets (HBV) is prescribed to treat chronic hepatitis B infection in a patient who has unrecognized HIV-1 infection or acquires HIV-1 infection during treatment [ see Warnings and Precautions ( 5.2 ) ].
2.2Recommended Dosage for Adult Patients The recommended oral dosage of lamivudine tablets (HBV) is 100 mg once daily.
2.3Recommended Dosage for Pediatric Patients The recommended oral dosage of lamivudine tablets (HBV) for pediatric patients aged 2 to 17 years is 3 mg per kg once daily up to a maximum daily dosage of 100 mg. The oral solution formulation should be prescribed for patients requiring a dosage less than 100 mg or if unable to swallow tablets.
2.4Patients with Renal Impairment Dosage recommendations for adult patients with reduced renal function are provided in Table 1 [ see Clinical Pharmacology ( 12.3 ) ]. Table 1. Dosage of Lamivudine Tablets (HBV) in Adult Patients with Renal Impairment Creatinine Clearance (mL/min) Recommended Dosage of Lamivudine Tablets (HBV) ≥50 100 mg once daily 30-49 100 mg first dose, then 50 mg once daily 15-29 100 mg first dose, then 25 mg once daily 5-14 35 mg first dose, then 15 mg once daily <5 35 mg first dose, then 10 mg once daily Following correction of the dosage for renal impairment, no additional dosage modification of lamivudine tablets (HBV) is required after routine (4-hour) hemodialysis or peritoneal dialysis [ see Clinical Pharmacology ( 12.3 )] .
There are insufficient data to recommend a specific dosage of lamivudine tablets (HBV) in pediatric patients with renal impairment.
2.5Important Administration Instructions Lamivudine tablets (HBV) may be administered with or without food. The tablets and oral solution may be used interchangeably [ see Clinical Pharmacology ( 12.3 ) ]. The oral solution should be used for doses less than 100 mg. Lamivudine tablets (HBV) should not be used with other medications that contain lamivudine or medications that contain emtricitabine.
2.6Assessing Patients during Treatment Patients should be monitored regularly during treatment by a physician experienced in the management of chronic hepatitis B. During treatment, combinations of events such as return of persistently elevated ALT, increasing levels of HBV DNA over time after an initial decline below assay limit, progression of clinical signs or symptoms of hepatic disease, and/or worsening of hepatic necroinflammatory findings may be considered as potentially reflecting loss of therapeutic response.
Such observations should be taken into consideration when determining the advisability of continuing therapy with lamivudine tablets (HBV). The optimal duration of treatment, the durability of HBeAg seroconversions occurring during treatment, and the relationship between treatment response and long-term outcomes such as hepatocellular carcinoma or decompensated cirrhosis are not known.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Lamivudine tablets (HBV): 100 mg, are orange-brown, capsule shaped, biconvex film-coated tablets engraved “APO” on one side, “LMV 100” on the other side. Tablets: 100 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Lamivudine tablets (HBV) are contraindicated in patients with a previous hypersensitivity reaction to lamivudine. Lamivudine tablets (HBV) is contraindicated in patients with previous hypersensitivity reaction to lamivudine. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Emergence of Resistance-Associated HBV Substitutions: Consider a switch to an alternative regimen if serum HBV DNA remains detectable after 24 weeks of treatment. ( 2.6 , 5.3 ) Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of nucleoside analogues. ( 5.4 )
5.1Exacerbations of Hepatitis after Discontinuation of Treatment Clinical and laboratory evidence of exacerbations of hepatitis have occurred after discontinuation of lamivudine. These exacerbations have been detected primarily by serum ALT elevations in addition to re-emergence of HBV DNA commonly observed after stopping treatment; see Table 4 for more information regarding frequency of posttreatment ALT elevations [ see Adverse Reactions ( 6.1 ) ]. Although most events appear to have been self-limited, fatalities have been reported in some cases.
The causal relationship to discontinuation of lamivudine treatment is unknown. Patients should be closely monitored with both clinical and laboratory follow-up for at least several months after stopping treatment with lamivudine tablets (HBV). There is insufficient evidence to determine whether re-initiation of lamivudine tablets (HBV) alters the course of posttreatment exacerbations of hepatitis.
5.2Risk of HIV-1 Resistance if Lamivudine Tablets (HBV) is Used in Patients with Unrecognized or Untreated HIV-1 Infection Lamivudine tablets (HBV) contain a lower lamivudine dose than the lamivudine dose used to treat HIV-1 infection with Epivir tablets and oral solution or with lamivudine containing antiretroviral fixed-dose combination products. Lamivudine tablets (HBV) is not appropriate for patients co-infected with HBV and HIV-1. If a patient with unrecognized or untreated HIV-1 infection is prescribed lamivudine tablets (HBV) for the treatment of HBV, rapid emergence of HIV-1 resistance is likely to result because of the subtherapeutic dose and the inappropriate use of monotherapy for HIV-1 treatment.
HIV counseling and testing should be offered to all patients before beginning treatment with lamivudine tablets (HBV) and periodically during treatment because of the risk of rapid emergence of resistant HIV-1 and limitation of treatment options if lamivudine tablets (HBV) is prescribed to treat chronic hepatitis B in a patient who has unrecognized or untreated HIV-1 infection or who acquires HIV-1 infection during treatment.
5.3Emergence of Resistance-Associated HBV Substitutions In controlled clinical trials, YMDD-mutant HBV was detected in subjects with on–lamivudine tablets (HBV) re-appearance of HBV DNA after an initial decline below the assay limit [see Microbiology ( 12.4 )]. Subjects treated with lamivudine tablets (HBV) (adults and children) with YMDD-mutant HBV at 52 weeks showed diminished treatment responses in comparison with subjects treated with lamivudine tablets (HBV) without evidence of YMDD substitutions, including the following: lower rates of HBeAg seroconversion and HBeAg loss (no greater than placebo recipients), more frequent return of positive HBV DNA, and more frequent ALT elevations.
In the controlled trials, when subjects developed YMDD-mutant HBV, they had a rise in HBV DNA and ALT from their previous on-treatment levels. Progression of hepatitis B, including death, has been reported in some subjects with YMDD-mutant HBV, including subjects from the liver transplant setting and from other clinical trials. In order to reduce the risk of resistance in patients receiving monotherapy with lamivudine tablets (HBV), a switch to an alternative regimen should be considered if serum HBV DNA remains detectable after 24 weeks of treatment.
Optimal therapy should be guided by resistance testing.
5.4Lactic Acidosis and Severe Hepatomegaly with Steatosis Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of nucleoside analogues, including lamivudine tablets (HBV). A…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in other sections of the labeling: Exacerbations of hepatitis B after discontinuation of treatment [ see Warnings and Precautions ( 5.1 ) ]. Risk of emergence of resistant HIV-1 infection [ see Warnings and Precautions ( 5.2 ) ]. Risk of emergence of resistant HBV infection [ see Warnings and Precautions ( 5.3) ].
Lactic acidosis and severe hepatomegaly with steatosis [ see Warnings and Precautions ( 5.4 ) ]. The most common reported adverse reactions in those receiving lamivudine tablets (HBV) (incidence greater than or equal to 10% and reported at a rate greater than placebo) were ear, nose, and throat infections; sore throat; and diarrhea. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Apotex Corp. at 1-800-706-5575 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared with rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Clinical Trials Experience in Adult Subjects with Chronic HBV Infection Clinical adverse reactions (regardless of investigator’s causality assessment) reported in greater than or equal to 10% of subjects who received lamivudine tablets (HBV) and reported at a rate greater than in subjects who received placebo are listed in Table 2.
Table 2. Clinical Adverse Reactions a Reported in Greater than or Equal to 10% of Subjects Who Received Lamivudine Tablets (HBV) for 52 to 68 Weeks and at an Incidence Greater than Placebo (Trials 1 to 3) a Includes adverse events regardless of severity and causality assessment. Adverse Event Lamivudine Tablets (HBV) (n = 332) Placebo (n = 200) Ear, Nose, and Throat Ear, nose, and throat infections 25% 21% Sore throat 13% 8% Gastrointestinal Diarrhea 14% 12% Specified laboratory abnormalities reported in subjects who received lamivudine tablets (HBV) and reported at a rate greater than in subjects who received placebo are listed in Table 3.
Table 3. Frequencies of Specified Laboratory Abnormalities Reported during Treatment at a Greater Frequency in Subjects Treated with Lamivudine Tablets (HBV) than with Placebo (Trials 1 to 3) a a Includes subjects treated for 52 to 68 weeks. b Includes observations during and after treatment in the 2 placebo-controlled trials that collected this information. ULN = Upper limit of normal.
Test (Abnormal Level) Subjects with Abnormality/Subjects with Observations Lamivudine Tabglets (HBV) Placebo Serum Lipase ≥2.5 x ULN b 10% 7% Creatine Phosphokinase (CPK) ≥7 x baseline 9% 5% Platelets <50,000/mm 3 4% 3% In subjects followed for up to 16 weeks after discontinuation of treatment, posttreatment ALT elevations were observed more frequently in subjects who had received lamivudine tablets (HBV) than in subjects who had received placebo. A comparison of ALT elevations between Weeks 52 and 68 in subjects who discontinued lamivudine tablets (HBV) at Week 52 and subjects in the same trials who received placebo throughout the treatment course is shown in Table 4.
Table 4. Posttreatment ALT Elevations with No-Active-Treatment Follow-up (Trials 1 and 3) a Each subject may be represented in one or more category. b During treatment phase. c Comparable to a Grade 3 toxicity in accordance with modified WHO criteria. ULN = Upper limit of normal.
Abnormal Value Subjects with ALT Elevation/ Subjects with Observations a Lamivudine Tablets (HBV) b Placebo b ALT ≥2 x baseline value 27% 19% ALT ≥3 x baseline value c 21% 8% ALT ≥2 x baseline value and absolute ALT >500 IU/L 15% 7% ALT ≥2 x baseline value; and bilirubin >2 x ULN and ≥2 x baseline value 0.7% 0.9% Clinical Trials Experience in Pediatric Subjects with Chronic HBV Infection Most commonly observed adverse reactions in the pediatric trials were similar to those in adult trials. Posttreatment…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Sorbitol: Coadministration of lamivudine and sorbitol may result in decreased lamivudine concentrations; when possible, avoid chronic coadministration. Consider more frequent monitoring of HBV viral load when chronic coadministration cannot be avoided. ( 7.2 )
7.1Drugs Inhibiting Organic Cation Transporters Lamivudine is predominantly eliminated in the urine by active organic cationic secretion. The possibility of interactions with other drugs administered concurrently should be considered, particularly when their main route of elimination is active renal secretion via the organic cationic transport system (e.g., trimethoprim) [see Clinical Pharmacology ( 12.3 )] . No data are available regarding interactions with other drugs that have renal clearance mechanisms similar to that of lamivudine.
7.2Sorbitol Coadministration of single doses of lamivudine and sorbitol resulted in a sorbitol dose-dependent reduction in lamivudine exposures. When possible, avoid use of sorbitol-containing medicines with lamivudine [see Clinical Pharmacology ( 12.3 )] . Consider more frequent monitoring of HBV viral load when chronic coadministration cannot be avoided.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to lamivudine during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Available data from the APR show no substantial difference in the risk of overall major birth defects for lamivudine compared with the background rate for major birth defects of 2.7% reported in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP).
The APR uses the MACDP as a U.S. reference population for birth defects in the general population. The MACDP evaluates women and infants from a limited geographic area and does not include outcomes for births that occur at less than 20 weeks’ gestation. Of over 12,900 women exposed to lamivudine in the APR, less than 2% were HBV mono-infected.
The majority of women exposed to lamivudine in the APR were HIV-1-infected and were treated with higher doses of lamivudine compared with HBV mono-infected women. In addition to lamivudine, HIV-1-infected women were also treated with other concomitant medications for HIV-1 infection [see Data]. The estimated rate of miscarriage for women exposed to lamivudine in the indicated population is unknown.
The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15% to 20%. Oral administration of lamivudine to pregnant rabbits during organogenesis resulted in embryolethality at systemic exposure (AUC) similar to the recommended clinical dose; however, no adverse developmental effects were observed with oral administration of lamivudine to pregnant rats during organogenesis at plasma concentrations (C max ) 60 times the recommended clinical dose [see Data] . Data Human Data Based on prospective reports from the APR of over 12,900 exposures to lamivudine during pregnancy resulting in live births (including over 5,400 exposed in the first trimester and over 7,500 exposed in the second/third trimester), there was no difference between the overall risk of birth defects with lamivudine compared with the background birth defect rate of 2.7% observed in the U.S. reference population of the MACDP.The prevalence of birth defects in live births was 3.1% (95% CI: 2.7% to 3.6%) following first trimester exposure to lamivudine-containing regimens and 2.9% (95% CI: 2.5% to 3.3%) following second/third trimester exposure to lamivudine-containing regimens.
The pharmacokinetics of lamivudine in patients with HBV or HIV-1 infection and in healthy volunteers are similar at similar doses. Lamivudine pharmacokinetics were studied in pregnant women with HIV-1 infection during 2 clinical trials conducted in South Africa. The trials assessed pharmacokinetics in 16 women at 36 weeks gestation using 150 mg lamivudine twice daily (3 times the recommended daily dosage for HBV) with zidovudine, 10 women at 38 weeks gestation using 150 mg lamivudine twice daily (3 times the recommended daily dosage for HBV) with zidovudine, and 10 women at 38 weeks gestation using lamivudine 300 mg twice daily (6 times the recommended daily dosage for HBV) without other antiretrovirals.
Lamivudine concentrations were generally similar in maternal, neonatal, and umbilical cord serum samples. In a subset of subjects, amniotic fluid specimens were collected following natural rupture of membranes and confirmed that lamivudine crosses the placenta in humans. Based on limited data at delivery, median (range) amniotic fluid concentrations of lamivudine were 3.9- (1.2- to 12.8-) fold greater compared with paired maternal serum concentrations (n = 8).
Animal Data Lamivudine was administered orally to pregnant rats (at 90, 600, and 4,000 mg per kg per day) and rabbits (at 90, 300, and 1,000 mg per kg per day and at 15, 40, and 90 mg per kg per day) during organogenesis (on Gestati…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to lamivudine during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Available data from the APR show no substantial difference in the risk of overall major birth defects for lamivudine compared with the background rate for major birth defects of 2.7% reported in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP).
The APR uses the MACDP as a U.S. reference population for birth defects in the general population. The MACDP evaluates women and infants from a limited geographic area and does not include outcomes for births that occur at less than 20 weeks’ gestation. Of over 12,900 women exposed to lamivudine in the APR, less than 2% were HBV mono-infected.
The majority of women exposed to lamivudine in the APR were HIV-1-infected and were treated with higher doses of lamivudine compared with HBV mono-infected women. In addition to lamivudine, HIV-1-infected women were also treated with other concomitant medications for HIV-1 infection [see Data]. The estimated rate of miscarriage for women exposed to lamivudine in the indicated population is unknown.
The estimated background rate of miscarriage in clinically recognized pregnancies in the U.S. general population is 15% to 20%. Oral administration of lamivudine to pregnant rabbits during organogenesis resulted in embryolethality at systemic exposure (AUC) similar to the recommended clinical dose; however, no adverse developmental effects were observed with oral administration of lamivudine to pregnant rats during organogenesis at plasma concentrations (C max ) 60 times the recommended clinical dose [see Data] . Data Human Data Based on prospective reports from the APR of over 12,900 exposures to lamivudine during pregnancy resulting in live births (including over 5,400 exposed in the first trimester and over 7,500 exposed in the second/third trimester), there was no difference between the overall risk of birth defects with lamivudine compared with the background birth defect rate of 2.7% observed in the U.S. reference population of the MACDP.The prevalence of birth defects in live births was 3.1% (95% CI: 2.7% to 3.6%) following first trimester exposure to lamivudine-containing regimens and 2.9% (95% CI: 2.5% to 3.3%) following second/third trimester exposure to lamivudine-containing regimens.
The pharmacokinetics of lamivudine in patients with HBV or HIV-1 infection and in healthy volunteers are similar at similar doses. Lamivudine pharmacokinetics were studied in pregnant women with HIV-1 infection during 2 clinical trials conducted in South Africa. The trials assessed pharmacokinetics in 16 women at 36 weeks gestation using 150 mg lamivudine twice daily (3 times the recommended daily dosage for HBV) with zidovudine, 10 women at 38 weeks gestation using 150 mg lamivudine twice daily (3 times the recommended daily dosage for HBV) with zidovudine, and 10 women at 38 weeks gestation using lamivudine 300 mg twice daily (6 times the recommended daily dosage for HBV) without other antiretrovirals.
Lamivudine concentrations were generally similar in maternal, neonatal, and umbilical cord serum samples. In a subset of subjects, amniotic fluid specimens were collected following natural rupture of membranes and confirmed that lamivudine crosses the placenta in humans. Based on limited data at delivery, median (range) amniotic fluid concentrations of lamivudine were 3.9- (1.2- to 12.8-) fold greater compared with paired maternal serum concentrations (n = 8).
Animal Data Lamivudine was administered orally to pregnant rats (at 90, 600, and 4,000 mg per kg per day) and rabbits (at 90, 300, and 1,000 mg per kg per day and at 15, 40, and 90 mg per kg per day) during organogenesis (on Gestation Days 7 through 16 [rat] and…
🧒 Pediatric Use ▾
8.4Pediatric Use Lamivudine tablets (HBV) is indicated for the treatment of chronic hepatitis B virus infection in pediatric patients aged 2 to 17 years [ see Indications and Usage ( 1 ) , Clinical Pharmacology ( 12.3 ) , Clinical Studies ( 14.2 ) ]. The safety and efficacy of lamivudine tablets (HBV) in pediatric patients younger than 2 years have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of lamivudine tablets (HBV) did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In general, caution should be exercised in the administration of lamivudine tablets (HBV) in elderly patients reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy [see Dosage and Administration ( 2.4 ), Clinical Pharmacology ( 12.3 )] .
🆘 Overdosage ▾
10 OVERDOSAGE There is no known specific treatment for overdose with lamivudine tablets (HBV). If overdose occurs, the patient should be monitored and standard supportive treatment applied, as required. Because a negligible amount of lamivudine was removed via (4-hour) hemodialysis, continuous ambulatory peritoneal dialysis, and automated peritoneal dialysis, it is not known if continuous hemodialysis would provide clinical benefit in a lamivudine overdose event.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Lamivudine is an antiviral agent with activity against HBV [ see Microbiology ( 12.4 ) ] .
12.3Pharmacokinetics Pharmacokinetics in Adults The pharmacokinetic properties of lamivudine have been studied as single and multiple oral doses ranging from 5 mg to 600 mg per day administered to HBV-infected subjects. Absorption and Bioavailability : Following single oral doses of 100 mg, the peak serum lamivudine concentration (C max ) in HBV-infected patients (steady state) and healthy subjects (single dose) was 1.28 ± 0.56 mcg per mL and 1.05 ± 0.32 mcg per mL (mean ± SD), respectively, which occurred between 0.5 and 2 hours after administration.
The area under the plasma concentration versus time curve (AUC[0-24 h]) following 100-mg lamivudine oral single and repeated daily doses to steady state was 4.3 ± 1.4 (mean ± SD) and 4.7 ± 1.7 mcg•hour per mL, respectively. The relative bioavailability of the tablet and oral solution were demonstrated in healthy subjects. Although the solution demonstrated a slightly higher peak serum concentration (C max ), there was no significant difference in systemic exposure (AUC) between the oral solution and the tablet.
Therefore, the oral solution and the tablet may be used interchangeably. After oral administration of lamivudine once daily to HBV-infected adults, the AUC and C max increased in proportion to dose over the range from 5 mg to 600 mg once daily. Absolute bioavailability in 12 adult subjects was 86% ± 16% (mean ± SD) for the 150-mg tablet and 87% ± 13% for the 10-mg per mL oral solution.
Effects of Food on Oral Absorption: Lamivudine tablets (HBV) may be administered with or without food. The 100-mg tablet was administered orally to 24 healthy subjects on 2 occasions, once in the fasted state and once with food (standard meal: 967 kcal; 67 grams fat, 33 grams protein, 58 grams carbohydrate). There was no significant difference in systemic exposure (AUC) in the fed and fasted states.
Distribution: The apparent volume of distribution after IV administration of lamivudine to 20 HIV-1-infected subjects was 1.3 ±
0.4L per kg, suggesting that lamivudine distributes into extravascular spaces. Volume of distribution was independent of dose and did not correlate with body weight. Binding of lamivudine to human plasma proteins is less than 36%.
In vitro studies showed that over the concentration range of 0.1 to 100 mcg per mL, the amount of lamivudine associated with erythrocytes ranged from 53% to 57% and was independent of concentration. Metabolism: Metabolism of lamivudine is a minor route of elimination. In humans, the only known metabolite of lamivudine is the trans-sulfoxide metabolite (approximately 5% of an oral dose after 12 hours).
Serum concentrations of this metabolite have not been determined. Lamivudine is not significantly metabolized by cytochrome P450 enzymes. Elimination: The majority of lamivudine is eliminated unchanged in urine by active organic cationic secretion.
In 9 healthy subjects given a single 300-mg oral dose of lamivudine, renal clearance was 199.7 ± 56.9 mL per min (mean ± SD). In 20 HIV-1-infected subjects given a single IV dose, renal clearance was 280.4 ± 75.2 mL per min (mean ± SD), representing 71% ± 16% (mean ± SD) of total clearance of lamivudine. In most single-dose trials with plasma sampling for up to 48 or 72 hours after dosing, the observed mean elimination half-life (t½) ranged from 13 to 19 hours.
In HIV-1-infected subjects, total clearance was 398.5 ± 69.1 mL per min (mean ± SD). Oral clearance and elimination half-life were independent of dose and body weight over an oral dosing range of 0.25 to 10 mg per kg. Spe cific Populations Patients with Renal Impairmen t The pharmacokinetic properties of lamivudine have been determined in healthy adults and in adults with impaired renal function, with and without hemodialysis (Table 5).
Table 5. Pharmacokinetic Parameters (Mean ± SD) Dose-Normalized to a S…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Lamivudine is an antiviral agent with activity against HBV [ see Microbiology ( 12.4 ) ] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Lamivudine tablets (HBV), 100 mg, are orange-brown, capsule shaped, biconvex film-coated tablets engraved “APO” on one side, “LMV 100” on the other side. Bottles of 60 tablets (NDC 60505-3250-6) with child-resistant closures. Store at 20ºC to 25ºC (68ºF to 77ºF); excursions permitted from 15ºC to 30ºC (59ºF to 86ºF) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Lamivudine tablets (HBV) is a synthetic nucleoside analogue with activity against HBV. The drug substance used in lamivudine tablets (HBV) is lamivudine in the form of lamivudine methanol solvate. The chemical name of lamivudine methanol solvate is (2R,cis)-4-amino-1-(2-hydroxymethyl-1,3-oxathiolan-5-yl) )2(1H)-pyrimidinone methanol solvate.
It has a molecular formula of C 8 H 11 N 3 O 3 S• O.2 CH 4 O C 8 H 11 N 3 O 3 S and a molecular weight of 235.66 g/mol. It has the following structural formula: Lamivudine is a white to off-white powder. It is highly soluble in water.
Lamivudine tablets (HBV) are for oral administration. Each tablet contains lamivudine methanol solvate equivalent to 100 mg of lamivudine and the inactive ingredients anhydrous lactose, colloidal silicon dioxide, crospovidone, ferric oxide red, ferric oxide yellow, hydroxypropyl cellulose, hypromellose, magnesium stearate, polyethylene glycol and titanium dioxide. Meets with USP dissolution test # 2
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Severe Acute Exacerbation of Hepatitis after Discontinuation of Treatment Inform patients that discontinuation of anti-hepatitis B therapy, including lamivudine tablets (HBV), may result in severe acute exacerbations of hepatitis B including decompensation of liver disease. Advise patients not to discontinue lamivudine tablets (HBV) without first informing their healthcare provider [see Warnings and Precautions ( 5.1 ) ] .
Risk of Development of HIV-1 Resistance in Patients with HIV-1 Co-infection Counsel patients on the importance of testing for HIV to avoid inappropriate therapy and development of resistance to HIV. HIV counseling and testing should be offered before starting lamivudine tablets (HBV) and periodically during therapy. Inform patients that if they have or develop HIV infection and are not receiving effective HIV treatment, lamivudine tablets (HBV) may increase the risk of development of resistance to HIV medications.
Advise patients that lamivudine tablets (HBV) contains a lower dose of the same active ingredient (lamivudine) as HIV drugs containing lamivudine [see Dosage and Administration ( 2.1 ), Warnings and Precautions ( 5.2 ) ] . Emergence of HBV Resistance Inform patients that emergence of resistant hepatitis B virus and worsening of disease can occur during treatment. Patients should promptly report any new or worsening symptoms to their physician [see Warnings and Precautions ( 5.3 ) ] .
Lactic Acidosis/Severe Hepatomegaly with Steatosis Advise patients that lactic acidosis and severe hepatomegaly with steatosis have been reported with use of nucleoside analogues and other antiretrovirals. Advise patients to stop taking lamivudine tablets (HBV) if they develop clinical symptoms suggestive of lactic acidosis or pronounced hepatotoxicity [see Warnings and Precautions ( 5.4 )]. Hepatitis B Transmission Advise patients that treatment with lamivudine tablets (HBV) has not been shown to reduce the risk of transmission of HBV to others through sexual contact or blood contamination.
Drug Interactions Inform patients that lamivudine tablets (HBV) may interact with some drugs; therefore, patients should be advised to report to their healthcare provider the use of any prescription or non-prescription medication, or herbal products. Advise patients to avoid chronic use of sorbitol-containing prescription and over-the-counter medicines when possible. Taking lamivudine tablets (HBV) with chronically administered sorbitol-containing medicines may decrease the concentrations of lamivudine [see Drug Interactions ( 7.2 )] .
Pregnancy Registry Advise patients that there is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to lamivudine tablets (HBV) during pregnancy [see Use in Specific Populations ( 8.1 )] . Missed Dosage Instruct patients that if they miss a dose of lamivudine tablets (HBV), to take it as soon as they remember. Advise patients not to double their next dose or take more than the prescribed dose [see Dosage and Administration ( 2 )] .
All registered trademarks in this document are the property of their respective owners. APOTEX INC. LAMIVUDINE TABLETS (HBV) 100 mg Manufactured by Manufactured for Apotex Inc.
Apotex Corp. Totonto, Ontario Weston, Florida Canada M9L 1T9 USA 33326 Revised: February 2022 Revision: 7