
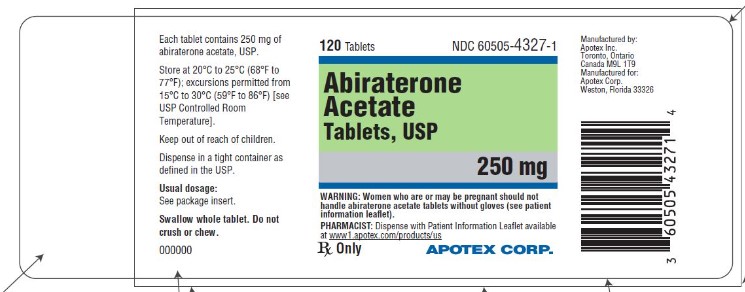
Abiraterone Acetate 250 mg Tablet, 120-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Cytochrome P450 17A1 Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Abiraterone is used in combination with prednisone to treat a certain type of prostate cancer that has spread to other parts of the body. Abiraterone is in a class of medications called androgen biosynthesis inhibitors. It works by decreasing the amount of certain hormones in the body.
Read the full MedlinePlus article ↗- Abiraterone blocks an enzyme that prostate cancer cells use to make the male hormones they need to grow — not just in the testes, but also in the adrenal glands and in the tumor it...
- What exactly does abiraterone do, and why do I need to take it with prednisone?
- Yes, this is really important and it depends on which product you have. Most abiraterone tablets — including Zytiga, Abirtega, and the generics — must be taken on a completely empt...
- Does it matter when I eat? My neighbor takes a different abiraterone and he eats with it.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Abiraterone Acetate — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 68401960MK
Crospovidone is a synthetic polymer made from polyvinylpyrrolidone. It acts as a disintegrant, helping tablets break apart quickly in the stomach so the medicine dissolves and absorbs into the body.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.775 | $92.95 / 120 tablets |
| Medicaid paysCMS SDUD · 12 mo | $4.23 | $507.68 / 120 tablets |
| Medicare drug plans payPart D · Q2 2026 | $10.71 | $1,285.68 / 120 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Abiraterone 250 mg 00143-9597-21 | Hikma | 120 tablets | $0.775 | AB | Availability likely | — |
| Abiraterone Acetate 250 mg 00378-6920-78 | Mylan | 120 tablets | $0.775 | AB | Availability likely | — |
| Abiraterone Acetate 250 mg 00904-6948-04 | Major | 30 tablets | $0.775 | AB | Availability likely | — |
| Abiraterone Acetate 250 mg 16714-0963-01 | NorthStar | 120 tablets | $0.775 | AB | Availability likely | — |
| Abiraterone Acetate 250 mg 43598-0358-04 | Dr. | 120 tablets | $0.775 | AB | Availability likely | — |
| Abiraterone Acetate 250 mg 50268-0032-12 | AvPAK | 20 tablets | $0.775 | AB | Availability likely | — |
| Abiraterone Acetate 250 mg 60219-1165-07 | Amneal | 120 tablets | $0.775 | AB | Availability likely | — |
| Abiraterone Acetate 250 mgthis 60505-4327-01 | Apotex | 120 tablets | $0.775 | AB | Availability likely | — |
| Abiraterone Acetate 250 mg 60687-0790-21 | American | 30 tablets | $0.775 | AB | Availability likely | — |
| Abiraterone acetate 250 mg 64980-0418-12 | Rising | 120 tablets | $0.775 | AB | Availability likely | — |
| Abiraterone 250 mg 68001-0489-07 | BluePoint | 120 tablets | $0.775 | AB | Availability likely | — |
| abiraterone acetate 250 mg 68462-0135-08 | Glenmark | 120 tablets | $0.775 | AB | Availability likely | — |
| Abiraterone Acetate 250 mg 69238-1165-07 | Amneal | 120 tablets | $0.775 | AB | Availability likely | — |
| abiraterone acetate 250 mg 71921-0178-20 | Florida | 120 tablets | $0.775 | AB | Availability likely | — |
| Abiraterone 250 mg 72205-0030-92 | Novadoz | 120 tablets | $0.775 | AB | Availability likely | — |
| abiraterone acetate 250 mg 72603-0110-01 | NORTHSTAR | 120 tablets | $0.775 | AB | Availability likely | — |
| Abiraterone Acetate 250 mg 75907-0224-04 | Dr. | 120 tablets | $0.775 | AB | Availability likely | — |
| Abiraterone 250 mg 82009-0139-12 | Quallent | 120 tablets | $0.775 | AB | Availability likely | — |
| Abiraterone 250 mg 82249-0010-12 | CivicaScript, | 120 tablets | $0.775 | AB | Availability likely | — |
| Abirtega 250 mg 82249-0011-12 | CivicaScript, | 120 tablets | $0.775 | AB | Availability likely | — |
| Abiraterone Acetate 250 mg 82293-0001-10 | Novugen | 120 tablets | $0.775 | AB | Availability likely | — |
| Abiraterone Acetate 250 mg 42291-0024-12 | AvKARE | 120 tablets | — | AB | FDA listed | — |
| Zytiga 250 mg 57894-0150-12 | Janssen | 120 tablets | — | AB | FDA listed | — |
| Abiraterone 250 mg 72205-0284-05 | Novadoz | 500 tablets | — | AB | FDA listed | — |
| Abiraterone 250 mg 72789-0213-98 | PD-Rx | 120 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 60505-4327-01 You're viewing this | 120 TABLET in 1 BOTTLE (60505-4327-1) | 2018-11-23 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Abiraterone acetate tablets are indicated in combination with prednisone for the treatment of patients with Metastatic castration-resistant prostate cancer (CRPC) Metastatic high-risk castration-sensitive prostate cancer (CSPC) Abiraterone acetate tablets are a CYP17 inhibitor indicated in combination with prednisone for the treatment of patients with metastatic castration-resistant prostate cancer (CRPC). ( 1 ) metastatic high-risk castration-sensitive prostate cancer (CSPC). ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Metastatic castration-resistant prostate cancer: Abiraterone acetate tablets 1,000 mg orally once daily with prednisone 5 mg orally twice daily. ( 2.1 ) Metastatic castration-sensitive prostate cancer: Abiraterone acetate tablets 1,000 mg orally once daily with prednisone 5 mg orally once daily. ( 2.2 ) Patients receiving abiraterone acetate tablets should also receive a gonadotropin-releasing hormone (GnRH) analog concurrently or should have had bilateral orchiectomy.
Abiraterone acetate tablets must be taken as a single dose once daily on an empty stomach. Do not eat food 2 hours before and 1 hour after taking abiraterone acetate tablets. The tablets must be swallowed whole with water.
Do not crush or chew tablets. ( 2.3 ) Dose Modification: For patients with baseline moderate hepatic impairment (Child-Pugh Class B), reduce the abiraterone acetate starting dose to 250 mg once daily. ( 2.4 ) For patients who develop hepatotoxicity during treatment, hold abiraterone acetate tablets until recovery.
Retreatment may be initiated at a reduced dose. Abiraterone acetate tablets should be discontinued if patients develop severe hepatotoxicity. ( 2.4 )
2.1Recommended Dose for Metastatic CRPC The recommended dose of abiraterone acetate tablets is 1,000 mg (four 250 mg tablets) orally once daily with prednisone 5 mg orally twice daily.
2.2Recommended Dose for Metastatic High-risk CSPC The recommended dose of abiraterone acetate tablets is 1,000 mg (four 250 mg tablets) orally once daily with prednisone 5 mg administered orally once daily.
2.3Important Administration Instructions Patients receiving abiraterone acetate tablets should also receive a gonadotropin-releasing hormone (GnRH) analog concurrently or should have had bilateral orchiectomy. Abiraterone acetate tablets must be taken as a single dose once daily on an empty stomach. Do not eat food 2 hours before and 1 hour after taking abiraterone acetate tablets.
The tablets must be swallowed whole with water. Do not crush or chew tablets.
2.4Dose Modification Guidelines in Hepatic Impairment and Hepatotoxicity Hepatic Impairment In patients with baseline moderate hepatic impairment (Child-Pugh Class B), reduce the recommended dose of abiraterone acetate to 250 mg once daily. In patients with moderate hepatic impairment monitor ALT, AST, and bilirubin prior to the start of treatment, every week for the first month, every two weeks for the following two months of treatment and monthly thereafter. If elevations in ALT and/or AST greater than 5 x upper limit of normal (ULN) or total bilirubin greater than 3 x ULN occur in patients with baseline moderate hepatic impairment, discontinue abiraterone acetate tablets and do not re-treat patients with abiraterone acetate tablets [see Use in Specific Populations ( 8.6 ) and Clinical Pharmacology ( 12.3 )].
Do not use abiraterone acetate tablets in patients with baseline severe hepatic impairment (Child-Pugh Class C). Hepatotoxicity For patients who develop hepatotoxicity during treatment with abiraterone acetate tablets (ALT and/or AST greater than 5 X ULN or total bilirubin greater than 3 X ULN), interrupt treatment with abiraterone acetate tablets [see Warnings and Precautions ( 5.3 )] . Treatment may be restarted at a reduced dose of 750 mg once daily following return of liver function tests to the patient’s baseline or to AST and ALT less than or equal to
2.5 X ULN and total bilirubin less than or equal to
1.5X ULN. For patients who resume treatment, monitor serum transaminases and bilirubin at a minimum of every two weeks for three months and monthly thereafter. If hepatotoxicity recurs at the dose of 750 mg once daily, re-treatment may be restarted at a reduced dose of 500 mg once daily following return of liver function tests to the patient’s baseline or to AST and ALT less than or equal to
2.5 X ULN and total bilirubin less than or equal to
1.5X ULN. If hepatotoxicity recurs at the reduced dose of 500…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Abiraterone acetate 250 mg tablets, USP are white to off-white, oval, biconvex uncoated tablets. Engraved "A250" on one side, "APO" on the other side. Uncoated Tablet 250 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Mineralocorticoid excess: Closely monitor patients with cardiovascular disease. Control hypertension and correct hypokalemia before treatment. Monitor blood pressure, serum potassium and symptoms of fluid retention at least monthly.
( 5.1 ) Adrenocortical insufficiency: Monitor for symptoms and signs of adrenocortical insufficiency. Increased dosage of corticosteroids may be indicated before, during and after stressful situations. ( 5.2 ) Hepatotoxicity: Can be severe and fatal.
Monitor liver function and modify, interrupt, or discontinue abiraterone acetate dosing as recommended. ( 5.3) Increased fractures and mortality in combination with radium Ra 223 dichloride: Use of abiraterone acetate plus prednisone/prednisolone in combination with radium Ra 223 dichloride is not recommended. ( 5.4 ) Embryo-Fetal Toxicity: Abiraterone acetate can cause fetal harm.
Advise males with female partners of reproductive potential to use effective contraception. ( 5.5 , 8.1 , 8.3 ) Hypoglycemia: Severe hypoglycemia has been reported in patients with pre-existing diabetes who are taking medications containing thiazolidinediones (including pioglitazone) or repaglinide. Monitor blood glucose in patients with diabetes and assess if antidiabetic agent dose modifications are required.
( 5.6)
5.1Hypokalemia, Fluid Retention, and Cardiovascular Adverse Reactions due to Mineralocorticoid Excess Abiraterone acetate may cause hypertension, hypokalemia, and fluid retention as a consequence of increased mineralocorticoid levels resulting from CYP17 inhibition [see Clinical Pharmacology ( 12.1 )] . Monitor patients for hypertension, hypokalemia, and fluid retention at least once a month. Control hypertension and correct hypokalemia before and during treatment with abiraterone acetate.
In the combined data from 4 placebo-controlled trials using prednisone 5 mg twice daily in combination with 1,000 mg abiraterone acetate daily, grades 3-4 hypokalemia were detected in 4% of patients on the abiraterone acetate arm and 2% of patients on the placebo arm. Grades 3 to 4 hypertension were observed in 2% of patients each arm and grades 3 to 4 fluid retention in 1% of patients each arm. In LATITUDE (a randomized placebo-controlled, multicenter clinical trial), which used prednisone 5 mg daily in combination with 1,000 mg abiraterone acetate daily, grades 3 to 4 hypokalemia were detected in 10% of patients on the abiraterone acetate arm and 1% of patients on the placebo arm, grades 3 to 4 hypertension were observed in 20% of patients on the abiraterone acetate arm and 10% of patients on the placebo arm.
Grades 3 to 4 fluid retention occurred in 1% of patients each arm [see Adverse Reactions ( 6 )] . Closely monitor patients whose underlying medical conditions might be compromised by increases in blood pressure, hypokalemia or fluid retention, such as those with heart failure, recent myocardial infarction, cardiovascular disease, or ventricular arrhythmia. In postmarketing experience, QT prolongation and Torsades de Pointes have been observed in patients who develop hypokalemia while taking abiraterone acetate.
The safety of abiraterone acetate in patients with left ventricular ejection fraction <50% or New York Heart Association (NYHA) Class III or IV heart failure (in COU-AA-301) or NYHA Class II to IV heart failure (in COU-AA-302 and LATITUDE) has not been established because these patients were excluded from these randomized clinical trials [see Clinical Studies ( 14 )] .
5.2Adrenocortical Insufficiency Adrenal insufficiency occurred in 0.3% of 2230 patients taking abiraterone acetate and in 0.1% of 1763 patients taking placebo in the combined data of the randomized, placebo-controlled clinical studies. Adrenocortical insufficiency was reported in patients receiving abiraterone acetate in combination with prednisone, following interruption of daily steroids and/or with concurrent infection or stress. Monitor patients for symptoms and si…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following are discussed in more detail in other sections of the labeling: Hypokalemia, Fluid Retention, and Cardiovascular Adverse Reactions due to Mineralocorticoid Excess [see Warnings and Precautions (5.1) ] . Adrenocortical Insufficiency [see Warnings and Precautions (5.2) ] . Hepatotoxicity [see Warnings and Precautions (5.3) ] .
Increased Fractures and Mortality in Combination with Radium Ra 223 Dichloride [see Warnings and Precautions ( 5.4 )]. The most common adverse reactions (≥10%) are fatigue, arthralgia, hypertension, nausea, edema, hypokalemia, hot flush, diarrhea, vomiting, upper respiratory infection, cough, and headache. ( 6.1 ).
The most common laboratory abnormalities (>20%) are anemia, elevated alkaline phosphatase, hypertriglyceridemia, lymphopenia, hypercholesterolemia, hyperglycemia, and hypokalemia. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Apotex Corp. at 1-800-706-5575 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Two randomized placebo-controlled, multicenter clinical trials (COU-AA-301 and COU-AA-302) enrolled patients who had metastatic CRPC in which abiraterone acetate was administered orally at a dose of 1,000 mg daily in combination with prednisone 5 mg twice daily in the active treatment arms.
Placebo plus prednisone 5 mg twice daily was given to patients on the control arm. Another randomized placebo-controlled, multicenter clinical trial (LATITUDE) enrolled patients who had metastatic high-risk CSPC in which abiraterone acetate tablets was administered at a dose of 1,000 mg daily in combination with prednisone 5 mg once daily. Placebos were administered to patients in the control arm.
Additionally, two other randomized, placebo-controlled trials were conducted in patients with metastatic CRPC. The safety data pooled from 2230 patients in the randomized controlled trials constitute the basis for the data presented in the Warnings and Precautions, Grade 1 to 4 adverse reactions, and Grade 1 to 4 laboratory abnormalities. In all trials, a gonadotropin-releasing hormone (GnRH) analog or prior orchiectomy was required in both arms.
In the pooled data, median treatment duration was 11 months (0.1, 43) for abiraterone acetate-treated patients and 7.2 months (0.1, 43) for placebo-treated patients. The most common adverse reactions (≥10%) that occurred more commonly (>2%) in the abiraterone acetate arm were fatigue, arthralgia, hypertension, nausea, edema, hypokalemia, hot flush, diarrhea, vomiting, upper respiratory infection, cough, and headache. The most common laboratory abnormalities (>20%) that occurred more commonly (≥2%) in the abiraterone acetate arm were anemia, elevated alkaline phosphatase, hypertriglyceridemia, lymphopenia, hypercholesterolemia, hyperglycemia, and hypokalemia.
Grades 3 to 4 adverse events were reported for 53% of patients in the abiraterone acetate arm and 46% of patients in the placebo arm. Treatment discontinuation was reported in 14% of patients in the abiraterone acetate arm and 13% of patients in the placebo arm. The common adverse events (≥1%) resulting in discontinuation of abiraterone acetate and prednisone were hepatotoxicity and cardiac disorders.
Deaths associated with treatment-emergent adverse events were reported for 7.5% of patients in the abiraterone acetate arm and 6.6% of patients in the placebo arm. Of the patients in the abiraterone acetate arm, the most common cause of death was disease progression (3.3%). Other reported causes of death in ≥ 5 patients included pneumonia, cardio-respiratory arrest, death (no additional information), and general physical health deterioration.
COU-AA-301 : Metastatic CRPC Following C…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS CYP3A4 Inducers: Avoid concomitant strong CYP3A4 inducers during abiraterone acetate treatment. If a strong CYP3A4 inducer must be co-administered, increase the abiraterone acetate dosing frequency. ( 2.5 , 7.1 ) CYP2D6 Substrates: Avoid co-administration of abiraterone acetate with CYP2D6 substrates that have a narrow therapeutic index.
If an alternative treatment cannot be used, exercise caution and consider a dose reduction of the concomitant CYP2D6 substrate. ( 7.2 )
7.1Drugs that Inhibit or Induce CYP3A4 Enzymes Based on in vitro data, abiraterone acetate is a substrate of CYP3A4. In a dedicated drug interaction trial, co-administration of rifampin, a strong CYP3A4 inducer, decreased exposure of abiraterone by 55%. Avoid concomitant strong CYP3A4 inducers during abiraterone acetate treatment.
If a strong CYP3A4 inducer must be co-administered, increase the abiraterone acetate dosing frequency [see Dosage and Administration ( 2.5 ) and Clinical Pharmacology ( 12.3 )] . In a dedicated drug interaction trial, co-administration of ketoconazole, a strong inhibitor of CYP3A4, had no clinically meaningful effect on the pharmacokinetics of abiraterone [see Clinical Pharmacology ( 12.3 )] .
7.2Effects of Abiraterone on Drug Metabolizing Enzymes Abiraterone acetate is an inhibitor of the hepatic drug-metabolizing enzymes CYP2D6 and CYP2C8. In a CYP2D6 drug-drug interaction trial, the C max and AUC of dextromethorphan (CYP2D6 substrate) were increased 2.8- and 2.9-fold, respectively, when dextromethorphan was given with abiraterone acetate 1,000 mg daily and prednisone 5 mg twice daily. Avoid co-administration of abiraterone acetate with substrates of CYP2D6 with a narrow therapeutic index (e.g., thioridazine).
If alternative treatments cannot be used, consider a dose reduction of the concomitant CYP2D6 substrate drug [see Clinical Pharmacology ( 12.3 )] . In a CYP2C8 drug-drug interaction trial in healthy subjects, the AUC of pioglitazone (CYP2C8 substrate) was increased by 46% when pioglitazone was given together with a single dose of 1,000 mg abiraterone acetate. Therefore, patients should be monitored closely for signs of toxicity related to a CYP2C8 substrate with a narrow therapeutic index if used concomitantly with abiraterone acetate [see Clinical Pharmacology ( 12.3 ) and Warnings and Precautions ( 5.6 )] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Do not use abiraterone acetate tablets in patients with baseline severe hepatic impairment (Child-Pugh Class C). ( 8.6 )
8.1Pregnancy Risk Summary The safety and efficacy of abiraterone acetate have not been established in females. Based on findings from animal studies and the mechanism of action, abiraterone acetate can cause fetal harm and potential loss of pregnancy. There are no human data on the use of abiraterone acetate in pregnant women.
In animal reproduction studies, oral administration of abiraterone acetate to pregnant rats during organogenesis caused adverse developmental effects at maternal exposures approximately ≥ 0.03 times the human exposure (AUC) at the recommended dose (see Data). Data Animal Data In an embryo-fetal developmental toxicity study in rats, abiraterone acetate caused developmental toxicity when administered at oral doses of 10, 30 or 100 mg/kg/day throughout the period of organogenesis (gestational days 6 to 17). Findings included embryo-fetal lethality (increased post implantation loss and resorptions and decreased number of live fetuses), fetal developmental delay (skeletal effects) and urogenital effects (bilateral ureter dilation) at doses ≥10 mg/kg/day, decreased fetal ano-genital distance at ≥30 mg/kg/day, and decreased fetal body weight at 100 mg/kg/day.
Doses ≥10 mg/kg/day caused maternal toxicity. The doses tested in rats resulted in systemic exposures (AUC) approximately 0.03, 0.1 and 0.3 times, respectively, the AUC in patients.
8.2Lactation Risk Summary The safety and efficacy of abiraterone acetate have not been established in females. There is no information available on the presence of abiraterone acetate in human milk, or on the effects on the breastfed child or milk production.
8.3Females and Males of Reproductive Potential Contraception Males Based on findings in animal reproduction studies and its mechanism of action, advise males with female partners of reproductive potential to use effective contraception during treatment and for 3 weeks after the final dose of abiraterone acetate [see Use in Specific Populations ( 8.1 )] . Infertility Based on animal studies, abiraterone acetate may impair reproductive function and fertility in males of reproductive potential [see Nonclinical Toxicology ( 13.1 )] .
8.4Pediatric Use Safety and effectiveness of abiraterone acetate in pediatric patients have not been established.
8.5Geriatric Use Of the total number of patients receiving abiraterone acetate in randomized clinical trials, 70% of patients were 65 years and over and 27% were 75 years and over. No overall differences in safety or effectiveness were observed between these elderly patients and younger patients. Other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
8.6Patients with Hepatic Impairment The pharmacokinetics of abiraterone were examined in subjects with baseline mild (N=8) or moderate (N=8) hepatic impairment (Child-Pugh Class A and B, respectively) and in 8 healthy control subjects with normal hepatic function. The systemic exposure (AUC) of abiraterone after a single oral 1,000 mg dose of abiraterone acetate increased by approximately 1.1-fold and 3.6-fold in subjects with mild and moderate baseline hepatic impairment, respectively compared to subjects with normal hepatic function.
In another trial, the pharmacokinetics of abiraterone were examined in subjects with baseline severe (N=8) hepatic impairment (Child-Pugh Class C) and in 8 healthy control subjects with normal hepatic function. The systemic exposure (AUC) of abiraterone increased by approximately 7-fold and the fraction of free drug increased 2-fold in subjects with severe baseline hepatic impairment compared to subjects with normal hepatic function. No dosage adjustment is necessary for patients with baseline mild hepatic impairment.
I…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary The safety and efficacy of abiraterone acetate have not been established in females. Based on findings from animal studies and the mechanism of action, abiraterone acetate can cause fetal harm and potential loss of pregnancy. There are no human data on the use of abiraterone acetate in pregnant women.
In animal reproduction studies, oral administration of abiraterone acetate to pregnant rats during organogenesis caused adverse developmental effects at maternal exposures approximately ≥ 0.03 times the human exposure (AUC) at the recommended dose (see Data). Data Animal Data In an embryo-fetal developmental toxicity study in rats, abiraterone acetate caused developmental toxicity when administered at oral doses of 10, 30 or 100 mg/kg/day throughout the period of organogenesis (gestational days 6 to 17). Findings included embryo-fetal lethality (increased post implantation loss and resorptions and decreased number of live fetuses), fetal developmental delay (skeletal effects) and urogenital effects (bilateral ureter dilation) at doses ≥10 mg/kg/day, decreased fetal ano-genital distance at ≥30 mg/kg/day, and decreased fetal body weight at 100 mg/kg/day.
Doses ≥10 mg/kg/day caused maternal toxicity. The doses tested in rats resulted in systemic exposures (AUC) approximately 0.03, 0.1 and 0.3 times, respectively, the AUC in patients.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of abiraterone acetate in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of patients receiving abiraterone acetate in randomized clinical trials, 70% of patients were 65 years and over and 27% were 75 years and over. No overall differences in safety or effectiveness were observed between these elderly patients and younger patients. Other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE Human experience of overdose with abiraterone acetate is limited. There is no specific antidote. In the event of an overdose, stop abiraterone acetate, undertake general supportive measures, including monitoring for arrhythmias and cardiac failure and assess liver function.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Abiraterone acetate is converted in vivo to abiraterone, an androgen biosynthesis inhibitor, that inhibits 17 α-hydroxylase/C17,20-lyase (CYP17). This enzyme is expressed in testicular, adrenal, and prostatic tumor tissues and is required for androgen biosynthesis. CYP17 catalyzes two sequential reactions: 1) the conversion of pregnenolone and progesterone to their 17α-hydroxy derivatives by 17α-hydroxylase activity and 2) the subsequent formation of dehydroepiandrosterone (DHEA) and androstenedione, respectively, by C17, 20 lyase activity.
DHEA and androstenedione are androgens and are precursors of testosterone. Inhibition of CYP17 by abiraterone can also result in increased mineralocorticoid production by the adrenals [see Warnings and Precautions (5.1) ] . Androgen sensitive prostatic carcinoma responds to treatment that decreases androgen levels.
Androgen deprivation therapies, such as treatment with GnRH agonists or orchiectomy, decrease androgen production in the testes but do not affect androgen production by the adrenals or in the tumor. Abiraterone acetate decreased serum testosterone and other androgens in patients in the placebo-controlled clinical trial. It is not necessary to monitor the effect of abiraterone acetate on serum testosterone levels.
Changes in serum prostate specific antigen (PSA) levels may be observed but have not been shown to correlate with clinical benefit in individual patients.
12.2Pharmacodynamics Cardiac Electrophysiology In a multi-center, open-label, single-arm trial, 33 patients with metastatic CRPC received abiraterone acetate orally at a dose of 1,000 mg once daily at least 1 hour before or 2 hours after a meal in combination with prednisone 5 mg orally twice daily. Assessments up to Cycle 2 Day 2 showed no large changes in the QTc interval (i.e., >20 ms) from baseline. However, small increases in the QTc interval (i.e., <10 ms) due to abiraterone acetate cannot be excluded due to study design limitations.
12.3Pharmacokinetics Following administration of abiraterone acetate, the pharmacokinetics of abiraterone have been studied in healthy subjects and in patients with metastatic CRPC. In vivo , abiraterone acetate is converted to abiraterone. In clinical studies, abiraterone acetate plasma concentrations were below detectable levels (<0.2 ng/mL) in >99% of the analyzed samples.
Absorption Following oral administration of abiraterone acetate to patients with metastatic CRPC, the median time to reach maximum plasma abiraterone concentrations is 2 hours. Abiraterone accumulation is observed at steady-state, with a 2-fold higher exposure (steady-state AUC) compared to a single 1,000 mg dose of abiraterone acetate. At the dose of 1,000 mg daily in patients with metastatic CRPC, steady-state values (mean ± SD) of C max were 226 ± 178 ng/mL and of AUC were 993 ± 639 ng.hr/mL.
No major deviation from dose proportionality was observed in the dose range of 250 mg to 1,000 mg. However, the exposure was not significantly increased when the dose was doubled from 1,000 to 2,000 mg (8% increase in the mean AUC). Effect of Food Systemic exposure of abiraterone is increased when abiraterone acetate is administered with food.
In healthy subjects abiraterone C max and AUC 0-∞ were approximately 7- and 5-fold higher, respectively, when a single dose of abiraterone acetate was administered with a low-fat meal (7% fat, 300 calories) and approximately 17- and 10-fold higher, respectively, when a single dose of abiraterone acetate was administered with a high-fat (57% fat, 825 calories) meal compared to overnight fasting. Abiraterone AUC 0-∞ was approximately 7-fold or 1.6-fold higher, respectively, when a single dose of abiraterone acetate was administered 2 hours after or 1 hour before a medium fat meal (25% fat, 491 calories) compared to overnight fasting.
Systemic exposures of abiraterone in patients with metastatic CRPC, after repeated dosing of abirate…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Abiraterone acetate is converted in vivo to abiraterone, an androgen biosynthesis inhibitor, that inhibits 17 α-hydroxylase/C17,20-lyase (CYP17). This enzyme is expressed in testicular, adrenal, and prostatic tumor tissues and is required for androgen biosynthesis. CYP17 catalyzes two sequential reactions: 1) the conversion of pregnenolone and progesterone to their 17α-hydroxy derivatives by 17α-hydroxylase activity and 2) the subsequent formation of dehydroepiandrosterone (DHEA) and androstenedione, respectively, by C17, 20 lyase activity.
DHEA and androstenedione are androgens and are precursors of testosterone. Inhibition of CYP17 by abiraterone can also result in increased mineralocorticoid production by the adrenals [see Warnings and Precautions (5.1) ] . Androgen sensitive prostatic carcinoma responds to treatment that decreases androgen levels.
Androgen deprivation therapies, such as treatment with GnRH agonists or orchiectomy, decrease androgen production in the testes but do not affect androgen production by the adrenals or in the tumor. Abiraterone acetate decreased serum testosterone and other androgens in patients in the placebo-controlled clinical trial. It is not necessary to monitor the effect of abiraterone acetate on serum testosterone levels.
Changes in serum prostate specific antigen (PSA) levels may be observed but have not been shown to correlate with clinical benefit in individual patients.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Abiraterone acetate 250 mg tablets, USP are white to off-white, oval, biconvex uncoated tablets. Engraved "A250" on one side, "APO" on the other side. Abiraterone acetate 250 mg tablets, USP are available in high-density polyethylene bottles of 120.
Bottle of 120 tablets NDC Number 60505-4327-1 Storage and Handling Store at 20°C to 25°C (68°F to 77°F); excursions permitted from 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature]. Keep out of reach of children. Based on its mechanism of action, abiraterone acetate may harm a developing fetus.
Women who are pregnant or women who may be pregnant should not handle abiraterone acetate 250 mg uncoated tablets or other abiraterone acetate tablets if broken, crushed, or damaged without protection, e.g., gloves [see Use in Specific Populations ( 8.1 )] .
📋 Description ▾
11 DESCRIPTION Abiraterone acetate, USP the active ingredient of abiraterone acetate tablets, USP is the acetyl ester of abiraterone. Abiraterone is an inhibitor of CYP17 (17α-hydroxylase/C17,20-lyase). Each abiraterone acetate tablet, USP contains 250 mg of abiraterone acetate, USP.
Abiraterone acetate, USP is designated chemically as (3β)-17-(3-pyridinyl) androsta-5,16-dien-3-yl acetate and its structure is: Abiraterone acetate, USP is a white to off-white, non-hygroscopic, crystalline powder. Its molecular formula is C 26 H 33 NO 2 and it has a molecular weight of 391.55 g/mol. Abiraterone acetate, USP is a lipophilic compound with an octanol-water partition coefficient of 5.12 (Log P) and is practically insoluble in water.
The pKa of the aromatic nitrogen is 5.19. Abiraterone acetate tablets are available in 250 mg uncoated tablets with the following inactive ingredients: colloidal silicon dioxide, crospovidone, lactose monohydrate, magnesium stearate, and sodium lauryl sulfate.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information ) Hypokalemia, Fluid Retention, and Cardiovascular Adverse Reactions Inform patients that abiraterone acetate is associated with hypertension, hypokalemia, and peripheral edema that may lead to QT prolongation and Torsades de Pointes in patients who develop hypokalemia while taking abiraterone acetate. Advise patients that their blood pressure, serum potassium and signs and symptoms of fluid retention will be monitored clinically at least monthly.
Advise patients to adhere to corticosteroids and to report symptoms of hypertension, hypokalemia, or edema to their healthcare provider [see Warnings and Precautions ( 5.1 )] . Adrenocortical Insufficiency Inform patients that abiraterone acetate with prednisone is associated with adrenal insufficiency. Advise patients to report symptoms of adrenocortical insufficiency to their healthcare provider [see Warnings and Precautions ( 5.2 )] .
Hepatotoxicity Inform patients that abiraterone acetate is associated with severe hepatotoxicity. Inform patients that their liver function will be monitored using blood tests. Advise patients to immediately report symptoms of hepatotoxicity to their healthcare provider [see Warnings and Precautions ( 5.3 )] .
Hypoglycemia Inform patients that severe hypoglycemia has been reported when abiraterone acetate was administered to patients with pre-existing diabetes who were receiving medications containing thiazolidinediones (including pioglitazone) or repaglinide, antidiabetic drugs. Advise patients with diabetes to monitor glucose levels during and after treatment with abiraterone acetate [see Warnings and Precautions (5.6) and Drug Interactions (7.2)]. Use in Combination with Radium Ra 223 Dichloride Advise patients that radium Ra 223 dichloride showed an increase in mortality and an increased rate of fracture when used in combination with abiraterone acetate plus prednisone/prednisolone.
Inform patients to speak with their healthcare provider about any other medications or treatment they are currently taking for prostate cancer [see Warnings and Precautions ( 5.4 )]. Dosing and Administration Inform patients that abiraterone acetate tablets are taken once daily with prednisone (twice daily according to their healthcare provider’s instructions) and to not interrupt or stop either of these medications without consulting their healthcare provider. Inform patients receiving GnRH therapy that they need to maintain this treatment during the course of treatment with abiraterone acetate.
Instruct patients to take abiraterone acetate tablets as a single dose once daily on an empty stomach. Instruct patients to not eat food 2 hours before and 1 hour after taking abiraterone acetate tablets. Abiraterone acetate tablets taken with food causes increased exposure and may result in adverse reactions.
Instruct patients to swallow tablets whole with water and not to crush or chew the tablets [see Dosage and Administration ( 2.3 )] . Inform patients that if they miss a dose of abiraterone acetate tablets or prednisone, they should take their normal dose the following day. If more than one daily dose is skipped, inform patients to contact their healthcare provider [see Dosage and Administration ( 2.3 )] .
Embryo-Fetal Toxicity Inform patients that abiraterone acetate may harm a developing fetus and can cause loss of pregnancy. Advise males with female partners of reproductive potential to use effective contraception during treatment and for 3 weeks after the final dose of abiraterone acetate tablets [see Use in Specific Populations ( 8.1 )] . Advise females who are pregnant or women who may be pregnant not to handle abiraterone acetate 250 mg uncoated tablets or other abiraterone tablets if broken, crushed, or damaged without protection, e.g., gloves [see Use in Specific Populations ( 8.1 ) and How Supplied/Storage and Handling ( 16 )] .
Infertility Advis…