
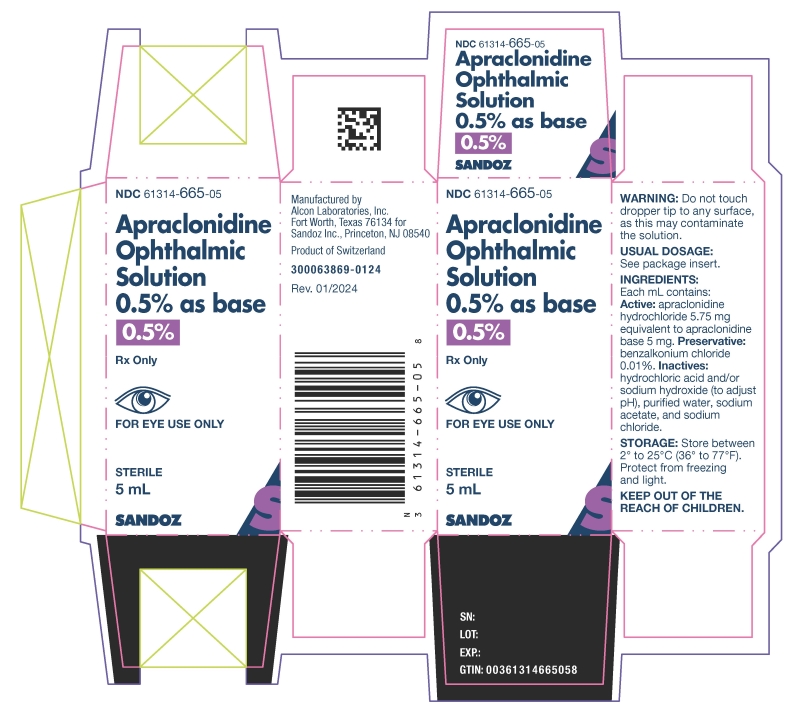
Apraclonidine 5.75 mg/mL Solution, 5 mL — NDC 61314-665-05 (Billing 61314-0665-05)
This is a package of 5 mL of Apraclonidine 5.75 mg/mL Solution from Sandoz Inc, marketed since Jul 2009 and currently FDA-listed; retail pharmacies pay about $9.16 per mL (NADAC). It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 61314-665-05 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 61314 labeler · 665 product · 05 package
- Package marketed since
- Jul 19, 2009
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 5 mL per package
- Barcode (UPC)
- 0361314665058, 0361314665102
- Medicaid fills, this package
- 648 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Past resolved recalls for this product (1)
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 020845
- GCN: 21081
- GPI-14 (Medi-Span): 86602010102010
- HICL (First Databank): 003441
- AHFS class code: 52:40.04.00
- RxCUI (RxNorm): 308345
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the alpha-Adrenergic Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Apraclonidine 0.5% eye drops are used for the short-term treatment of glaucoma (a condition that can cause damage to the optic nerve and vision loss, usually due to increased pressure in the eye) in people who are taking other medications for this condition and still have increased pressure in the eye. Apraclonidine 1% eye drops are used to prevent or reduce increased pressure in the eye during and after certain types of laser eye surgery. Apraclonidine is in a class of medications called alpha-2-adrenergic agonists. It lowers the pressure in the eye by decreasing the amount of fluid produced...
Read the full MedlinePlus article ↗- It's used to lower the pressure inside your eye — called intraocular pressure or IOP — when you have glaucoma. It's specifically for people who are already using as many glaucoma m...
- What is apraclonidine eye drops actually used for?
- Place one to two drops into your affected eye(s) three times a day. If you use other eye drops, wait about 5 minutes between each one — this prevents the first drop from being rins...
- How do I use the drops, and what if I use other eye drops too?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Apraclonidine — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $9.156 | $45.78 / 5 ml |
| Medicaid paysCMS SDUD · 12 mo | $10.74 | $53.70 / 5 ml |
| Medicare drug plans payPart D · Q2 2026 | $11.65 | $58.25 / 5 ml |
Where does this data come from?
- CMS NADAC weekly file · file of Oct 7, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 61314-0665-05 You're viewing this Main listing | 5 mL in 1 BOTTLE | $9.16 / mL | $45.78 | 2009-07-19 | — | Active |
| 61314-0665-10 61314-665-10 | 10 mL in 1 BOTTLE | $9.42 / mL | $94.22 | 2009-07-19 | — | Active |
You're viewing the smallest of 2 pack sizes for this product.
This pack has the lowest per-mL cost of the 2 priced pack sizes ($9.16 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 61314-0665-10?
What NDC number is used to bill for this package of Apraclonidine 5.75 mg/mL Solution?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Apraclonidine 5.75 mg/mLthis 61314-0665-05 | Sandoz | 5 ml | $9.156 | AT | Availability likely | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Oct 7, 2026
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Apraclonidine Ophthalmic inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII F5UM2KM3W7
Benzalkonium chloride is a chemical compound that works as a preservative and antimicrobial agent in medications. It prevents bacterial and fungal growth in liquid formulations to keep the product safe during storage and use.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 4550K0SC9B
Sodium acetate is a salt derived from acetic acid. It acts as a buffer to help maintain the medicine's pH stability and may serve as a preservative or solubilizer in liquid formulations.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Sandoz Inc labeler code 61314
- Neomycin and Polymyxin B Sulfates and Hydrocortisone neomycin sulfate, polymyxin b sulfate 3.5 mg/mL; 10000 [iU]/mL; 10 mg/mL Solution NDC 61314-646-10
- Tobramycin and Dexamethasone 3 mg/mL; 1 mg/mL Suspension/ Drops NDC 61314-647-05
- PYZCHIVA ustekinumab-ttwe 45 mg/.5mL Injection, Solution NDC 61314-651-01
- PYZCHIVA ustekinumab-ttwe 90 mg/mL Injection, Solution NDC 61314-652-01
- PYZCHIVA ustekinumab-ttwe 130 mg/26mL Injection, Solution NDC 61314-654-94
- Ciprofloxacin Hydrochloride 3 mg/mL Solution/ Drops NDC 61314-656-05
- Gatifloxacin 5 mg/mL Solution/ Drops NDC 61314-672-25
- ZIEXTENZO pegfilgrastim-bmez 6 mg/.6mL Injection NDC 61314-866-01
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Apraclonidine ophthalmic solution 0.5% is indicated for short-term adjunctive therapy, in patients on maximally tolerated medical therapy, who require additional IOP reduction. Patients on maximally tolerated medical therapy, who are treated with apraclonidine ophthalmic solution 0.5% to delay surgery, should have frequent follow-up examinations and treatment should be discontinued if the IOP rises significantly. The addition of apraclonidine ophthalmic solution 0.5% to patients already using two aqueous suppressing drugs (i.e., beta-blocker plus carbonic anhydrase inhibitor) as part of their maximally tolerated medical therapy may not provide additional benefit.
This is because apraclonidine ophthalmic solution 0.5% is an aqueous suppressing drug and the addition of a third aqueous suppressant may not significantly reduce IOP. The IOP lowering efficacy of apraclonidine ophthalmic solution 0.5% diminishes over time in some patients. This loss of effect, or tachyphylaxis, appears to be an individual occurrence with a variable time of onset and should be closely monitored.
The benefit for most patients is less than one month.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION One to two drops of apraclonidine ophthalmic solution 0.5% should be instilled in the affected eye(s) three times daily. Since apraclonidine ophthalmic solution 0.5% will be used with other ocular glaucoma therapies, an approximate 5 minute interval between instillation of each medication should be practiced to prevent washout of the previous dose. NOT FOR INJECTION INTO THE EYE. NOT FOR ORAL INGESTION.
⛔ Contraindications ▾
CONTRAINDICATIONS Apraclonidine ophthalmic solution 0.5% is contraindicated in patients with hypersensitivity to apraclonidine or any other component of this medication, as well as systemic clonidine. It is also contraindicated in patients receiving monoamine oxidase (MAO) inhibitors.
⚠️ Warnings ▾
WARNINGS Not for injection or oral ingestion. FOR EYE USE ONLY.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS In clinical studies the overall discontinuation rate related to apraclonidine ophthalmic solution 0.5% was 15%. The most commonly reported events leading to discontinuation included (in decreasing order of frequency) hyperemia, pruritus, tearing, discomfort, lid edema, dry mouth, and foreign body sensation. The following adverse reactions (incidences) were reported in clinical studies of apraclonidine ophthalmic solution 0.5% as being possibly, probably, or definitely related to therapy: Ocular The following adverse reactions were reported in 5% to 15% of the patients: discomfort, hyperemia, and pruritus.
The following adverse reactions were reported in 1% to 5% of the patients: blanching, blurred vision, conjunctivitis, discharge, dry eye, foreign body sensation, lid edema, and tearing. The following adverse reactions were reported in less than 1% of the patients: abnormal vision, blepharitis, blepharoconjunctivitis, conjunctival edema, conjunctival follicles, corneal erosion, corneal infiltrate, corneal staining, edema, irritation, keratitis, keratopathy, lid disorder, lid erythema, lid margin crusting, lid retraction, lid scales, pain, and photophobia.
Nonocular Dry mouth occurred in approximately 10% of the patients. The following adverse reactions were reported in less than 3% of the patients: abnormal coordination, asthenia, arrhythmia, asthma, chest pain, constipation, contact dermatitis, depression, dermatitis, dizziness, dry nose, dyspnea, facial edema, headache, insomnia, malaise, myalgia, nausea, nervousness, paresthesia, parosmia, peripheral edema, pharyngitis, rhinitis, somnolence, and taste perversion. Clinical Practice The following events have been identified during postmarketing use of apraclonidine ophthalmic solution 0.5% in clinical practice.
Because they are reported voluntarily from a population of unknown size, estimates of frequency cannot be made. The events, which have been chosen for inclusion due to either their seriousness, frequency of reporting, possible causal connection to apraclonidine ophthalmic solution 0.5%, or a combination of these factors, include bradycardia and hypersensitivity.
🔄 Drug Interactions ▾
Drug Interactions Apraclonidine should not be used in patients receiving MAO inhibitors (see CONTRAINDICATIONS). Although no specific drug interactions with topical glaucoma drugs or systemic medications were identified in clinical studies of apraclonidine ophthalmic solution 0.5%, the possibility of an additive or potentiating effect with CNS depressants (alcohol, barbiturates, opiates, sedatives, anesthetics) should be considered. Tricyclic antidepressants have been reported to blunt the hypotensive effect of systemic clonidine.
It is not known whether the concurrent use of these agents with apraclonidine can lead to a reduction in IOP lowering effect. No data on the level of circulating catecholamines after apraclonidine withdrawal are available. Caution, however, is advised in patients taking tricyclic antidepressants which can affect the metabolism and uptake of circulating amines.
An additive hypotensive effect has been reported with the combination of systemic clonidine and neuroleptic therapy. Systemic clonidine may inhibit the production of catecholamines in response to insulin-induced hypoglycemia and mask the signs and symptoms of hypoglycemia. Since apraclonidine may reduce pulse and blood pressure, caution in using drugs such as beta-blockers (ophthalmic and systemic), antihypertensives, and cardiac glycosides is advised.
Patients using cardiovascular drugs concurrently with apraclonidine ophthalmic solution 0.5% should have pulse and blood pressures frequently monitored. Caution should be exercised with simultaneous use of clonidine and other similar pharmacologic agents.
🤰 Pregnancy ▾
Pregnancy Apraclonidine HCl has been shown to have an embryocidal effect in rabbits when given in an oral dose of 3.0 mg/kg (60 times the maximum recommended human dose). Dose related maternal toxicity was observed in pregnant rats at 0.3 mg/kg (6 times the maximum recommended human dose). There are no adequate and well controlled studies in pregnant women.
Apraclonidine ophthalmic solution 0.5% should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
Geriatric Use No overall differences in safety or effectiveness have been observed between elderly and younger patients.
🆘 Overdosage ▾
OVERDOSAGE Ingestion of apraclonidine ophthalmic solution 0.5% has been reported to cause bradycardia, drowsiness, and hypothermia. Accidental or intentional ingestion of oral clonidine has been reported to cause apnea, arrhythmias, asthenia, bradycardia, conduction defects, diminished or absent reflexes, dryness of the mouth, hypotension, hypothermia, hypoventilation, irritability, lethargy, miosis, pallor, respiratory depression, sedation or coma, seizure, somnolence, transient hypertension, and vomiting. Treatment of an oral overdose includes supportive and symptomatic therapy; a patent airway should be maintained.
Hemodialysis is of limited value since a maximum of 5% of circulating drug is removed.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Apraclonidine hydrochloride is a relatively selective alpha-2-adrenergic agonist. When instilled in the eye, apraclonidine ophthalmic solution 0.5%, has the action of reducing elevated, as well as normal, intraocular pressure (IOP), whether or not accompanied by glaucoma. Ophthalmic apraclonidine has minimal effect on cardiovascular parameters.
Elevated IOP presents a major risk factor in glaucomatous field loss. The higher the level of IOP, the greater the likelihood of optic nerve damage and visual field loss. Apraclonidine ophthalmic solution 0.5% has the action of reducing IOP.
The onset of action of apraclonidine can usually be noted within one hour, and maximum IOP reduction occurs about three hours after instillation. Aqueous fluorophotometry studies demonstrate that apraclonidine's predominant mechanism of action is reduction of aqueous flow via stimulation of the alpha-adrenergic system. Repeated dose-response and comparative studies (0.125%-1.0% apraclonidine) demonstrate that 0.5% apraclonidine is at the top of the dose-response IOP reduction curve.
The clinical utility of apraclonidine ophthalmic solution 0.5% is most apparent for those glaucoma patients on maximally tolerated medical therapy. Patients on maximally tolerated medical therapy with uncontrolled IOP, and scheduled to undergo laser trabeculoplasty or trabeculectomy surgery were enrolled into a double-masked, placebo-controlled, multicenter clinical trial to determine if apraclonidine ophthalmic solution 0.5%, dosed three times daily, could delay the need for surgery for up to three months. All patients enrolled into this trial had advanced glaucoma and were undergoing maximally tolerated medical therapy, i.e., patients were using combinations of a topical beta blocker, sympathomimetics, parasympathomimetics and oral carbonic anhydrase inhibitors.
Patients were considered to be treatment failures in this study if, in the opinion of the investigators, their IOP was uncontrolled by the masked study medication or there was evidence of further optic nerve damage or visual field loss, and surgery was indicated. Of 171 patients receiving masked medication, 84 were treated with apraclonidine ophthalmic solution 0.5% and 87 were treated with placebo (apraclonidine vehicle). Apraclonidine treatment resulted in a significantly greater percentage of treatment successes compared to patients treated with placebo.
In this placebo-controlled maximum therapy trial, 14.3% of patients treated with apraclonidine ophthalmic solution 0.5% were discontinued due to adverse events, primarily allergic-like reactions (12.9%). The IOP lowering efficacy of apraclonidine ophthalmic solution 0.5% diminishes over time in some patients. This loss of effect, or tachyphylaxis, appears to be an individual occurrence with a variable time of onset and should be closely monitored.
An unpredictable decrease of IOP control in some patients, incidence of ocular allergic responses and systemic side effects, may limit the utility of apraclonidine ophthalmic solution 0.5%. However, patients on maximally tolerated medical therapy may still benefit from the additional IOP reduction provided by the short-term use of apraclonidine ophthalmic solution 0.5%. Topical use of apraclonidine ophthalmic solution 0.5% leads to systemic absorption.
Studies of apraclonidine ophthalmic solution 0.5% dosed one drop three times a day in both eyes for 10 days, in normal volunteers, yielded mean peak and trough concentrations of 0.9 ng/mL and 0.5 ng/mL, respectively. The half-life of apraclonidine ophthalmic solution 0.5% was calculated to be 8 hours. Apraclonidine ophthalmic solution 0.5%, because of its alpha adrenergic activity, is a vasoconstrictor.
Single dose ocular blood flow studies in monkeys, using the microsphere technique, demonstrated a reduced blood flow for the anterior segment; however, no reduction in blood flow was observed in the posterior segment of the eye after a topical do… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Apraclonidine ophthalmic solution 0.5% as base in a sterile, isotonic, aqueous solution containing apraclonidine hydrochloride. Supplied in plastic ophthalmic dispenser as follows: 5 mL NDC 61314-665-05 10 mL NDC 61314-665-10 Storage: Store between 2° to 25°C (36° to 77°F). Protect from freezing and light. To report SUSPECTED ADVERSE REACTIONS, contact Sandoz Inc., at 1-800-525-8747 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
📋 Description ▾
DESCRIPTION Apraclonidine ophthalmic solution 0.5% contains apraclonidine hydrochloride, an alpha adrenergic agonist, in a sterile isotonic solution for topical application to the eye. Apraclonidine hydrochloride is a white to off-white powder and is highly soluble in water. Its chemical name is 2-[(4-amino-2,6 dichlorophenyl) imino]imidazolidine monohydrochloride with an empirical formula of C 9 H 11 Cl 3 N 4 and a molecular weight of 281.57 g/mol.
The chemical structure of apraclonidine hydrochloride is: Each mL of apraclonidine ophthalmic solution 0.5% contains: Active: apraclonidine hydrochloride 5.75 mg equivalent to apraclonidine base 5 mg. Preservative: benzalkonium chloride 0.01%. Inactives: hydrochloric acid and/or sodium hydroxide (to adjust pH), purified water, sodium acetate, and sodium chloride. image
💬 Information for Patients ▾
Information for Patients Do not touch dropper tip to any surface as this may contaminate the contents. The preservative in apraclonidine ophthalmic solution 0.5%, benzalkonium chloride, may be absorbed by soft contact lenses. Contact lenses should be removed during instillation of apraclonidine ophthalmic solution 0.5% but may be reinserted 15 minutes after instillation.
⚠️ Precautions ▾
PRECAUTIONS General Glaucoma patients on maximally tolerated medical therapy who are treated with apraclonidine ophthalmic solution 0.5% to delay surgery should have their visual fields monitored periodically. Although the topical use of apraclonidine ophthalmic solution 0.5% has not been studied in renal failure patients, structurally related clonidine undergoes a significant increase in half-life in patients with severe renal impairment. Close monitoring of cardiovascular parameters in patients with impaired renal function is advised if they are candidates for topical apraclonidine therapy.
Close monitoring of cardiovascular parameters in patients with impaired liver function is also advised as the systemic dosage form of clonidine is partly metabolized in the liver. While the topical administration of apraclonidine ophthalmic solution 0.5% had minimal effect on heart rate or blood pressure in clinical studies evaluating glaucoma patients, the preclinical pharmacology profile of this drug suggests that caution should be observed in treating patients with severe, uncontrolled cardiovascular disease, including hypertension.
The possibility of a vasovagal attack should be considered and caution should be exercised in patients with a history of such episodes. Apraclonidine ophthalmic solution 0.5% should be used with caution in patients with coronary insufficiency, recent myocardial infarction, cerebrovascular disease, chronic renal failure, Raynaud’s disease, or thromboangiitis obliterans. Caution and monitoring of depressed patients are advised since apraclonidine has been infrequently associated with depression.
Apraclonidine can cause dizziness and somnolence. Patients who engage in hazardous activities requiring mental alertness should be warned of the potential for a decrease in mental alertness while using apraclonidine. Topical ocular administration of two drops of 0.5%, 1.0%, and 1.5% apraclonidine ophthalmic solution to New Zealand albino rabbits three times daily for one month resulted in sporadic and transient instances of minimal corneal edema in the 1.5% group only; no histopathological changes were noted in those eyes.
Use of apraclonidine ophthalmic solution 0.5% can lead to an allergic-like reaction characterized wholly or in part by the symptoms of hyperemia, pruritus, discomfort, tearing, foreign body sensation, and edema of the lids and conjunctiva. If ocular allergic-like symptoms occur, apraclonidine ophthalmic solution 0.5% therapy should be discontinued. Information for Patients Do not touch dropper tip to any surface as this may contaminate the contents.
The preservative in apraclonidine ophthalmic solution 0.5%, benzalkonium chloride, may be absorbed by soft contact lenses. Contact lenses should be removed during instillation of apraclonidine ophthalmic solution 0.5% but may be reinserted 15 minutes after instillation. Drug Interactions Apraclonidine should not be used in patients receiving MAO inhibitors (see CONTRAINDICATIONS).
Although no specific drug interactions with topical glaucoma drugs or systemic medications were identified in clinical studies of apraclonidine ophthalmic solution 0.5%, the possibility of an additive or potentiating effect with CNS depressants (alcohol, barbiturates, opiates, sedatives, anesthetics) should be considered. Tricyclic antidepressants have been reported to blunt the hypotensive effect of systemic clonidine. It is not known whether the concurrent use of these agents with apraclonidine can lead to a reduction in IOP lowering effect.
No data on the level of circulating catecholamines after apraclonidine withdrawal are available. Caution, however, is advised in patients taking tricyclic antidepressants which can affect the metabolism and uptake of circulating amines. An additive hypotensive effect has been reported with the combination of systemic clonidine and neuroleptic therapy.
Systemic clonidine may inhibit the production of catecholamines in response to insulin-i… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers It is not known whether this drug is excreted in human milk. Because many drugs are excreted in human milk, caution should be exercised when apraclonidine ophthalmic solution 0.5% is administered to a nursing woman.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility No significant change in tumor incidence or type was observed following two years of oral administration of apraclonidine HCl to rats and mice at dosages of 1.0 and 0.6 mg/kg, up to 20 and 12 times, respectively, the maximum dose recommended for human topical ocular use. Apraclonidine HCl was not mutagenic in a series of in vitro mutagenicity tests, including the Ames test, a mouse lymphoma forward mutation assay, a chromosome aberration assay in cultured Chinese hamster ovary (CHO) cells, a sister chromatid exchange assay in CHO cells, and a cell transformation assay.
An in vivo mouse micronucleus assay conducted with apraclonidine HCl also provided no evidence of mutagenicity. Reproduction and fertility studies in rats showed no adverse effect on male or female fertility at a dose of 0.5 mg/kg (5 to 10 times the maximum recommended human dose).
📄 Package Label / Principal Display Panel ▾
PRINCIPLE DISPLAY PANEL - 5mL Carton NDC 61314-665-05 Apraclonidine Ophthalmic Solution 0.5% as base 0.5% Rx Only FOR EYE USE ONLY STERILE 5 mL SANDOZ 5mlcarton
PRINCIPLE DISPLAY PANEL - 10mL Carton NDC 61314-665-10 Apraclonidine Ophthalmic Solution 0.5% as base 0.5% Rx Only FOR EYE USE ONLY STERILE 10 mL SANDOZ SANDOZ 10mlcarton