
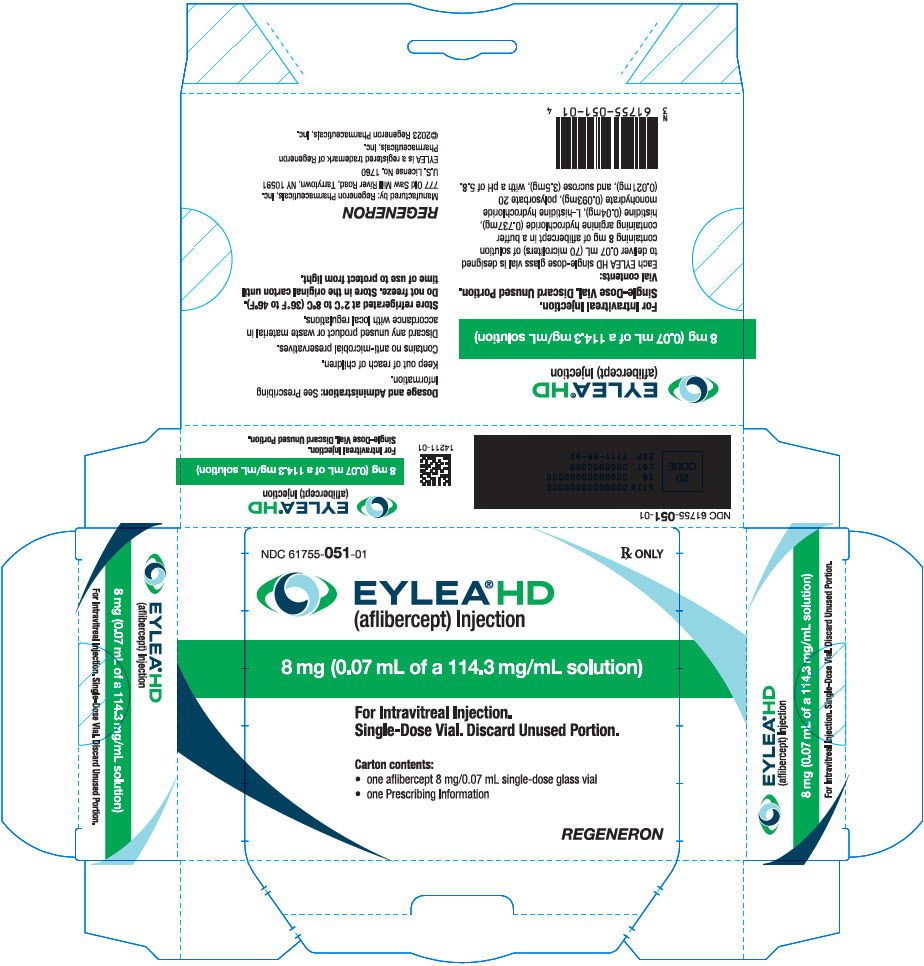
EYLEA HD aflibercept 8 mg/.07mL Injection, Solution, 1 vial — NDC 61755-050-01 (Billing 61755-0050-01)
This is a package of 1 vial of EYLEA HD aflibercept 8 mg/.07mL Injection, Solution from Regeneron Pharmaceuticals, Inc, marketed since Aug 2023 and currently FDA-listed. It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 61755-050-01 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 61755 labeler · 050 product · 01 package
- Package marketed since
- Aug 18, 2023
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC-A, from the NDC)
- 3 6175505001 7
- Medicaid fills, this package
- 34,824 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 085183
- GCN: 54599
- GPI-14 (Medi-Span): 86655010002080
- HICL (First Databank): 038209
- AHFS class code: 52:56.00.00
- RxCUI (RxNorm): 2645305
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Vascular Endothelial Growth Factor Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Aflibercept injection is used to treat: wet age-related macular degeneration (AMD; an ongoing disease of the eye that causes loss of the ability to see straight ahead and may make it more difficult to read, drive, or perform other daily activities) diabetic macular edema (an eye disease caused by diabetes that can lead to vision loss) diabetic retinopathy (damage to the eyes caused by diabetes) macular edema after retinal vein occlusion (an eye disease caused by blockage of blood flow from the eye that leads to blurry vision and vision loss) retinopathy of prematurity (ROP; an eye disea...
Read the full MedlinePlus article ↗- Right now, injecting aflibercept directly into the eye is the only way the medication works for these conditions. It needs to reach the retina in high enough concentrations to bloc...
- Why do I need injections in my eye — is there any other way to take this?
- It depends on your specific condition. For wet AMD and diabetic conditions, you'll typically start with monthly injections for a few months, and then your doctor will likely space...
- How often will I need to come in for injections?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $21,103.92 | $1,477.27 / 0.07 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J0177 | $298.683 / J0177 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 61755-0050-01 You're viewing this Main listing | 1 VIAL, SINGLE-DOSE in 1 CARTON / .07 mL in 1 VIAL, SINGLE-DOSE | 2023-08-18 | — | Active |
| 61755-0050-51 61755-050-51 | 1 VIAL, SINGLE-DOSE in 1 CARTON / .07 mL in 1 VIAL, SINGLE-DOSE | 2023-08-18 | — | Active |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 61755-0050-51?
What NDC number is used to bill for this package of EYLEA HD aflibercept 8 mg/.07mL Injection, Solution?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Eylea Hd 8 mg/.07mLthis 61755-0050-01 | Regeneron | 1 vial | — | — | FDA listed | — |
| Eylea Hd 8 mg/.07mL 61755-0051-01 | Regeneron | 1 vial | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Purple Book · refreshed Sep 5, 2026
- CMS NADAC weekly file
Availability & biosimilar status
5 biosimilars and 1 interchangeable are FDA-licensed for this reference biologic — see the list below. (Biologics have no small-molecule generics.)
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 11,084,865 ↗ | Biologic patent | — | Jun 14, 2027 |
| US 11,104,715 ↗ | Biologic patent | — | Aug 18, 2040 |
| US D934,069 ↗ | Biologic patent | — | Oct 26, 2036 |
| US 11,160,918 ↗ | Biologic patent | — | Jul 29, 2040 |
| US 11,174,283 ↗ | Biologic patent | — | Aug 18, 2040 |
| US 11,186,625 ↗ | Biologic patent | — | Aug 18, 2040 |
| US 11,253,572 ↗ | Biologic patent | — | Jan 11, 2032 |
| US 11,299,532 ↗ | Biologic patent | — | Aug 18, 2040 |
| US 11,306,135 ↗ | Biologic patent | — | Aug 18, 2040 |
| US 11,332,771 ↗ | Biologic patent | — | Mar 14, 2034 |
| US D961,376 ↗ | Biologic patent | — | Aug 23, 2037 |
| US D961,377 ↗ | Biologic patent | — | Aug 23, 2037 |
| US 11,433,186 ↗ | Biologic patent | — | Dec 12, 2038 |
| US 11,439,758 ↗ | Biologic patent | — | Jun 4, 2040 |
| US 11,459,373 ↗ | Biologic patent | — | Aug 18, 2040 |
| US 11,459,374 ↗ | Biologic patent | — | Aug 18, 2040 |
| US 11,472,861 ↗ | Biologic patent | — | Aug 18, 2040 |
| US 11,478,588 ↗ | Biologic patent | — | Jul 25, 2040 |
| US 11,485,770 ↗ | Biologic patent | — | Aug 18, 2040 |
| US 11,505,593 ↗ | Biologic patent | — | Aug 18, 2040 |
| US 11,649,273 ↗ | Biologic patent | — | Aug 18, 2040 |
| US 11,821,001 ↗ | Biologic patent | — | Jan 27, 2040 |
| US 12,077,570 ↗ | Biologic patent | — | Aug 18, 2040 |
| US 12,268,730 ↗ | Biologic patent | — | Jan 11, 2032 |
| US 12,282,004 ↗ | Biologic patent | — | Dec 9, 2041 |
| US 12,280,093 ↗ | Biologic patent | — | May 17, 2039 |
| US 11,559,564 ↗ | Biologic patent | — | Jan 11, 2032 |
| US 11,732,024 ↗ | Biologic patent | — | Jun 14, 2027 |
| US 11,535,663 ↗ | Biologic patent | — | Aug 18, 2040 |
| US 11,542,317 ↗ | Biologic patent | — | Aug 18, 2040 |
| US 11,707,506 ↗ | Biologic patent | — | Jan 11, 2032 |
| US 11,753,459 ↗ | Biologic patent | — | Aug 18, 2040 |
| US 11,769,597 ↗ | Biologic patent | — | Aug 15, 2038 |
| US 11,788,102 ↗ | Biologic patent | — | Oct 21, 2035 |
| US 11,793,926 ↗ | Biologic patent | — | Jul 29, 2040 |
| US 7,771,997 ↗ | Biologic patent | — | Jul 2, 2028 |
| US 9,315,281 ↗ | Biologic patent | — | Sep 16, 2034 |
| US 9,932,605 ↗ | Biologic patent | — | Jun 4, 2028 |
| US 10,182,969 ↗ | Biologic patent | — | Jul 13, 2037 |
| US 11,103,552 ↗ | Biologic patent | — | May 15, 2039 |
| US 11,268,109 ↗ | Biologic patent | — | Oct 21, 2035 |
| US 11,312,936 ↗ | Biologic patent | — | Aug 3, 2036 |
| US 11,525,833 ↗ | Biologic patent | — | Nov 29, 2040 |
| US 9,562,238 ↗ | Biologic patent | — | Jun 4, 2028 |
| US 11,549,154 ↗ | Biologic patent | — | Dec 25, 2036 |
| US 11,680,930 ↗ | Biologic patent | — | Oct 25, 2037 |
| US 11,850,407 ↗ | Biologic patent | — | Sep 18, 2039 |
| US 11,548,932 ↗ | Biologic patent | — | Aug 18, 2040 |
| US 11,555,176 ↗ | Biologic patent | — | Jan 27, 2040 |
| US 10,669,594 ↗ | Biologic patent | — | Feb 12, 2037 |
| US 11,732,025 ↗ | Biologic patent | — | Aug 18, 2040 |
| US 7,070,959 ↗ | Biologic patent | — | Jun 16, 2023 |
| US 9,222,106 ↗ | Biologic patent | — | Jul 2, 2028 |
| US 9,254,338 ↗ | Biologic patent | — | May 22, 2032 |
| US 9,669,069 ↗ | Biologic patent | — | Jan 11, 2032 |
| US 9,816,110 ↗ | Biologic patent | — | Oct 21, 2035 |
| US 10,130,681 ↗ | Biologic patent | — | Jan 11, 2032 |
| US D858,754 ↗ | Biologic patent | — | Sep 3, 2034 |
| US 10,406,226 ↗ | Biologic patent | — | Mar 22, 2026 |
| US 10,415,055 ↗ | Biologic patent | — | Jun 4, 2028 |
| US 10,464,992 ↗ | Biologic patent | — | Jun 14, 2027 |
| US 11,066,458 ↗ | Biologic patent | — | Jun 14, 2027 |
| US 10,828,345 ↗ | Biologic patent | — | Jan 11, 2032 |
| US 10,857,205 ↗ | Biologic patent | — | Jan 11, 2032 |
| US 10,857,231 ↗ | Biologic patent | — | — |
| US D906,102 ↗ | Biologic patent | — | Dec 29, 2035 |
| US 10,888,601 ↗ | Biologic patent | — | Jan 11, 2032 |
| US 10,905,786 ↗ | Biologic patent | — | Mar 6, 2038 |
| US 10,918,754 ↗ | Biologic patent | — | Mar 6, 2038 |
| US 10,927,342 ↗ | Biologic patent | — | Aug 3, 2036 |
| US 10,973,879 ↗ | Biologic patent | — | May 17, 2039 |
| US 11,053,280 ↗ | Biologic patent | — | Aug 18, 2040 |
| US 12,054,533 ↗ | Biologic patent | — | Aug 18, 2040 |
| US 11,918,785 ↗ | Biologic patent | — | Jun 29, 2037 |
| US 11,970,724 ↗ | Biologic patent | — | Mar 14, 2034 |
| US 11,975,045 ↗ | Biologic patent | — | Jan 11, 2032 |
| US 11,986,511 ↗ | Biologic patent | — | Jan 11, 2032 |
| US D1,035,436 ↗ | Biologic patent | — | Jul 16, 2039 |
| US D1,042,107 ↗ | Biologic patent | — | Sep 17, 2039 |
| US 12,116,622 ↗ | Biologic patent | — | May 25, 2038 |
| US D1,047,700 ↗ | Biologic patent | — | Oct 22, 2039 |
| US 12,163,122 ↗ | Biologic patent | — | May 10, 2042 |
| US 12,168,036 ↗ | Biologic patent | — | May 10, 2039 |
| US 12,202,883 ↗ | Biologic patent | — | Aug 18, 2040 |
| US 11,577,025 ↗ | Biologic patent | — | Oct 6, 2037 |
| US 12,221,619 ↗ | Biologic patent | — | Aug 3, 2036 |
| US 10,961,500 ↗ | Biologic patent | — | Jan 27, 2040 |
| US 11,286,460 ↗ | Biologic patent | — | Jan 27, 2040 |
| Code | What it grants | Expires |
|---|---|---|
| RefProduct | Reference-product exclusivity (12-year, BPCIA) — no biosimilar can be licensed before this date | Aug 18, 2035 |
Is there a biosimilar for EYLEA HD 8 MG/0.07 ML VIAL?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
- FDA Purple Book · refreshed Sep 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII F7LTH1E20Y
Arginine hydrochloride is an amino acid salt used as a buffer and pH adjuster in medicines. It helps maintain the correct acidity level to keep the drug stable and effective.
-
UNII 4QD397987E
An amino acid used as a buffer and stabilizer in medications. It helps maintain the pH balance and protects the active drug from breaking down during storage and use.
-
UNII X573657P6P
Histidine monohydrochloride monohydrate is an amino acid salt used as a buffer in medicines. It helps maintain the proper acidity level of liquid formulations to keep the drug stable and effective.
-
UNII 7T1F30V5YH
A synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together and keeps them from separating in liquid formulations.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Regeneron Pharmaceuticals, Inc labeler code 61755
- Evkeeza evinacumab 150 mg/mL Injection, Solution, Concentrate NDC 61755-013-01
- VEOPOZ Pozelimab 200 mg/mL Injection, Solution NDC 61755-014-01
- Inmazeb atoltivimab, maftivimab, and odesivimab-ebgn 241.7 mg/14.5mL; 241.7 mg/14.5mL; 241.7 mg/14.5mL Injection, Solution NDC 61755-018-01
- Inmazeb atoltivimab, maftivimab, and odesivimab-ebgn 483.3 mg/14.5mL; 483.3 mg/14.5mL; 483.3 mg/14.5mL Injection, Solution NDC 61755-019-01
- Praluent alirocumab 75 mg/mL Injection, Solution NDC 61755-020-01
- Praluent alirocumab 150 mg/mL Injection, Solution NDC 61755-021-01
- EYLEA HD aflibercept 8 mg/.07mL Injection, Solution NDC 61755-051-01
- LYNOZYFIC linvoseltamab-gcpt 5 mg/2.5mL Injection, Solution, Concentrate NDC 61755-054-01
- LYNOZYFIC linvoseltamab-gcpt 200 mg/10mL Injection, Solution, Concentrate NDC 61755-056-01
- OTARMENI lunsotogene parvec 3' VECTOR 30000000000000 {GC}/mL Injection, Solution NDC 61755-062-99
- aflibercept 40 mg/mL Injection, Solution NDC 61755-905-00
- cemiplimab 50 mg/mL Solution NDC 61755-908-00
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE EYLEA HD is indicated for the treatment of: EYLEA HD is a vascular endothelial growth factor (VEGF) inhibitor indicated for the treatment of patients with: Neovascular (Wet) Age-Related Macular Degeneration (nAMD) ( 1.1 ) Diabetic Macular Edema (DME) ( 1.2 ) Diabetic Retinopathy (DR) ( 1.3 ) Macular Edema Following Retinal Vein Occlusion (RVO) ( 1.4 )
1.1 Neovascular (Wet) Age-Related Macular Degeneration (nAMD)
1.2 Diabetic Macular Edema (DME)
1.3 Diabetic Retinopathy (DR)
1.4 Macular Edema Following Retinal Vein Occlusion (RVO)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Neovascular (Wet) Age-Related Macular Degeneration (nAMD) The recommended dose for EYLEA HD is 8 mg (0.07 mL of 114.3 mg/mL solution) administered by intravitreal injection every 4 weeks (approximately every 28 days +/- 7 days) for the first three doses, followed by 8 mg (0.07 mL of 114.3 mg/mL solution) via intravitreal injection once every 8 to 16 weeks, +/- 1 week. ( 2.2 ) Some patients did not maintain a response with 8 mg once every 8 to 16 weeks, +/- 1 week, after successful response to the three initial monthly doses.
These patients may benefit from resuming every 4-week dosing (approximately every 28 days +/- 7 days). ( 2.2 ) Extended dosing intervals (8 mg once every 20 weeks, +/- 1 week) may be considered after one year of successful response based on visual and anatomic outcomes. ( 2.2 ).
Diabetic Macular Edema (DME) The recommended dose for EYLEA HD is 8 mg (0.07 mL of 114.3 mg/mL solution) administered by intravitreal injection every 4 weeks (approximately every 28 days +/- 7 days) for the first three doses, followed by 8 mg (0.07 mL of 114.3 mg/mL solution) via intravitreal injection once every 8 to 16 weeks, +/- 1 week. ( 2.3 ) Some patients did not maintain a response with 8 mg once every 8 to 16 weeks, +/- 1 week, after successful response to the three initial monthly doses. These patients may benefit from resuming every 4-week dosing (approximately every 28 days +/- 7 days).
( 2.3 ) Extended dosing intervals (8 mg once every 20 weeks, +/- 1 week) may be considered after one year of successful response based on visual and anatomic outcomes. ( 2.3 ) Diabetic Retinopathy (DR) The recommended dose for EYLEA HD is 8 mg (0.07 mL of 114.3 mg/mL solution) administered by intravitreal injection every 4 weeks (approximately every 28 days +/- 7 days) for the first three doses, followed by 8 mg (0.07 mL of 114.3 mg/mL solution) via intravitreal injection once every 8 to 12 weeks, +/- 1 week. ( 2.4 ) Some patients did not maintain a response with 8 mg once every 8 to 12 weeks, +/- 1 week, after successful response to the three initial monthly doses.
These patients may benefit from resuming every 4-week dosing (approximately every 28 days +/- 7 days). ( 2.4 ) Macular Edema Following Retinal Vein Occlusion (RVO) The recommended dose for EYLEA HD is 8 mg (0.07 mL of 114.3 mg/mL solution) administered by intravitreal injection every 4 weeks (approximately every 28 days +/- 7 days) for the first three to five doses, followed by 8 mg (0.07 mL of 114.3 mg/mL solution) via intravitreal injection once every 8 weeks, +/- 1 week. ( 2.5 ) Some patients did not maintain a response with extended dosing intervals after successful response to the first three to five initial monthly doses.
These patients may benefit from resuming every 4-week dosing (approximately every 28 days +/- 7 days). ( 2.5 )
2.1Important Injection Instructions For ophthalmic intravitreal injection. EYLEA HD must only be administered by a qualified physician. A 5-micron sterile filter needle (18-gauge × 1½-inch), a 1-mL Luer lock syringe and a 30-gauge × ½-inch sterile injection needle are needed. EYLEA HD is available packaged as follows: Vial Only Vial Kit with Injection Components (filter needle, syringe, injection needle) [see How Supplied/Storage and Handling (16) ] .
2.2Neovascular (Wet) Age-Related Macular Degeneration (nAMD) The recommended dose for EYLEA HD is 8 mg (0.07 mL of 114.3 mg/mL solution) administered by intravitreal injection every 4 weeks (approximately every 28 days +/- 7 days) for the first three doses, followed by 8 mg (0.07 mL of 114.3 mg/mL solution) via intravitreal injection once every 8 to 16 weeks, +/- 1 week. Some patients did not maintain a response with 8 mg once every 8 to 16 weeks,+/- 1 week, after successful response to the three initial monthly doses [see Clinical Studies (14.1) ] .
These patients may benefit from resuming every 4-week dosing (approximately every 28 days +/- 7 days). Extended dosing… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS EYLEA HD is a clear to slightly opalescent, colorless to pale yellow solution available as: Injection: 8 mg (0.07 mL of a 114.3 mg/mL solution) in a single-dose glass vial Injection: 8 mg (0.07 mL of 114.3 mg/mL solution) in a single-dose vial ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Ocular or periocular infection ( 4.1 ) Active intraocular inflammation ( 4.2 ) Hypersensitivity ( 4.3 )
4.1Ocular or Periocular Infections EYLEA HD is contraindicated in patients with ocular or periocular infections.
4.2Active Intraocular Inflammation EYLEA HD is contraindicated in patients with active intraocular inflammation.
4.3Hypersensitivity EYLEA HD is contraindicated in patients with known hypersensitivity to aflibercept or any of the excipients in EYLEA HD. Hypersensitivity reactions may manifest as rash, pruritus, urticaria, severe anaphylactic/anaphylactoid reactions, or severe intraocular inflammation.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Endophthalmitis, retinal detachments, and retinal vasculitis with or without occlusion may occur following intravitreal injections. Patients should be instructed to report any symptoms suggestive of endophthalmitis, retinal detachment, or retinal vasculitis without delay and should be managed appropriately. ( 5.1 ) Increases in intraocular pressure have been seen within 60 minutes of an intravitreal injection.
( 5.2 ) There is a potential risk of arterial thromboembolic events following intravitreal use of VEGF inhibitors. ( 5.3 )
5.1Endophthalmitis, Retinal Detachments, and Retinal Vasculitis with or without Occlusion Intravitreal injections including those with aflibercept have been associated with endophthalmitis and retinal detachments [see Adverse Reactions (6.1) ] and, more rarely, retinal vasculitis with or without occlusion [see Adverse Reactions (6.2) ] . Proper aseptic injection technique must always be used when administering EYLEA HD. Patients and/or caregivers should be instructed to report any signs and/or symptoms suggestive of endophthalmitis, retinal detachment, or retinal vasculitis without delay and should be managed appropriately [see Dosage and Administration (2.7) and Patient Counseling Information (17) ].
5.2Increase in Intraocular Pressure Acute increases in intraocular pressure have been seen within 60 minutes of intravitreal injection, including with EYLEA HD [see Adverse Reactions (6.1) ]. Sustained increases in intraocular pressure have also been reported after repeated intravitreal dosing with vascular endothelial growth factor (VEGF) inhibitors. Intraocular pressure and the perfusion of the optic nerve head should be monitored and managed appropriately [see Dosage and Administration (2.7) ].
5.3Thromboembolic Events There is a potential risk of arterial thromboembolic events (ATEs) following intravitreal use of VEGF inhibitors, including EYLEA HD. ATEs are defined as nonfatal stroke, nonfatal myocardial infarction, or vascular death (including deaths of unknown cause). The incidence of reported thromboembolic events in the wet AMD study (PULSAR) from baseline through week 96 was 1.8% (12 out of 673) in the combined group of patients treated with EYLEA HD compared with 3.3% (11 out of 336) in patients treated with EYLEA 2 mg.
The incidence of reported thromboembolic events in the DME study (PHOTON) from baseline to week 96 was 6.7% (33 out of 491) in the combined group of patients treated with EYLEA HD compared with 7.2% (12 out of 167) in patients treated with EYLEA 2 mg. The incidence of reported thromboembolic events in the RVO study (QUASAR) from baseline to week 36 was 0.5% (3 out of 591) in the combined group of patients treated with EYLEA HD compared with 1.7% (5 out of 301) in patients treated with EYLEA 2 mg.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following potentially serious adverse reactions are described elsewhere in the labeling: Hypersensitivity [see Contraindications (4.3) ] Endophthalmitis, Retinal Detachments, and Retinal Vasculitis with or without Occlusion [see Warnings and Precautions (5.1) ] Increase in intraocular pressure [see Warnings and Precautions (5.2) ] Thromboembolic events [see Warnings and Precautions (5.3) ] The most common adverse reactions (≥3%) reported in patients treated with EYLEA HD were cataract, conjunctival hemorrhage, corneal epithelium defect, intraocular pressure increased, ocular discomfort/eye pain/eye irritation, retinal hemorrhage, vision blurred, vitreous detachment, and vitreous floaters.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Regeneron at 1-855-395-3248 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in other clinical trials of the same or another drug and may not reflect the rates observed in practice. A total of 1755 patients were treated with EYLEA HD and 804 patients were treated with EYLEA 2 mg in three clinical studies. The most common adverse reactions reported in ≥3% of patients treated with EYLEA HD were cataract, conjunctival hemorrhage, corneal epithelium defect, intraocular pressure increased, ocular discomfort/eye pain/eye irritation, retinal hemorrhage, vision blurred, vitreous detachment and vitreous floaters.
Neovascular (Wet) Age-Related Macular Degeneration (AMD) and Diabetic Macular Edema (DME) The data described below reflect exposure to EYLEA HD administered every 12 weeks (HDq12), EYLEA HD administered every 16 weeks (HDq16), or EYLEA 2 mg administered every 8 weeks (2q8) in controlled clinical studies (PULSAR and PHOTON), each for 96 weeks [see Clinical Studies (14.1 , 14.2) ]. Table 1: Adverse Reactions (≥1%) in at least one group in the PULSAR or PHOTON studies Adverse Reactions PULSAR PHOTON EYLEA HDq12 EYLEA HDq16 EYLEA 2q8 EYLEA HDq12 EYLEA HDq16 EYLEA 2q8 n=335 n=338 n=336 n=328 n=163 n=167 Cataract Represents grouping of related terms 10% 10% 10% 10% 13% 7% Vision blurred 9% 9% 8% 5% 4% 6% Intraocular pressure increased 5% 4% 3% 4% 1% 5% Conjunctival hemorrhage 3% 3% 3% 5% 5% 4% Ocular discomfort/eye pain/eye irritation 3% 4% 4% 5% 4% 4% Vitreous floaters 2% 6% 5% 6% 4% 4% Vitreous detachment 2% 4% 2% 5% 3% 4% Corneal epithelium defect 3% 3% 4% 4% 9% 2% Retinal hemorrhage 5% 6% 6% 0 4% 1% Dry eye 3% 3% 5% 2% 4% 2% Intraocular inflammation 2% 1% 2% 2% 1% 1% Retinal pigment epithelial tear/epitheliopathy 2% 2% 2% 1% 0 0 Vitreous hemorrhage <1% 1% 1% 2% 3% 2% Retinal Detachment 1% 1% <1% <1% 1% 0 Foreign body sensation in eyes 1% 2% 2% <1% 1% 0 Ocular hyperemia 1% <1% 1% <1% 0 0 Retinal pigment epithelial detachment 1% 1% 3% 0 0 0 Adverse drug reactions (ADRs) reported in <1% of participants treated with EYLEA HD were lacrimation increased, eyelid edema, hypersensitivity (includes adverse events of rash, urticaria, pruritus), and injection site hemorrhage.
Macular Edema Following Retinal Vein Occlusion (RVO) The data described below reflects 36 weeks exposure to EYLEA HD administered every 8 weeks (HDq8) after 3 or 5 initial monthly doses (HDq4), or EYLEA 2 mg administered every 4 weeks (2q4) in a controlled clinical study (QUASAR). [see Clinical Studies (14.4) ] . Table 2: Most Common Adverse Reactions (≥1%) in at least one group in the QUASAR study Adverse Reactions EYLEA HDq8 following 3 initial doses (HDq4) (N=293) EYLEA HDq8 following 5 initial doses (HDq4) (N=298) EYLEA 2q4 (N=301) Intraocular pressure increased Represents grouping of related terms 7% 6% 3% Vision blurred 5% 3% 2% Conjunctival hemorrhage 3% 2% 2% Ocular discomfort/eye pain/eye irritation 3% 3% 1% Vitreous detachment 3% 3% 1% Cataract 2% 4% 3% Corneal epithelium defect 2% 2% 2% Dry eye… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Adequate and well-controlled studies with EYLEA HD have not been conducted in pregnant women. Aflibercept produced adverse embryofetal effects in rabbits, including external, visceral, and skeletal malformations. A fetal No Observed Adverse Effect Level (NOAEL) was not identified.
At the lowest dose shown to produce adverse embryofetal effects, systemic exposure (based on AUC for free aflibercept) was approximately 0.9 -fold of the population pharmacokinetic estimated exposure in humans after an intravitreal dose of 8 mg (see Data ) . Animal reproduction studies are not always predictive of human response, and it is not known whether EYLEA HD can cause fetal harm when administered to a pregnant woman. Based on the anti-VEGF mechanism of action for aflibercept [see Clinical Pharmacology (12.1) ] , treatment with EYLEA HD may pose a risk to human embryofetal development.
EYLEA HD should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. The background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Data Animal Data In two embryofetal development studies, aflibercept produced adverse embryofetal effects when administered every three days during organogenesis to pregnant rabbits at intravenous doses ≥3 mg per kg, or every six days during organogenesis at subcutaneous doses ≥0.1 mg per kg. Adverse embryofetal effects included increased incidences of postimplantation loss and fetal malformations, including anasarca, umbilical hernia, diaphragmatic hernia, gastroschisis, cleft palate, ectrodactyly, intestinal atresia, spina bifida, encephalomeningocele, heart and major vessel defects, and skeletal malformations (fused vertebrae, sternebrae, and ribs; supernumerary vertebral arches and ribs; and incomplete ossification).
The maternal No Observed Adverse Effect Level (NOAEL) in these studies was 3 mg per kg. Aflibercept produced fetal malformations at all doses assessed in rabbits and the fetal NOAEL was not identified. At the lowest dose shown to produce adverse embryofetal effects in rabbits (0.1 mg per kg), systemic exposure (AUC) of free aflibercept was approximately 0.9-fold of the population pharmacokinetic estimated systemic exposure (AUC) in humans after an intravitreal dose of 8 mg.
8.2Lactation Risk Summary There is no information regarding the presence of aflibercept in human milk, the effects of the drug on the breastfed infant, or the effects of the drug on milk production/excretion. Because many drugs are excreted in human milk, and because the potential for absorption and harm to infant growth and development exists, EYLEA HD is not recommended during breastfeeding. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for EYLEA HD and any potential adverse effects on the breastfed child from EYLEA HD.
8.3Females and Males of Reproductive Potential Contraception Females of reproductive potential are advised to use effective contraception prior to the initial dose, during treatment, and for at least 4 months after the last intravitreal injection of EYLEA HD. Infertility There are no data regarding the effects of EYLEA HD on human fertility. Aflibercept adversely affected female and male reproductive systems in cynomolgus monkeys when administered by intravenous injection at a dose 91 times higher (based on AUC of free aflibercept) than the corresponding systemic level estimated based on population pharmacokinetic analysis in humans following an intravitreal dose of 8 mg.
A No Observed Adverse Effect Level (NOAEL) was not identified. These findings were reversible wit… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Adequate and well-controlled studies with EYLEA HD have not been conducted in pregnant women. Aflibercept produced adverse embryofetal effects in rabbits, including external, visceral, and skeletal malformations. A fetal No Observed Adverse Effect Level (NOAEL) was not identified.
At the lowest dose shown to produce adverse embryofetal effects, systemic exposure (based on AUC for free aflibercept) was approximately 0.9 -fold of the population pharmacokinetic estimated exposure in humans after an intravitreal dose of 8 mg (see Data ) . Animal reproduction studies are not always predictive of human response, and it is not known whether EYLEA HD can cause fetal harm when administered to a pregnant woman. Based on the anti-VEGF mechanism of action for aflibercept [see Clinical Pharmacology (12.1) ] , treatment with EYLEA HD may pose a risk to human embryofetal development.
EYLEA HD should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. The background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively. Data Animal Data In two embryofetal development studies, aflibercept produced adverse embryofetal effects when administered every three days during organogenesis to pregnant rabbits at intravenous doses ≥3 mg per kg, or every six days during organogenesis at subcutaneous doses ≥0.1 mg per kg. Adverse embryofetal effects included increased incidences of postimplantation loss and fetal malformations, including anasarca, umbilical hernia, diaphragmatic hernia, gastroschisis, cleft palate, ectrodactyly, intestinal atresia, spina bifida, encephalomeningocele, heart and major vessel defects, and skeletal malformations (fused vertebrae, sternebrae, and ribs; supernumerary vertebral arches and ribs; and incomplete ossification).
The maternal No Observed Adverse Effect Level (NOAEL) in these studies was 3 mg per kg. Aflibercept produced fetal malformations at all doses assessed in rabbits and the fetal NOAEL was not identified. At the lowest dose shown to produce adverse embryofetal effects in rabbits (0.1 mg per kg), systemic exposure (AUC) of free aflibercept was approximately 0.9-fold of the population pharmacokinetic estimated systemic exposure (AUC) in humans after an intravitreal dose of 8 mg.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of EYLEA HD in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use In the clinical studies, approximately 66% (1156/1755) of the patients in the HD groups were 65 years of age or older and approximately 31% (543/1755) of the patients were 75 years of age or older. No overall differences in safety or effectiveness of EYLEA HD have been observed.
🆘 Overdosage ▾
10 OVERDOSAGE Overdosing with increased injection volume may increase intraocular pressure. Therefore, in case of overdosage, intraocular pressure should be monitored and if deemed necessary by the treating physician, adequate treatment should be initiated.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Vascular endothelial growth factor-A (VEGF-A) and placental growth factor (PlGF) are members of the VEGF family of angiogenic factors that can act as mitogenic, chemotactic, and vascular permeability factors for endothelial cells. VEGF acts via two receptor tyrosine kinases, VEGFR-1 and VEGFR-2, present on the surface of endothelial cells. PlGF binds only to VEGFR-1, which is also present on the surface of leucocytes.
Activation of these receptors by VEGF-A can result in neovascularization and vascular permeability. Aflibercept acts as a soluble decoy receptor that binds VEGF-A and PlGF, and thereby can inhibit the binding and activation of these cognate VEGF receptors.
12.2Pharmacodynamics Increased retinal thickness, assessed by optical coherence tomography (OCT), is associated with nAMD, DME, and RVO. Reductions in central subfield thickness (CST) were observed across all treatment arms throughout the three Phase 3 studies in nAMD, DME, and RVO.
12.3Pharmacokinetics EYLEA HD is administered intravitreally to exert local effects in the eye. In patients with wet AMD, or DME, following intravitreal administration of EYLEA HD, a fraction of the administered dose is expected to bind with endogenous VEGF in the eye to form an inactive aflibercept: VEGF complex. Once absorbed into the systemic circulation, aflibercept presents in the plasma as free aflibercept (unbound to VEGF) and a more predominant stable inactive form with circulating endogenous VEGF (i.e., aflibercept: VEGF complex).
Absorption/Distribution As no relevant differences in pharmacokinetics between the nAMD, DME, and RVO populations were observed based on a population pharmacokinetic analysis of the data, population pharmacokinetic estimated parameters are presented for the combined populations. Following unilateral intravitreal administration of 8 mg aflibercept, the mean (SD) C max of free aflibercept in plasma was 0.32 (0.27) mg/L, and the median time to maximal concentration in plasma was 2.9 days. The accumulation of free aflibercept in plasma following three initial monthly intravitreal doses was minimal (mean accumulation ratio 1.2); subsequently, no further accumulation was observed.
The volume of distribution of free aflibercept following intravenous (I.V.) administration of aflibercept is approximately 7 L. Metabolism/Elimination Aflibercept is a therapeutic protein and no drug metabolism studies have been conducted. Aflibercept is expected to undergo elimination through both target-mediated disposition via binding to free endogenous VEGF and metabolism via proteolysis.
The median time to reach non-quantifiable concentrations of free aflibercept in plasma for 8 mg administered intravitreally was 3.5 weeks. Specific Populations Renal and Hepatic Impairment Population pharmacokinetic analysis revealed that systemic exposures to aflibercept in patients with mild to severe renal impairment (eGFR 15 to < 90 mL/min, estimated using the Chronic Kidney Disease Epidemiology Collaboration (CKD-EPI) equation for eGFR were similar to those with normal renal function. Mild hepatic impairment had no influence on systemic exposures to aflibercept compared to patients with normal hepatic function .
No data for patients with moderate and severe hepatic impairment are available. No dose adjustment based on renal or hepatic impairment status is needed. Other No dosage adjustment is required for any of the populations that have been studied (e.g., age and race).
12.6Immunogenicity The observed incidence of anti-drug antibodies is highly dependent on the sensitivity and specificity of the assay. Differences in assay methods preclude meaningful comparisons of the incidence of anti-drug antibodies in the studies described below with the incidence of anti-drug antibodies for other products. In the nAMD [PULSAR] and DME [PHOTON] studies, the pre-treatment incidence of anti-aflibercept antibodies in the 8 mg treatment groups wa… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Vascular endothelial growth factor-A (VEGF-A) and placental growth factor (PlGF) are members of the VEGF family of angiogenic factors that can act as mitogenic, chemotactic, and vascular permeability factors for endothelial cells. VEGF acts via two receptor tyrosine kinases, VEGFR-1 and VEGFR-2, present on the surface of endothelial cells. PlGF binds only to VEGFR-1, which is also present on the surface of leucocytes.
Activation of these receptors by VEGF-A can result in neovascularization and vascular permeability. Aflibercept acts as a soluble decoy receptor that binds VEGF-A and PlGF, and thereby can inhibit the binding and activation of these cognate VEGF receptors.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied EYLEA HD (aflibercept) is a clear to slightly opalescent, colorless to pale yellow solution supplied in the following presentations [see Dosage and Administration (2.6) and (2.7) ]. Each vial is for single eye use only. Discard unused portion.
NDC NUMBER CARTON TYPE CARTON CONTENTS 61755-050-01 Vial Kit with Injection Components one EYLEA HD 8 mg (0.07 mL of a 114.3 mg/mL solution), single-dose glass vial one 18-gauge × 1½-inch, 5-micron, filter needle for withdrawal of the vial contents one 30-gauge × ½-inch injection needle for intravitreal injection one 1-mL syringe for administration one Prescribing Information 61755-051-01 Vial Only one EYLEA HD 8 mg (0.07 mL of a 114.3 mg/mL solution) single-dose glass vial one Prescribing Information
16.2Storage and Handling Refrigerate EYLEA HD at 2°C to 8°C (36°F to 46°F). Do not freeze. Do not use beyond the date stamped on the carton and container label. Store in the original carton until time of use to protect from light.
📦 Storage and Handling ▾
16.2Storage and Handling Refrigerate EYLEA HD at 2°C to 8°C (36°F to 46°F). Do not freeze. Do not use beyond the date stamped on the carton and container label. Store in the original carton until time of use to protect from light.
📋 Description ▾
11 DESCRIPTION Aflibercept is a recombinant fusion protein consisting of portions of human VEGF receptors 1 and 2 extracellular domains fused to the Fc portion of human IgG1 formulated as an iso-osmotic solution for intravitreal administration. Aflibercept is a dimeric glycoprotein and contains glycosylation, constituting an additional 15% of the total molecular mass, resulting in a total molecular weight of 115 kDa. Aflibercept is produced in recombinant Chinese hamster ovary (CHO) cells.
EYLEA HD (aflibercept) injection is a sterile, clear to slightly opalescent, and colorless to pale yellow solution. EYLEA HD is supplied as a sterile, aqueous solution for intravitreal injection in a single-dose glass vial designed to deliver 0.07 mL (70 microliters) of solution containing 8 mg of aflibercept in a buffer containing arginine hydrochloride (0.737 mg), histidine (0.04 mg), L-histidine hydrochloride monohydrate (0.093 mg), polysorbate 20 (0.021 mg), sucrose (3.5 mg) and water for injection with a pH of 5.8.
EYLEA HD does not contain an anti-microbial preservative.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION In the days following EYLEA HD administration, patients are at risk of developing endophthalmitis, retinal detachment, or retinal vasculitis with or without occlusion. If the eye becomes red, sensitive to light, painful, or develops a change in vision, advise patients and/or caregivers to seek immediate care from an ophthalmologist [see Warnings and Precautions (5.1) ] . Patients may experience temporary visual disturbances after an intravitreal injection with EYLEA HD and the associated eye examinations [see Adverse Reactions (6.1) ] .
Advise patients not to drive or use machinery until visual function has recovered sufficiently.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics EYLEA HD is administered intravitreally to exert local effects in the eye. In patients with wet AMD, or DME, following intravitreal administration of EYLEA HD, a fraction of the administered dose is expected to bind with endogenous VEGF in the eye to form an inactive aflibercept: VEGF complex. Once absorbed into the systemic circulation, aflibercept presents in the plasma as free aflibercept (unbound to VEGF) and a more predominant stable inactive form with circulating endogenous VEGF (i.e., aflibercept: VEGF complex).
Absorption/Distribution As no relevant differences in pharmacokinetics between the nAMD, DME, and RVO populations were observed based on a population pharmacokinetic analysis of the data, population pharmacokinetic estimated parameters are presented for the combined populations. Following unilateral intravitreal administration of 8 mg aflibercept, the mean (SD) C max of free aflibercept in plasma was 0.32 (0.27) mg/L, and the median time to maximal concentration in plasma was 2.9 days. The accumulation of free aflibercept in plasma following three initial monthly intravitreal doses was minimal (mean accumulation ratio 1.2); subsequently, no further accumulation was observed.
The volume of distribution of free aflibercept following intravenous (I.V.) administration of aflibercept is approximately 7 L. Metabolism/Elimination Aflibercept is a therapeutic protein and no drug metabolism studies have been conducted. Aflibercept is expected to undergo elimination through both target-mediated disposition via binding to free endogenous VEGF and metabolism via proteolysis.
The median time to reach non-quantifiable concentrations of free aflibercept in plasma for 8 mg administered intravitreally was 3.5 weeks. Specific Populations Renal and Hepatic Impairment Population pharmacokinetic analysis revealed that systemic exposures to aflibercept in patients with mild to severe renal impairment (eGFR 15 to < 90 mL/min, estimated using the Chronic Kidney Disease Epidemiology Collaboration (CKD-EPI) equation for eGFR were similar to those with normal renal function. Mild hepatic impairment had no influence on systemic exposures to aflibercept compared to patients with normal hepatic function .
No data for patients with moderate and severe hepatic impairment are available. No dose adjustment based on renal or hepatic impairment status is needed. Other No dosage adjustment is required for any of the populations that have been studied (e.g., age and race).
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Increased retinal thickness, assessed by optical coherence tomography (OCT), is associated with nAMD, DME, and RVO. Reductions in central subfield thickness (CST) were observed across all treatment arms throughout the three Phase 3 studies in nAMD, DME, and RVO.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Neovascular (Wet) Age-Related Macular Degeneration (nAMD) The safety and efficacy of EYLEA HD were assessed in a randomized, multi-center, double-masked, active-controlled study (PULSAR) in treatment-naïve patients with nAMD. A total of 1009 patients were treated and analyzed for efficacy (673 with EYLEA HD). Patients were randomly assigned in a 1:1:1 ratio to 1 of 3 treatment groups: 1) EYLEA HD administered every 12 weeks following 3 initial monthly doses (HDq12); 2) EYLEA HD administered every 16 weeks following 3 initial monthly doses (HDq16); 3) EYLEA 2 mg administered every 8 weeks (2q8) following 3 initial monthly doses.
In the EYLEA HD groups, patients could be treated as frequently as every 8 weeks based on protocol-defined visual and anatomic criteria, starting at week 16. Starting at week 52, patient dosing intervals could be extended by 4-week increments if all protocol-defined visual and anatomic criteria were met at visits in Year 2 (i.e., BCVA loss <5 letters from Week 12, no fluid in the central subfield on OCT, and no new onset foveal hemorrhage or foveal neovascularization). Patients ranged from 50 to 96 years of age with a mean of 74.5 years.
At baseline, mean visual acuity was approximately 60 letters (range: 24 to 78 letters). The primary efficacy endpoint was the change from baseline in BCVA at week 48 as measured by the Early Treatment Diabetic Retinopathy Study (ETDRS) letter score. Both HDq12 and HDq16 treatments were shown to be non-inferior and clinically equivalent to 2q8 treatment with respect to the change in BCVA score at week 48 using the pre-specified non-inferiority margin of 4 letters.
6.2% of total EYLEA HD treated patients who met protocol-defined criteria to be treated every 8 weeks did not maintain a response with every 8 weeks dosing after successful response to the 3 initial monthly doses. In patients completing week 48, the mean number of injections administered was 5.2 in the HDq16 group (n=312), 6.1 in the HDq12 group (n=316) and 6.9 in the EYLEA q8 group (n=309). The treatment effect with EYLEA HD in mean change in BCVA was maintained through week 96.
During the second year of treatment in patients who completed week 96, the mean number of injections administered was 3 in the HDq16 group (n=292), 3.7 in the HDq12 group (n=291) and 5.8 in the 2q8 group (n=286). In the pooled HDq12 and HDq16 groups, patients maintained their visual and anatomic outcomes through week 96, with 71% and 46.8% of patients attaining treatment intervals of ≥16 weeks and ≥20 weeks, respectively, at week 96. Detailed results from the analysis of the PULSAR study are shown in Table 3 and Figure 8 below.
Efficacy results in all subgroups (e.g., age, gender, geographic region, ethnicity, race, baseline BCVA and lesion type) were consistent with those in the overall population. Table 3: Efficacy Outcomes at Weeks 48 and 96 (Full Analysis Set) in PULSAR Study Efficacy Outcomes EYLEA HDq12 EYLEA HDq16 EYLEA 2q8 BCVA = Best Corrected Visual Acuity; ETDRS = Early Treatment Diabetic Retinopathy Study; SD = Standard Deviation; LS = Least Square; SE = Standard Error; CI = Confidence Interval; MMRM = Mixed Model for Repeated Measurements Full Analysis Set Full Analysis Set (FAS) includes all randomized patients who received at least 1 dose of study medication N=335 N=338 N=336 Efficacy Outcomes at Week 48 Mean change in BCVA as measured by ETDRS letter score from baseline (SD) Observed values at week 48: n=299 for HDq12; n=289 for HDq16; n=285 for 2q8 6.7 (12.6) 6.2 (11.7) 7.6 (12.2) LS mean (SE) change from baseline Estimate based on the MMRM model, was computed for the differences of HDq12 minus 2q8 and HDq16 minus 2q8, respectively, with two-sided 95% CIs 6.1 (0.8) 5.9 (0.7) 7.0 (0.7) Difference in LS mean (95% CI) -1.0 (-2.9, 0.9) -1.1 (-3.0, 0.7) Efficacy Outcomes at Week 96 Mean change in BCVA as measured by ETDRS letter score from baseline (SD) Observed values at week 96: n=256 for HDq12; n… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No studies have been conducted on the mutagenic or carcinogenic potential of aflibercept. Effects on male and female fertility were assessed as part of a 6-month study in monkeys with intravenous administration of aflibercept at weekly doses ranging from 3 to 30 mg per kg. Absent or irregular menses associated with alterations in female reproductive hormone levels and changes in sperm morphology and motility were observed at all dose levels.
In addition, females showed decreased ovarian and uterine weight accompanied by compromised luteal development and reduction of maturing follicles. These changes correlated with uterine and vaginal atrophy. All changes were reversible within 20 weeks after cessation of treatment.
A No Observed Adverse Effect Level (NOAEL) was not identified. Intravenous administration of the lowest dose of aflibercept assessed in monkeys (3 mg per kg) resulted in systemic exposure (AUC) for free aflibercept that was 91 times higher than the population pharmacokinetic estimated systemic exposure in humans after an intravitreal dose of 8 mg.
13.2Animal Toxicology and/or Pharmacology Erosions and ulcerations of the respiratory epithelium in nasal turbinates in monkeys treated with aflibercept intravitreally were observed at intravitreal doses of 2, 4 or 7 mg per eye. At the NOAEL of 0.5 mg per eye in monkeys, the systemic exposure (AUC) for free aflibercept was approximately 3 times higher than the population pharmacokinetic estimated exposure observed in humans after an intravitreal dose of 8 mg. Similar effects were not seen in clinical studies [see Clinical Studies (14) ].
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility No studies have been conducted on the mutagenic or carcinogenic potential of aflibercept. Effects on male and female fertility were assessed as part of a 6-month study in monkeys with intravenous administration of aflibercept at weekly doses ranging from 3 to 30 mg per kg. Absent or irregular menses associated with alterations in female reproductive hormone levels and changes in sperm morphology and motility were observed at all dose levels.
In addition, females showed decreased ovarian and uterine weight accompanied by compromised luteal development and reduction of maturing follicles. These changes correlated with uterine and vaginal atrophy. All changes were reversible within 20 weeks after cessation of treatment.
A No Observed Adverse Effect Level (NOAEL) was not identified. Intravenous administration of the lowest dose of aflibercept assessed in monkeys (3 mg per kg) resulted in systemic exposure (AUC) for free aflibercept that was 91 times higher than the population pharmacokinetic estimated systemic exposure in humans after an intravitreal dose of 8 mg.
📄 Recent Major Changes ▾
Indications and Usage ( 1.4 ) 11/2025 Dosage and Administration ( 2.2 , 2.3 , 2.4 ) 4/2026 Dosage and Administration ( 2.5 ) 11/2025 Warnings and Precautions ( 5.3 ) 4/2026
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 0.07 mL Vial Carton - 050 NDC 61755-050-01 Rx ONLY EYLEA ® HD (aflibercept) Injection 8 mg (0.07 mL of a 114.3 mg/mL solution) For Intravitreal Injection. Single-Dose Vial. Discard Unused Portion.
Carton contents: one aflibercept 8 mg/0.07 mL single-dose glass vial one 18-gauge × 1½-inch, 5-micron, filter needle for withdrawal of the vial contents one 30-gauge × ½-inch injection needle for intravitreal injection one 1-mL syringe for administration one Prescribing Information REGENERON PRINCIPAL DISPLAY PANEL - 0.07 mL Vial Carton - 050
PRINCIPAL DISPLAY PANEL - 0.07 mL Vial Carton - 051 NDC 61755-051-01 Rx ONLY EYLEA ® HD (aflibercept) Injection 8 mg (0.07 mL of a 114.3 mg/mL solution) For Intravitreal Injection. Single-Dose Vial. Discard Unused Portion. Carton contents: one aflibercept 8 mg/0.07 mL single-dose glass vial one Prescribing Information REGENERON PRINCIPAL DISPLAY PANEL - 0.07 mL Vial Carton - 051
Medicaid utilization & spend
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |