
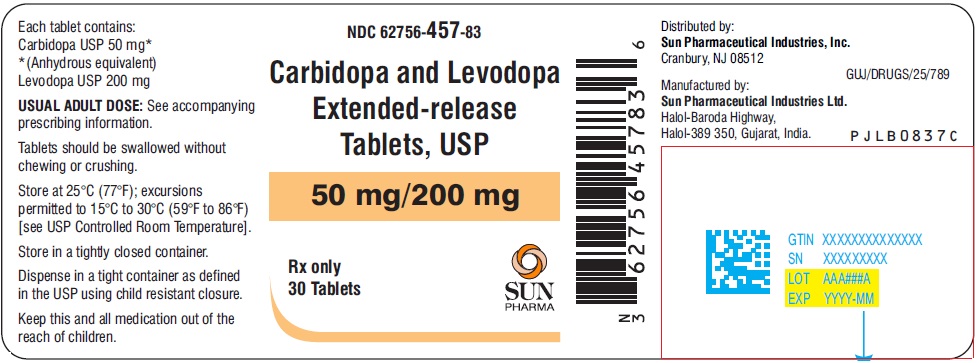
CARBIDOPA AND LEVODOPA 50 mg; 200 mg Tablet, Extended Release, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Aromatic Amino Acid Decarboxylation Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Levodopa and carbidopa is used to treat the symptoms of Parkinson's disease and Parkinson's-like symptoms that may develop after encephalitis (swelling of the brain) or injury to the nervous system caused by carbon monoxide poisoning or manganese poisoning. Levodopa is in a class of medications called central nervous system agents. It works by being converted to dopamine in the brain (the natural substance that is low in Parkinson's and causes the symptoms of tremor, stiffness, and slowness of movement). Carbidopa is in a class of medications called decarboxylase inhibitors. It works by preven...
Read the full MedlinePlus article ↗- Levodopa is the medicine that actually works in your brain — it crosses into the brain and gets converted into dopamine, the chemical that Parkinson's disease depletes. The problem...
- What exactly does levodopa and carbidopa do, and why do I need both?
- Generally yes, but the timing and content of your meals can matter. High-protein foods — like large servings of meat, eggs, or dairy — can compete with levodopa for absorption in y...
- Can I eat normally while taking this medication?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII UKE75GEA7F
Hydroxypropyl cellulose is a plant-based polymer used as a binder and thickener. It helps hold tablet ingredients together, controls how fast the medicine dissolves, and improves the texture of liquid formulations.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.174 | $17.35 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.2420 | $24.20 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Carbidopa and Levodopa 50 mg/1; 200 mg 00378-0094-01 | Mylan | 100 tablets | $0.173 | AB | Availability likely | — |
| Carbidopa And Levodopa 50 mg/1; 200 mg 16729-0079-01 | Accord | 100 tablets | $0.173 | AB | Availability likely | — |
| Carbidopa and Levodopa 50 mg/1; 200 mg 50228-0461-01 | ScieGen | 100 tablets | $0.173 | AB | Availability likely | — |
| Carbidopa and Levodopa 50 mg/1; 200 mg 51079-0923-20 | Mylan | 1 tablet | $0.173 | AB | Availability likely | — |
| Carbidopa and Levodopa 50 mg/1; 200 mg 60219-2034-01 | Amneal | 100 tablets | $0.173 | AB | Availability likely | — |
| Carbidopa And Levodopa 50 mg/1; 200 mgthis 62756-0457-88 | Sun | 100 tablets | $0.173 | — | Discontinued | — |
| Carbidopa and Levodopa 50 mg/1; 200 mg 00615-8461-39 | NCS | 30 tablets | — | AB | FDA listed | — |
| Carbidopa and Levodopa 50 mg/1; 200 mg 46708-0333-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Carbidopa and Levodopa 50 mg/1; 200 mg 48433-0016-20 | Safecor | 1 tablet | — | AB | FDA listed | — |
| Carbidopa and Levodopa 50 mg/1; 200 mg 62332-0333-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Carbidopa and Levodopa 50 mg/1; 200 mg 72162-2193-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Carbidopa and levodopa 50 mg/1; 200 mg 72888-0156-00 | Advagen | 1000 tablets | — | AB | FDA listed | — |
| Carbidopa and Levodopa 50 mg/1; 200 mg 77771-0461-01 | Radha | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
💊 Medicaid utilization by pack size
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 62756-0457-08 | 100 TABLET, EXTENDED RELEASE in 1 BOTTLE (62756-457-08) | — | — | 2007-08-23 | Active |
| 62756-0457-18 | 1000 TABLET, EXTENDED RELEASE in 1 BOTTLE (62756-457-18) | — | — | 2007-08-23 | Active |
| 62756-0457-83 | 30 TABLET, EXTENDED RELEASE in 1 BOTTLE (62756-457-83) | — | — | 2007-08-23 | Active |
| 62756-0457-88 You're viewing this | 100 TABLET, EXTENDED RELEASE in 1 BOTTLE (62756-457-88) | $0.1735 / ea | $17.35 | 2007-08-23 | Discontinued by firm |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 62756-0457-88?
What is the difference between NDC 62756-0457-88 and NDC 62756-0457-83?
What NDC number is used to bill for this package of CARBIDOPA AND LEVODOPA 50 mg; 200 mg Tablet, Extended Release?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Carbidopa and levodopa extended-release tablets are indicated in the treatment of Parkinson's disease, post-encephalitic parkinsonism, and symptomatic parkinsonism that may follow carbon monoxide intoxication or manganese intoxication.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Carbidopa and levodopa extended-release tablet contains carbidopa and levodopa in a 1:4 ratio as either the 50 mg/200 mg tablet or the 25 mg/100 mg tablet. The daily dosage of carbidopa and levodopa extended-release tablets must be determined by careful titration. Patients should be monitored closely during the dose adjustment period, particularly with regard to appearance or worsening of involuntary movements, dyskinesias or nausea.
Carbidopa and levodopa extended-release tablets should not be chewed or crushed. Standard drugs for Parkinson's disease, other than levodopa without a decarboxylase inhibitor, may be used concomitantly while carbidopa and levodopa extended-release tablet is being administered, although their dosage may have to be adjusted. Since carbidopa prevents the reversal of levodopa effects caused by pyridoxine, carbidopa and levodopa extended-release tablets can be given to patients receiving supplemental pyridoxine (vitamin B 6 ).
Initial Dosage Patients currently treated with conventional carbidopa and levodopa preparations: Studies show that peripheral dopa-decarboxylase is saturated by the bioavailable carbidopa at doses of 70 mg a day and greater. Because the bioavailabilities of carbidopa and levodopa in carbidopa and levodopa tablets and carbidopa and levodopa extended-release tablets are different, appropriate adjustments should be made, as shown in Table 2. Table 2.
Approximate Bioavailabilities at Steady State This table is only a guide to bioavailabilities since other factors such as food, drugs, and inter-patient variabilities may affect the bioavailability of carbidopa and levodopa. Tablet Amount of Levodopa (mg) in Each Tablet Approximate Bioavailability Approximate Amount of Bioavailable Levodopa (mg) in Each Tablet Carbidopa and levodopa extended-release tablets 50 mg/200 mg 200 0.7 to
0.75The extent of availability of levodopa from carbidopa and levodopa extended-release tablets was about 70 to 75% relative to intravenous levodopa or standard carbidopa and levodopa tablets in the elderly. 140 to 150 Carbidopa and levodopa tablets 25 mg/100 mg 100
0.99The extent of availability of levodopa from carbidopa and levodopa tablets was 99% relative to intravenous levodopa in the healthy elderly. 99 Dosage with carbidopa and levodopa extended-release tablets should be substituted at an amount that provides approximately 10% more levodopa per day, although this may need to be increased to a dosage that provides up to 30% more levodopa per day depending on clinical response (see DOSAGE AND ADMINISTRATION, Titration with carbidopa and levodopa extended-release tablets ).
The interval between doses of carbidopa and levodopa extended-release tablets should be 4 to 8 hours during the waking day. (See CLINICAL PHARMACOLOGY, Pharmacodynamics . ) A guideline for initiation of carbidopa and levodopa extended-release tablets is shown in Table 3. Table 3.
Guidelines for Initial Conversion from Carbidopa and Levodopa Tablets to Carbidopa and Levodopa Extended-Release Tablets Carbidopa and levodopa tablets Carbidopa and levodopa extended-release tablets Total Daily Dose For dosing ranges not shown in the table see DOSAGE AND ADMINISTRATION, Initial Dosage-Patients currently treated with conventional carbidopa and levodopa preparations. Suggested Levodopa (mg) Dosage Regimen 300 to 400 200 mg b.i.d. 500 to 600 300 mg b.i.d. or 200 mg t.i.d.
700 to 800 A total of 800 mg in 3 or more divided doses (e.g., 300 mg a.m., 300 mg early p.m., and 200 mg later p.m.) 900 to 1,000 A total of 1,000 mg in 3 or more divided doses (e.g., 400 mg a.m., 400 mg early p.m., and 200 mg later p.m.) Patients currently treated with levodopa without a decarboxylase inhibitor: Levodopa must be discontinued at least twelve hours before therapy with carbidopa and levodopa extended-release tablets is started. Carbidopa and levodopa extended-release tablets should be substituted at a dosage that will provide approxim…
⛔ Contraindications ▾
CONTRAINDICATIONS Nonselective monoamine oxidase (MAO) inhibitors are contraindicated for use with carbidopa and levodopa extended-release tablets. These inhibitors must be discontinued at least two weeks prior to initiating therapy with carbidopa and levodopa extended-release tablets. Carbidopa and levodopa extended-release tablets may be administered concomitantly with the manufacturer's recommended dose of an MAO inhibitor with selectivity for MAO type B (e.g., selegiline HCl) (see PRECAUTIONS, Drug Interactions ).
Carbidopa and levodopa extended-release tablets are contraindicated in patients with known hypersensitivity to any component of this drug, and in patients with narrow-angle glaucoma.
⚠️ Warnings ▾
WARNINGS When patients are receiving levodopa without a decarboxylase inhibitor, levodopa must be discontinued at least twelve hours before carbidopa and levodopa extended-release tablets are started. In order to reduce adverse reactions, it is necessary to individualize therapy. See DOSAGE AND ADMINISTRATION section before initiating therapy.
Carbidopa and levodopa extended-release tablets should be substituted at a dosage that will provide approximately 25% of the previous levodopa dosage (see DOSAGE AND ADMINISTRATION ). Carbidopa does not decrease adverse reactions due to central effects of levodopa. By permitting more levodopa to reach the brain, particularly when nausea and vomiting is not a dose-limiting factor, certain adverse central nervous system (CNS) effects, e.g., dyskinesias, will occur at lower dosages and sooner during therapy with carbidopa and levodopa extended-release tablets than with levodopa alone.
Patients receiving carbidopa and levodopa extended-release tablets may develop increased dyskinesias compared to carbidopa and levodopa tablets. Dyskinesias are a common side effect of carbidopa and levodopa treatment. The occurrence of dyskinesias may require dosage reduction.
All patients should be observed carefully for the development of depression with concomitant suicidal tendencies. Carbidopa and levodopa extended-release tablets should be administered cautiously to patients with severe cardiovascular or pulmonary disease, bronchial asthma, renal, hepatic or endocrine disease. As with levodopa, care should be exercised in administering carbidopa and levodopa extended-release tablets to patients with a history of myocardial infarction who have residual atrial, nodal, or ventricular arrhythmias.
In such patients, cardiac function should be monitored with particular care during the period of initial dosage adjustment, in a facility with provisions for intensive cardiac care. As with levodopa, treatment with carbidopa and levodopa extended-release tablets may increase the possibility of upper gastrointestinal hemorrhage in patients with a history of peptic ulcer. Falling Asleep During Activities of Daily Living and Somnolence Patients taking carbidopa and levodopa extended-release tablets alone or with other dopaminergic drugs have reported suddenly falling asleep without prior warning of sleepiness while engaged in activities of daily living (includes operation of motor vehicles).
Road traffic accidents attributed to sudden sleep onset have been reported. Although many patients reported somnolence while on dopaminergic medications, there have been reports of road traffic accidents attributed to sudden onset of sleep in which the patient did not perceive any warning signs, such as excessive drowsiness, and believed that they were alert immediately prior to the event. Sudden onset of sleep has been reported to occur as long as one year after the initiation of treatment.
Falling asleep while engaged in activities of daily living usually occurs in patients experiencing preexisting somnolence, although some patients may not give such a history. For this reason, prescribers should reassess patients for drowsiness or sleepiness especially since some of the events occur well after the start of treatment. Prescribers should be aware that patients may not acknowledge drowsiness or sleepiness until directly questioned about drowsiness or sleepiness during specific activities.
Patients should be advised to exercise caution while driving or operating machines during treatment with carbidopa and levodopa extended-release tablets. Patients who have already experienced somnolence or an episode of sudden sleep onset should not participate in these activities during treatment with carbidopa and levodopa extended-release tablets. Before initiating treatment with carbidopa and levodopa extended-release tablets, advise patients about the potential to develop drowsiness and ask specifically about factors that may increase the r…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS In controlled clinical trials, patients predominantly with moderate to severe motor fluctuations while on carbidopa and levodopa tablets were randomized to therapy with either carbidopa and levodopa tablets or carbidopa and levodopa extended-release tablets. The adverse experience frequency profile of carbidopa and levodopa extended-release tablets did not differ substantially from that of carbidopa and levodopa tablets, as shown in Table 1. Table 1.
Clinical Adverse Experiences Occurring in 1% or Greater of Patients Carbidopa and levodopa extended-release tablets Carbidopa and levodopa tablets n = 491 n = 524 Adverse Experience % % Dyskinesia 16.5
12.2Nausea 5.5
5.7Hallucinations 3.9
3.2Confusion 3.7
2.3Dizziness 2.9
2.3Depression 2.2
1.3Urinary tract infection 2.2
2.3 Headache 2
1.9Dream abnormalities 1.8
0.8Dystonia 1.8
0.8Vomiting 1.8
1.9Upper respiratory infection 1.8 1 Dyspnea 1.6 0.4 `On-Off' phenomena 1.6
1.1Back pain 1.6
0.6Dry mouth 1.4
1.1Anorexia 1.2
1.1Diarrhea 1.2
0.6Insomnia 1.2 1 Orthostatic hypotension 1
1.1 Shoulder pain 1
0.6 Chest pain 1
0.8Muscle cramps 0.8 1 Paresthesia 0.8
1.1Urinary frequency 0.8
1.1Dyspepsia 0.6
1.1Constipation 0.2
1.5Abnormal laboratory findings occurring at a frequency of 1% or greater in approximately 443 patients who received carbidopa and levodopa extended-release tablets and 475 who received carbidopa and levodopa tablets during controlled clinical trials included: decreased hemoglobin and hematocrit; elevated serum glucose; white blood cells, bacteria and blood in the urine. The adverse experiences observed in patients in uncontrolled studies were similar to those seen in controlled clinical studies. Other adverse experiences reported overall in clinical trials in 748 patients treated with carbidopa and levodopa extended-release tablets, listed by body system in order of decreasing frequency, include: Body as a Whole: Asthenia, fatigue, abdominal pain, orthostatic effects.
Cardiovascular: Palpitation, hypertension, hypotension, myocardial infarction. Gastrointestinal : Gastrointestinal pain, dysphagia, heartburn. Metabolic: Weight loss.
Musculoskeletal: Leg pain. Nervous System/Psychiatric: Chorea, somnolence, falling, anxiety, disorientation, decreased mental acuity, gait abnormalities, extrapyramidal disorder, agitation, nervousness, sleep disorders, memory impairment. Respiratory: Cough, pharyngeal pain, common cold.
Skin: Rash. Special Senses: Blurred vision. Urogenital: Urinary incontinence.
Laboratory Tests: Decreased white blood cell count and serum potassium; increased BUN, serum creatinine and serum LDH; protein and glucose in the urine. The following adverse experiences have been reported in postmarketing experience with carbidopa and levodopa extended-release tablets: Cardiovascular: Cardiac irregularities, syncope Gastrointestinal: Taste alterations, dark saliva. Hypersensitivity: Angioedema, urticaria, pruritus, bullous lesions (including pemphigus-like reactions).
Nervous System/Psychiatric: Increased tremor, peripheral neuropathy, psychotic episodes including delusions and paranoid ideation, pathological gambling, increased libido including hypersexuality, impulse control symptoms. Skin: Alopecia, flushing, dark sweat. Urogenital: Dark urine.
Other adverse reactions that have been reported with levodopa alone and with various carbidopa and levodopa formulations and may occur with carbidopa and levodopa extended-release tablets are: Cardiovascular: Phlebitis. Gastrointestinal: Gastrointestinal bleeding, development of duodenal ulcer, sialorrhea, bruxism, hiccups, flatulence, burning sensation of tongue. Hematologic: Hemolytic and non-hemolytic anemia, thrombocytopenia, leukopenia, agranulocytosis.
Hypersensitivity: Henoch-Schönlein purpura. Metabolic: Weight gain, edema. Nervous System/Psychiatric: Ataxia, depression with suicidal tendencies, dementia, euphoria, convulsions (however, a causal relationship has not been establish…
🔄 Drug Interactions ▾
Drug Interactions Caution should be exercised when the following drugs are administered concomitantly with carbidopa and levodopa extended-release tablets. Symptomatic postural hypotension has occurred when carbidopa and levodopa preparations were added to the treatment of patients receiving some antihypertensive drugs. Therefore, when therapy with carbidopa and levodopa extended-release tablets is started, dosage adjustment of the antihypertensive drug may be required.
For patients receiving MAO inhibitors (Type A or B), see CONTRAINDICATIONS . Concomitant therapy with selegiline and carbidopa and levodopa may be associated with severe orthostatic hypotension not attributable to carbidopa and levodopa alone (see CONTRAINDICATIONS ). There have been rare reports of adverse reactions, including hypertension and dyskinesia, resulting from the concomitant use of tricyclic antidepressants and carbidopa and levodopa preparations.
Dopamine D 2 receptor antagonists (e.g., phenothiazines, butyrophenones, risperidone) and isoniazid may reduce the therapeutic effects of levodopa. In addition, the beneficial effects of levodopa in Parkinson's disease have been reported to be reversed by phenytoin and papaverine. Patients taking these drugs with carbidopa and levodopa extended-release tablets should be carefully observed for loss of therapeutic response.
Use of carbidopa and levodopa extended-release tablets with dopamine-depleting agents (e.g., reserpine and tetrabenazine) or other drugs known to deplete monoamine stores is not recommended. Carbidopa and levodopa extended-release tablets iron salts or multivitamins containing iron salts should be coadministered with caution. Iron salts can form chelates with levodopa and carbidopa and consequently reduce the bioavailability of carbidopa and levodopa.
Although metoclopramide may increase the bioavailability of levodopa by increasing gastric emptying, metoclopramide may also adversely affect disease control by its dopamine receptor antagonistic properties.
🤰 Pregnancy ▾
Pregnancy Pregnancy Category C . No teratogenic effects were observed in a study in mice receiving up to 20 times the maximum recommended human dose of carbidopa and levodopa tablets. There was a decrease in the number of live pups delivered by rats receiving approximately two times the maximum recommended human dose of carbidopa and approximately five times the maximum recommended human dose of levodopa during organogenesis.
Carbidopa and levodopa tablets caused both visceral and skeletal malformations in rabbits at all doses and ratios of carbidopa/levodopa tested, which ranged from 10 times/5 times the maximum recommended human dose of carbidopa/levodopa to 20 times/10 times the maximum recommended human dose of carbidopa/levodopa. There are no adequate or well-controlled studies in pregnant women. It has been reported from individual cases that levodopa crosses the human placental barrier, enters the fetus, and is metabolized.
Carbidopa concentrations in fetal tissue appeared to be minimal. Use of carbidopa and levodopa extended-release tablets in women of childbearing potential requires that the anticipated benefits of the drug be weighed against possible hazards to mother and child.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in pediatric patients have not been established. Use of the drug in patients below the age of 18 is not recommended.
🧓 Geriatric Use ▾
Geriatric Use In the clinical efficacy trials for carbidopa and levodopa tablets, almost half of the patients were older than 65, but few were older than 75. No overall meaningful differences in safety or effectiveness were observed between these subjects and younger subjects, but greater sensitivity of some older individuals to adverse drug reactions such as hallucinations cannot be ruled out. There is no specific dosing recommendation based upon clinical pharmacology data as carbidopa and levodopa tablets and carbidopa and levodopa extended-release tablets are titrated as tolerated for clinical effect.
🆘 Overdosage ▾
OVERDOSAGE Management of acute overdosage with carbidopa and levodopa extended-release tablets is the same as with levodopa. Pyridoxine is not effective in reversing the actions of carbidopa and levodopa extended-release tablets. General supportive measures should be employed, along with immediate gastric lavage.
Intravenous fluids should be administered judiciously and an adequate airway maintained. Electrocardiographic monitoring should be instituted and the patient carefully observed for the development of arrhythmias; if required, appropriate antiarrhythmic therapy should be given. The possibility that the patient may have taken other drugs as well as carbidopa and levodopa extended-release tablets should be taken into consideration.
To date, no experience has been reported with dialysis; hence, its value in overdosage is not known. Based on studies in which high doses of levodopa and/or carbidopa were administered, a significant proportion of rats and mice given single oral doses of levodopa of approximately 1,500 to 2,000 mg/kg are expected to die. A significant proportion of infant rats of both sexes are expected to die at a dose of 800 mg/kg.
A significant proportion of rats are expected to die after treatment with similar doses of carbidopa. The addition of carbidopa in a 1:10 ratio with levodopa increases the dose at which a significant proportion of mice are expected to die to 3,360 mg/kg.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Parkinson's disease is a progressive, neurodegenerative disorder of the extrapyramidal nervous system affecting the mobility and control of the skeletal muscular system. Its characteristic features include resting tremor, rigidity, and bradykinetic movements. Symptomatic treatments, such as levodopa therapies, may permit the patient better mobility.
Current evidence indicates that symptoms of Parkinson's disease are related to depletion of dopamine in the corpus striatum. Administration of dopamine is ineffective in the treatment of Parkinson's disease apparently because it does not cross the blood-brain barrier. However, levodopa, the metabolic precursor of dopamine, does cross the blood-brain barrier, and presumably is converted to dopamine in the brain.
This is thought to be the mechanism whereby levodopa relieves symptoms of Parkinson's disease. Pharmacodynamics When levodopa is administered orally, it is rapidly decarboxylated to dopamine in extracerebral tissues so that only a small portion of a given dose is transported unchanged to the central nervous system. For this reason, large doses of levodopa are required for adequate therapeutic effect, and these may often be accompanied by nausea and other adverse reactions, some of which are attributable to dopamine formed in extracerebral tissues.
Since levodopa competes with certain amino acids for transport across the gut wall, the absorption of levodopa may be impaired in some patients on a high protein diet. Carbidopa inhibits decarboxylation of peripheral levodopa. It does not cross the blood-brain barrier and does not affect the metabolism of levodopa within the central nervous system.
Since its decarboxylase inhibiting activity is limited to extracerebral tissues, administration of carbidopa with levodopa makes more levodopa available for transport to the brain. Patients treated with levodopa therapy for Parkinson's disease may develop motor fluctuations characterized by end-of-dose failure, peak dose dyskinesia, and akinesia. The advanced form of motor fluctuations (`on-off' phenomenon) is characterized by unpredictable swings from mobility to immobility.
Although the causes of the motor fluctuations are not completely understood, in some patients they may be attenuated by treatment regimens that produce steady plasma levels of levodopa. Carbidopa and levodopa extended-release tablet contains either 50 mg of carbidopa and 200 mg of levodopa, or 25 mg of carbidopa and 100 mg of levodopa in an extended-release dosage form designed to release these ingredients over a 4- to 6-hour period. With carbidopa and levodopa extended-release tablets there is less variation in plasma levodopa levels than with carbidopa and levodopa tablets, the conventional formulation.
However, carbidopa and levodopa extended-release tablets are less systemically bioavailable than carbidopa and levodopa tablets and may require increased daily doses to achieve the same level of symptomatic relief as provided by carbidopa and levodopa tablets. In clinical trials, patients with moderate to severe motor fluctuations who received carbidopa and levodopa extended-release tablets did not experience quantitatively significant reductions in `off' time when compared to carbidopa and levodopa tablets. However, global ratings of improvement as assessed by both patient and physician were better during therapy with carbidopa and levodopa extended-release tablets than with carbidopa and levodopa tablets.
In patients without motor fluctuations, carbidopa and levodopa extended-release tablets, under controlled conditions, provided the same therapeutic benefit with less frequent dosing when compared to carbidopa and levodopa tablets. Pharmacokinetics Carbidopa reduces the amount of levodopa required to produce a given response by about 75% and, when administered with levodopa, increases both plasma levels and the plasma half-life of levodopa, and decreases plasma and urinar…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Carbidopa and levodopa extended-release tablets, USP 50 mg/200 mg containing 50 mg of carbidopa and 200 mg of levodopa, are buff colored, oval, biconvex uncoated tablets debossed “457” on one side and scored on other side, with mottled appearance. They are supplied as follows: NDC 62756-457-83 bottles of 30 NDC 62756-457-88 bottles of 100 (CRC) NDC 62756-457-08 bottles of 100 (NCRC) NDC 62756-457-18 bottles of 1000 Carbidopa and levodopa extended-release tablets, USP 25 mg/100 mg containing 25 mg carbidopa and 100 mg of levodopa, are buff colored, oval, biconvex, uncoated tablets debossed “461” on one side and plain on other side, with mottled appearance.
They are supplied as follows: NDC 62756-461-83 bottles of 30 NDC 62756-461-88 bottles of 100 (CRC) NDC 62756-461-08 bottles of 100 (NCRC) NDC 62756-461-18 bottles of 1000 Storage Store at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F). [See USP Controlled Room Temperature]. Store in a tightly closed container. Protected from light and moisture.
Dispense in a tightly closed, light-resistant container.
📋 Description ▾
DESCRIPTION Carbidopa and levodopa extended-release tablets, USP are extended-release combination of carbidopa and levodopa for the treatment of Parkinson's disease and syndrome. Carbidopa, an inhibitor of aromatic amino acid decarboxylation, is a white, crystalline compound, slightly soluble in water, with a molecular weight of 244.3. It is designated chemically as (-)-L-α-hydrazino-α-methyl-β-(3,4-dihydroxybenzene) propanoic acid monohydrate.
Its molecular formula is C 10 H 14 N 2 O 4 ·H 2 O and its structural formula is: Tablet content is expressed in terms of anhydrous carbidopa, which has a molecular weight of 226.3. Levodopa, an aromatic amino acid, is a white, crystalline compound, slightly soluble in water, with a molecular weight of 197.2. It is designated chemically as (-)-L-α-amino-β-(3,4-dihydroxybenzene) propanoic acid.
Its molecular formula is C 9 H 11 NO 4 and its structural formula is: Carbidopa and levodopa extended-release tablets, USP are supplied as extended-release tablets containing either 50 mg of carbidopa USP and 200 mg of levodopa USP, or 25 mg of carbidopa USP and 100 mg of levodopa USP. Inactive ingredients: microcrystalline cellulose, colloidal silicon dioxide, hypromellose, hydroxypropyl cellulose, magnesium stearate, red ferric oxide and D&C Yellow 10 Aluminum lake. The 50 mg/200 mg tablet is supplied as an oval, scored, biconvex, compressed tablet debossed “457” on one side and scored on other side that is buff colored with mottled appearance.
The 25 mg/100 mg tablet is supplied as an oval, biconvex, compressed tablet debossed “461” on one side and plain on other side that is buff colored with mottled appearance. Carbidopa and levodopa extended-release tablet is a polymeric-based drug delivery system that controls the release of carbidopa and levodopa as it slowly erodes. Carbidopa and levodopa extended-release tablet 25 mg/100 mg is available to facilitate titration when 100 mg steps are required.
Meets USP dissolution test 6. carbidopa-structure levodopa-structure
💬 Information for Patients ▾
Information for Patients The patient should be informed that carbidopa and levodopa extended-release tablet is an extended-release formulation of carbidopa and levodopa which releases these ingredients over a 4- to 6-hour period. It is important that carbidopa and levodopa extended-release tablets be taken at regular intervals according to the schedule outlined by the physician. The patient should be cautioned not to change the prescribed dosage regimen and not to add any additional antiparkinson medications, including other carbidopa and levodopa preparations, without first consulting the physician.
If abnormal involuntary movements appear or get worse during treatment with carbidopa and levodopa extended-release tablets, the physician should be notified, as dosage adjustment may be necessary. Patients should be advised that sometimes the onset of effect of the first morning dose of carbidopa and levodopa extended-release tablets may be delayed for up to 1 hour compared with the response usually obtained from the first morning dose of carbidopa and levodopa tablets. The physician should be notified if such delayed responses pose a problem in treatment.
Patients should be advised that, occasionally, dark color (red, brown, or black) may appear in saliva, urine, or sweat after ingestion of carbidopa and levodopa extended-release tablets. Although the color appears to be clinically insignificant, garments may become discolored. The patient should be informed that a change in diet to foods that are high in protein may delay the absorption of levodopa and may reduce the amount taken up in the circulation.
Excessive acidity also delays stomach emptying, thus delaying the absorption of levodopa. Iron salts (such as in multivitamin tablets) may also reduce the amount of levodopa available to the body. The above factors may reduce the clinical effectiveness of the levodopa or carbidopa and levodopa therapy.
Patients must be advised that the whole or half tablet should be swallowed without chewing or crushing. Patients should be alerted to the possibility of sudden onset of sleep during daily activities, in some cases without awareness or warning signs, when they are taking dopaminergic agents, including levodopa. Patients should be advised to exercise caution while driving or operating machinery and that if they have experienced somnolence and/or sudden sleep onset, they must refrain from these activities.
(See WARNINGS, Falling Asleep During Activities of Daily Living and Somnolence) There have been reports of patients experiencing intense urges to gamble, increased sexual urges, and other intense urges, and the inability to control these urges while taking one or more of the medications that increase central dopaminergic tone and that are generally used for the treatment of Parkinson’s disease, including carbidopa and levodopa extended-release tablets. Although it is not proven that the medications caused these events, these urges were reported to have stopped in some cases when the dose was reduced or the medication was stopped.
Prescribers should ask patients about the development of new or increased gambling urges, sexual urges or other urges while being treated with carbidopa and levodopa extended-release tablets. Patients should inform their physician if they experience new or increased gambling urges, increased sexual urges, or other intense urges while taking carbidopa and levodopa extended-release tablets. Physicians should consider dose reduction or stopping the medication if a patient develops such urges while taking carbidopa and levodopa extended-release tablets.
(See PRECAUTIONS, Impulse Control / Compulsive Behaviors)