
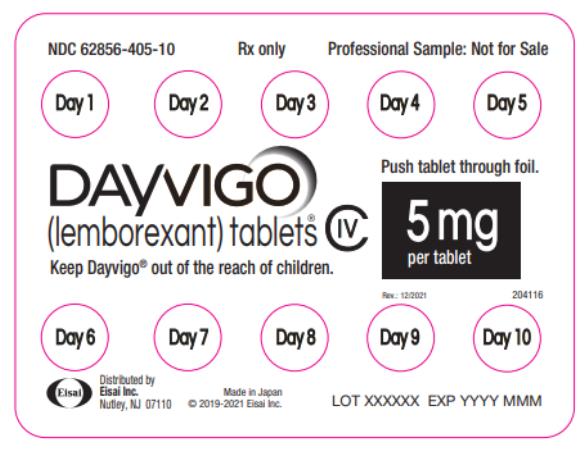
Dayvigo lemborexant 5 mg Tablet, Film Coated, 10-count — NDC 62856-405-10 (Billing 62856-0405-10)
This is a package of 10 tablets of Dayvigo lemborexant 5 mg Tablet, Film Coated from Eisai Inc., marketed since Apr 2020 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 62856-405-10 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 62856 labeler · 405 product · 10 package
- Package marketed since
- Apr 7, 2020
- Sample package
- Yes — professional sample, not for sale
- Listing certified through
- Dec 31, 2026
- Barcode (UPC)
- 0362856410304, 0362856405300, 0362856410908, 0362856405904
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 080590
- GCN: 47479
- GPI-14 (Medi-Span): 60500040000320
- HICL (First Databank): 046275
- AHFS class code: 28:24.40.00
- RxCUI (RxNorm): 2272408
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Orexin Receptor Antagonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Lemborexant is used to treat insomnia (difficulty falling asleep or staying asleep). Lemborexant belongs to a class of medications called hypnotics. It works by slowing activity in the brain to allow sleep.
Read the full MedlinePlus article ↗- Lemborexant, sold as Dayvigo, treats insomnia in adults. It can help if you have trouble falling asleep, staying asleep, or both.
- Take your tablet by mouth right before bed, no more than once a night. Make sure you have at least 7 hours left to sleep. Taking it with or just after a meal may slow how fast it w...
- Be careful. It can leave you drowsy or less alert the next day, and driving was impaired in some people on the higher dose. Don't drive or do tasks needing full alertness until you...
- It's best not to. Alcohol adds to the sedation and can worsen your balance and memory.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Lemborexant — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $11.59 | $115.87 / 10 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 8, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 62856-0405-10 You're viewing this | 1 BLISTER PACK in 1 CARTON / 10 TABLET, FILM COATED in 1 BLISTER PACK Sample | — | — | 2020-04-07 | — | Active |
| 62856-0405-30 62856-405-30 Main listing | 30 TABLET, FILM COATED in 1 BOTTLE | $11.58 / ea | $347.33 | 2020-04-07 | — | Active |
| 62856-0405-90 62856-405-90 | 90 TABLET, FILM COATED in 1 BOTTLE | — | — | 2020-04-07 | — | Active |
This pack shows little to no recent Medicaid volume — the 30 tablets pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 62856-0405-30?
What NDC number is used to bill for this package of Dayvigo lemborexant 5 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Dayvigo 5 mgthis 62856-0405-10 | Eisai | 10 tablets | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8268848 ↗ | Drug substance | U-2791 | Sep 20, 2031 |
| US 10188652 ↗ | Method of use | U-2791 | Oct 21, 2035 |
| US 10188652 ↗ | Method of use | U-2791 | Oct 21, 2035 |
| US 8268848 ↗ | Drug substance | U-2791 | Sep 20, 2031 |
| US 11026944 ↗ | Drug product | — | Oct 21, 2035 |
| US 10702529 ↗ | Drug product | — | Oct 21, 2035 |
| US 11026944 ↗ | Drug product | — | Oct 21, 2035 |
| US 10702529 ↗ | Drug product | — | Oct 21, 2035 |
| Code | What it grants | Expires |
|---|---|---|
| M-293 | New indication / labeling change (3-year) | Apr 20, 2026 |
| M-293 | New indication / labeling change (3-year) | Apr 20, 2026 |
Is there a generic version of DAYVIGO 5 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Lemborexant inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 8VAB711C5E
Hydroxypropyl cellulose is a plant-based thickener made from cellulose. In medicines, it acts as a binder to hold ingredients together, a coating to protect the tablet or capsule, and a thickener to create the right texture in liquids or gels.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII NZ94SDL6WR
Low-substituted hydroxypropyl cellulose is a plant-based thickener and binder made from cellulose. It helps hold the medicine together, controls how quickly it dissolves, and improves texture in tablets and capsules.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII Q662QK8M3B
Polyethylene glycol 8000 is a synthetic polymer made from ethylene oxide. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and add bulk to the medicine.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Eisai Inc. labeler code 62856
- Fycompa perampanel 6 mg Tablet NDC 62856-276-30
- Fycompa perampanel 8 mg Tablet NDC 62856-278-30
- Fycompa perampanel 10 mg Tablet NDC 62856-280-30
- Fycompa perampanel 12 mg Tablet NDC 62856-282-30
- Fycompa perampanel .5 mg/mL Suspension NDC 62856-290-38
- Halaven eribulin mesylate .5 mg/mL Injection NDC 62856-389-01
- Dayvigo lemborexant 10 mg Tablet, Film Coated NDC 62856-410-30
- Banzel rufinamide 200 mg Tablet, Film Coated NDC 62856-582-04
- Banzel rufinamide 400 mg Tablet, Film Coated NDC 62856-583-14
- Banzel rufinamide 40 mg/mL Suspension NDC 62856-584-46
- Lenvima Lenvatinib 4 mg Capsule NDC 62856-704-30
- Lenvima Lenvatinib 4 mg Capsule NDC 62856-708-30
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE DAYVIGO is indicated for the treatment of adult patients with insomnia, characterized by difficulties with sleep onset and/or sleep maintenance [see Clinical Studies ( 14.1 )] . DAYVIGO is an orexin receptor antagonist indicated for the treatment of adult patients with insomnia, characterized by difficulties with sleep onset and/or sleep maintenance. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended dose is 5 mg taken no more than once per night, immediately before going to bed, with at least 7 hours remaining before the planned time of awakening. Dosage may be increased to 10 mg based on clinical response and tolerability. ( 2.1 ) The maximum recommended dose is 10 mg once daily.
( 2.1 ) Time to sleep onset may be delayed if taken with or soon after a meal. ( 2.1 ) Hepatic Impairment: ( 2.3 ) ○ Moderate hepatic impairment: Initial and maximum recommended dosage is 5 mg no more than once per night. ○ Severe hepatic impairment: Not recommended.
2.1Dosing Information The recommended dosage of DAYVIGO is 5 mg taken no more than once per night, immediately before going to bed, with at least 7 hours remaining before the planned time of awakening. The dose may be increased to the maximum recommended dose of 10 mg based on clinical response and tolerability. Time to sleep onset may be delayed if taken with or soon after a meal [see Clinical Pharmacology ( 12.3 )].
2.2Dosage Recommendations for Concomitant Use with CYP3A Inhibitors or CYP3A Inducers Co-administration with Strong or Moderate CYP3A Inhibitors Avoid concomitant use of DAYVIGO with strong or moderate CYP3A inhibitors [see Drug Interactions ( 7.1 ), Clinical Pharmacology ( 12.3 )]. Co-administration with Weak CYP3A Inhibitors The maximum recommended dosage of DAYVIGO is 5 mg no more than once per night when co-administered with weak CYP3A inhibitors [see Drug Interactions ( 7.1 ), Clinical Pharmacology ( 12.3 )]. Co-administration with Strong or Moderate CYP3A Inducers Avoid concomitant use of DAYVIGO with strong or moderate CYP3A inducers [see Drug Interactions ( 7.1 ), Clinical Pharmacology ( 12.3 )].
2.3Dosage Recommendations for Patients with Hepatic Impairment The maximum recommended dose of DAYVIGO is 5 mg no more than once per night in patients with moderate hepatic impairment [see Use in Specific Populations ( 8.7 ), Clinical Pharmacology ( 12.3 )]. DAYVIGO is not recommended in patients with severe hepatic impairment [see Use in Specific Populations ( 8.7 )].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS DAYVIGO (lemborexant) tablets are available as: 5 mg tablets: pale yellow, round, biconvex, film-coated tablets, and debossed with "5" on one side and "LЄM" on the other side. 10 mg tablets: orange, round, biconvex, film-coated tablets, and debossed with "10" on one side and "LЄM" on the other side. Tablets: 5 mg, 10 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS DAYVIGO is contraindicated in patients with narcolepsy. DAYVIGO is contraindicated in patients with narcolepsy. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS CNS Depressant Effects and Daytime Impairment: Impairs alertness and motor coordination including morning impairment. Risk increases with dose and use with other central nervous system (CNS) depressants. For patients taking DAYVIGO 10 mg, caution against next-day driving and other activities requiring complete mental alertness.
( 5.1 ) Sleep Paralysis, Hypnagogic/Hypnopompic Hallucinations, and Cataplexy-like Symptoms: May occur with use of DAYVIGO. ( 5.2 ) Complex Sleep Behaviors: Behaviors including sleep-walking, sleep-driving, and engaging in other activities while not fully awake may occur. Discontinue immediately if a complex sleep behavior occurs.
( 5.3 ) Compromised Respiratory Function: Effect on respiratory function should be considered. ( 5.4 , 8.8 ) Worsening of Depression/Suicidal Ideation: Worsening of depression or suicidal thinking may occur. Prescribe the lowest number of tablets feasible to avoid intentional overdosage.
( 5.5 ) Need to Evaluate for Co-morbid Diagnoses: Reevaluate if insomnia persists after 7 to 10 days of treatment. ( 5.6 )
5.1CNS Depressant Effects and Daytime Impairment DAYVIGO is a central nervous system (CNS) depressant that can impair daytime wakefulness even when used as prescribed. CNS depressant effects may persist in some patients for up to several days after discontinuing DAYVIGO. Prescribers should advise patients about the potential for next-day somnolence.
Driving ability was impaired in some subjects taking DAYVIGO 10 mg [see Clinical Studies ( 14.2 )]. The risk of daytime impairment is increased if DAYVIGO is taken with less than a full night of sleep remaining or if a higher than recommended dose is taken [see Dosage and Administration ( 2.1 )]. If DAYVIGO is taken in these circumstances, patients should be cautioned against driving and other activities requiring complete mental alertness.
Co-administration with other CNS depressants (e.g., benzodiazepines, opioids, tricyclic antidepressants, alcohol) increases the risk of CNS depression, which can cause daytime impairment. Dosage adjustments of DAYVIGO and of concomitant CNS depressants may be necessary when administered together because of potentially additive effects. The use of DAYVIGO with other drugs to treat insomnia is not recommended .
Patients should be advised not to consume alcohol in combination with DAYVIGO because of additive effects [see Drug Interactions ( 7.1 )]. Because DAYVIGO can cause drowsiness, patients, particularly the elderly, are at a higher risk of falls.
5.2Sleep Paralysis, Hypnagogic/Hypnopompic Hallucinations, and Cataplexy - l ike Symptoms Sleep paralysis, an inability to move or speak for up to several minutes during sleep-wake transitions, and hypnagogic/hypnopompic hallucinations, including vivid and disturbing perceptions, can occur with the use of DAYVIGO. Prescribers should explain the nature of these events to patients when prescribing DAYVIGO. Symptoms similar to mild cataplexy can occur with DAYVIGO.
Such symptoms can include periods of leg weakness lasting from seconds to a few minutes, can occur either at night or during the day, and may not be associated with an identified triggering event (e.g., laughter or surprise).
5.3Complex Sleep Behaviors Complex sleep behaviors, including sleep-walking, sleep-driving, and engaging in other activities while not fully awake (e.g., preparing and eating food, making phone calls, having sex), have been reported to occur with the use of hypnotics such as DAYVIGO. These events can occur in hypnotic-naïve as well as in hypnotic-experienced persons. Patients usually do not remember these events.
Complex sleep behaviors may occur following the first or any subsequent use of DAYVIGO, with or without the concomitant use of alcohol and other CNS depressants [see Drug Interactions ( 7.1 )] . Discontinue DAYVIGO immediately if a patient experiences a complex sleep behavior.
5.4Patients with Compromised Respiratory Function DA… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are discussed in detail in other sections of the labeling: CNS Depressant Effects and Daytime Impairment [see Warnings and Precautions ( 5.1 )] Sleep Paralysis, Hypnagogic/Hypnopompic Hallucinations, and Cataplexy-like Symptoms [see Warnings and Precautions ( 5.2 )] Complex Sleep Behaviors [see Warnings and Precautions ( 5.3 )] Patients with Compromised Respiratory Function [see Warnings and Precautions ( 5.4 )] Worsening of Depression/Suicidal Ideation [see Warnings and Precautions ( 5.5 )] The most common adverse reaction (reported in ≥5% of patients treated with DAYVIGO and at least twice the rate of placebo) was somnolence.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Eisai Inc. at 1-888-274-2378 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety of DAYVIGO was evaluated in 1418 adult patients with insomnia disorder (age 18 to 88 years) from two controlled efficacy trials (Study 1 and Study 2). Study 1 was a 6-month placebo-controlled trial assessing DAYVIGO 5 or 10 mg once nightly, followed by a 6-month parallel-group extension period in which patients initially treated with DAYVIGO continued on the same dose, and patients who received placebo were re-randomized to receive DAYVIGO 5 or 10 mg once nightly.
In Study 1, 434 patients were treated with DAYVIGO for one year. Study 2 was a 30-day placebo- and active-controlled trial assessing DAYVIGO 5 or 10 mg once nightly. Adverse Reactions Resulting in Discontinuation of Treatment The frequencies of discontinuation due to adverse reactions in Study 1 (the first 30 days) and Study 2 were 2.6% and 1.4% for patients treated with 10 mg and 5 mg DAYVIGO, respectively, compared to 1.5% for patients in the placebo group.
The most common adverse reactions leading to discontinuation of DAYVIGO were somnolence (1.0% for 10 mg, 0.7% for 5 mg, and 0.4% for placebo) and nightmares (0.3% for 10 mg, 0.3% for 5 mg, and 0% for placebo). The frequencies of discontinuation due to adverse reactions in the 6-month placebo-controlled period of Study 1 were 8.3% and 4.1% for patients treated with DAYVIGO 10 mg and 5 mg, respectively, compared to 3.8% for patients in the placebo group. The most common reasons for discontinuation of DAYVIGO and occurring in more than one patient within a treatment arm were somnolence (2.9% for 10 mg, 1.0% for 5 mg, and 0.6% for placebo), nightmares (1.3% for 10 mg, 0.3% for 5 mg, and 0% for placebo), and palpitations (0.6% for 10 mg, 0% for 5 mg, and 0% for placebo).
Most Common Adverse Reactions The most common adverse reaction (reported in 5% or more of patients treated with DAYVIGO and at least twice the rate of placebo) in Study 1 (the first 30 days) and Study 2 was somnolence (10% for DAYVIGO 10 mg, 7% for DAYVIGO 5 mg, and 1% for placebo). Table 1 presents the adverse reactions based on the pooled data from the first 30 days of Study 1 (6-month controlled efficacy trial) and Study 2 (1-month controlled efficacy trial) where the incidence was ≥2% in DAYVIGO-treated patients and greater than in placebo-treated patients.
Table 1: Adverse Reactions Reported in ≥ 2% of DAYVIGO-Treated Patients and at a Greater Frequency than Placebo-Treated Patients During the First 30 D ays of Study 1 and Study 2 DAYVIGO Placebo 5 mg 10 mg n=528 n=580 n=582 (%) (%) (%) Somnolence or fatigue * 1.3 6.9
9.6Headache 3.4 5.9
4.5Nightmare or abnormal dreams 0.9 0.9 2.2 * Combines preferred terms somnolence, lethargy, fatigue, sluggishness Other Adverse Reactions Observed During Clinical Trials (Studies 1 and 2) Other adverse reactions of <2% incidence but greater than placebo are shown below. The follow… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Strong or moderate CYP3A inhibitors: Avoid concomitant use. ( 7.1 ) Weak CYP3A inhibitors: The maximum recommended dose is 5 mg. ( 2.2 , 7.1 ) Strong or moderate CYP3A inducers: Avoid concomitant use. ( 7.1 )
7.1Drugs Having Clinically Important Interactions with DAYVIGO Table 2: Clinically Important Drug Interactions with DAYVIGO Effect of Other Drugs on DAYVIGO Strong, Moderate, and Weak CYP3A Inhibitors Clinical Impact: Concomitant use with a strong, moderate, or weak CYP3A inhibitor increases lemborexant AUC and C max which may increase the risk of DAYVIGO adverse reactions [see Clinical Pharmacology ( 12.3 )]. Intervention: Avoid concomitant use of DAYVIGO with strong or moderate CYP3A inhibitors [see Dosage and Administration ( 2.2 )].
The maximum recommended dose of DAYVIGO with weak CYP3A inhibitors is 5 mg [see Dosage and Administration ( 2.2 )]. Examples: Strong CYP3A inhibitors: itraconazole, clarithromycin Moderate CYP3A inhibitors: fluconazole, verapamil Weak CYP3A inhibitors: chlorzoxazone, ranitidine Strong and Moderate CYP3A Inducers Clinical Impact: Concomitant use with a strong or moderate CYP3A inducer decreases lemborexant exposure, which may reduce DAYVIGO efficacy [see Clinical Pharmacology ( 12.3 )]. Intervention: Avoid concomitant use of DAYVIGO with strong or moderate CYP3A inducers [see Dosage and Administration ( 2.2 )].
Examples: Strong CYP3A inducers: rifampin, carbamazepine, St. John’s wort Moderate CYP3A inducers: bosentan, efavirenz, etravirine, modafinil Alcohol Clinical Impact: Concomitant use of alcohol increases lemborexant C max and AUC. Co-administration of DAYVIGO with alcohol produced a numerically greater negative impact on postural stability and memory as compared with alcohol alone when assessed near the t max of DAYVIGO (2 hours post-dose) [see Clinical Pharmacology ( 12.2 )].
Intervention: Avoid alcohol consumption with DAYVIGO [see Warnings and Precautions ( 5.1 )]. Effect of DAYVIGO on Other Drugs CYP2B6 Substrates Clinical Impact: Concomitant use of DAYVIGO decreases the AUC of drugs that are CYP2B6 substrates, which may result in reduced efficacy for these concomitant medications [see Clinical Pharmacology ( 12.3 )]. Intervention: Patients receiving DAYVIGO and CYP2B6 substrates concurrently should be monitored for adequate clinical response.
Increasing the doses of CYP2B6 substrates may be considered as needed. Examples: Bupropion, methadone
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women who are exposed to psychiatric medications, including DAYVIGO, during pregnancy. Healthcare providers are encouraged to advise patients to register by calling the National Pregnancy Registry for Psychiatric Medications, at1-866-961-2388 or visiting online at https://womensmentalhealth.org/research/pregnancyregistry . Risk Summary There are no available data on DAYVIGO use in pregnant women to evaluate for drug-associated risks of major birth defects, miscarriage or adverse maternal or fetal outcomes.
In animal reproduction studies, oral administration of lemborexant to pregnant rats and rabbits during the period of organogenesis caused toxicities only at high multiples of the human exposure at the maximum recommended human dose (MRHD) based on AUC. The no observed adverse effect levels (NOAEL) are approximately >100 and 23 times the MRHD based on AUC in rats and rabbits, respectively. Similarly, oral administration of lemborexant to pregnant and lactating rats caused toxicities only at high multiples of the human exposure at the MRHD based on AUC.
The NOAEL is 93 times the MRHD based on AUC ( see Data ) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies are 2% to 4% and 15% to 20%, respectively. Data Animal Data Lemborexant was administered orally to pregnant rats during the period of organogenesis in 2 studies at doses of 60, 200, and 600 mg/kg/day or 20, 60, and 200 mg/kg/day, which are approximately 6 to >300 times the MRHD based on AUC. Lemborexant caused maternal toxicity, manifested by decreased body weight and food consumption, decreased mean fetal body weight, an increased number of dead fetuses, and skeletal, external and visceral malformations (omphalocele, cleft palate, and membranous ventricular septal defect) at >300 times the MRHD based on AUC.
The NOAEL of 200 mg/kg/day is approximately 143 times the MRHD based on AUC. Lemborexant was administered orally to pregnant rabbits during the period of organogenesis at doses of 10, 30, and 100 mg/kg/day, which are approximately 7 to 139 times the MRHD based on AUC. Lemborexant caused maternal toxicity that consisted of decreased body weight and food consumption and a higher incidence of skeletal variations (presence of cervical ribs and supernumerary lung lobes) at approximately 139 times the MRHD based on AUC.
The NOAEL of 30 mg/kg/day is approximately 23 times the MRHD based on AUC. Lemborexant was administered orally to pregnant rats during pregnancy and lactation at doses of 30, 100, and 300 mg/kg/day, which are approximately 15 to 206 times the MRHD based on AUC. Lemborexant caused maternal toxicity that consisted of decreased body weight and food consumption and toxicity to offspring consisting of decreased pup body weights, decreased femur length, and decreased acoustic startle responses at 206 times the MRHD based on AUC.
The NOAEL of 100 mg/kg/day is approximately 93 times the MRHD based on AUC.
8.2Lactation Risk Summary Available data from a lactation study in 8 women indicates that lemborexant is transferred into the breastmilk of nursing mothers, and the results have established a mean daily infant dose of 0.0029 mg/kg/day and a relative infant dose of less than 2% of the maternal dose. These data support that transfer of lemborexant into breastmilk is low (see Data). There are no data on the effects of lemborexant on the breastfed infant, or the effects on milk production.
Infants exposed to DAYVIGO through breastmilk should be monitored for excessive sedation. The developmental and health benefits of breastfeeding should… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women who are exposed to psychiatric medications, including DAYVIGO, during pregnancy. Healthcare providers are encouraged to advise patients to register by calling the National Pregnancy Registry for Psychiatric Medications, at1-866-961-2388 or visiting online at https://womensmentalhealth.org/research/pregnancyregistry . Risk Summary There are no available data on DAYVIGO use in pregnant women to evaluate for drug-associated risks of major birth defects, miscarriage or adverse maternal or fetal outcomes.
In animal reproduction studies, oral administration of lemborexant to pregnant rats and rabbits during the period of organogenesis caused toxicities only at high multiples of the human exposure at the maximum recommended human dose (MRHD) based on AUC. The no observed adverse effect levels (NOAEL) are approximately >100 and 23 times the MRHD based on AUC in rats and rabbits, respectively. Similarly, oral administration of lemborexant to pregnant and lactating rats caused toxicities only at high multiples of the human exposure at the MRHD based on AUC.
The NOAEL is 93 times the MRHD based on AUC ( see Data ) . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies are 2% to 4% and 15% to 20%, respectively. Data Animal Data Lemborexant was administered orally to pregnant rats during the period of organogenesis in 2 studies at doses of 60, 200, and 600 mg/kg/day or 20, 60, and 200 mg/kg/day, which are approximately 6 to >300 times the MRHD based on AUC. Lemborexant caused maternal toxicity, manifested by decreased body weight and food consumption, decreased mean fetal body weight, an increased number of dead fetuses, and skeletal, external and visceral malformations (omphalocele, cleft palate, and membranous ventricular septal defect) at >300 times the MRHD based on AUC.
The NOAEL of 200 mg/kg/day is approximately 143 times the MRHD based on AUC. Lemborexant was administered orally to pregnant rabbits during the period of organogenesis at doses of 10, 30, and 100 mg/kg/day, which are approximately 7 to 139 times the MRHD based on AUC. Lemborexant caused maternal toxicity that consisted of decreased body weight and food consumption and a higher incidence of skeletal variations (presence of cervical ribs and supernumerary lung lobes) at approximately 139 times the MRHD based on AUC.
The NOAEL of 30 mg/kg/day is approximately 23 times the MRHD based on AUC. Lemborexant was administered orally to pregnant rats during pregnancy and lactation at doses of 30, 100, and 300 mg/kg/day, which are approximately 15 to 206 times the MRHD based on AUC. Lemborexant caused maternal toxicity that consisted of decreased body weight and food consumption and toxicity to offspring consisting of decreased pup body weights, decreased femur length, and decreased acoustic startle responses at 206 times the MRHD based on AUC.
The NOAEL of 100 mg/kg/day is approximately 93 times the MRHD based on AUC.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of DAYVIGO have not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of patients treated with DAYVIGO (n=1418) in controlled Phase 3 studies, 491 patients were 65 years and over, and 87 patients were 75 years and over. Overall, efficacy results for patients <65 years of age were similar compared to patients ≥65 years. In a pooled analysis of Study 1 (the first 30 days) and Study 2, the incidence of somnolence in patients ≥65 years with DAYVIGO 10 mg was higher (9.8%) compared to 7.7% in patients <65 years.
The incidence of somnolence with DAYVIGO 5 mg was similar in patients ≥65 years (4.9%) and <65 years (5.1%). The incidence of somnolence in patients treated with placebo was 2% or less regardless of age [see Clinical Studies ( 14.2 )]. Because DAYVIGO can increase somnolence and drowsiness, patients, particularly the elderly, are at a higher risk of falls [see Warning s and Precautions ( 5.1 )] .
Exercise caution when using doses higher than 5 mg in patients ≥65 years old.
🆘 Overdosage ▾
10 OVERDOSAGE There is limited clinical experience with DAYVIGO overdose. In clinical pharmacology studies, healthy patients who were administered multiple doses of up to 75 mg (7.5 times the maximum recommended dose) of DAYVIGO showed dose-dependent increases in the frequency of somnolence. There is no available specific antidote to an overdose of DAYVIGO.
In the event of overdose, standard medical practice for the management of any overdose should be used. In managing overdose, provide supportive care, including close medical supervision and monitoring and consider the possibility of multiple drug involvement. Consult a Certified Poison Control Center for the most up to date information on the management of overdosage (1-800-222-1222 or www.poison.org).
The value of dialysis in the treatment of overdosage has not been determined with lemborexant. As lemborexant is highly protein-bound, hemodialysis is not expected to contribute to elimination of lemborexant.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY Figure 1. Effects of Hepatic and Renal Impairment on Lemborexant Pharmacokinetics Figure 2. Effects of Co-administered Drugs on the Pharmacokinetics of Lemborexant 10 mg Figure 3. Effects of Lemborexant 10 mg on the Pharmacokinetics of Co-Administered Drugs
12.1Mechanism of Action The mechanism of action of lemborexant in the treatment of insomnia is presumed to be through antagonism of orexin receptors. The orexin neuropeptide signaling system plays a role in wakefulness. Blocking the binding of wake-promoting neuropeptides orexin A and orexin B to receptors OX1R and OX2R is thought to suppress wake drive.
12.2Pharmacodynamics Lemborexant binds to orexin receptors OX1R and OX2R and acts as a competitive antagonist (IC 50 values of 6.1 nM and 2.6 nM, respectively). A major metabolite of lemborexant, M10, binds with comparable affinity as the parent drug to orexin receptors OX1R and OX2R (IC 50 values of 4.2 nM and 2.9 nM), respectively. Cardiac Electrophysiology In a concentration-QTcF analysis using the data from two randomized, double-blind, placebo-controlled, multiple ascending dose studies in healthy subjects, lemborexant does not prolong the QTcF interval to any clinically relevant extent at a dose 5 times the maximum recommended dose.
Drug Interactions Lemborexant co-administered with alcohol produced a numerically greater negative impact on postural stability and memory as compared with alcohol alone at approximately 2 hours post-dose [see Drug Interactions 7.1 ].
12.3Pharmacokinetics Following single doses of lemborexant 2.5 to 75 mg, geometric mean C max and AUC 0-24h increased slightly less than in proportion to dose. The extent of accumulation of lemborexant at steady-state is 1.5- to 3-fold across this dose range. Absorption The time to peak concentration (t max ) of lemborexant is approximately 1 to 3 hours.
Effect of Food Lemborexant C max decreased by 23%, AUC 0-inf increased by 18%, and t max was delayed by 2 hours following administration of a high-fat and high-calorie meal (containing approximately 150, 250, and 500 to 600 calories from protein, carbohydrate, and fat, respectively). Distribution The volume of distribution of lemborexant is 1970 L. Plasma protein binding of lemborexant is approximately 88% in vitro and 94% in clinical samples.
The blood to plasma concentration ratio of lemborexant is 0.65. Elimination Metabolism Lemborexant is primarily metabolized by CYP3A4, and to a lesser extent by CYP3A5. The major circulating metabolite is M10.
Excretion Following administration of an oral dose, 57.4% of the dose was recovered in the feces and 29.1% in the urine (<1% as unchanged). The effective half-life for lemborexant 5 mg and 10 mg is 17 and 19 hours, respectively. Specific Populations No clinically significant differences in the pharmacokinetics of lemborexant were observed based on age, sex, race/ethnicity, or body mass index.
No studies have been conducted to investigate the pharmacokinetics of lemborexant in pediatric patients. Exposures of lemborexant in patients with hepatic and renal impairment are summarized in Figure 1. Figure 1.
Effects of Hepatic and Renal Impairment on Lemborexant Pharmacokinetics Drug Interaction Studies The effects of other drugs on the exposures of lemborexant are summarized in Figure 2. The effects of lemborexant on the exposures of other drugs are summarized in Figure 3. Based on these results, drug interactions between lemborexant and strong CYP3A inducers, strong CYP3A inhibitors, moderate CYP3A inhibitors, and CYP2B6 substrates are clinically significant [see Dosage and Administration ( 2.2 ), Drug Interactions ( 7.1 )].
Physiologically-based pharmacokinetic (PBPK) modeling predicted that concomitant use of weak CYP3A inhibitors increased lemborexant exposure by less than 2-fold [see Dosage and Administration ( 2.2 ), Drug Interactions ( 7.1 )] , and that lemborexant is expected to have minimal effect on the pharmacokinetics of CYP2C8,… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action of lemborexant in the treatment of insomnia is presumed to be through antagonism of orexin receptors. The orexin neuropeptide signaling system plays a role in wakefulness. Blocking the binding of wake-promoting neuropeptides orexin A and orexin B to receptors OX1R and OX2R is thought to suppress wake drive.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied DAYVIGO tablets are available as: 5 mg, pale yellow, round, biconvex, film-coated tablets, and debossed with "5" on one side and "LЄM" on the other side. NDC 62856-405-30, bottle of 30 with child-resistant closure NDC 62856-405-90, bottle of 90 with child-resistant closure 10 mg, orange, round, biconvex, film-coated tablets, and debossed with "10" on one side and "LЄM" on the other side. NDC 62856-410-30, bottle of 30 with child-resistant closure NDC 62856-410-90, bottle of 90 with child-resistant closure
16.2Storage and Handling Store at 20°C to 25°C (68°F to 77°F), excursions permitted between 15°C and 30°C (59°F and 86°F) [See USP Controlled Room Temperature].
16.1How Supplied DAYVIGO tablets are available as: 5 mg, pale yellow, round, biconvex, film-coated tablets, and debossed with "5" on one side and "LЄM" on the other side. NDC 62856-405-30, bottle of 30 with child-resistant closure NDC 62856-405-90, bottle of 90 with child-resistant closure 10 mg, orange, round, biconvex, film-coated tablets, and debossed with "10" on one side and "LЄM" on the other side. NDC 62856-410-30, bottle of 30 with child-resistant closure NDC 62856-410-90, bottle of 90 with child-resistant closure
📦 Storage and Handling ▾
16.2Storage and Handling Store at 20°C to 25°C (68°F to 77°F), excursions permitted between 15°C and 30°C (59°F and 86°F) [See USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION DAYVIGO contains lemborexant, an orexin receptor antagonist. The chemical name of lemborexant is (1R,2S)-2-{[(2,4-dimethylpyrimidin-5-yl)oxy]methyl}-2-(3-fluorophenyl)- N -(5-fluoropyridin-2-yl) cyclopropanecarboxamide. The molecular formula is C 22 H 20 F 2 N 4 O 2 .
The molecular weight is 410.42. The structural formula is: Lemborexant is a white to off-white powder that is practically insoluble in water. DAYVIGO tablets are intended for oral administration.
Each film coated tablet contains 5 mg or 10 mg of lemborexant. The inactive ingredients are: hydroxypropyl cellulose, lactose monohydrate, low-substituted hydroxypropyl cellulose, and magnesium stearate. In addition, the film coating contains the following inactive ingredients: hypromellose 2910, polyethylene glycol 8000, talc, titanium dioxide, and either (a) ferric oxide yellow for the 5 mg tablet; or, (b) both ferric oxide yellow and ferric oxide red for the 10 mg tablet.
The structural formula for DAYVIGO contains lemborexant, an orexin receptor antagonist. The chemical name of lemborexant is (1R,2S)-2-{[(2,4-dimethylpyrimidin-5-yl)oxy]methyl}-2-(3-fluorophenyl)-N-(5-fluoropyridin-2-yl) cyclopropanecarboxamide. The molecular formula is C22H20F2N4O2.
The molecular weight is 410.42.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Medication Guide ). Administration Instructions Advise patients to take DAYVIGO only when preparing for or getting into bed and only if they can stay in bed for a full night (at least 7 hours) before being active again [see Dosage and Administration ( 2.1 ) ] . Advise patients that the effect of DAYVIGO may be delayed if taken with or soon after a meal [see Dosage and Administration ( 2.1 ), Clinical Pharmacology ( 12.3 )] .
CNS Depressant Effects and Daytime Impairment Advise patients that DAYVIGO can impair daytime wakefulness even when used as prescribed. The risk of daytime impairment is increased if DAYVIGO is taken with less than a full night of sleep remaining or if a higher than recommended dose is taken. If DAYVIGO is taken in these circumstances, caution patients against driving and other activities requiring complete mental alertness.
Advise patients that increased drowsiness may increase the risk of falls in some patients [see Warnings and Precautions ( 5.1 )]. Sleep Paralysis, Hypnagogic/Hypnopompic Hallucinations, and Cataplexy-Like Symptoms Advise patients and their families that DAYVIGO may cause sleep paralysis, which is an inability to move or speak for several minutes during sleep-wake transitions, despite being aware of surroundings; hypnagogic/hypnopompic hallucinations, including vivid and disturbing perceptions; and symptoms similar to mild cataplexy [see Warnings and Precautions ( 5.2 )].
Complex Sleep Behaviors Instruct patients and their families that DAYVIGO may cause complex sleep behaviors, including sleep-walking, sleep-driving, preparing and eating food, making phone calls, or having sex while not being fully awake. Tell patients to discontinue DAYVIGO and notify their healthcare provider immediately if they develop any of these symptoms [see Warnings and Precautions ( 5.3 )]. Worsening of Depression/Suicidal Ideation Tell patients to report any worsening of depression or suicidal thoughts immediately [see Warnings and Precautions ( 5.4 )].
Pregnancy Advise patients that there is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to DAYVIGO during pregnancy [see Use in Specific Populations ( 8.1 )]. Concomitant Medications Ask patients about alcohol consumption, medicines they are taking, and drugs they may be taking without a prescription. Advise patients not to consume alcohol in combination with DAYVIGO [see Drug Interactions ( 7.1 ), Clinical Pharmacology ( 12.3 )].
Tolerance, Abuse, and Dependence Tell patients not to increase the dose of DAYVIGO on their own, and to inform you if they believe the drug “does not work” [see Drug Abuse and Dependence ( 9 )]. Distributed by: Eisai Inc. Nutley, NJ 07110 DAYVIGO ® is a registered trademark of Eisai R&D Management Co., Ltd. and is licensed to Eisai Inc. © 2019-2025 Eisai Inc.
💬 Medication Guide ▾
MEDICATION GUIDE DAYVIGO ® (daye-vi'-goe) (lemborexant) tablets, for oral use , CIV What is the most important information I should know about DAYVIGO? DAYVIGO may cause serious side effects including: Decreased awareness and alertness. The morning after you take DAYVIGO, your ability to drive safely and think clearly may be decreased.
You may also have sleepiness during the day. ○ Do not take more DAYVIGO than prescribed. ○ Do not take DAYVIGO unless you are able to stay in bed for a full night (at least 7 hours) before you must be active again. ○ Take DAYVIGO right before going to bed. See “What are the possible side effects of DAYVIGO?” for more information about side effects. What is DAYVIGO?
DAYVIGO is a prescription medicine for adults who have trouble falling or staying asleep (insomnia). It is not known if DAYVIGO is safe and effective in children under the age of 18 years. DAYVIGO is a federally controlled substance (CIV) because it can be abused or cause dependence.
Keep DAYVIGO in a safe place to prevent misuse and abuse. Selling or giving away DAYVIGO may harm others and is against the law. Tell your doctor if you have ever abused or have been dependent on alcohol, prescription medicines or street drugs.
Who should not take DAYVIGO? Do not take DAYVIGO if you fall asleep often at unexpected times (narcolepsy). Before taking DAYVIGO, tell your healthcare provider about all of your medical conditions, including if you: have a history of depression, mental illness, or suicidal thoughts. have a history of drug or alcohol abuse or addiction. have a history of a sudden onset of muscle weakness (cataplexy). have a history of daytime sleepiness. have lung problems or breathing problems. have liver problems. are pregnant or plan to become pregnant.
It is not known if DAYVIGO can harm your unborn baby. Pregnancy Registry : There is a pregnancy registry for women who are exposed to DAYVIGO during pregnancy or who become pregnant while taking DAYVIGO. The purpose of this registry is to collect information about the health of you and your baby.
For more information or to participate in the registry, call 1-866-961-2388 or go to https://womensmentalhealth.org/research/pregnancyregistry. Talk with your healthcare provider about the risk to your unborn baby if you take DAYVIGO during pregnancy. are breastfeeding or plan to breastfeed. DAYVIGO passes into your breastmilk.
Talk to your healthcare provider about the best way to feed your baby during treatment with DAYVIGO. Tell your healthcare provider about all of the medicines you take , including prescription and over-the-counter medicines, vitamins and herbal supplements. Taking DAYVIGO with certain other medicines can cause serious side effects.
DAYVIGO may affect the way other medicines work and other medicines may affect the way DAYVIGO works. Do not take DAYVIGO with other medicines that can make you sleepy unless your healthcare provider tells you to. Know the medicines you take.
Keep a list of your medicines with you to show your healthcare provider and pharmacist each time you get a new medicine. How should I take DAYVIGO? Take DAYVIGO exactly as your healthcare provider tells you to take it.
Only take DAYVIGO one time each night, right before going to bed. Only take DAYVIGO when you can stay in bed for a full night (at least 7 hours). DAYVIGO may take longer to work if you take it with or soon after a meal.
Do not increase your dose of DAYVIGO without talking to your healthcare provider first. Call your healthcare provider if your insomnia (sleep problem) worsens or is not improved within 7 to 10 days. This may mean that there is another condition causing your sleep problem.
If you take too much DAYVIGO, call your healthcare provider or go to the nearest hospital emergency room right away. What should I avoid while taking DAYVIGO? Do not drink alcohol while taking DAYVIGO.
It can increase your chances of getting serious side effects. Do not drive , operate heavy machinery… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Following single doses of lemborexant 2.5 to 75 mg, geometric mean C max and AUC 0-24h increased slightly less than in proportion to dose. The extent of accumulation of lemborexant at steady-state is 1.5- to 3-fold across this dose range. Absorption The time to peak concentration (t max ) of lemborexant is approximately 1 to 3 hours.
Effect of Food Lemborexant C max decreased by 23%, AUC 0-inf increased by 18%, and t max was delayed by 2 hours following administration of a high-fat and high-calorie meal (containing approximately 150, 250, and 500 to 600 calories from protein, carbohydrate, and fat, respectively). Distribution The volume of distribution of lemborexant is 1970 L. Plasma protein binding of lemborexant is approximately 88% in vitro and 94% in clinical samples.
The blood to plasma concentration ratio of lemborexant is 0.65. Elimination Metabolism Lemborexant is primarily metabolized by CYP3A4, and to a lesser extent by CYP3A5. The major circulating metabolite is M10.
Excretion Following administration of an oral dose, 57.4% of the dose was recovered in the feces and 29.1% in the urine (<1% as unchanged). The effective half-life for lemborexant 5 mg and 10 mg is 17 and 19 hours, respectively. Specific Populations No clinically significant differences in the pharmacokinetics of lemborexant were observed based on age, sex, race/ethnicity, or body mass index.
No studies have been conducted to investigate the pharmacokinetics of lemborexant in pediatric patients. Exposures of lemborexant in patients with hepatic and renal impairment are summarized in Figure 1. Figure 1.
Effects of Hepatic and Renal Impairment on Lemborexant Pharmacokinetics Drug Interaction Studies The effects of other drugs on the exposures of lemborexant are summarized in Figure 2. The effects of lemborexant on the exposures of other drugs are summarized in Figure 3. Based on these results, drug interactions between lemborexant and strong CYP3A inducers, strong CYP3A inhibitors, moderate CYP3A inhibitors, and CYP2B6 substrates are clinically significant [see Dosage and Administration ( 2.2 ), Drug Interactions ( 7.1 )].
Physiologically-based pharmacokinetic (PBPK) modeling predicted that concomitant use of weak CYP3A inhibitors increased lemborexant exposure by less than 2-fold [see Dosage and Administration ( 2.2 ), Drug Interactions ( 7.1 )] , and that lemborexant is expected to have minimal effect on the pharmacokinetics of CYP2C8, CYP2C9, or CYP2C19 substrates. Figure 2. Effects of Co-administered Drugs on the Pharmacokinetics of Lemborexant 10 mg Figure 3.
Effects of Lemborexant 10 mg on the Pharmacokinetics of Co-Administered Drugs In Vitro Studies In vitro metabolism studies demonstrated that lemborexant and M10 have the potential to induce CYP3A and a weak potential to inhibit CYP3A and induce CYP2B6. Lemborexant and M10 do not inhibit other CYP isoforms (CYP1A2, CYP2A6, CYP2B6, CYP2C8, CYP2C9, CYP2C19, CYP2D6, and CYP2E1) or transporters (P-gp, BCRP, BSEP, OAT1, OAT3, OATP1B1, OATP1B3, OCT1, OCT2, MATE1, and MATE2-K). Lemborexant and M10 do not induce CYP2C8, CYP2C9, and CYP2C19 at clinically relevant concentrations.
Lemborexant is a potential poor substrate of P-gp, but M10 is a substrate of P-gp. Lemborexant and M10 are not substrates of BCRP, OATP1B1, or OATP1B3.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Lemborexant binds to orexin receptors OX1R and OX2R and acts as a competitive antagonist (IC 50 values of 6.1 nM and 2.6 nM, respectively). A major metabolite of lemborexant, M10, binds with comparable affinity as the parent drug to orexin receptors OX1R and OX2R (IC 50 values of 4.2 nM and 2.9 nM), respectively. Cardiac Electrophysiology In a concentration-QTcF analysis using the data from two randomized, double-blind, placebo-controlled, multiple ascending dose studies in healthy subjects, lemborexant does not prolong the QTcF interval to any clinically relevant extent at a dose 5 times the maximum recommended dose.
Drug Interactions Lemborexant co-administered with alcohol produced a numerically greater negative impact on postural stability and memory as compared with alcohol alone at approximately 2 hours post-dose [see Drug Interactions 7.1 ].
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Controlled Clinical Studies DAYVIGO was evaluated in two clinical trials in patients with insomnia characterized by difficulties with sleep onset and/or sleep maintenance (Study 1, NCT02952820 and Study 2, NCT02783729). Study 1 was a 6-month, randomized, double-blind, placebo-controlled, multi-center trial in adult patients age 18 or older who met DSM-5 criteria for insomnia disorder. Patients were randomized to placebo (n=325), DAYVIGO 5 mg (n=323), or DAYVIGO 10 mg (n=323) once nightly.
The primary efficacy endpoint was the mean change from baseline to end of treatment at 6 months for log-transformed patient-reported (subjective) sleep onset latency (sSOL), defined as the estimated minutes from the time that the patient attempted to sleep until sleep onset. Pre-specified secondary efficacy endpoints for sleep maintenance were change from baseline to end of treatment at 6 months for patient-reported sleep efficiency (sSEF) and wake after sleep onset (sWASO). sSEF is defined as the proportion of time spent asleep per time in bed. sWASO is defined as the minutes of wake from the onset of sleep until wake time.
The primary and pre-specified secondary efficacy endpoints were measured by sleep diary. The demographic characteristics of patients in Study 1 were similar across the treatment arms. Patients had a median age of 55 years (range 18 to 88) and were 68% female, 72% White, 8% Black or African American, 17% Japanese, and 3.5% other; 28% were elderly (≥65 years).
Examination of subgroups by age, race, and sex did not suggest differences in response to DAYVIGO. In Study 1, DAYVIGO 5 mg and 10 mg demonstrated statistically significant superiority on the primary efficacy measure, sSOL, compared to placebo (Table 3). DAYVIGO 5 mg and 10 mg also showed statistically significant superiority in sSEF and sWASO.
Table 3: Primary and Secondary Efficacy Results for Change from Baseline in Sleep Onset and Sleep Maintenance at 6 Months in Patients with Insomnia (Study 1) Endpoint Treatment Group Number of Patients ITT Baseline Mean a (SD) Month 6 LS Mean a (SE) Treatment Effect (95% CI) Sleep Onset sSOL (minutes) DAYVIGO 5 mg * 316 43.0 (31.5) 20.0 (1.1) 0.7 (0.6, 0.8) DAYVIGO 10 mg * 315 45.0 (33.4) 19.2 (1.1) 0.7 (0.6, 0.8) Placebo 318 45.0 (31.8) 27.3 (1.4) (ratio vs placebo) b Sleep Maintenance sSEF (%) DAYVIGO 5 mg * 316 63.1 (18.2) 75.9 (0.9) 4.5 (2.2, 6.9) DAYVIGO 10 mg * 315 62.0 (17.2) 75.9 (0.9) 4.7 (2.4, 7.0) Placebo 318 61.3 (17.8) 71.4 (0.8) (%) c Sleep Maintenance sWASO (minutes) DAYVIGO 5 mg * 316 132.8 (82.5) 87.9 (3.7) -17.5 (-27.3, -7.6) DAYVIGO 10 mg * 315 136.8 (87.4) 92.7 (3.7) -12.7 (-22.4, -3.0) Placebo 318 132.5 (80.2) 105.3 (3.6) (minutes) c ITT (intention to treat); sSOL (subjective sleep onset latency); SD (standard deviation); LS (least squares); SE (standard error); CI (unadjusted confidence interval); sSEF (subjective sleep efficiency); sWASO (subjective wake after sleep onset) a For the sleep onset sSOL endpoint, the mean refers to geometric mean, which was used due to the approximately log normal distribution of the outcomes; SD for the geometric mean is calculated as GM*SD (log transformed sSOL); SE for the least squares geometric mean is calculated in the same way as the SD. b For the sleep onset sSOL endpoint, treatment effect refers to the ratio of [Month 6 sSOL / Baseline sSOL] for DAYVIGO versus placebo, such that a smaller ratio corresponds to a greater improvement. c Treatment effect refers to the treatment difference between DAYVIGO versus placebo, such that a larger value for sSEF and smaller value for sWASO correspond to greater improvement. * Doses that were statistically significantly superior (p<0.05) to placebo after multiplicity adjustment.
Study 2 was a 1-month, randomized, double-blind, placebo- and active-controlled, multi-center, parallel-group clinical trial in adult female patients age 55 and older and male patients 65 years and older who met DSM-5 criteria for… [Excerpted — this section continues on DailyMed.]
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.1Controlled Substance DAYVIGO contains lemborexant, a Schedule IV controlled substance.
9.2Abuse Abuse is the intentional, non-therapeutic use of a drug, even once, for its desirable psychological or physiological effects. In a human abuse potential study conducted in recreational sedative abusers (n=29), lemborexant 10 mg, 20 mg (two times the maximum recommended dose), and 30 mg (three times the maximum recommended dose) produced responses on positive subjective measures such as “Drug Liking,” “Overall Drug Liking,” “Take Drug Again,” and “Good Drug Effects” that were statistically similar to those produced by the sedatives zolpidem (30 mg) and suvorexant (40 mg), and statistically greater than the responses on these measures that were produced by placebo.
Because individuals with a history of abuse or addiction to alcohol or other drugs may be at increased risk for abuse and addiction to DAYVIGO, follow such patients carefully.
9.3Dependence Physical dependence is a state that develops as a result of physiological adaptation in response to repeated drug use, manifested by withdrawal signs and symptoms after abrupt discontinuation or a significant dose reduction of a drug. In animal studies and clinical trials evaluating physical dependence, chronic administration of lemborexant did not produce withdrawal signs or symptoms upon drug discontinuation. This suggests that lemborexant does not produce physical dependence.
🔒 Controlled Substance ▾
9.1Controlled Substance DAYVIGO contains lemborexant, a Schedule IV controlled substance.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Lemborexant did not increase the incidence of tumors in rats treated for 2 years at oral doses of 30, 100, and 300 mg/kg/day (males) and 10, 30, and 100 mg/kg/day (females), which are >80 times the MRHD based on AUC. Lemborexant did not increase the incidence of tumors in Tg ras H2 mice treated for 26 weeks at oral doses of 50, 150, and 500 mg/kg/day. Mutagenesis Lemborexant was not mutagenic in the in vitro bacterial reverse mutation (Ames) assay or in the in vitro mouse lymphoma thymidine kinase assay, and was not clastogenic in the in vivo rat micronucleus assay.
Impairment of Fertility Lemborexant was orally administered to female rats at doses of 30, 100, or 1000 mg/kg/day prior to and throughout mating and continuing to gestation Day 6. These doses are approximately 12 to >500 times the MRHD based on AUC. Irregular estrous cycles and decreased pregnancy rate were observed at 60 times the MRHD based on AUC, and decreased numbers of corpora lutea, implantations, and live embryos were observed at >500 times the MRHD based on AUC.
The exposure at the NOAEL of 30 mg/kg/day is approximately 12 times the MRHD based on AUC. Lemborexant did not affect fertility when orally administered to male rats at doses of 30, 100, or 1000 mg/kg/day prior to and throughout mating; the highest dose is approximately 138 times the MRHD based on AUC.
13.2Animal Toxicology and/or Pharmacology Lemborexant administered to mice at oral doses of 10 or 30 mg/kg resulted in behavior characteristic of cataplexy when presented with chocolate. Chocolate is a stimulus that has been demonstrated to increase cataplexy occurrences in narcoleptic mice.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Lemborexant did not increase the incidence of tumors in rats treated for 2 years at oral doses of 30, 100, and 300 mg/kg/day (males) and 10, 30, and 100 mg/kg/day (females), which are >80 times the MRHD based on AUC. Lemborexant did not increase the incidence of tumors in Tg ras H2 mice treated for 26 weeks at oral doses of 50, 150, and 500 mg/kg/day. Mutagenesis Lemborexant was not mutagenic in the in vitro bacterial reverse mutation (Ames) assay or in the in vitro mouse lymphoma thymidine kinase assay, and was not clastogenic in the in vivo rat micronucleus assay.
Impairment of Fertility Lemborexant was orally administered to female rats at doses of 30, 100, or 1000 mg/kg/day prior to and throughout mating and continuing to gestation Day 6. These doses are approximately 12 to >500 times the MRHD based on AUC. Irregular estrous cycles and decreased pregnancy rate were observed at 60 times the MRHD based on AUC, and decreased numbers of corpora lutea, implantations, and live embryos were observed at >500 times the MRHD based on AUC.
The exposure at the NOAEL of 30 mg/kg/day is approximately 12 times the MRHD based on AUC. Lemborexant did not affect fertility when orally administered to male rats at doses of 30, 100, or 1000 mg/kg/day prior to and throughout mating; the highest dose is approximately 138 times the MRHD based on AUC.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL NDC 62856-405-30 DAYVIGO (lemborexant) tablets 5 mg 30 Tablets NDC 62856-405-30 DAYVIGO (lemborexant) tablets 5 mg 30 Tablets
PRINCIPAL DISPLAY PANEL NDC 62856-405-90 DAYVIGO (lemborexant) tablets 5 mg 90 Tablets NDC 62856-405-90 DAYVIGO (lemborexant) tablets 5 mg 90 Tablets
PRINCIPAL DISPLAY PANEL NDC 62856-410-30 DAYVIGO (lemborexant) tablets 10 mg 30 Tablets NDC 62856-410-30 DAYVIGO (lemborexant) tablets 10 mg 30 Tablets
PRINCIPAL DISPLAY PANEL NDC 62856-410-90 DAYVIGO (lemborexant) tablets 10 mg 90 Tablets NDC 62856-410-90 DAYVIGO (lemborexant) tablets 10 mg 90 Tablets
PRINCIPAL DISPLAY PANEL NDC 62856-405-10 DAYVIGO (lemborexant) tablets 5 mg Professional Sample: Not for Sale NDC 62856-405-10 DAYVIGO (lemborexant) tablets 5 mg Professional Sample: Not for Sale
PRINCIPAL DISPLAY PANEL NDC 62856-405-10 DAYVIGO (lemborexant) tablets 5 mg Professional Sample: Not for Sale NDC 62856-405-10 DAYVIGO (lemborexant) tablets 5 mg Professional Sample: Not for Sale
PRINCIPAL DISPLAY PANEL NDC 62856-455-10 DAYVIGO (lemborexant) tablets 5 mg Professional Sample: Not for Sale PRINCIPAL DISPLAY PANEL NDC 62856-455-10 DAYVIGO (lemborexant) tablets 5 mg Professional Sample: Not for Sale
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |