
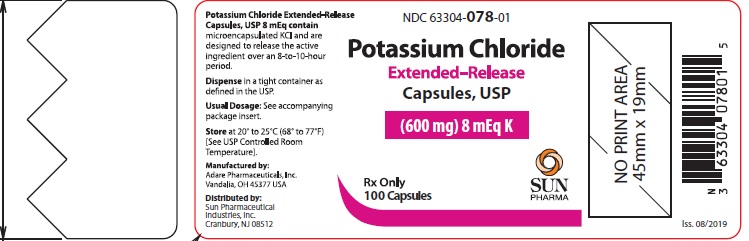
POTASSIUM CHLORIDE 750 mg Capsule, Extended Release, 500-count
Other active recalls for Potassium Chloride (different manufacturers) — 6 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Potassium class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- You're right that food is the first line — bananas, potatoes, and leafy greens are all rich in potassium. But sometimes diet alone isn't enough, especially if you're taking a diure...
- Why did my doctor prescribe potassium chloride? I thought potassium just came from bananas.
- Yes — always take oral tablets or capsules with a meal or right after eating. Taking them on an empty stomach can irritate or even ulcerate the lining of your stomach or intestines...
- Do I have to take it with food? What happens if I forget?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Potassium Chloride (prescription drug) — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.133 | $66.45 / 500 capsules |
| Medicaid paysCMS SDUD · 12 mo | $0.2979 | $148.95 / 500 capsules |
| Medicare drug plans payPart D · Q2 2026 | $0.2694 | $134.70 / 500 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Potassium Chloride 750 mg 59917-0103-01 | Adare | 100 capsules | $0.130 | — | FDA listed | save 2% |
| Potassium Chloride 750 mg 68462-0357-01 | Glenmark | 100 capsules | $0.130 | — | FDA listed | save 2% |
| Potassium Chloride 750 mg 68001-0396-00 | BluePoint | 100 capsules | $0.131 | — | FDA listed | save 2% |
| Potassium Chloride 750 mg 00904-7543-61 | Major | 1 capsule | $0.133 | AB | Availability likely | — |
| potassium chloride 750 mg 43547-0553-10 | Solco | 100 capsules | $0.133 | AB | Availability likely | — |
| Potassium Chloride 750 mg 50268-0671-13 | AvPAK | 1 capsule | $0.133 | AB | Availability likely | — |
| Potassium Chloride 750 mg 53746-0542-01 | Amneal | 100 capsules | $0.133 | AB | Availability likely | — |
| Potassium Chloride 750 mg 60687-0653-01 | American | 1 capsule | $0.133 | AB | Availability likely | — |
| Potassium Chloride 750 mg 62037-0560-01 | Actavis | 100 capsules | $0.133 | AB | Availability likely | — |
| Potassium Chloride 750 mgthis 63304-0090-05 | Sun | 500 capsules | $0.133 | AB | Availability likely | — |
| Potassium Chloride 750 mg 68001-0619-00 | BluePoint | 100 capsules | $0.133 | AB | Availability likely | — |
| Potassium Chloride 750 mg 70010-0148-01 | Granules | 100 capsules | $0.133 | AB | Availability likely | — |
| Potassium Chloride 750 mg 00615-8442-05 | NCS | 15 capsules | — | AB | FDA listed | — |
| Potassium Chloride 750 mg 16714-0824-01 | Northstar | 100 capsules | — | — | FDA listed | — |
| Potassium Chloride 750 mg 42291-0679-50 | AvKARE | 500 capsules | — | AB | FDA listed | — |
| Potassium Chloride 10 meq 50090-4734-09 | A-S | 90 capsules | — | — | FDA listed | — |
| Potassium Chloride 750 mg 50090-7469-00 | A-S | 30 capsules | — | AB | FDA listed | — |
| Potassium Chloride 750 mg 62207-0915-43 | Granules | 100 capsules | — | AB | FDA listed | — |
| potassium chloride 750 mg 68382-0854-01 | Zydus | 100 capsules | — | AB | FDA listed | — |
| Potassium Chloride 750 mg 70518-4050-00 | REMEDYREPACK | 30 capsules | — | AB | FDA listed | — |
| Potassium Chloride 750 mg 72789-0057-01 | PD-Rx | 100 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 63304-0090-01 | 100 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (63304-090-01) | $0.1329 / ea | $13.29 | 2020-01-02 | Active |
| 63304-0090-05 You're viewing this | 500 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (63304-090-05) | $0.1329 / ea | $66.43 | 2020-01-02 | Active |
You're viewing the largest of 2 pack sizes for this product.
This pack effectively ties for the lowest per-ea cost of the 2 priced pack sizes ($0.1329 NADAC).
This pack accounts for about 13% of this product's recent Medicaid fills; most go to the 100 capsules pack. See all packs ↓
Pack size FAQ
What quantity is in NDC 63304-0090-05?
What is the difference between NDC 63304-0090-05 and NDC 63304-0090-01?
What NDC number is used to bill for this package of POTASSIUM CHLORIDE 750 mg Capsule, Extended Release?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Potassium chloride extended-release capsules are indicated for the treatment and prophylaxis of hypokalemia in adults and children with or without metabolic alkalosis, in patients for whom dietary management with potassium-rich foods or diuretic dose reduction is insufficient. Potassium chloride extended-release capsules contain potassium chloride, a potassium salt indicated for the treatment and prophylaxis of hypokalemia with or without metabolic alkalosis, in patients for whom dietary management with potassium-rich foods or diuretic dose reduction is insufficient.
(1)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Monitor serum potassium and adjust dosage accordingly (2.1) If serum potassium concentration is <2.5 mEq/L, use intravenous potassium instead of oral supplementation. (2.1) Treatment of hypokalemia: Adults: Typical doses range from 40-100 mEq/day in 2-5 divided doses; limit doses to 40 mEq per dose. (2.2) Pediatric patients: 2-4 mEq/kg/day in divided doses not to exceed 1 mEq/kg as a single dose or 20 mEq, whichever is lower; if deficits are severe or ongoing losses are great, consider intravenous therapy.
(2.3) Maintenance or Prophylaxis of hypokalemia: Adults: Typical dose is 20 mEq per day (2.2) Pediatric patients: Typical dose is 1 mEq/kg/day. (2.3)
2.1Administration and Monitoring If serum potassium concentration is <2.5 mEq/L, use intravenous potassium instead of oral supplementation. Monitoring Monitor serum potassium and adjust dosages accordingly. Monitor serum potassium periodically during maintenance therapy to ensure potassium remains in desired range.
The treatment of potassium depletion, particularly in the presence of cardiac disease, renal disease, or acidosis requires careful attention to acid-base balance, volume status, electrolytes, including magnesium, sodium, chloride, phosphate, and calcium, electrocardiograms and the clinical status of the patient. Correct volume status, acid-base balance and electrolyte deficits as appropriate. Administration Take with meals and with a full glass of water or other liquid.
Do not take on an empty stomach because of the potential for gastric irritation [see Warnings and Precautions (5.1) ] . Patients who have difficulty swallowing capsules may sprinkle the contents of the capsule onto a spoonful of soft food. The soft food, such as applesauce or pudding, should be swallowed immediately without chewing and followed with a glass of water or juice to ensure complete swallowing of the microcapsules.
Do not add to hot foods. Any microcapsule/food mixture should be used immediately and not stored for future use.
2.2Adult Dosing Dosage must be adjusted to the individual needs of each patient. Dosages greater than 40 mEq per day should be divided such that no more than 40 mEq is given in a single dose. Treatment of hypokalemia: Typical dose range is 40-100 mEq per day. Maintenance or Prophylaxis: Typical dose is 20 mEq per day.
2.3Pediatric Dosing Pediatric patients aged birth to 16 years old: Dosage must be adjusted to the individual needs of each patient. Do not exceed as a single dose 1 mEq/kg or 20 mEq, whichever is lower. Treatment of hypokalemia : The recommended initial dose is 2 to 4 mEq/kg/day in divided doses. If deficits are severe or ongoing losses are great, consider intravenous therapy. Maintenance or Prophylaxis : Typical dose is 1 mEq/kg/day.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 600 mg (8 mEq): White to ivory opaque capsules printed with “102” in black ink on the cap. 750 mg (10 mEq): Light blue opaque capsules printed with “103” in black ink on the cap. Extended-release capsules: 600 mg (8mEq) and 750 mg (10 mEq)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Potassium chloride extended-release capsules are contraindicated in patients on amiloride or triamterene. Concomitant use with triamterene and amiloride. (4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Gastrointestinal Irritation: Take with meals (5.1)
5.1Gastrointestinal Adverse Reactions Solid oral dosage forms of potassium chloride can produce ulcerative and/or stenotic lesions of the gastrointestinal tract, particularly if the drug is in contact with the gastrointestinal mucosa for a prolonged period of time. Consider the use of liquid potassium in patients with dysphagia, swallowing disorders, or severe gastrointestinal motility disorders. If severe vomiting, abdominal pain, distention, or gastrointestinal bleeding occurs, discontinue potassium chloride extended-release capsules and consider possibility of ulceration, obstruction or perforation.
Potassium chloride extended-release capsules should not be taken on an empty stomach because of its potential for gastric irritation [see Dosage and Administration (2.1) ].
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions have been identified with use of oral potassium salts. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. The most common adverse reactions to oral potassium salts are nausea, vomiting, flatulence, abdominal pain/discomfort, and diarrhea.
There have been reports of hyperkalemia and of upper and lower gastrointestinal conditions including obstruction, bleeding, ulceration, and perforation. Skin rash has been reported rarely. Most common adverse reactions are nausea, vomiting, flatulence, abdominal pain/discomfort, and diarrhea.
(6) To report SUSPECTED ADVERSE REACTIONS, contact the manufacturer Adare at 1-877-731-5116, or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Triamterene and amiloride: Concomitant use is contraindicated (7.1) Renin-angiotensin-aldosterone inhibitors: Monitor for hyperkalemia (7.2) Nonsteroidal Anti-inflammatory drugs (NSAIDS): Monitor for hyperkalemia (7.3)
7.1Amiloride and Triamterene Use with triamterene or amiloride can produce severe hyperkalemia. Concomitant use is contraindicated [see Contraindications (4) ].
7.2Renin-Angiotensin-Aldosterone Inhibitors Drugs that inhibit the renin-angiotensin-aldosternone system (RAAS) including angiotensin converting enzyme (ACE) inhibitors, angiotensin receptor blockers (ARBs), spironolactone, eplerenone, or aliskiren produces potassium retention by inhibiting aldosterone production. Closely monitor potassium in patients taking drugs that inhibit RAAS.
7.3Nonsteroidal Anti-Inflammatory Drugs (NSAIDs) NSAIDs may produce potassium retention by reducing renal synthesis of prostaglandin E and impairing the renin-angiotensin system. Closely monitor potassium in patients taking NSAIDS.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Cirrhosis: Initiate therapy at the low end of the dosing range (8.6) Renal Impairment: Initiate therapy at the low end of the dosing range (8.7)
8.1Pregnancy Risk Summary There are no human data related to use of potassium chloride extended-release capsules during pregnancy and animal reproductive studies have not been conducted. Potassium supplementation that does not lead to hyperkalemia is not expected to cause fetal harm. The background risk for major birth defects and miscarriage in the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
8.2Lactation Risk Summary The normal potassium ion content of human milk is about 13 mEq per liter. Since oral potassium becomes part of the body potassium pool, as long as body potassium is not excessive, the contribution of potassium chloride supplementation should have little or no effect on the level in human milk.
8.4Pediatric Use Clinical trial data from published literature have demonstrated the safety and effectiveness of potassium chloride in children with diarrhea and malnutrition from birth to 18 years.
8.5Geriatric Use Clinical studies of potassium chloride did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
This drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
8.6Cirrhotics Based on published literature, the baseline corrected serum concentrations of potassium measured over 3 hours after administration in cirrhotic subjects who received an oral potassium load rose to approximately twice that of normal subjects who received the same load. Patients with cirrhosis should usually be started at the low end of the dosing range, and the serum potassium level should be monitored frequently [see Clinical Pharmacology (12.3) ].
8.7Renal Impairment Patients with renal impairment have reduced urinary excretion of potassium and are at substantially increased risk of hyperkalemia. Patients with impaired renal function, particularly if the patient is on RAAS inhibitors or nonsteroidal anti-inflammatory drugs, should usually be started at the low end of the dosing range because of the potential for development of hyperkalemia [see Drug Interactions (7.2 , 7.3) ] . The serum potassium level should be monitored frequently.
Renal function should be assessed periodically.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no human data related to use of potassium chloride extended-release capsules during pregnancy and animal reproductive studies have not been conducted. Potassium supplementation that does not lead to hyperkalemia is not expected to cause fetal harm. The background risk for major birth defects and miscarriage in the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
🧒 Pediatric Use ▾
8.4Pediatric Use Clinical trial data from published literature have demonstrated the safety and effectiveness of potassium chloride in children with diarrhea and malnutrition from birth to 18 years.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of potassium chloride did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
This drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Symptoms The administration of oral potassium salts to persons with normal excretory mechanisms for potassium rarely causes serious hyperkalemia. However, if excretory mechanisms are impaired, potentially fatal hyperkalemia can result. Hyperkalemia is usually asymptomatic and may be manifested only by an increased serum potassium concentration (6.5- 8.0 mEq/L) and characteristic electrocardiographic changes (peaking of T-waves, loss of P-waves, depression of S-T segment, and prolongation of the QT-interval).
Late manifestations include muscle paralysis and cardiovascular collapse from cardiac arrest (9-12 mEq/L).
10.2Treatment Treatment measures for hyperkalemia include the following: Monitor closely for arrhythmias and electrolyte changes. Eliminate foods and medications containing potassium and any agents with potassium-sparing properties such as potassium-sparing diuretics, ARBs, ACE inhibitors, NSAIDs, certain nutritional supplements, and many others. Administer intravenous calcium gluconate if the patient is at no risk or low risk of developing digitalis toxicity.
Administer 300 to 500 mL/hr of 10% dextrose solution containing 10 to 20 units of crystalline insulin per 1,000 mL. Correct acidosis, if present, with intravenous sodium bicarbonate. Use exchange resins, hemodialysis, or peritoneal dialysis.
In patients who have been stabilized on digitalis, too rapid a lowering of the serum potassium concentration can produce digitalis toxicity. The extended-release feature means that absorption and toxic effects may be delayed for hours. Consider standard measures to remove any unabsorbed drug.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The potassium ion (K+) is the principal intracellular cation of most body tissues. Potassium ions participate in a number of essential physiological processes, including the maintenance of intracellular tonicity; the transmission of nerve impulses; the contraction of cardiac, skeletal, and smooth muscle; and the maintenance of normal renal function. The intracellular concentration of potassium is approximately 150 to 160 mEq per liter.
The normal adult plasma concentration is 3.5 to 5 mEq per liter. An active ion transport system maintains this gradient across the plasma membrane. Potassium is a normal dietary constituent and under steady-state conditions the amount of potassium absorbed from the gastrointestinal tract is equal to the amount excreted in the urine.
The usual dietary intake of potassium is 50 to 100 mEq per day.
12.3Pharmacokinetics Each crystal of KCl is microencapsulated and allows for the controlled release of potassium and chloride ions over an eight to ten-hour period. Specific Populations Cirrhotics Based on published literature, the baseline corrected serum - concentrations of potassium measured over 3 hours after administration in cirrhotic subjects who received an oral potassium load rose to approximately twice that of normal subjects who received the same load.
🧬 Mechanism of Action ▾
12.1Mechanism of Action The potassium ion (K+) is the principal intracellular cation of most body tissues. Potassium ions participate in a number of essential physiological processes, including the maintenance of intracellular tonicity; the transmission of nerve impulses; the contraction of cardiac, skeletal, and smooth muscle; and the maintenance of normal renal function. The intracellular concentration of potassium is approximately 150 to 160 mEq per liter.
The normal adult plasma concentration is 3.5 to 5 mEq per liter. An active ion transport system maintains this gradient across the plasma membrane. Potassium is a normal dietary constituent and under steady-state conditions the amount of potassium absorbed from the gastrointestinal tract is equal to the amount excreted in the urine.
The usual dietary intake of potassium is 50 to 100 mEq per day.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Potassium chloride extended-release capsules, USP, 8 mEq and 10 mEq contain 600 mg and 750 mg of potassium chloride (equivalent to 8 mEq and 10 mEq, respectively). Table 1: How Supplied Dose Color Printing NDC#: 63304 -xxx-xx Bottle Count 100 500 600 mg (8 mEq) white to ivory 102 078-01 - 750 mg (10 mEq) light blue 103 090-01 090-05 Store at 20° to 25°C (68°-77°F); excursions are permitted to 15° to 30°C (59°-86°F) [see USP Controlled Room Temperature.] Dispense in tight, light-resistant container as defined in the USP, with a child-resistant closure.
Rx only
📋 Description ▾
11 DESCRIPTION Potassium chloride extended-release capsules, USP, are an oral dosage form of microencapsulated potassium chloride containing 600 mg and 750 mg of potassium chloride, USP, equivalent to 8 mEq and 10 mEq of potassium, respectively. The chemical name of the active ingredient is potassium chloride and the structural formula is KCl. It has a molecular mass of 74.55.
Potassium chloride, USP, occurs as a white granular powder or as colorless crystals. It is odorless and has a saline taste. Its solutions are neutral to litmus.
It is freely soluble in water and insoluble in alcohol. Inactive ingredients: ethylcellulose, gelatin, magnesium stearate, sodium lauryl sulfate, titanium dioxide and edible black ink. The 10 mEq capsules also contain black iron oxide, FD&C blue No.1 and FD&C red No.3.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Inform patients to take each dose with meals and with a full glass of water or other liquid. Advise patients to seek medical attention if tarry stools or other evidence of gastrointestinal toxicity is noticed. Manufactured By: Adare Pharmaceuticals, Inc. Vandalia, OH 45377 Distributed By: Sun Pharmaceutical Industries, Inc. Cranbury, NJ 08512 Iss. 10/2019