
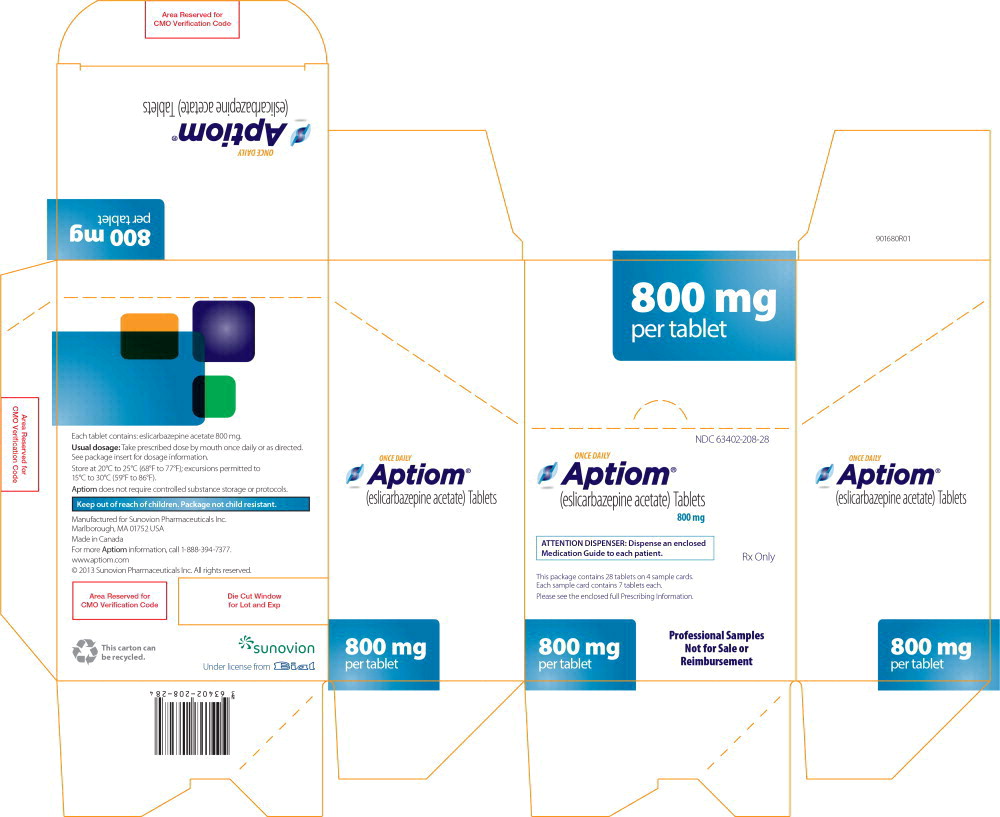
Aptiom ESLICARBAZEPINE ACETATE 800 mg Tablet, 28-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Carboxamide derivatives class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Eslicarbazepine is used in combination with other medications to control focal (partial) seizures (seizures that involve only one part of the brain). Eslicarbazepine is in a class of medications called anticonvulsants. It works by decreasing abnormal excitement in the brain.
Read the full MedlinePlus article ↗- Sure. Eslicarbazepine acetate (brand name Aptiom) is specifically approved to treat partial-onset seizures — that's when a seizure starts in just one area of the brain rather than...
- What exactly is this medicine for? My doctor said it's for seizures — can you tell me more?
- Good news — food doesn't affect how this medicine works, so you can take it with or without a meal, whichever is easier for you. It's taken just once a day, which most people find...
- Can I take this pill with food, or does it have to be on an empty stomach?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Eslicarbazepine Acetate — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $45.51 | $1,274.24 / 28 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Eslicarbazepine acetate 800 mg 31722-0431-30 | Camber | 30 tablets | $2.099 | AB | Availability likely | — |
| Eslicarbazepine Acetate 800 mg 43598-0687-30 | Dr.Reddys | 30 tablets | $2.099 | AB | Availability likely | — |
| Eslicarbazepine Acetate 800 mg 60505-4661-03 | Apotex | 30 tablets | $2.099 | AB | Availability likely | — |
| Eslicarbazepine Acetate 800 mg 67877-0588-30 | Ascend | 30 tablets | $2.099 | AB | Availability likely | — |
| Eslicarbazepine Acetate 800 mg 68180-0293-06 | Lupin | 30 tablets | $2.099 | AB | Availability likely | — |
| Eslicarbazepine acetate 800 mg 13668-0541-05 | Torrent | 500 tablets | — | AB | FDA listed | — |
| Eslicarbazepine Acetate 800 mg 51407-0782-30 | Golden | 30 tablets | — | AB | FDA listed | — |
| Eslicarbazepine Acetate 800 mg 59746-0720-05 | Jubilant | 500 tablets | — | AB | FDA listed | — |
| Aptiom 800 mgthis 63402-0208-28 | Sumitomo | 28 tablets | — | AB | FDA listed | — |
| Eslicarbazepine Acetate 800 mg 59651-0536-30 | Aurobindo | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9763954 ↗ | Method of use | U-2123 | Sep 13, 2028 |
| US 9763954 ↗ | Method of use | U-2123 | Sep 13, 2028 |
| US 9750747 ↗ | Method of use | U-2121 | Aug 24, 2032 |
| US 9750747 ↗ | Method of use | U-2121 | Aug 24, 2032 |
| US 9750747 ↗ | Method of use | U-2041 | Aug 24, 2032 |
| US 9750747 ↗ | Method of use | U-2041 | Aug 24, 2032 |
| US 9750747 ↗ | Method of use | U-2041 | Aug 24, 2032 |
| US 9750747 ↗ | Method of use | U-2041 | Aug 24, 2032 |
| US 9763954 ↗ | Method of use | U-2123 | Sep 13, 2028 |
| US 9750747 ↗ | Method of use | U-2121 | Aug 24, 2032 |
| US 9750747 ↗ | Method of use | U-2121 | Aug 24, 2032 |
| US 9763954 ↗ | Method of use | U-2123 | Sep 13, 2028 |
| US 9206135 ↗ | Drug substance | — | Apr 21, 2026 |
| US 9643929 ↗ | Drug product | — | Apr 21, 2026 |
| US 9566244 ↗ | Drug product | — | Oct 23, 2028 |
| US 9206135 ↗ | Drug substance | — | Apr 21, 2026 |
| US 10912781 ↗ | Drug product | — | Oct 23, 2028 |
| US 8372431 ↗ | Drug product | — | Apr 17, 2030 |
| US 10912781 ↗ | Drug product | — | Oct 23, 2028 |
| US 10912781 ↗ | Drug product | — | Oct 23, 2028 |
| US 10912781 ↗ | Drug product | — | Oct 23, 2028 |
| US 9566244 ↗ | Drug product | — | Oct 23, 2028 |
| US 8372431 ↗ | Drug product | — | Apr 17, 2030 |
| US 9643929 ↗ | Drug product | — | Apr 21, 2026 |
| US 9643929 ↗ | Drug product | — | Apr 21, 2026 |
| US 8372431 ↗ | Drug product | — | Apr 17, 2030 |
| US 9566244 ↗ | Drug product | — | Oct 23, 2028 |
| US 9206135 ↗ | Drug substance | — | Apr 21, 2026 |
| US 9566244 ↗ | Drug product | — | Oct 23, 2028 |
| US 9206135 ↗ | Drug substance | — | Apr 21, 2026 |
| US 9643929 ↗ | Drug product | — | Apr 21, 2026 |
| US 8372431 ↗ | Drug product | — | Apr 17, 2030 |
Is there a generic version of APTIOM 800 MG TABLET?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 63402-0208-28 You're viewing this | 4 BLISTER PACK in 1 CARTON (63402-208-28) / 7 TABLET in 1 BLISTER PACK (63402-208-07) | — | — | 2014-04-07 | Active |
| 63402-0208-30 | 30 TABLET in 1 BOTTLE (63402-208-30) | $44.19 / ea | $1,325.70 | 2014-04-07 | Active |
This pack shows little to no recent Medicaid volume — the 30 tablets pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 63402-0208-28?
What is the difference between NDC 63402-0208-28 and NDC 63402-0208-30?
What NDC number is used to bill for this package of Aptiom ESLICARBAZEPINE ACETATE 800 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE APTIOM is indicated for the treatment of partial-onset seizures in patients 4 years of age and older. APTIOM is indicated for the treatment of partial-onset seizures in patients 4 years of age and older. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Adult Patients: The recommended initial dosage of APTIOM is 400 mg once daily. For some patients, treatment may be initiated at 800 mg once daily if the need for seizure reduction outweighs an increased risk of adverse reactions. Increase the dose in weekly increments of 400 mg to 600 mg once daily, based on clinical response and tolerability, to a recommended maintenance dosage of 800 mg to 1600 mg once daily.
( 2.2 ) Pediatric Patients: The recommended dosage of APTIOM is based on body weight and is administered orally once daily. Increase the dose in weekly intervals based on clinical response and tolerability, to the recommended maintenance dosage. ( 2.2 ) Patients with Moderate or Severe Renal Impairment: Reduce dosage by 50%.
( 2.4 )
2.1Important Administration Instructions Instruct patients to administer APTIOM either as whole or as crushed tablets. Instruct patients to take APTIOM either with or without food. The APTIOM dosing regimen depends on age, weight, and renal function.
2.2General Dosing Recommendations Monotherapy and Adjunctive Therapy Adult Patients The recommended initial dosage of APTIOM is 400 mg administered orally once daily. For some patients, treatment may be initiated at 800 mg once daily if the need for seizure reduction outweighs an increased risk of adverse reactions during initiation [see Adverse Reactions ( 6.1 )] . Dosage should be increased in weekly increments of 400 mg to 600 mg, based on clinical response and tolerability, to a recommended maintenance dosage of 800 mg to 1600 mg once daily.
For patients on APTIOM monotherapy, the 800 mg once daily maintenance dose should generally be considered in patients who are unable to tolerate a 1200 mg daily dose. For patients on APTIOM adjunctive therapy, the 1600 mg daily dose should generally be considered in patients who did not achieve a satisfactory response with a 1200 mg daily dose. Pediatric Patients (4 to 17 Years of Age) In pediatric patients 4 to 17 years of age, the recommended dosing regimen is dependent upon body weight and is administered orally once daily.
The recommended initial dosage of APTIOM is shown in Table 1 . Dosage should be increased based on clinical response and tolerability, no more frequently than once per week. Titration increments should not exceed those shown in Table 1 .
The daily maintenance dosage should not exceed the maintenance dosage for each body weight range shown in Table 1 . Table 1: APTIOM Once Daily Dosage Schedule for Pediatric Patients 4 to 17 Years of Age Body Weight Range Initial and Maximum Titration Increment Dosage (mg/day) Maintenance Dosage (mg/day) 11 to 21 kg 200 400 to 600 22 to 31 kg 300 500 to 800 32 to 38 kg 300 600 to 900 more than 38 kg 400 800 to 1200
2.3Dosage Modifications with Other Antiepileptic Drugs Some adverse reactions occur more frequently when patients take APTIOM adjunctively with carbamazepine [see Warnings and Precautions ( 5.6 )] . However, carbamazepine reduces the plasma concentration of eslicarbazepine [see Drug Interactions ( 7.1 )] . When APTIOM and carbamazepine are taken concomitantly, the dose of APTIOM or carbamazepine may need to be adjusted based on efficacy and tolerability.
For patients taking other enzyme-inducing AEDs (i.e., phenobarbital, phenytoin, and primidone), higher doses of APTIOM may be needed [see Drug Interactions ( 7.1 )]. APTIOM should not be taken as an adjunctive therapy with oxcarbazepine.
2.4Dosage Modifications in Patients with Renal Impairment In patients with moderate and severe renal impairment (i.e., creatinine clearance < 50 mL/min), the initial, titration, and maintenance dosages should generally be reduced by 50%. Titration and maintenance dosages may be adjusted according to clinical response [see Use in Specific Populations ( 8.6 ) and Clinical Pharmacology ( 12.3 )].
2.5Patients with Hepatic Impairment Dose adjustments are not required in patients with mild to moderate hepatic impairment. Use of…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS APTIOM tablets are available in the following shapes and color ( Table 2 ) with respective one-sided engraving: Table 2: APTIOM Tablet Presentations Tablet Strength Tablet Color/Shape Tablet Markings Functional Score 200 mg White oblong ESL 200 Yes 400 mg White circular bi-convex ESL 400 No 600 mg White oblong ESL 600 Yes 800 mg White oblong ESL 800 Yes Tablets: 200 mg, 400 mg, 600 mg, 800 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS APTIOM is contraindicated in patients with a hypersensitivity to eslicarbazepine acetate or oxcarbazepine [see Warnings and Precautions ( 5.2 , 5.3 , and 5.4 )]. Hypersensitivity to eslicarbazepine acetate or oxcarbazepine. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Suicidal Behavior and Ideation: Monitor for suicidal thoughts or behavior. ( 5.1 ) Serious Dermatologic Reactions, Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS), Anaphylactic Reactions and Angioedema: Monitor and discontinue if another cause cannot be established. ( 5.2 , 5.3 , 5.4 ) Hyponatremia: Monitor sodium levels in patients at risk or patients experiencing hyponatremia symptoms.
( 5.5 ) Neurological Adverse Reactions: Monitor for dizziness, disturbance in gait and coordination, somnolence, fatigue, cognitive dysfunction, and visual changes. Use caution when driving or operating machinery. ( 5.6 ) Withdrawal of APTIOM: Withdraw APTIOM gradually to minimize the risk of increased seizure frequency and status epilepticus.
( 2.6 , 5.7 , 8.1 ) Drug Induced Liver Injury: Discontinue APTIOM in patients with jaundice or evidence of significant liver injury. ( 5.8 ) Hematologic Adverse Reactions: Consider discontinuing. ( 5.10 )
5.1Suicidal Behavior and Ideation Antiepileptic drugs (AEDs), including APTIOM, increase the risk of suicidal thoughts or behavior in patients taking these drugs for any indication. Patients treated with any AED for any indication should be monitored for the emergence or worsening of depression, suicidal thoughts or behavior, and/or any unusual changes in mood or behavior. Pooled analyses of 199 placebo-controlled clinical trials (mono- and adjunctive therapy) of 11 different AEDs showed that patients randomized to one of the AEDs had approximately twice the risk (adjusted Relative Risk 1.8, 95% confidence interval [CI]: 1.2, 2.7) of suicidal thinking or behavior compared to patients randomized to placebo.
In these trials, which had a median treatment duration of 12 weeks, the estimated incidence of suicidal behavior or ideation among 27,863 AED-treated patients was 0.43%, compared to 0.24% among 16,029 placebo-treated patients, representing an increase of approximately one case of suicidal thinking or behavior for every 530 patients treated. There were four suicides in drug-treated patients in the trials and none in placebo-treated patients, but the number of events is too small to allow any conclusion about drug effect on suicide.
The increased risk of suicidal thoughts or behavior with AEDs was observed as early as one week after starting treatment with AEDs and persisted for the duration of treatment assessed. Because most trials included in the analysis did not extend beyond 24 weeks, the risk of suicidal thoughts or behavior beyond 24 weeks could not be assessed. The risk of suicidal thoughts or behavior was generally consistent among drugs in the data analyzed.
The finding of increased risk with AEDs of varying mechanisms of action and across a range of indications suggests that the risk applies to all AEDs used for any indication. The risk did not vary substantially by age (5-100 years) in the clinical trials analyzed. Table 3 shows absolute and relative risk by indication for all evaluated AEDs.
Table 3: Risk of Suicidal Thoughts or Behaviors by Indication for Antiepileptic Drugs in the Pooled Analysis Indication Placebo Patients with Events Per 1000 Patients Drug Patients with Events Per 1000 Patients Relative Risk: Incidence of Events in Drug Patients/Incidence in Placebo Patients Risk Differences: Additional Drug Patients with Events Per 1000 Patients Epilepsy 1.0 3.4 3.5
2.4Psychiatric 5.7 8.5 1.5
2.9Other 1.0 1.8 1.9
0.9Total 2.4 4.3 1.8
1.9The relative risk for suicidal thoughts or behavior was higher in clinical trials in patients with epilepsy than in clinical trials in patients with psychiatric or other conditions, but the absolute risk differences were similar for epilepsy and psychiatric indications. Anyone considering prescribing APTIOM or any other AED must balance this risk with the risk of untreated illness. Epilepsy and many other illnesses for which AEDs are prescribed are themselves associated with morbidity and mortality and an in…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are described in more detail in the Warnings and Precautions section of the label: Suicidal Behavior and Ideation [see Warnings and Precautions ( 5.1 )] Serious Dermatologic Reactions [see Warnings and Precautions ( 5.2 )] Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multiorgan Hypersensitivity [see Warnings and Precautions ( 5.3 )] Anaphylactic Reactions and Angioedema [see Warnings and Precautions ( 5.4 )] Hyponatremia [see Warnings and Precautions ( 5.5 )] Neurological Adverse Reactions [see Warnings and Precautions ( 5.6 )] Drug Induced Liver Injury [see Warnings and Precautions ( 5.8 )] Abnormal Thyroid Function Tests [see Warnings and Precautions ( 5.9 )] Pancytopenia, Agranulocytosis, and Leukopenia [see Warnings and Precautions ( 5.10 )] Most common adverse reactions in adult patients receiving APTIOM (≥4% and ≥2% greater than placebo): dizziness, somnolence, nausea, headache, diplopia, vomiting, fatigue, vertigo, ataxia, blurred vision, and tremor.
( 6.1 ) Adverse reactions in pediatric patients are similar to those seen in adult patients. To report SUSPECTED ADVERSE REACTIONS, contact Sumitomo Pharma America, Inc. at 1-877-737-7226 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adult Patients In monotherapy trials in patients with partial-onset seizures [Study 1 and Study 2, see Clinical Studies ( 14.1 ) ] , 365 patients received APTIOM, of whom 225 were treated for longer than 12 months and 134 for longer than 24 months.
Of the patients in those trials, 95% were between 18 and 65 years old; 48% were male, and 84% were Caucasian. Across controlled and uncontrolled trials in patients receiving adjunctive therapy for partial-onset seizures, 1195 patients received APTIOM, of whom 586 were treated for longer than 6 months and 462 for longer than 12 months. In the placebo controlled adjunctive therapy trials in patients with partial-onset seizures (Study 3, Study 4 and Study 5), 1021 patients received APTIOM.
Of the patients in those trials, approximately 95% were between 18 and 60 years old, approximately 50% were male, and approximately 80% were Caucasian. Monotherapy Historical Control Trials In the monotherapy epilepsy trials (Study 1 and Study 2), 13% of patients randomized to receive APTIOM at the recommended doses of 1200 mg and 1600 mg once daily discontinued from the trials as a result of an adverse event. The adverse reaction most commonly (≥1% on APTIOM) leading to discontinuation was hyponatremia.
Adverse reactions observed in these studies were generally similar to those observed and attributed to drug in adjunctive placebo-controlled studies. Because these studies did not include a placebo control group, causality could not be established. Dizziness, nausea, somnolence, and fatigue were all reported at lower incidences during the AED Withdrawal Phase and Monotherapy Phase compared with the Titration Phase.
Adjunctive Therapy Controlled Trials In the controlled adjunctive therapy epilepsy trials (Study 3, Study 4, and Study 5) , the rate of discontinuation as a result of any adverse reaction was 14% for the 800 mg dose, 25% for the 1200 mg dose, and 7% in subjects randomized to placebo. The adverse reactions most commonly (≥1% in any APTIOM treatment group, and greater than placebo) leading to discontinuation, in descending order of frequency, were dizziness, nausea, vomiting, ataxia, diplopia, somnolence, headache, blurred vision, vertigo, asthenia, fatigue, rash, dysarthria, and tremor.
The most frequently reported adverse reactions in patients receiving APTIOM at doses of 800 mg or 1200 mg (≥4% and ≥2% greater than placebo) were dizziness, somno…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Carbamazepine: May need dose adjustment for APTIOM or carbamazepine. ( 2.3 , 5.6 , 7.1 ) Phenytoin: Higher dosage of APTIOM may be necessary and dose adjustment may be needed for phenytoin. ( 2.3 , 7.1 , 7.2 ) Phenobarbital or Primidone: Higher dosage of APTIOM may be necessary. ( 2.3 , 7.1 ) Hormonal Contraceptives: APTIOM may decrease the effectiveness of hormonal contraceptives. ( 7.4 , 8.3 )
7.1Other Antiepileptic Drugs Several AEDs (e.g., carbamazepine, phenobarbital, phenytoin, and primidone) can induce enzymes that metabolize APTIOM and can cause decreased plasma concentrations of eslicarbazepine [see Clinical Pharmacology ( 12.3 )]. Higher doses of Aptiom may be needed [see Dosage and Administration ( 2.4 )].
7.2CYP2C19 Substrates APTIOM can inhibit CYP2C19, which can cause increased plasma concentrations of drugs that are metabolized by this isoenzyme (e.g., phenytoin, clobazam, and omeprazole) [see Clinical Pharmacology ( 12.3 )]. Dose adjustment may be needed.
7.3CYP3A4 Substrates In vivo studies suggest that APTIOM can induce CYP3A4, decreasing plasma concentrations of drugs that are metabolized by this isoenzyme (e.g., simvastatin, lovastatin) [see Clinical Pharmacology ( 12.3 )]. Dose adjustment of simvastatin and lovastatin may be needed if a clinically significant change in lipids is noted.
7.4Oral Contraceptives Because concomitant use of APTIOM and ethinylestradiol and levonorgestrel is associated with lower plasma levels of these hormones, females of reproductive potential should use additional or alternative non-hormonal birth control.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause fetal harm. ( 8.1 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to AEDs, such as APTIOM, during pregnancy. Encourage women who are taking APTIOM during pregnancy to enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry by calling 1-888-233-2334 or visiting http://www.aedpregnancyregistry.org. Risk Summary Limited available data with APTIOM use in pregnant women are insufficient to inform a drug-associated risk of adverse developmental outcomes.
In oral studies conducted in pregnant mice, rats, and rabbits, eslicarbazepine acetate demonstrated developmental toxicity, including increased incidence of malformations (mice), embryolethality (rats), and fetal growth retardation (all species), at clinically relevant doses (see Data). Advise a pregnant woman of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
The background risk of major birth defects and miscarriage for the indicated population is unknown. Data Animal Data When eslicarbazepine acetate was orally administered (150, 350, 650 mg/kg/day) to pregnant mice throughout organogenesis, increased incidences of fetal malformations was observed at all doses and fetal growth retardation was observed at the mid and high doses. A no-effect dose for adverse developmental effects was not identified.
At the lowest dose tested, plasma eslicarbazepine exposure (C max , AUC) is less than that in humans at the maximum recommended human dose (MRHD, 1600 mg/day). Oral administration of eslicarbazepine acetate (40, 160, 320 mg/kg/day) to pregnant rabbits throughout organogenesis resulted in fetal growth retardation and increased incidences of skeletal variations at the mid and high doses. The no-effect dose (40 mg/kg/day) is less than the MRHD on a mg/m 2 basis.
Oral administration to pregnant rats (65, 125, 250 mg/kg/day) throughout organogenesis resulted in embryolethality at all doses, increased incidences of skeletal variations at the mid and high doses, and fetal growth retardation at the high dose. The lowest dose tested (65 mg/kg/day) is less than the MRHD on a mg/m 2 basis. When eslicarbazepine acetate was orally administered to female mice during pregnancy and lactation (150, 350, 650 mg/kg/day), the gestation period was prolonged at the highest dose tested.
In offspring, a persistent reduction in offspring body weight and delayed physical development and sexual maturation were observed at the mid and high doses. The lowest dose tested (150 mg/kg/day) is less than the MRHD on a mg/m 2 basis. When eslicarbazepine acetate was orally administered (65, 125, 250 mg/kg/day) to rats during pregnancy and lactation, reduced offspring body weight was seen at the mid and high doses.
Delayed sexual maturation and a neurological deficit (decreased motor coordination) were observed at the highest dose tested. The no-effect dose for adverse developmental effects (65 mg/kg/day) is less than the MRHD on a mg/m 2 basis. The rat data are of uncertain relevance to humans because of differences in metabolic profile between species.
8.2Lactation Eslicarbazepine is present in human milk. The effects of APTIOM on the breastfed infant or on milk production are unknown. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for APTIOM and any potential adverse effects on the breastfed infant from APTIOM or from the underlying maternal condition.
8.3Females and Males of Reproductive Potential Contraception Use of APTIOM with hormonal contraceptives containing ethinylestradiol or levonorgestrel is associated with lower plasma levels of these hormones. Advise women of reproductive potential taking APTIOM who are using a con…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to AEDs, such as APTIOM, during pregnancy. Encourage women who are taking APTIOM during pregnancy to enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry by calling 1-888-233-2334 or visiting http://www.aedpregnancyregistry.org. Risk Summary Limited available data with APTIOM use in pregnant women are insufficient to inform a drug-associated risk of adverse developmental outcomes.
In oral studies conducted in pregnant mice, rats, and rabbits, eslicarbazepine acetate demonstrated developmental toxicity, including increased incidence of malformations (mice), embryolethality (rats), and fetal growth retardation (all species), at clinically relevant doses (see Data). Advise a pregnant woman of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
The background risk of major birth defects and miscarriage for the indicated population is unknown. Data Animal Data When eslicarbazepine acetate was orally administered (150, 350, 650 mg/kg/day) to pregnant mice throughout organogenesis, increased incidences of fetal malformations was observed at all doses and fetal growth retardation was observed at the mid and high doses. A no-effect dose for adverse developmental effects was not identified.
At the lowest dose tested, plasma eslicarbazepine exposure (C max , AUC) is less than that in humans at the maximum recommended human dose (MRHD, 1600 mg/day). Oral administration of eslicarbazepine acetate (40, 160, 320 mg/kg/day) to pregnant rabbits throughout organogenesis resulted in fetal growth retardation and increased incidences of skeletal variations at the mid and high doses. The no-effect dose (40 mg/kg/day) is less than the MRHD on a mg/m 2 basis.
Oral administration to pregnant rats (65, 125, 250 mg/kg/day) throughout organogenesis resulted in embryolethality at all doses, increased incidences of skeletal variations at the mid and high doses, and fetal growth retardation at the high dose. The lowest dose tested (65 mg/kg/day) is less than the MRHD on a mg/m 2 basis. When eslicarbazepine acetate was orally administered to female mice during pregnancy and lactation (150, 350, 650 mg/kg/day), the gestation period was prolonged at the highest dose tested.
In offspring, a persistent reduction in offspring body weight and delayed physical development and sexual maturation were observed at the mid and high doses. The lowest dose tested (150 mg/kg/day) is less than the MRHD on a mg/m 2 basis. When eslicarbazepine acetate was orally administered (65, 125, 250 mg/kg/day) to rats during pregnancy and lactation, reduced offspring body weight was seen at the mid and high doses.
Delayed sexual maturation and a neurological deficit (decreased motor coordination) were observed at the highest dose tested. The no-effect dose for adverse developmental effects (65 mg/kg/day) is less than the MRHD on a mg/m 2 basis. The rat data are of uncertain relevance to humans because of differences in metabolic profile between species.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of APTIOM have been established in the age groups 4 to 17 years. Use of APTIOM in these age groups is supported by evidence from adequate and well-controlled studies of APTIOM in adults with partial-onset seizures, pharmacokinetic data from adult and pediatric patients, and safety data from clinical studies in 393 pediatric patients 4 to 17 years of age [see Adverse Reactions ( 6.1 ) and Clinical Pharmacology ( 12.3 )] . Safety and effectiveness in pediatric patients below the age of 4 years have not been established.
Animal Data In a juvenile animal study in which eslicarbazepine acetate (40, 80, 160 mg/kg/day) was orally administered to young dogs for 10 months starting on postnatal day 21, adverse effects on bone growth (decreased bone mineral content and density) were seen in females at all doses at the end of the dosing period, but not at the end of a 2-month recovery period. Convulsions were seen at the highest dose tested. A no-effect dose for adverse effects in juvenile dogs was not identified.
The lowest dose tested is less than the maximum recommended pediatric dose (1200 mg/day) on a body surface area (mg/m 2 ) basis. A separate juvenile animal study was conducted to assess possible adverse effects on the immune system. Eslicarbazepine acetate (10, 40, 80 mg/kg/day) was orally administered to young dogs for 17 weeks starting on postnatal day 21.
No effects on the immune system were observed.
🧓 Geriatric Use ▾
8.5Geriatric Use There were insufficient numbers of patients ≥65 years old enrolled in the controlled adjunctive epilepsy trials (N=15) to determine the efficacy of APTIOM in this patient population. The pharmacokinetics of APTIOM were evaluated in elderly healthy subjects (N=12) ( Figure 1 ). Although the pharmacokinetics of eslicarbazepine are not affected by age independently, dose selection should take in consideration the greater frequency of renal impairment and other concomitant medical conditions and drug therapies in the elderly patient.
Dose adjustment is necessary if CrCl is <50 mL/min [see Clinical Pharmacology ( 12.3 )].
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Signs, Symptoms, and Laboratory Findings of Acute Overdose in Humans Symptoms of overdose are consistent with the known adverse reactions of APTIOM and include hyponatremia (sometimes severe), dizziness, nausea, vomiting, somnolence, euphoria, oral paraesthesia, ataxia, walking difficulties, and diplopia. The maximum dosage studied in open-label adult monotherapy treatment following withdrawal of concomitant AEDs was 2400 mg once daily.
10.2Treatment or Management of Overdose There is no specific antidote for overdose with APTIOM. Symptomatic and supportive treatment should be administered as appropriate. Removal of the drug by gastric lavage and/or inactivation by administering activated charcoal should be considered.
Standard hemodialysis procedures result in partial clearance of APTIOM. Hemodialysis may be considered based on the patient's clinical state or in patients with significant renal impairment.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action APTIOM is extensively converted to eslicarbazepine, which is considered to be responsible for therapeutic effects in humans. The precise mechanism(s) by which eslicarbazepine exerts anticonvulsant activity is unknown but is thought to involve inhibition of voltage-gated sodium channels.
12.2Pharmacodynamics The effect of APTIOM on cardiac repolarization was evaluated in a randomized, double-blind, placebo- and active-controlled 4-period crossover trial in healthy adult men and women. Subjects received APTIOM 1200 mg once daily × 5 days, APTIOM 2400 mg once daily × 5 days, an active-control, moxifloxacin 400 mg × 1 dose on Day 5, and placebo once daily × 5 days. At both doses of APTIOM, no significant effect on the QTc interval was detected.
12.3Pharmacokinetics The pharmacokinetics of eslicarbazepine is linear and dose-proportional in the dose range of 400 mg to 1600 mg once daily, both in healthy adult subjects and patients. The apparent half-life of eslicarbazepine in plasma was 13-20 hours in adult epilepsy patients. Steady-state plasma concentrations are attained after 4 to 5 days of once daily dosing.
Absorption, Distribution, Metabolism, and Excretion Absorption APTIOM is mostly undetectable (0.01% of the systemic exposure) after oral administration. Eslicarbazepine, the major metabolite, is primarily responsible for the pharmacological effect of APTIOM. Peak plasma concentrations (Cmax) of eslicarbazepine are attained at 1-4 hours post-dose.
Eslicarbazepine is highly bioavailable, because the amount of eslicarbazepine and glucuronide metabolites recovered in urine corresponded to more than 90% of an APTIOM dose. Food has no effect on the pharmacokinetics of eslicarbazepine after oral administration of APTIOM. Distribution The binding of eslicarbazepine to plasma proteins is relatively low (<40%) and independent of concentration.
In vitro studies have shown that plasma protein binding was not relevantly affected by the presence of warfarin, diazepam, digoxin, phenytoin, or tolbutamide. Similarly, the binding of warfarin, diazepam, digoxin, phenytoin or tolbutamide was not significantly affected by the presence of eslicarbazepine. The apparent volume of distribution of eslicarbazepine is 61 L for body weight of 70 kg based on population PK analysis.
Metabolism APTIOM is rapidly and extensively metabolized to its major active metabolite eslicarbazepine by hydrolytic first-pass metabolism. Eslicarbazepine corresponds to 91% of systemic exposure. The systemic exposure to minor active metabolites of (R)-licarbazepine is 5% and oxcarbazepine is 1%.
The inactive glucuronides of these active metabolites correspond to approximately 3% of systemic exposure. In i n vitro studies in human liver microsomes, eslicarbazepine had no clinically relevant inhibitory effect on the activity of CYP1A2, CYP2A6, CYP2B6, CYP2D6, CYP2E1, and CYP3A4, and only a moderate inhibitory effect on CYP2C19. Studies with eslicarbazepine in fresh human hepatocytes showed no induction of enzymes involved in glucuronidation and sulfation of 7-hydroxy-coumarin.
A mild activation of UGT1A1-mediated glucuronidation was observed in human hepatic microsomes. No apparent autoinduction of metabolism has been observed with APTIOM in humans. Excretion APTIOM metabolites are eliminated from the systemic circulation primarily by renal excretion, in the unchanged and glucuronide conjugate forms.
In total, eslicarbazepine and its glucuronide account for more than 90% of total metabolites excreted in urine, approximately two thirds in the unchanged form and one third as glucuronide conjugate. Other minor metabolites account for the remaining 10% excreted in the urine. In healthy subjects with normal renal function, the renal clearance of eslicarbazepine (approximately 20 mL/min) is substantially lower than glomerular filtration rate (80-120 mL/min), suggesting that renal tubular reabsorption occurs.
The apparent plasma ha…
🧬 Mechanism of Action ▾
12.1Mechanism of Action APTIOM is extensively converted to eslicarbazepine, which is considered to be responsible for therapeutic effects in humans. The precise mechanism(s) by which eslicarbazepine exerts anticonvulsant activity is unknown but is thought to involve inhibition of voltage-gated sodium channels.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied APTIOM tablets are white, oblong and with functional scoring on one side (200 mg, 600 mg, and 800 mg) or white, circular bi-convex and plain on one side (400 mg) and identified with strength-specific one-sided engraving on the other side, “ESL 200” (200 mg), “ESL 400” (400 mg), “ESL 600” (600 mg), or “ESL 800” (800 mg). Tablets are supplied in the following strengths and package configurations ( Table 6 ): Table 6: Package Configuration for APTIOM Tablets Tablet Strength Package Configuration NDC Code 200 mg Bottles of 30 63402-202-30 400 mg Bottles of 30 63402-204-30 600 mg Bottles of 60 63402-206-60 800 mg Bottles of 30 63402-208-30
16.2Storage and Handling Store APTIOM tablets at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
16.1How Supplied APTIOM tablets are white, oblong and with functional scoring on one side (200 mg, 600 mg, and 800 mg) or white, circular bi-convex and plain on one side (400 mg) and identified with strength-specific one-sided engraving on the other side, “ESL 200” (200 mg), “ESL 400” (400 mg), “ESL 600” (600 mg), or “ESL 800” (800 mg). Tablets are supplied in the following strengths and package configurations ( Table 6 ): Table 6: Package Configuration for APTIOM Tablets Tablet Strength Package Configuration NDC Code 200 mg Bottles of 30 63402-202-30 400 mg Bottles of 30 63402-204-30 600 mg Bottles of 60 63402-206-60 800 mg Bottles of 30 63402-208-30
📦 Storage and Handling ▾
16.2Storage and Handling Store APTIOM tablets at 20°C to 25°C (68°F to 77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION The chemical name of APTIOM (eslicarbazepine acetate) is (S)-10-Acetoxy-10,11-dihydro-5H-dibenz[b,f]azepine-5-carboxamide. APTIOM is a dibenz[b,f]azepine-5-carboxamide derivative. Its molecular formula is C 17 H 16 N 2 O 3 and its molecular weight is 296.32.
The chemical structure is: APTIOM is a white to off-white, odorless crystalline solid. It is insoluble in hexane, very slightly soluble in aqueous solvents and soluble in organic solvents such as acetone, acetonitrile, and methanol. Each APTIOM tablet contains 200 mg, 400 mg, 600 mg or 800 mg of eslicarbazepine acetate and the following inactive ingredients: croscarmellose sodium, magnesium stearate, and povidone.
Chemical structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-approved patient labeling (Medication Guide). Inform patients and caregivers of the availability of a Medication Guide, and instruct them to read the Medication Guide prior to taking APTIOM. Instruct patients and caregivers that APTIOM should only be taken as prescribed.
Suicidal Behavior and Ideation Counsel patients, their caregivers, and families that AEDs, including APTIOM, may increase the risk of suicidal thoughts and behavior and advise them of the need to be alert for the emergence or worsening of symptoms of depression, any unusual changes in mood or behavior, or the emergence of suicidal thoughts, behavior, or thoughts about self-harm. Instruct patients, caregivers, and families to report behaviors of concern immediately to healthcare providers [see Warnings and Precautions ( 5.1 )].
Serious Dermatologic Reactions Advise patients and caregivers about the risk of potentially fatal serious skin reactions. Educate patients and caregivers about the signs and symptoms that may signal a serious skin reaction. Instruct patients and caregivers to consult with their healthcare provider immediately if a skin reaction occurs during treatment with APTIOM [see Warnings and Precautions ( 5.2 )].
DRESS/Multi-organ Hypersensitivity Instruct patients and caregivers that a fever associated with signs of other organ system involvement (e.g., rash, lymphadenopathy, hepatic dysfunction) may be drug-related and should be reported to their healthcare provider immediately [see Warnings and Precautions ( 5.3 )]. Anaphylactic Reactions and Angioedema Advise patients and caregivers of life threatening symptoms suggesting anaphylaxis or angioedema (swelling of the face, eyes, lips, tongue, or difficulty in swallowing or breathing) that can occur with APTIOM.
Instruct them to immediately report these symptoms to their healthcare provider [see Warnings and Precautions ( 5.4 )]. Hyponatremia Advise patients and caregivers that APTIOM may reduce serum sodium concentrations, especially if they are taking other medications that can lower sodium. Advise patients and caregivers to report symptoms of low sodium such as nausea, tiredness, lack of energy, irritability, confusion, muscle weakness/spasms, or more frequent or more severe seizures [see Warnings and Precautions ( 5.5 )].
Neurological Adverse Reactions Counsel patients and caregivers that APTIOM may cause dizziness, gait disturbance, somnolence/fatigue, cognitive dysfunction, and visual changes. These adverse reactions, if observed, are more likely to occur during the titration period compared to the maintenance period. Advise patients not to drive or operate machinery until they have gained sufficient experience on APTIOM to gauge whether it adversely affects their ability to drive or operate machinery [see Warnings and Precautions ( 5.6 )].
Withdrawal of APTIOM Advise patients and caregivers not to discontinue use of APTIOM without consulting with their healthcare provider. APTIOM should be gradually withdrawn to minimize the potential of increased seizure frequency and status epilepticus [see Warnings and Precautions ( 5.7 )]. Hematologic Adverse Reactions Advise patients and caregivers that there have been rare reports of blood disorders reported in patients treated with APTIOM.
Instruct patients to immediately consult with their physician if they experience symptoms suggestive of blood disorders [see Warnings and Precautions ( 5.10 )]. Interaction with Oral Contraceptives Inform patients and caregivers that APTIOM can significantly decrease the effectiveness of hormonal contraceptives. Recommend that female patients of childbearing potential use additional or alternative non-hormonal forms of contraception during treatment with APTIOM and after treatment has been discontinued for at least one menstrual cycle or until otherwise instructed by their healthcare provider [see Drug Interactions ( 7.3 , 7.4 )].
Pregnancy Registry Encourage patients to enr…
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised 9/2017 MEDICATION GUIDE APTIOM (ap tee' om) (eslicarbazepine acetate) tablets What is the most important information I should know about APTIOM?
Do not stop taking APTIOM without first talking to your healthcare provider. Stopping APTIOM suddenly can cause serious problems. Stopping a seizure medicine suddenly in a patient who has epilepsy may cause seizures that will not stop (status epilepticus).
1. Like other antiepileptic drugs, APTIOM may cause suicidal thoughts or actions in a very small number of people, about 1 in 500. Call a healthcare provider right away if you have any of these symptoms, especially if they are new, worse, or worry you: thoughts about suicide or dying new or worse depression feeling agitated or restless trouble sleeping (insomnia) acting aggressive, being angry, or violent an extreme increase in activity and talking (mania) attempt to commit suicide new or worse anxiety panic attacks new or worse irritability acting on dangerous impulses other unusual changes in behavior or mood How can I watch for early symptoms of suicidal thoughts and actions?
Pay attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings. Keep all follow-up visits with your healthcare provider as scheduled. Call your healthcare provider between visits as needed, especially if you are worried about symptoms.
Suicidal thoughts or actions may be caused by things other than medicines. If you have suicidal thoughts or actions, your healthcare provider may check for other causes. 2.
APTIOM may cause allergic reactions or serious problems which may affect organs and other parts of your body like the liver or blood cells. You may or may not have a rash with these types of reactions. Call your healthcare provider right away if you have any of the following: swelling of your face, eyes, lips, or tongue a skin rash fever, swollen glands, or sore throat that do not go away or come and go yellowing of your skin or eyes severe fatigue or weakness frequent infections or infections that do not go away trouble swallowing or breathing hives painful sores in the mouth or around your eyes unusual bruising or bleeding severe muscle pain APTIOM may cause the level of sodium in your blood to be low.
Symptoms of low blood sodium include: nausea irritability muscle weakness or muscle spasms tiredness, lack of energy confusion more frequent or more severe seizures Some medicines can also cause low sodium in your blood. Be sure to tell your healthcare provider about all the other medicines that you are taking. What is APTIOM?
APTIOM is a prescription medicine used to treat partial-onset seizures. It is not known if APTIOM is safe and effective in children under 4 years of age. Who should not take APTIOM?
Do not take APTIOM if you are allergic to eslicarbazepine acetate, any of the other ingredients in APTIOM, or oxcarbazepine. See the end of this Medication Guide for a complete list of ingredients in APTIOM. What should I tell my healthcare provider before taking APTIOM?
Before taking APTIOM, tell your healthcare provider about all your medical conditions, including if you: have or have had suicidal thoughts or actions, depression or mood problems have liver, kidney, or blood problems are allergic to oxcarbazepine. Some people who are allergic to oxcarbazepine may also be allergic to APTIOM. use birth control medicine. APTIOM may cause your birth control medicine to be less effective.
Talk to your healthcare provider about the best birth control method to use. are pregnant or plan to become pregnant. APTIOM may harm your unborn baby. Tell your healthcare provider right away if you become pregnant while taking APTIOM.
You and your healthcare provider will decide if you should take APTIOM while you are pregnant. If you become pregnant while taking APTIOM, talk to your healthcare provider about registering with the North American Antie…