
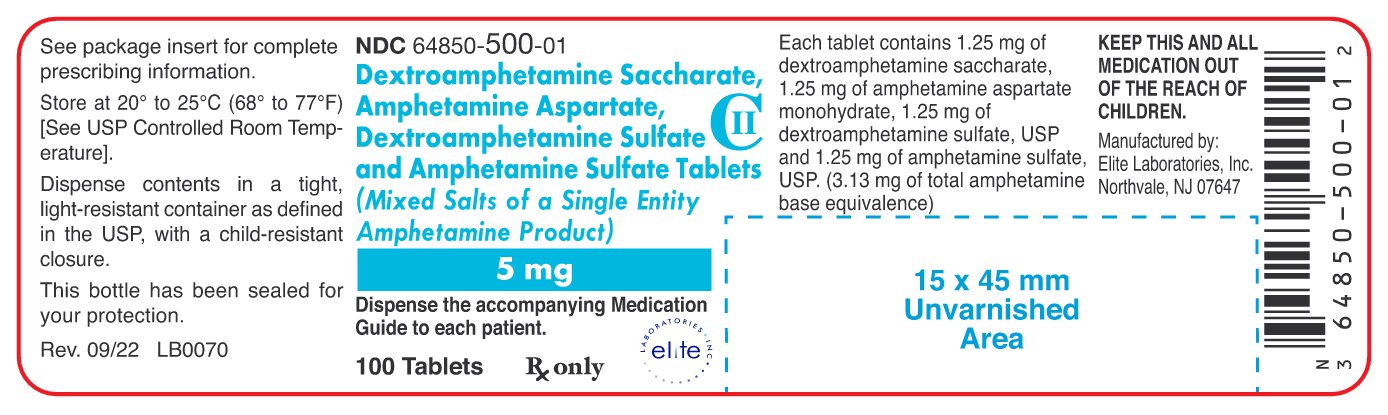
Dextroamphetamine Saccharate, Amphetamine Aspartate, Dextroamphetamine Sulfate and 1.25 mg; 1.25 mg; 1.25 mg; 1.25 mg Tablet, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Central Nervous System Stimulant class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
The combination of dextroamphetamine and amphetamine (Adderall®, Adderall® XR, Mydayis®) is used as part of a treatment program to control symptoms of attention deficit hyperactivity disorder (ADHD; more difficulty focusing, controlling actions, and remaining still or quiet than other people who are the same age). Adderall® is used to treat ADHD in adults and children 3 years of age and older. Adderall® XR is used to treat ADHD in adults and children 6 years of age and older. Mydayis® is used to treat ADHD in adults and children 13 years of age and older. Dextroamphetamine and amphetamine (Add...
Read the full MedlinePlus article ↗- It helps your brain maintain higher levels of two key signaling chemicals — dopamine and norepinephrine. In people with ADHD, those chemical signals can be inconsistent, making it...
- What exactly is this medication supposed to do for ADHD?
- The most common ones, especially at first, are reduced appetite, trouble falling asleep, and sometimes a stomachache or headache. These often improve after your body adjusts to the...
- What side effects should I actually expect when I first start taking it?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 7CVR7L4A2D
A starch-derived carbohydrate produced by breaking down corn, potato, or tapioca starch. It functions as a filler and binder to give the medicine bulk and texture, and sometimes as a mild sweetener or texture enhancer in powders and tablets.
-
UNII SB8ZUX40TY
Saccharin sodium is an artificial sweetener made from saccharin salt. It's added to medicines to improve taste, especially in liquid formulations for children or bitter drugs.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.264 | $26.40 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.4497 | $44.97 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.5376 | $53.76 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 64850-0500-01 You're viewing this | 100 TABLET in 1 BOTTLE (64850-500-01) | $0.2640 / ea | $26.40 | 2022-12-29 | Active |
| 64850-0500-05 | 500 TABLET in 1 BOTTLE (64850-500-05) | — | — | 2022-12-29 | Active |
| 64850-0500-30 | 30 TABLET in 1 BOTTLE (64850-500-30) | — | — | 2022-12-29 | Active |
You're viewing one of 3 pack sizes for this product.
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 64850-0500-01?
What is the difference between NDC 64850-0500-01 and NDC 64850-0500-30?
What NDC number is used to bill for this package of Dextroamphetamine Saccharate, Amphetamine Aspartate, Dextroamphetamine Sulfate and 1.25 mg; 1.25 mg; 1.25 mg; 1.25 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: ABUSE, MISUSE, AND ADDICTION Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets has a high potential for abuse and misuse, which can lead to the development of a substance use disorder, including addiction. Misuse and abuse of CNS stimulants, including dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets, can result in overdose and death (see OVERDOSAGE ), and this risk is increased with higher doses or unapproved methods of administration, such as snorting or injection.
Before prescribing dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets, assess each patient’s risk for abuse, misuse, and addiction. Educate patients and their families about these risks, proper storage of the drug, and proper disposal of any unused drug. Throughout dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets treatment, reassess each patient’s risk of abuse, misuse, and addiction and frequently monitor for signs and symptoms of abuse, misuse and addiction (see WARNINGS and DRUG ABUSE AND DEPENDENCE ).
🎯 Indications and Usage ▾
INDICATIONS & USAGE Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets is indicated for the treatment of Attention Deficit Hyperactivity Disorder (ADHD) and Narcolepsy. Attention Deficit Hyperactivity Disorder (ADHD) A diagnosis of Attention Deficit Hyperactivity Disorder (ADHD; DSM-IV ® ) implies the presence of hyperactive-impulsive or inattentive symptoms that caused impairment and were present before age 7 years. The symptoms must cause clinically significant impairment, e.g., in social, academic, or occupational functioning, and be present in two or more settings, e.g., school (or work) and at home.
The symptoms must not be better accounted for by another mental disorder. For the Inattentive Type, at least six of the following symptoms must have persisted for at least 6 months: lack of attention to details/careless mistakes; lack of sustained attention; poor listener; failure to follow through on tasks; poor organization; avoids tasks requiring sustained mental effort; loses things; easily distracted; forgetful. For the Hyperactive-Impulsive Type, at least six of the following symptoms must have persisted for at least 6 months: fidgeting/squirming; leaving seat; inappropriate running/climbing; difficulty with quiet activities; “on the go;” excessive talking; blurting answers; can't wait turn; intrusive.
The Combined Type requires both inattentive and hyperactive-impulsive criteria to be met.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Regardless of indication, amphetamines should be administered at the lowest effective dosage, and dosage should be individually adjusted according to the therapeutic needs and response of the patient. Late evening doses should be avoided because of the resulting insomnia. Attention Deficit Hyperactivity Disorder Not recommended for children under 3 years of age.
In children from 3 to 5 years of age, start with 2.5 mg daily; daily dosage may be raised in increments of 2.5 mg at weekly intervals until optimal response is obtained. In children 6 years of age and older, start with 5 mg once or twice daily; daily dosage may be raised in increments of 5 mg at weekly intervals until optimal response is obtained. Only in rare cases will it be necessary to exceed a total of 40 mg per day.
Give first dose on awakening; additional doses (1 or 2) at intervals of 4 to 6 hours. Where possible, drug administration should be interrupted occasionally to determine if there is a recurrence of behavioral symptoms sufficient to require continued therapy. Prior to treating patients with dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets assess: for the presence of cardiac disease (i.e., perform a careful history, family history of sudden death or ventricular arrhythmia, and physical exam [see WARNINGS ]. the family history and clinically evaluate patients for motor or verbal tics or Tourette’s syndrome before initiating dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets [see WARNINGS ].
Narcolepsy Usual dose 5 mg to 60 mg per day in divided doses, depending on the individual patient response. Narcolepsy seldom occurs in children under 12 years of age; however, when it does, dextroamphetamine sulfate may be used. The suggested initial dose for patients aged 6 to 12 is 5 mg daily; daily dose may be raised in increments of 5 mg at weekly intervals until optimal response is obtained.
In patients 12 years of age and older, start with 10 mg daily; daily dosage may be raised in increments of 10 mg at weekly intervals until optimal response is obtained. If bothersome adverse reactions appear (e.g., insomnia or anorexia), dosage should be reduced. Give first dose on awakening; additional doses (1 or 2) at intervals of 4 to 6 hours.
⛔ Contraindications ▾
CONTRAINDICATIONS In patients known to be hypersensitive to amphetamine, or other components of dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets. Hypersensitivity reactions such as angioedema and anaphylactic reactions have been reported in patients treated with other amphetamine products [see ADVERSE REACTIONS ]. Patients taking monoamine oxidase inhibitors (MAOIs), or within 14 days of stopping MAOIs (including MAOIs such as linezolid or intravenous methylene blue), because of an increased risk of hypertensive crisis [see WARNINGS and DRUG INTERACTIONS ].
Patients with pheochromocytoma or a history of pheochromocytoma. Serious reactions, including elevated blood pressure and tachyarrhythmia, have been reported in patients with pheochromocytoma or a history of pheochromocytoma who received an amphetamine product.
⚠️ Warnings ▾
WARNINGS Abuse, Misuse and Addiction Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets has a high potential for abuse and misuse. The use of dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets exposes individuals to the risks of abuse and misuse, which can lead to the development of a substance use disorder, including addiction. Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets can be diverted for non-medical use into illicit channels or distribution [see DRUG ABUSE and DEPENDENCE : Abuse].
Misuse and abuse of CNS stimulants, including dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets, can result in overdose and death [see OVERDOSAGE ], and this risk is increased with higher doses or unapproved methods or administration, such as snorting or injection. Before prescribing dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets, assess each patient’s risk for abuse, misuse, and addiction. Educate patients and their families about these risks and proper disposal of any unused drug.
Advise patients to store amphetamine sulfate in a safe place, preferably locked, and instruct patients to not give dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets to anyone else. Throughout dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets treatment, reassess each patient’s risk of abuse, misuse, and addiction and frequently monitor for signs and symptoms of abuse, misuse, and addiction. Risks to Patients with Serious Cardiovascular Disease Sudden Death- has been reported in patients with structural cardiac abnormalities or other serious cardiac disease who were treated with CNS stimulant treatment at the recommended ADHD dosages.
Avoid dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets use in patients with known structural cardiac abnormalities, cardiomyopathy, serious cardiac arrhythmia, coronary artery disease, or other serious cardiac disease. Increased Blood Pressure and Heart Rate CNS stimulants cause an increase in blood pressure (mean increase about 2 to 4 mm Hg) and heart rate (mean increase about 3 to 6 bpm). Some patients may have larger increases.
Monitor all dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets-treated patients for potential tachycardia and hypertension. Psychiatric Adverse Reactions Exacerbation of Preexisting Psychosis CNS stimulants may exacerbate symptoms of behavior disturbance and thought disorder in patients with a pre-existing psychotic disorder. Induction of a Manic Episode in Patients with Bipolar Disorder CNS stimulants may induce a manic or mixed episode in patients.
Prior to initiating treatment, screen patients for risk factors for developing a manic episode (e.g., comorbid or history of depressive symptoms or a family history of suicide, bipolar disorder, or depression). New Psychotic or Manic Symptoms CNS stimulants, at recommended doses, may cause psychotic or manic symptoms (e.g., hallucinations, delusional thinking, or mania) in patients without a prior history of psychotic illness or mania. In a pooled analysis of multiple short-term, placebo-controlled studies of CNS stimulants, psychotic or manic symptoms occurred in approximately 0.1% of CNS stimulant-treated patients, compared with 0% of placebo-treated patients.
If such symptoms occur, consider discontinuing dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets. Long-Term Suppression of Growth in Pediatric Patients CNS stimulants have been associated with weight los…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Cardiovascular Palpitations, tachycardia, elevation of blood pressure, sudden death, myocardial infarction. There have been isolated reports of cardiomyopathy associated with chronic amphetamine use. Central Nervous System Psychotic episodes at recommended doses, overstimulation, restlessness, irritability, euphoria, dyskinesia, dysphoria, depression, tremor, tics, aggression, anger, logorrhea, dermatillomania.
Eye Disorders Vision blurred, mydriasis. Gastrointestinal Dryness of the mouth, unpleasant taste, diarrhea, constipation, intestinal ischemia and other gastrointestinal disturbances. Anorexia and weight loss may occur as undesirable effects.
Allergic Urticaria, rash, hypersensitivity reactions including angioedema and anaphylaxis. Serious skin rashes, including Stevens-Johnson syndrome and toxic epidermal necrolysis have been reported. Endocrine Impotence, changes in libido, frequent or prolonged erections.
Skin Alopecia. Musculoskeletal Rhabdomyolysis.
🔄 Drug Interactions ▾
Drug Interactions MAO Inhibitors Concomitant use of MAOIs and CNS stimulants can cause hypertensive crisis. Potential outcomes include death, stroke, myocardial infarction, aortic dissection, ophthalmological complications, eclampsia, pulmonary edema, and renal failure. Do not administer dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets concomitantly or within 14 days after discontinuing MAOI [see CONTRAINDICATIONS and WARNINGS ].
Serotonergic Drugs The concomitant use of dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets and serotonergic drugs increases the risk of serotonin syndrome. Initiate with lower doses and monitor patients for signs and symptoms of serotonin syndrome, particularly during dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets initiation or dosage increase. If serotonin syndrome occurs, discontinue dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets and the concomitant serotonergic drug(s) [see WARNINGS and PRECAUTIONS ].
CYP2D6 Inhibitors The concomitant use of dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets and CYP2D6 inhibitors may increase the exposure of dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets compared to the use of the drug alone and increase the risk of serotonin syndrome. Initiate with lower doses and monitor patients for signs and symptoms of serotonin syndrome particularly during dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets initiation and after a dosage increase.
If serotonin syndrome occurs, discontinue dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets and the CYP2D6 inhibitor [see WARNINGS, OVERDOSAGE ]. Acidifying Agents Lower blood levels and efficacy of amphetamines. Increase dose based on clinical response.
Examples of acidifying agents include gastrointestinal acidifying agents and urinary acidifying agents. Adrenergic Blockers Adrenergic blockers are inhibited by amphetamines. Alkalinizing Agents Increase blood levels and potentiate the action of amphetamine.
Co-administration of dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets and gastrointestinal alkalinizing agents should be avoided. Examples of alkalinizing agents include gastrointestinal alkalinizing agents and urinary alkalinizing agents. Tricyclic Antidepressants May enhance the activity of tricyclic or sympathomimetic agents causing striking and sustained increases in the concentration of d-amphetamine in the brain; cardiovascular effects can be potentiated.
Monitor frequently and adjust or use alternative therapy based on clinical response. Antihistamines Amphetamines may counteract the sedative effect of antihistamines. Antihypertensives Amphetamines may antagonize the hypotensive effects of antihypertensives.
Chlorpromazine Chlorpromazine blocks dopamine and norepinephrine receptors, thus inhibiting the central stimulant effects of amphetamines, and can be used to treat amphetamine poisoning. Ethosuximide Amphetamines may delay intestinal absorption of ethosuximide. Haloperidol Haloperidol blocks dopamine receptors, thus inhibiting the central stimulant effects of amphetamines.
Lithium Carbonate The anorectic and stimulatory effects of amphetamines may be inhibited by lithium carbonate. Meperidine Amphetamines potentiate the analgesic effect of meperidine. Methenamine Therapy Urinary excretion of amphetamines is increased, and efficacy is reduced, by acidifying agents used in methenamine therapy.
Norepinephrine Amphetamines enhance the adrenergic effect of norepinephrine. Phen…
🔄 Drug / Laboratory Test Interactions ▾
Drug/Laboratory Test Interactions Amphetamines can cause a significant elevation in plasma corticosteroid levels. This increase is greatest in the evening. Amphetamines may interfere with urinary steroid determinations.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Amphetamine, in the enantiomer ratio present in dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets (d- to l- ratio of 3:1), had no apparent effects on embryofetal morphological development or survival when orally administered to pregnant rats and rabbits throughout the period of organogenesis at doses of up to 6 and 16 mg/kg/day, respectively. These doses are approximately 1.5 and 8 times, respectively, the maximum recommended human dose of 30 mg/day [child] on a mg/m 2 body surface area basis.
Fetal malformations and death have been reported in mice following parenteral administration of d-amphetamine doses of 50 mg/kg/day (approximately 6 times that of a human dose of 30 mg/day [child] on a mg/m 2 basis) or greater to pregnant animals. Administration of these doses was also associated with severe maternal toxicity. A number of studies in rodents indicate that prenatal or early postnatal exposure to amphetamine (d- or d,l-), at doses similar to those used clinically, can result in long-term neurochemical and behavioral alterations.
Reported behavioral effects include learning and memory deficits, altered locomotor activity, and changes in sexual function. There are no adequate and well-controlled studies in pregnant women. There has been one report of severe congenital bony deformity, tracheo-esophageal fistula, and anal atresia (vater association) in a baby born to a woman who took dextroamphetamine sulfate with lovastatin during the first trimester of pregnancy.
Amphetamines should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Nonteratogenic Effects Infants born to mothers dependent on amphetamines have an increased risk of premature delivery and low birth weight. Also, these infants may experience symptoms of withdrawal as demonstrated by dysphoria, including agitation, and significant lassitude.
🧒 Pediatric Use ▾
Pediatric Use Long-term effects of amphetamines in children have not been well established. Amphetamines are not recommended for use in children under 3 years of age with Attention Deficit Hyperactivity Disorder described under INDICATIONS AND USAGE .
🧓 Geriatric Use ▾
Geriatric Use Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets has not been studied in the geriatric population.
🆘 Overdosage ▾
OVERDOSAGE Clinical Effects of Overdose Overdose of CNS stimulants is characterized by the following sympathomimetic effects: Cardiovascular effects including tachyarrhythmias, and hypertension or hypotension. Vasospasm, myocardial infarction, or aortic dissection may precipitate sudden cardiac death. Takotsubo cardiomyopathy may develop.
CNS effects including psychomotor agitation, confusion, and hallucinations. Serotonin syndrome, seizures, cerebral vascular accidents, and coma may occur. Life-threatening hyperthermia (temperature greater than 104°F) and rhabdomyolysis may develop.
Posterior reversible encephalopathy syndrome (PRES) symptoms including headache, altered mental status, hypertension, seizures, and visual disturbances including blindness have occurred in the setting of an amphetamine product overdose. Symptoms of PRES are usually reversible but may evolve into ischemic stroke or cerebral hemorrhage. Diagnosis of PRES should be confirmed by radiological procedure (e.g., MRI).
Overdose Management Consider the possibility of multiple drug ingestion. D-amphetamine is not dialyzable. Consider contacting the Poison Help line (1-800-222-1222) or a medical toxicologist for additional overdose management recommendations.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Pharmacodynamics Amphetamines are non-catecholamine sympathomimetic amines with CNS stimulant activity. The mode of therapeutic action in Attention Deficit Hyperactivity Disorder (ADHD) is not known. Amphetamines are thought to block the reuptake of norepinephrine and dopamine into the presynaptic neuron and increase the release of these monoamines into the extraneuronal space.
Pharmacokinetics Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets contain d-amphetamine and l-amphetamine salts in the ratio of 3:1. Following administration of a single dose 10 or 30 mg of dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets to healthy volunteers under fasted conditions, peak plasma concentrations occurred approximately 3 hours post-dose for both d-amphetamine and l-amphetamine. The mean elimination half-life (t 1/2 ) for d-amphetamine was shorter than the t 1/2 of the l-isomer (9.77 to 11 hours vs.11.5 to 13.8 hours).
The PK parameters (C max , AUC 0-inf ) of d- and l-amphetamine increased approximately three-fold from 10 mg to 30 mg indicating dose-proportional pharmacokinetics. The effect of food on the bioavailability of dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets has not been studied. Metabolism and Excretion Amphetamine is reported to be oxidized at the 4 position of the benzene ring to form 4-hydroxyamphetamine, or on the side chain α or β carbons to form alpha-hydroxy-amphetamine or norephedrine, respectively.
Norephedrine and 4-hydroxy-amphetamine are both active and each is subsequently oxidized to form 4-hydroxy-norephedrine. Alpha-hydroxy-amphetamine undergoes deamination to form phenylacetone, which ultimately forms benzoic acid and its glucuronide and the glycine conjugate hippuric acid. Although the enzymes involved in amphetamine metabolism have not been clearly defined, CYP2D6 is known to be involved with formation of 4-hydroxy-amphetamine.
Since CYP2D6 is genetically polymorphic, population variations in amphetamine metabolism are a possibility. Amphetamine is known to inhibit monoamine oxidase, whereas the ability of amphetamine and its metabolites to inhibit various P450 isozymes and other enzymes has not been adequately elucidated. In vitro experiments with human microsomes indicate minor inhibition of CYP2D6 by amphetamine and minor inhibition of CYP1A2, 2D6, and 3A4 by one or more metabolites.
However, due to the probability of auto-inhibition and the lack of information on the concentration of these metabolites relative to in vivo concentrations, no predications regarding the potential for amphetamine or its metabolites to inhibit the metabolism of other drugs by CYP isozymes in vivo can be made. With normal urine pHs approximately half of an administered dose of amphetamine is recoverable in urine as derivatives of alpha-hydroxy-amphetamine and approximately another 30% to 40% of the dose is recoverable in urine as amphetamine itself.
Since amphetamine has a pKa of 9.9, urinary recovery of amphetamine is highly dependent on pH and urine flow rates. Alkaline urine pHs result in less ionization and reduced renal elimination, and acidic pHs and high flow rates result in increased renal elimination with clearances greater than glomerular filtration rates, indicating the involvement of active secretion. Urinary recovery of amphetamine has been reported to range from 1% to 75%, depending on urinary pH, with the remaining fraction of the dose hepatically metabolized.
Consequently, both hepatic and renal dysfunction have the potential to inhibit the elimination of amphetamine and result in prolonged exposures. In addition, drugs that affect urinary pH are known to alter the elimination of amphetamine, and any decrease in amphetamine's metabolism that might occur due to drug interactions or genetic polymorphisms i…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Dextroamphetamine Saccharate, Amphetamine Aspartate, Dextroamphetamine Sulfate and Amphetamine Sulfate Tablets are supplied as follows: 5 mg: A blue, oval, flat-faced, beveled-edge tablet debossed with “e” over “500” separated by a full score on one side and a full score on the other side debossed with 5 │ . 30 Tablets NDC 64850-500-30 100 Tablets NDC 64850-500-01 500 Tablets NDC 64850-500-05 7.5 mg: A blue, oval, flat-faced, beveled-edge tablet debossed with “e” over “501” separated by a full score on one side and two partial bisects and a full score on the other side debossed with 7 │ 1/2.
30 Tablets NDC 64850-501-30 100 Tablets NDC 64850-501-01 500 Tablets NDC 64850-501-05 10 mg: A blue, flat-faced, beveled-edge tablet debossed with “e” over “502” separated by a full score on one side and two partial bisects and a full score on the other side debossed with 1 │ 0. 30 Tablets NDC 64850-502-30 100 Tablets NDC 64850-502-01 500 Tablets NDC 64850-502-05 12.5 mg: A peach, oval biconvex tablet debossed with “e” over “503” separated by a full score on one side and four partial bisects on the other side debossed with 12 1/2.
30 Tablets NDC 64850-503-30 100 Tablets NDC 64850-503-01 500 Tablets NDC 64850-503-05 15 mg: A peach, oval, flat-faced, beveled-edge tablet debossed with “e” over “504” separated by a full score on one side and two partial bisects and a full score on the other side debossed with 1 │ 5. 30 Tablets NDC 64850-504-30 100 Tablets NDC 64850-504-01 500 Tablets NDC 64850-504-05 20 mg: A peach, oval, flat-faced, beveled-edge tablet with two partial bisects on one side debossed with “e” over “505” and two partial bisects and a full score on the other side debossed with 2 │ 0.
30 Tablets NDC 64850-505-30 100 Tablets NDC 64850-505-01 500 Tablets NDC 64850-505-05 30 mg: A peach, oval, biconvex tablet with two partial bisects on one side debossed with “e” over “506” and two partial bisects and a full score on the other side debossed with 3 │ 0. 30 Tablets NDC 64850-506-30 100 Tablets NDC 64850-506-01 500 Tablets NDC 64850-506-05 Dispense in a tight, light-resistant container. Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature].
Distributed by: Elite Laboratories, Inc. Northvale, NJ 07647 Rev. 07/26 IN0522
📋 Description ▾
DESCRIPTION A single-entity amphetamine product combining the neutral sulfate salts of dextroamphetamine and amphetamine, with the dextro isomer of amphetamine saccharate and d, l-amphetamine aspartate monohydrate. EACH TABLET CONTAINS 5 mg 7.5 mg 10 mg 12.5 mg 15 mg 20 mg 30 mg Dextroamphetamine Saccharate 1.25 mg 1.875mg 2.5 mg 3.125mg 3.75 mg 5 mg 7.5 mg Amphetamine Aspartate Monohydrate 1.25 mg 1.875mg 2.5 mg 3.125mg 3.75 mg 5 mg 7.5 mg Dextroamphetamine Sulfate, USP 1.25 mg 1.875mg 2.5 mg 3.125mg 3.75 mg 5 mg 7.5 mg Amphetamine Sulfate, USP 1.25 mg 1.875mg 2.5 mg 3.125mg 3.75 mg 5 mg 7.5 mg Total Amphetamine Base Equivalence 3.13 mg 4.7 mg 6.3 mg 7.8 mg 9.4 mg 12.6 mg 18.8 mg Inactive Ingredients: compressible sugar, magnesium stearate, maltodextrin, microcrystalline cellulose, sodium saccharin, and pregelatinized starch.
Colors: Dextroamphetamine Saccharate, Amphetamine Aspartate, Dextroamphetamine Sulfate and Amphetamine Sulfate Tablets 5 mg, 7.5 mg and 10 mg contain FD&C Blue #1 Aluminum Lake. Dextroamphetamine Saccharate, Amphetamine Aspartate, Dextroamphetamine Sulfate and Amphetamine Sulfate Tablets 12.5 mg, 15 mg, 20 mg and 30 mg contain FD&C Yellow #6 Aluminum Lake as a color additive.
💬 Medication Guide ▾
MEDICATION GUIDE MEDICATION GUIDE Dextroamphetamine Saccharate, Amphetamine Aspartate, Dextroamphetamine Sulfate and Amphetamine Sulfate Tablets CII (DEX-troe-am-FET-uh-meen SACK-uh-rate, am-FET-uh-meen ass-PAR-tate, DEX-troe-am-FET-uh-meen SULL-fate, and am-FET-uh-meen SULL-fate) What is the most important information I should know about dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets? Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets may cause serious side effects, including: Abuse, misuse, and addiction.
Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets has a high chance for abuse and misuse and may lead to substance use problems, including addiction. Misuse and abuse of dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets, other amphetamine containing medicines, and methylphenidate containing medicines, can lead to overdose and death. The risk of overdose and death is increased with higher doses of dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets or when it is used in ways that are not approved, such as snorting or injection.
Your healthcare provider should check you or your child’s risk for abuse, misuse, and addiction before starting treatment with dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets and will monitor you or your child during treatment. Dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets may lead to physical dependence after prolonged use, even if taken as directed by your healthcare provider. Do not give dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets to anyone else.
See “What is dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets?” for more information. Keep dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets in a safe place and properly dispose of any unused medicine. See “How should I store dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets?” for more information.
Tell your healthcare provider if you or your child have ever abused or been dependent on alcohol, prescription medicines, or street drugs. Risks for people with serious heart disease: Sudden death has happened in people who have heart defects or other serious heart disease. Your healthcare provider should check you or your child carefully for heart problems before starting treatment with dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets.
Tell your healthcare provider if you or your child have any heart problems, heart disease, or heart defects. Call your healthcare provider right away or go to the nearest hospital emergency room right away if you or your child have any signs of heart problems such as chest pain, shortness of breath, or fainting during treatment with dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets. Increased blood pressure and heart rate.
Your healthcare provider should check you or your child's blood pressure and heart rate regularly during treatment with dextroamphetamine saccharate, amphetamine aspartate, dextroamphetamine sulfate and amphetamine sulfate tablets. Mental (psychiatric) problems, including: new or worse behavior and thought problems new or worse bipolar illness new psychotic symptoms (such as hearing voices, or seeing or believing things that are not real) or new manic symptoms Tell your healthcare provider about any mental problems you…