
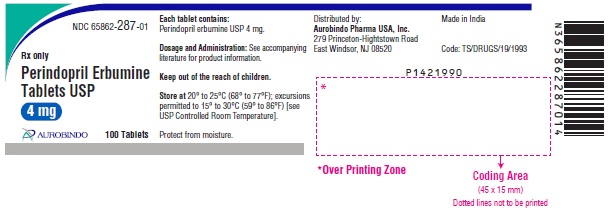
Perindopril Erbumine 4 mg Tablet, 100-count — NDC 65862-287-01 (Billing 65862-0287-01)
This is a package of 100 tablets of Perindopril Erbumine 4 mg Tablet from Aurobindo Pharma Limited, marketed since Nov 2009 and currently FDA-listed; retail pharmacies pay about $0.4947 per tablet (NADAC). It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 65862-287-01 alone.
- Record
- FDA NDC Directory package listing · Drug for further processing
- Code segments
- 65862 labeler · 287 product · 01 package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 100 EA per package
- Barcode (UPC-A, from the NDC)
- 3 6586228701 4
- Medicaid fills, this package
- 644 prescriptions in the last four reported quarters
- FDA record last changed
- Oct 4, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 033722
- GCN: 13759
- GPI-14 (Medi-Span): 36100035100320
- HICL (First Databank): 013911
- AHFS class code: 24:32.04.00
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
Clinical
- It treats essential hypertension (high blood pressure). It is also used in people with stable coronary artery disease to lower the risk of cardiovascular death or a nonfatal heart...
- Take it by mouth, usually once a day, exactly as your prescriber says. Food doesn't significantly change how much you absorb. Your doctor may start you low and raise the dose over...
- A dry, persistent cough is a known effect of ACE inhibitors like perindopril. It was the most common complaint in trials. Tell your doctor if it bothers you, since it usually goes...
- Get emergency help for swelling of your face, lips, tongue or throat, or trouble breathing. Call your doctor for fainting, severe belly pain, yellow skin or eyes, or signs of infec...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Perindopril Erbumine — tap one for details:
Perindopril Erbumine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.495 | $49.47 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.6506 | $65.06 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.7080 | $70.80 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 65862-0287-01 You're viewing this Main listing | 100 TABLET in 1 BOTTLE | $0.4947 / ea | $49.47 | 2009-11-10 | — | Active |
| 65862-0287-19 65862-287-19 | 10000 TABLET in 1 BAG | — | — | — | — | Active |
You're viewing the smallest of 2 pack sizes for this product.
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 65862-0287-19?
What NDC number is used to bill for this package of Perindopril Erbumine 4 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Perindopril Erbumine 4 mgthis 65862-0287-01 | Aurobindo | 100 tablets | $0.495 | — | Availability likely | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Perindopril inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Aurobindo Pharma Limited labeler code 65862
- Sulbactam Sodium 50 kg/50kg Powder NDC 65862-279-37
- Tazobactam Hemihydrate 50 kg/50kg Powder NDC 65862-280-37
- Ampicillin Sodium (Sterile) 50 kg/50kg Powder NDC 65862-282-37
- Ampicillin and Sulbactam for Injection 33.25 kg/50kg; 16.75 kg/50kg Powder NDC 65862-283-37
- Sulbactam Sodium 50 kg/50kg Powder NDC 65862-285-37
- Perindopril Erbumine 2 mg Tablet NDC 65862-286-01
- Perindopril Erbumine 8 mg Tablet NDC 65862-288-01
- Ribavirin 200 mg Capsule NDC 65862-290-05
- Rosuvastatin Calcium 5 mg Tablet, Film Coated NDC 65862-293-05
- Rosuvastatin Calcium 10 mg Tablet, Film Coated NDC 65862-294-05
- Rosuvastatin Calcium 20 mg Tablet, Film Coated NDC 65862-295-05
- Rosuvastatin Calcium 40 mg Tablet, Film Coated NDC 65862-296-05
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full FDA label FDA SPL
🚨 Boxed Warning ▾
WARNING: FETAL TOXICITY When pregnancy is detected, discontinue perindopril erbumine as soon as possible [see Warnings and Precautions (5.4) ]. Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus [see Warnings and Precautions (5.4) ] . WARNING: FETAL TOXICITY See full prescribing information for complete boxed warning.
When pregnancy is detected, discontinue perindopril erbumine as soon as possible [see Warnings and Precautions (5.4) ] . Drugs that act directly on the renin-angiotensin system can cause injury and death to the developing fetus [ see Warnings and Precautions (5.4) ] .
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Perindopril erbumine tablets are indicated for the treatment of patients with essential hypertension. (1.1) Perindopril erbumine tablets are indicated for treatment of patients with stable coronary artery disease to reduce the risk of cardiovascular mortality or nonfatal myocardial infarction. (1.2)
1.1Hypertension Perindopril erbumine tablets are indicated for the treatment of patients with essential hypertension. Perindopril erbumine tablets may be used alone or given with other classes of antihypertensives, especially thiazide diuretics.
1.2Stable Coronary Artery Disease Perindopril erbumine tablets are indicated for treatment of patients with stable coronary artery disease to reduce the risk of cardiovascular mortality or nonfatal myocardial infarction. Perindopril erbumine tablets can be used with conventional treatment for management of coronary artery disease, such as antiplatelet, antihypertensive or lipid-lowering therapy.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Hypertension The recommended initial dose is 4 mg once a day. The dosage may be titrated upward until blood pressure, when measured just before the next dose, is controlled or to a maximum of 16 mg per day. (2.1) Stable Coronary Artery Disease Perindopril erbumine tablets should be given at an initial dose of 4 mg once daily for 2 weeks, and then increased, as tolerated, to a maintenance dose of 8 mg once daily. (2.2)
2.1Hypertension Use in Uncomplicated Hypertensive Patients: In patients with essential hypertension, the recommended initial dose is 4 mg once a day. The dose may be titrated, as needed to a maximum of 16 mg per day. The usual maintenance dose range is 4 mg to 8 mg administered as a single daily dose or in two divided doses.
Use in Elderly Patients: The recommended initial daily dosage of perindopril erbumine tablets for the elderly is 4 mg daily, given in one or two divided doses. Experience with perindopril erbumine tablets is limited in the elderly at doses exceeding 8 mg. Dosages above 8 mg should be administered with careful blood pressure monitoring and dose titration [see Use in Specific Populations (8.5) ] .
Use with Diuretics: In patients who are currently being treated with a diuretic, symptomatic hypotension can occur following the initial dose of perindopril erbumine tablets. Consider reducing the dose of diuretic prior to starting perindopril erbumine tablets [see Drug Interactions (7.1) ] .
2.2Stable Coronary Artery Disease In patients with stable coronary artery disease, perindopril erbumine tablets should be given at an initial dose of 4 mg once daily for 2 weeks, and then increased as tolerated, to a maintenance dose of 8 mg once daily. In elderly patients (greater than 70 years), perindopril erbumine tablets should be given as a 2 mg dose once daily in the first week, followed by 4 mg once daily in the second week and 8 mg once daily for maintenance dose if tolerated.
2.3Dose Adjustment in Renal Impairment and Dialysis Perindoprilat elimination is decreased in renally impaired patients. Perindopril erbumine tablets are not recommended in patients with creatinine clearance <30 mL/min. For patients with lesser degrees of impairment, the initial dosage should be 2 mg/day and dosage should not exceed 8 mg/day. During dialysis, perindopril is removed with the same clearance as in patients with normal renal function.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 2 mg tablet is white to off-white colored round biconvex, uncoated tablets, with debossing “D” on one side and “5” & “7” on either side of the breakline on another side. 4 mg tablet is white to off-white colored capsule shaped uncoated tablets, with debossing “D” on one side and “5” & “8” on either side of the breakline on another side. 8 mg tablet is white to off-white colored round biconvex uncoated tablets, with debossing “D” on one side and “5” & “9” on either side of breakline on another side.
Tablets: 2 mg, 4 mg and 8 mg (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Perindopril erbumine tablets are contraindicated in patients known to be hypersensitive (including angioedema) to this product or to any other ACE inhibitor. Perindopril erbumine tablets are also contraindicated in patients with hereditary or idiopathic angioedema. Do not co-administer aliskiren with perindopril erbumine tablets in patients with diabetes. [see Drug Interactions (7.8) ] Perindopril erbumine tablets are contraindicated in combination with neprilysin inhibitor (e.g., sacubitril).
Do not administer perindopril erbumine tablets within 36 hours of switching to or from sacubitril/valsartan, a neprilysin inhibitor [see Warnings and Precautions (5.1) ]. Angioedema related to previous treatment with an ACE inhibitor, or a history of hereditary or idiopathic angioedema. ( 4 , 5.1 ) Do not co-administer aliskiren with perindopril erbumine tablets in patients with diabetes ( 4 , 7.8 ) Do not take a neprilysin inhibitor with perindopril erbumine tablets ( 4 ).
Do not administer perindopril erbumine tablets within 36 hours of switching to or from sacubitril/valsartan ( 4 ).
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Watch for anaphylactoid reactions, including angioedema. (5.1) Monitor renal function during therapy. (5.5) Assess for hypotension and hyperkalemia. (5.2 , 5.6)
5.1Anaphylactoid and Possibly Related Reactions Presumably because angiotensin-converting enzyme inhibitors affect the metabolism of eicosanoids and polypeptides, including endogenous bradykinin, patients receiving ACE inhibitors (including perindopril erbumine) may be subject to a variety of adverse events, some of them serious. Black patients receiving ACE inhibitors have a higher incidence of angioedema compared to nonblacks. Head and Neck Angioedema: Angioedema of the face, extremities, lips, tongue, glottis, or larynx has been reported in patients treated with ACE inhibitors, including perindopril erbumine (0.1% of patients treated with perindopril erbumine in U.S. clinical trials).
Angioedema associated with involvement of the tongue, glottis or larynx may be fatal. In such cases, discontinue perindopril erbumine treatment immediately and observe until the swelling disappears. When involvement of the tongue, glottis, or larynx appears likely to cause airway obstruction, administer appropriate therapy, such as subcutaneous epinephrine solution 1:1000 (0.3 to 0.5 mL), promptly.
Patients taking concomitant mTOR inhibitor (e.g., temsirolimus) therapy or a neprilysin inhibitor may be at increased risk for angioedema [see Drug Interactions (7.9 ; 7.10) ]. Intestinal Angioedema: Intestinal angioedema has been reported in patients treated with ACE inhibitors. These patients presented with abdominal pain (with or without nausea or vomiting); in some cases there was no prior history of facial angioedema and C-1 esterase levels were normal.
The angioedema was diagnosed by procedures including abdominal CT scan or ultrasound, or at surgery, and symptoms resolved after stopping the ACE inhibitor. Intestinal angioedema should be included in the differential diagnosis of patients on ACE inhibitors presenting with abdominal pain.
5.2Hypotension Perindopril erbumine can cause symptomatic hypotension. Perindopril erbumine has been associated with hypotension in 0.3% of uncomplicated hypertensive patients in U.S. placebo-controlled trials. Symptoms related to orthostatic hypotension were reported in another 0.8% of patients.
Symptomatic hypotension is most likely to occur in patients who have been volume or salt-depleted as a result of prolonged diuretic therapy, dietary salt restriction, dialysis, diarrhea or vomiting [see Dosage and Administration (2.1) ] . ACE inhibitors may cause excessive hypotension, and may be associated with oliguria or azotemia, and rarely with acute renal failure and death. In patients with ischemic heart disease or cerebrovascular disease, an excessive fall in blood pressure could result in a myocardial infarction or a cerebrovascular accident.
In patients at risk of excessive hypotension, perindopril erbumine therapy should be started under very close medical supervision. Patients should be followed closely for the first two weeks of treatment and whenever the dose of perindopril erbumine and/or diuretic is increased. If excessive hypotension occurs, the patient should be placed immediately in a supine position and, if necessary, treated with an intravenous infusion of physiological saline.
Perindopril erbumine treatment can usually be continued following restoration of volume and blood pressure.
5.3Neutropenia/Agranulocytosis ACE inhibitors have been associated with agranulocytosis and bone marrow depression, most frequently in patients with renal impairment, especially patients with a collagen vascular disease such as systemic lupus erythematosus or scleroderma.
5.4Fetal Toxicity Pregnancy Category D Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be as… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Because clinical trials are conducted under widely varying conditions, adverse event rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Hypertension: Most common adverse events (incidence greater than or equal to 5%) are cough, dizziness and back pain. (6.1) Stable Coronary Artery Disease: Most common adverse events leading to discontinuation were cough, drug intolerance, and hypotension.
(6.1) To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience The following adverse reactions are discussed elsewhere in labeling: Anaphylactoid reactions, including angioedema [see Warnings and Precautions (5.1) ] Hypotension [see Warnings and Precautions (5.2) ] Neutropenia and agranulocytosis [see Warnings and Precautions (5.3) ] Impaired renal function [see Warnings and Precautions (5.5) ] Hyperkalemia [see Warnings and Precautions (5.6) ] Cough [see Warnings and Precautions (5.7) ] Hypertension Perindopril erbumine has been evaluated for safety in approximately 3,400 patients with hypertension in U.S. and foreign clinical trials.
The data presented here are based on results from the 1,417 perindopril erbumine-treated patients who participated in the U.S. clinical trials. Over 220 of these patients were treated with perindopril erbumine for at least one year. In placebo-controlled U.S. clinical trials, the incidence of premature discontinuation of therapy due to adverse events was 6.5% in patients treated with perindopril erbumine and 6.7% in patients treated with placebo.
The most common causes were cough, headache, asthenia and dizziness. Among 1,012 patients in placebo-controlled U.S. trials, the overall frequency of reported adverse events was similar in patients treated with perindopril erbumine and in those treated with placebo (approximately 75% in each group). The only adverse events whose incidence on perindopril erbumine was at least 2% greater than on placebo were cough (12% vs.
4.5%) and back pain (5.8% vs. 3.1%). Dizziness was not reported more frequently in the perindopril group (8.2%) than in the placebo group (8.5%), but its likelihood increased with dose, suggesting a causal relationship with perindopril.
Stable Coronary Artery Disease Perindopril has been evaluated for safety in EUROPA, a double-blind, placebo-controlled study in 12,218 patients with stable coronary artery disease. The overall rate of discontinuation was about 22% on drug and placebo. The most common medical reasons for discontinuation that were more frequent on perindopril than placebo were cough, drug intolerance and hypotension.
6.2Postmarketing Experience Voluntary reports of adverse events in patients taking perindopril erbumine that have been received since market introduction and are of unknown causal relationship to perindopril erbumine include: cardiac arrest, eosinophilic pneumonitis, neutropenia/agranulocytosis, pancytopenia, anemia (including hemolytic and aplastic), thrombocytopenia, acute renal failure, nephritis, hepatic failure, jaundice (hepatocellular or cholestatic), symptomatic hyponatremia, bullous pemphigoid, pemphigus, acute pancreatitis, falls, psoriasis, exfoliative dermatitis and a syndrome which may include: arthralgia/arthritis, vasculitis, serositis, myalgia, fever, rash or other dermatologic manifestations, a positive antinuclear antibody (ANA), leukocytosis, eosinophilia or an elevated erythrocyte sedimentation rate (ESR).
6.3Clinical Laboratory Test Findings Hematology: Small decreases in hemoglobin and hematocrit occur frequently in hypertensive patients treated with perindopril erbumine, but are rarely of clinical importance. In controlled clinical trials, no patient was discontinued from therapy due to the development of anemia. Leukopenia (including neutropeni… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Diuretics: Excessive drop in blood pressure. (7.1) Potassium-Sparing Diuretics/Potassium Supplements: Hyperkalemia. (7.2) Lithium: Increase serum lithium levels, symptoms of lithium toxicity.
(7.3) Injectable Gold: Nitritoid reactions (facial flushing, nausea, vomiting, and hypotension). (7.4) NSAID use may lead to increased risk of renal impairment and loss of antihypertensive effect. (7.7) Dual inhibition of the renin-angiotensin system: Increased risk of renal impairment, hypotension, and hyperkalemia.
( 7.8 ) Neprilysin Inhibitor: risk of angioedema ( 7 ).
7.1Diuretics Patients on diuretics, and especially those started recently, may occasionally experience an excessive reduction of blood pressure after initiation of perindopril erbumine therapy. The possibility of hypotensive effects can be minimized by either decreasing the dose of or discontinuing the diuretic or increasing the salt intake prior to initiation of treatment with perindopril. If diuretic therapy cannot be altered, provide close medical supervision with the first dose of perindopril erbumine, for at least two hours and until blood pressure has stabilized for another hour [see Warnings and Precautions (5.2) ] .
The rate and extent of perindopril absorption and elimination are not affected by concomitant diuretics. The bioavailability of perindoprilat was reduced by diuretics, however, and this was associated with a decrease in plasma ACE inhibition.
7.2Potassium Supplements and Potassium-Sparing Diuretics Perindopril erbumine may increase serum potassium because of its potential to decrease aldosterone production. Use of potassium-sparing diuretics (spironolactone, amiloride, triamterene and others), potassium supplements or other drugs capable of increasing serum potassium (indomethacin, heparin, cyclosporine and others) can increase the risk of hyperkalemia. Therefore, if concomitant use of such agents is indicated, monitor the patient’s serum potassium frequently.
7.3Lithium Increased serum lithium and symptoms of lithium toxicity have been reported in patients receiving concomitant lithium and ACE inhibitor therapy. Frequent monitoring of serum lithium concentration is recommended. Use of a diuretic may further increase the risk of lithium toxicity.
7.4Gold Nitritoid reactions (symptoms include facial flushing, nausea, vomiting and hypotension) have been reported rarely in patients on therapy with injectable gold (sodium aurothiomalate) and concomitant ACE Inhibitor therapy including perindopril erbumine.
7.5Digoxin A controlled pharmacokinetic study has shown no effect on plasma digoxin concentrations when coadministered with perindopril erbumine, but an effect of digoxin on the plasma concentration of perindopril/perindoprilat has not been excluded.
7.6Gentamicin Animal data have suggested the possibility of interaction between perindopril and gentamicin. However, this has not been investigated in human studies.
7.7Non-Steroidal Anti-Inflammatory Agents including Selective Cyclooxygenase-2 Inhibitors (COX-2 Inhibitors) In patients who are elderly, volume-depleted (including those on diuretic therapy), or with compromised renal function, co-administration of NSAIDs, including selective COX-2 inhibitors, with ACE inhibitors, including perindopril, may result in deterioration of renal function, including possible acute renal failure. These effects are usually reversible. Monitor renal function periodically in patients receiving perindopril and NSAID therapy.
The antihypertensive effect of ACE inhibitors, including perindopril, may be attenuated by NSAIDs including selective COX-2 inhibitors.
7.8Dual Blockade of the Renin-Angiotensin System (RAS) Dual blockade of the RAS with angiotensin receptor blockers, ACE inhibitors, or aliskiren is associated with increased risks of hypotension, hyperkalemia, and changes in renal function (including acute renal failure) compared to monotherapy. Most patients receiving the combination of tw… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Geriatrics: Start at low daily dose (4 mg or less) and titrate slowly as needed. Experience with doses exceeding 8 mg is limited. (8.5) Dosage adjustment may be necessary in renally impaired patients. (8.6)
8.1Pregnancy Pregnancy Category D [see Boxed Warning and Warnings and Precautions (5.4) ] . Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations.
Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death. When pregnancy is detected, discontinue perindopril erbumine as soon as possible. These adverse outcomes are usually associated with use of these drugs in the second and third trimester of pregnancy.
Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents. Appropriate management of maternal hypertension during pregnancy is important to optimize outcomes for both mother and fetus. In the unusual case that there is no appropriate alternative to therapy with drugs affecting the renin-angiotensin system for a particular patient, apprise the mother of the potential risk to the fetus.
Perform serial ultrasound examinations to assess the intra-amniotic environment. If oligohydramnios is observed, discontinue perindopril erbumine, unless it is considered lifesaving for the mother. Fetal testing may be appropriate, based on the week of pregnancy.
Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury. Closely observe infants with histories of in utero exposure to perindopril erbumine for hypotension, oliguria, and hyperkalemia [see Use in Specific Populations (8.4) ] . Radioactivity was detectable in fetuses after administration of 14 C-perindopril to pregnant rats.
8.3Nursing Mothers Milk of lactating rats contained radioactivity following administration of 14 C-perindopril. It is not known whether perindopril is secreted in human milk. Because many drugs are secreted in human milk, caution should be exercised when perindopril erbumine is given to nursing mothers.
8.4Pediatric Use Neonates With a History of in utero Exposure to Perindopril Erbumine: If oliguria or hypotension occurs, direct attention toward support of blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and/or substituting for disordered renal function. Perindopril, which crosses the placenta, can theoretically be removed from the neonatal circulation by these means, but limited experience has not shown that such removal is central to the treatment of these infants.
Safety and effectiveness of perindopril erbumine in pediatric patients have not been established.
8.5Geriatric Use The mean blood pressure effect of perindopril was somewhat smaller in patients over 60 than in younger patients, although the difference was not significant. Plasma concentrations of both perindopril and perindoprilat were increased in elderly patients compared to concentrations in younger patients. No adverse effects were clearly increased in older patients with the exception of dizziness and possibly rash.
Start at a low dose and titrate slowly as needed. Monitor for dizziness because of potential for falls. Experience with perindopril erbumine in elderly patients at daily doses exceeding 8 mg is limited.
8.6Renal Impairment Dosage adjustment may be necessary in renally impaired patients [see Dosage and Administration (2.3) and Clinical Pharmacology (12.3) ] .
8.7Hepatic Impairment The bioavailability of perindoprilat is increased in patients with impaired hep… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Category D [see Boxed Warning and Warnings and Precautions (5.4) ] . Use of drugs that act on the renin-angiotensin system during the second and third trimesters of pregnancy reduces fetal renal function and increases fetal and neonatal morbidity and death. Resulting oligohydramnios can be associated with fetal lung hypoplasia and skeletal deformations.
Potential neonatal adverse effects include skull hypoplasia, anuria, hypotension, renal failure, and death. When pregnancy is detected, discontinue perindopril erbumine as soon as possible. These adverse outcomes are usually associated with use of these drugs in the second and third trimester of pregnancy.
Most epidemiologic studies examining fetal abnormalities after exposure to antihypertensive use in the first trimester have not distinguished drugs affecting the renin-angiotensin system from other antihypertensive agents. Appropriate management of maternal hypertension during pregnancy is important to optimize outcomes for both mother and fetus. In the unusual case that there is no appropriate alternative to therapy with drugs affecting the renin-angiotensin system for a particular patient, apprise the mother of the potential risk to the fetus.
Perform serial ultrasound examinations to assess the intra-amniotic environment. If oligohydramnios is observed, discontinue perindopril erbumine, unless it is considered lifesaving for the mother. Fetal testing may be appropriate, based on the week of pregnancy.
Patients and physicians should be aware, however, that oligohydramnios may not appear until after the fetus has sustained irreversible injury. Closely observe infants with histories of in utero exposure to perindopril erbumine for hypotension, oliguria, and hyperkalemia [see Use in Specific Populations (8.4) ] . Radioactivity was detectable in fetuses after administration of 14 C-perindopril to pregnant rats.
🧒 Pediatric Use ▾
8.4Pediatric Use Neonates With a History of in utero Exposure to Perindopril Erbumine: If oliguria or hypotension occurs, direct attention toward support of blood pressure and renal perfusion. Exchange transfusions or dialysis may be required as a means of reversing hypotension and/or substituting for disordered renal function. Perindopril, which crosses the placenta, can theoretically be removed from the neonatal circulation by these means, but limited experience has not shown that such removal is central to the treatment of these infants.
Safety and effectiveness of perindopril erbumine in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use The mean blood pressure effect of perindopril was somewhat smaller in patients over 60 than in younger patients, although the difference was not significant. Plasma concentrations of both perindopril and perindoprilat were increased in elderly patients compared to concentrations in younger patients. No adverse effects were clearly increased in older patients with the exception of dizziness and possibly rash.
Start at a low dose and titrate slowly as needed. Monitor for dizziness because of potential for falls. Experience with perindopril erbumine in elderly patients at daily doses exceeding 8 mg is limited.
🆘 Overdosage ▾
10 OVERDOSAGE In animals, doses of perindopril up to 2,500 mg/kg in mice, 3,000 mg/kg in rats and 1,600 mg/kg in dogs were non-lethal. Past experiences were scant but suggested that overdosage with other ACE inhibitors was also fairly well tolerated by humans. The most likely manifestation is hypotension, and treatment should be symptomatic and supportive.
Therapy with the ACE inhibitor should be discontinued, and the patient should be observed. Dehydration, electrolyte imbalance and hypotension should be treated by established procedures. Among the reported cases of perindopril overdosage, patients who were known to have ingested a dose of 80 mg to 120 mg required assisted ventilation and circulatory support.
One additional patient developed hypothermia, circulatory arrest and died following ingestion of up to 180 mg of perindopril. The intervention for perindopril overdose may require vigorous support. Laboratory determinations of serum levels of perindopril and its metabolites are not widely available, and such determinations have, in any event, no established role in the management of perindopril overdose.
No data are available to suggest physiological maneuvers ( e.g., maneuvers to change the pH of the urine) that might accelerate elimination of perindopril and its metabolites. Perindopril can be removed by hemodialysis, with clearance of 52 mL/min for perindopril and 67 mL/min for perindoprilat. Angiotensin II could presumably serve as a specific antagonist-antidote in the settling of perindopril overdose, but angiotensin II is essentially unavailable outside of scattered research facilities.
Because the hypotensive effect of perindopril is achieved through vasodilation and effective hypovolemia, it is reasonable to treat perindopril overdose by infusion of normal saline solution.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Perindopril erbumine is a pro-drug for perindoprilat, which inhibits ACE in human subjects and animals. The mechanism through which perindoprilat lowers blood pressure is believed to be primarily inhibition of ACE activity. ACE is a peptidyl dipeptidase that catalyzes conversion of the inactive decapeptide, angiotensin I, to the vasoconstrictor, angiotensin II.
Angiotensin II is a potent peripheral vasoconstrictor, which stimulates aldosterone secretion by the adrenal cortex, and provides negative feedback on renin secretion. Inhibition of ACE results in decreased plasma angiotensin II, leading to decreased vasoconstriction, increased plasma renin activity and decreased aldosterone secretion. The latter results in diuresis and natriuresis and may be associated with a small increase of serum potassium.
ACE is identical to kininase II, an enzyme that degrades bradykinin. Whether increased levels of bradykinin, a potent vasodepressor peptide, play a role in the therapeutic effects of perindopril erbumine remains to be elucidated. While the principal mechanism of perindopril in blood pressure reduction is believed to be through the renin-angiotensin-aldosterone system, ACE inhibitors have some effect even in apparent low-renin hypertension.
Perindopril has been studied in relatively few black patients, usually a low-renin population, and the average response of diastolic blood pressure to perindopril was about half the response seen in nonblack patients, a finding consistent with previous experience of other ACE inhibitors.
12.2Pharmacodynamics After administration of perindopril, ACE is inhibited in a dose and blood concentration-related fashion, with the maximal inhibition of 80 to 90% attained by 8 mg persisting for 10 to 12 hours. Twenty-four hour ACE inhibition is about 60% after these doses. The degree of ACE inhibition achieved by a given dose appears to diminish over time (the ID 50 increases).
The pressor response to an angiotensin I infusion is reduced by perindopril, but this effect is not as persistent as the effect on ACE; there is about 35% inhibition at 24 hours after a 12 mg dose.
12.3Pharmacokinetics Absorption: Oral administration of perindopril erbumine results in peak plasma concentrations that occur at approximately 1 hour. The absolute oral bioavailability of perindopril is about 75%. Following absorption, approximately 30 to 50% of systemically available perindopril is hydrolyzed to its active metabolite, perindoprilat, which has a mean bioavailability of about 25%.
Peak plasma concentrations of perindoprilat are attained 3 to 7 hours after perindopril administration. Oral administration of perindopril erbumine with food does not significantly lower the rate or extent of perindopril absorption relative to the fasted state. However, the extent of biotransformation of perindopril to the active metabolite, perindoprilat, is reduced approximately 43%, resulting in a reduction in the plasma ACE inhibition curve of approximately 20%, probably clinically insignificant.
In clinical trials, perindopril was generally administered in a non-fasting state. With 4 mg, 8 mg and 16 mg doses of perindopril erbumine, C max and AUC of perindopril and perindoprilat increase in a dose-proportional manner following both single oral dosing and at steady state during a once-a-day multiple dosing regimen. Distribution: Approximately 60% of circulating perindopril is bound to plasma proteins, and only 10 to 20% of perindoprilat is bound.
Therefore, drug interactions mediated through effects on protein binding are not anticipated. Metabolism and Elimination: Following oral administration perindopril exhibits multicompartment pharmacokinetics including a deep tissue compartment (ACE binding sites). The mean half-life of perindopril associated with most of its elimination is approximately 0.8 to 1 hours.
Perindopril is extensively metabolized following oral administration, with only 4… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Perindopril erbumine is a pro-drug for perindoprilat, which inhibits ACE in human subjects and animals. The mechanism through which perindoprilat lowers blood pressure is believed to be primarily inhibition of ACE activity. ACE is a peptidyl dipeptidase that catalyzes conversion of the inactive decapeptide, angiotensin I, to the vasoconstrictor, angiotensin II.
Angiotensin II is a potent peripheral vasoconstrictor, which stimulates aldosterone secretion by the adrenal cortex, and provides negative feedback on renin secretion. Inhibition of ACE results in decreased plasma angiotensin II, leading to decreased vasoconstriction, increased plasma renin activity and decreased aldosterone secretion. The latter results in diuresis and natriuresis and may be associated with a small increase of serum potassium.
ACE is identical to kininase II, an enzyme that degrades bradykinin. Whether increased levels of bradykinin, a potent vasodepressor peptide, play a role in the therapeutic effects of perindopril erbumine remains to be elucidated. While the principal mechanism of perindopril in blood pressure reduction is believed to be through the renin-angiotensin-aldosterone system, ACE inhibitors have some effect even in apparent low-renin hypertension.
Perindopril has been studied in relatively few black patients, usually a low-renin population, and the average response of diastolic blood pressure to perindopril was about half the response seen in nonblack patients, a finding consistent with previous experience of other ACE inhibitors.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Perindopril Erbumine T ablets USP, 2 mg are white to off-white colored round biconvex, uncoated tablets, with debossing “D” on one side and “5” & “7” on either side of the breakline on another side. Bottles of 100 NDC 65862-286-01 Perindopril Erbumine T ablets USP, 4 mg are white to off-white colored capsule shaped uncoated tablets, with debossing “D” on one side and “5” & “8” on either side of the breakline on another side. Bottles of 100 NDC 65862-287-01 Perindopril Erbumine T ablets USP, 8 mg are white to off-white colored round biconvex uncoated tablets, with debossing “D” on one side and “5” & “9” on either side of breakline on another side.
Bottles of 100 NDC 65862-288-01 Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Protect from moisture. Keep out of the reach of children.
For further information, please call Aurobindo Pharma USA, Inc. at 1-866-850-2876.
📋 Description ▾
11 DESCRIPTION Perindopril erbumine tablets USP contain the tert-butylamine salt of perindopril, the ethyl ester of a non-sulfhydryl angiotensin-converting enzyme (ACE) inhibitor. Perindopril erbumine is chemically described as (2S,3DS,7DS)-1-[(S)-N-[(S)-1-Carboxy-butyl]alanyl]hexahydro-2-indolinecarboxylic acid, 1-ethyl ester, compound with tert-butylamine (1:1). Its molecular formula is C 19 H 32 N 2 O 5 C 4 H 11 N.
Its structural formula is: Perindopril erbumine USP is a white or almost white, crystalline powder, slightly hygroscopic with a molecular weight of 368.47 (free acid) or 441.61 (salt form). It is freely soluble in water (60% w/w), alcohol and chloroform. Perindopril is the free acid form of perindopril erbumine, is a pro-drug and metabolized in vivo by hydrolysis of the ester group to form perindoprilat, the biologically active metabolite.
Perindopril erbumine tablets USP are available in 2 mg, 4 mg and 8 mg strengths for oral administration. In addition to perindopril erbumine, each tablet contains the following inactive ingredients: anhydrous lactose, silica hydrophobic colloidal anhydrous, microcrystalline cellulose, and magnesium stearate. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Female patients of childbearing age should be told about the consequences of exposure to perindopril erbumine during pregnancy. Discuss treatment options with women planning to become pregnant. Patients should be asked to report pregnancies to their physicians as soon as possible.
Tell patients to report promptly any indication of infection ( e.g., sore throat, fever) which could be a sign of neutropenia. Distributed by: Aurobindo Pharma USA, Inc. 279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 032, India Revised: 03/2024
🍼 Nursing Mothers ▾
8.3Nursing Mothers Milk of lactating rats contained radioactivity following administration of 14 C-perindopril. It is not known whether perindopril is secreted in human milk. Because many drugs are secreted in human milk, caution should be exercised when perindopril erbumine is given to nursing mothers.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption: Oral administration of perindopril erbumine results in peak plasma concentrations that occur at approximately 1 hour. The absolute oral bioavailability of perindopril is about 75%. Following absorption, approximately 30 to 50% of systemically available perindopril is hydrolyzed to its active metabolite, perindoprilat, which has a mean bioavailability of about 25%.
Peak plasma concentrations of perindoprilat are attained 3 to 7 hours after perindopril administration. Oral administration of perindopril erbumine with food does not significantly lower the rate or extent of perindopril absorption relative to the fasted state. However, the extent of biotransformation of perindopril to the active metabolite, perindoprilat, is reduced approximately 43%, resulting in a reduction in the plasma ACE inhibition curve of approximately 20%, probably clinically insignificant.
In clinical trials, perindopril was generally administered in a non-fasting state. With 4 mg, 8 mg and 16 mg doses of perindopril erbumine, C max and AUC of perindopril and perindoprilat increase in a dose-proportional manner following both single oral dosing and at steady state during a once-a-day multiple dosing regimen. Distribution: Approximately 60% of circulating perindopril is bound to plasma proteins, and only 10 to 20% of perindoprilat is bound.
Therefore, drug interactions mediated through effects on protein binding are not anticipated. Metabolism and Elimination: Following oral administration perindopril exhibits multicompartment pharmacokinetics including a deep tissue compartment (ACE binding sites). The mean half-life of perindopril associated with most of its elimination is approximately 0.8 to 1 hours.
Perindopril is extensively metabolized following oral administration, with only 4 to 12% of the dose recovered unchanged in the urine. Six metabolites resulting from hydrolysis, glucuronidation and cyclization via dehydration have been identified. These include the active ACE inhibitor, perindoprilat (hydrolyzed perindopril), perindopril and perindoprilat glucuronides, dehydrated perindopril and the diastereoisomers of dehydrated perindoprilat.
In humans, hepatic esterase appears to be responsible for the hydrolysis of perindopril. The active metabolite, perindoprilat, also exhibits multicompartment pharmacokinetics following the oral administration of perindopril erbumine. Formation of perindoprilat is gradual with peak plasma concentrations occurring between 3 and 7 hours.
The subsequent decline in plasma concentration shows an apparent mean half-life of 3 to 10 hours for the majority of the elimination, with a prolonged terminal elimination half-life of 30 to 120 hours resulting from slow dissociation of perindoprilat from plasma/tissue ACE binding sites. During repeated oral once daily dosing with perindopril, perindoprilat accumulates about 1.5 to 2 fold and attains steady state plasma levels in 3 to 6 days. The clearance of perindoprilat and its metabolites is almost exclusively renal.
Elderly: Plasma concentrations of both perindopril and perindoprilat in elderly patients (greater than 70 years) are approximately twice those observed in younger patients, reflecting both increased conversion of perindopril to perindoprilat and decreased renal excretion of perindoprilat [see Dosage and Administration (2.1) and Use in Specific Populations (8.5) ] . Heart Failure: Perindoprilat clearance is reduced in congestive heart failure patients, resulting in a 40% higher dose interval AUC. Renal Impairment: With perindopril doses of 2 mg to 4 mg, perindoprilat AUC increases with decreasing renal function.
At creatinine clearances of 30 to 80 mL/min, AUC is about double that at 100 mL/min. When creatinine clearance drops below 30 mL/min, AUC increases more markedly. In a limited number of patients studied, perindopril clearance by dialysis ranged from about 40 to 80 mL/min.
Perindoprilat clearance by dialysis ranged from about 40 t… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics After administration of perindopril, ACE is inhibited in a dose and blood concentration-related fashion, with the maximal inhibition of 80 to 90% attained by 8 mg persisting for 10 to 12 hours. Twenty-four hour ACE inhibition is about 60% after these doses. The degree of ACE inhibition achieved by a given dose appears to diminish over time (the ID 50 increases).
The pressor response to an angiotensin I infusion is reduced by perindopril, but this effect is not as persistent as the effect on ACE; there is about 35% inhibition at 24 hours after a 12 mg dose.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Hypertension In placebo-controlled studies of perindopril monotherapy (2 mg to 16 mg once daily) in patients with a mean blood pressure of about 150/100 mm Hg, 2 mg had little effect, but doses of 4 mg to 16 mg lowered blood pressure. The 8 mg and 16 mg doses were indistinguishable, and both had a greater effect than the 4 mg dose. In these studies, doses of 8 mg and 16 mg per day gave supine, trough blood pressure reductions of 9 to 15/5 to 6 mm Hg.
When once daily and twice daily dosing were compared, the twice daily dosing regimen was generally slightly superior, but by not more than about 0.5 mm Hg to 1 mm Hg. After 2 mg to 16 mg doses of perindopril, the trough mean systolic and diastolic blood pressure effects were about 75 to 100% of peak effects. Perindopril’s effects on blood pressure were similar when given alone or on a background of 25 mg hydrochlorothiazide.
In general, the effect of perindopril occurred promptly, with effects increasing slightly over several weeks. Formal interaction studies of perindopril erbumine have not been carried out with antihypertensive agents other than thiazides. Limited experience in controlled and uncontrolled trials coadministering perindopril erbumine with a calcium channel blocker, a loop diuretic or triple therapy (beta-blocker, vasodilator and a diuretic), does not suggest any unexpected interactions.
In general, ACE inhibitors have less than additive effects when given with beta-adrenergic blockers, presumably because both work in part through the renin angiotensin system. In uncontrolled studies in patients with insulin-dependent diabetes, perindopril did not appear to affect glycemic control. In long-term use, no effect on urinary protein excretion was seen in these patients.
The effectiveness of perindopril erbumine was not influenced by sex and it was less effective in black patients than in nonblack patients. In elderly patients (greater than or equal to 60 years), the mean blood pressure effect was somewhat smaller than in younger patients, although the difference was not significant.
14.2Stable Coronary Artery Disease The EURopean trial On reduction of cardiac events with Perindopril in stable coronary Artery disease (EUROPA) was a multicenter, randomized, double-blind and placebo-controlled study conducted in 12,218 patients who had evidence of stable coronary artery disease without clinical heart failure. Patients had evidence of coronary artery disease documented by previous myocardial infarction more than 3 months before screening, coronary revascularization more than 6 months before screening, angiographic evidence of stenosis (at least 70% narrowing of one or more major coronary arteries), or positive stress test in men with a history of chest pain.
After a run-in period of 4 weeks during which all patients received perindopril 2 mg to 8 mg, the patients were randomly assigned to perindopril 8 mg once daily (n=6,110) or matching placebo (n=6,108). The mean follow-up was 4.2 years. The study examined the long-term effects of perindopril on time to first event of cardiovascular mortality, nonfatal myocardial infarction, or cardiac arrest in patients with stable coronary artery disease.
The mean age of patients was 60 years; 85% were male, 92% were taking platelet inhibitors, 63% were taking β blockers, and 56% were taking lipid-lowering therapy. The EUROPA study showed that perindopril significantly reduced the relative risk for the primary endpoint events (Table 1). This beneficial effect is largely attributable to a reduction in the risk of nonfatal myocardial infarction.
This beneficial effect of perindopril on the primary outcome was evident after about one year of treatment (Figure 1). The outcome was similar across all predefined subgroups by age, underlying disease or concomitant medication (Figure 2). Table 1.
Primary Endpoint and Relative Risk Reduction Perindopril (N = 6,110) Placebo (N = 6,108) RRR (95% CI) P CI=confidence interva… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity: No evidence of carcinogenic effect was observed in studies in rats and mice when perindopril was administered at dosages up to 20 times (mg/kg) or 2 to 4 times (mg/m 2 ) the maximum proposed clinical doses (16 mg/day) for 104 weeks. Mutagenesis: No genotoxic potential was detected for perindopril erbumine, perindoprilat and other metabolites in various in vitro and in vivo investigations, including the Ames test, the Saccharomyces cerevisiae D4 test, cultured human lymphocytes, TK ± mouse lymphoma assay, mouse and rat micronucleus tests and Chinese hamster bone marrow assay.
Impairment of Fertility: There was no meaningful effect on reproductive performance or fertility in the rat given up to 30 times (mg/kg) or 6 times (mg/m 2 ) the proposed maximum clinical dosage of perindopril erbumine during the period of spermatogenesis in males or oogenesis and gestation in females.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity: No evidence of carcinogenic effect was observed in studies in rats and mice when perindopril was administered at dosages up to 20 times (mg/kg) or 2 to 4 times (mg/m 2 ) the maximum proposed clinical doses (16 mg/day) for 104 weeks. Mutagenesis: No genotoxic potential was detected for perindopril erbumine, perindoprilat and other metabolites in various in vitro and in vivo investigations, including the Ames test, the Saccharomyces cerevisiae D4 test, cultured human lymphocytes, TK ± mouse lymphoma assay, mouse and rat micronucleus tests and Chinese hamster bone marrow assay.
Impairment of Fertility: There was no meaningful effect on reproductive performance or fertility in the rat given up to 30 times (mg/kg) or 6 times (mg/m 2 ) the proposed maximum clinical dosage of perindopril erbumine during the period of spermatogenesis in males or oogenesis and gestation in females.
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 2 mg (100 Tablet Bottle) NDC 65862-286-01 Rx only Perindopril Erbumine Tablets USP 2 mg AUROBINDO 100 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 2 mg (100 Tablet Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 4 mg (100 Tablet Bottle) NDC 65862-287-01 Rx only Perindopril Erbumine Tablets USP 4 mg AUROBINDO 100 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 4 mg (100 Tablet Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 8 mg (100 Tablet Bottle) NDC 65862-288-01 Rx only Perindopril Erbumine Tablets USP 8 mg AUROBINDO 100 Tablets PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 8 mg (100 Tablet Bottle)
Medicaid utilization & spend
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What "drug for further processing" means
FDA lists this package under the "drug for further processing" marketing category: Aurobindo Pharma Limited supplies it to other companies for further processing or repackaging (blister cards that are later repackaged or co-packaged are a common example). The units themselves are a finished dosage form — which is why pricing or Medicaid data can still appear — but this exact package code may not be the presentation a retail pharmacy dispenses.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |