
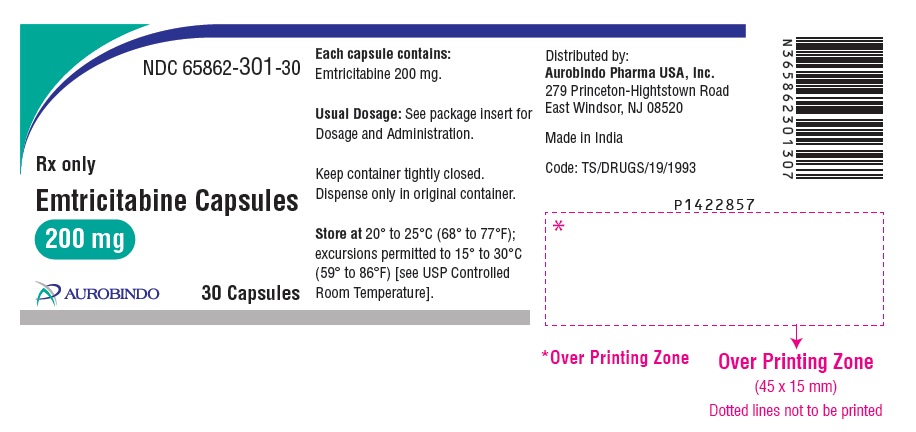
Emtricitabine 200 mg Capsule, 2,500-count
🆔 Identity & classification
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Emtricitabine doesn't cure HIV, but it's an important part of keeping the virus under control. It works by blocking an enzyme HIV needs to make copies of itself. When it's used alo...
- What exactly does emtricitabine do — does it cure HIV?
- Please don't stop without talking to your doctor first. If you also have hepatitis B, stopping emtricitabine can trigger a sudden, severe flare of hepatitis B — sometimes serious e...
- Can I stop taking emtricitabine if I feel fine or if I also have hepatitis B?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Emtricitabine — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 5138Q19F1X
Ammonia is a colorless gas made from nitrogen and hydrogen. It's used in medicines as a pH buffer to maintain the correct acidity level and help keep the product stable.
-
UNII 68401960MK
Crospovidone is a synthetic polymer made from polyvinylpyrrolidone. It acts as a disintegrant, helping tablets break apart quickly in the stomach so the medicine dissolves and absorbs into the body.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII W7YXH6D4BD
A plant-derived cellulose processed into tiny crystals. It serves as a binder to hold tablet ingredients together and as a filler to give the medicine its shape and size.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII RDH86HJV5Z
Povidone K90 is a synthetic polymer made from a chemical called vinyl pyrrolidone. It acts as a binder to hold pill ingredients together and as a dispersant to help the medicine break down and dissolve properly in your body.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
13 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| emtricitabine 200 mg 69097-0642-02 | Cipla | 30 capsules | $12.486 | AB | Availability likely | — |
| Emtriva 200 mg 61958-0601-01 | Gilead | 30 capsules | $17.446 | AB | Availability likely | — |
| Emtricitabine 200 mgthis 65862-0301-26 | Aurobindo | 2500 capsules | — | — | FDA listed | — |
| Emtricitabine 200 mg 46014-6010-01 | Excella | 30 capsules | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 65862-0301-05 | 500 CAPSULE in 1 BOTTLE (65862-301-05) | — | — | 2023-03-15 | Active |
| 65862-0301-30 | 30 CAPSULE in 1 BOTTLE (65862-301-30) | $12.49 / ea | $374.59 | 2023-03-15 | Active |
| 65862-0301-26 You're viewing this | 2500 CAPSULE in 1 BAG (65862-301-26) | — | — | — | Active |
You're viewing the largest of 3 pack sizes for this product.
This pack shows little to no recent Medicaid volume — the 30 capsules pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 65862-0301-26?
What is the difference between NDC 65862-0301-26 and NDC 65862-0301-30?
What NDC number is used to bill for this package of Emtricitabine 200 mg Capsule?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What "drug for further processing" means
FDA lists this package under the "drug for further processing" marketing category: Aurobindo Pharma Limited supplies it to other companies for further processing or repackaging (blister cards that are later repackaged or co-packaged are a common example). The units themselves are a finished dosage form — which is why pricing or Medicaid data can still appear — but this exact package code may not be the presentation a retail pharmacy dispenses.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Is this NDC FDA-approved?
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Where does this data come from?
📄 Full FDA label FDA SPL
🚨 Boxed Warning ▾
WARNING: POSTTREATMENT ACUTE EXACERBATION OF HEPATITIS B Severe acute exacerbations of hepatitis B (HBV) have been reported in patients who are coinfected with HIV-1 and HBV and have discontinued emtricitabine. Hepatic function should be monitored closely with both clinical and laboratory follow-up for at least several months in patients who are coinfected with HIV-1 and HBV and discontinue emtricitabine. If appropriate, initiation of anti-hepatitis B therapy may be warranted [see Warnings and Precautions (5.1) ] .
WARNING: POSTTREATMENT ACUTE EXACERBATION OF HEPATITIS B See full prescribing information for complete boxed warning. Severe acute exacerbations of Hepatitis B (HBV) have been reported in patients coinfected with HIV-1 and HBV who have discontinued emtricitabine. Hepatic function should be monitored closely in patients coinfected with HIV-1 and HBV who discontinue emtricitabine.
If appropriate, initiation of anti-hepatitis B therapy may be warranted. ( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Emtricitabine capsules are indicated in combination with other antiretroviral agents for the treatment of HIV-1 infection. Emtricitabine, a nucleoside analog HIV-1 reverse transcriptase inhibitor, is indicated in combination with other antiretroviral agents for the treatment of HIV-1 infection. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Testing: Prior to or when initiating emtricitabine capsules test for hepatitis B virus infection. ( 2.1 ) Emtricitabine capsules may be taken without regard to food. ( 2.2 ) Adult Patients (18 years of age and older) ( 2.3 ): One 200 mg capsule administered once daily orally.
Pediatric Patients (3 months through 17 years of age) ( 2.5 ): For children weighing more than 33 kg who can swallow an intact capsule, one 200 mg capsule administered once daily orally. Dose interval adjustment in adult patients with renal impairment ( 2.6 ): Formulation Creatinine Clearance (mL/min) ≥50 mL/min 30 to 49 mL/min 15 to 29 mL/min <15 mL/min or on hemodialysis a Capsule (200 mg) 200 mg every 24 hours 200 mg every 48 hours 200 mg every 72 hours 200 mg every 96 hours a. Hemodialysis Patients: If dosing on day of dialysis, give dose after dialysis.
2.1Testing Prior to Initiation of Treatment with Emtricitabine Capsules Prior to or when initiating emtricitabine capsules, test patients for hepatitis B virus infection [see Warnings and Precautions (5.1) ].
2.2Recommended Dosage Emtricitabine capsules are taken by mouth once daily and may be taken without regard to food [see Clinical Pharmacology (12.3) ].
2.3Recommended Dosage in Adult Patients (18 years of age and older) One 200 mg capsule administered once daily orally.
2.5Recommended Dosage in Pediatric Patients (3 months through 17 years of age) For pediatric patients weighing more than 33 kg who can swallow an intact capsule, one 200 mg capsule administered once daily orally.
2.6Dosage Adjustment in Patients with Renal Impairment Table 1 provides dosage interval adjustment for patients with renal impairment. No dosage adjustment is necessary for patients with mild renal impairment (creatinine clearance 50 to 80 mL/min). The safety and effectiveness of dose adjustment recommendations in patients with moderate to severe renal impairment (creatinine clearance below 50 mL/min) have not been clinically evaluated.
Therefore, clinical response to treatment and renal function should be closely monitored in these patients [see Warnings and Precautions (5.4) , Use in Specific Populations (8.6) ]. Table 1 Dose Interval Adjustment for Adult Patients with Altered Creatinine Clearance a. Hemodialysis Patients: If dosing on day of dialysis, give dose after dialysis.
Formulation Creatinine Clearance (mL/min) ≥50 mL/min 30 to 49 mL/min 15 to 29 mL/min <15 mL/min or on hemodialysis a Capsule (200 mg) 200 mg every 24 hours 200 mg every 48 hours 200 mg every 72 hours 200 mg every 96 hours There are insufficient data available to make dosage recommendations in pediatric patients with renal impairment.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Emtricitabine Capsules, 200 mg are cream cap/cream body, size ‘1’ hard gelatin capsule filled with white to off-white granular powder and imprinted with ‘F’ on cap and ‘36’ on body with black ink. Capsules: 200 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Emtricitabine capsules are contraindicated in patients with previously demonstrated hypersensitivity to any of the components of the products. Emtricitabine capsules are contraindicated in patients with previously demonstrated hypersensitivity to any of the components of the products. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Immune reconstitution syndrome: May necessitate further evaluation and treatment. ( 5.2 ) Lactic acidosis/severe hepatomegaly with steatosis: Discontinue treatment in patients who develop symptoms or laboratory findings suggestive of lactic acidosis or pronounced hepatotoxicity. ( 5.3 )
5.1Severe Acute Exacerbation of Hepatitis B in Patients Coinfected with HIV-1 and HBV All patients should be tested for the presence of chronic Hepatitis B virus (HBV) before or when initiating emtricitabine [see Dosage and Administration (2.1) ]. Severe acute exacerbations of hepatitis B (e.g., liver decompensation and liver failure) have been reported in patients who are coinfected with HIV-1 and HBV and have discontinued emtricitabine. Patients who are coinfected with HIV-1 and HBV who discontinue emtricitabine should be closely monitored with both clinical and laboratory follow-up for at least several months after stopping treatment.
If appropriate, initiation of anti-hepatitis B therapy may be warranted, especially in patients with advanced liver disease or cirrhosis, since posttreatment exacerbation of hepatitis may lead to hepatic decompensation and liver failure.
5.2Immune Reconstitution Syndrome Immune reconstitution syndrome has been reported in patients treated with combination antiretroviral therapy, including emtricitabine. During the initial phase of combination antiretroviral treatment, patients whose immune system responds may develop an inflammatory response to indolent or residual opportunistic infections (such as Mycobacterium avium infection, cytomegalovirus, Pneumocystis jirovecii pneumonia [PCP], or tuberculosis), which may necessitate further evaluation and treatment.
Autoimmune disorders (such as Graves' disease, polymyositis, and Guillain-Barré syndrome) have also been reported to occur in the setting of immune reconstitution; however, the time to onset is more variable, and can occur many months after initiation of treatment.
5.3Lactic Acidosis/Severe Hepatomegaly with Steatosis Lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported with the use of nucleoside analogs, including FTC, alone or in combination with other antiretrovirals. Treatment with emtricitabine should be suspended in any patient who develops clinical or laboratory findings suggestive of lactic acidosis or pronounced hepatotoxicity (which may include hepatomegaly and steatosis even in the absence of marked transaminase elevations).
5.4Dose Adjustment in Patients with New Onset or Worsening Renal Impairment Emtricitabine is principally eliminated by the kidney. Reduction of the dosage of emtricitabine is recommended for patients with impaired renal function [see Dosage and Administration (2.6) , Use in Specific Populations (8.6) , and Clinical Pharmacology (12.3) ] .
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in other sections of the labeling: Severe Acute Exacerbation of Hepatitis B in Patients Coinfected with HIV-1 and HBV [see Warnings and Precautions (5.1) ] . Immune Reconstitution Syndrome [see Warnings and Precautions (5.2) ] . Lactic Acidosis/Severe Hepatomegaly with Steatosis [see Warnings and Precautions (5.3) ].
Most common adverse reactions (incidence ≥10%) are headache, diarrhea, nausea, fatigue, dizziness, depression, insomnia, abnormal dreams, rash, abdominal pain, asthenia, increased cough, and rhinitis. Skin hyperpigmentation was very common (≥10%) in pediatric patients. ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse Reactions from Clinical Trials Experience in Adults More than 2,000 adult subjects with HIV-1 infection have been treated with emtricitabine alone or in combination with other antiretroviral agents for periods of 10 days to 200 weeks in clinical trials.
The most common adverse reactions (incidence greater than or equal to 10%, any severity) identified from any of the three large, controlled clinical trials include headache, diarrhea, nausea, fatigue, dizziness, depression, insomnia, abnormal dreams, rash, abdominal pain, asthenia, increased cough, and rhinitis. In Trials 301A and 303, the most common adverse reactions that occurred in subjects receiving emtricitabine with other antiretroviral agents were headache, diarrhea, nausea, and rash, which were generally mild to moderate.
Approximately 1% of subjects discontinued participation in the clinical trials due to these events. All adverse reactions were reported with similar frequency in emtricitabine and control treatment groups except for skin discoloration, which was reported with higher frequency in the emtricitabine-treated group. Skin discoloration, manifested by hyperpigmentation on the palms or soles, was generally mild and asymptomatic.
The mechanism and clinical significance are unknown. A summary of emtricitabine treatment-emergent clinical adverse reactions in Trials 301A and 303 is provided in Table 2. Table 2 Selected Treatment-Emergent Adverse Reactions (All Grades, Regardless of Causality) Reported in ≥3% of Emtricitabine-Treated Subjects in Either Trial 301A or 303 (0 to 48 Weeks) AZT=zidovudine; d4T=stavudine; NNRTI/PI=non-nucleoside reverse transcriptase inhibitor/protease inhibitor; 3TC=lamivudine; EFV=efavirenz. a.
Rash event includes rash, pruritus, maculopapular rash, urticaria, vesiculobullous rash, pustular rash, and allergic reaction. 303 301A Emtricitabine + AZT/d4T + NNRTI/PI (N=294) 3TC + AZT/d4T + NNRTI/PI (N=146) Emtricitabine + didanosine + EFV (N=286) d4 T + didanosine + EFV (N=285) Body as a Whole Asthenia 16% 10% 12% 17% Headache 13% 6% 22% 25% Abdominal pain 8% 11% 14% 17% Digestive System Diarrhea 23% 18% 23% 32% Nausea 18% 12% 13% 23% Vomiting 9% 7% 9% 12% Dyspepsia 4% 5% 8% 12% Musculoskeletal Myalgia 4% 4% 6% 3% Arthralgia 3% 4% 5% 6% Nervous System Insomnia 7% 3% 16% 21% Depressive disorders 6% 10% 9% 13% Paresthesia 5% 7% 6% 12% Dizziness 4% 5% 25% 26% Neuropathy/peripheral neuritis 4% 3% 4% 13% Abnormal dreams 2% <1% 11% 19% Respiratory Rhinitis 18% 12% 12% 10% Increased cough 14% 11% 14% 8% Skin Rash event a 17% 14% 30% 33% Laboratory Abnormalities : Laboratory abnormalities in these trials occurred with similar frequency in the emtricitabine and comparator groups.
A summary of Grades 3 to 4 laboratory abnormalities is provided in Table 3. Table 3 Treatment-Emergent Grades 3 to 4 Laboratory Abnormalities Reported in ≥1% of Emtricitabine-Treated Sub…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS The potential for drug interactions with emtricitabine has been studied in combination with AZT, indinavir, d4T, famciclovir, and tenofovir DF (TDF). There were no clinically significant drug interactions for any of these drugs. Drug interactions trials are described elsewhere in the labeling [see Clinical Pharmacology (12.3) ].
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Breastfeeding is not recommended. ( 8.2 ) Pediatrics: Dose adjustment based on age and weight. ( 2.5 , 12.3 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to emtricitabine during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Available data from the APR show no increase in the overall risk of major birth defects with first trimester exposure for emtricitabine (FTC) (2.3%) compared with the background rate for major birth defects of 2.7% in a U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP) (see Data) .
The rate of miscarriage for individual drugs is not reported in the APR. In the U.S. general population, the estimated background risk of miscarriage in clinically recognized pregnancies is 15 to 20%. In animal reproduction studies, no adverse developmental effects were observed when FTC was administered at exposures ≥60 times that of the recommended daily dose of emtricitabine (see Data) .
Data Human Data Based on prospective reports to the APR of exposures to FTC-containing regimens during pregnancy resulting in live births (including over 2,700 exposed in the first trimester and over 1,200 exposed in the second/third trimester), there was no increase between FTC and overall birth defects compared with the background birth defect rate of 2.7% in a U.S. reference population of the MACDP. The prevalence of birth defects in live births was 2.4% (95% CI: 1.9% to 3.1%) with first trimester exposure to FTC-containing regimens and 2.3% (95% CI: 1.5% to 3.3%) with the second/third trimester exposure to FTC-containing regimens.
Prospective reports from the APR of overall major birth defects in pregnancies exposed to FTC are compared with a U.S. background major birth defect rate. Methodologic limitations of the APR include the use of MACDP as the external comparator group. Limitations of using an external comparator include differences in methodology and populations, as well as confounding due to the underlying disease.
Additionally, published observational studies on FTC exposure in pregnancy have not shown an increased risk for major malformations. Animal Data FTC was administered orally to pregnant mice (at 0, 250, 500, or 1,000 mg/kg/day), and rabbits (at 0, 100, 300, or 1,000 mg/kg/day) through organogenesis (on gestation days 6 through 15, and 7 through 19, respectively). No significant toxicological effects were observed in embryo-fetal toxicity studies performed with FTC in mice at exposures (AUC) approximately 60 times higher and in rabbits at approximately 120 times higher than human exposures at the recommended daily dose.
In a pre/postnatal development study in mice, FTC was administered orally at doses up to 1,000 mg/kg/day; no significant adverse effects directly related to drug were observed in the offspring exposed daily from before birth ( in utero ) through sexual maturity at daily exposures (AUC) of approximately 60 times higher than human exposures at the recommended daily dose.
8.2Lactation Risk Summary The Centers for Disease Control and Prevention recommend that HIV-1 infected mothers not breastfeed their infants to avoid risking postnatal transmission of HIV-1. Based on published data, FTC has been shown to be present in human breast milk. It is not known if FTC affects milk production or has effects on the breastfed child.
Because of the potential for: (1) HIV transmission (in HIV-negative infants); (2) developing viral resistance (in HIV-positive infants); and (3) adverse reactions in a breastfed infant similar to those seen in adults, instruct mothers not to breastfeed if they are taking emtricitabine.
8.4Pediatric Use The safety and efficacy of FTC in patients between 3 months and 21 years of age is supported by data from three open-lab…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to emtricitabine during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Available data from the APR show no increase in the overall risk of major birth defects with first trimester exposure for emtricitabine (FTC) (2.3%) compared with the background rate for major birth defects of 2.7% in a U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP) (see Data) .
The rate of miscarriage for individual drugs is not reported in the APR. In the U.S. general population, the estimated background risk of miscarriage in clinically recognized pregnancies is 15 to 20%. In animal reproduction studies, no adverse developmental effects were observed when FTC was administered at exposures ≥60 times that of the recommended daily dose of emtricitabine (see Data) .
Data Human Data Based on prospective reports to the APR of exposures to FTC-containing regimens during pregnancy resulting in live births (including over 2,700 exposed in the first trimester and over 1,200 exposed in the second/third trimester), there was no increase between FTC and overall birth defects compared with the background birth defect rate of 2.7% in a U.S. reference population of the MACDP. The prevalence of birth defects in live births was 2.4% (95% CI: 1.9% to 3.1%) with first trimester exposure to FTC-containing regimens and 2.3% (95% CI: 1.5% to 3.3%) with the second/third trimester exposure to FTC-containing regimens.
Prospective reports from the APR of overall major birth defects in pregnancies exposed to FTC are compared with a U.S. background major birth defect rate. Methodologic limitations of the APR include the use of MACDP as the external comparator group. Limitations of using an external comparator include differences in methodology and populations, as well as confounding due to the underlying disease.
Additionally, published observational studies on FTC exposure in pregnancy have not shown an increased risk for major malformations. Animal Data FTC was administered orally to pregnant mice (at 0, 250, 500, or 1,000 mg/kg/day), and rabbits (at 0, 100, 300, or 1,000 mg/kg/day) through organogenesis (on gestation days 6 through 15, and 7 through 19, respectively). No significant toxicological effects were observed in embryo-fetal toxicity studies performed with FTC in mice at exposures (AUC) approximately 60 times higher and in rabbits at approximately 120 times higher than human exposures at the recommended daily dose.
In a pre/postnatal development study in mice, FTC was administered orally at doses up to 1,000 mg/kg/day; no significant adverse effects directly related to drug were observed in the offspring exposed daily from before birth ( in utero ) through sexual maturity at daily exposures (AUC) of approximately 60 times higher than human exposures at the recommended daily dose.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and efficacy of FTC in patients between 3 months and 21 years of age is supported by data from three open-label, nonrandomized clinical trials in which FTC was administered to 169 HIV-1 infected treatment-naïve and experienced (defined as virologically suppressed on a 3TC containing regimen for which FTC was substituted for 3TC) subjects [see Clinical Studies (14.4) ] . The pharmacokinetics of FTC were studied in 20 neonates born to HIV-1 positive mothers [see Clinical Studies (14.4) ] .
All neonates were HIV-1 negative at the end of the trial; the efficacy of FTC in preventing or treating HIV-1 could not be determined.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of emtricitabine did not include sufficient numbers of subjects aged 65 years and over to determine whether they respond differently from younger subjects. In general, dose selection for the elderly patient should be cautious, keeping in mind the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE If overdose occurs, the patient should be monitored for evidence of toxicity, and standard supportive treatment applied as necessary. Hemodialysis treatment removes approximately 30% of the FTC dose over a 3-hour dialysis period starting within 1.5 hours of FTC dosing (blood flow rate of 400 mL/min and a dialysate flow rate of 600 mL/min). It is not known whether FTC can be removed by peritoneal dialysis.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Emtricitabine is an antiretroviral drug [see Microbiology (12.4) ] .
12.3Pharmacokinetics Adults The pharmacokinetic properties of FTC were evaluated in healthy subjects and HIV-1-infected subjects. Emtricitabine pharmacokinetics are similar between these populations. Figure 1 shows the mean steady-state plasma FTC concentration-time profile in 20 HIV‑1-infected subjects receiving emtricitabine capsules.
Figure 1 Mean ( ± 95% CI) Steady-State Plasma FTC Concentrations in HIV‑1 Infected Adults (N=20) Absorption Emtricitabine is rapidly and extensively absorbed following oral administration, with peak plasma concentrations occurring at 1 to 2 hours postdose. Following multiple dose oral administration of emtricitabine capsules to 20 HIV-1 infected subjects, the (mean ± SD) steady-state plasma FTC peak concentration (C max ) was 1.8 ± 0.7 mcg/mL and the area-under the plasma concentration-time curve over a 24-hour dosing interval (AUC) was 10.0 ± 3.1 mcg·hr/mL.
The mean steady-state plasma trough concentration at 24 hours postdose was 0.09 mcg/mL. The mean absolute bioavailability of emtricitabine capsules was 93%, while the mean absolute bioavailability of emtricitabine oral solution was 75%. The relative bioavailability of emtricitabine oral solution was approximately 80% of emtricitabine capsules.
The multiple dose pharmacokinetics of FTC are dose proportional over a dose range of 25 to 200 mg. Distribution In vitro binding of FTC to human plasma proteins was less than 4% and independent of concentration over the range of 0.02 to 200 mcg/mL. At peak plasma concentration, the mean plasma to blood drug concentration ratio was ~1.0 and the mean semen to plasma drug concentration ratio was ~4.0.
Metabolism Following administration of radiolabelled FTC, complete recovery of the dose was achieved in urine (~86%) and feces (~14%). Thirteen percent (13%) of the dose was recovered in urine as three putative metabolites. The biotransformation of FTC includes oxidation of the thiol moiety to form the 3’-sulfoxide diastereomers (~9% of dose) and conjugation with glucuronic acid to form 2’-O-glucuronide (~4% of dose).
No other metabolites were identifiable. Elimination The plasma FTC half-life is approximately 10 hours. The renal clearance of FTC is greater than the estimated creatinine clearance, suggesting elimination by both glomerular filtration and active tubular secretion.
There may be competition for elimination with other compounds that are also renally eliminated. Effects of Food on Oral Absorption Emtricitabine capsules and oral solution may be taken with or without food. Emtricitabine systemic exposure (AUC) was unaffected while C max decreased by 29% when emtricitabine capsules were administered with food (an approximately 1000 kcal high-fat meal).
Emtricitabine systemic exposure (AUC) and C max were unaffected when 200 mg emtricitabine oral solution was administered with either a high-fat or low-fat meal. Specific Populations Geriatric Patients The pharmacokinetics of FTC have not been fully evaluated in the elderly (65 years of age and older). Pediatric Patients The pharmacokinetics of FTC at steady state were determined in 77 HIV-1 infected pediatric subjects, and the pharmacokinetic profile was characterized in four age groups (Table 6).
The FTC exposure achieved in pediatric subjects receiving a daily dose of 6 mg/kg up to a maximum of 240 mg oral solution or a 200 mg capsule is similar to exposures achieved in adult subjects receiving a once-daily dose of 200 mg. The pharmacokinetics of FTC were studied in 20 neonates born to HIV-1 positive mothers. Each mother received prenatal and intrapartum combination antiretroviral therapy.
Neonates received up to 6 weeks of AZT prophylactically after birth. The neonates were administered two short courses of FTC oral solution (each 3 mg/kg once daily × 4 days) during the first 3 months of life. The AUC observed in neonates who rece…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Emtricitabine is an antiretroviral drug [see Microbiology (12.4) ] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Emtricitabine Capsules, 200 mg are cream cap/cream body, size ‘1’ hard gelatin capsule filled with white to off-white granular powder and imprinted with ‘F’ on cap and ‘36’ on body with black ink. Bottles of 30 NDC 65862-301-30 Bottles of 500 NDC 65862-301-05 Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Keep container tightly closed.
📋 Description ▾
11 DESCRIPTION Emtricitabine (FTC) is a synthetic nucleoside analog with activity against human immunodeficiency virus type 1 (HIV-1) reverse transcriptase. The chemical name of FTC is 5-fluoro-1-(2 R ,5 S )-[2-(hydroxymethyl)-1,3-oxathiolan-5-yl]cytosine. Emtricitabine is the (-) enantiomer of a thio analog of cytidine, which differs from other cytidine analogs in that it has a fluorine in the 5-position.
It has a molecular formula of C 8 H 10 FN 3 O 3 S and a molecular weight of 247.24. It has the following structural formula: Emtricitabine is a white to off-white powder with a solubility of approximately 112 mg/mL in water at 25°C. The partition coefficient (log P) for FTC is −0.43 and the pKa is 2.65.
Emtricitabine capsules are for oral administration. Each capsule contains 200 mg of FTC and the inactive ingredients: crospovidone, gelatin, magnesium stearate, microcrystalline cellulose, povidone, sodium lauryl sulphate, titanium dioxide and yellow iron oxide. The capsules are imprinted with edible ink containing black iron oxide, potassium hydroxide, propylene glycol, shellac and strong ammonia solution.
Figure1
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information). Severe Acute Exacerbation of Hepatitis B in Patients Coinfected with HIV-1 and HBV Inform patients that severe acute exacerbations of hepatitis B have been reported in patients who are coinfected with HIV-1 and hepatitis B virus (HBV) who have discontinued emtricitabine. Advise patients not to discontinue emtricitabine without first informing their healthcare provider.
All patients should be tested for HBV infection before or when starting emtricitabine and those who are infected with HBV need close medical follow-up for several months after stopping emtricitabine to monitor for exacerbations of hepatitis [see Warnings and Precautions (5.1) ]. Immune Reconstitution Syndrome Inform patients that in some patients with advanced HIV infection (AIDS), signs and symptoms of inflammation from previous infections may occur soon after anti-HIV treatment is started. It is believed that these symptoms are due to an improvement in the body's immune response, enabling the body to fight infections that may have been present with no obvious symptoms.
Advise patients to inform their healthcare provider immediately of any symptoms of infection [see Warnings and Precautions (5.2) ]. Lactic Acidosis and Severe Hepatomegaly Inform patients that lactic acidosis and severe hepatomegaly with steatosis, including fatal cases, have been reported. Treatment with emtricitabine should be suspended in any patient who develops clinical symptoms suggestive of lactic acidosis or pronounced hepatotoxicity [see Warnings and Precautions (5.3) ].
Pregnancy Registry Inform patients that there is an antiretroviral pregnancy registry to monitor fetal outcomes of pregnant women exposed to emtricitabine [see Use in Specific Populations (8.1 )]. Lactation Instruct mothers not to breastfeed if they are taking emtricitabine because of the risk of passing the HIV-1 virus to the baby [see Use in Specific Populations (8.2) ] .