
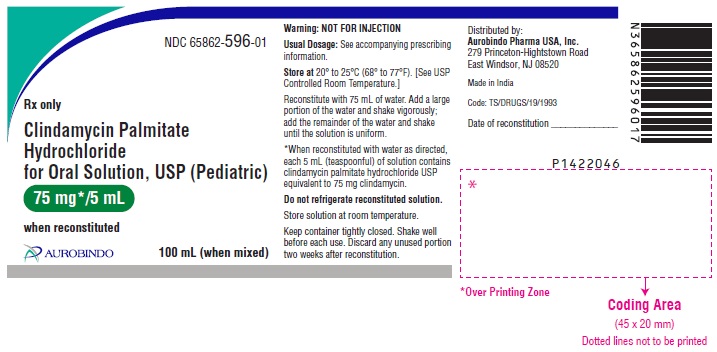
Clindamycin Palmitate Hydrochloride (Pediatric) 75 mg/5mL Solution — NDC 65862-596-01 (Billing 65862-0596-01)
This is a package of Clindamycin Palmitate Hydrochloride (Pediatric) 75 mg/5mL Solution from Aurobindo Pharma Limited, marketed since Apr 2013 and currently FDA-listed; retail pharmacies pay about $0.1288 per mL (NADAC).
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 009346
- GCN: 40860
- GPI-14 (Medi-Span): 16220020222120
- HICL (First Databank): 019818
- AHFS class code: 08:12.28.20
- RxCUI (RxNorm): 562266
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Lincosamide Antibacterial class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Clindamycin is used to treat certain types of bacterial infections. Clindamycin is in a class of medications called lincomycin antibiotics. It works by slowing or stopping the growth of bacteria. Antibiotics such as clindamycin will not work for colds, flu, or other viral infections. Using antibiotics when they are not needed increases your risk of getting an infection later that resists antibiotic treatment.
Read the full MedlinePlus article ↗- It treats serious bacterial infections, such as anaerobic infections, skin, lung, abdominal, gynecological, and bone and joint infections, depending on the product. It is often use...
- Swallow them with a full glass of water and stay upright for at least 30 minutes afterward. This helps prevent irritation of your throat. Take it as often as your prescriber says a...
- Rash, nausea, vomiting, stomach pain and itching are among the more commonly reported effects. Call your doctor right away if you get severe, watery or bloody diarrhea, even weeks...
- What side effects are normal, and when should I call you?
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.129 | $12.88 / 100 ml |
| Medicaid paysCMS SDUD · 12 mo | $0.1953 | $19.53 / 100 ml |
| Medicare drug plans payPart D · Q2 2026 | $0.2712 | $27.12 / 100 ml |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 65862-0596-01 You're viewing this | 1 BOTTLE in 1 CARTON / 100 mL in 1 BOTTLE | $0.1288 / mL | $12.88 | 2013-04-30 | — | Active |
| 65862-0596-02 65862-596-02 Main listing | 1 BOTTLE, PLASTIC in 1 CARTON / 100 mL in 1 BOTTLE, PLASTIC | $0.1288 / mL | $12.88 | 2022-11-14 | — | Active |
This pack has the lowest per-mL cost of the 2 priced pack sizes ($0.1288 NADAC).
This pack accounts for about 2.3% of this product's recent Medicaid fills; most go to a different pack size. See all packs ↓
Pack size FAQ
What quantity is in this package?
What NDC number is used to bill for this package of Clindamycin Palmitate Hydrochloride (Pediatric) 75 mg/5mL Solution?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Clindamycin Palmitate Hydrochloride (Pediatric) 75 mg/5mL 16714-0483-01 | NorthStar | 1 bottle | $0.129 | AA | Availability likely | — |
| clindamycin palmitate hydrochloride 75 mg/5mL 23155-0603-51 | Heritage | 1 bottle | $0.129 | AA | Availability likely | — |
| Clindamycin Palmitate Hydrochloride (Pediatric) 75 mg/5mL 53746-0468-19 | Amneal | 1 bottle | $0.129 | — | Availability likely | — |
| CLINDAMYCIN PALMITATE HYDROCHLORIDE (Pediatric) 75 mg/5mL 64980-0511-10 | Rising | 100 ml | $0.129 | AA | Availability likely | — |
| Clindamycin Palmitate Hydrochloride (Pediatric) 75 mg/5mL 65162-0468-19 | Amneal | 1 bottle | $0.129 | — | Discontinued | — |
| Clindamycin Palmitate Hydrochloride (Pediatric) 75 mg/5mLthis 65862-0596-01 | Aurobindo | 1 bottle | $0.129 | AA | Availability likely | — |
| Cleocin Pediatric 75 mg/5mL 00009-0760-04 | Pharmacia | 1 bottle | — | AA | Discontinued | — |
| Clindamycin Palmitate Hydrochloride 75 mg/5mL 62135-0926-01 | Chartwell | 100 ml | — | AA | FDA listed | — |
| CLINDAMYCIN PALMITATE HYDROCHLORIDE (Pediatric) 75 mg/5mL 63629-2391-01 | Bryant | 100 ml | — | AA | FDA listed | — |
| CLINDAMYCIN PALMITATE HYDROCHLORIDE (Pediatric) 75 mg/5mL 72162-1809-01 | Bryant | 100 ml | — | AA | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII BUC5I9595W
A natural flavoring derived from cherry fruit that gives the medicine its cherry taste. It helps mask bitter drug flavors and makes the medication more pleasant to take.
-
UNII 92RU3N3Y1O
Dimethicone is a silicone-based oil that acts as an anti-foaming agent and lubricant in medicines. It reduces gas bubbles in liquid formulations and helps coat and protect the stomach lining when ingested.
-
UNII 14255EXE39
Ethylparaben is a preservative, a chemical that stops bacteria and mold from growing in the medicine. It keeps the product safe and effective throughout its shelf life.
-
UNII 2NX48Z0A9G
Icodextrin is a glucose polymer derived from starch. It acts as a thickening agent and osmotic agent in medicines, helping to control texture and absorption in formulations like eye drops or injectable solutions.
-
UNII ND2M416302
Isopropyl alcohol is a clear liquid solvent derived from petroleum. In medicines, it dissolves active ingredients and other components, helps the product flow smoothly, and aids in sterilization during manufacturing.
-
UNII LQA7B6G8JG
A synthetic polymer made by combining water-soluble compounds. It acts as a surfactant and solubilizer to help mix oil and water-based ingredients, improving the medicine's texture and how active ingredients dissolve.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING Clostridium difficile associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including clindamycin and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C.difficile . Because clindamycin therapy has been associated with severe colitis which may end fatally, it should be reserved for serious infections where less toxic antimicrobial agents are inappropriate, as described in the INDICATIONS AND USAGE section.
It should not be used in patients with nonbacterial infections such as most upper respiratory tract infections. C.difficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin producing strains of C.difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy.
CDAD must be considered in all patients who present with diarrhea following antibiotic use. Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents. If CDAD is suspected or confirmed, ongoing antibiotic use not directed against C.difficile may need to be discontinued.
Appropriate fluid and electrolyte management, protein supplementation, antibiotic treatment of C.difficile , and surgical evaluation should be instituted as clinically indicated.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Clindamycin palmitate hydrochloride for oral solution (Pediatric) is indicated in the treatment of serious infections caused by susceptible anaerobic bacteria. Clindamycin is also indicated in the treatment of serious infections due to susceptible strains of streptococci, pneumococci and staphylococci. Its use should be reserved for penicillin-allergic patients or other patients for whom, in the judgment of the physician, a penicillin is inappropriate.
Because of the risk of colitis, as described in the BOXED WARNING , before selecting clindamycin the physician should consider the nature of the infection and the suitability of less toxic alternatives (e.g., erythromycin). Anaerobes: Serious respiratory tract infections such as empyema, anaerobic pneumonitis and lung abscess; serious skin and soft tissue infections; septicemia; intra-abdominal infections such as peritonitis and intra-abdominal abscess (typically resulting from anaerobic organisms resident in the normal gastrointestinal tract); infections of the female pelvis and genital tract such as endometritis, nongonococcal tubo-ovarian abscess, pelvic cellulitis and postsurgical vaginal cuff infection.
Streptococci: Serious respiratory tract infections; serious skin and soft tissue infections. Staphylococci: Serious respiratory tract infections; serious skin and soft tissue infections. Pneumococci: Serious respiratory tract infections.
Bacteriologic studies should be performed to determine the causative organisms and their susceptibility to clindamycin. To reduce the development of drug-resistant bacteria and maintain the effectiveness of clindamycin palmitate hydrochloride for oral solution (Pediatric) and other antibacterial drugs, clindamycin palmitate hydrochloride for oral solution (Pediatric) should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy.
In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION If significant diarrhea occurs during therapy, this antibiotic should be discontinued (see BOXED WARNING ). Concomitant administration of food does not adversely affect the absorption of clindamycin palmitate hydrochloride contained in clindamycin palmitate hydrochloride for oral solution (Pediatric). Serious infections: 8 to 12 mg/kg/day (4 to 6 mg/lb/day) divided into 3 or 4 equal doses.
Severe infections: 13 to 16 mg/kg/day (6.5 to 8 mg/lb/day) divided into 3 or 4 equal doses. More severe infections: 17 to 25 mg/kg/day (8.5 to 12.5 mg/lb/day) divided into 3 or 4 equal doses. In pediatric patients weighing 10 kg or less, ½ teaspoon (37.5 mg) three times a day should be considered the minimum recommended dose.
Clindamycin should be dosed based on total body weight regardless of obesity. Serious infections due to anaerobic bacteria are usually treated with clindamycin injection. However, in clinically appropriate circumstances, the physician may elect to initiate treatment or continue treatment with clindamycin palmitate hydrochloride for oral solution (Pediatric).
NOTE: In cases of β-hemolytic streptococcal infections, treatment should be continued for at least 10 days. Reconstitution Instructions When reconstituted with water as follows, each 5 mL (teaspoon) of solution contains clindamycin palmitate hydrochloride equivalent to 75 mg clindamycin. Reconstitute bottles of 100 mL with 75 mL of water.
Add a large portion of the water and shake vigorously; add the remainder of the water and shake until the solution is uniform. Storage Conditions Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.] Do NOT refrigerate the reconstituted solution; when chilled, the solution may thicken and be difficult to pour. The solution is stable for 2 weeks at room temperature.
⛔ Contraindications ▾
CONTRAINDICATIONS This drug is contraindicated in individuals with a history of hypersensitivity to preparations containing clindamycin or lincomycin.
⚠️ Warnings ▾
WARNINGS See BOXED WARNING . Clostridium difficile Associated Diarrhea Clostridium difficile associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including clindamycin palmitate hydrochloride for oral solution (Pediatric), and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile .
C. difficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy. CDAD must be considered in all patients who present with diarrhea following antibiotic use.
Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents. If CDAD is suspected or confirmed, ongoing antibiotic use not directed against C. difficile may need to be discontinued. Appropriate fluid and electrolyte management, protein supplementation, antibiotic treatment of C. difficile , and surgical evaluation should be instituted as clinically indicated.
Anaphylactic and Severe Hypersensitivity Reactions Anaphylactic shock and anaphylactic reactions have been reported (see ADVERSE REACTIONS ). Severe hypersensitivity reactions, including severe skin reactions such as toxic epidermal necrolysis (TEN), drug reaction with eosinophilia and systemic symptoms (DRESS), and Stevens-Johnson syndrome (SJS), some with fatal outcome, have been reported (see ADVERSE REACTIONS ). In case of such an anaphylactic or severe hypersensitivity reaction, discontinue treatment permanently and institute appropriate therapy.
A careful inquiry should be made concerning previous sensitivities to drugs and other allergens. Usage in Meningitis: Since clindamycin does not diffuse adequately into the cerebrospinal fluid, the drug should not be used in the treatment of meningitis.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The following reactions have been reported with the use of clindamycin. Infections and infestations: Clostridium difficile colitis Gastrointestinal: Abdominal pain, pseudomembranous colitis, esophagitis, nausea, vomiting and diarrhea (see BOXED WARNING ). The onset of pseudomembranous colitis symptoms may occur during or after antibacterial treatment (see WARNINGS ).
An unpleasant or metallic taste has been reported after oral administration. Hypersensitivity Reactions: Generalized mild to moderate morbilliform-like (maculopapular) skin rashes are the most frequently reported adverse reactions. Vesiculobullous rashes, as well as urticaria, have been observed during drug therapy.
Severe skin reactions such as Toxic Epidermal Necrolysis, some with fatal outcome, have been reported (See WARNINGS ). Cases of Acute Generalized Exanthematous Pustulosis (AGEP), erythema multiforme, some resembling Stevens-Johnson syndrome, anaphylactic shock, anaphylactic reaction and hypersensitivity have also been reported. Skin and Mucous Membranes: Pruritus, vaginitis, angioedema, and rare instances of exfoliative dermatitis have been reported.
(See Hypersensitivity Reactions .) Liver: Jaundice and abnormalities in liver function tests have been observed during clindamycin therapy. Renal: Although no direct relationship of clindamycin to renal damage has been established, renal dysfunction as evidenced by azotemia, oliguria, and/or proteinuria has been observed. Hematopoietic: Transient neutropenia (leukopenia) and eosinophilia have been reported.
Reports of agranulocytosis and thrombocytopenia have been made. No direct etiologic relationship to concurrent clindamycin therapy could be made in any of the foregoing. Immune system: Drug reaction with eosinophilia and systemic symptoms (DRESS) cases have been reported.
Musculoskeletal: Cases of polyarthritis have been reported.
🔄 Drug Interactions ▾
Drug Interactions Clindamycin has been shown to have neuromuscular blocking properties that may enhance the action of other neuromuscular blocking agents. Therefore, it should be used with caution in patients receiving such agents. Clindamycin is metabolized predominantly by CYP3A4, and to a lesser extent by CYP3A5, to the major metabolite clindamycin sulfoxide and minor metabolite N-desmethylclindamycin.
Therefore inhibitors of CYP3A4 and CYP3A5 may increase plasma concentrations of clindamycin and inducers of these isoenzymes may reduce plasma concentrations of clindamycin. In the presence of strong CYP3A4 inhibitors, monitor for adverse reactions. In the presence of strong CYP3A4 inducers such as rifampicin, monitor for loss of effectiveness.
In vitro studies indicate that clindamycin does not inhibit CYP1A2, CYP2C9, CYP2C19, CYP2E1 or CYP2D6 and only moderately inhibits CYP3A4.
🤰 Pregnancy ▾
Pregnancy In clinical trials with pregnant women, the systemic administration of clindamycin during the second and third trimesters, has not been associated with an increased frequency of congenital abnormalities. Clindamycin should be used during the first trimester of pregnancy only if clearly needed. There are no adequate and well-controlled studies in pregnant women during the first trimester of pregnancy.
Because animal reproduction studies are not always predictive of the human response, this drug should be used during pregnancy only if clearly needed. Reproduction studies performed in rats and mice using oral doses of clindamycin up to 600 mg/kg/day (3.2 and 1.6 times the highest recommended adult human dose based on mg/m 2 , respectively) or subcutaneous doses of clindamycin up to 250 mg/kg/day (1.3 and 0.7 times the highest recommended adult human dose based on mg/m 2 , respectively) revealed no evidence of teratogenicity.
🧒 Pediatric Use ▾
Pediatric Use When clindamycin palmitate hydrochloride for oral solution (Pediatric) is administered to the pediatric population (birth to 16 years), appropriate monitoring of organ system functions is desirable.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of clindamycin did not include sufficient numbers of patients age 65 and over to determine whether they respond differently from younger patients. However, other reported clinical experience indicates that antibiotic-associated colitis and diarrhea (due to Clostridium difficile ) seen in association with most antibiotics occur more frequently in the elderly (>60 years) and may be more severe. These patients should be carefully monitored for the development of diarrhea.
Pharmacokinetic studies with clindamycin have shown no clinically important differences between young subjects (18 to 39 years) and elderly subjects (61 to 79 years) with normal hepatic function and normal (age-adjusted) renal function after oral or intravenous administration.
🆘 Overdosage ▾
OVERDOSAGE Significant mortality was observed in mice at an intravenous dose of 855 mg/kg and in rats at an oral or subcutaneous dose of approximately 2618 mg/kg. In the mice, convulsions and depression were observed. Hemodialysis and peritoneal dialysis are not effective in removing clindamycin from the serum.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Human Pharmacology Absorption Blood level studies comparing clindamycin palmitate hydrochloride with clindamycin hydrochloride show that both drugs reach their peak active serum levels at the same time, indicating a rapid hydrolysis of the palmitate to the clindamycin. Serum level studies with clindamycin palmitate hydrochloride in normal pediatric patients weighing 50 to 100 lbs given 2, 3 or 4 mg/kg every 6 hours (8, 12 or 16 mg/kg/day) demonstrated mean peak clindamycin serum levels of 1.24, 2.25 and 2.44 mcg/mL respectively, one hour after the first dose.
By the fifth dose, the 6-hour serum concentration had reached equilibrium. Peak serum concentrations after this time would be about 2.46, 2.98 and 3.79 mcg/mL with doses of 8, 12 and 16 mg/kg/day, respectively. Serum levels have been uniform and predictable from person to person and dose to dose.
Distribution Multiple-dose studies in neonates and infants up to 6 months of age show that the drug does not accumulate in the serum and is excreted rapidly. Serum levels exceed the MICs for most indicated organisms for at least six hours following administration of the usually recommended doses of clindamycin palmitate hydrochloride for oral solution (Pediatric) in adults and pediatric patients. Clindamycin is widely distributed in body fluids and tissues (including bones).
No significant levels of clindamycin are attained in the cerebrospinal fluid, even in the presence of inflamed meninges. Metabolism In vitro studies in human liver and intestinal microsomes indicated that clindamycin is predominantly metabolized by Cytochrome P450 3A4 (CYP3A4), with minor contribution from CYP3A5, to form clindamycin sulfoxide and a minor metabolite, N-desmethylclindamycin. Excretion Approximately 10% of the bioactivity is excreted in the urine and 3.6% in the feces; the remainder is excreted as bioinactive metabolites.
The average serum half-life after doses of clindamycin palmitate hydrochloride for oral solution (Pediatric) is approximately two hours in pediatric patients. Special Populations Patients with Renal Impairment Serum half-life of clindamycin is increased slightly in patients with markedly reduced renal function. Hemodialysis and peritoneal dialysis are not effective in removing clindamycin from the serum.
Elderly Patients Pharmacokinetic studies in elderly volunteers (61 to 79 years) and younger adults (18 to 39 years) indicate that age alone does not alter clindamycin pharmacokinetics (clearance, elimination half-life, volume of distribution, and area under the serum concentration-time curve) after IV administration of clindamycin phosphate. After oral administration of clindamycin hydrochloride, elimination half-life is increased to approximately 4.0 hours (range 3.4 to 5.1 h) in the elderly compared to 3.2 hours (range 2.1 to 4.2 h) in younger adults; administration of clindamycin palmitate hydrochloride resulted in a similar elimination half-life value of about 4.5 hours in elderly subjects.
However, the extent of absorption is not different between age groups and no dosage alteration is necessary for the elderly with normal hepatic function and normal (age-adjusted) renal function 1 . Obese Pediatric Patients Aged 2 to Less than 18 Years and Obese Adults Aged 18 to 20 Years An analysis of pharmacokinetic data in obese pediatric patients aged 2 to less than 18 years and obese adults aged 18 to 20 years demonstrated that clindamycin clearance and volume of distribution, normalized by total body weight, are comparable regardless of obesity.
Microbiology Mechanism of Action Clindamycin inhibits bacterial protein synthesis by binding to the 23S RNA of the 50S subunit of the ribosome. Clindamycin is bacteriostatic. Resistance Resistance to clindamycin is most often caused by modification of specific bases of the 23S ribosomal RNA.
Cross-resistance between clindamycin and lincomycin is complete. Because the binding sites for these antibacterial drugs overlap… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Clindamycin palmitate hydrochloride for oral solution, USP (Pediatric) is white flavored granules and becomes colorless to off-white with cherry flavored solution after reconstitution. It is available in bottles of 100 mL. Bottles of 100 mL (Glass) NDC 65862-596-01 Bottles of 100 mL (HDPE) NDC 65862-596-02 When reconstituted as directed, each bottle yields a solution containing 75 mg of clindamycin per 5 mL.
Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature.]
📋 Description ▾
DESCRIPTION Clindamycin palmitate hydrochloride is a water soluble hydrochloride salt of the ester of clindamycin and palmitic acid. Clindamycin is a semisynthetic antibiotic produced by a 7(S)-chloro-substitution of the 7(R)-hydroxyl group of the parent compound lincomycin. The structural formula is represented below: The chemical name for clindamycin palmitate hydrochloride is Methyl 7-chloro-6, 7, 8-trideoxy-6-(1-methyl- trans -4-propyl-L-2-pyrrolidinecarboxamido)-1-thio-L- threo -α-D- galacto -octopyranoside 2-palmitate monohydrochloride.
Clindamycin palmitate hydrochloride for oral solution, USP (Pediatric) is white flavored granules containing clindamycin palmitate hydrochloride USP and becomes colorless to off-white with cherry flavored solution after reconstitution. Each 5 mL contains the equivalent of 75 mg clindamycin. Inactive ingredients: artificial cherry flavor, dextrin, ethylparaben, isopropyl alcohol, poloxamer, simethicone emulsion, and sucrose.
Strucutre
💬 Information for Patients ▾
Information for Patients Patients should be counseled that antibacterial drugs including clindamycin palmitate hydrochloride for oral solution (Pediatric) should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold). When clindamycin palmitate hydrochloride for oral solution (Pediatric) is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed.
Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by clindamycin palmitate hydrochloride for oral solution (Pediatric) or other antibacterial drugs in the future. Diarrhea is a common problem caused by antibiotics which usually ends when the antibiotic is discontinued. Sometimes after starting treatment with antibiotics, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibiotic.
If this occurs, patients should contact their physician as soon as possible.
⚠️ Precautions ▾
PRECAUTIONS General Review of experience to date suggests that a subgroup of older patients with associated severe illness may tolerate diarrhea less well. When clindamycin is indicated in these patients, they should be carefully monitored for change in bowel frequency. Clindamycin palmitate hydrochloride for oral solution (Pediatric) should be prescribed with caution in individuals with a history of gastrointestinal disease, particularly colitis.
Clindamycin palmitate hydrochloride for oral solution (Pediatric) should be prescribed with caution in atopic individuals. Indicated surgical procedures should be performed in conjunction with antibiotic therapy. The use of clindamycin palmitate hydrochloride for oral solution (Pediatric) occasionally results in overgrowth of nonsusceptible organisms-particularly yeasts.
Should superinfections occur, appropriate measures should be taken as indicated by the clinical situation. Clindamycin dosage modification may not be necessary in patients with renal disease. In patients with moderate to severe liver disease, prolongation of clindamycin half-life has been found.
However, it was postulated from studies that when given every eight hours, accumulation should rarely occur. Therefore, dosage modification in patients with liver disease may not be necessary. However, periodic liver enzyme determinations should be made when treating patients with severe liver disease.
Prescribing clindamycin palmitate hydrochloride for oral solution (Pediatric) in the absence of a proven or strongly suspected bacterial infection or a prophylactic indication is unlikely to provide benefit to the patient and increases the risk of the development of drug-resistant bacteria. Information for Patients Patients should be counseled that antibacterial drugs including clindamycin palmitate hydrochloride for oral solution (Pediatric) should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold).
When clindamycin palmitate hydrochloride for oral solution (Pediatric) is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by clindamycin palmitate hydrochloride for oral solution (Pediatric) or other antibacterial drugs in the future.
Diarrhea is a common problem caused by antibiotics which usually ends when the antibiotic is discontinued. Sometimes after starting treatment with antibiotics, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibiotic. If this occurs, patients should contact their physician as soon as possible.
Laboratory Tests During prolonged therapy, periodic liver and kidney function tests and blood counts should be performed. Drug Interactions Clindamycin has been shown to have neuromuscular blocking properties that may enhance the action of other neuromuscular blocking agents. Therefore, it should be used with caution in patients receiving such agents.
Clindamycin is metabolized predominantly by CYP3A4, and to a lesser extent by CYP3A5, to the major metabolite clindamycin sulfoxide and minor metabolite N-desmethylclindamycin. Therefore inhibitors of CYP3A4 and CYP3A5 may increase plasma concentrations of clindamycin and inducers of these isoenzymes may reduce plasma concentrations of clindamycin. In the presence of strong CYP3A4 inhibitors, monitor for adverse reactions.
In the presence of strong CYP3A4 inducers such as rifampicin, monitor for loss of effectiveness. In vitro studies indicate that clindamycin does not inhibit CYP1A2, CYP2C9, CYP2C19, CYP2E1 or CYP2D6 and only moderately inhi… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Limited published data based on breast milk sampling reports that clindamycin appears in human breast milk in the range of less than 0.5 to 3.8 mcg/mL. Clindamycin has the potential to cause adverse effects on the breast-fed infant's gastrointestinal flora. If oral or intravenous clindamycin is required by a nursing mother, it is not a reason to discontinue breastfeeding, but an alternate drug may be preferred.
Monitor the breast-fed infant for possible adverse effects on the gastrointestinal flora, such as diarrhea, candidiasis (thrush, diaper rash) or rarely, blood in the stool indicating possible antibiotic-associated colitis. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for clindamycin and any potential adverse effects on the breast-fed child from clindamycin or from the underlying maternal condition.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility Long term studies in animals have not been performed with clindamycin to evaluate carcinogenic potential. Genotoxicity tests performed included a rat micronucleus test and an Ames Salmonella reversion test. Both tests were negative.
Fertility studies in rats treated orally with up to 300 mg/kg/day (approximately 1.6 times the highest recommended adult human oral dose based on mg/m 2 ) revealed no effects on fertility or mating ability.
📚 References ▾
References 1. Smith RB, Phillips JP: Evaluation of CLEOCIN HCl and CLEOCIN Phosphate in an Aged Population. Upjohn TR 8147-82-9122-021, December 1982. Trademarks are the property of their respective owners. Distributed by: Aurobindo Pharma USA, Inc. 279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 032, India Revised: 12/2022
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 75 mg/5 mL (100 mL Bottle) NDC 65862-596-01 Rx only Clindamycin Palmitate Hydrochloride for Oral Solution, USP (Pediatric) 75 mg*/5 mL when reconstituted AUROBINDO 100 mL (when mixed) PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 75 mg/5 mL (100 mL Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 75 mg/5 mL Container Carton Label NDC 65862-596-01 Clindamycin Palmitate Hydrochloride for Oral Solution, USP ( Pediatric) 75 mg*/5 mL when reconstituted Rx only 100 mL (when mixed) AUROBINDO PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 75 mg/5 mL Container Carton Label