
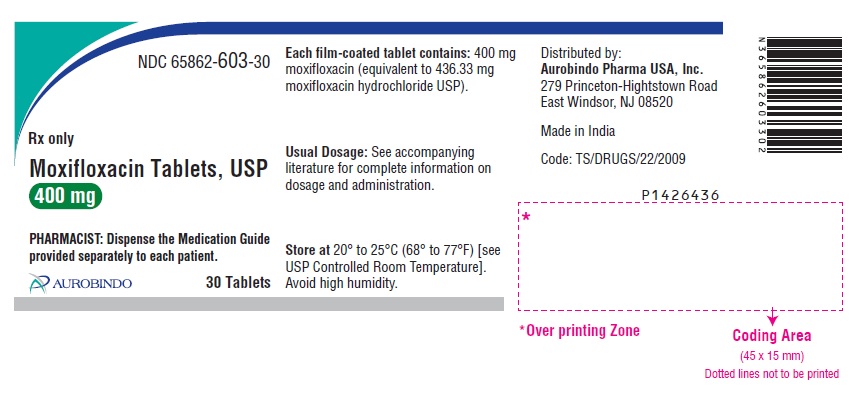
MOXIFLOXACIN HYDROCHLORIDE 400 mg Tablet, Film Coated, 1,000-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Fluoroquinolone Antibacterial class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Moxifloxacin is used to treat certain infections caused by bacteria. Moxifloxacin is also used to prevent and treat plague (a serious infection that may be spread on purpose as part of a bioterror attack). Moxifloxacin is in a class of antibiotics called fluoroquinolones. It works by killing the bacteria that cause infections. Antibiotics such as moxifloxacin will not work for colds, flu, or other viral infections. Using antibiotics when they are not needed increases your risk of getting an infection later that resists antibiotic treatment.
Read the full MedlinePlus article ↗- Yes — you can take moxifloxacin with or without food, and even a big, fatty meal or a cup of yogurt won't affect how well it works. The one thing to watch is timing with antacids,...
- Can I eat or drink normally while taking moxifloxacin tablets?
- The most common ones are nausea, diarrhea, headache, and dizziness — these are annoying but usually manageable. What you really need to stop the medication for and call your doctor...
- What side effects should I actually expect, and which ones should make me stop taking it?
Patient education
Supplement & herbal interactions
Moxifloxacin may be associated with lower levels of 11 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 4R4HFI6D95
Polyethylene glycol 4000 is a synthetic polymer derived from petroleum. It serves as a binder, filler, and lubricant in solid dosage forms, and helps control how quickly the medicine dissolves.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $2.73 | $2,728.50 / 1000 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Moxifloxacin Hydrochloride 400 mg 00904-7407-04 | Major | 1 tablet | $1.343 | AB | Availability likely | — |
| Moxifloxacin Hydrochloride 400 mg 50268-0576-13 | AvPAK | 1 tablet | $1.343 | AB | Availability likely | — |
| Moxifloxacin Hydrochloride 400 mg 57237-0156-30 | Rising | 30 tablets | $1.343 | AB | Availability likely | — |
| Moxifloxacin Hydrochloride 400 mg 68084-0722-65 | American | 1 tablet | $1.343 | AB | Availability likely | — |
| Moxifloxacin 400 mg 73473-0903-30 | Solaris | 30 tablets | $1.343 | AB | Availability likely | — |
| Moxifloxacin Hydrochloride Tablets, 400 mg 72205-0001-05 | Novadoz | 500 tablets | $1.672 | AB | FDA listed | — |
| Moxifloxacin 400 mg 31722-0845-05 | Camber | 500 tablets | — | AB | FDA listed | — |
| Moxifloxacin 400 mg 33342-0322-07 | Macleods | 30 tablets | — | AB | FDA listed | — |
| Moxifloxacin Hydrochloride 400 mg 50090-6609-00 | A-S | 10 tablets | — | AB | FDA listed | — |
| Moxifloxacin Hydrochloride 400 mg 50090-7244-01 | A-S | 7 tablets | — | AB | FDA listed | — |
| Moxifloxacin Hydrochloride 400 mg 50090-7665-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Moxifloxacin 400 mg 55111-0112-01 | Dr. | 100 tablets | — | AB | FDA listed | — |
| Moxifloxacin 400 mg 63629-8357-01 | Bryant | 7 tablets | — | AB | FDA listed | — |
| Moxifloxacin Hydrochloride 400 mgthis 65862-0603-99 | Aurobindo | 1000 tablets | — | AB | FDA listed | — |
| Moxifloxacin Hydrochloride 400 mg 70518-3738-00 | REMEDYREPACK | 7 tablets | — | AB | FDA listed | — |
| Moxifloxacin Hydrochloride Tablets, 400 mg 70518-4312-00 | REMEDYREPACK | 7 tablets | — | AB | FDA listed | — |
| Moxifloxacin Hydrochloride 400 mg 70518-4458-00 | REMEDYREPACK | 7 tablets | — | AB | FDA listed | — |
| Moxifloxacin Hydrochloride 400 mg 71335-2329-01 | Bryant | 7 tablets | — | AB | FDA listed | — |
| Moxifloxacin Hydrochloride 400 mg 71335-2815-01 | Bryant | 7 tablets | — | AB | FDA listed | — |
| Moxifloxacin Hydrochloride 400 mg 72789-0037-10 | PD-Rx | 10 tablets | — | AB | FDA listed | — |
| Moxifloxacin Hydrochloride 400 mg 72789-0038-10 | PD-Rx | 10 tablets | — | AB | FDA listed | — |
| Moxifloxacin Hydrochloride Tablets, 400 mg 72789-0080-10 | PD-Rx | 10 tablets | — | AB | FDA listed | — |
| Moxifloxacin 400 mg 72789-0233-10 | PD-Rx | 10 tablets | — | AB | FDA listed | — |
| Moxifloxacin Hydrochloride 400 mg 72789-0350-10 | PD-Rx | 10 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
💊 Medicaid utilization by pack size
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 65862-0603-30 | 30 TABLET, FILM COATED in 1 BOTTLE (65862-603-30) | $1.34 / ea | $40.28 | 2014-03-04 | Active |
| 65862-0603-55 | 50 BLISTER PACK in 1 BOX, UNIT-DOSE (65862-603-55) / 1 TABLET, FILM COATED in 1 BLISTER PACK (65862-603-10) | — | — | 2014-03-04 | Active |
| 65862-0603-99 You're viewing this | 1000 TABLET, FILM COATED in 1 BOTTLE (65862-603-99) | — | — | 2014-03-04 | Active |
| 65862-0603-26 | 2500 TABLET, FILM COATED in 1 BAG (65862-603-26) | — | — | — | Active |
This pack shows little to no recent Medicaid volume — the 30 tablets pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 65862-0603-99?
What is the difference between NDC 65862-0603-99 and NDC 65862-0603-30?
What NDC number is used to bill for this package of MOXIFLOXACIN HYDROCHLORIDE 400 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SERIOUS ADVERSE REACTIONS INCLUDING TENDINITIS, TENDON RUPTURE, PERIPHERAL NEUROPATHY, CENTRAL NERVOUS SYSTEM EFFECTS AND EXACERBATION OF MYASTHENIA GRAVIS Fluoroquinolones, including moxifloxacin hydrochloride, have been associated with disabling and potentially irreversible serious adverse reactions that have occurred together [see Warnings and Precautions (5.1) ] , including: Tendinitis and tendon rupture [see Warnings and Precautions (5.2) ] Peripheral neuropathy [see Warnings and Precautions (5.3) ] Central nervous system effects [see Warnings and Precautions (5.4) ] Discontinue moxifloxacin hydrochloride immediately and avoid the use of fluoroquinolones, including moxifloxacin hydrochloride, in patients who experience any of these serious adverse reactions [see Warnings and Precautions (5.1) ].
Fluoroquinolones, including moxifloxacin hydrochloride, may exacerbate muscle weakness in patients with myasthenia gravis. Avoid moxifloxacin hydrochloride in patients with known history of myasthenia gravis [see Warnings and Precautions (5.5) ]. Because fluoroquinolones, including moxifloxacin hydrochloride, have been associated with serious adverse reactions [see Warnings and Precautions (5.1 to 5.14) ] , reserve moxifloxacin hydrochloride for use in patients who have no alternative treatment options for the following indications: Acute bacterial sinusitis [see Indications and Usage (1.6) ] Acute bacterial exacerbation of chronic bronchitis [see Indications and Usage (1.7) ] WARNING: SERIOUS ADVERSE REACTIONS INCLUDING TENDINITIS, TENDON RUPTURE, PERIPHERAL NEUROPATHY, CENTRAL NERVOUS SYSTEM EFFECTS and EXACERBATION OF MYASTHENIA GRAVIS See full prescribing information for complete boxed warning Fluoroquinolones, including moxifloxacin hydrochloride, have been associated with disabling and potentially irreversible serious adverse reactions that have occurred together (5.1) including: Tendinitis and tendon rupture (5.2) Peripheral Neuropathy (5.3) Central nervous system effects (5.4) Discontinue moxifloxacin hydrochloride immediately and avoid the use of fluoroquinolones, including moxifloxacin hydrochloride, in patients who experience any of these serious adverse reactions (5.1) Fluoroquinolones, including moxifloxacin hydrochloride, may exacerbate muscle weakness in patients with myasthenia gravis.
Avoid moxifloxacin hydrochloride in patients with known history of myasthenia gravis (5.5) . Because fluoroquinolones, including moxifloxacin hydrochloride, have been associated with serious adverse reactions (5.1 to 5.14) , reserve moxifloxacin hydrochloride for use in patients who have no alternative treatment options for the following indications: Acute bacterial sinusitis (1.6) Acute bacterial exacerbation of chronic bronchitis (1.7)
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Moxifloxacin tablets are a fluoroquinolone antibacterial indicated for treating infections in adults 18 years of age and older caused by designated susceptible bacteria, in the conditions listed below: Community Acquired Pneumonia ( 1.1 ) Skin and Skin Structure Infections: Uncomplicated ( 1.2 ) and Complicated ( 1.3 ) Complicated Intra-Abdominal Infections ( 1.4 ) Plague ( 1.5 ) Acute Bacterial Sinusitis ( 1.6 ) Acute Bacterial Exacerbation of Chronic Bronchitis ( 1.7 ) To reduce the development of drug-resistant bacteria and maintain the effectiveness of moxifloxacin tablets and other antibacterial drugs.
Moxifloxacin tablets should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. ( 1.8 )
1.1Community Acquired Pneumonia Moxifloxacin tablets are indicated in adult patients for the treatment of Community Acquired Pneumonia caused by susceptible isolates of Streptococcus pneumoniae (including multi-drug resistant Streptococcus pneumoniae [MDRSP]) , Haemophilus influenzae, Moraxella catarrhalis, methicillin-susceptible Staphylococcus aureus, Klebsiella pneumoniae, Mycoplasma pneumoniae, or Chlamydophila pneumoniae [see Clinical Studies (14.3) ] . MDRSP isolates are isolates resistant to two or more of the following antibacterial drugs: penicillin (minimum inhibitory concentrations [MIC] ≥ 2 mcg/mL), 2nd generation cephalosporins (for example, cefuroxime), macrolides, tetracyclines, and trimethoprim/sulfamethoxazole.
1.2Uncomplicated Skin and Skin Structure Infections Moxifloxacin tablets are indicated in adult patients for the treatment of Uncomplicated Skin and Skin Structure Infections caused by susceptible isolates of methicillin-susceptible Staphylococcus aureus or Streptococcus pyogenes [see Clinical Studies (14.4) ].
1.3Complicated Skin and Skin Structure Infections Moxifloxacin tablets are indicated in adult patients for the treatment of Complicated Skin and Skin Structure Infections caused by susceptible isolates of methicillin-susceptible Staphylococcus aureus, Escherichia coli, Klebsiella pneumoniae, or Enterobacter cloacae [see Clinical Studies (14.5) ].
1.4Complicated Intra-Abdominal Infections Moxifloxacin tablets are indicated in adult patients for the treatment of Complicated Intra-Abdominal Infections (cIAI) including polymicrobial infections such as abscess caused by susceptible isolates of Escherichia coli, Bacteroides fragilis, Streptococcus anginosus, Streptococcus constellatus, Enterococcus faecalis, Proteus mirabilis, Clostridium perfringens, Bacteroides thetaiotaomicron, or Peptostreptococcus species [see Clinical Studies (14.6) ] .
1.5Plague Moxifloxacin tablets are indicated in adult patients for the treatment of plague, including pneumonic and septicemic plague, due to susceptible isolates of Yersinia pestis and prophylaxis of plague in adult patients. Efficacy studies of moxifloxacin could not be conducted in humans with plague for feasibility reasons. Therefore, this indication is based on an efficacy study conducted in animals only [see Clinical Studies (14.7) ] .
1.6Acute Bacterial Sinusitis Moxifloxacin tablets are indicated in adult patients for the treatment of acute bacterial sinusitis (ABS) caused by susceptible isolates of Streptococcus pneumoniae, Haemophilus influenzae , or Moraxella catarrhalis [see Clinical Studies (14.1) ] . Because fluoroquinolones, including moxifloxacin tablets, have been associated with serious adverse reactions [see Warnings and Precautions (5.1 to 5.14) ] and for some patients ABS is self-limiting, reserve moxifloxacin tablets for treatment of ABS in patients who have no alternative treatment options.
1.7Acute Bacterial Exacerbation of Chronic Bronchitis Moxifloxacin tablets are indicated in adult patients for the treatment of Acute Bacterial Exacerbation of Chronic Bronchitis (ABECB) caused by susceptible isolates of Streptococcus pneumoniae, Haemophilus influenzae…
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Type of Infection Dose Every 24 hours Duration (days) Community Acquired Pneumonia ( 1.1 ) 400 mg 7 to 14 Uncomplicated Skin and Skin Structure Infections (SSSI) ( 1.2 ) 400 mg 7 Complicated SSSI ( 1.3 ) 400 mg 7 to 21 Complicated Intra-Abdominal Infections ( 1.4 ) 400 mg 5 to 14 Plague ( 1.5 ) 400 mg 10 to 14 Acute Bacterial Sinusitis ( 1.6 ) 400 mg 10 Acute Bacterial Exacerbation of Chronic Bronchitis ( 1.7 ) 400 mg 5 No dosage adjustment in patients with renal or hepatic impairment. ( 8.6 , 8.7 )
2.1Dosage in Adult Patients The dose of moxifloxacin is 400 mg (orally) once every 24 hours. The duration of therapy depends on the type of infection as described in Table 1. Table 1: Dosage and Duration of Therapy in Adult Patients a) Due to the designated pathogens [see Indications and Usage (1) ] . b) Sequential therapy (intravenous to oral) may be instituted at the discretion of the physician c) Drug administration should begin as soon as possible after suspected or confirmed exposure to Yersinia pestis .
Type of Infection a Dose Every 24 hours Duration b (days) Community Acquired Pneumonia ( 1.1 ) 400 mg 7 to 14 Uncomplicated Skin and Skin Structure Infections (SSSI) ( 1.2 ) 400 mg 7 Complicated SSSI ( 1.3 ) 400 mg 7 to 21 Complicated Intra-Abdominal Infections ( 1.4 ) 400 mg 5 to 14 Plague ( 1.5 ) C 400 mg 10 to 14 Acute Bacterial Sinusitis (ABS) ( 1.6 ) 400 mg 10 Acute Bacterial Exacerbation of Chronic Bronchitis (ABECB) ( 1.7 ) 400 mg 5 Conversion of Intravenous to Oral Dosing in Adults Intravenous formulation is indicated when it offers a route of administration advantageous to the patient (for example, patient cannot tolerate an oral dosage form).
When switching from intravenous to oral formulation, no dosage adjustment is necessary. Patients whose therapy is started with moxifloxacin hydrochloride injection may be switched to moxifloxacin tablets when clinically indicated at the discretion of the physician.
2.2Important Administration Instructions With Multivalent Cations Administer moxifloxacin tablets at least 4 hours before or 8 hours after products containing magnesium, aluminum, iron or zinc, including antacids, sucralfate, multivitamins and didanosine buffered tablets for oral suspension or the pediatric powder for oral solution [see Drug Interactions (7.1) and Clinical Pharmacology (12.3) ]. With Food Moxifloxacin tablets can be taken with or without food, drink fluids liberally. Missed Doses If a dose is missed, it should be taken anytime but not later than 8 hours prior to the next scheduled dose.
If less than 8 hours remain before the next dose, the missed dose should not be taken and treatment should be continued as prescribed with the next scheduled dose. Double doses should not be taken to compensate for a missed dose.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tablets: 400 mg moxifloxacin ( 3.1 )
3.1Moxifloxacin Tablets, USP Modified capsule shaped, dull red, film-coated tablets debossed with E-18 on one side and plain on the other side containing 400 mg moxifloxacin.
⛔ Contraindications ▾
4 CONTRAINDICATIONS Moxifloxacin tablets are contraindicated in persons with a history of hypersensitivity to moxifloxacin or any member of the quinolone class of antibacterials [see Warnings and Precautions (5.8) ] . Known hypersensitivity to moxifloxacin tablets or other quinolones (4, 5.8 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Prolongation of the QT interval and isolated cases of torsade de pointes has been reported. Avoid use in patients with known prolongation, proarrhythmic conditions such as clinically significant bradycardia or acute myocardial ischemia, hypokalemia, hypomagnesemia, and with drugs that prolong the QT interval. ( 5.6 , 7.5 , 8.5 ) Hypersensitivity and other serious reactions: Serious and sometimes fatal reactions, including anaphylactic reactions, may occur after first or subsequent doses of moxifloxacin hydrochloride.
Discontinue moxifloxacin hydrochloride at first sign of skin rash, jaundice or any other sign of hypersensitivity. ( 5.7 , 5.8 ) Clostridioides difficile -Associated Diarrhea: Evaluate if diarrhea occurs. ( 5.10 )
5.1Disabling and Potentially Irreversible Serious Adverse Reactions Including Tendinitis and Tendon Rupture, Peripheral Neuropathy, and Central Nervous System Effects Fluoroquinolones, including moxifloxacin hydrochloride, have been associated with disabling and potentially irreversible serious adverse reactions from different body systems that can occur together in the same patient. Commonly seen adverse reactions include tendinitis, tendon rupture, arthralgia, myalgia, peripheral neuropathy, and central nervous system effects (hallucinations, anxiety, depression, insomnia, severe headaches, and confusion).
These reactions can occur within hours to weeks after starting moxifloxacin hydrochloride. Patients of any age or without pre-existing risk factors have experienced these adverse reactions [see Warnings and Precautions (5.2, 5.3, 5.4) ] . Discontinue moxifloxacin hydrochloride immediately at the first signs or symptoms of any serious adverse reaction.
In addition, avoid the use of fluoroquinolones, including moxifloxacin hydrochloride, in patients who have experienced any of these serious adverse reactions associated with fluoroquinolones.
5.2Tendinitis and Tendon Rupture Fluoroquinolones, including moxifloxacin hydrochloride, have been associated with an increased risk of tendinitis and tendon rupture in all ages [see Warnings and Precautions (5.1) and Adverse Reactions (6.2) ] . This adverse reaction most frequently involves the Achilles tendon, and has also been reported with the rotator cuff (the shoulder), the hand, the biceps, the thumb, and other tendons. Tendinitis or tendon rupture can occur within hours or days of starting moxifloxacin or as long as several months after completion of therapy.
Tendinitis and tendon rupture can occur bilaterally. The risk of developing fluoroquinolone-associated tendinitis and tendon rupture is increased in patients over 60 years of age, in patients taking corticosteroid drugs, and in patients with kidney, heart or lung transplants. Other factors that may independently increase the risk of tendon rupture include strenuous physical activity, renal failure, and previous tendon disorders such as rheumatoid arthritis.
Tendinitis and tendon rupture have also occurred in patients taking fluoroquinolones who do not have the above risk factors. Discontinue moxifloxacin hydrochloride immediately if the patient experiences pain, swelling, inflammation or rupture of a tendon. Patients should be advised to rest at the first sign of tendinitis or tendon rupture, and to contact their healthcare provider regarding changing to a non-quinolone antimicrobial drug.
Avoid fluoroquinolones, including moxifloxacin hydrochloride, in patients who have a history of tendon disorders or who have experienced tendinitis or tendon rupture [see Adverse Reactions (6.2) ].
5.3Peripheral Neuropathy Fluoroquinolones, including moxifloxacin hydrochloride, have been associated with an increased risk of peripheral neuropathy. Cases of sensory or sensorimotor axonal polyneuropathy affecting small and/or large axons resulting in paresthesias, hypoesthesias, dysesthesias and weakness have been reported in patients receiving fluoroquinolones including moxifloxacin hydroc…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious and otherwise important adverse reactions are discussed in greater detail in the warnings and precautions section of the label: Disabling and Potentially Irreversible Serious Adverse Reactions Including Tendinitis and Tendon Rupture, Peripheral Neuropathy, and Central Nervous System Effects [see Warnings and Precautions (5.1) ] Tendinitis and Tendon Rupture [see Warnings and Precautions (5.2) ] Peripheral Neuropathy [see Warnings and Precautions (5.3) ] Central Nervous System Effects [see Warnings and Precautions (5.4) ] Exacerbation of Myasthenia Gravis [see Warnings and Precautions (5.5) ] QT Prolongation [see Warnings and Precautions (5.6) ] Other Serious and Sometimes Fatal Adverse Reactions [see Warnings and Precautions (5.7) ] Risk of Aortic Aneurysm and Dissection [see Warnings and Precautions (5.9) ] Hypersensitivity Reactions [see Warnings and Precautions (5.8) ] Clostridioides difficile -Associated Diarrhea [see Warnings and Precautions (5.10) ] Blood Glucose Disturbances [see Warnings and Precautions (5.12) ] Photosensitivity/Phototoxicity [see Warnings and Precautions (5.13) ] Development of Drug Resistant Bacteria [see Warnings and Precautions (5.14) ] Most common reactions (3% or greater) were nausea, diarrhea, headache, and dizziness.
( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-866-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The data described below reflect exposure to moxifloxacin hydrochloride in 14981 patients in 71 active controlled Phase II to IV clinical trials in different indications [see Indications and Usage (1) ] . The population studied had a mean age of 50 years (approximately 73% of the population was less than 65 years of age), 50% were male, 63% were Caucasian, 12% were Asian and 9% were Black.
Patients received moxifloxacin 400 mg once daily oral, intravenous, or sequentially (intravenous followed by oral). Treatment duration was usually 6 to 10 days, and the mean number of days on therapy was 9 days. Discontinuation of moxifloxacin due to adverse reactions occurred in 5% of patients overall, 4% of patients treated with 400 mg PO, 4% with 400 mg intravenous and 8% with sequential therapy 400 mg oral/intravenous.
The most common adverse reactions (>0.3%) leading to discontinuation with the 400 mg oral doses were nausea, diarrhea, dizziness, and vomiting. The most common adverse reaction leading to discontinuation with the 400 mg intravenous dose was rash. The most common adverse reactions leading to discontinuation with the 400 mg intravenous/oral sequential dose were diarrhea, pyrexia.
Adverse reactions occurring in 1% of moxifloxacin hydrochloride-treated patients and less common adverse reactions, occurring in 0.1 to 1% of moxifloxacin hydrochloride-treated patients, are shown in Tables 2 and Table 3, respectively. The most common adverse drug reactions (3%) are nausea, diarrhea, headache, and dizziness. Table 2: Common (1% or more) Adverse Reactions Reported in Active-Controlled Clinical Trials with Moxifloxacin Hydrochloride System Organ Class Adverse Reactions % (N=14,981) Blood and Lymphatic System Disorders Anemia 1 Gastrointestinal Disorders Nausea 7 Diarrhea 6 Vomiting 2 Constipation 2 Abdominal pain 2 Dyspepsia 1 General Disorders and Administration Site Conditions Pyrexia 1 Investigations Alanine aminotransferase increased 1 Metabolism and Nutritional Disorder Hypokalemia 1 Nervous System Disorders Headache 4 Dizziness 3 Psychiatric Disorders Insomnia 2 Table 3: Less Common (0.1 to less than 1%) Adverse Reactions Reported in Active-Controlled Clinical Trials with Moxifloxacin Hydrochloride (N=14,98…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Interacting Drug Interaction Multivalent cation-containing products including: antacids, sucralfate, multivitamins Decreased moxifloxacin hydrochloride absorption. Take moxifloxacin tablet at least 4 hours before or 8 hours after these products. ( 2.2 , 7.1 , 12.3 ) Warfarin Anticoagulant effect enhanced.
Monitor prothrombin time/INR, and bleeding. ( 6 , 7.2 , 12.3 ) Class IA and Class III antiarrhythmics: Proarrhythmic effect may be enhanced. Avoid concomitant use.
( 5.6 , 7.5 ) Antidiabetic agents Carefully monitor blood glucose. ( 5.12 , 7.3 )
7.1Antacids, Sucralfate, Multivitamins and Other Products Containing Multivalent Cations Fluoroquinolones, including moxifloxacin hydrochloride, form chelates with alkaline earth and transition metal cations. Oral administration of moxifloxacin hydrochloride with antacids containing aluminum or magnesium, with sucralfate, with metal cations such as iron, or with multivitamins containing iron or zinc, or with formulations containing divalent and trivalent cations such as didanosine buffered tablets for oral suspension or the pediatric powder for oral solution, may substantially interfere with the absorption of moxifloxacin hydrochloride, resulting in systemic concentrations considerably lower than desired.
Therefore, moxifloxacin hydrochloride should be taken at least 4 hours before or 8 hours after these agents [see Dosage and Administration (2.2) and Clinical Pharmacology (12.3) ].
7.2Warfarin Fluoroquinolones, including moxifloxacin hydrochloride, have been reported to enhance the anticoagulant effects of warfarin or its derivatives in the patient population. In addition, infectious disease and its accompanying inflammatory process, age, and general status of the patient are risk factors for increased anticoagulant activity. Therefore the prothrombin time, International Normalized Ratio (INR), or other suitable anticoagulation tests should be closely monitored if moxifloxacin hydrochloride is administered concomitantly with warfarin or its derivatives [see Adverse Reactions (6.2) and Clinical Pharmacology (12.3) ].
7.3Antidiabetic Agents Disturbances of blood glucose, including hyperglycemia and hypoglycemia, have been reported in patients treated concomitantly with fluoroquinolones, including moxifloxacin hydrochloride, and an antidiabetic agent. Therefore, careful monitoring of blood glucose is recommended when these agents are co-administered. If a hypoglycemic reaction occurs, moxifloxacin hydrochloride should be discontinued and appropriate therapy should be initiated immediately [see Warnings and Precautions (5.12) and Adverse Reactions (6.1) ].
7.4Nonsteroidal Anti-Inflammatory Drugs The concomitant administration of a nonsteroidal anti-inflammatory drug (NSAID) with a fluoroquinolone, including moxifloxacin hydrochloride, may increase the risks of CNS stimulation and convulsions [see Warnings and Precautions (5.4) ].
7.5Drugs that Prolong QT There is limited information available on the potential for a pharmacodynamic interaction in humans between moxifloxacin hydrochloride and other drugs that prolong the QTc interval of the electrocardiogram. Sotalol, a Class III antiarrhythmic, has been shown to further increase the QTc interval when combined with high doses of intravenous moxifloxacin hydrochloride in dogs. Therefore, moxifloxacin hydrochloride should be avoided with Class IA and Class III antiarrhythmics [see Warnings and Precautions (5.6) , and Nonclinical Toxicology (13.2) ].
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data may cause fetal harm. (8.1) Geriatrics: Increased risk for severe tendon disorders further increased by concomitant corticosteroid therapy and increased risk of prolongation of the QT interval. (5.1 , 5.6 , 8.5)
8.1Pregnancy Risk Summary There are no available human data establishing a drug associated risk with the use of moxifloxacin. Based on animal studies with moxifloxacin, moxifloxacin hydrochloride may cause fetal harm. Moxifloxacin did not cause fetal malformations when administered to pregnant rats (IV and oral), rabbits (IV), and monkeys (oral) at exposures that were 0.24 to 2.5 times of those at the human clinical dose (400 mg/day moxifloxacin hydrochloride).
However, when moxifloxacin was administered to rats and rabbits during pregnancy and throughout lactation (rats only) at doses associated with maternal toxicity, decreased neonatal body weights, increased incidence of skeletal variations (rib and vertebra combined), and increased fetal loss were observed (see Data). Advise pregnant women of the potential risk to the fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Animal reproductive and development studies were done in rats, rabbits and cynomolgus macaques.
Moxifloxacin did not cause fetal malformations when administered to pregnant rats during organogenesis (gestation days 6 to 17) at oral doses as high as 500 mg/kg/day or 0.24 times the maximum recommended human dose based on systemic exposure (AUC), but decreased fetal body weights and slightly delayed fetal skeletal development were observed. Intravenous administration of 80 mg/kg/day (approximately 2 times the maximum recommended human dose based on body surface area) to pregnant rats resulted in maternal toxicity and a marginal effect on fetal and placental weights and the appearance of the placenta (Gestation days 6 to 17).
Fetal malformations were not observed at intravenous doses as high as 80 mg/kg/day (approximately 2 times the maximum recommended human dose based on body surface area) in litters of pregnant rats that received moxifloxacin during organogenesis (Gestation days 6 to 17). Intravenous administration of 20 mg/kg/day (approximately equal to the maximum recommended human oral dose based upon systemic exposure) to pregnant rabbits during organogenesis (gestation days 6 to 20) resulted in decreased fetal body weights and delayed fetal skeletal ossification.
When rib and vertebral malformations were combined, there was an increased fetal and litter incidence of these effects in rabbits. Signs of maternal toxicity in rabbits at this dose included mortality, abortions, marked reduction of food consumption, decreased water intake, body weight loss and hypoactivity. Fetal malformations were not observed when pregnant cynomolgus macaques were given oral doses as high as 100 mg/kg/day (2.5 times the maximum recommended human dose based upon systemic exposure) during organogenesis (gestation days 20 to 50).
An increased incidence of smaller fetuses was observed at 100 mg/kg/day in macaques. In a pre- and postnatal development study conducted in rats given oral doses from Gestation day 6, throughout gestation and rearing to Postpartum day 21, effects observed at 500 mg/kg/day (0.24 times the maximum recommended human dose based on systemic exposure (AUC)) included slight increases in duration of pregnancy and prenatal loss, reduced pup birth weight and decreased neonatal survival. Treatment-related maternal mortality occurred during gestation at 500 mg/kg/day in this study.
8.2 Lactation Risk Summary It is not known if moxifloxacin is present i…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no available human data establishing a drug associated risk with the use of moxifloxacin. Based on animal studies with moxifloxacin, moxifloxacin hydrochloride may cause fetal harm. Moxifloxacin did not cause fetal malformations when administered to pregnant rats (IV and oral), rabbits (IV), and monkeys (oral) at exposures that were 0.24 to 2.5 times of those at the human clinical dose (400 mg/day moxifloxacin hydrochloride).
However, when moxifloxacin was administered to rats and rabbits during pregnancy and throughout lactation (rats only) at doses associated with maternal toxicity, decreased neonatal body weights, increased incidence of skeletal variations (rib and vertebra combined), and increased fetal loss were observed (see Data). Advise pregnant women of the potential risk to the fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Animal reproductive and development studies were done in rats, rabbits and cynomolgus macaques.
Moxifloxacin did not cause fetal malformations when administered to pregnant rats during organogenesis (gestation days 6 to 17) at oral doses as high as 500 mg/kg/day or 0.24 times the maximum recommended human dose based on systemic exposure (AUC), but decreased fetal body weights and slightly delayed fetal skeletal development were observed. Intravenous administration of 80 mg/kg/day (approximately 2 times the maximum recommended human dose based on body surface area) to pregnant rats resulted in maternal toxicity and a marginal effect on fetal and placental weights and the appearance of the placenta (Gestation days 6 to 17).
Fetal malformations were not observed at intravenous doses as high as 80 mg/kg/day (approximately 2 times the maximum recommended human dose based on body surface area) in litters of pregnant rats that received moxifloxacin during organogenesis (Gestation days 6 to 17). Intravenous administration of 20 mg/kg/day (approximately equal to the maximum recommended human oral dose based upon systemic exposure) to pregnant rabbits during organogenesis (gestation days 6 to 20) resulted in decreased fetal body weights and delayed fetal skeletal ossification.
When rib and vertebral malformations were combined, there was an increased fetal and litter incidence of these effects in rabbits. Signs of maternal toxicity in rabbits at this dose included mortality, abortions, marked reduction of food consumption, decreased water intake, body weight loss and hypoactivity. Fetal malformations were not observed when pregnant cynomolgus macaques were given oral doses as high as 100 mg/kg/day (2.5 times the maximum recommended human dose based upon systemic exposure) during organogenesis (gestation days 20 to 50).
An increased incidence of smaller fetuses was observed at 100 mg/kg/day in macaques. In a pre- and postnatal development study conducted in rats given oral doses from Gestation day 6, throughout gestation and rearing to Postpartum day 21, effects observed at 500 mg/kg/day (0.24 times the maximum recommended human dose based on systemic exposure (AUC)) included slight increases in duration of pregnancy and prenatal loss, reduced pup birth weight and decreased neonatal survival. Treatment-related maternal mortality occurred during gestation at 500 mg/kg/day in this study.
🧒 Pediatric Use ▾
8.4Pediatric Use Effectiveness in pediatric patients and adolescents less than 18 years of age has not been established. Moxifloxacin hydrochloride causes arthropathy in juvenile animals. Limited information on the safety of moxifloxacin hydrochloride in 301 pediatric patients is available from the cIAI trial [see Boxed Warning , Warnings and Precautions (5.11) and Nonclinical Toxicology (13.2) ].
Active Controlled Trial in Complicated Intra-Abdominal Infection (cIAI) The safety and efficacy of moxifloxacin hydrochloride in pediatric patients for the treatment of cIAI has not been demonstrated. Pediatric patients 3 months to <18 years of age (mean age of 12 ± 4 years) were enrolled in a single randomized, double-blind, active controlled trial in cIAI including appendicitis with perforation, abscesses and peritonitis. Pediatric patients were randomized (2:1) to receive either moxifloxacin hydrochloride or comparator.
This study enrolled 451 patients who received study medication, 301 treated with moxifloxacin, and 150 with comparator. Of the 301 pediatric patients treated with moxifloxacin hydrochloride, 15 were below the age of 6 years and 286 were between the ages of 6 to <18 years. Patients received sequential intravenous/oral moxifloxacin hydrochloride or comparator (intravenous ertapenem followed by oral amoxicillin/clavulanate) for 5 to 14 days (mean duration was 9 days with a range of 1 to 24 days).
The overall adverse reaction profile in pediatric patients was comparable to that of adult patients. The most frequently occurring adverse reactions in pediatric patients treated with moxifloxacin hydrochloride were QT prolongation 9.3% (28/301), vomiting, 6.6% (20/301), diarrhea 3.7% (11/301), arthralgia 3.0% (9/301), and phlebitis 2.7% (8/301) (see Table 5). Discontinuation of study drug due to an adverse reaction was reported in 5.3% (16/301) of moxifloxacin hydrochloride-treated patients versus 1.3% (2/150) of comparator-treated patients.
The adverse reaction profile of moxifloxacin hydrochloride or comparator was similar across all age groups studied. Musculoskeletal adverse reactions were monitored and followed up to 5 years after the end of study treatment. The rates of musculoskeletal adverse reactions were 4.3% (13/301) in the moxifloxacin hydrochloride-treated group versus 3.3% (5/150) in the comparator-treated group.
The majority of musculoskeletal adverse reactions were reported between 12 and 53 weeks after start of study treatment with complete resolution at the end of the study [see Warnings and Precautions (5.11) and Nonclinical Toxicology (13.2) ]. Table 5 Incidence (%) of Selected Adverse Reactions in ≥2.0% of Pediatric Patients Treated with Moxifloxacin Hydrochloride in cIAI Clinical Trial System Organ Class Adverse Reactions Moxifloxacin Hydrochloride N = 301 (%) Comparator N = 150 (%) Gastrointestinal disorders Abdominal pain 8 (2.7) 3 (2.0) Diarrhea 11 (3.7) 1 (0.7) Vomiting 20 (6.6) 12 (8.0) General disorders and administration site conditions Pyrexia 6 (2.0) 4 (2.7) Investigations Aspartate aminotransferase increased 2 (0.7) 3 (2.0) Electrocardiogram QT prolonged 28 (9.3) 4 (2.7) Musculoskeletal and connective tissue disorders Arthralgia 9 (3.0) 2 (1.3) Nervous system disorders Headache 6 (2.0) 2 (1.3) Vascular disorders Phlebitis 8 (2.7) 0 (0) Clinical response was assessed at the test-of-cure visit (28 to 42 days after end of treatment).
The clinical response rates observed in the modified intent to treat population were 83.9% (208/248) for moxifloxacin hydrochloride and 95.5% (127/133) for comparator; see Table 6. Table 6: Clinical Response Rates at 28 to 42 Days After End of Treatment in Pediatric Patients with cIAI 1 The modified intent-to-treat (mITT) population is defined as all subjects who were treated with at least one dose of study medication and who have at least one pre-treatment causative organism from the intra-abdominal site of infection or from blood cultures.
2 Difference in clinical…
🧓 Geriatric Use ▾
8.5Geriatric Use Geriatric patients are at increased risk for developing severe tendon disorders including tendon rupture when being treated with a fluoroquinolone such as moxifloxacin hydrochloride. This risk is further increased in patients receiving concomitant corticosteroid therapy. Tendinitis or tendon rupture can involve the Achilles, hand, shoulder, or other tendon sites and can occur during or after completion of therapy; cases occurring up to several months after fluoroquinolone treatment have been reported.
Caution should be used when prescribing moxifloxacin hydrochloride to elderly patients especially those on corticosteroids. Patients should be informed of this potential side effect and advised to discontinue moxifloxacin tablets and contact their healthcare provider if any symptoms of tendinitis or tendon rupture occur [see Boxed Warning , and Warnings and Precautions (5.2) ]. Epidemiologic studies report an increased rate of aortic aneurysm and dissection within two months following use of fluoroquinolones, particularly in elderly patients [see Warnings and Precautions (5.9) ].
In controlled multiple-dose clinical trials, 23% of patients receiving oral moxifloxacin hydrochloride were greater than or equal to 65 years of age and 9% were greater than or equal to 75 years of age. The clinical trial data demonstrate that there is no difference in the safety and efficacy of oral moxifloxacin hydrochloride in patients aged 65 or older compared to younger adults. In trials of intravenous use, 42% of moxifloxacin hydrochloride patients were greater than or equal to 65 years of age, and 23% were greater than or equal to 75 years of age.
The clinical trial data demonstrate that the safety of intravenous moxifloxacin hydrochloride in patients aged 65 or older was similar to that of comparator-treated patients. In general, elderly patients may be more susceptible to drug-associated effects of the QT interval. Therefore, moxifloxacin hydrochloride should be avoided in patients taking drugs that can result in prolongation of the QT interval (for example, class IA or class III antiarrhythmics) or in patients with risk factors for torsade de pointes (for example, known QT prolongation, uncorrected hypokalemia) [see Warnings and Precautions (5.6) , Drug Interactions (7.5) , and Clinical Pharmacology (12.3) ].
🆘 Overdosage ▾
10 OVERDOSAGE Single oral overdoses up to 2.8 g were not associated with any serious adverse events. In the event of acute overdose, empty the stomach and maintain adequate hydration. Monitor ECG due to the possibility of QT interval prolongation.
Carefully observe the patient and give supportive treatment. The administration of activated charcoal as soon as possible after oral overdose may prevent excessive increase of systemic moxifloxacin exposure. About 3% and 9% of the dose of moxifloxacin, as well as about 2% and 4.5% of its glucuronide metabolite are removed by continuous ambulatory peritoneal dialysis and hemodialysis, respectively.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Moxifloxacin hydrochloride is a member of the fluoroquinolone class of antibacterial agents [see Microbiology (12.4) ] .
12.2Pharmacodynamics Photosensitivity Potential A study of the skin response to ultraviolet (UVA and UVB) and visible radiation conducted in 32 healthy volunteers (8 per group) demonstrated that moxifloxacin hydrochloride does not show phototoxicity in comparison to placebo. The minimum erythematous dose (MED) was measured before and after treatment with moxifloxacin (200 mg or 400 mg once daily), lomefloxacin (400 mg once daily), or placebo. In this study, the MED measured for both doses of moxifloxacin were not significantly different from placebo, while lomefloxacin significantly lowered the MED [see Warnings and Precautions (5.13) ] .
12.3Pharmacokinetics Absorption Moxifloxacin, given as an oral tablet, is well absorbed from the gastrointestinal tract. The absolute bioavailability of moxifloxacin is approximately 90 percent. Co-administration with a high fat meal (that is, 500 calories from fat) does not affect the absorption of moxifloxacin.
Consumption of 1 cup of yogurt with moxifloxacin does not affect the rate or extent of the systemic absorption (that is, area under the plasma concentration time curve (AUC). Table 7: Mean (± SD) C max and AUC values following single and multiple doses of 400 mg moxifloxacin given orally a) Range of means from different studies C max (mg/L) AUC (mg•h/L) Half-life (hr) Single Dose Oral Healthy (n = 372) 3.1 ± 1 36.1 ± 9.1 11.5 to 15.6 a Multiple Dose Oral Healthy young male/female (n = 15) 4.5 ± 0.5 48 ± 2.7 12.7 ±
1.9Healthy elderly male (n = 8) 3.8 ± 0.3 51.8 ±
6.7Healthy elderly female (n = 8) 4.6 ± 0.6 54.6 ±
6.7Healthy young male (n = 8) 3.6 ± 0.5 48.2 ± 9 Healthy young female (n = 9) 4.2 ± 0.5 49.3 ±
9.5Table 8: Mean (± SD) C max and AUC values following single and multiple doses of 400 mg moxifloxacin given by 1-hour intravenous infusion a) Range of means from different studies b) Expected C max (concentration obtained around the time of the end of the infusion) C max (mg/L) AUC (mg•h/L) Half-life (hour) Single Dose intravenous Healthy young male/female (n = 56) 3.9 ± 0.9 39.3 ± 8.6 8.2 to 15.4 a Patients (n = 118) Male (n = 64) 4.4 ±
3.7Female (n = 54) 4.5 ± 2 < 65 years (n = 58) 4.6 ± 4.2 ≥ 65 years (n = 60) 4.3 ±
1.3Multiple Dose intravenous Healthy young male (n = 8) 4.2 ± 0.8 38 ± 4.7 14.8 ±
2.2Healthy elderly (n = 12; 8 male, 4 female) 6.1 ± 1.3 48.2 ± 0.9 10.1 ±
1.6Patients b (n = 107) Male (n = 58) 4.2 ±
2.6Female (n = 49) 4.6 ± 1.5 <65 years (n = 52) 4.1 ± 1.4 ≥65 years (n = 55) 4.7 ±
2.7Plasma concentrations increase proportionately with dose up to the highest dose tested (1200 mg single oral dose). The mean (± SD) elimination half-life from plasma is 12 ± 1.3 hours; steady-state is achieved after at least three days with a 400 mg once daily regimen. Mean Steady-State Plasma Concentrations of Moxifloxacin Obtained With Once Daily Dosing of 400 mg Either Orally (n=10) or by Intravenous Infusion (n=12) Distribution Moxifloxacin is approximately 30 to 50% bound to serum proteins, independent of drug concentration.
The volume of distribution of moxifloxacin ranges from 1.7 to
2.7L/kg. Moxifloxacin is widely distributed throughout the body, with tissue concentrations often exceeding plasma concentrations. Moxifloxacin has been detected in the saliva, nasal and bronchial secretions, mucosa of the sinuses, skin blister fluid, subcutaneous tissue, skeletal muscle, and abdominal tissues and fluids following oral or intravenous administration of 400 mg.
Moxifloxacin concentrations measured post-dose in various tissues and fluids following a 400 mg oral or intravenous dose are summarized in Table 9. The rates of elimination of moxifloxacin from tissues generally parallel the elimination from plasma. Table 9: Moxifloxacin Concentrations (mean ± SD) in Tissues and the Corresponding Plasma Concentrati…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Moxifloxacin hydrochloride is a member of the fluoroquinolone class of antibacterial agents [see Microbiology (12.4) ] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1Moxifloxacin Tablets, USP Moxifloxacin Tablets, USP are available as modified capsule shaped, dull red film-coated tablets containing 400 mg moxifloxacin. The tablet is debossed with E-18 on one side and plain on the other side. Bottles of 30 NDC 65862-603-30 Bottles of 1,000 NDC 65862-603-99 Cartons of 50 (5 x 10) Unit-dose Tablets NDC 65862-603-55 Store at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature]. Avoid high humidity.
📋 Description ▾
11 DESCRIPTION Moxifloxacin hydrochloride is a synthetic antibacterial agent for oral administration. Moxifloxacin, a fluoroquinolone, is available as the monohydrochloride salt of 1-cyclopropyl-7-[(S,S)-2,8-diazabicyclo[4.3.0]non-8-yl]-6-fluoro-8-methoxy-1,4-dihydro-4-oxo-3 quinoline carboxylic acid. It is a slightly yellow to yellow powder or crystals, slightly hygroscopic substance with a molecular weight of 437.9.
Its molecular formula is C 21 H 24 FN 3 O 4 *HCl and its chemical structure is as follows:
11.1Moxifloxacin Tablets, USP Moxifloxacin tablets, USP are available as film-coated tablets containing 400 mg moxifloxacin (equivalent to 436.33 mg moxifloxacin hydrochloride USP). The inactive ingredients are hypromellose, iron oxide red, magnesium stearate, microcrystalline cellulose, polyethylene glycol, povidone, sodium starch glycolate, and titanium dioxide. Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Medication Guide ) Serious Adverse Reactions Advise patients to stop taking moxifloxacin hydrochloride if they experience an adverse reaction and to call their healthcare provider for advice on completing the full course of treatment with another antibacterial drug. Inform patients of the following serious adverse reactions that have been associated with moxifloxacin hydrochloride or other fluoroquinolone use: Disabling and potentially irreversible serious adverse reactions that may occur together: Inform patients that disabling and potentially irreversible serious adverse reactions, including tendinitis and tendon rupture, peripheral neuropathies, and central nervous system effects, have been associated with use of moxifloxacin hydrochloride and may occur together in the same patient.
Inform patients to stop taking moxifloxacin hydrochloride immediately if they experience an adverse reaction and to call their healthcare provider. Tendinitis and Tendon Rupture: Instruct patients to contact their healthcare provider if they experience pain, swelling, or inflammation of a tendon, or weakness or inability to use one of their joints; rest and refrain from exercise; and discontinue moxifloxacin hydrochloride treatment. Symptoms may be irreversible.
The risk of severe tendon disorder with fluoroquinolones is higher in older patients usually over 60 years of age, in patients taking corticosteroid drugs, and in patients with kidney, heart or lung transplants. Peripheral Neuropathies: Inform patients that peripheral neuropathies have been associated with moxifloxacin hydrochloride use, symptoms may occur soon after initiation of therapy and may be irreversible. If symptoms of peripheral neuropathy including pain, burning, tingling, numbness and/or weakness develop, immediately discontinue moxifloxacin hydrochloride and tell them to contact their physician.
Central nervous system effects (for example, convulsions, dizziness, lightheadedness, increased intracranial pressure) : Inform patients that convulsions have been reported in patients receiving fluoroquinolones, including moxifloxacin hydrochloride. Instruct patients to notify their physician before taking this drug if they have a history of convulsions. Inform patients that they should know how they react to moxifloxacin hydrochloride before they operate an automobile or machinery or engage in other activities requiring mental alertness and coordination.
Instruct patients to notify their physician if persistent headache with or without blurred vision occurs. Exacerbation of Myasthenia Gravis: Instruct patients to inform their physician of any history of myasthenia gravis. Instruct patients to notify their physician if they experience any symptoms of muscle weakness, including respiratory difficulties.
Hypersensitivity Reactions: Inform patients that moxifloxacin hydrochloride can cause hypersensitivity reactions, even following a single dose, and to discontinue the drug at the first sign of a skin rash, hives or other skin reactions, a rapid heartbeat, difficulty in swallowing or breathing, any swelling suggesting angioedema (for example, swelling of the lips, tongue, face, tightness of the throat, hoarseness), or other symptoms of an allergic reaction. Hepatotoxicity: Inform patients that severe hepatotoxicity (including acute hepatitis and fatal events) has been reported in patients taking moxifloxacin hydrochloride.
Instruct patients to inform their physician if they experience any signs or symptoms of liver injury including: loss of appetite, nausea, vomiting, fever, weakness, tiredness, right upper quadrant tenderness, itching, yellowing of the skin and eyes, light colored bowel movements or dark colored urine. Aortic aneurysm and dissection: Inform patients to seek emergency medical care if they experience sudden chest, stomach, or back pain. Diarrhea: Diarrhea is a common problem…
💬 Medication Guide ▾
MEDICATION GUIDE Moxifloxacin (mox'' i flox' a sin) Tablets, USP for oral use Read the Medication Guide that comes with moxifloxacin tablets before you start taking them and each time you get a refill. There may be new information. This Medication Guide does not take the place of talking to your healthcare provider about your medical condition or your treatment.
What is the most important information I should know about moxifloxacin tablets? Moxifloxacin tablets is in a class of antibiotics called fluoroquinolones. Moxifloxacin tablets can cause serious side effects that can happen at the same time and could result in death.
If you get any of the following serious side effects, you should stop taking moxifloxacin tablets and get medical help right away. Talk with your healthcare provider about whether you should continue to take moxifloxacin tablets. 1.
Tendon rupture or swelling of the tendon (tendinitis). Tendon problems can happen in people of all ages who take moxifloxacin tablets. Tendons are tough cords of tissue that connect muscles to bones.
Symptoms of tendon problems may include: Pain, swelling, tears and inflammation of tendons including the back of the ankle (Achilles), shoulder, hand, or other tendon sites. The risk of getting tendon problems while you take moxifloxacin tablets is higher if you: Are over 60 years of age. Are taking steroids (corticosteroids).
Have had a kidney, heart or lung transplant. Tendon problems can happen in people who do not have the above risk factors when they take moxifloxacin tablets. Other reasons that can increase your risk of tendon problems can include: Physical activity or exercise.
Kidney failure. Tendon problems in the past, such as in people with rheumatoid arthritis (RA). Stop taking moxifloxacin tablets immediately and call your healthcare provider right away at the first sign of tendon pain, swelling or inflammation.
Stop taking moxifloxacin tablets until tendinitis or tendon rupture has been ruled out by your healthcare provider. Avoid exercise and using the affected area. The most common area of pain and swelling is in the Achilles tendon at the back of your ankle.
This can also happen with other tendons. Talk to your healthcare provider about the risk of tendon rupture with continued use of moxifloxacin tablets. You may need a different antibiotic that is not a fluoroquinolone to treat your infection.
Tendon rupture can happen while you are taking or after you have stopped taking moxifloxacin tablets . Tendon ruptures can happen within hours or days after taking moxifloxacin tablets and have happened up to several months after people have stopped taking their fluoroquinolone. Stop taking moxifloxacin tablets immediately and get medical help right away if you get any of the following signs or symptoms of a tendon rupture: Hear or feel a snap or pop in a tendon area.
Bruising right after an injury in a tendon area. Unable to move the affected area or put weight on the area. 2.
Changes in sensation and possible nerve damage (Peripheral Neuropathy). Damage to the nerves in arms, hands, legs, or feet can happen in people who take fluoroquinolones, including moxifloxacin tablets. Stop taking moxifloxacin tablets immediately and talk to your healthcare provider right away if you get any of the following symptoms of peripheral neuropathy in your arms, hands, legs, or feet: pain tingling weakness burning numbness Moxifloxacin tablets may need to be stopped to prevent permanent nerve damage.
3. Central Nervous System (CNS) effects . Seizures have been reported in people who take fluoroquinolone antibiotic medicines, including moxifloxacin tablets.
Tell your healthcare provider if you have a history of seizures before you start taking moxifloxacin tablets. CNS side effects may happen as soon as after taking the first dose of moxifloxacin tablets. Stop taking moxifloxacin tablets immediately and talk to your healthcare provider right away if you get any of these side effects, or oth…